
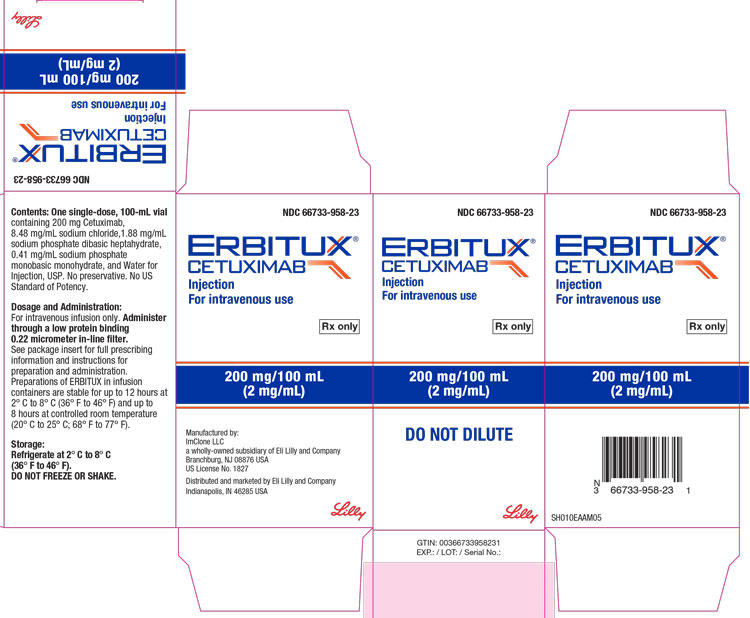
ERBITUX cetuximab 2 mg/mL Solution — NDC 66733-958-23 (Billing 66733-0958-23)
This is a package of ERBITUX cetuximab 2 mg/mL Solution from ImClone LLC, marketed since Oct 2007 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 66733-958-23 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 66733 labeler · 958 product · 23 package
- Package marketed since
- Oct 2, 2007
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 6673395823 1
- Medicaid fills, this package
- 5,333 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 064615
- GCN: 15983
- GPI-14 (Medi-Span): 21360015002025
- HICL (First Databank): 025947
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1657658
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Epidermal Growth Factor Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cetuximab is used with or without radiation therapy to treat a certain type of cancer of the head and neck that has spread to nearby tissues or other parts of the body. It can also be used with other medications to treat a certain type of head and neck cancer that has spread to other parts of the body or keeps coming back after treatment. Cetuximab is also used alone or in combination with other medications to treat a certain type of cancer of the colon (large intestine) or rectum that has spread to other parts of the body. Cetuximab is in a class of medications called monoclonal antibodies. I...
Read the full MedlinePlus article ↗- Erbitux treats squamous cell carcinoma of the head and neck and certain metastatic colorectal cancers. For colorectal cancer, tumor testing is used to decide if it fits. Your oncol...
- It is given through an IV by a healthcare professional, usually once a week or every two weeks. The first infusion takes longer, and later ones are shorter. You will get an antihis...
- How is it given, and how long does it take?
- Skin reactions like rash, itching and nail changes are very common. Headache, diarrhea and infections can also happen. Tell your team early about skin problems so they can be manag...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cetuximab — tap one for details:
Cetuximab may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $14.78 | $1,477.66 / 100 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9055 | $81.666 / J9055 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 66733-0958-23 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 100 mL in 1 VIAL, SINGLE-DOSE | 2007-10-02 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Erbitux 2 mg/mLthis 66733-0958-23 | ImClone | 1 vial | — | — | FDA listed | — |
| Erbitux 2 mg/mL 66733-0948-23 | ImClone | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Cetuximab Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
8.48 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
1.88 mg / 1 mL
UNII 70WT22SF4B
A mineral salt that acts as a buffer to maintain the pH balance of the medication. It helps stabilize the drug's potency and prevents unwanted chemical changes during storage.
-
0.41 mg / 1 mL
UNII 593YOG76RN
A salt made from sodium and phosphate that helps regulate acidity and maintain proper pH balance in the medicine. It also acts as a buffer to keep the product stable.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from ImClone LLC labeler code 66733
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: INFUSION REACTIONS and CARDIOPULMONARY ARREST Infusion Reactions: ERBITUX can cause serious and fatal infusion reactions [see Warnings and Precautions ( 5.1 ), Adverse Reactions ( 6 )] . Immediately interrupt and permanently discontinue ERBITUX for serious infusion reactions [see Dosage and Administration ( 2.5 )] . Cardiopulmonary Arrest: Cardiopulmonary arrest or sudden death occurred in patients with squamous cell carcinoma of the head and neck receiving ERBITUX with radiation therapy or a cetuximab product with platinum-based therapy and fluorouracil.
Monitor serum electrolytes, including serum magnesium, potassium, and calcium, during and after ERBITUX administration [see Warnings and Precautions ( 5.2 , 5.6 )] . WARNING: INFUSION REACTIONS and CARDIOPULMONARY ARREST See full prescribing information for complete boxed warning. ERBITUX can cause serious and fatal infusion reactions.
( 5.1 , 6 ) Immediately interrupt and permanently discontinue ERBITUX for serious infusion reactions. ( 2.5 ) Cardiopulmonary arrest or sudden death occurred in patients with squamous cell carcinoma of the head and neck receiving ERBITUX with radiation therapy or with a cetuximab product with platinum-based therapy and fluorouracil. Monitor serum electrolytes, including serum magnesium, potassium, and calcium, during and after ERBITUX administration.
( 5.2 , 5.6 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ERBITUX ® is an epidermal growth factor receptor (EGFR) antagonist indicated for treatment of: Head and Neck Cancer Locally or regionally advanced squamous cell carcinoma of the head and neck in combination with radiation therapy. ( 1.1 , 14.1 ) Recurrent locoregional disease or metastatic squamous cell carcinoma of the head and neck in combination with platinum-based therapy with fluorouracil. ( 1.1 , 14.1 ) Recurrent or metastatic squamous cell carcinoma of the head and neck progressing after platinum-based therapy.
( 1.1 , 14.1 ) Colorectal Cancer K-Ras wild-type, EGFR-expressing, metastatic colorectal cancer as determined by an FDA-approved test in combination with FOLFIRI for first-line treatment, in combination with irinotecan in patients who are refractory to irinotecan-based chemotherapy, as a single-agent in patients who have failed oxaliplatin- and irinotecan-based chemotherapy or who are intolerant to irinotecan. ( 1.2 , 5.7 , 12.1 , 14.2 ) Limitations of Use: ERBITUX is not indicated for treatment of Ras-mutant colorectal cancer or when the results of the Ras mutation tests are unknown.
( 5.7 ) BRAF V600E Mutation-Positive Metastatic Colorectal Cancer (CRC) in combination with encorafenib, for the treatment of adult patients with metastatic colorectal cancer (CRC) with a BRAF V600E mutation, as detected by an FDA-approved test, after prior therapy. ( 1.3 )
1.1Squamous Cell Carcinoma of the Head and Neck (SCCHN) ERBITUX ® is indicated: in combination with radiation therapy for the initial treatment of locally or regionally advanced squamous cell carcinoma of the head and neck (SCCHN). in combination with platinum-based therapy with fluorouracil for the first-line treatment of patients with recurrent locoregional disease or metastatic SCCHN. as a single-agent for the treatment of patients with recurrent or metastatic SCCHN for whom prior platinum-based therapy has failed.
1.2K-Ras Wild-type, EGFR-expressing Colorectal Cancer (CRC) ERBITUX is indicated for the treatment of K-Ras wild-type, epidermal growth factor receptor (EGFR)-expressing, metastatic colorectal cancer (mCRC) as determined by an FDA-approved test [see Dosage and Administration ( 2.2 )] : in combination with FOLFIRI (irinotecan, fluorouracil, leucovorin) for first-line treatment, in combination with irinotecan in patients who are refractory to irinotecan-based chemotherapy, as a single-agent in patients who have failed oxaliplatin- and irinotecan-based chemotherapy or who are intolerant to irinotecan.
Limitations of Use: ERBITUX is not indicated for treatment of Ras-mutant colorectal cancer or when the results of the Ras mutation tests are unknown [see Warnings and Precautions ( 5.7 )] .
1.3BRAF V600E Mutation-Positive Metastatic Colorectal Cancer (CRC) ERBITUX is indicated, in combination with encorafenib, for the treatment of adult patients with metastatic colorectal cancer (CRC) with a BRAF V600E mutation, as detected by an FDA-approved test, after prior therapy [see Dosage and Administration ( 2.3 )] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Premedicate with an H 1 receptor antagonist. ( 2.4 ) In Combination With Radiation Therapy: Initial dose: 400 mg/m 2 administered as a 120-minute intravenous infusion one week prior to initiating a course of radiation therapy. ( 2.2 ) Subsequent doses: 250 mg/m 2 administered as a 60-minute infusion every week for the duration of radiation therapy (6–7 weeks).
( 2.2 ) Complete ERBITUX administration 1 hour prior to radiation therapy. ( 2.2 ) As Single-Agent or in Combination With Chemotherapy: Weekly: Administer initial dose of 400 mg/m 2 as a 120-minute intravenous infusion, and subsequent doses of 250 mg/m 2 infused over 60 minutes once weekly. ( 2.2 , 2.3 ) Biweekly: Administer 500 mg/m 2 as a 120-minute intravenous infusion every two weeks.
( 2.2 , 2.3 ) Complete ERBITUX administration 1 hour prior to chemotherapy. Continue treatment until disease progression or unacceptable toxicity. ( 2.2 , 2.3 ) See full prescribing information for dosage adjustments for adverse reactions.
( 2.5 )
2.1Patient Selection Select patients with metastatic colorectal cancer (CRC) for treatment with ERBITUX based on the presence of: Ras wild-type, EGFR-expressing CRC [see Clinical Studies ( 14.2 )], or BRAF V600E mutation-positive metastatic CRC [see Clinical Studies ( 14.3 )] Information on FDA-approved tests for the detection of K-Ras or BRAF V600E mutations in CRC in patients with metastatic CRC is available at: http://www.fda.gov/CompanionDiagnostics.
2.2Recommended Dosage for Squamous Cell Carcinoma of the Head and Neck (SCCHN) In combination with radiation therapy Initial dose: 400 mg/m 2 administered as a 120-minute intravenous infusion one week prior to initiating a course of radiation therapy. Subsequent doses: 250 mg/m 2 administered as a 60-minute infusion every week for the duration of radiation therapy (6–7 weeks). Complete ERBITUX administration 1 hour prior to radiation therapy.
As a single-agent or in combination with platinum-based therapy and fluorouracil Administer Erbitux as a single-agent or in combination with platinum-based therapy and fluorouracil on a weekly or biweekly schedule. Weekly Dosage Initial dose: 400 mg/m 2 administered as a 120-minute intravenous infusion Subsequent doses: 250 mg/m 2 administered as a 60-minute infusion every week Biweekly Dosage Initial and subsequent doses: 500 mg/m 2 administered as a 120-minute intravenous infusion every 2 weeks Complete ERBITUX administration 1 hour prior to platinum-based therapy with fluorouracil.
Continue treatment until disease progression or unacceptable toxicity.
2.3Recommended Dosage for Colorectal Cancer (CRC) As a single-agent or in combination with irinotecan or FOLFIRI (irinotecan, fluorouracil, leucovorin) Administer Erbitux as a single-agent or in combination with irinotecan or FOLFIRI (irinotecan, fluorouracil, leucovorin) on a weekly or biweekly schedule. Weekly Dosage Initial dose: 400 mg/m 2 administered as a 120-minute intravenous infusion Subsequent doses: 250 mg/m 2 administered as a 60-minute infusion every week Biweekly Dosage Initial and subsequent doses: 500 mg/m 2 administered as a 120-minute intravenous infusion every 2 weeks Complete ERBITUX administration 1 hour prior to irinotecan or FOLFIRI.
Continue treatment until disease progression or unacceptable toxicity. In combination with encorafenib The recommended initial dose is 400 mg/m 2 administered as a 120-minute intravenous infusion in combination with encorafenib. The recommended subsequent dosage is 250 mg/m 2 weekly as a 60-minute infusion in combination with encorafenib until disease progression or unacceptable toxicity.
Refer to the encorafenib prescribing information for recommended encorafenib dosage information.
2.4Premedication Premedicate with a histamine-1 (H 1 ) receptor antagonist intravenously 30–60 minutes prior to the first dose or subsequent doses as deemed necessary [see Warnings and Precautions ( 5.1 )] .
2.5Dosage Modifications for Adver… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 100 mg/50 mL (2 mg/mL) or 200 mg/100 mL (2 mg/mL) as a clear, colorless solution in a single-dose vial. Injection: 100 mg/50 mL (2 mg/mL) or 200 mg/100 mL (2 mg/mL) in a single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Infusion Reactions: Monitor patients following infusion. Immediately stop and permanently discontinue ERBITUX for serious infusion reactions. ( 2.5 , 5.1 ) Cardiopulmonary Arrest: Monitor serum electrolytes during and after ERBITUX.
( 5.2 , 5.6 ) Pulmonary Toxicity: Interrupt or permanently discontinue for acute onset or worsening of pulmonary symptoms. ( 2.5 , 5.3 ) Dermatologic Toxicity: Monitor for dermatologic toxicities or infectious sequelae. Limit sun exposure.
( 2.5 , 5.4 ) Hypomagnesemia and Accompanying Electrolyte Abnormalities: Monitor during treatment and for at least 8 weeks following the completion. Replete electrolytes as necessary. ( 5.6 ) Increased tumor progression, increased mortality, or lack of benefit observed in patients with Ras-mutant mCRC.
( 5.7 ) Embryo-Fetal Toxicity: Can cause fetal harm. Advise females of potential risk to the fetus and to use effective contraception. ( 5.8 , 8.1 , 8.3 )
5.1Infusion Reactions ERBITUX can cause serious and fatal infusion reactions. Infusion reactions of any grade occurred in 8.4% of 1373 patients who received ERBITUX across clinical trials. Severe (Grades 3 and 4) infusion reactions occurred in 2.2% of patients [see Adverse Reactions ( 6.1 )] .
Signs and symptoms included rapid onset of airway obstruction (bronchospasm, stridor, hoarseness), hypotension, shock, loss of consciousness, myocardial infarction, and/or cardiac arrest. The risk of anaphylactic reactions may be increased in patients with a history of tick bites, red meat allergy, or in the presence of IgE antibodies directed against galactose-α-1,3-galactose (alpha-gal). Consider testing patients for alpha-gal IgE antibodies using FDA-cleared methods prior to initiating ERBITUX.
Negative results for alpha-gal antibodies do not rule out the risk of severe infusion reactions. Approximately 90% of severe infusion reactions occurred with the first infusion despite premedication with antihistamines. Infusion reactions may occur during or several hours following completion of the infusion.
Premedicate with a histamine-1(H 1 ) receptor antagonist as recommended [see Dosage and Administration ( 2.4 )] . Monitor patients for at least 1 hour following each ERBITUX infusion, in a setting with resuscitation equipment and other agents necessary to treat anaphylaxis. In patients requiring treatment for infusion reactions, monitor for more than 1 hour to confirm resolution of the reaction.
Interrupt the infusion and upon recovery, resume the infusion at a slower rate or permanently discontinue ERBITUX based on severity [see Dosage and Administration ( 2.5 )] .
5.2Cardiopulmonary Arrest ERBITUX can cause cardiopulmonary arrest. Cardiopulmonary arrest or sudden death occurred in 2% of 208 patients treated with radiation therapy and ERBITUX in BONNER. Three patients with prior history of coronary artery disease died at home, with myocardial infarction as the presumed cause of death.
One of these patients had arrhythmia and one had congestive heart failure. Death occurred 27, 32, and 43 days after the last dose of ERBITUX. One patient with no prior history of coronary artery disease died one day after the last dose of ERBITUX.
In EXTREME, fatal cardiac disorders and/or sudden death occurred in 3% of 219 patients treated with a cetuximab product in combination with platinum-based therapy and fluorouracil. Carefully consider use of ERBITUX with radiation therapy or platinum-based therapy with fluorouracil in patients with SCCHN with a history of coronary artery disease, congestive heart failure, or arrhythmias. Monitor serum electrolytes, including serum magnesium, potassium, and calcium, during and after ERBITUX [see Warnings and Precautions ( 5.6 )] .
5.3Pulmonary Toxicity ERBITUX can cause interstitial lung disease (ILD). ILD, including 1 fatality, occurred in <0.5% of 1570 patients receiving ERBITUX in clinical trials. Monitor patients for signs and symptoms of pulmonary toxicity. Interrupt o… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: Infusion reactions [see Warnings and Precautions ( 5.1 )] . Cardiopulmonary arrest [see Warnings and Precautions ( 5.2 )] . Pulmonary toxicity [see Warnings and Precautions ( 5.3 )] .
Dermatologic toxicity [see Warnings and Precautions ( 5.4 )] . Hypomagnesemia and Electrolyte Abnormalities [see Warnings and Precautions ( 5.6 )] . The most common adverse reactions (incidence ≥25%) with Erbitux as a single-agent or in combination with radiotherapy or chemotherapy (FOLFIRI, Irinotecan and 5-Fluorouracil/Platinum) are: cutaneous adverse reactions (including rash, pruritus, and nail changes), headache, diarrhea, and infection.
( 6 ) The most common adverse reactions (>25%) for ERBITUX, in combination with encorafenib, are fatigue, nausea, diarrhea, dermatitis acneiform, abdominal pain, decreased appetite, arthralgia, and rash. ( 6 ). To report SUSPECTED ADVERSE REACTIONS, contact Eli Lilly and Company at 1-800-LillyRx (1-800-545-5979) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described in Warnings and Precautions reflect exposure to ERBITUX in 1373 patients with SCCHN or CRC enrolled in clinical trials and treated at the recommended dosage for a median of 7 to 14 weeks [see Clinical Studies ( 14.1 , 14.2 )] .
The most common adverse reactions in clinical trials with ERBITUX as a single-agent or in combination with radiotherapy or chemotherapy [FOLFIRI, irinotecan and 5-fluorouracil/platinum] (incidence ≥25%) include cutaneous adverse reactions (including rash, pruritus, and nail changes), headache, diarrhea, and infection. Squamous Cell Carcinoma of the Head and Neck (SCCHN) In Combination with Radiation Therapy The safety of ERBITUX in combination with radiation therapy compared to radiation therapy alone was evaluated in BONNER.
The data described below reflect exposure to ERBITUX in 420 patients with locally or regionally advanced SCCHN. ERBITUX was administered at the recommended dosage (400 mg/m 2 initial dose, followed by 250 mg/m 2 weekly). Patients received a median of 8 infusions (range 1 to 11) [see Clinical Studies ( 14.1 )] .
Table 2 provides the frequency and severity of adverse reactions in BONNER. Table 2: Selected Adverse Reactions in ≥10% of Patients with Locoregionally Advanced SCCHN (BONNER) a Adverse Reaction ERBITUX with Radiation (n=208) Radiation Therapy Alone (n=212) Grades 1–4 b Grades 3 and 4 Grades 1–4 Grades 3 and 4 a Adverse reactions occurring in ≥10% of patients in the ERBITUX combination arm and at a higher incidence (≥5%) compared to the radiation alone arm. b Adverse reactions were graded using the NCI CTC, version 2.0. c Includes cases also reported as infusion reaction. d Infusion reaction defined as any event described at any time during the clinical study as “allergic reaction” or “anaphylactoid reaction”, or any event occurring on the first day of dosing described as “allergic reaction”, “anaphylactoid reaction”, “fever”, “chills”, “chills and fever”, or “dyspnea”. e Based on laboratory measurements, not on reported adverse reactions, the number of subjects with tested samples varied from 205–206 for ERBITUX with Radiation arm; 209–210 for Radiation alone. f Acneiform rash defined as any event described as “acne”, “rash”, “maculopapular rash”, “pustular rash”, “dry skin”, or “exfoliative dermatitis”.
General Asthenia 56 4 49 5 Fever c 29 1 13 1 Headache 19 <1 8 <1 Chills c 16 0 5 0 Infusion Reaction d 15 3 2 0 Infection 13 1 9 1 Gastrointestinal Nausea 49 2 37 2 Emesis 29 2 23 4 Diarrhea 19 2 13 1 Dyspepsia 14 0 9 1 Metabolism and Nutrition Weight Loss 84 11 72 7 Dehydrati… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology ( 12.1 )] , ERBITUX can cause fetal harm when administered to a pregnant woman. There are no available data for ERBITUX exposure in pregnant women. In an animal reproduction study, intravenous administration of cetuximab once weekly to pregnant cynomolgus monkeys during the period of organogenesis resulted in an increased incidence of embryolethality and abortion.
Disruption or depletion of EGFR in animal models results in impairment of embryo-fetal development including effects on placental, lung, cardiac, skin, and neural development ( see Data ). Human IgG is known to cross the placental barrier; therefore, cetuximab may be transmitted from the mother to the developing fetus. Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively. Data Animal Data Pregnant cynomolgus monkeys were administered cetuximab intravenously once weekly during the period of organogenesis (gestation day [GD] 20-48) at dose levels 0.4 to 4 times the recommended dose of ERBITUX based on body surface area (BSA). Cetuximab was detected in the amniotic fluid and in the serum of embryos from treated dams on GD 49.
While no fetal malformations occurred in offspring, there was an increased incidence of embryolethality and abortions at doses approximately 1 to 4 times the recommended dose of ERBITUX based on BSA. In mice, EGFR is critically important in reproductive and developmental processes including blastocyst implantation, placental development, and embryo-fetal/postnatal survival and development. Reduction or elimination of embryo-fetal or maternal EGFR signaling can prevent implantation, can cause embryo-fetal loss during various stages of gestation (through effects on placental development), and can cause developmental anomalies and early death in surviving fetuses.
Adverse developmental outcomes were observed in multiple organs in embryos/neonates of mice with disrupted EGFR signaling.
8.2Lactation Risk Summary There is no information regarding the presence of ERBITUX in human milk, the effects on the breastfed infant, or the effects on milk production. Human IgG antibodies can be excreted in human milk. Due to the potential for serious adverse reactions in breastfed infants from ERBITUX, advise women not to breastfeed during treatment with ERBITUX and for 2 months after the last dose of ERBITUX.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating ERBITUX [see Use in Specific Population ( 8.1 )] . Contraception Based on its mechanism of action, ERBITUX can cause harm to the fetus when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )] . Females Advise females of reproductive potential to use effective contraception during treatment with ERBITUX and for 2 months after the last dose of ERBITUX.
Infertility Females Based on animal studies, ERBITUX may impair fertility in females of reproductive potential [see Nonclinical Toxicology ( 13.1 )] .
8.4Pediatric Use The safety and effectiveness of ERBITUX in pediatric patients have not been established. The pharmacokinetics of cetuximab, in combination with irinotecan, were evaluated in pediatric patients with refractory solid tumors in an open-label, single-arm, dose-finding study. ERBITUX was administered once-weekly, at doses up to 250 mg/m 2 , to 27 patients ranging from 1 to 12 years old; and in 19 patients ranging from 13 to 18 years old.
No new safety signals were identified in pediatric patients. The pharmacokinetics of cetuximab between the two age groups were similar following a single dose of 75 mg/m 2 and 150 mg/m… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology ( 12.1 )] , ERBITUX can cause fetal harm when administered to a pregnant woman. There are no available data for ERBITUX exposure in pregnant women. In an animal reproduction study, intravenous administration of cetuximab once weekly to pregnant cynomolgus monkeys during the period of organogenesis resulted in an increased incidence of embryolethality and abortion.
Disruption or depletion of EGFR in animal models results in impairment of embryo-fetal development including effects on placental, lung, cardiac, skin, and neural development ( see Data ). Human IgG is known to cross the placental barrier; therefore, cetuximab may be transmitted from the mother to the developing fetus. Advise pregnant women of the potential risk to a fetus.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively. Data Animal Data Pregnant cynomolgus monkeys were administered cetuximab intravenously once weekly during the period of organogenesis (gestation day [GD] 20-48) at dose levels 0.4 to 4 times the recommended dose of ERBITUX based on body surface area (BSA). Cetuximab was detected in the amniotic fluid and in the serum of embryos from treated dams on GD 49.
While no fetal malformations occurred in offspring, there was an increased incidence of embryolethality and abortions at doses approximately 1 to 4 times the recommended dose of ERBITUX based on BSA. In mice, EGFR is critically important in reproductive and developmental processes including blastocyst implantation, placental development, and embryo-fetal/postnatal survival and development. Reduction or elimination of embryo-fetal or maternal EGFR signaling can prevent implantation, can cause embryo-fetal loss during various stages of gestation (through effects on placental development), and can cause developmental anomalies and early death in surviving fetuses.
Adverse developmental outcomes were observed in multiple organs in embryos/neonates of mice with disrupted EGFR signaling.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ERBITUX in pediatric patients have not been established. The pharmacokinetics of cetuximab, in combination with irinotecan, were evaluated in pediatric patients with refractory solid tumors in an open-label, single-arm, dose-finding study. ERBITUX was administered once-weekly, at doses up to 250 mg/m 2 , to 27 patients ranging from 1 to 12 years old; and in 19 patients ranging from 13 to 18 years old.
No new safety signals were identified in pediatric patients. The pharmacokinetics of cetuximab between the two age groups were similar following a single dose of 75 mg/m 2 and 150 mg/m 2 . The volume of the distribution appears to be independent of dose and approximates the vascular space of 2 L/m 2 to 3 L/m 2 .
Following a single dose of 250 mg/m 2 , the mean AUC 0-inf (CV%) was 17.7 mg*h/mL (34%) in the younger age group (1–12 years, n=9) and 13.4 mg*h/mL (38%) in the adolescent group (13–18 years, n=6). The mean half-life of cetuximab was 110 hours (69 to 188 hours) in the younger group and 82 hours (55 to 117 hours) in the adolescent group.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 1662 patients with advanced colorectal cancer who received ERBITUX with irinotecan, with FOLFIRI or as single-agent in six studies (BOND, IMCL-CP02-9923, IMCL-CP02-0141, IMCL-CP02-0144, CA225-025 and CRYSTAL), 35% of patients were 65 years of age or older. No overall differences in safety or efficacy were observed between these patients and younger patients. Clinical studies of ERBITUX conducted in patients with head and neck cancer did not include sufficient number of subjects aged 65 and over to determine whether they respond differently from younger subjects.
Of the 216 patients with BRAF V600E mutation positive metastatic CRC who received ERBITUX in combination with encorafenib 300 mg, once daily, 29% were 65 years of age to up to 75 years of age, while 20 (9%) were 75 years of age and over [see Clinical Studies ( 14.3 )] . No overall differences in the safety or effectiveness of ERBITUX plus encorafenib were observed in elderly patients as compared to younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The epidermal growth factor receptor (EGFR, HER1, c-ErbB-1) is a transmembrane glycoprotein that is a member of a subfamily of type I receptor tyrosine kinases including EGFR, HER2, HER3, and HER4. The EGFR is constitutively expressed in many normal epithelial tissues, including the skin and hair follicle. Expression of EGFR is also detected in many human cancers including those of the head and neck, colon, and rectum.
Cetuximab binds specifically to the EGFR on both normal and tumor cells, and competitively inhibits the binding of epidermal growth factor (EGF) and other ligands, such as transforming growth factor-alpha. In vitro assays and in vivo animal studies have shown that binding of cetuximab to the EGFR blocks phosphorylation and activation of receptor-associated kinases, resulting in inhibition of cell growth, induction of apoptosis, and decreased matrix metalloproteinase and vascular endothelial growth factor production.
Signal transduction through the EGFR results in activation of wild-type Ras proteins, but in cells with activating Ras somatic mutations, the resulting mutant Ras proteins are continuously active regardless of EGFR regulation. In vitro , cetuximab can mediate antibody-dependent cellular cytotoxicity (ADCC) against certain human tumor types. In vitro assays and in vivo animal studies have shown that cetuximab inhibits the growth and survival of tumor cells that express the EGFR.
No anti-tumor effects of cetuximab were observed in human tumor xenografts lacking EGFR expression. The addition of cetuximab to radiation therapy or irinotecan in human tumor xenograft models in mice resulted in an increase in anti-tumor effects compared to radiation therapy or chemotherapy alone. In the setting of BRAF-mutant CRC, induction of EGFR-mediated MAPK pathway activation has been identified as a mechanism of resistance to BRAF inhibitors.
Combinations of a BRAF inhibitor and agents targeting EGFR have been shown to overcome this resistance mechanism in nonclinical models. Coadministration of cetuximab and encorafenib had an anti-tumor effect greater than either drug alone, in a mouse model of colorectal cancer with mutated BRAF V600E.
12.3Pharmacokinetics ERBITUX administered as a single-agent or in combination with concomitant chemotherapy or radiation therapy exhibits nonlinear pharmacokinetics. The area under the concentration time curve (AUC) increased in a greater than dose proportional manner while clearance of cetuximab decreased from
0.08 L/h/m 2 to
0.02L/h/m 2 as the dose increased from 20 mg/m 2 to 200 mg/m 2 and plateaued at doses >200 mg/m 2 . The systemic exposure of cetuximab after ERBITUX administration was 22% (90% CI: 6%, 38%) higher than that of another cetuximab product used in EXTREME and CRYSTAL. Distribution The volume of the distribution for cetuximab appeared to be independent of dose and approximated the vascular space of 2–3 L/m 2 .
Elimination Following the recommended dosage (400 mg/m 2 initial dose; 250 mg/m 2 weekly dose), concentrations of cetuximab reached steady-state levels by the third weekly infusion with mean peak and trough concentrations across studies ranging from 168 μg/mL to 235 μg/mL and 41 μg/mL to 85 μg/mL, respectively. The mean half-life of cetuximab was approximately 112 hours (63 to 230 hours). Specific Population Age, sex, race, hepatic and renal function had no clinically significant effect on the pharmacokinetics of cetuximab.
Clearance of cetuximab increased 1.8-fold as body surface area increased from 1.3 m 2 to 2.3 m 2 , which is consistent with the recommended dosing of cetuximab on mg/m 2 basis. Drug Interaction Studies No pharmacokinetic interaction was observed between cetuximab and irinotecan, cetuximab and cisplatin, and cetuximab and carboplatin. No clinically significant differences in the pharmacokinetics of cetuximab or encorafenib were observed when the recommended ERBITUX initial dose of 400 mg/m 2… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The epidermal growth factor receptor (EGFR, HER1, c-ErbB-1) is a transmembrane glycoprotein that is a member of a subfamily of type I receptor tyrosine kinases including EGFR, HER2, HER3, and HER4. The EGFR is constitutively expressed in many normal epithelial tissues, including the skin and hair follicle. Expression of EGFR is also detected in many human cancers including those of the head and neck, colon, and rectum.
Cetuximab binds specifically to the EGFR on both normal and tumor cells, and competitively inhibits the binding of epidermal growth factor (EGF) and other ligands, such as transforming growth factor-alpha. In vitro assays and in vivo animal studies have shown that binding of cetuximab to the EGFR blocks phosphorylation and activation of receptor-associated kinases, resulting in inhibition of cell growth, induction of apoptosis, and decreased matrix metalloproteinase and vascular endothelial growth factor production.
Signal transduction through the EGFR results in activation of wild-type Ras proteins, but in cells with activating Ras somatic mutations, the resulting mutant Ras proteins are continuously active regardless of EGFR regulation. In vitro , cetuximab can mediate antibody-dependent cellular cytotoxicity (ADCC) against certain human tumor types. In vitro assays and in vivo animal studies have shown that cetuximab inhibits the growth and survival of tumor cells that express the EGFR.
No anti-tumor effects of cetuximab were observed in human tumor xenografts lacking EGFR expression. The addition of cetuximab to radiation therapy or irinotecan in human tumor xenograft models in mice resulted in an increase in anti-tumor effects compared to radiation therapy or chemotherapy alone. In the setting of BRAF-mutant CRC, induction of EGFR-mediated MAPK pathway activation has been identified as a mechanism of resistance to BRAF inhibitors.
Combinations of a BRAF inhibitor and agents targeting EGFR have been shown to overcome this resistance mechanism in nonclinical models. Coadministration of cetuximab and encorafenib had an anti-tumor effect greater than either drug alone, in a mouse model of colorectal cancer with mutated BRAF V600E.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied ERBITUX ® (cetuximab) injection is a sterile, preservative-free, clear, colorless solution in a 2 mg/mL single-dose vial supplied as follows: 100 mg/50 mL individually packaged in a carton (NDC 66733-948-23) 200 mg/100 mL individually packaged in a carton (NDC 66733-958-23) Storage and Handling Store vials under refrigeration at 2° C to 8° C (36° F to 46° F). Do not freeze or shake. Increased particulate formation may occur at temperatures at or below 0° C (32° F).
Discard any remaining solution in the infusion container after 8 hours at controlled room temperature or after 12 hours at 2° C to 8° C. Discard any unused portion of the vial.
How Supplied ERBITUX ® (cetuximab) injection is a sterile, preservative-free, clear, colorless solution in a 2 mg/mL single-dose vial supplied as follows: 100 mg/50 mL individually packaged in a carton (NDC 66733-948-23) 200 mg/100 mL individually packaged in a carton (NDC 66733-958-23)
📦 Storage and Handling ▾
Storage and Handling Store vials under refrigeration at 2° C to 8° C (36° F to 46° F). Do not freeze or shake. Increased particulate formation may occur at temperatures at or below 0° C (32° F). Discard any remaining solution in the infusion container after 8 hours at controlled room temperature or after 12 hours at 2° C to 8° C. Discard any unused portion of the vial.
📋 Description ▾
11 DESCRIPTION Cetuximab is an epidermal growth factor receptor (EGFR) antagonist. It is a recombinant, human/mouse chimeric monoclonal antibody that binds specifically to the extracellular domain of the human epidermal growth factor receptor (EGFR). Cetuximab is composed of the Fv regions of a murine anti-EGFR antibody with human IgG1 heavy and kappa light chain constant regions and has an approximate molecular weight of 152 kDa.
Cetuximab is produced in mammalian (murine myeloma) cell culture. ERBITUX (cetuximab) injection for intravenous use, is a sterile, preservative-free, clear, colorless solution, which may contain a small amount of visible, white, amorphous cetuximab particulates in a single-dose vial. Each 1 mL of solution contains 2 mg of cetuximab, sodium chloride (8.48 mg), sodium phosphate dibasic heptahydrate (1.88 mg), sodium phosphate monobasic monohydrate (0.41 mg), and Water for Injection, USP at pH of 7.0 to 7.4.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Infusion Reactions Advise patients that the risk of serious infusion reactions may be increased in patients who have had a tick bite or red meat allergy. Advise patients to contact their healthcare provider and to report signs and symptoms of infusion reactions, including late onset infusion reactions, such as fever, chills, or breathing problems [see Warnings and Precautions ( 5.1 )] . Cardiopulmonary Arrest Advise patients of the risk of cardiopulmonary arrest or sudden death and to report any history of coronary artery disease, congestive heart failure, or arrhythmias [see Warnings and Precautions ( 5.2 )] .
Pulmonary Toxicity Advise patients to contact their healthcare provider immediately for new or worsening cough, chest pain, or shortness of breath [see Warnings and Precautions ( 5.3 )] . Dermatologic Toxicities Advise patients to limit sun exposure during ERBITUX treatment and for 2 months after the last dose of ERBITUX. Advise patients to notify their healthcare provider of any sign of acne-like rash, (which can include itchy, dry, scaly, or cracking skin and inflammation, infection or swelling at the base of the nails or loss of the nails), conjunctivitis, blepharitis, or decreased vision [see Warnings and Precautions ( 5.4 )] .
Embryo-Fetal Toxicity Advise female patients of reproductive potential of the potential risk to a fetus and to use effective contraception during ERBITUX treatment and for 2 months after the last dose of ERBITUX. Advise patients to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions ( 5.8 ), Use in Specific Populations ( 8.3 )] . Lactation Advise patients not to breastfeed during ERBITUX treatment and for 2 months after the last dose of ERBITUX [see Use in Specific Populations ( 8.2 )] .
ERBITUX ® is a registered trademark of ImClone LLC a wholly-owned subsidiary of Eli Lilly and Company. Manufactured by ImClone LLC a wholly-owned subsidiary of Eli Lilly and Company, Branchburg, NJ 08876 USA Eli Lilly and Company, Indianapolis, IN 46285, USA US License No. 1827 Copyright © 2004, 2021, ImClone LLC a wholly-owned subsidiary of Eli Lilly and Company.
All rights reserved. ERB-0009-USPI-20210927
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics ERBITUX administered as a single-agent or in combination with concomitant chemotherapy or radiation therapy exhibits nonlinear pharmacokinetics. The area under the concentration time curve (AUC) increased in a greater than dose proportional manner while clearance of cetuximab decreased from
0.08 L/h/m 2 to
0.02L/h/m 2 as the dose increased from 20 mg/m 2 to 200 mg/m 2 and plateaued at doses >200 mg/m 2 . The systemic exposure of cetuximab after ERBITUX administration was 22% (90% CI: 6%, 38%) higher than that of another cetuximab product used in EXTREME and CRYSTAL. Distribution The volume of the distribution for cetuximab appeared to be independent of dose and approximated the vascular space of 2–3 L/m 2 .
Elimination Following the recommended dosage (400 mg/m 2 initial dose; 250 mg/m 2 weekly dose), concentrations of cetuximab reached steady-state levels by the third weekly infusion with mean peak and trough concentrations across studies ranging from 168 μg/mL to 235 μg/mL and 41 μg/mL to 85 μg/mL, respectively. The mean half-life of cetuximab was approximately 112 hours (63 to 230 hours). Specific Population Age, sex, race, hepatic and renal function had no clinically significant effect on the pharmacokinetics of cetuximab.
Clearance of cetuximab increased 1.8-fold as body surface area increased from 1.3 m 2 to 2.3 m 2 , which is consistent with the recommended dosing of cetuximab on mg/m 2 basis. Drug Interaction Studies No pharmacokinetic interaction was observed between cetuximab and irinotecan, cetuximab and cisplatin, and cetuximab and carboplatin. No clinically significant differences in the pharmacokinetics of cetuximab or encorafenib were observed when the recommended ERBITUX initial dose of 400 mg/m 2 was co-administered with encorafenib.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Squamous Cell Carcinoma of the Head and Neck (SCCHN) In Combination with Radiation Therapy BONNER (NCT00004227) was a randomized, multicenter, controlled trial of 424 patients with locally or regionally advanced SCCHN. Patients with Stage III/IV SCCHN of the oropharynx, hypopharynx, or larynx with no prior therapy were randomized (1:1) to receive either ERBITUX in combination with radiation therapy or radiation therapy alone. Stratification factors were Karnofsky performance status (60–80 versus 90–100), nodal stage (N0 versus N+), tumor stage (T1–3 versus T4 using American Joint Committee on Cancer 1998 staging criteria), and radiation therapy fractionation (concomitant boost versus once-daily versus twice-daily).
Radiation therapy was administered for 6–7 weeks as once-daily, twice-daily, or concomitant boost. ERBITUX was administered intravenously as a 400 mg/m 2 initial dose beginning one week prior to initiation of radiation therapy, followed by 250 mg/m 2 weekly administered 1 hour prior to radiation therapy for the duration of radiation therapy (6–7 weeks). The main efficacy outcome measure was duration of locoregional control.
Another outcome measure was overall survival (OS). Of the 424 randomized patients, the median age was 57 years, 80% were male, 83% were White, and 90% had baseline Karnofsky performance status ≥80. There were 258 patients enrolled in U.S. sites (61%).
Sixty percent of patients had oropharyngeal, 25% laryngeal, and 15% hypopharyngeal primary tumors; 28% had AJCC T4 tumor stage. Fifty-six percent of the patients received radiation therapy with concomitant boost, 26% received once-daily regimen, and 18% twice-daily regimen. Efficacy results are presented in Table 8 .
Table 8: Efficacy Results in Locoregionally Advanced SCCHN in BONNER ERBITUX plus Radiation (n=211) Radiation Alone (n=213) Hazard Ratio (95% CI a ) Stratified Log-rank p-value a CI = confidence interval. Locoregional Control Median duration (months) 24.4 14.9 0.68 (0.52–0.89) 0.005 Overall Survival Median duration (months) 49.0 29.3 0.74 (0.57–0.97)
0.03In Combination with Platinum-based Therapy with Fluorouracil EXTREME (NCT00122460) was an open-label, randomized, multicenter, controlled trial of 442 patients with recurrent locoregional disease or metastatic SCCHN. Patients with no prior therapy for recurrent locoregional disease or metastatic SCCHN were randomized (1:1) to receive a cetuximab product in combination with platinum-based therapy and fluorouracil or platinum-based therapy and fluorouracil alone. Choice of cisplatin or carboplatin was at the discretion of the investigator.
Stratification factors were Karnofsky performance status (<80 versus ≥80) and previous chemotherapy. Cisplatin (100 mg/m 2 intravenously on Day 1) or carboplatin (AUC 5 mg/mL*min intravenously on Day 1) and fluorouracil (1000 mg/m 2 /day intravenously on Days 1–4) were administered every 3 weeks (1 cycle) for a maximum of 6 cycles in the absence of disease progression or unacceptable toxicity. Cetuximab was administered intravenously at a 400 mg/m 2 initial dose, followed by a 250 mg/m 2 weekly dose.
In the absence of disease progression or unacceptable toxicity after completion of 6 planned courses of platinum-based therapy, weekly cetuximab as a single-agent could be continued until disease progression or unacceptable toxicity. If chemotherapy was delayed because of adverse reactions, weekly cetuximab was continued. If chemotherapy was discontinued for adverse reactions, weekly cetuximab as a single-agent could be continued until disease progression or unacceptable toxicity.
The main efficacy outcome measure was OS. Other outcome measures were PFS and objective response rate (ORR). Of the 442 randomized patients, the median age was 57 years, 90% were male, 98% were White, and 88% had baseline Karnofsky performance status ≥80.
Thirty-four percent of patients had oropharyngeal, 25% laryngeal, 20% oral cavity, and 14% hypopharyn… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term animal studies have not been performed to test cetuximab for carcinogenic potential, and no mutagenic or clastogenic potential of cetuximab was observed in the Salmonella-Escherichia coli (Ames) assay or in the in vivo rat micronucleus test. Menstrual cyclicity was impaired in female cynomolgus monkeys receiving weekly doses of 0.4 to 4 times the recommended dose of ERBITUX (based on total body surface area). Cetuximab-treated animals exhibited increased incidences of irregular or absent cycles, as compared to control animals.
These effects were initially noted beginning on week 25 and continued through the 6-week recovery period. No effects of cetuximab were observed on measured male fertility parameters (i.e., serum testosterone levels and analysis of sperm counts, viability, and motility) as compared to control male monkeys.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term animal studies have not been performed to test cetuximab for carcinogenic potential, and no mutagenic or clastogenic potential of cetuximab was observed in the Salmonella-Escherichia coli (Ames) assay or in the in vivo rat micronucleus test. Menstrual cyclicity was impaired in female cynomolgus monkeys receiving weekly doses of 0.4 to 4 times the recommended dose of ERBITUX (based on total body surface area). Cetuximab-treated animals exhibited increased incidences of irregular or absent cycles, as compared to control animals.
These effects were initially noted beginning on week 25 and continued through the 6-week recovery period. No effects of cetuximab were observed on measured male fertility parameters (i.e., serum testosterone levels and analysis of sperm counts, viability, and motility) as compared to control male monkeys.
📄 Recent Major Changes ▾
Indications and Usage ( 1.3 ) 09/2021 Dosage and Administration Recommended Dosage for Squamous Cell Carcinoma of the Head and Neck (SCCHN) ( 2.1 ) 04/2021 Recommended Dosage for Colorectal Cancer (CRC) ( 2.2 ) 04/2021 Dosage and Administration ( 2.1 , 2.3 ) 09/2021 Warnings and Precautions, Infusion Reactions ( 5.1 ) 11/2020
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL- Erbitux 50 mL (2mg/mL) Vial Carton NDC 66733-948-23 ERBITUX ® CETUXIMAB Injection For intravenous use Rx only 100 mg/50 mL (2 mg/mL) DO NOT DILUTE Lilly Erbitux 100mg Vial Erbitux 100mg Vial
PACKAGE LABEL- Erbitux 100 mL (2mg/mL) Vial Carton NDC 66733-958-23 ERBITUX ® CETUXIMAB Injection For intravenous use Rx only 200 mg/100 mL (2 mg/mL) DO NOT DILUTE Lilly Erbitux 200mg Vial Erbitux 200mg Vial
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |