
telmisartan 40 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin 2 Receptor Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Telmisartan is used to treat high blood pressure. Telmisartan is also used to decrease the chance of heart attack, stroke, or death in people 55 years of age or older who are at high risk for cardiovascular disease. Telmisartan is in a class of medications called angiotensin II receptor antagonists. It works by blocking the action of certain natural substances that tighten the blood vessels, allowing the blood to flow more smoothly and the heart to pump more efficiently. Untreated high blood pressure can damage the brain, heart, blood vessels, kidneys and other parts of the body. This damage m...
Read the full MedlinePlus article ↗- Telmisartan is used for two main reasons. First, it treats high blood pressure — bringing your numbers down protects you from strokes and heart attacks. Second, for people 55 and o...
- You take telmisartan once a day, and it can be taken with or without food — whichever fits your routine best. The most important thing is to take it at roughly the same time every...
- When should I take it, and does it matter if I take it with food?
- Most people do fine on telmisartan. Back pain, a stuffy or sore throat, mild diarrhea, or a runny nose are the more common, minor complaints. What you really need to call about rig...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Telmisartan — tap one for details:
Telmisartan may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 6HG8UB2MUY
Meglumine is a sugar-alcohol compound used as a solubilizer and pH buffer in medicines. It helps dissolve drugs that don't mix well in water and maintains stable acidity levels in the formulation.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.154 | $4.61 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3894 | $11.68 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.3317 | $9.95 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Telmisartan 40 mg 00378-2921-77 | Mylan | 90 tablets | $0.154 | AB | Availability likely | — |
| Telmisartan 40 mg 43547-0284-03 | Solco | 30 tablets | $0.154 | AB | Availability likely | — |
| Telmisartan 40 mg 65862-0868-03 | Aurobindo | 30 tablets | $0.154 | AB | Availability likely | — |
| telmisartan 40 mgthis 67877-0483-30 | Ascend | 30 tablets | $0.154 | AB | Availability likely | — |
| Telmisartan 40 mg 70756-0313-30 | Lifestar | 30 tablets | $0.154 | AB | Availability likely | — |
| Telmisartan 40 mg 72603-0832-01 | NorthStar | 30 tablets | $0.154 | AB | Availability likely | — |
| Telmisartan 40 mg 59746-0440-32 | Jubilant | 30 tablets | $0.258 | AB | FDA listed | +68% |
| Micardis 40 mg 00597-0040-37 | Boehringer | 30 tablets | $4.502 | — | Discontinued | +2831% |
| Telmisartan 40 mg 33342-0119-07 | Macleods | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 42291-0791-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 42571-0227-05 | Micro | 500 tablets | — | AB | Discontinued | — |
| Telmisartan 40 mg 46708-0609-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 50090-5490-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 53746-0292-30 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 62135-0536-30 | Chartwell | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 62332-0088-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| telmisartan 40 mg 63629-5682-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 65162-0292-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| telmisartan 40 mg 65841-0805-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| telmisartan 40 mg 68382-0472-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 68462-0200-01 | Glenmark | 100 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 68788-4034-03 | Preferred | 30 tablets | — | AB | FDA listed | — |
| telmisartan 40 mg 68788-8440-03 | Preferred | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 68788-8665-03 | Preferred | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 71209-0050-16 | Cadila | 300 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 71335-2173-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 72162-2439-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Telmisartan 40 mg 72241-0016-16 | Modavar | 300 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 67877-0483-05 | 500 TABLET in 1 BOTTLE (67877-483-05) | — | — | 2019-07-25 | Active |
| 67877-0483-30 You're viewing this | 30 TABLET in 1 BOTTLE (67877-483-30) | $0.1536 / ea | $4.61 | 2019-07-25 | Active |
| 67877-0483-84 | 3 BLISTER PACK in 1 CARTON (67877-483-84) / 10 TABLET in 1 BLISTER PACK | $0.1536 / ea | $4.61 | 2016-06-12 | Active |
| 67877-0483-90 | 90 TABLET in 1 BOTTLE (67877-483-90) | — | — | 2019-07-25 | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.1536 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 99% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 67877-0483-30?
What is the difference between NDC 67877-0483-30 and NDC 67877-0483-84?
What NDC number is used to bill for this package of telmisartan 40 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue telmisartan as soon as possible [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ]. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning. When pregnancy is detected, discontinue telmisartan as soon as possible ( 5.1 , 8.1 ) Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus ( 5.1 , 8.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Telmisartan tablets, USP are an angiotensin II receptor blocker (ARB) indicated for: Treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. ( 1.1 ) Cardiovascular (CV) risk reduction in patients unable to take ACE inhibitors ( 1.2 )
1.1Hypertension Telmisartan tablets, USP are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including the class to which this drug principally belongs.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Telmisartan may be used alone or in combination with other antihypertensive agents [see Clinical Studies (14.1) ].
1.2Cardiovascular Risk Reduction Telmisartan tablets, USP are indicated for reduction of the risk of myocardial infarction, stroke, or death from cardiovascular causes in patients 55 years of age or older at high risk of developing major cardiovascular events who are unable to take ACE inhibitors. High risk for cardiovascular events can be evidenced by a history of coronary artery disease, peripheral arterial disease, stroke, transient ischemic attack, or high-risk diabetes (insulin-dependent or non-insulin dependent) with evidence of end-organ damage [see Clinical Studies ( 14.2 )] .
Telmisartan can be used in addition to other needed treatment (such as antihypertensive, antiplatelet or lipid-lowering therapy) [see Clinical Studies ( 14.2 )]. Studies of telmisartan in this setting do not exclude the possibility that telmisartan may not preserve a meaningful fraction of the effect of the ACE inhibitor to which it was compared. Consider using the ACE inhibitor first, and, if it is st…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION May be administered with or without food ( 2.1 ) When used for cardiovascular risk reduction, monitoring of blood pressure is recommended, and if appropriate, adjustment of medications that lower blood pressure may be necessary ( 2.2 ) Indication Starting Dose Dose Range Hypertension ( 2.1 ) 40 mg once daily 40 to 80 mg once daily Cardiovascular Risk Reduction ( 2.2 ) 80 mg once daily 80 mg once daily
2.1Hypertension Dosage must be individualized. The usual starting dose of telmisartan tablets is 40 mg once a day. Blood pressure response is dose-related over the range of 20 to 80 mg [see Clinical Studies (14.1) ].
Most of the antihypertensive effect is apparent within 2 weeks and maximal reduction is generally attained after 4 weeks. No initial dosage adjustment is necessary for elderly patients or patients with renal impairment, including those on hemodialysis. Patients on dialysis may develop orthostatic hypotension; their blood pressure should be closely monitored.
Telmisartan tablets may be administered with other antihypertensive agents. Telmisartan tablets may be administered with or without food.
2.2Cardiovascular Risk Reduction The recommended dose of telmisartan tablets is 80 mg once a day and can be administered with or without food. It is not known whether doses lower than 80 mg of telmisartan are effective in reducing the risk of cardiovascular morbidity and mortality. When initiating telmisartan therapy for cardiovascular risk reduction, monitoring of blood pressure is recommended, and if appropriate, adjustment of medications that lower blood pressure may be necessary.
2.2Cardiovascular Risk Reduction The recommended dose of telmisartan tablets is 80 mg once a day and can be administered with or without food. It is not known whether doses lower than 80 mg of telmisartan are effective in reducing the risk of cardiovascular morbidity and mortality. When initiating telmisartan therapy for cardiovascular risk reduction, monitoring of blood pressure is recommended, and if appropriate, adjustment of medications that lower blood pressure may be necessary.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 20 mg, white to off-white, uncoated round shaped tablets, flat with beveled edges, plain on one side and debossed “036” on other side. 40 mg, white to off-white, uncoated oval shaped tablets, biconvex with beveled edges, plain on one side and debossed “037” on other side. 80 mg, white to off-white, uncoated oval shaped tablets, biconvex with beveled edges, plain on one side and debossed “038” on other side.
Tablets: 20mg, 40mg, 80mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Telmisartan is contraindicated in patients with known hypersensitivity (e.g., anaphylaxis or angioedema) to telmisartan or any other component of this product [see Adverse Reactions (6.2) ]. Do not co-administer aliskiren with telmisartan in patients with diabetes. [see Drug interactions(7) ]. Known hypersensitivity (e.g., anaphylaxis or angioedema) to telmisartan or any other component of this product ( 4 ) Do not co-administer aliskiren with telmisartan in patients with diabetes ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Avoid fetal or neonatal exposure ( 5.1 ) Hypotension: Correct any volume or salt depletion before initiating therapy. Observe for signs and symptoms of hypotension ( 5.2 ) Monitor carefully in patients with impaired hepatic ( 5.4 ) or renal function ( 5.5 ) Avoid concomitant use of an ACE inhibitor and angiotensin receptor blocker ( 5.6)
5.1Fetal Toxicity Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations. Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death.
When pregnancy is detected, discontinue telmisartan as soon as possible [see Use in Specific Populations (8.1) ].
5.2Hypotension In patients with an activated renin-angiotensin system, such as volume- or salt-depleted patients (e.g., those being treated with high doses of diuretics), symptomatic hypotension may occur after initiation of therapy with telmisartan. Either correct this condition prior to administration of telmisartan, or start treatment under close medical supervision with a reduced dose. If hypotension does occur, the patient should be placed in the supine position and, if necessary, given an intravenous infusion of normal saline.
A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized.
5.3Hyperkalemia Hyperkalemia may occur in patients on ARBs, particularly in patients with advanced renal impairment, heart failure, on renal replacement therapy, or on potassium supplements, potassium-sparing diuretics, potassium-containing salt substitutes or other drugs that increase potassium levels. Consider periodic determinations of serum electrolytes to detect possible electrolyte imbalances, particularly in patients at risk.
5.4Impaired Hepatic Function As the majority of telmisartan is eliminated by biliary excretion, patients with biliary obstructive disorders or hepatic insufficiency can be expected to have reduced clearance. Initiate telmisartan at low doses and titrate slowly in these patients [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ].
5.5Impaired Renal Function As a consequence of inhibiting the renin-angiotensin-aldosterone system, anticipate changes in renal function in susceptible individuals. In patients whose renal function may depend on the activity of the renin-angiotensin-aldosterone system (e.g., patients with severe congestive heart failure or renal dysfunction), treatment with angiotensin-converting enzyme (ACE) inhibitors and angiotensin receptor antagonists has been associated with oliguria and/or progressive azotemia and (rarely) with acute renal failure and/or death.
Similar results have been reported with telmisartan [see Clinical Pharmacology (12.3) ]. In studies of ACE inhibitors in patients with unilateral or bilateral renal artery stenosis, increases in serum creatinine or blood urea nitrogen were observed. There has been no long-term use of telmisartan in patients with unilateral or bilateral renal artery stenosis, but anticipate an effect similar to that seen with ACE inhibitors.
5.6Dual Blockade of the Renin-Angiotensin-Aldosterone System (RAS) Dual blockade of the RAS with angiotensin-receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. The ONTARGET trial enrolled 25,620 patients ≥55 years old with atherosclerotic disease or diabetes with end-organ damage, randomizing them to telmisartan only, ramipril only, or the combination, and followed them for a median of 56 months.
Patients receiving the combination of telmisartan and ramipril d…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reaction is described elsewhere in labeling: Renal dysfunction upon use with ramipril [see Warnings and Precautions (5.6) ] Hypertension: The most common adverse events (≥1%) reported in hypertension trials are back pain, sinusitis, and diarrhea ( 6.1 ) Cardiovascular risk reduction: The serious adverse events (≥1%) reported in cardiovascular risk reduction trials were intermittent claudication and skin ulcer ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ascend Laboratories, LLC at 1-877-272-7901 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reactions rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Hypertension Telmisartan has been evaluated for safety in more than 3700 patients, including 1900 treated for over 6 months and more than 1300 for over one year. Adverse experiences have generally been mild and transient in nature and have infrequently required discontinuation of therapy.
In placebo-controlled trials involving 1041 patients treated with various doses of telmisartan (20 to 160 mg) monotherapy for up to 12 weeks, the overall incidence of adverse events was similar to that in patients treated with placebo. Adverse events occurring at an incidence of ≥1% in patients treated with telmisartan and at a greater rate than in patients treated with placebo, irrespective of their causal association, are presented in Table 1. Table 1 Adverse Events Occurring at an Incidence of ≥1% in Patients Treated with Telmisartan and at a Greater Rate Than Patients Treated with Placebo Telmisartan n=1455 % Placebo n=380 % Upper respiratory tract infection 7 6 Back pain 3 1 Sinusitis 3 2 Diarrhea 3 2 Pharyngitis 1 0 In addition to the adverse events in the table, the following events occurred at a rate of ≥1% but were at least as frequent in the placebo group: influenza-like symptoms, dyspepsia, myalgia, urinary tract infection, abdominal pain, headache, dizziness, pain, fatigue, coughing, hypertension, chest pain, nausea, and peripheral edema.
Discontinuation of therapy because of adverse events was required in 2.8% of 1455 patients treated with telmisartan tablets and 6.1% of 380 placebo patients in placebo-controlled clinical trials. The incidence of adverse events was not dose-related and did not correlate with gender, age, or race of patients. The incidence of cough occurring with telmisartan in 6 placebo-controlled trials was identical to that noted for placebo-treated patients (1.6%).
In addition to those listed above, adverse events that occurred in more than 0.3% of 3500 patients treated with telmisartan monotherapy in controlled or open trials are listed below. It cannot be determined whether these events were causally related to telmisartan tablets: Autonomic Nervous System: impotence, increased sweating, flushing; Body as a Whole: allergy, fever, leg pain, malaise; Cardiovascular: palpitation, dependent edema, angina pectoris, tachycardia, leg edema, abnormal ECG; CNS: insomnia, somnolence, migraine, vertigo, paresthesia, involuntary muscle contractions, hypoesthesia; Gastrointestinal: flatulence, constipation, gastritis, vomiting, dry mouth, hemorrhoids, gastroenteritis, enteritis, gastroesophageal reflux, toothache, nonspecific gastrointestinal disorders; Metabolic: gout, hypercholesterolemia, diabetes mellitus; Musculoskeletal: arthritis, arthralgia, leg cramps; Psychiatric: anxiety, depression, nervousness; Resistance Mechanism: infection, fungal infection, abscess, otitis media; Respiratory: asthma, bronchitis, rhinitis, dyspnea, epistaxis; Skin: dermatitis, rash, eczema, pruritus; Urinary: micturition frequency, cystitis; Vascular: cerebrovascular disorder; and Special Senses: abnormal vision, conjunctivitis, tinnitus, earache.
During…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Aliskiren: Do not co-administer aliskiren with telmisartan in patients with diabetes. Avoid use of aliskiren with telmisartan in patients with renal impairment (GFR <60 mL/min). Digoxin: When telmisartan was co-administered with digoxin, median increases in digoxin peak plasma concentration (49%) and in trough concentration (20%) were observed.
Therefore, monitor digoxin levels when initiating, adjusting, and discontinuing telmisartan for the purpose of keeping the digoxin level within the therapeutic range. Lithium: Reversible increases in serum lithium concentrations and toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists including telmisartan. Therefore, monitor serum lithium levels during concomitant use.
Non-Steroidal Anti-Inflammatory Agents including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors): In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including telmisartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving telmisartan and NSAID therapy.
The antihypertensive effect of angiotensin II receptor antagonists, including telmisartan may be attenuated by NSAIDs including selective COX-2 inhibitors. NSAIDs : Increased risk of renal impairment and loss of anti-hypertensive effect ( 7 ) Do not co-administer aliskiren with telmisartan in patients with diabetes ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Do not breastfeed during treatment with telmisartan ( 8.2 ) Geriatric Patients: No overall difference in efficacy or safety vs younger patients, but greater sensitivity of some older individuals cannot be ruled out ( 8.5 )
8.1Pregnancy Risk Summary Telmisartan can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death (see Clinical Considerations ). Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Studies in rats and rabbits with telmisartan showed fetotoxicity only at maternally toxic doses (see Data ). When pregnancy is detected, discontinue telmisartan as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal adverse reactions Use of drugs that act on the RAS in the second and third trimesters of pregnancy can result in the following: oligohydramnios, reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death.
In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus. In patients taking telmisartan during pregnancy, perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation.
If oligohydramnios is observed, discontinue telmisartan, unless it is considered lifesaving for the mother. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to telmisartan for hypotension, oliguria, and hyperkalemia.
If oliguria or hypotension occurs, support blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function [see Use in Specific Populations (8.4) ] . Data Animal Data No teratogenic effects were observed when telmisartan was administered to pregnant rats at oral doses of up to 50 mg/kg/day and to pregnant rabbits at oral doses up to 45 mg/kg/day.
In rabbits, embryolethality associated with maternal toxicity (reduced body weight gain and food consumption) was observed at 45 mg/kg/day [about 12 times the maximum recommended human dose (MRHD) of 80 mg on a mg/m 2 basis]. In rats, maternally toxic (reduction in body weight gain and food consumption) telmisartan doses of 15 mg/kg/day (about 1.9 times the MRHD on a mg/m 2 basis), administered during late gestation and lactation, were observed to produce adverse effects in neonates, including reduced viability, low birth weight, delayed maturation, and decreased weight gain.
The no observed effect doses fo…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Telmisartan can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death (see Clinical Considerations ). Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Studies in rats and rabbits with telmisartan showed fetotoxicity only at maternally toxic doses (see Data ). When pregnancy is detected, discontinue telmisartan as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal adverse reactions Use of drugs that act on the RAS in the second and third trimesters of pregnancy can result in the following: oligohydramnios, reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death.
In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus. In patients taking telmisartan during pregnancy, perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation.
If oligohydramnios is observed, discontinue telmisartan, unless it is considered lifesaving for the mother. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to telmisartan for hypotension, oliguria, and hyperkalemia.
If oliguria or hypotension occurs, support blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function [see Use in Specific Populations (8.4) ] . Data Animal Data No teratogenic effects were observed when telmisartan was administered to pregnant rats at oral doses of up to 50 mg/kg/day and to pregnant rabbits at oral doses up to 45 mg/kg/day.
In rabbits, embryolethality associated with maternal toxicity (reduced body weight gain and food consumption) was observed at 45 mg/kg/day [about 12 times the maximum recommended human dose (MRHD) of 80 mg on a mg/m 2 basis]. In rats, maternally toxic (reduction in body weight gain and food consumption) telmisartan doses of 15 mg/kg/day (about 1.9 times the MRHD on a mg/m 2 basis), administered during late gestation and lactation, were observed to produce adverse effects in neonates, including reduced viability, low birth weight, delayed maturation, and decreased weight gain.
The no observed effect doses for developmental toxicity in rats and rabbits, 5 and 15 mg/kg/day, respectively, are about 0.64 and 3.7 times, on a mg/m 2 basis, the maximum recommended human dose of telmisartan (80 mg/day).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established [see Clinical Pharmacology (12.3) ]. Neonates with a history of in utero exposure to telmisartan If oliguria or hypotension occurs, support blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients receiving telmisartan in hypertension clinical studies, 551 (19%) were 65 to 74 years of age and 130 (4%) were 75 years or older. No overall differences in effectiveness and safety were observed in these patients compared to younger patients and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Of the total number of patients receiving telmisartan in the cardiovascular risk reduction study (ONTARGET), the percentage of patients ≥65 to <75 years of age was 42%; 15% of patients were ≥75 years old.
No overall differences in effectiveness and safety were observed in these patients compared to younger patients and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Limited data are available with regard to overdosage in humans. The most likely manifestation of overdosage with telmisartan tablets would be hypotension, dizziness and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation. If symptomatic hypotension should occur, supportive treatment should be instituted. Telmisartan is not removed by hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the reninangiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Telmisartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland.
Its action is therefore independent of the pathways for angiotensin II synthesis. There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Telmisartan has much greater affinity (>3,000 fold) for the AT 1 receptor than for the AT 2 receptor.
Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE. Because telmisartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin.
Whether this difference has clinical relevance is not yet known. Telmisartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of telmisartan on blood pressure.
12.2Pharmacodynamics In normal volunteers, a dose of telmisartan 80 mg inhibited the pressor response to an intravenous infusion of angiotensin II by about 90% at peak plasma concentrations with approximately 40% inhibition persisting for 24 hours. Plasma concentration of angiotensin II and plasma renin activity (PRA) increased in a dosedependent manner after single administration of telmisartan to healthy subjects and repeated administration to hypertensive patients. The once-daily administration of up to 80 mg telmisartan to healthy subjects did not influence plasma aldosterone concentrations.
In multiple dose studies with hypertensive patients, there were no clinically significant changes in electrolytes (serum potassium or sodium), or in metabolic function (including serum levels of cholesterol, triglycerides, HDL, LDL, glucose, or uric acid). In 30 hypertensive patients with normal renal function treated for 8 weeks with telmisartan 80 mg or telmisartan 80 mg in combination with hydrochlorothiazide 12.5 mg, there were no clinically significant changes from baseline in renal blood flow, glomerular filtration rate, filtration fraction, renovascular resistance, or creatinine clearance.
12.3Pharmacokinetics Absorption: Following oral administration, peak concentrations (C max ) of telmisartan are reached in 0.5 to 1 hour after dosing. Food slightly reduces the bioavailability of telmisartan, with a reduction in the area under the plasma concentration-time curve (AUC) of about 6% with the 40 mg tablet and about 20% after a 160 mg dose. The absolute bioavailability of telmisartan is dose dependent.
At 40 and 160 mg the bioavailability was 42% and 58%, respectively. The pharmacokinetics of orally administered telmisartan are nonlinear over the dose range 20 to 160 mg, with greater than proportional increases of plasma concentrations (C max and AUC) with increasing doses. Telmisartan shows bi-exponential decay kinetics with a terminal elimination half-life of approximately 24 hours.
Trough plasma concentrations of telmisartan with once daily dosing are about 10% to 25% of peak plasma concentrations. Telmisartan has an accumulation index in plasma of 1.5 to 2.0 upon repeated…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the reninangiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Telmisartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland.
Its action is therefore independent of the pathways for angiotensin II synthesis. There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Telmisartan has much greater affinity (>3,000 fold) for the AT 1 receptor than for the AT 2 receptor.
Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE. Because telmisartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin.
Whether this difference has clinical relevance is not yet known. Telmisartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of telmisartan on blood pressure.
📦 How Supplied / Storage and Handling ▾
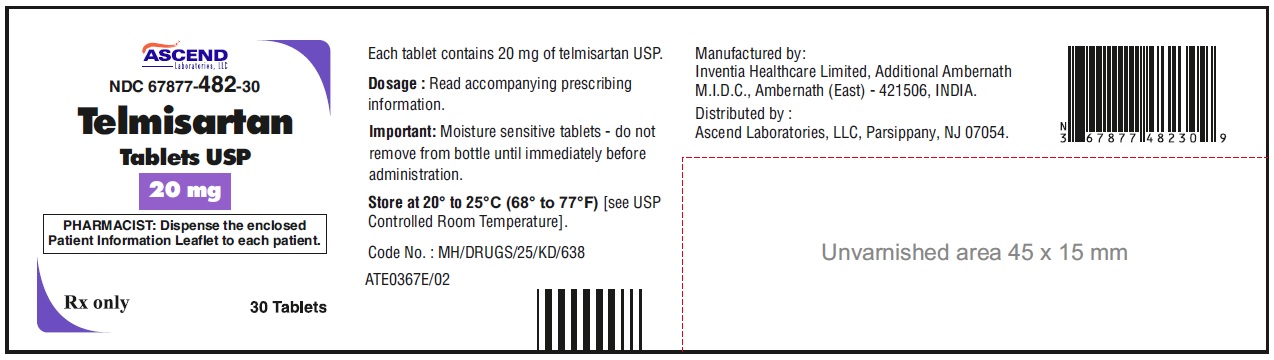
16 HOW SUPPLIED/STORAGE AND HANDLING Telmisartan Tablets, USP are supplied as below: 20 mg, white to off-white uncoated round shaped tablets, flat, with beveled edges, plain on one side and debossed “036”on other side. NDC 67877-482-30 bottle of 30 units NDC 67877-482-90 bottle of 90 units NDC 67877-482-05 bottle of 500 units 40 mg, white to off-white uncoated oval shaped tablets, biconvex with beveled edges, plain on one side and debossed “037”on other side. NDC 67877-483-30 bottle of 30 units NDC 67877-483-90 bottle of 90 units NDC 67877-483-05 bottle of 500 units 80 mg, white to off-white uncoated oval shaped tablets, biconvex with beveled edges, plain on one side and debossed “038”on other side.
NDC 67877-484-30 bottle of 30 units NDC 67877-484-90 bottle of 90 units NDC 67877-484-05 bottle of 500 units Storage Store at 20 o to 25 o C (68 o to 77 o F) [see USP Controlled Room Temperature]. Dispense in a tightly closed container. Insert the cotton every time back in to the bottle after every consumption
📋 Description ▾
11 DESCRIPTION Telmisartan tablets USP is a non-peptide angiotensin II receptor (type AT 1 ) antagonist. Telmisartan is chemically described as 4'-[(1,4'-dimethyl-2'-propyl [2,6'-bi-1H-benzimidazol]-1'-yl)methyl]-[1,1'-biphenyl]-2-carboxylic acid. Its empirical formula is C 33 H 30 N 4 O 2 , its molecular weight is 514.63, and its structural formula is: Telmisartan, USP is a white to slightly yellowish solid.
It is practically insoluble in water and in the pH range of 3 to 9, sparingly soluble in strong acid (except insoluble in hydrochloric acid), and soluble in strong base. Telmisartan is available as tablets for oral administration, containing 20 mg, 40 mg or 80 mg of telmisartan USP. The tablets contain the following inactive ingredients: magnesium stearate, mannitol, meglumine, povidone, sodium hydroxide and sodium streayl fumarate.
Telmisartan tablets, USP are hygroscopic and require protection from moisture. telmisartan-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information) Pregnancy Advise female patients of childbearing age about the consequences of exposure to telmisartan during pregnancy. Discuss treatment options with women planning to become pregnant. Tell patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] .
Lactation Advise nursing women not to breastfeed during treatment with telmisartan [see Use in Specific Populations (8.2) ] . Symptomatic Hypotension and Syncope Advise patients that lightheadedness can occur, especially during the first days of therapy, and to report it to their healthcare provider. Inform patients that inadequate fluid intake, excessive perspiration, diarrhea, or vomiting can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope.
Advise patients to contact their healthcare provider if syncope occurs [see Warnings and Precautions (5.2) ] . Potassium Supplements Advise patients not to use potassium supplements or salt substitutes that contain potassium without consulting the prescribing healthcare provider [see Warnings and Precautions (5.3) ] . Manufactured By: Inventia Healthcare Limited, F1-F1/1-F75/1, Additional Ambernath M.I.D.C., Ambernath (East)-421506, Thane 421506, Maharashtra State, India Distributed by: Ascend Laboratories, LLC Bedminster, NJ 07921.
Revised: March 2025 Trademarks are the property of their respective owners. 2011663