
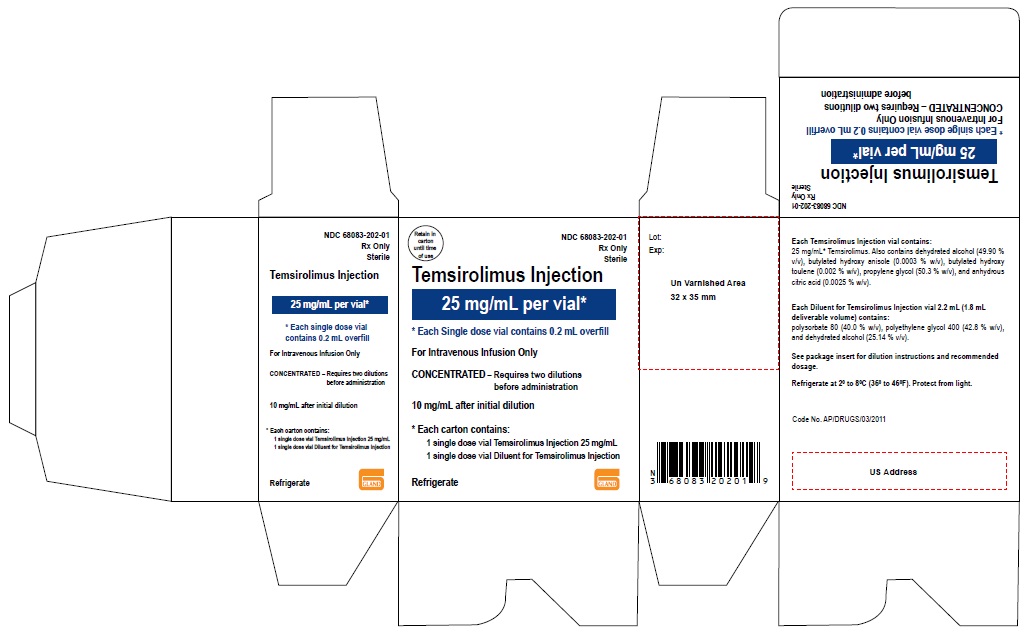
Temsirolimus Kit — NDC 68083-202-01 (Billing 68083-0202-01)
This is a package of Temsirolimus Kit from Gland Pharma Limited, marketed since Aug 2019 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 68083-202-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 68083 labeler · 202 product · 01 package
- Package marketed since
- Aug 26, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6808320201 9
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 722289
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Temsirolimus is used to treat advanced renal cell carcinoma (RCC, a type of cancer that begins in the kidney). Temsirolimus is in a class of medications called kinase inhibitors. It works by blocking the action of the abnormal protein that tells the cancer cells to multiply. This may help slow the growth of tumors.
Read the full MedlinePlus article ↗- It treats advanced renal cell carcinoma, a type of kidney cancer. It works by blocking a protein called mTOR that helps cancer cells divide and grow.
- A nurse or doctor gives it as an IV infusion that takes about 30 to 60 minutes, once a week. You will get an antihistamine first to lower the chance of an allergic-type reaction. T...
- Common ones are rash, tiredness, mouth sores, nausea, swelling and low appetite. Your blood sugar, cholesterol and blood counts may also change, which is why you will have regular...
- Call for new or worsening cough or shortness of breath, fever, signs of infection, severe belly pain, or blood in your stool. Also report excessive thirst or a big change in urinat...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68083-0202-01 You're viewing this Main listing | 1 KIT in 1 CARTON * 1 mL in 1 VIAL, SINGLE-USE * 1.8 mL in 1 VIAL, SINGLE-USE | 2019-08-26 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Torisel 00008-1179-01 | Wyeth | 1 kit | — | AP | FDA listed | — |
| Temsirolimus 16729-0223-61 | Accord | 1 kit | — | AP | FDA listed | — |
| Temsirolimus 65219-0200-05 | Fresenius | 1 kit | — | AP | FDA listed | — |
| Temsirolimusthis 68083-0202-01 | Gland | 1 kit | — | AP | FDA listed | — |
| Temsirolimus 72611-0785-02 | Almaject, | 1 kit | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Gland Pharma Limited labeler code 68083
- CARBOPLATIN 10 mg/mL Injection, Solution NDC 68083-190-01
- CARBOPLATIN 10 mg/mL Injection, Solution NDC 68083-191-01
- CARBOPLATIN 10 mg/mL Injection, Solution NDC 68083-192-01
- CARBOPLATIN 10 mg/mL Injection, Solution NDC 68083-193-01
- Dexrazoxane 500 mg/50mL Injection, Powder, Lyophilized, For Solution NDC 68083-195-01
- Azithromycin monohydrate 500 mg/10mL Injection, Powder, Lyophilized, For Solution NDC 68083-199-10
- Moxifloxacin Ophthalmic Solution 5 mg/mL Solution/ Drops NDC 68083-210-01
- Esmolol Hydrochloride 10 mg/mL Injection NDC 68083-211-25
- Olopatadine Hydrochloride Ophthalmic Solution 2 mg/mL Solution NDC 68083-231-01
- Nelarabine 5 mg/mL Injection NDC 68083-233-06
- Etomidate 2 mg/mL Solution NDC 68083-234-10
- Etomidate 2 mg/mL Solution NDC 68083-235-10
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Temsirolimus injection is indicated for the treatment of advanced renal cell carcinoma. Temsirolimus injection is a kinase inhibitor indicated for the treatment of advanced renal cell carcinoma. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION • The recommended dose of Temsirolimus injection is 25 mg administered as an intravenous infusion over a 30-60 minute period once a week. Treat until disease progression or unacceptable toxicity. (2.1) • Antihistamine pre-treatment is recommended.
(2.2) • Dose reduction is required in patients with mild hepatic impairment. (2.4) • Temsirolimus injection vial contents must first be diluted with the enclosed diluent before diluting the resultant solution with 250 mL of 0.9% Sodium Chloride Injection. (2.5)
2.1Advanced Renal Cell Carcinoma The recommended dose of Temsirolimus injection for advanced renal cell carcinoma is 25 mg administered as an intravenous infusion over a 30 – 60 minute period once a week. Treatment should continue until disease progression or unacceptable toxicity occurs.
2.2Premedication Patients should receive prophylactic intravenous diphenhydramine 25 to 50 mg (or similar antihistamine) approximately 30 minutes before the start of each dose of Temsirolimus injection [see Warnings and Precautions (5.1)] .
2.3Dosage Interruption/Adjustment Temsirolimus injection should be held for absolute neutrophil count (ANC) <1,000/mm 3 , platelet count <75,000/mm 3 , or NCI CTCAE grade 3 or greater adverse reactions. Once toxicities have resolved to grade 2 or less, Temsirolimus injection may be restarted with the dose reduced by 5 mg/week to a dose no lower than 15 mg/week.
2.4Dose Modification Guidelines Hepatic Impairment : Use caution when treating patients with hepatic impairment. If Temsirolimus injection must be given in patients with mild hepatic impairment (bilirubin >1 – 1.5×ULN or AST >ULN but bilirubin ≤ULN), reduce the dose of Temsirolimus injection to 15 mg/week. Temsirolimus injection is contraindicated in patients with bilirubin >1.5×ULN [see Contraindications (4), Warnings and Precautions (5.2) and Use in Specific Populations (8.7)] .
Concomitant Strong CYP3A4 Inhibitors : The concomitant use of strong CYP3A4 inhibitors should be avoided (e.g. ketoconazole, itraconazole, clarithromycin, atazanavir, indinavir, nefazodone, nelfinavir, ritonavir, saquinavir, telithromycin, and voriconazole). Grapefruit juice may also increase plasma concentrations of sirolimus (a major metabolite of temsirolimus) and should be avoided. If patients must be co-administered a strong CYP3A4 inhibitor, based on pharmacokinetic studies, a Temsirolimus injection dose reduction to 12.5 mg/week should be considered.
This dose of Temsirolimus injection is predicted to adjust the AUC to the range observed without inhibitors. However, there are no clinical data with this dose adjustment in patients receiving strong CYP3A4 inhibitors. If the strong inhibitor is discontinued, a washout period of approximately 1 week should be allowed before the Temsirolimus injection dose is adjusted back to the dose used prior to initiation of the strong CYP3A4 inhibitor [see Warnings and Precautions (5.12) and Drug Interactions (7.2)] Concomitant Strong CYP3A4 Inducers: The use of concomitant strong CYP3A4 inducers should be avoided (e.g. dexamethasone, phenytoin, carbamazepine, rifampin, rifabutin, rifampacin, phenobarbital).
If patients must be co-administered a strong CYP3A4 inducer, based on pharmacokinetic studies, a Temsirolimus injection dose increase from 25 mg/week up to 50 mg/week should be considered. This dose of Temsirolimus injection is predicted to adjust the AUC to the range observed without inducers. However, there are no clinical data with this dose adjustment in patients receiving strong CYP3A4 inducers.
If the strong inducer is discontinued the temsirolimus dose should be returned to the dose used prior to initiation of the strong CYP3A4 inducer [see Warnings and Precautions (5.12) and Drug Interactions (7.1)].
2.5Instructions for Preparation Temsirolimus injection is a cytotoxic drug. Follow applicable special handling and disposal procedures1. Temsirolimus injection must be stored under refrigeratio… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Temsirolimus injection is supplied as a kit consisting of the following: Temsirolimus injection (25 mg/mL). The Temsirolimus injection vial contains temsirolimus at a concentration of 25 mg/mL. The vial contains an overfill of 0.2 mL to ensure the ability to withdraw the recommended dose.
DILUENT for Temsirolimus injection. The DILUENT vial includes a deliverable volume of 1.8 mL. This vial contains an overfill in order to ensure that the appropriate volume can be withdrawn.
Temsirolimus injection, 25 mg/mL supplied with DILUENT for Temsirolimus injection. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Temsirolimus injection is contraindicated in patients with bilirubin >1.5×ULN [ see Warnings and Precautions (5.2) ]. Temsirolimus injection is contraindicated in patients with bilirubin > 1.5×ULN. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypersensitivity/Infusion Reactions (including some life-threatening and rare fatal reactions) can occur early in the first infusion of Temsirolimus injection. Patients should be monitored throughout the infusion. (5.1) • To treat hypersensitivity reactions stop Temsirolimus injection and treat with an antihistamine.
Temsirolimus injection may be restarted at physician discretion at a slower rate. (5.1) • Hepatic Impairment: Use caution when treating patients with mild hepatic impairment and reduce dose. (2.4, 5.2) • Hyperglycemia and hyperlipidemia are likely and may require treatment.
Monitor glucose and lipid profiles. (5.3, 5.6) • Infections may result from immunosuppression. (5.4) • Monitor for symptoms or radiographic changes of interstitial lung disease (ILD).
If ILD is suspected, discontinue Temsirolimus injection, and consider use of corticosteroids and/or antibiotics. (5.5) • Bowel perforation may occur. Evaluate fever, abdominal pain, bloody stools, and/or acute abdomen promptly.
(5.7) • Renal failure, sometimes fatal, has occurred. Monitor renal function at baseline and while on Temsirolimus injection. (5.8) • Due to abnormal wound healing, use Temsirolimus injection with caution in the perioperative period.
(5.9) • Proteinuria and nephrotic syndrome may occur. Monitor urine protein prior to the start of Temsirolimus injection therapy and periodically thereafter. Discontinue Temsirolimus injection in patients with who develop nephrotic syndrome.
(5.11) • Live vaccinations and close contact with those who received live vaccines should be avoided. (5.14) • Embryo-Fetal Toxicity: Can cause fetal harm. Advise patients of the potential hazard to the fetus and to use effective contraception.
(5.15, 8.1, 8.3) • Elderly patients may be more likely to experience certain adverse reactions, including diarrhea, edema and pneumonia. (5.16)
5.1Hypersensitivity/Infusion Reactions Hypersensitivity/infusion reactions, including but not limited to flushing, chest pain, dyspnea, hypotension, apnea, loss of consciousness, hypersensitivity and anaphylaxis, have been associated with the administration of temsirolimus. These reactions can occur very early in the first infusion, but may also occur with subsequent infusions. Patients should be monitored throughout the infusion and appropriate supportive care should be available.
Temsirolimus infusion should be interrupted in all patients with severe infusion reactions and appropriate medical therapy administered. Temsirolimus injection should be used with caution in persons with known hypersensitivity to temsirolimus or its metabolites (including sirolimus), polysorbate 80, or to any other component (including the excipients) of Temsirolimus injection. An H 1 antihistamine should be administered to patients before the start of the intravenous temsirolimus infusion.
Temsirolimus injection should be used with caution in patients with known hypersensitivity to an antihistamine, or patients who cannot receive an antihistamine for other medical reasons. If a patient develops a hypersensitivity reaction during the Temsirolimus injection infusion, the infusion should be stopped and the patient should be observed for at least 30 to 60 minutes (depending on the severity of the reaction). At the discretion of the physician, treatment may be resumed with the administration of an H 1 -receptor antagonist (such as diphenhydramine), if not previously administered [see Dosage and Administration (2.2)] , and/or an H 2 -receptor antagonist (such as intravenous famotidine 20 mg or intravenous ranitidine 50 mg) approximately 30 minutes before restarting the Temsirolimus injection infusion.
The infusion may then be resumed at a slower rate (up to 60 minutes). A benefit-risk assessment should be done prior to the continuation of temsirolimus therapy in patients with severe or life-threatening reactions.
5.2Hepatic Impairment The safety and pharmacokinetics of Temsirolimus injecti… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions have been associated with Temsirolimus injection in clinical trials and are discussed in greater detail in other sections of the label [see Warnings and Precautions (5)]. • Hypersensitivity/Infusion Reactions [see Warnings and Precautions (5.1)] • Hepatic Impairment [see Warnings and Precautions (5.2)] • Hyperglycemia/Glucose Intolerance [see Warnings and Precautions (5.3)] • Infections [see Warnings and Precautions (5.4)] • Interstitial Lung Disease [see Warnings and Precautions (5.5)] • Hyperlipidemia [see Warnings and Precautions (5.6)] • Bowel Perforation [see Warnings and Precautions (5.7)] • Renal Failure [see Warnings and Precautions (5.8)] • Wound Healing Complications [see Warnings and Precautions (5.9)] • Intracerebral Hemorrhage [see Warnings and Precautions (5.10)] The most common (≥ 30%) adverse reactions observed with Temsirolimus injection are rash, asthenia, mucositis, nausea, edema, and anorexia.
The most common (≥30%) laboratory abnormalities observed with Temsirolimus injection are anemia, hyperglycemia, hyperlipidemia, hypertriglyceridemia, lymphopenia, elevated alkaline phosphatase, elevated serum creatinine, hypophosphatemia, thrombocytopenia, elevated AST, and leukopenia. The most common adverse reactions (incidence ≥ 30%) are rash, asthenia, mucositis, nausea, edema, and anorexia. The most common laboratory abnormalities (incidence ≥30%) are anemia, hyperglycemia, hyperlipidemia, hypertriglyceridemia, elevated alkaline phosphatase, elevated serum creatinine, lymphopenia, hypophosphatemia, thrombocytopenia, elevated AST, and leukopenia.
(6) To report SUSPECTED ADVERSE REACTIONS, contact FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, the adverse reaction rates observed cannot be directly compared to rates in other trials and may not reflect the rates observed in clinical practice. In the Phase 3 randomized, open-label study of interferon alfa (IFN-α) alone, Temsirolimus injection alone, and Temsirolimus injection and IFN-α, a total of 616 patients were treated. Two hundred patients received IFN-α weekly, 208 received Temsirolimus injection 25 mg weekly, and 208 patients received a combination of Temsirolimus injection and IFN-α weekly [see Clinical Studies (14)] .
Treatment with the combination of Temsirolimus injection 15 mg and IFN-α was associated with an increased incidence of multiple adverse reactions and did not result in a significant increase in overall survival when compared with IFN-α alone. Table 1 shows the percentage of patients experiencing treatment emergent adverse reactions. Reactions reported in at least 10% of patients who received Temsirolimus injection 25 mg alone or IFN-α alone are listed.
Table 2 shows the percentage of patients experiencing selected laboratory abnormalities. Data for the same adverse reactions and laboratory abnormalities in the IFN-α alone arm are shown for comparison : Table 1 – Adverse Reactions Reported in at Least 10% of Patients Who Received 25 mg IV Temsirolimus injection or IFN-α in the Randomized Trial Adverse Reaction Temsirolimus injection 25 mg n=208 IFN-α n=200 All Grades* n (% ) Grades 3&4* n (% ) All Grades* n (% ) Grades 3&4* n (%) General disorders Asthenia Edema a Pain Pyrexia Weight Loss Headache Chest Pain Chills 106 (51) 73 (35) 59 (28) 50 (24) 39 (19) 31 (15) 34 (16) 17 (8) 23 (11) 7 (3) 10 (5) 1 (1) 3 (1) 1 (1) 2 (1) 1 (1) 127 (64) 21 (11) 31 (16) 99 (50) 50 (25) 30 (15) 18 (9) 59 (30) 52 (26) 1 (1) 4 (2) 7 (4) 4 (2) 0 (0) 2 (1) 3 (2) Gastrointestinal disorders Mucositis b Anorexia Nausea Diarrhea Abdominal Pain Constipation Vomiting 86 (41) 66 (32) 77 (37) 56 (27) 44 (21) 42 (20) 40 (19) 6 (3) 6 (3) 5 (2) 3 (1) 9 (4) 0 (0) 4 (2) 19 (10) 87 (44) 82 (41) 40 (20) 34 (17) 36 (18) 57 (29) 0 (0) 8 (4) 9 (5) 4 (2) 3 (2) 1 (1) 5 (3) Infections Infections c Urinary tract infection d Pharyngi… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong inducers of CYP3A4/5 and inhibitors of CYP3A4 may affect concentrations of the primary metabolite of Temsirolimus injection. If alternatives cannot be used, dose modifications of Temsirolimus injection are recommended. (7.1, 7.2,7.3)
7.1Agents Inducing CYP3A Metabolism Co-administration of Temsirolimus injection with rifampin, a potent CYP3A4/5 inducer, had no significant effect on temsirolimus C max (maximum concentration) and AUC (area under the concentration versus the time curve) after intravenous administration, but decreased sirolimus C max by 65% and AUC by 56% compared to Temsirolimus injection treatment alone. If alternative treatment cannot be administered, a dose adjustment should be considered [see Dosage and Administration (2.4)] .
7.2Agents Inhibiting CYP3A Metabolism Co-administration of Temsirolimus injection with ketoconazole, a potent CYP3A4 inhibitor, had no significant effect on temsirolimus C max or AUC; however, sirolimus AUC increased 3.1-fold, and C max increased 2.2-fold compared to Temsirolimus injection alone. If alternative treatment cannot be administered, a dose adjustment should be considered [see Dosage and Administration (2.4)] .
7.3Angioedema with ACE inhibitors and Calcium Channel Blokers Angioedema has been reported in patients taking mammalian target of rapamycin (mTOR) inhibitors in combination with ramipril and/or amlodipine. Monitor patients for signs and symptoms of angioedema when temsirolimus is given concomitantly with an angiotensin converting enzyme (ACE) inhibitors (e.g., ramipril) or calcium channel blockers (CCB) (e.g., amlodipine).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Do not breastfeed. (8.2)
8.1Pregnancy Risk Summary Based on findings in animal studies and its mechanism of action, temsirolimus can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. Although there are no data on the use of Temsirolimus injection in pregnant women, there are limited data on the use of sirolimus, the active metabolite of temsirolimus, during pregnancy; however, these data are insufficient to inform a drug-associated risk of adverse developmental outcomes. In animal reproductive studies, oral daily administration of temsirolimus to pregnant rats and rabbits during organogenesis caused adverse embryo-fetal effects at approximately 0.04 and 0.12 times the AUC in patients at the recommended dose, respectively (see Data).
Advise pregnant women of the potential hazard to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Animal Data Temsirolimus administered daily as an oral formulation throughout organogenesis caused adverse embryo-fetal effects in rats and rabbits at human sub-therapeutic exposures. Embryo-fetal adverse effects in rats consisted of reduced fetal weight and reduced ossifications, and in rabbits included reduced fetal weight, omphalocele, bifurcated sternabrae, notched ribs, and incomplete ossifications In rats, the adverse embryo-fetal effects were observed at the oral dose of 2.7 mg/m2/day (approximately 0.04-fold the AUC in patients with cancer at the human recommended dose).
In rabbits, the adverse embryo-fetal effects were observed at the oral dose of ≥7.2 mg/m2/day (approximately 0.12-fold the AUC in patients with cancer at the recommended human dose).
8.2Lactation Risk Summary There is no information regarding the presence of Temsirolimus injection or its metabolites in human milk, or their effects on the breastfed child or milk production. Trace amounts of sirolimus, the active metabolite of temsirolimus, were present in milk from lactating rats administered sirolimus. Because of the potential for serious adverse reactions in a breastfed child from Temsirolimus injection, advise a lactating woman not to breastfeed during treatment with Temsirolimus injection and for 3 weeks after the final dose.
8.3Females and Males of Reproductive Potential Contraception Females Temsirolimus injection can cause fetal harm when administered to a pregnant woman [see Use in Specific Population (8.1)] . Advise females of reproductive potential to use effective contraception during treatment with Temsirolimus injection and for 3 months after the last dose. Males Advise males with partners of reproductive potential to use effective contraception during treatment with Temsirolimus injection and for 3 months after the last dose [see Nonclinical Toxicology (13.1)].
Infertility Based on the findings in animal fertility studies, male and female fertility may be compromised by the treatment with Temsirolimus injection. It is not known if the effects on fertility in animal studies were reversible [see Nonclinical Toxicology (13.1)].
8.4Pediatric Use Limited data are available on the use of temsirolimus in pediatric patients. The effectiveness of temsirolimus in pediatric patients with advanced recurrent/refractory solid tumors has not been established. Temsirolimus injection was studied in 71 patients (59 patients ages 1 to 17 years and 12 patients ages 18 to 21 years) with relapsed/refractory solid tumors in a phase 1-2 safety and exploratory pharmacodynamic study.
In phase 1, 19 pediatric patients with advanced recurrent/refractory solid tumors received Temsirolimus injection at doses ranging from 10 mg/m 2… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animal studies and its mechanism of action, temsirolimus can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1)]. Although there are no data on the use of Temsirolimus injection in pregnant women, there are limited data on the use of sirolimus, the active metabolite of temsirolimus, during pregnancy; however, these data are insufficient to inform a drug-associated risk of adverse developmental outcomes. In animal reproductive studies, oral daily administration of temsirolimus to pregnant rats and rabbits during organogenesis caused adverse embryo-fetal effects at approximately 0.04 and 0.12 times the AUC in patients at the recommended dose, respectively (see Data).
Advise pregnant women of the potential hazard to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Animal Data Temsirolimus administered daily as an oral formulation throughout organogenesis caused adverse embryo-fetal effects in rats and rabbits at human sub-therapeutic exposures. Embryo-fetal adverse effects in rats consisted of reduced fetal weight and reduced ossifications, and in rabbits included reduced fetal weight, omphalocele, bifurcated sternabrae, notched ribs, and incomplete ossifications In rats, the adverse embryo-fetal effects were observed at the oral dose of 2.7 mg/m2/day (approximately 0.04-fold the AUC in patients with cancer at the human recommended dose).
In rabbits, the adverse embryo-fetal effects were observed at the oral dose of ≥7.2 mg/m2/day (approximately 0.12-fold the AUC in patients with cancer at the recommended human dose).
🧒 Pediatric Use ▾
8.4Pediatric Use Limited data are available on the use of temsirolimus in pediatric patients. The effectiveness of temsirolimus in pediatric patients with advanced recurrent/refractory solid tumors has not been established. Temsirolimus injection was studied in 71 patients (59 patients ages 1 to 17 years and 12 patients ages 18 to 21 years) with relapsed/refractory solid tumors in a phase 1-2 safety and exploratory pharmacodynamic study.
In phase 1, 19 pediatric patients with advanced recurrent/refractory solid tumors received Temsirolimus injection at doses ranging from 10 mg/m 2 to 150 mg/m 2 as a 60-minute intravenous infusion once weekly in three-week cycles. In phase 2, 52 pediatric patients with recurrent/relapsed neuroblastoma, rhabdomyosarcoma or high grade glioma received Temsirolimus injection at a weekly dose of 75 mg/m 2 . One of 19 patients with neuroblastoma achieved a partial response.
There were no objective responses in pediatric patients with recurrent/relapsed rhabdomyosarcoma or high grade glioma. Adverse reactions associated with Temsirolimus injection were similar to those observed in adults. The most common adverse reactions (≥20%) in pediatric patients receiving the 75 mg/m 2 dose included thrombocytopenia, infections, asthenia/fatigue, fever, pain, leukopenia, rash, anemia, hyperlipidemia, increased cough, stomatitis, anorexia, increased plasma levels of alanine aminotransferase and aspartate aminotransferase, hypercholesterolemia, hyperglycemia, abdominal pain, headache, arthralgia, upper respiratory infection, nausea and vomiting, neutropenia, hypokalemia and hypophosphatemia.
Pharmacokinetics: In phase 1 of the above mentioned pediatric trial, the single dose and multiple dose total systemic exposure (AUC) of temsirolimus and sirolimus were less than dose-proportional over the dose range of 10 to 150 mg/m 2 . In the phase 2 portion, the multiple dose (Day 1, Cycle 2) pharmacokinetics of Temsirolimus injection 75 mg/m 2 were characterized in an additional 35 patients ages 28 days to 21 years (median age of 8 years). The geometric mean body surface adjusted clearance of temsirolimus and sirolimus was
9.45 L/h/m 2 and
9.26L/h/m 2 , respectively. The mean elimination half-life of temsirolimus and sirolimus was 31 hours and 44 hours, respectively. The exposure (AUCss) to temsirolimus and sirolimus was approximately 6-fold and 2-fold higher, respectively than the exposure in adult patients receiving a 25 mg intravenous infusion.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Temsirolimus injection did not include sufficient numbers of subjects aged 65 and older to determine whether they respond differently from younger subjects. Based on the results of a phase 3 study, elderly patients may be more likely to experience certain adverse reactions including diarrhea, edema and pneumonia [see Warnings and Precautions (5.16)] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific treatment for Temsirolimus injection intravenous overdose. Temsirolimus injection has been administered to patients with cancer in phase 1 and 2 trials with repeated intravenous doses as high as 220 mg/m 2 . The risk of several serious adverse events, including thrombosis, bowel perforation, interstitial lung disease (ILD), seizure, and psychosis, is increased with doses of Temsirolimus injection greater than 25 mg.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Temsirolimus is an inhibitor of mTOR (mammalian target of rapamycin). Temsirolimus binds to an intracellular protein (FKBP-12), and the protein-drug complex inhibits the activity of mTOR that controls cell division. Inhibition of mTOR activity resulted in a G1 growth arrest in treated tumor cells.
When mTOR was inhibited, its ability to phosphorylate p70S6k and S6 ribosomal protein, which are downstream of mTOR in the PI3 kinase/AKT pathway was blocked. In in vitro studies using renal cell carcinoma cell lines, temsirolimus inhibited the activity of mTOR and resulted in reduced levels of the hypoxia-inducible factors HIF-1 and HIF-2 alpha, and the vascular endothelial growth factor.
12.2Pharmacodynamics Effects on Electrocardiogram: There were no clinically relevant QT changes observed at the recommended dose for Temsirolimus injection. In a randomized, single-blinded, crossover study, 58 healthy subjects received Temsirolimus injection 25 mg, placebo, and a single oral dose of moxifloxacin 400 mg. A supratherapeutic Temsirolimus injection dose was not studied in this randomized QT trial.
The largest difference between the upper bound 2-sided 90% CI for the mean difference between Temsirolimus injection and placebo-corrected QT interval was less than 10 ms. In a different trial in 69 patients with a hematologic malignancy, Temsirolimus injection doses up to 175 mg were studied. No patient with a normal QTcF at baseline had an increase in QTcF >60 ms.
Additionally, there were no patients with a QTcF interval greater than 500 ms.
12.3Pharmacokinetics Absorption Following administration of a single 25 mg dose of Temsirolimus injection in patients with cancer, mean temsirolimus C max in whole blood was 585 ng/mL (coefficient of variation, CV =14%), and mean AUC in blood was 1627 ng•h/mL (CV=26%). Typically C max occurred at the end of infusion. Over the dose range of 1 mg to 25 mg, temsirolimus exposure increased in a less than dose proportional manner while sirolimus exposure increased proportionally with dose.
Following a single 25 mg intravenous dose in patients with cancer, sirolimus AUC was 2.7-fold that of temsirolimus AUC, due principally to the longer half-life of sirolimus. Distribution Following a single 25 mg intravenous dose, mean steady-state volume of distribution of temsirolimus in whole blood of patients with cancer was 172 liters. Both temsirolimus and sirolimus are extensively partitioned into formed blood elements.
Metabolism Cytochrome P450 3A4 is the major isozyme responsible for the formation of five temsirolimus metabolites. Sirolimus, an active metabolite of temsirolimus, is the principal metabolite in humans following intravenous treatment. The remainder of the metabolites account for less than 10% of radioactivity in the plasma.
In human liver microsomes temsirolimus was an inhibitor of CYP2D6 and 3A4. However, there was no effect observed in vivo when temsirolimus was administered with desipramine (a CYP2D6 substrate), and no effect is anticipated with substrates of CYP3A4 metabolism. Elimination Elimination is primarily via the feces.
After a single IV dose of [ 14 C]-temsirolimus approximately 82% of total radioactivity was eliminated within 14 days, with 4.6% and 78% of the administered radioactivity recovered in the urine and feces, respectively. Following a single 25 mg dose of Temsirolimus injection in patients with cancer, temsirolimus mean (CV) systemic clearance was 16.2 (22%) L/h. Temsirolimus exhibits a bi-exponential decline in whole blood concentrations and the mean half-lives of temsirolimus and sirolimus were 17.3 hr and 54.6 hr, respectively.
Drug-Transport Systems -P-glycoprotein Temsirolimus is a substrate of the efflux transporter P-glycoprotein (Pgp) in vitro . If Temsirolimus injection is administered with drugs that inhibit Pgp, increased concentrations of temsirolimus are likely and caution should be exercised. In vitro , temsirol… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Temsirolimus is an inhibitor of mTOR (mammalian target of rapamycin). Temsirolimus binds to an intracellular protein (FKBP-12), and the protein-drug complex inhibits the activity of mTOR that controls cell division. Inhibition of mTOR activity resulted in a G1 growth arrest in treated tumor cells.
When mTOR was inhibited, its ability to phosphorylate p70S6k and S6 ribosomal protein, which are downstream of mTOR in the PI3 kinase/AKT pathway was blocked. In in vitro studies using renal cell carcinoma cell lines, temsirolimus inhibited the activity of mTOR and resulted in reduced levels of the hypoxia-inducible factors HIF-1 and HIF-2 alpha, and the vascular endothelial growth factor.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Temsirolimus injection 25 mg/mL is available as “a clear, colorless to light yellow viscous solution and is supplied in single-dose vial of 25 mg/mL (NDC 68083-200-01)”. Diluent for Temsirolimus injection is available as “a clear, colorless to light yellow non aqueous solution and is supplied in single-dose vial of 2.2 mL (NDC 68083-201-01)”. A KIT of Temsirolimus injection, 25 mg/mL; Single carton containing both the vials (NDC 68083-202-01).
Each kit is supplied in a single carton containing one single-dose vial of 25 mg/mL of temsirolimus and one DILUENT vial which includes a deliverable volume of 1.8 mL, and must be stored at 2º to 8º C (36º–46º F) and Protect from light. Temsirolimus injection is a cytotoxic drug. Follow applicable special handling and disposal procedures.
📋 Description ▾
11 DESCRIPTION Temsirolimus, an inhibitor of mTOR, is an antineoplastic agent. Temsirolimus is a white to off-white powder with a molecular formula of C 56 H 87 NO 16 and a molecular weight of 1030.30. It is non-hygroscopic.
Temsirolimus is practically insoluble in water and soluble in alcohol. It has no ionizable functional groups, and its solubility is independent of pH. The chemical name of temsirolimus is (3 S ,6 R ,7 E ,9 R ,10 R ,12 R ,14 S ,15 E ,17 E ,19 E ,21 S ,23 S ,26 R ,27 R ,34a S )-9,10,12,13,14,21,22,23,24,25,26,27,32,33,34,34a-Hexadecahydro-9,27-dihydroxy-3-[(1 R )-2-[(1 S ,3 R ,4 R )-4-hydroxy-3-methoxycyclohexyl]-1-methylethyl]-10,21-dimethoxy-6,8,12,14,20,26-hexamethyl-23,27-epoxy-3 H -pyrido[2,1- c ][1,4]oxaazacyclohentriacontine-1,5,11,28,29(4 H ,6 H ,31 H )-pentone 4′-[2,2-bis(hydroxymethyl)propionate]; or Rapamycin, 42-[3-hydroxy-2-(hydroxymethyl)-2-methylpropanoate].
Temsirolimus injection, 25 mg/mL, is a clear, colorless to light yellow, non-aqueous, ethanolic, sterile solution. Temsirolimus injection requires two dilutions prior to intravenous infusion. Temsirolimus injection should be diluted only with the supplied DILUENT for Temsirolimus injection.
DILUENT for Temsirolimus injection is a sterile, non-aqueous solution that is supplied with Temsirolimus injection, as a kit. Temsirolimus injection, 25 mg/mL: Active ingredient: temsirolimus (25 mg/mL) Inactive ingredients: dehydrated alcohol (49.90 % v/v), butylated hydroxy anisole (0.0003 % w/v), butylated hydroxy toluene (0.002 % w/v), propylene glycol (50.3% w/v), and anhydrous citric acid (0.0025% w/v). DILUENT for Temsirolimus injection: Inactive ingredients: polysorbate 80 (40.0% w/v), polyethylene glycol 400 (42.8% w/v) and dehydrated alcohol (25.14% v/v).
After the Temsirolimus injection vial has been diluted with DILUENT for Temsirolimus injection, in accordance with the instructions in section 2.5, the solution contains 35.04 % alcohol. Temsirolimus injection and DILUENT for Temsirolimus injection are filled in clear glass vials with butyl rubber stoppers. Temsirolimus-SPL-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Allergic (Hypersensitivity/Infusion) Reactions Patients should be informed of the possibility of serious allergic reactions, including anaphylaxis (including life threatening and fatal reactions), despite premedication with antihistamines, and to immediately report any facial swelling or difficulty breathing [ see Warnings and Precautions (5.1) ]. Increased Blood Glucose Levels Patients are likely to experience increased blood glucose levels while taking Temsirolimus injection. This may result in the need for initiation of, or increase in the dose of, insulin and/or hypoglycemic agents.
Patients should be directed to report any excessive thirst or frequency of urination to their physician [see Warnings and Precautions (5.3)] . Infections Patients should be informed that they may be more susceptible to infections while being treated with Temsirolimus injection [see Warnings and Precautions (5.4)] . Interstitial Lung Disease Patients should be warned of the possibility of developing interstitial lung disease, a chronic inflammation of the lungs, which may rarely result in death [see Warnings and Precautions (5.5)] .
Patients, including those who are taking or have taken corticosteroids or immunosuppressive agents, should be directed to report promptly any new or worsening respiratory symptoms to their physician. Increased Blood Triglycerides and/or Cholesterol Patients are likely to experience elevated triglycerides and/or cholesterol during Temsirolimus injection treatment. This may require initiation of, or increase in the dose of, lipid-lowering agents [see Warnings and Precautions (5.6)] .
Bowel Perforation Patients should be warned of the possibility of bowel perforation. Patients should be directed to report promptly any new or worsening abdominal pain or blood in their stools [see Warnings and Precautions (5.7)] . Renal Failure Patients should be informed of the risk of renal failure [see Warnings and Precautions (5.8)] .
Wound Healing Complications Patients should be advised of the possibility of abnormal wound healing if they have surgery within a few weeks of initiating therapy or during therapy [see Warnings and Precautions (5.9)] . Intracerebral Bleeding Patients with CNS tumors and/or receiving anticoagulants should be informed of the increased risk of developing intracerebral bleeding (including fatal outcomes) while on Temsirolimus injection [see Warnings and Precautions (5.10)] . Proteinuria and Nephrotic Syndrome Advise patients that treatment with Temsirolimus injection may require monitoring for proteinuria and nephrotic syndrome and to contact their health care provider for signs and symptoms of nephrotic syndrome [see Warnings and Precautions (5.11)].
Medications that can interfere with Temsirolimus injection Some medicines can interfere with the breakdown or metabolism of Temsirolimus injection. In particular, patients should be directed to inform their physician if they are taking any of the following: Protease inhibitors, anti-epileptic medicines including carbamazepine, phenytoin, and barbiturates, St. John’s Wort, rifampicin, rifabutin, nefazodone or selective serotonin re-uptake inhibitors used to treat depression, antibiotics or antifungal medicines used to treat infections [see Warnings and Precautions (5.12)].
Vaccinations Patients should be advised that vaccinations may be less effective while being treated with Temsirolimus injection. In addition, the use of live vaccines, and close contact with those who have received live vaccines, while on Temsirolimus injection should be avoided [see Warnings and Precautions (5.14)]. Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential that Temsirolimus injection can cause fetal harm.
Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.15) and Use in Specific Populations (8.1)]. Advise females of reproductiv… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Contraception Females Temsirolimus injection can cause fetal harm when administered to a pregnant woman [see Use in Specific Population (8.1)] . Advise females of reproductive potential to use effective contraception during treatment with Temsirolimus injection and for 3 months after the last dose. Males Advise males with partners of reproductive potential to use effective contraception during treatment with Temsirolimus injection and for 3 months after the last dose [see Nonclinical Toxicology (13.1)].
Infertility Based on the findings in animal fertility studies, male and female fertility may be compromised by the treatment with Temsirolimus injection. It is not known if the effects on fertility in animal studies were reversible [see Nonclinical Toxicology (13.1)].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following administration of a single 25 mg dose of Temsirolimus injection in patients with cancer, mean temsirolimus C max in whole blood was 585 ng/mL (coefficient of variation, CV =14%), and mean AUC in blood was 1627 ng•h/mL (CV=26%). Typically C max occurred at the end of infusion. Over the dose range of 1 mg to 25 mg, temsirolimus exposure increased in a less than dose proportional manner while sirolimus exposure increased proportionally with dose.
Following a single 25 mg intravenous dose in patients with cancer, sirolimus AUC was 2.7-fold that of temsirolimus AUC, due principally to the longer half-life of sirolimus. Distribution Following a single 25 mg intravenous dose, mean steady-state volume of distribution of temsirolimus in whole blood of patients with cancer was 172 liters. Both temsirolimus and sirolimus are extensively partitioned into formed blood elements.
Metabolism Cytochrome P450 3A4 is the major isozyme responsible for the formation of five temsirolimus metabolites. Sirolimus, an active metabolite of temsirolimus, is the principal metabolite in humans following intravenous treatment. The remainder of the metabolites account for less than 10% of radioactivity in the plasma.
In human liver microsomes temsirolimus was an inhibitor of CYP2D6 and 3A4. However, there was no effect observed in vivo when temsirolimus was administered with desipramine (a CYP2D6 substrate), and no effect is anticipated with substrates of CYP3A4 metabolism. Elimination Elimination is primarily via the feces.
After a single IV dose of [ 14 C]-temsirolimus approximately 82% of total radioactivity was eliminated within 14 days, with 4.6% and 78% of the administered radioactivity recovered in the urine and feces, respectively. Following a single 25 mg dose of Temsirolimus injection in patients with cancer, temsirolimus mean (CV) systemic clearance was 16.2 (22%) L/h. Temsirolimus exhibits a bi-exponential decline in whole blood concentrations and the mean half-lives of temsirolimus and sirolimus were 17.3 hr and 54.6 hr, respectively.
Drug-Transport Systems -P-glycoprotein Temsirolimus is a substrate of the efflux transporter P-glycoprotein (Pgp) in vitro . If Temsirolimus injection is administered with drugs that inhibit Pgp, increased concentrations of temsirolimus are likely and caution should be exercised. In vitro , temsirolimus inhibited human Pgp (IC 50 value of 2μM).
If Temsirolimus injection is administered with drugs that are substrates of Pgp, increased concentrations of the substrate drug are likely and caution should be exercised. Effects of Age and Gender In population pharmacokinetic-based data analyses, no relationship was apparent between drug exposure and patient age or gender. Drug Interactions Effect of Temsirolimus on CYP2D6 or CYP3A The concentration of desipramine, a CYP2D6 substrate, was unaffected when 25 mg of temsirolimus was co-administered.
No clinically significant effect is anticipated when 25 mg of temsirolimus is co-administered with agents that are metabolized by CYP2D6 or CYP3A.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Effects on Electrocardiogram: There were no clinically relevant QT changes observed at the recommended dose for Temsirolimus injection. In a randomized, single-blinded, crossover study, 58 healthy subjects received Temsirolimus injection 25 mg, placebo, and a single oral dose of moxifloxacin 400 mg. A supratherapeutic Temsirolimus injection dose was not studied in this randomized QT trial.
The largest difference between the upper bound 2-sided 90% CI for the mean difference between Temsirolimus injection and placebo-corrected QT interval was less than 10 ms. In a different trial in 69 patients with a hematologic malignancy, Temsirolimus injection doses up to 175 mg were studied. No patient with a normal QTcF at baseline had an increase in QTcF >60 ms.
Additionally, there were no patients with a QTcF interval greater than 500 ms.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES A phase 3, multi-center, three-arm, randomized, open-label study was conducted in previously untreated patients with advanced renal cell carcinoma (clear cell and non-clear cell histologies). The objectives were to compare Overall Survival (OS), Progression-Free Survival (PFS), Objective Response Rate (ORR), and safety in patients receiving IFN-α to those receiving Temsirolimus injection or Temsirolimus injection plus IFN-α. Patients in this study had 3 or more of 6 pre-selected prognostic risk factors (less than one year from time of initial RCC diagnosis to randomization, Karnofsky performance status of 60 or 70, hemoglobin less than the lower limit of normal, corrected calcium of greater than 10 mg/dL, lactate dehydrogenase > 1.5 times the upper limit of normal, more than one metastatic organ site).
Patients were stratified for prior nephrectomy status within three geographic regions and were randomly assigned (1:1:1) to receive IFN-α alone (n=207), Temsirolimus injection alone (25 mg weekly; n=209), or the combination arm (n=210). The ITT population for this interim analysis included 626 patients. Demographics were comparable between the three treatment arms with regard to age, gender, and race.
The mean age of all groups was 59 years (range 23–86). Sixty-nine percent were male and 31% were female. The racial distribution for all groups was 91% White, 4% Black, 2% Asian, and 3% other.
Sixty-seven percent of patients had a history of prior nephrectomy. The median duration of treatment in the Temsirolimus injection arm was 17 weeks (range 1–126 weeks). The median duration of treatment on the IFN arm was 8 weeks (range 1–124 weeks).
There was a statistically significant improvement in OS (time from randomization to death) in the Temsirolimus injection 25 mg arm compared to IFN-α. The combination of Temsirolimus injection 15 mg and IFN-α did not result in a significant increase in overall survival when compared with IFN-α alone. Figure 1 is a Kaplan-Meier plot of OS in this study.
The evaluations of PFS (time from randomization to disease progression or death) and ORR, were based on blinded independent radiologic assessment of tumor response. Efficacy results are summarized in Table 4. Table 4-Summary of Efficacy Results of Temsirolimus injection vs.
IFN-α Parameter Temsirolimus injection n = 209 IFN-α n = 207 P-value a Hazard Ratio (95% CI) b Median Overall Survival Months (95% CI) 10.9 (8.6, 12.7) 7.3 (6.1, 8.8) 0.0078* 0.73 (0.58, 0.92) Median Progression-Free Survival Months (95% CI) 5.5 (3.9, 7.0) 3.1 (2.2, 3.8) 0.0001** 0.66 (0.53, 0.81) Overall Response Rate % (95% CI) 8.6 (4.8, 12.4) 4.8 (1.9, 7.8) 0.1232** C NA CI = confidence interval; NA = not applicable * A comparison is considered statistically significant if the p-value is <0.0159 (O'Brien-Fleming boundary at 446 deaths). ** Not adjusted for multiple comparisons. a Based on log-rank test stratified by prior nephrectomy and region. b Based on Cox proportional hazard model stratified by prior nephrectomy and region. c Based on Cochran-Mantel-Haenszel test stratified by prior nephrectomy and region.
Figure 1: Kaplan-Meier Curves for Overall Survival – Temsirolimus injection vs. IFN temsirolimus-spl-graph1
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with temsirolimus. However, sirolimus, the major metabolite of temsirolimus in humans, was carcinogenic in mice and rats. The following effects were reported in mice and/or rats in the carcinogenicity studies conducted with sirolimus: lymphoma, hepatocellular adenoma and carcinoma, and testicular adenoma.
Temsirolimus was not genotoxic in a battery of in vitro (bacterial reverse mutation in Salmonella typhimurium and Escherichia coli, forward mutation in mouse lymphoma cells, and chromosome aberrations in Chinese hamster ovary cells) and in vivo (mouse micronucleus) assays. In a fertility study in male rats, decreased number of pregnancies, decreased sperm concentration and motility, decreased reproductive organ weights, and testicular tubular degeneration were observed. These effects were observed at oral temsirolimus doses ≥3 mg/m2/day (approximately 0.2-fold the human recommended intravenous dose).
Fertility was absent at 30 mg/m2/day. In a fertility study in female rats, an increased incidence of pre-and post-implantation losses occurred at oral doses ≥ 4.2 mg/m2/day (approximately 0.3-fold the human recommended intravenous dose), resulting in decreased numbers of live fetuses.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with temsirolimus. However, sirolimus, the major metabolite of temsirolimus in humans, was carcinogenic in mice and rats. The following effects were reported in mice and/or rats in the carcinogenicity studies conducted with sirolimus: lymphoma, hepatocellular adenoma and carcinoma, and testicular adenoma.
Temsirolimus was not genotoxic in a battery of in vitro (bacterial reverse mutation in Salmonella typhimurium and Escherichia coli, forward mutation in mouse lymphoma cells, and chromosome aberrations in Chinese hamster ovary cells) and in vivo (mouse micronucleus) assays. In a fertility study in male rats, decreased number of pregnancies, decreased sperm concentration and motility, decreased reproductive organ weights, and testicular tubular degeneration were observed. These effects were observed at oral temsirolimus doses ≥3 mg/m2/day (approximately 0.2-fold the human recommended intravenous dose).
Fertility was absent at 30 mg/m2/day. In a fertility study in female rats, an increased incidence of pre-and post-implantation losses occurred at oral doses ≥ 4.2 mg/m2/day (approximately 0.3-fold the human recommended intravenous dose), resulting in decreased numbers of live fetuses.
📚 References ▾
15 REFERENCES 1. OSHA Hazardous Drugs. OSHA. https://www.osha.gov/SLTC/hazardousdrugs/index.html.
📄 Recent Major Changes ▾
Warnings and Precautions, Proteinuria and Nephrotic Syndrome (5.11) 3/2018 Warnings and Precautions, Embryo-Fetal Toxicity (5.15) 3/2018
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - 25 mg/mL Per Vial* Temsirolimus Injection, 25 mg/mL Per Vial* *each vial contains 0.2 mL overfill NDC 68083-200-01 MUST BE DILUTED 10 mg/mL after initial dilution Single Dose Vial - Refrigerate Rx only PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - 2.2 mL Vial Label NDC 68083-201-01 DILUENT for Temsirolimus Injection 2.2 mL Not for direct administration Only for dilution of Temsirolimus Injection Vial. Single Dose Vial - Refrigerate PACKAGE LABEL - PRINCIPAL DISPLAY PANEL - 25 mg/mL Per Vial* NDC 68083-202-01 Rx only Temsirolimus Injection 25 mg/mL Per Vial* *each Single dose vial contains 0.2 mL overfill CONCENTRATED - Requires two dilutions before administration 10 mg/mL after initial dilution For intravenous infusion only *Each carton contains: 1 Single dose vial Temsirolimus Injection, 25 mg/mL 1 Single dose vial Diluent for Temsirolimus Injection Refrigerate Temsirolimus-SPL-product-label1 Temsirolimus-SPL-diluent-label1 Temsirolimus-SPL-Carton-Label
Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |