
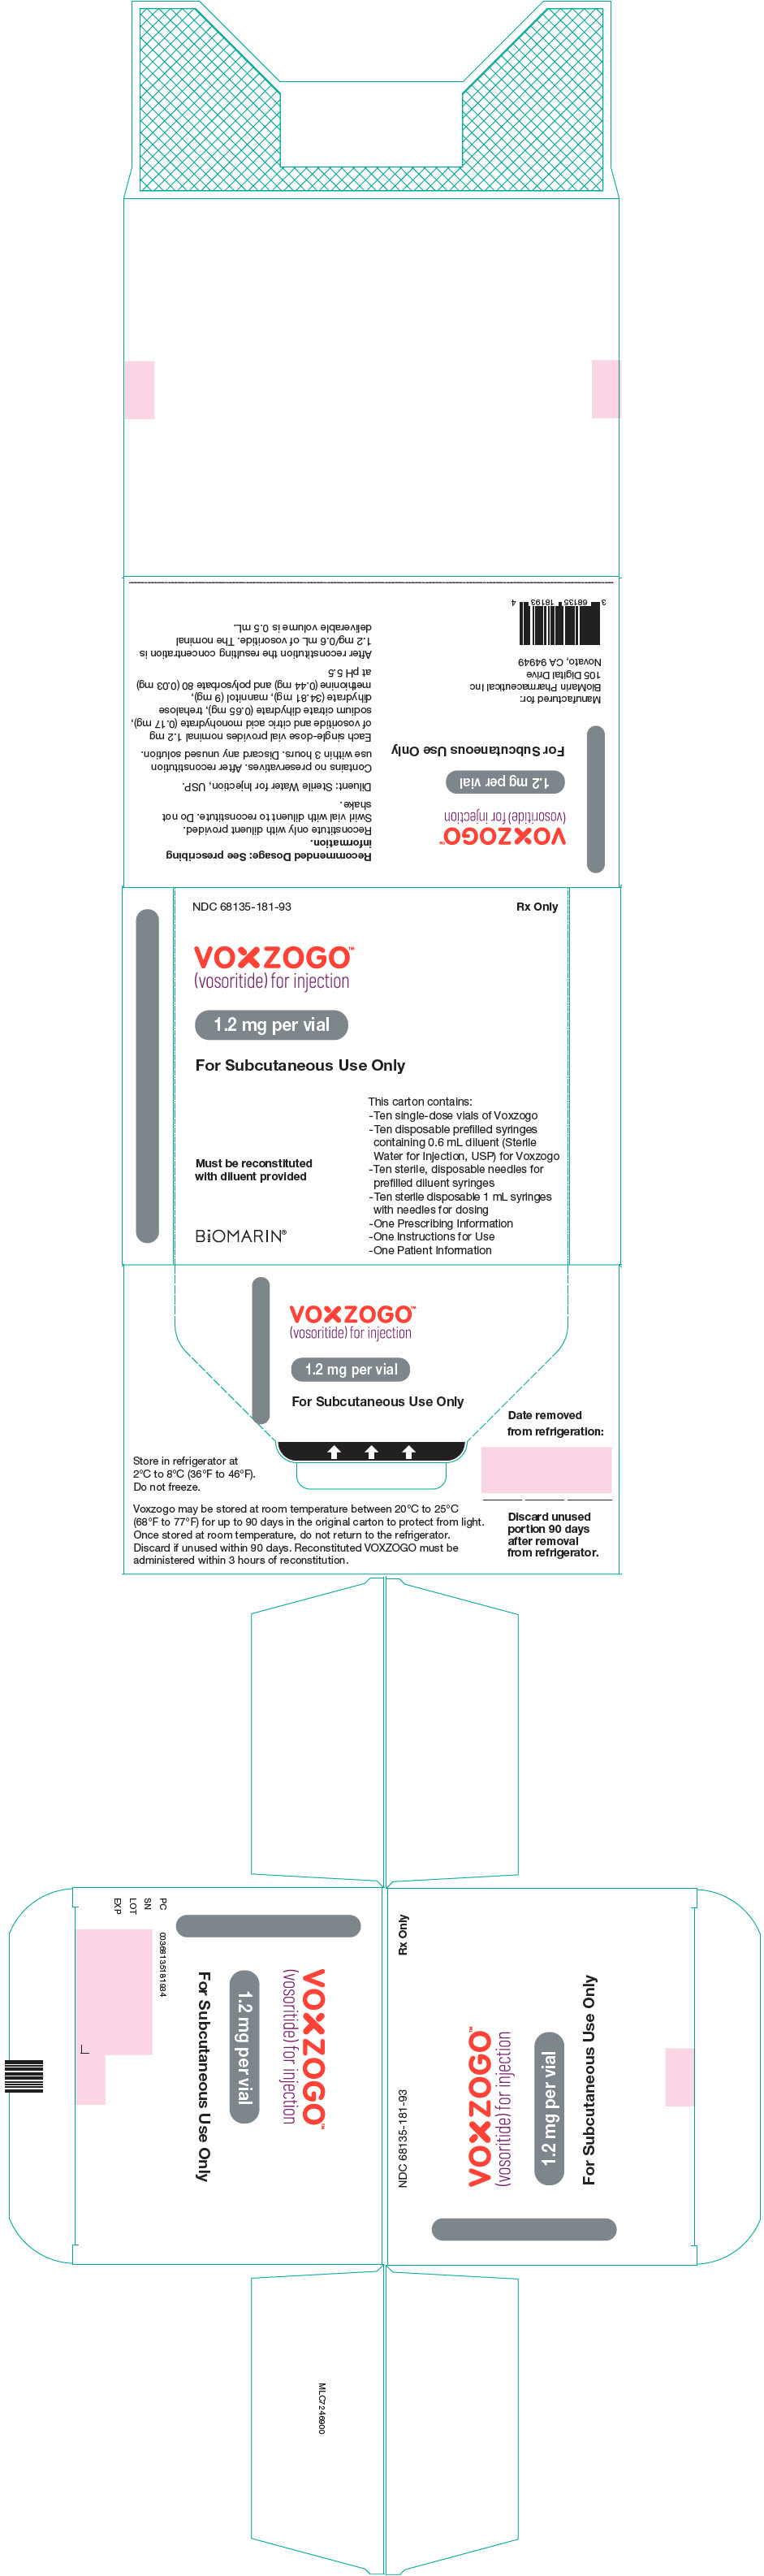
VOXZOGO 1.2mg vosoritide Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the C-type Natriuretic Peptide Analog class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- VOXZOGO works by releasing the biological brake that achondroplasia puts on your child's bone growth. In clinical trials, children using it grew faster than those on placebo. That...
- What exactly does VOXZOGO do, and will it make my child grow to a normal height?
- Your care team will walk you through the full process before you do it at home — so don't worry, you won't be sent home to figure it out alone. Each day you'll mix the powder with...
- How do I give this injection at home, and does it hurt my child?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1,069.88 | — |
| Medicare drug plans payPart D · Q2 2026 | $1,121.67 | — |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| VOXZOGO 1.2mgthis 68135-0181-93 | BioMarin | 1 kit | — | — | FDA listed | — |
| VOXZOGO 0.4mg 68135-0082-36 | BioMarin | 1 kit | — | — | FDA listed | — |
| VOXZOGO 0.56mg 68135-0119-66 | BioMarin | 1 kit | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11911446 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 11911446 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 11911446 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 11590204 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 11590204 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 11590204 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 12233106 ↗ | Method of use | U-3927 | Jul 11, 2042 |
| US 12233106 ↗ | Method of use | U-3927 | Jul 11, 2042 |
| US 12233106 ↗ | Method of use | U-3927 | Jul 11, 2042 |
| US 12514906 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 12514906 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 12514906 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US RE48267 ↗ | Method of use | U-3927 | May 20, 2030 |
| US RE48267 ↗ | Method of use | U-3927 | May 20, 2030 |
| US RE48267 ↗ | Method of use | U-3927 | May 20, 2030 |
| US 8198242 ↗ | Drug substance | U-3927 | Jun 11, 2035 |
| US 8198242 ↗ | Drug substance | U-3927 | Jun 11, 2035 |
| US 8198242 ↗ | Drug substance | U-3927 | Jun 11, 2035 |
| US 10646550 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 10646550 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 10646550 ↗ | Method of use | U-3927 | Aug 1, 2036 |
| US 9907834 ↗ | Drug product | — | Aug 1, 2036 |
| US 9907834 ↗ | Drug product | — | Aug 1, 2036 |
| US 9907834 ↗ | Drug product | — | Aug 1, 2036 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Nov 19, 2026 |
| NPP | New Patient Population | Oct 20, 2026 |
| ODE-387 | Orphan Drug Exclusivity (7-year) | Nov 19, 2028 |
| ODE-449 | Orphan Drug Exclusivity (7-year) | Oct 20, 2030 |
| NCE | New Chemical Entity (5-year) | Nov 19, 2026 |
| NPP | New Patient Population | Oct 20, 2026 |
| ODE-387 | Orphan Drug Exclusivity (7-year) | Nov 19, 2028 |
| ODE-449 | Orphan Drug Exclusivity (7-year) | Oct 20, 2030 |
| NCE | New Chemical Entity (5-year) | Nov 19, 2026 |
| NPP | New Patient Population | Oct 20, 2026 |
| ODE-387 | Orphan Drug Exclusivity (7-year) | Nov 19, 2028 |
| ODE-449 | Orphan Drug Exclusivity (7-year) | Oct 20, 2030 |
Is there a generic version of VOXZOGO 1.2 MG VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68135-0181-93 You're viewing this | 1 KIT in 1 CARTON (68135-181-93) * 10 VIAL, SINGLE-DOSE in 1 CARTON (68135-130-92) / .6 mL in 1 VIAL, SINGLE-DOSE * 10 INJECTION, SOLUTION in 1 CARTON (68135-158-17) | 2021-11-19 | Active |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE VOXZOGO is indicated to increase linear growth in pediatric patients with achondroplasia with open epiphyses. This indication is approved under accelerated approval based on an improvement in annualized growth velocity [see Clinical Studies (14) ] . Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trial(s).
VOXZOGO is a C type natriuretic peptide (CNP) analog indicated to increase linear growth in pediatric patients with achondroplasia with open epiphyses. This indication is approved under accelerated approval based on an improvement in annualized growth velocity. Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trial(s).
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Ensure adequate food and fluid intake prior to administration. ( 2.1 ) Recommended dosage is based on patient's actual body weight. Administer VOXZOGO subcutaneously once daily.
( 2.2 ) Reconstitute prior to use. Injection volume is based on both patient's weight and concentration of reconstituted VOXZOGO. ( 2.2 ) Monitor growth and adjust dosage according to actual body weight.
Permanently discontinue upon closure of epiphyses. ( 2.3 ) See full prescribing information for reconstitution, dilution, and administration instructions. ( 2.4 )
2.1Important Instructions Prior to Administration of VOXZOGO To reduce the risk of low blood pressure and its associated signs and symptoms, instruct the caregiver and patient that the patient should [see Warnings and Precautions (5.1) ] : Have adequate food intake prior to VOXZOGO administration. Drink approximately 240 to 300 mL of fluid in the hour prior to VOXZOGO administration.
2.2Recommended Dosage and Administration The recommended dosage of VOXZOGO is based on the patient's actual body weight (see Table 1 ). VOXZOGO is administered by subcutaneous injection once daily [see Dosage and Administration (2.4) ] . Inject VOXZOGO at approximately the same time each day, if possible.
The volume of VOXZOGO to be administered (injection volume) is based on the patient's actual body weight and the concentration of reconstituted VOXZOGO (0.8 mg/mL or 2 mg/mL) (see Table 1 ). VOXZOGO must be reconstituted prior to use [see Dosage and Administration (2.4) ] . Table 1: Recommended VOXZOGO Daily Dosage and Injection Volume Actual Body Weight Intermediate body weights that fall within these weight bands should be rounded to the nearest whole number.
Dose Injection Volume Vial Strength for Reconstitution The concentration of vosoritide in reconstituted 0.4 mg vial and 0.56 mg vial is 0.8 mg/mL. The concentration of vosoritide in reconstituted 1.2 mg vial is 2 mg/mL. 3 kg 0.096 mg 0.12 mL 0.4 mg 4 kg 0.12 mg 0.15 mL 0.4 mg 5 kg 0.16 mg 0.2 mL 0.4 mg 6 to 7 kg 0.2 mg 0.25 mL 0.4 mg 8 to 11 kg 0.24 mg 0.3 mL 0.4 mg 12 to 16 kg 0.28 mg 0.35 mL 0.56 mg 17 to 21 kg 0.32 mg 0.4 mL 0.56 mg 22 to 32 kg 0.4 mg 0.5 mL 0.56 mg 33 to 43 kg 0.5 mg 0.25 mL 1.2 mg 44 to 59 kg 0.6 mg 0.3 mL 1.2 mg 60 to 89 kg 0.7 mg 0.35 mL 1.2 mg ≥ 90 kg 0.8 mg 0.4 mL 1.2 mg Missed dose If a dose of VOXZOGO is missed, it can be administered within 12 hours of the scheduled time of administration.
Beyond 12 hours, skip the missed dose and administer the next daily dose according to the usual dosing schedule.
2.3Growth Monitoring Monitor and assess patient body weight, growth, and physical development regularly every 3 to 6 months. Adjust the dosage according to the patient's actual body weight [see Dosage and Administration (2.2) ] . Permanently discontinue VOXZOGO upon confirmation of no further growth potential, indicated by closure of epiphyses.
2.4Preparation and Administration Reconstitute VOXZOGO before administration using the provided diluent syringe containing Sterile Water for Injection, USP (see Reconstitution Instructions below). Caregivers may inject VOXZOGO subcutaneously after proper training by a healthcare professional on the preparation and administration of VOXZOGO [see Instructions for Use ]. Reconstitution Instructions Select the correct VOXZOGO vial strength (co-packaged with prefilled syringe with Sterile Water for Injection diluent) based on the patient's actual body weight [see Dosage and Administration (2.2) ] .
Remove VOXZOGO vial and prefilled diluent syringe from the refrigerator and allow the vial and prefilled diluent syringe to reach room temperature before reconstituting VOXZOGO. Attach the diluent needle provided with ancillary supplies to the diluent prefilled syringe. Inject the entire diluent prefilled syringe volume into the vial (see Table 2 ).
Gently swirl the diluent in the vial until the white powder is completely dissolved. Do not shake. Parenteral drug product…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For Injection: 0.4 mg, 0.56 mg, or 1.2 mg of vosoritide as a white to yellow lyophilized powder in a single-dose vial for reconstitution. For injection: 0.4 mg, 0.56 mg, or 1.2 mg of vosoritide as a lyophilized powder in a single-dose vial for reconstitution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of Low Blood Pressure : Transient decreases in blood pressure have been reported. Instruct patients to be well-hydrated and have adequate food intake prior to administration of VOXZOGO ( 5.1 )
5.1Risk of Low Blood Pressure Transient decreases in blood pressure were observed in clinical studies of VOXZOGO. Subjects with significant cardiac or vascular disease and patients on anti-hypertensive medicinal products were excluded from participation in VOXZOGO clinical trials. To reduce the risk of a decrease in blood pressure and associated symptoms (dizziness, fatigue and/or nausea), instruct patients to be well hydrated and have adequate food intake prior to administration of VOXZOGO [see Dosage and Administration (2.1) and Adverse Reactions (6.1) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Risk of Low Blood Pressure [see Warnings and Precautions (5.1) ] Most common adverse reactions (>10%) are injection site erythema, injection site swelling, rash, vomiting, injection site urticaria, arthralgia, decreased blood pressure, and gastroenteritis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact BioMarin Pharmaceutical Inc. at 1-866-906-6100, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Pediatric Patients 5 Years of Age and Older VOXZOGO was studied in a 52-week, randomized, double-blind, placebo-controlled trial in 121 subjects with achondroplasia (Study 1) [see Clinical Studies (14) ] . The subjects' ages ranged from 5.1 to 14.9 years with a mean of 8.7 years.
Sixty four (53%) subjects were male and 57 (47%) were female. Overall, 86 (71%) subjects were White, 23 (19%) were Asian, 5 (4%) were Black or African American, and 7 (6%) were classified as "multiple" race. The demographic and baseline characteristics were balanced between treatment groups.
The subjects received either VOXZOGO 15 mcg/kg, or placebo administered subcutaneously once daily. Table 3 shows adverse reactions that occurred in ≥5% of patients treated with VOXZOGO and at a percentage greater than placebo. Table 3: Adverse Reactions that Occurred in ≥5% of Patients Treated with VOXZOGO and at a Percentage Greater than Placebo in Study 1 Includes adverse reactions occurring more frequently in the vosoritide arm and with a risk difference of ≥5% (i.e., difference of >2 subjects) between treatment arms Adverse Reaction Placebo (N=61) n (%) VOXZOGO (N=60) n (%) Abbreviations: N, total number of subjects in the treatment arm; n, number of subjects with the adverse reaction; %, percent of subjects with the adverse reaction.
Injection site erythema 42 (69%) 45 (75%) Injection site swelling 22 (36%) 37 (62%) Vomiting 12 (20%) 16 (27%) Injection site urticaria 6 (10%) 15 (25%) Arthralgia 4 (7%) 9 (15%) Decreased blood pressure 3 (5%) 8 (13%) Gastroenteritis Includes the preferred terms: gastroenteritis and gastroenteritis, viral 5 (8%) 8 (13%) Diarrhea 2 (3%) 6 (10%) Dizziness Includes the preferred terms: dizziness, presyncope, procedural dizziness, vertigo 2 (3%) 6 (10%) Ear pain 3 (5%) 6 (10%) Influenza 3 (5%) 6 (10%) Fatigue Includes the preferred terms: fatigue, lethargy, malaise 2 (3%) 5 (8%) Seasonal allergy 1 (2%) 4 (7%) Dry skin 0 3 (5%) Laboratory Abnormalities Increase in Alkaline Phosphatase More VOXZOGO-treated patients had an increase in alkaline phosphatase levels during the study compared to placebo (17% vs 7%).
Discussion of Selected Adverse Reactions Decreased blood pressure Eight (13%) of 60 subjects treated with VOXZOGO had a total of 11 events of transient decrease in blood pressure compared to 3 (5%) of 61 subjects on placebo, identified predominantly during periods of frequent monitoring at clinical visits after dosing over a 52-week treatment period. The median time to onset from injection was 31 (18 to 120) minutes with resolution within 31 (5 to 90) minutes in VOXZOGO-treated subjects. Two out of 60 (3%) VOXZOGO-treated subjects each had one symptomatic episode of decreased blood pressure with vomiting and/or dizziness compared to 0 of 61 (0%) subjects on placebo.
Injection site reactions Injection site reactions occurred in 51 (85%) subjects receiving VOXZOGO and 50 (82%) subjects receiving placebo over a 52 week period of treatment. Injection site reactions included the preferred terms injection site erythema, injection site reaction, injection site swelling, injection site urticaria, injection site pain, injection site…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal Impairment: Not recommended in patients with eGFR < 60 mL/min/1.73 m 2 . ( 8.6 )
8.1Pregnancy Risk Summary There are no available data on vosoritide use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, there was no evidence of embryo-fetal toxicity or congenital malformations when pregnant rats and rabbits were administered vosoritide subcutaneously at doses equivalent to 14-times and 200-times, respectively, the exposure at the maximum recommended human dose (MRHD) (see Data ). The estimated background risk of major birth defects for the indicated population is higher than the general population.
The estimated background risk of miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data In an embryofetal developmental toxicity study in rats, vosoritide was administered at 90, 270, 540 mcg/kg once daily by subcutaneous injection during the period of major organogenesis from gestation day (GD) 6 – 17. There were no effects on maternal animals or on embryofetal development at the highest dose administered (14-times the exposure at the MRHD). In an embryofetal developmental toxicity study in rabbits, vosoritide was administered at 45, 135, 240 mcg/kg once daily by subcutaneous injection during the period of major organogenesis (GD 7 – 19).
No effects were observed in maternal animals or on embryofetal development at the highest dose administered (200-times the exposure at the MRHD). In a pre- and postnatal toxicity study in rats, vosoritide was administered at 90, 270, and 540 mcg/kg once daily by subcutaneous injection during the period of major organogenesis and continuing to weaning (GD 6 through postpartum day 20). There were no effects on maternal animals, including maintenance of pregnancy, parturition, or care of offspring, and no effects were noted on offspring growth and development or ability to reproduce at the highest dose (14-times the exposure at the MRHD).
8.2Lactation Risk Summary There is no information regarding the presence of vosoritide in human milk, the effects on the breastfed infant, or the effects on milk production. Vosoritide is present in rat milk. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for VOXZOGO and any potential adverse effects on the breastfed child from VOXZOGO or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of VOXZOGO have been established in pediatric patients for the improvement in linear growth in patients with achondroplasia with open epiphyses. Use of VOXZOGO for this indication is supported by evidence from an adequate and well-controlled study in 121 pediatric patients aged 5 to 15 years with achondroplasia, pharmacokinetic data in pediatric patients aged 4.5 months to 15 years, and additional safety data in pediatric patients aged 4.4 months to <5 years [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14) ] .
8.6Renal Impairment The effect of renal impairment on the pharmacokinetics of VOXZOGO has not been evaluated. No dosage adjustment is needed for patients with eGFR ≥ 60 mL/min/1.73 m 2 . VOXZOGO is not recommended for patients with eGFR < 60 mL/min/1.73 m 2 .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on vosoritide use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, there was no evidence of embryo-fetal toxicity or congenital malformations when pregnant rats and rabbits were administered vosoritide subcutaneously at doses equivalent to 14-times and 200-times, respectively, the exposure at the maximum recommended human dose (MRHD) (see Data ). The estimated background risk of major birth defects for the indicated population is higher than the general population.
The estimated background risk of miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data In an embryofetal developmental toxicity study in rats, vosoritide was administered at 90, 270, 540 mcg/kg once daily by subcutaneous injection during the period of major organogenesis from gestation day (GD) 6 – 17. There were no effects on maternal animals or on embryofetal development at the highest dose administered (14-times the exposure at the MRHD). In an embryofetal developmental toxicity study in rabbits, vosoritide was administered at 45, 135, 240 mcg/kg once daily by subcutaneous injection during the period of major organogenesis (GD 7 – 19).
No effects were observed in maternal animals or on embryofetal development at the highest dose administered (200-times the exposure at the MRHD). In a pre- and postnatal toxicity study in rats, vosoritide was administered at 90, 270, and 540 mcg/kg once daily by subcutaneous injection during the period of major organogenesis and continuing to weaning (GD 6 through postpartum day 20). There were no effects on maternal animals, including maintenance of pregnancy, parturition, or care of offspring, and no effects were noted on offspring growth and development or ability to reproduce at the highest dose (14-times the exposure at the MRHD).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of VOXZOGO have been established in pediatric patients for the improvement in linear growth in patients with achondroplasia with open epiphyses. Use of VOXZOGO for this indication is supported by evidence from an adequate and well-controlled study in 121 pediatric patients aged 5 to 15 years with achondroplasia, pharmacokinetic data in pediatric patients aged 4.5 months to 15 years, and additional safety data in pediatric patients aged 4.4 months to <5 years [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action In patients with achondroplasia, endochondral bone growth is negatively regulated due to a gain of function mutation in fibroblast growth factor receptor 3 ( FGFR3 ). Binding of vosoritide to natriuretic peptide receptor-B (NPR-B) antagonizes FGFR3 downstream signaling by inhibiting the extracellular signal-regulated kinases 1 and 2 (ERK1/2) in the mitogen-activated protein kinase (MAPK) pathway at the level of rapidly accelerating fibrosarcoma serine/threonine protein kinase (RAF-1). As a result, vosoritide, like CNP, acts as a positive regulator of endochondral bone growth as it promotes chondrocyte proliferation and differentiation.
In animal models with open growth plates, vosoritide administration resulted in the promotion of chondrocyte proliferation and differentiation that led to a widening of the growth plate and subsequent increase in skeletal growth. In the mouse models of FGFR3-related chondrodysplasia, a partial or complete normalization of the dwarfism phenotype was observed.
12.2Pharmacodynamics NPR-B Binding Activity Biomarker and Bone Metabolism Biomarker An increase in urinary cyclic guanosine monophosphate (cGMP) concentrations from pre-dose baseline were observed within the first four hours post-dose, with a maximum level at 2 hours post-dose, after VOXZOGO administration to pediatric patients with achondroplasia. Daily administration of VOXZOGO also led to the increase from baseline in serum collagen type X marker (CXM), an endochondral ossification biomarker and remains elevated beyond 24 months.
In subjects aged 5 - 14 years old at screening, exposure-response analyses showed that vosoritide activity measured by urinary cGMP was near saturation at the dose of 15 mcg/kg once daily, while maximal increase in growth plate activity indicated by CXM was achieved at this dose. Cardiac Electrophysiology At the maximum approved recommended dose, VOXZOGO does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics The area under the concentration-time curve (AUC) and peak concentration (C max ) of vosoritide increased greater than proportionally following subcutaneous administration to pediatric subjects with achondroplasia in the dose range of 7.5 to 30.0 mcg/kg. The pharmacokinetics of vosoritide were evaluated in 58 subjects aged 5 to 13 years with achondroplasia who received subcutaneous injections of vosoritide 15 mcg/kg once daily for 52 weeks. The mean (± SD) C max and area under the concentration-time curve from time zero to the last measurable concentration (AUC 0-t ) observed across 52 weeks of treatment ranged from 4.71 (± 2.32) to 7.18 (± 9.65) ng/mL, and 161 (± 98.1) to 290 (± 235) ng-min/mL, respectively.
No drug accumulation was observed following 15 mcg/kg once daily dosing. The exposure of vosoritide increased with the duration of treatment. The mean AUC 0-t at week 52 increased approximately 20% compared to that at day 1.
Absorption Absolute bioavailability for vosoritide following subcutaneous injection was not determined. Vosoritide was absorbed with a median T max of 15 minutes after dosing. Distribution The mean (± SD) apparent volume of distribution of vosoritide across 52 weeks of subcutaneous administration of VOXZOGO 15 mcg/kg once daily ranged from 2880 (± 2450) to 3020 (± 1980) mL/kg.
Elimination The mean (± SD) apparent clearance of vosoritide across 52 weeks of subcutaneous administration of VOXZOGO 15 mcg/kg once daily ranged from 79.4 (± 53.0) to 104 (± 98.8) mL/min/kg. The mean (± SD) half-life ranged from 21.0 (± 4.7) to 27.9 (± 9.9) minutes. Metabolism The metabolism of vosoritide is expected to occur via catabolic pathways with degradation into small peptide fragments and amino acids.
Specific Populations No clinically significant differences in the vosoritide pharmacokinetics were observed based on age (0.4 to 15 years), sex or race. The effect of hepatic or renal impairment on the pharmacokinetics…
🧬 Mechanism of Action ▾
12.1Mechanism of Action In patients with achondroplasia, endochondral bone growth is negatively regulated due to a gain of function mutation in fibroblast growth factor receptor 3 ( FGFR3 ). Binding of vosoritide to natriuretic peptide receptor-B (NPR-B) antagonizes FGFR3 downstream signaling by inhibiting the extracellular signal-regulated kinases 1 and 2 (ERK1/2) in the mitogen-activated protein kinase (MAPK) pathway at the level of rapidly accelerating fibrosarcoma serine/threonine protein kinase (RAF-1). As a result, vosoritide, like CNP, acts as a positive regulator of endochondral bone growth as it promotes chondrocyte proliferation and differentiation.
In animal models with open growth plates, vosoritide administration resulted in the promotion of chondrocyte proliferation and differentiation that led to a widening of the growth plate and subsequent increase in skeletal growth. In the mouse models of FGFR3-related chondrodysplasia, a partial or complete normalization of the dwarfism phenotype was observed.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied VOXZOGO for injection is a white to yellow lyophilized powder for reconstitution and is provided as a co-pack which includes ten: Sterile, single-dose 2 mL glass vials containing VOXZOGO Diluent (Sterile Water for Injection, USP) in a single-dose prefilled syringe Diluent transfer needles (23 gauge) Single-dose administration syringes (30 gauge) both with needle retraction safety devices Strength (mg) Diluent (mL) Co-pack NDC Number Flip Cap Color 0.4
0.5NDC 68135-082-36 White 0.56
0.7NDC 68135-119-66 Magenta 1.2
0.6NDC 68135-181-93 Grey The following items to be obtained separately; alcohol aseptic wipes, gauze, bandages and sharps container. Storage Refrigerate VOXZOGO vials and prefilled diluent syringes at 2°C to 8°C (36°F to 46°F). Do not freeze.
VOXZOGO can be stored at room temperature 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) for 90 days. Do not return VOXZOGO to the refrigerator once stored at room temperature. After reconstitution, VOXZOGO can be held in the vial at room temperature 20°C to 25°C (68°F to 77°F) for a maximum of 3 hours [see Dosage and Administration (2.4) ] .
Record the starting date of room-temperature storage clearly on the unopened product carton. Do not use beyond expiration date on the label. Store in the original package to protect from light.
Handling Reconstituted VOXZOGO must be administered within 3 hours of reconstitution [see Dosage and Administration (2.4) ] .
📦 Storage and Handling ▾
Storage Refrigerate VOXZOGO vials and prefilled diluent syringes at 2°C to 8°C (36°F to 46°F). Do not freeze. VOXZOGO can be stored at room temperature 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) for 90 days.
Do not return VOXZOGO to the refrigerator once stored at room temperature. After reconstitution, VOXZOGO can be held in the vial at room temperature 20°C to 25°C (68°F to 77°F) for a maximum of 3 hours [see Dosage and Administration (2.4) ] . Record the starting date of room-temperature storage clearly on the unopened product carton.
Do not use beyond expiration date on the label. Store in the original package to protect from light.
📋 Description ▾
11 DESCRIPTION VOXZOGO contains vosoritide, a human C type natriuretic peptide (CNP) analog. Vosoritide is a 39 amino acid peptide. Its amino acid sequence includes the 37 C terminal amino acids of the human CNP53 sequence plus Pro Gly on the N terminus to convey resistance to neutral endopeptidase (NEP) degradation.
Vosoritide is manufactured from Escherichia coli using recombinant DNA technology. Vosoritide has a chemical formula of C 176 H 290 N 56 O 51 S 3 with a molecular weight of 4.1 kDa. Vosoritide has the structural formula shown in Figure 1.
Figure 1 VOXZOGO (vosoritide) for injection, is a sterile, preservative-free white-to-yellow lyophilized powder, for subcutaneous administration after reconstitution with Sterile Water for Injection, USP. VOXZOGO is provided as a single-dose vial containing 0.4 mg, 0.56 mg, or 1.2 mg of vosoritide per vial. A pre-filled syringe containing Sterile Water for Injection, USP for use as a diluent is also provided.
The contents of each single dose vial are summarized by strength in Table 4. The product contains no preservative. Table 4: Contents of VOXZOGO Strength Inactive Ingredients per Vial Trehalose dihydrate and D-Mannitol are used as isotonic agent.
Citric acid monohydrate and sodium citrate dihydrate are used as buffering agent. VOXZOGO 0.4 mg Citric acid monohydrate (0.14 mg), mannitol (7.5 mg), methionine (0.36 mg), polysorbate 80 (0.025 mg), sodium citrate dihydrate (0.54 mg) and trehalose dihydrate (29.01 mg). After reconstitution with 0.5 mL Sterile Water for Injection USP, the resulting concentration is 0.4 mg/0.5 mL of vosoritide and the nominal deliverable volume is 0.4 mL.
VOXZOGO 0.56 mg Citric acid monohydrate (0.20 mg), mannitol (10.50 mg), methionine (0.51 mg), polysorbate 80 (0.035 mg), sodium citrate dihydrate (0.76 mg) and trehalose dihydrate (40.61 mg). After reconstitution with 0.7 mL Sterile Water for Injection USP, the resulting concentration is 0.56 mg/0.7 mL of vosoritide and the nominal deliverable volume is 0.6 mL. VOXZOGO 1.2 mg Citric acid monohydrate (0.17 mg), mannitol (9 mg), methionine (0.44 mg), polysorbate 80 (0.030 mg), sodium citrate dihydrate (0.65 mg) and trehalose dihydrate (34.81 mg).
After reconstitution with 0.6 mL Sterile Water for Injection USP, the resulting concentration is 1.2 mg/0.6 mL of vosoritide and the nominal deliverable volume is 0.5 mL. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and caregiver to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Preparation and Administration Instruct caregivers on proper preparation and administration of VOXZOGO. Ensure caregivers have demonstrated the ability to perform a subcutaneous injection [see Dosage and Administration (2.4) ] .
Instruct caregivers in the technique of proper syringe and needle disposal, and advise them not to reuse these items. Instruct caregivers to dispose needles and syringes in a puncture-resistant container. Risk of Low Blood Pressure Inform caregivers and patients that VOXZOGO may lower blood pressure after administration.
Instruct caregivers and patients that prior to VOXZOGO administration, the patient should have adequate food intake and within the hour prior to administration, the patient should drink approximately 8-10 ounces (240-300 mL) of fluid [see Dosage and Administration (2.1) and Warnings and Precautions (5.1) ] .