
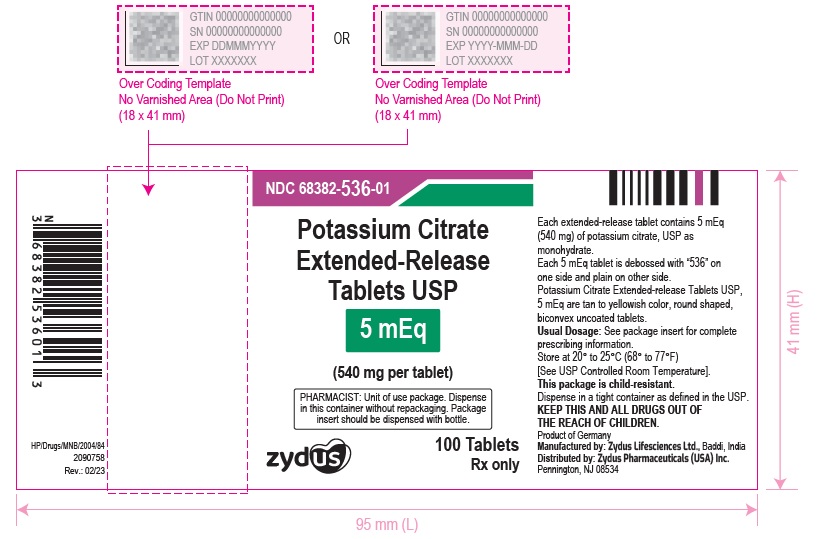
Potassium Citrate 10 meq Tablet, Extended Release, 1,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Potassium class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Great question. Potassium citrate works in two main ways. First, it increases the amount of citrate in your urine — citrate acts like a natural stone-fighter by grabbing onto calci...
- What exactly is potassium citrate doing to stop my kidney stones?
- Yes, it really does matter. You should take your dose with meals or within 30 minutes after eating — or with a bedtime snack if you have a dose then. Taking it on an empty stomach...
- Do I have to take this with food? Does it really matter?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Potassium Citrate (prescription drug) — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2772 | $277.20 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Potassium Citrate 10 meq 00245-0071-11 | Upsher-Smith | 100 tablets | $0.180 | AB | Availability likely | — |
| Potassium Citrate 10 meq 00591-2729-01 | Actavis | 100 tablets | $0.180 | — | Availability likely | — |
| Potassium Citrate 1080 mg 16571-0865-01 | Rising | 100 tablets | $0.180 | AB | Availability likely | — |
| Potassium Citrate 10 meq 31722-0130-01 | Camber | 100 tablets | $0.180 | AB | Availability likely | — |
| Potassium Citrate Extended Release 10 meq 42543-0407-01 | Strides | 100 tablets | $0.180 | AB | Availability likely | — |
| Potassium Citrate 10 meq 44523-0410-01 | Biocomp | 100 tablets | $0.180 | AB | Availability likely | — |
| Potassium Citrate 10 meq 62559-0291-01 | ANI | 100 tablets | $0.180 | AB | Availability likely | — |
| Potassium Citrate 10 meq 68084-0850-32 | American | 1 tablet | $0.180 | AB | Availability likely | — |
| Urocit-K 10 meq 00178-0610-01 | Mission | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 51407-0450-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 63629-1966-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 63629-8759-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 65841-0537-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meqthis 68382-0537-10 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 70518-3160-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 70518-4477-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate Extended Release 10 meq 71335-1706-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 71335-1967-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Potassium Citrate Extended Release 10 meq 71335-2871-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 72162-1758-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 72162-2120-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate Extended Release 10 meq 72162-2477-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Potassium Citrate 10 meq 72865-0192-01 | XLCare | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 68382-0537-01 | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (68382-537-01) | $0.1798 / ea | $17.98 | 2014-08-12 | Active |
| 68382-0537-05 | 500 TABLET, EXTENDED RELEASE in 1 BOTTLE (68382-537-05) | — | — | 2014-08-12 | Active |
| 68382-0537-06 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (68382-537-06) | — | — | 2014-08-12 | Active |
| 68382-0537-10 You're viewing this | 1000 TABLET, EXTENDED RELEASE in 1 BOTTLE (68382-537-10) | — | — | 2014-08-12 | Active |
| 68382-0537-16 | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE (68382-537-16) | — | — | 2014-08-12 | Active |
| 68382-0537-30 | 10 BLISTER PACK in 1 CARTON (68382-537-30) / 10 TABLET, EXTENDED RELEASE in 1 BLISTER PACK | — | — | 2014-08-12 | Active |
This pack shows little to no recent Medicaid volume — the 100 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 68382-0537-10?
What is the difference between NDC 68382-0537-10 and NDC 68382-0537-06?
What NDC number is used to bill for this package of Potassium Citrate 10 meq Tablet, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Potassium citrate extended-release tablet is a citrate salt of potassium indicated for the management of: Renal tubular acidosis (RTA) with calcium stones (1.1) Hypocitraturic calcium oxalate nephrolithiasis of any etiology (1.2) Uric acid lithiasis with or without calcium stones (1.3)
1.1Renal Tubular Acidosis (RTA) with Calcium Stones Potassium citrate is indicated for the management of renal tubular acidosis [see Clinical Studies (14.1)].
1.2Hypocitraturic Calcium Oxalate Nephrolithiasis of any Etiology Potassium citrate is indicated for the management of Hypocitraturic calcium oxalate nephrolithiasis [see Clinical Studies (14.2)].
1.3Uric Acid Lithiasis with or without Calcium Stones Potassium citrate is indicated for the management of Uric acid lithiasis with or without calcium stones [see Clinical Studies (14.3)].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Objective: To restore normal urinary citrate (greater than 320 mg/day and as close to the normal mean of 640 mg/day as possible), and to increase urinary pH to a level of 6 to 7. Severe hypocitraturia (urinary citrate < 150 mg/day): therapy should be initiated at 60 mEq per day; a dose of 30 mEq two times per day or 20 mEq three times per day with meals or within 30 minutes after meals or bedtime snack (2.2) Mild to moderate hypocitraturia (urinary citrate >150 mg/day): therapy should be initiated at 30 mEq per day; a dose of 15 mEq two times per day or 10 mEq three times per day with meals or within 30 minutes after meals or bedtime snack (2.3)
2.1Dosing Instructions Treatment with extended release potassium citrate should be added to a regimen that limits salt intake (avoidance of foods with high salt content and of added salt at the table) and encourages high fluid intake (urine volume should be at least two liters per day). The objective of treatment with potassium citrate extended-release tablets is to provide potassium citrate in sufficient dosage to restore normal urinary citrate (greater than 320 mg/day and as close to the normal mean of 640 mg/day as possible), and to increase urinary pH to a level of 6 or 7.
Monitor serum electrolytes (sodium, potassium, chloride and carbon dioxide), serum creatinine and complete blood counts every four months and more frequently in patients with cardiac disease, renal disease or acidosis. Perform electrocardiograms periodically. Treatment should be discontinued if there is hyperkalemia, a significant rise in serum creatinine or a significant fall in blood hematocrit or hemoglobin.
2.2Severe Hypocitraturia In patients with severe hypocitraturia (urinary citrate < 150 mg/day), therapy should be initiated at a dosage of 60 mEq/day (30 mEq two times/day or 20 mEq three times/day with meals or within 30 minutes after meals or bedtime snack). Twenty-four hour urinary citrate and/or urinary pH measurements should be used to determine the adequacy of the initial dosage and to evaluate the effectiveness of any dosage change. In addition, urinary citrate and/or pH should be measured every four months.
Doses of potassium citrate extended-release tablets greater than 100 mEq/day have not been studied and should be avoided.
2.3Mild to Moderate Hypocitraturia In patients with mild to moderate hypocitraturia (urinary citrate > 150 mg/day) therapy should be initiated at 30 mEq/day (15 mEq two times/day or 10 mEq three times/day with meals or within 30 minutes after meals or bedtime snack). Twenty-four hour urinary citrate and/or urinary pH measurements should be used to determine the adequacy of the initial dosage and to evaluate the effectiveness of any dosage change. Doses of potassium citrate extended-release tablet greater than 100 mEq/day have not been studied and should be avoided.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 5 mEq, 10 mEq and 15 mEq (3) 5 mEq tablets are tan to yellowish color, round shaped, biconvex uncoated tablets debossed with "536" on one side and plain on the other side. 10 mEq tablets are tan to yellowish color, oval shaped, biconvex uncoated tablets debossed with "537" on one side and plain on the other side. 15 mEq tablets are tan to yellowish color, oblong shaped, biconvex uncoated tablets debossed with "538" on one side and plain on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Patients with hyperkalemia (or who have conditions predisposing them to hyperkalemia). Such conditions include chronic renal failure, uncontrolled diabetes mellitus, acute dehydration, strenuous physical exercise in unconditioned individuals, adrenal insufficiency, extensive tissue breakdown (4) Patients for whom there is cause for arrest or delay in tablet passage through the gastrointestinal tract such as those suffering from delayed gastric emptying, esophageal compression, intestinal obstruction or stricture (4) Patients with peptic ulcer disease (4) Patients with active urinary tract infection (4) Patients with renal insufficiency (glomerular filtration rate of less than 0.7 ml/kg/min) (4) Potassium citrate extended-release tablets are contraindicated: In patients with hyperkalemia (or who have conditions predisposing them to hyperkalemia), as a further rise in serum potassium concentration may produce cardiac arrest.
Such conditions include: chronic renal failure, uncontrolled diabetes mellitus, acute dehydration, strenuous physical exercise in unconditioned individuals, adrenal insufficiency, extensive tissue breakdown or the administration of a potassium-sparing agent (such as triamterene, spironolactone or amiloride). In patients in whom there is cause for arrest or delay in tablet passage through the gastrointestinal tract, such as those suffering from delayed gastric emptying, esophageal compression, intestinal obstruction or stricture, or those taking anticholinergic medication.
In patients with peptic ulcer disease because of its ulcerogenic potential. In patients with active urinary tract infection (with either urea-splitting or other organisms, in association with either calcium or struvite stones). The ability of potassium citrate extended-release tablet to increase urinary citrate may be attenuated by bacterial enzymatic degradation of citrate.
Moreover, the rise in urinary pH resulting from potassium citrate extended-release tablet therapy might promote further bacterial growth. In patients with renal insufficiency (glomerular filtration rate of less than 0.7 ml/kg/min), because of the danger of soft tissue calcification and increased risk for the development of hyperkalemia.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hyperkalemia: In patients with impaired mechanisms for excreting potassium, potassium citrate administration can produce hyperkalemia and cardiac arrest. Potentially fatal hyperkalemia can develop rapidly and be asymptomatic. The use of potassium citrate in patients with chronic renal failure, or any other condition which impairs potassium excretion such as severe myocardial damage or heart failure, should be avoided (5.1) Gastrointestinal lesions: if there is severe vomiting, abdominal pain or gastrointestinal bleeding, potassium citrate should be discontinued immediately and the possibility of bowel perforation or obstruction investigated (5.2)
5.1Hyperkalemia In patients with impaired mechanisms for excreting potassium, potassium citrate administration can produce hyperkalemia and cardiac arrest. Potentially fatal hyperkalemia can develop rapidly and be asymptomatic. The use of potassium citrate in patients with chronic renal failure, or any other condition which impairs potassium excretion such as severe myocardial damage or heart failure, should be avoided.
Closely monitor for signs of hyperkalemia with periodic blood tests and ECGs.
5.2Gastrointestinal Lesions Solid dosage forms of potassium chlorides have produced stenotic and/or ulcerative lesions of the small bowel and deaths. These lesions are caused by a high local concentration of potassium ions in the region of the dissolving tablets, which injured the bowel. In addition, perhaps because wax-matrix preparations are not enteric-coated and release some of their potassium content in the stomach, there have been reports of upper gastrointestinal bleeding associated with these products.
The frequency of gastrointestinal lesions with wax-matrix potassium chloride products is estimated at one per 100,000 patient-years. Experience with potassium citrate is limited, but a similar frequency of gastrointestinal lesions should be anticipated. If there is severe vomiting, abdominal pain or gastrointestinal bleeding, potassium citrate should be discontinued immediately and the possibility of bowel perforation or obstruction investigated.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Some patients may develop minor gastrointestinal complaints such as abdominal discomfort, vomiting, diarrhea, loose bowel movements or nausea. These may be alleviated by taking the dose with meals or snacks or by reducing the dosage (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Zydus Pharmaceuticals (USA) Inc. at 1-877-993-8779 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Postmarketing Experience Some patients may develop minor gastrointestinal complaints during potassium citrate therapy, such as abdominal discomfort, vomiting, diarrhea, loose bowel movements or nausea. These symptoms are due to the irritation of the gastrointestinal tract, and may be alleviated by taking the dose with meals or snacks, or by reducing the dosage. Patients may find intact matrices in their feces.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The following drug interactions may occur with potassium citrate: Potassium-sparing diuretics: concomitant administration should be avoided since the simultaneous administration of these agents can produce severe hyperkalemia (7.1) Drugs that slow gastrointestinal transit time: These agents (such as anticholinergics) can be expected to increase the gastrointestinal irritation produced by potassium salts (7.2) Renin-angiotensin-aldosterone inhibitors: Monitor for hyperkalemia (7.3) Nonsteroidal Anti-inflammatory drugs (NSAIDs) monitor for hyperkalemia (7.4)
7.1Potential Effects of Potassium Citrate on Other Drugs Potassium-sparing Diuretics: Concomitant administration of potassium citrate and a potassium-sparing diuretic (such as triamterene, spironolactone or amiloride) should be avoided since the simultaneous administration of these agents can produce severe hyperkalemia.
7.2Potential Effects of Other Drugs on Potassium Citrate Drugs that slow gastrointestinal transit time: These agents (such as anticholinergics) can be expected to increase the gastrointestinal irritation produced by potassium salts.
7.3Renin-Angiotensin-Aldosterone System Inhibitors Drugs that inhibit the renin-angiotensin-aldosterone system (RAAS) including angiotensin converting enzyme (ACE) inhibitors, angiotensin receptor blockers (ARBs), spironolactone, eplerenone, or aliskiren produce potassium retention by inhibiting aldosterone production. Closely monitor potassium in patients receiving concomitant RAAS therapy.
7.4Nonsteroidal Anti-Inflammatory Drugs (NSAIDs) NSAIDs may produce potassium retention by reducing renal synthesis of prostagladin E and impairing the renin-angiotensin system. Closely monitor potassium in patients on concomitant NSAIDs.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnant women: Animal reproduction studies have not been conducted. It is not known whether potassium citrate can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Potassium citrate should be given to a pregnant woman only if clearly needed (8.1) Nursing mothers: The normal potassium ion content of human milk is about 13 mEq/L.
It is not known if potassium citrate has an effect on this content. Potassium citrate should be given to a woman who is breast feeding only if clearly needed (8.3) Pediatric Use: Safety and effectiveness in children have not been established (8.4)
8.1Pregnancy Animal reproduction studies have not been conducted. It is also not known whether potassium citrate can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Potassium citrate should be given to a pregnant woman only if clearly needed.
8.3Nursing Mothers The normal potassium ion content of human milk is about 13 mEq/L. It is not known if potassium citrate has an effect on this content. Potassium citrate should be given to a woman who is breast feeding only if clearly needed.
8.4Pediatric Use Safety and effectiveness in children have not been established.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in children have not been established.
🆘 Overdosage ▾
10 OVERDOSAGE Treatment of Overdosage : The administration of potassium salts to persons without predisposing conditions for hyperkalemia rarely causes serious hyperkalemia at recommended dosages. It is important to recognize that hyperkalemia is usually asymptomatic and may be manifested only by an increased serum potassium concentration and characteristic electrocardiographic changes (peaking of T-wave, loss of P-wave, depression of S-T segment and prolongation of the QT interval). Late manifestations include muscle paralysis and cardiovascular collapse from cardiac arrest.
Treatment measures for hyperkalemia include the following: Patients should be closely monitored for arrhythmias and electrolyte changes. Elimination of medications containing potassium and of agents with potassium-sparing properties such as potassium-sparing diuretics, ARBs, ACE inhibitors, NSAIDs, certain nutritional supplements and many others. Elimination of foods containing high levels of potassium such as almonds, apricots, bananas, beans (lima, pinto, white), cantaloupe, carrot juice (canned), figs, grapefruit juice, halibut, milk, oat bran, potato (with skin), salmon, spinach, tuna and many others.
Intravenous calcium gluconate if the patient is at no risk or low risk of developing digitalis toxicity. Intravenous administration of 300 to 500 mL/hr of 10% dextrose solution containing 10 to 20 units of crystalline insulin per 1,000 mL. Correction of acidosis, if present, with intravenous sodium bicarbonate.
Hemodialysis or peritoneal dialysis. Exchange resins may be used. However, this measure alone is not sufficient for the acute treatment of hyperkalemia.
Lowering potassium levels too rapidly in patients taking digitalis can produce digitalis toxicity.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action When potassium citrate is given orally, the metabolism of absorbed citrate produces an alkaline load. The induced alkaline load in turn increases urinary pH and raises urinary citrate by augmenting citrate clearance without measurably altering ultrafilterable serum citrate. Thus, potassium citrate therapy appears to increase urinary citrate principally by modifying the renal handling of citrate, rather than by increasing the filtered load of citrate.
The increased filtered load of citrate may play some role, however, as in small comparisons of oral citrate and oral bicarbonate, citrate had a greater effect on urinary citrate. In addition to raising urinary pH and citrate, potassium citrate increases urinary potassium by approximately the amount contained in the medication. In some patients, potassium citrate causes a transient reduction in urinary calcium.
The changes induced by potassium citrate produce urine that is less conducive to the crystallization of stone-forming salts (calcium oxalate, calcium phosphate and uric acid). Increased citrate in the urine, by complexing with calcium, decreases calcium ion activity and thus the saturation of calcium oxalate. Citrate also inhibits the spontaneous nucleation of calcium oxalate and calcium phosphate (brushite).
The increase in urinary pH also decreases calcium ion activity by increasing calcium complexation to dissociated anions. The rise in urinary pH also increases the ionization of uric acid to the more soluble urate ion. Potassium citrate therapy does not alter the urinary saturation of calcium phosphate, since the effect of increased citrate complexation of calcium is opposed by the rise in pH-dependent dissociation of phosphate.
Calcium phosphate stones are more stable in alkaline urine. In the setting of normal renal function, the rise in urinary citrate following a single dose begins by the first hour and lasts for 12 hours. With multiple doses the rise in citrate excretion reaches its peak by the third day and averts the normally wide circadian fluctuation in urinary citrate, thus maintaining urinary citrate at a higher, more constant level throughout the day.
When the treatment is withdrawn, urinary citrate begins to decline toward the pre-treatment level on the first day. The rise in citrate excretion is directly dependent on the potassium citrate dosage. Following long-term treatment, potassium citrate at a dosage of 60 mEq/day raises urinary citrate by approximately 400 mg/day and increases urinary pH by approximately 0.7 units.
In patients with severe renal tubular acidosis or chronic diarrheal syndrome where urinary citrate may be very low (<100 mg/day), potassium citrate may be relatively ineffective in raising urinary citrate. A higher dose of potassium citrate may therefore be required to produce a satisfactory citraturic response. In patients with renal tubular acidosis in whom urinary pH may be high, potassium citrate produces a relatively small rise in urinary pH.
🧬 Mechanism of Action ▾
12.1Mechanism of Action When potassium citrate is given orally, the metabolism of absorbed citrate produces an alkaline load. The induced alkaline load in turn increases urinary pH and raises urinary citrate by augmenting citrate clearance without measurably altering ultrafilterable serum citrate. Thus, potassium citrate therapy appears to increase urinary citrate principally by modifying the renal handling of citrate, rather than by increasing the filtered load of citrate.
The increased filtered load of citrate may play some role, however, as in small comparisons of oral citrate and oral bicarbonate, citrate had a greater effect on urinary citrate. In addition to raising urinary pH and citrate, potassium citrate increases urinary potassium by approximately the amount contained in the medication. In some patients, potassium citrate causes a transient reduction in urinary calcium.
The changes induced by potassium citrate produce urine that is less conducive to the crystallization of stone-forming salts (calcium oxalate, calcium phosphate and uric acid). Increased citrate in the urine, by complexing with calcium, decreases calcium ion activity and thus the saturation of calcium oxalate. Citrate also inhibits the spontaneous nucleation of calcium oxalate and calcium phosphate (brushite).
The increase in urinary pH also decreases calcium ion activity by increasing calcium complexation to dissociated anions. The rise in urinary pH also increases the ionization of uric acid to the more soluble urate ion. Potassium citrate therapy does not alter the urinary saturation of calcium phosphate, since the effect of increased citrate complexation of calcium is opposed by the rise in pH-dependent dissociation of phosphate.
Calcium phosphate stones are more stable in alkaline urine. In the setting of normal renal function, the rise in urinary citrate following a single dose begins by the first hour and lasts for 12 hours. With multiple doses the rise in citrate excretion reaches its peak by the third day and averts the normally wide circadian fluctuation in urinary citrate, thus maintaining urinary citrate at a higher, more constant level throughout the day.
When the treatment is withdrawn, urinary citrate begins to decline toward the pre-treatment level on the first day. The rise in citrate excretion is directly dependent on the potassium citrate dosage. Following long-term treatment, potassium citrate at a dosage of 60 mEq/day raises urinary citrate by approximately 400 mg/day and increases urinary pH by approximately 0.7 units.
In patients with severe renal tubular acidosis or chronic diarrheal syndrome where urinary citrate may be very low (<100 mg/day), potassium citrate may be relatively ineffective in raising urinary citrate. A higher dose of potassium citrate may therefore be required to produce a satisfactory citraturic response. In patients with renal tubular acidosis in whom urinary pH may be high, potassium citrate produces a relatively small rise in urinary pH.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Potassium Citrate Extended-release Tablets USP, 5 mEq are tan to yellowish color, round shaped, biconvex uncoated tablets debossed with "536" on one side and plain on the other side and are supplied as follows: NDC 68382-536-06 in bottle of 30 tablets with child-resistant closure NDC 68382-536-16 in bottle of 90 tablets with child-resistant closure NDC 68382-536-01 in bottle of 100 tablets with child-resistant closure NDC 68382-536-05 in bottle of 500 tablets NDC 68382-536-10 in bottle of 1,000 tablets NDC 68382-536-30 in unit-dose blister cartons of 100 (10×10) unit dose tablets Potassium Citrate Extended-release Tablets USP, 10 mEq are tan to yellowish color, oval shaped, biconvex uncoated tablets debossed with "537" on one side and plain on the other side and are supplied as follows: NDC 68382-537-06 in bottle of 30 tablets with child-resistant closure NDC 68382-537-16 in bottle of 90 tablets with child-resistant closure NDC 68382-537-01 in bottle of 100 tablets with child-resistant closure NDC 68382-537-05 in bottle of 500 tablets NDC 68382-537-10 in bottle of 1,000 tablets NDC 68382-537-30 in unit-dose blister cartons of 100 (10×10) unit dose tablets Potassium Citrate Extended-release Tablets USP, 15 mEq are tan to yellowish color, oblong shaped, biconvex uncoated tablets debossed with "538" on one side and plain on the other side and are supplied as follows: NDC 68382-538-06 in bottle of 30 tablets with child-resistant closure NDC 68382-538-16 in bottle of 90 tablets with child-resistant closure NDC 68382-538-01 in bottle of 100 tablets with child-resistant closure NDC 68382-538-05 in bottle of 500 tablets NDC 68382-538-10 in bottle of 1,000 tablets NDC 68382-538-30 in unit-dose blister cartons of 100 (10×10) unit dose tablets Storage: Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Dispense in a tight container as defined in the USP.
📋 Description ▾
11 DESCRIPTION Potassium citrate is a citrate salt of potassium. Its molecular formula is K 3 C 6 H 5 O 7 • H 2 O, and it has the following chemical structure: Potassium citrate, USP is a transparent crystals or white, granular powder. It is freely soluble in water and slightly soluble in alcohol.
Potassium citrate extended-release tablets, USP intended for oral administration, each contains 5 mEq (540 mg), 10 mEq (1,080 mg) or 15 mEq (1,620 mg) of potassium citrate, USP as monohydrate. In addition, each tablet contains the following inactive ingredients: carnauba wax and magnesium stearate. Meets USP Dissolution Test 2 figure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Administration of Drug Tell patients to take each dose without crushing, chewing or sucking the tablet. Tell patients to take this medicine only as directed. This is especially important if the patient is also taking both diuretics and digitalis preparations.
Tell patients to check with the doctor if there is trouble swallowing tablets or if the tablet seems to stick in the throat. Tell patients to check with the doctor at once if tarry stools or other evidence of gastrointestinal bleeding is noticed. Tell patients that their doctor will perform regular blood tests and electrocardiograms to ensure safety.
Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088. Manufactured by: Zydus Lifesciences Ltd., Baddi, India Distributed by: Zydus Pharmaceuticals (USA) Inc.
Pennington, NJ 08534 Rev.: 01/23