
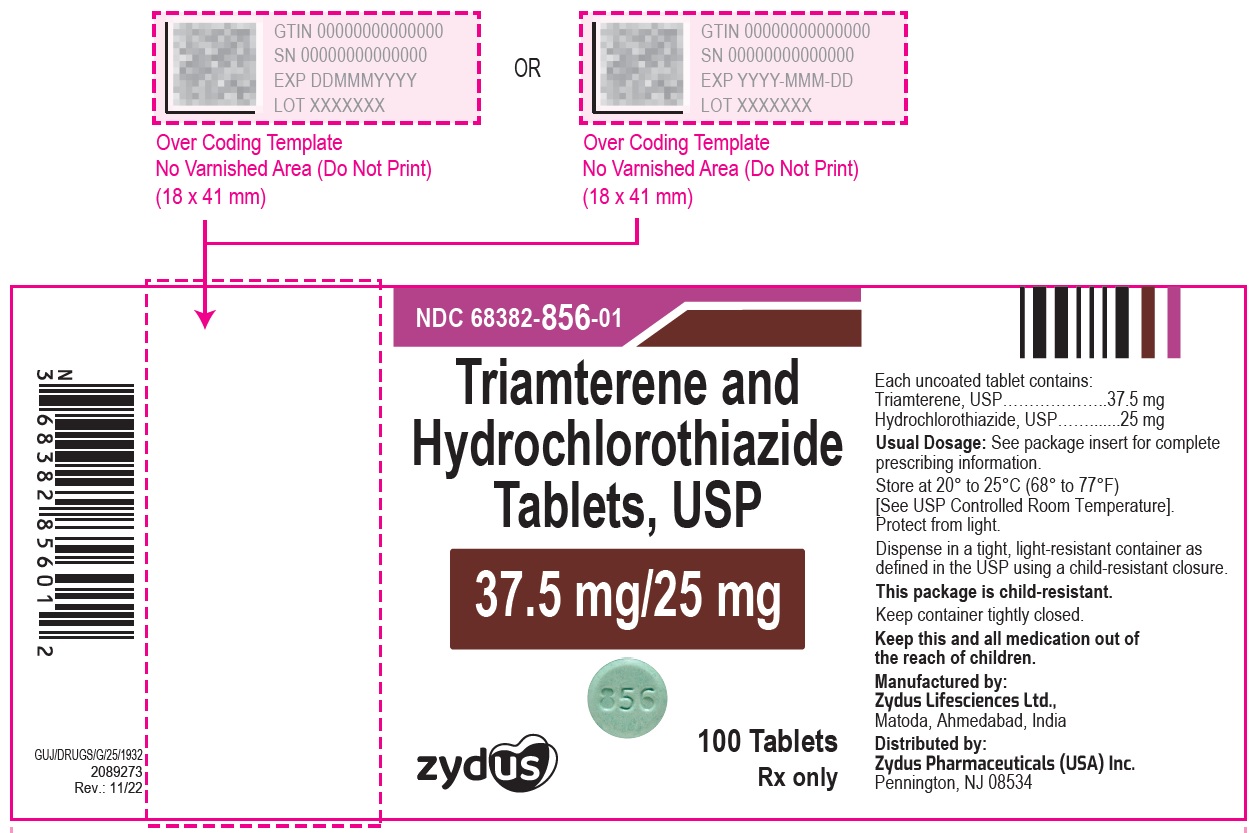
triamterene and hydrochlorothiazide 37.5 mg; 25 mg Tablet, 100-count — NDC 68382-856-01 (Billing 68382-0856-01)
This is a package of 100 tablets of triamterene and hydrochlorothiazide 37.5 mg; 25 mg Tablet from Zydus Pharmaceuticals (USA) Inc., marketed since Sep 2018 and currently FDA-listed; retail pharmacies pay about $0.0969 per tablet (NADAC). It is the main listing for this product, which comes in 4 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 008176
- GCN: 88741
- GPI-14 (Medi-Span): 37990002300315
- HICL (First Databank): 003647
- AHFS class code: 24:36.20.00
- RxCUI (RxNorm): 310812
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Potassium-sparing Diuretic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
The combination of triamterene and hydrochlorothiazide is used to treat high blood pressure and edema (fluid retention; excess fluid held in body tissues) in patients who have lower amounts of potassium in their bodies or for whom low potassium levels in the body could be dangerous. The combination of triamterene and hydrochlorothiazide is in a class of medications called diuretics ('water pills'). They work by causing the kidneys to get rid of unneeded water and salt from the body into the urine. High blood pressure is a common condition, and when not treated it can cause damage to the brain,...
Read the full MedlinePlus article ↗- It treats high blood pressure or fluid swelling (edema). It is mainly for people who lose too much potassium on hydrochlorothiazide alone, or who need a water pill but can't risk l...
- Take it by mouth, usually once a day, exactly as your prescriber directs. Don't split the daily dose unless told to. You'll need regular blood tests to check your potassium.
- No, not unless your doctor tells you to. Most salt substitutes are full of potassium. With this medicine, they can push your potassium dangerously high.
- Can I use salt substitutes or potassium supplements?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.097 | $9.69 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2335 | $23.35 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1535 | $15.35 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 68382-0856-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | $0.0969 / ea | $9.69 | 2018-09-04 | — | Active |
| 68382-0856-05 68382-856-05 | 500 TABLET in 1 BOTTLE | $0.0969 / ea | $48.47 | 2018-09-04 | — | Active |
| 68382-0856-10 68382-856-10 | 1000 TABLET in 1 BOTTLE | — | — | 2018-09-04 | — | Active |
| 68382-0856-77 68382-856-77 | 10 BLISTER PACK in 1 CARTON / 10 TABLET in 1 BLISTER PACK | — | — | 2018-09-04 | — | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.0969 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 73% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 68382-0856-77?
What NDC number is used to bill for this package of triamterene and hydrochlorothiazide 37.5 mg; 25 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 68001-0387-00 | BluePoint | 100 tablets | $0.091 | AB | Discontinued | save 6% |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 00591-0424-01 | Actavis | 100 tablets | $0.097 | — | Availability likely | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 60505-2656-01 | Apotex | 100 tablets | $0.097 | AB | Availability likely | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 68001-0327-00 | BluePoint | 100 tablets | $0.097 | AB | Availability likely | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 68084-0750-25 | American | 30 tablets | $0.097 | AB | Availability likely | — |
| triamterene and hydrochlorothiazide 37.5 mg/1; 25 mgthis 68382-0856-01 | Zydus | 100 tablets | $0.097 | AB | Availability likely | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 50090-1270-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| triamterene and hydrochlorothiazide 37.5 mg/1; 25 mg 50090-5801-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 51407-0286-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 51655-0630-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 55289-0090-15 | PD-Rx | 15 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 68071-1834-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 68071-2371-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 68788-7526-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 70518-1662-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| triamterene and hydrochlorothiazide 37.5 mg/1; 25 mg 70771-1361-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 71335-0356-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 71335-0968-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 71335-2631-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 71335-2806-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| triamterene and hydrochlorothiazide 37.5 mg/1; 25 mg 71610-0602-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 71610-0605-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 71610-0684-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 72789-0183-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 72888-0094-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
| Triamterene and Hydrochlorothiazide 37.5 mg/1; 25 mg 82868-0006-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII 0VUT3PMY82
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. In medicines, it forms protective coatings on tablets or capsules, controls how fast the drug releases, and thickens liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNINGS Hyperkalemia Abnormal elevation of serum potassium levels (greater than or equal to 5.5 mEq/liter) can occur with all potassium-conserving diuretic combinations, including triamterene and hydrochlorothiazide. Hyperkalemia is more likely to occur in patients with renal impairment, diabetes (even without evidence of renal impairment), or elderly or severely ill patients. Since uncorrected hyperkalemia may be fatal, serum potassium levels must be monitored at frequent intervals especially in patients first receiving triamterene and hydrochlorothiazide, when dosages are changed or with any illness that may influence renal function.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE This fixed combination drug is not indicated for the initial therapy of edema or hypertension except in individuals in whom the development of hypokalemia cannot be risked. Triamterene and hydrochlorothiazide tablets, USP are indicated for the treatment of hypertension or edema in patients who develop hypokalemia on hydrochlorothiazide alone. Triamterene and hydrochlorothiazide tablets, USP are also indicated for those patients who require a thiazide diuretic and in whom the development of hypokalemia cannot be risked (e.g., patients on concomitant digitalis preparations, or with a history of cardiac arrhythmias, etc.).
Triamterene and hydrochlorothiazide tablets, USP may be used alone or in combination with other antihypertensive drugs, such as beta-blockers. Since triamterene and hydrochlorothiazide tablets, USP may enhance the actions of these drugs, dosage adjustments may be necessary. Usage in Pregnancy The routine use of diuretics in an otherwise healthy woman is inappropriate and exposes mother and fetus to unnecessary hazard.
Diuretics do not prevent development of toxemia of pregnancy, and there is no satisfactory evidence that they are useful in the treatment of developed toxemia. Edema during pregnancy may arise from pathological causes or from the physiologic and mechanical consequences of pregnancy. Thiazides are indicated in pregnancy when edema is due to pathologic causes, just as they are in the absence of pregnancy.
Dependent edema in pregnancy, resulting from restriction of venous return by the expanded uterus, is properly treated through elevation of the lower extremities and use of support hose; use of diuretics to lower intravascular volume in this case is illogical and unnecessary. There is hypervolemia during normal pregnancy which is harmful to neither the fetus nor the mother (in the absence of cardiovascular disease), but which is associated with edema, including generalized edema, in the majority of pregnant women. If this edema produces discomfort, increased recumbency will often provide relief.
In rare instances, this edema may cause extreme discomfort which is not relieved by rest. In these cases, a short course of diuretics may provide relief and may be appropriate.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The usual dose of triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg is one or two tablets daily, given as a single dose, with appropriate monitoring of serum potassium ( see WARNINGS ). The usual dose of triamterene and hydrochlorothiazide tablets, 75 mg/50 mg is one tablet daily, with appropriate monitoring of serum potassium ( see WARNINGS ). There is no experience with the use of more than one 75 mg/50 mg (75 mg triamterene and 50 mg hydrochlorothiazide) tablet daily or more than two 37.5 mg/25 mg (37.5 mg triamterene and 25 mg hydrochlorothiazide) tablets daily.
Clinical experience with the administration of two 37.5 mg/25 mg (37.5 mg triamterene and 25 mg hydrochlorothiazide) tablets daily in divided doses (rather than as a single dose) suggests an increased risk of electrolyte imbalance and renal dysfunction. Patients receiving 50 mg of hydrochlorothiazide who become hypokalemic may be transferred to triamterene and hydrochlorothiazide tablets, 75 mg/50 mg directly. Patients receiving 25 mg hydrochlorothiazide who become hypokalemic may be transferred to triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg directly.
In patients requiring hydrochlorothiazide therapy and in whom hypokalemia cannot be risked therapy may be initiated with triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg. If an optimal blood pressure response is not obtained with triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg, the dose should be increased to two 37.5 mg/25 mg (37.5 mg triamterene and 25 mg hydrochlorothiazide) tablets daily as a single dose, or one triamterene and hydrochlorothiazide tablets, 75 mg/50 mg daily. If blood pressure still is not controlled, another antihypertensive agent may be added ( see PRECAUTIONS: Drug Interactions ).
Clinical studies have shown that patients taking less bioavailable formulations of triamterene and hydrochlorothiazide in daily doses of 25 mg to 50 mg hydrochlorothiazide and 50 mg to 100 mg triamterene may be safely changed to one triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg daily. All patients changed from less bioavailable formulations to triamterene and hydrochlorothiazide tablets, 75 mg/50 mg should be monitored clinically and for serum potassium after the transfer.
⛔ Contraindications ▾
CONTRAINDICATIONS Hyperkalemia Triamterene and hydrochlorothiazide should not be used in the presence of elevated serum potassium levels (greater than or equal to 5.5 mEq/liter). If hyperkalemia develops, this drug should be discontinued and a thiazide alone should be substituted. Antikaliuretic Therapy or Potassium Supplementation Triamterene and hydrochlorothiazide should not be given to patients receiving other potassium-conserving agents such as spironolactone, amiloride hydrochloride or other formulations containing triamterene.
Concomitant potassium supplementation in the form of medication, potassium-containing salt substitute or potassium-enriched diets should also not be used. Impaired Renal Function Triamterene and hydrochlorothiazide is contraindicated in patients with anuria, acute and chronic renal insufficiency or significant renal impairment. Hypersensitivity Triamterene and hydrochlorothiazide should not be used in patients who are hypersensitive to triamterene or hydrochlorothiazide or other sulfonamide-derived drugs.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Side effects observed in association with the use of triamterene and hydrochlorothiazide tablets, other combination products containing triamterene/hydrochlorothiazide, and products containing triamterene or hydrochlorothiazide include the following: Gastrointestinal: jaundice (intrahepatic cholestatic jaundice), pancreatitis, nausea, appetite disturbance, taste alteration, vomiting, diarrhea, constipation, anorexia, gastric irritation, cramping. Central Nervous System: drowsiness and fatigue, insomnia, headache, dizziness, dry mouth, depression, anxiety, vertigo, restlessness, paresthesias.
Cardiovascular: tachycardia, shortness of breath and chest pain, orthostatic hypotension (may be aggravated by alcohol, barbiturates or narcotics). Renal: acute renal failure, acute interstitial nephritis, renal stones composed of triamterene in association with other calculus materials, urine discoloration. Hematologic: leukopenia, agranulocytosis, thrombocytopenia, aplastic anemia, hemolytic anemia and megaloblastosis.
Ophthalmic: xanthopsia, transient blurred vision. Hypersensitivity: anaphylaxis, photosensitivity, rash, urticaria, purpura, necrotizing angiitis (vasculitis, cutaneous vasculitis), fever, respiratory distress including pneumonitis. Other: muscle cramps and weakness, decreased sexual performance and sialadenitis.
Whenever adverse reactions are moderate to severe, therapy should be reduced or withdrawn. Altered Laboratory Findings Serum Electrolytes: hyperkalemia, hypokalemia, hyponatremia, hypomagnesemia, hypochloremia ( see WARNINGS and PRECAUTIONS ). Creatinine , Blood Urea Nitrogen: Reversible elevations in BUN and serum creatinine have been observed in hypertensive patients treated with triamterene and hydrochlorothiazide.
Glucose: hyperglycemia, glycosuria and diabetes mellitus ( see PRECAUTIONS ). Serum Uric Acid , PBI and Calcium: ( see PRECAUTIONS ). Other: Elevated liver enzymes have been reported in patients receiving triamterene and hydrochlorothiazide.
Postmarketing Experience Non-melanoma Skin Cancer: Hydrochlorothiazide is associated with an increased risk of non-melanoma skin cancer. In a study conducted in the Sentinel System, increased risk was predominantly for squamous cell carcinoma (SCC) and in white patients taking large cumulative doses. The increased risk for SCC in the overall population was approximately 1 additional case per 16,000 patients per year, and for white patients taking a cumulative dose of ≥ 50,000 mg the risk increase was approximately 1 additional SCC case for every 6,700 patients per year.
🔄 Drug Interactions ▾
Drug Interactions Thiazides may add to or potentiate the action of other antihypertensive drugs. The thiazides may decrease arterial responsiveness to norepinephrine. This diminution is not sufficient to preclude effectiveness of the pressor agent for therapeutic use.
Thiazides have also been shown to increase the responsiveness to tubocurarine. Lithium generally should not be given with diuretics because they reduce its renal clearance and add a high risk of lithium toxicity. Refer to the package insert on lithium before use of such concomitant therapy.
Acute renal failure has been reported in a few patients receiving indomethacin and formulations containing triamterene and hydrochlorothiazide. Caution is therefore advised when administering non-steroidal anti-inflammatory agents with triamterene and hydrochlorothiazide. Potassium-sparing agents should be used very cautiously, if at all, in conjunction with angiotensin-converting enzyme (ACE) inhibitors due to a greatly increased risk of hyperkalemia.
Serum potassium should be monitored frequently.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Triamterene and Hydrochlorothiazide Animal reproduction studies to determine the potential for fetal harm by triamterene and hydrochlorothiazide have not been conducted. Nevertheless, a One Generation Study in the rat approximated triamterene and hydrochlorothiazide's composition by using a 1:1 ratio of triamterene to hydrochlorothiazide (30:30 mg/kg/day). There was no evidence of teratogenicity at those doses that were, on a body-weight basis, 15 and 30 times, respectively, the MRHD, and, on the basis of body-surface area, 3.1 and 6.2 times, respectively, the MRHD.
The safe use of triamterene and hydrochlorothiazide in pregnancy has not been established since there are no adequate and well controlled studies with triamterene and hydrochlorothiazide in pregnant women. Triamterene and hydrochlorothiazide should be used during pregnancy only if the potential benefit justifies the risk to the fetus. Triamterene Reproduction studies have been performed in rats at doses as high as 20 times the Maximum Recommended Human Dose (MRHD) on the basis of body-weight, and 6 times the MRHD on the basis of body-surface area without evidence of harm to the fetus due to triamterene.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Hydrochlorothiazide Hydrochlorothiazide was orally administered to pregnant mice and rats during respective periods of major organogenesis at doses up to 3000 and 1000 mg/kg/day, respectively. At these doses, which are multiples of the MRHD equal to 3000 for mice and 1000 for rats, based on body-weight, and equal to 282 for mice and 206 for rats, based on body-surface area, there was no evidence of harm to the fetus.
There are, however, no adequate and well controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🆘 Overdosage ▾
OVERDOSAGE No specific data are available regarding triamterene and hydrochlorothiazide overdosage in humans and no specific antidote is available. Fluid and electrolyte imbalances are the most important concern. Excessive doses of the triamterene component may elicit hyperkalemia, dehydration, nausea, vomiting and weakness and possibly hypotension.
Overdosing with hydrochlorothiazide has been associated with hypokalemia, hypochloremia, hyponatremia, dehydration, lethargy (may progress to coma) and gastrointestinal irritation. Treatment is symptomatic and supportive. Therapy with triamterene and hydrochlorothiazide should be discontinued.
Induce emesis or institute gastric lavage. Monitor serum electrolyte levels and fluid balance. Institute supportive measures as required to maintain hydration, electrolyte balance, respiratory, cardiovascular and renal function.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Triamterene and hydrochlorothiazide is a diuretic, antihypertensive drug product, principally due to its hydrochlorothiazide component; the triamterene component of triamterene and hydrochlorothiazide reduces the excessive potassium loss which may occur with hydrochlorothiazide use. Hydrochlorothiazide Hydrochlorothiazide is a diuretic and antihypertensive agent. It blocks the renal tubular absorption of sodium and chloride ions.
This natriuresis and diuresis is accompanied by a secondary loss of potassium and bicarbonate. Onset of hydrochlorothiazide's diuretic effect occurs within 2 hours and the peak action takes place in 4 hours. Diuretic activity persists for approximately 6 to 12 hours.
The exact mechanism of hydrochlorothiazide's antihypertensive action is not known although it may relate to the excretion and redistribution of body sodium. Hydrochlorothiazide does not affect normal blood pressure. Following oral administration, peak hydrochlorothiazide plasma levels are attained in approximately 2 hours.
It is excreted rapidly and unchanged in the urine. Well controlled studies have demonstrated that doses of hydrochlorothiazide as low as 25 mg given once daily are effective in treating hypertension, but the dose-response has not been clearly established. Triamterene Triamterene is a potassium-conserving (antikaliuretic) diuretic with relatively weak natriuretic properties.
It exerts its diuretic effect on the distal renal tubule to inhibit the reabsorption of sodium in exchange for potassium and hydrogen. With this action, triamterene increases sodium excretion and reduces the excessive loss of potassium and hydrogen associated with hydrochlorothiazide. Triamterene is not a competitive antagonist of the mineralocorticoids and its potassium-conserving effect is observed in patients with Addison's disease, i.e., without aldosterone.
Triamterene's onset and duration of activity is similar to hydrochlorothiazide. No predictable antihypertensive effect has been demonstrated with triamterene. Triamterene is rapidly absorbed following oral administration.
Peak plasma levels are achieved within one hour after dosing. Triamterene is primarily metabolized to the sulfate conjugate of hydroxytriamterene. Both the plasma and urine levels of this metabolite greatly exceed triamterene levels.
The amount of triamterene added to 50 mg of hydrochlorothiazide in triamterene and hydrochlorothiazide tablets, 75 mg/50 mg was determined from steady-state dose-response evaluations in which various doses of liquid preparations of triamterene were administered to hypertensive persons who developed hypokalemia with hydrochlorothiazide (50 mg given once daily). Single daily doses of 75 mg triamterene resulted in greater increases in serum potassium than lower doses (25 mg and 50 mg), while doses greater than 75 mg of triamterene resulted in no additional elevations in serum potassium levels.
The amount of triamterene added to the 25 mg of hydrochlorothiazide in triamterene and hydrochlorothiazide tablets, 37.5 mg/25 mg was also determined from steady-state dose-response evaluations in which various doses of liquid preparations of triamterene were administered to hypertensive persons who developed hypokalemia with hydrochlorothiazide (25 mg given once daily). Single daily doses of 37.5 mg triamterene resulted in greater increases in serum potassium than a lower dose (25 mg), while doses greater than 37.5 mg of triamterene, i.e., 75 mg and 100 mg, resulted in no additional elevations in serum potassium levels.
The dose-response relationship of triamterene was also evaluated in patients rendered hypokalemic by hydrochlorothiazide given 25 mg twice daily. Triamterene given twice daily increased serum potassium levels in a dose related fashion. However, the combination of triamterene and hydrochlorothiazide given twice daily also appeared to produce an increased frequency of elevation in serum BUN and creatinine levels.
The large… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Triamterene and Hydrochlorothiazide Tablets USP, 37.5 mg/25 mg are yellowish green to green colored, spotted, round shaped, flat, uncoated tablets debossed with '856' on one side and breakline on the other side and are supplied as follows: NDC 68382-856-01 in bottles of 100 tablets with child-resistant closure NDC 68382-856-05 in bottles of 500 tablets NDC 68382-856-10 in bottles of 1000 tablets NDC 68382-856-77 in unit-dose blister cartons of 100 tablets (10 X 10 Unit-dose) Triamterene and Hydrochlorothiazide Tablets USP, 75 mg/50 mg are light yellow to yellow colored, round shaped, flat, uncoated tablets debossed with '857' on one side and breakline on the other side and are supplied as follows: NDC 68382-857-01 in bottles of 100 tablets with child-resistant closure NDC 68382-857-05 in bottles of 500 tablets NDC 68382-857-10 in bottles of 1000 tablets NDC 68382-857-77 in unit-dose blister cartons of 100 tablets (10 X 10 Unit-dose) Store at 20º to 25º C (68º to 77º F) [See USP Controlled Room Temperature].
Protect from light. Dispense in a tight, light-resistant container as defined in the USP. Call your doctor for medical advice about side effects.
You may report side effects to FDA at 1-800-FDA-1088. Manufactured by: Zydus Lifesciences Ltd., Matoda, Ahmedabad, India Distributed by: Zydus Pharmaceuticals ( USA) Inc. Pennington, NJ 08534 Rev.: 11/22
📋 Description ▾
DESCRIPTION Triamterene and hydrochlorothiazide combines triamterene a potassium-conserving diuretic, with the natriuretic agent, hydrochlorothiazide. Each Triamterene and Hydrochlorothiazide Tablet USP, 37.5 mg/25 mg contains: Triamterene, USP ..............................................................................37.5 mg Hydrochlorothiazide, USP ................................................................25 mg Each Triamterene and Hydrochlorothiazide Tablet USP, 75 mg/50 mg contains: Triamterene, USP .............................................................................75 mg Hydrochlorothiazide, USP ................................................................50 mg Each triamterene and hydrochlorothiazide tablet, USP intended for oral administration contains 37.5 mg triamterene USP with 25 mg hydrochlorothiazide USP and 75 mg triamterene USP with 50 mg hydrochlorothiazide USP.
In addition, each tablet contains the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, D&C Yellow No. 10 Aluminum Lake, hypromellose, magnesium stearate and microcrystalline cellulose. Additionally, the 37.5 mg/25 mg tablets contain FD&C Blue No.
1 Aluminum Lake. Triamterene is 2,4,7-triamino-6-phenylpteridine. Triamterene, USP is soluble in formic acid.
It is sparingly soluble in methoxyethanol. It is very slightly soluble in acetic acid, alcohol and dilute mineral acids. It is practically insoluble in water, benzene, ether, chloroform and dilute alkali hydroxides.
Its molecular weight is 253.26. Its structural formula is: Hydrochlorothiazide is 6-chloro-3,4-dihydro-2 H -1,2,4, benzothiadiazine-7-sulfonamide 1,1-dioxide. Hydrochlorothiazide, USP is very slightly soluble in water.
It is freely soluble in sodium hydroxide solution, n-butylamine and dimethyl formamide. It is sparingly soluble in methanol. It is insoluble in ether, chloroform and dilute mineral acids.
Its molecular weight is 297.7. Its structural formula is: figure figure
⚠️ Precautions ▾
PRECAUTIONS General Electrolyte Imbalance and BUN Increases Patients receiving triamterene and hydrochlorothiazide should be carefully monitored for fluid or electrolyte imbalances, i.e., hyponatremia, hypochloremic alkalosis, hypokalemia and hypomagnesemia. Determination of serum electrolytes to detect possible electrolyte imbalance should be performed at appropriate intervals. Serum and urine electrolyte determinations are especially important and should be frequently performed when the patient is vomiting or receiving parenteral fluids.
Warning signs or symptoms of fluid and electrolyte imbalance include: dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia and gastrointestinal disturbances such as nausea and vomiting. Any chloride deficit during thiazide therapy is generally mild and usually does not require any specific treatment except under extraordinary circumstances (as in liver disease or renal disease). Dilutional hyponatremia may occur in edematous patients in hot weather; appropriate therapy is water restriction, rather than administration of salt, except in rare instances when the hyponatremia is life threatening.
In actual salt depletion, appropriate replacement is the therapy of choice. Hypokalemia may develop with thiazide therapy, especially with brisk diuresis, when severe cirrhosis is present, or during concomitant use of corticosteroids, ACTH, amphotericin B or after prolonged thiazide therapy. However, hypokalemia of this type is usually prevented by the triamterene component of triamterene and hydrochlorothiazide.
Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Hypokalemia can sensitize or exaggerate the response of the heart to the toxic effects of digitalis (e.g., increased ventricular irritability). Triamterene and hydrochlorothiazide may produce an elevated blood urea nitrogen level (BUN), creatinine level or both.
This is probably not the result of renal toxicity but is secondary to a reversible reduction of the glomerular filtration rate or a depletion of the intravascular fluid volume. Elevations in BUN and creatinine levels may be more frequent in patients receiving divided dose diuretic therapy. Periodic BUN and creatinine determinations should be made especially in elderly patients, patients with suspected or confirmed hepatic disease or renal insufficiencies.
If azotemia increases, triamterene and hydrochlorothiazide should be discontinued. Hepatic Coma Triamterene and hydrochlorothiazide should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma. Renal Stones Triamterene has been reported in renal stones in association with other calculus components.
Triamterene and hydrochlorothiazide should be used with caution in patients with histories of renal lithiasis. Folic Acid Deficiency Triamterene is a weak folic acid antagonist and may contribute to the appearance of megaloblastosis in instances where folic acid stores are decreased. In such patients, periodic blood elevations are recommended.
Hyperuricemia Hyperuricemia may occur or acute gout may be precipitated in certain patients receiving thiazide therapy. Metabolic and Endocrine Effects The thiazides may decrease serum PBI levels without signs of thyroid disturbance. Calcium excretion is decreased by thiazides.
Pathological changes in the parathyroid gland with hypercalcemia and hypophosphatemia have been observed in a few patients on prolonged thiazide therapy. The common complications of hyperparathyroidism such as renal lithiasis, bone resorption, and peptic ulceration have not been seen. Thiazides should be discontinued before carrying out tests for parathyroid function.
Insulin requirements in diabetic patients may be increased, decreased or unchanged. Diabetes mellitus which… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Thiazides and triamterene in combination have not been studied in nursing mothers. Triamterene appears in animal milk and this may occur in humans. Thiazides are excreted in human breast milk. If use of the combination drug product is deemed essential, the patient should stop nursing.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 68382-856-01 Triamterene and Hydrochlorothiazide Tablets USP, 37.5 mg/25 mg 100 Tablets Rx only Zydus NDC 68382-857-01 Triamterene and Hydrochlorothiazide Tablets USP, 75 mg/50 mg 100 Tablets Rx only Zydus figure figure