
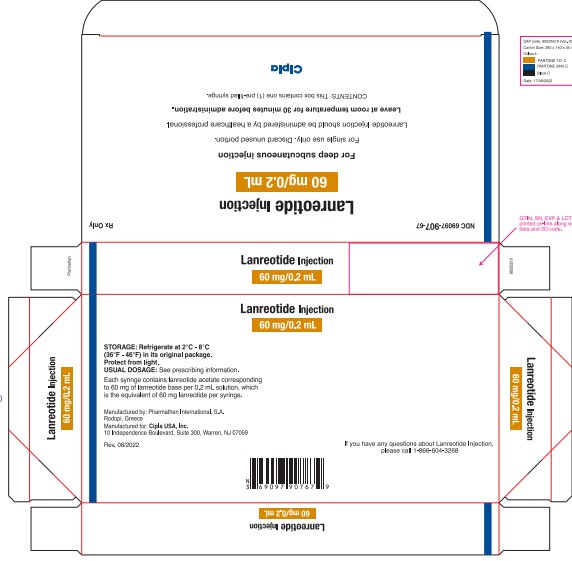
LANREOTIDE ACETATE 60 mg/.2mL Injection, 1 pouch — NDC 69097-907-67 (Billing 69097-0907-67)
This is a package of 1 pouch of LANREOTIDE ACETATE 60 mg/.2mL Injection from Cipla USA Inc., marketed since May 2025 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 69097-907-67 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 69097 labeler · 907 product · 67 package
- Package marketed since
- May 30, 2025
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6909790767 9
- FDA record last changed
- Jul 24, 2026
Other active recalls for Lanreotide Acetate (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 063199
- GCN: 98956
- HICL (First Databank): 010781
- AHFS class code: 68:29.04.00
- RxCUI (RxNorm): 749811
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Somatostatin Analog class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Lanreotide injection is used to treat people with acromegaly (condition in which the body produces too much growth hormone, causing enlargement of the hands, feet, and facial features; joint pain; and other symptoms) who have not successfully, or cannot be treated with surgery or radiation. Lanreotide injection is also used to treat people with neuroendocrine tumors in the gastrointestinal (GI) tract or the pancreas (GEP-NETs) that have spread or cannot be removed by surgery. It is also used to treat carcinoid syndrome (a condition in which slow-growing tumors release natural substances that c...
Read the full MedlinePlus article ↗- That depends on why you're taking it. If you have acromegaly, it's working to lower your growth hormone and IGF-1 levels back toward normal — which helps ease symptoms like enlarge...
- What is lanreotide actually doing for my condition?
- Lanreotide Injection is given as a deep shot under the skin in the upper outer area of the buttock — and it's meant to be given by a healthcare provider, not typically at home. You...
- How is this injection given, and do I have to give it to myself?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 69097-0907-67 You're viewing this Main listing | 1 POUCH in 1 CARTON / 1 SYRINGE in 1 POUCH / .2 mL in 1 SYRINGE | 2025-05-30 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Somatuline Depot 60 mg/.2mL 15054-1060-04 | Ipsen | 1 pouch | — | AB | FDA listed | — |
| Lanreotide Acetate 60 mg/.2mL 69097-0880-67 | Cipla | 1 syringe | — | — | FDA listed | — |
| Lanreotide Acetate 60 mg/.2mLthis 69097-0907-67 | Cipla | 1 pouch | — | AB | FDA listed | — |
| Lanreotide Acetate 60 mg/.2mL 76282-0718-67 | EXELAN | 1 pouch | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Q40Q9N063P
Acetic acid is a weak organic acid commonly used in medicines as a buffer and pH adjuster. It helps maintain the proper acidity level to ensure the drug remains stable and effective in its formulation.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Cipla USA Inc. labeler code 69097
- Fenofibrate 200 mg Capsule NDC 69097-896-02
- Atorvastatin Calcium 10 mg Tablet, Film Coated NDC 69097-897-05
- Atorvastatin Calcium 20 mg Tablet, Film Coated NDC 69097-898-05
- Atorvastatin Calcium 40 mg Tablet, Film Coated NDC 69097-899-05
- OSELTAMIVIR PHOSPHATE 6 mg/mL For Suspension NDC 69097-904-43
- LANREOTIDE ACETATE 120 mg/.5mL Injection NDC 69097-906-67
- LANREOTIDE ACETATE 90 mg/.3mL Injection NDC 69097-908-67
- Leuprolide Acetate Depot Kit NDC 69097-909-50
- liraglutide 6 mg/mL Injection, Solution NDC 69097-910-55
- Atorvastatin Calcium 80 mg Tablet, Film Coated NDC 69097-911-05
- Trospium Chloride 20 mg Tablet, Film Coated NDC 69097-912-02
- omeprazole sodium bicarbonate 20 mg; 1100 mg Capsule NDC 69097-913-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lanreotide Injection is a somatostatin analog indicated for: the long-term treatment of acromegalic patients who have had an inadequate response to or cannot be treated with surgery and/or radiotherapy. ( 1.1 ) the treatment of adult patients with unresectable, well- or moderately- differentiated, locally advanced or metastatic gastroenteropancreatic neuroendocrine tumors (GEP-NETs) to improve progression-free survival. ( 1.2 ) the treatment of adults with carcinoid syndrome; when used, it reduces the frequency of short-acting somatostatin analog rescue therapy.
( 1.3 )
1.1Acromegaly Lanreotide Injection is indicated for the long-term treatment of acromegalic patients who have had an inadequate response to surgery and/or radiotherapy, or for whom surgery and/or radiotherapy is not an option. The goal of treatment in acromegaly is to reduce growth hormone (GH) and insulin growth factor-1 (IGF-1) levels to normal.
1.2Gastroenteropancreatic Neuroendocrine Tumors Lanreotide Injection is indicated for the treatment of adult patients with unresectable, well or moderately differentiated, locally advanced or metastatic gastroenteropancreatic neuroendocrine tumors (GEP-NETs) to improve progression-free survival.
1.3Carcinoid Syndrome Lanreotide Injection is indicated for the treatment of adults with carcinoid syndrome; when used, it reduces the frequency of short-acting somatostatin analog rescue therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administration ( 2.1 ): For deep subcutaneous injection only. Intended for administration by a healthcare provider. Administer in the superior external quadrant of the buttock.
Alternate injection sites. Recommended Dosage ( 2.1 ) Acromegaly: 90 mg every 4 weeks for 3 months. Adjust thereafter based on GH and/or IGF-1 levels.
See full prescribing information for titration regimen. GEP-NETs: 120 mg every 4 weeks. Carcinoid Syndrome: 120 mg every 4 weeks.
If patients are already being treated with Lanreotide Injection for GEP-NET, do not administer an additional dose for carcinoid syndrome. Dosage Adjustment: See full prescribing information for dosage adjustment in patients with acromegaly and renal or hepatic impairment. ( 2.3 , 2.4 )
2.1Important Administration Instructions For deep subcutaneous injection only. Lanreotide Injection is intended for administration by a healthcare provider. Refer to the Instructions For Use (IFU) for complete administration instructions with illustrations.
Preparation Remove Lanreotide Injection from the refrigerator 30 minutes prior to administration and allow to come to room temperature. Keep pouch sealed until just prior to injection. Product left in its sealed pouch at room temperature (not to exceed 104°F or 40°C) for up to 72 hours may be returned to the refrigerator for continued storage and use at a later time.
Prior to administration, inspect the Lanreotide Injection syringe visually for particulate matter and discoloration. Do not administer if particulate matter or discoloration is observed. The content of the prefilled syringe is a semi-solid phase having a gel-like appearance, with viscous characteristics and a color varying from white to pale yellow.
The supersaturated solution can also contain micro bubbles that can clear up during injection. These differences are normal and do not interfere with the quality of the product. Administration Slowly administer for 20 seconds as a deep subcutaneous injection in the superior external quadrant of the buttock.
Alternate the injection site between the right and left sides from one injection to the next.
2.2Recommended Dosage Acromegaly The recommended starting dosage of Lanreotide Injection is 90 mg given via the deep subcutaneous route, at 4-week intervals for 3 months. After 3 months, the dosage may be adjusted as follows: GH greater than 1 ng/mL to less than or equal to 2.5 ng/mL, IGF-1 normal, and clinical symptoms controlled: maintain Lanreotide Injection dosage at 90 mg every 4 weeks. GH greater than 2.5 ng/mL, IGF-1 elevated, and/or clinical symptoms uncontrolled: increase Lanreotide Injection dosage to 120 mg every 4 weeks.
GH less than or equal to 1 ng/mL, IGF-1 normal, and clinical symptoms controlled: reduce Lanreotide Injection dosage to 60 mg every 4 weeks. Thereafter, the dosage should be adjusted according to the response of the patient as judged by a reduction in serum GH and/or IGF-1 levels; and/or changes in symptoms of acromegaly. Patients who are controlled on Lanreotide Injection 60 or 90 mg may be considered for an extended dosing interval of Lanreotide Injection 120 mg every 6 or 8 weeks.
GH and IGF-1 levels should be obtained 6 weeks after this change in dosing regimen to evaluate persistence of patient response. Continued monitoring of patient response with dosage adjustments for biochemical and clinical symptom control, as necessary, is recommended. Gastroenteropancreatic Neuroendocrine Tumors (GEP-NETs) The recommended dosage of Lanreotide Injection is 120 mg administered every 4 weeks by deep subcutaneous injection.
Carcinoid Syndrome The recommended dosage of Lanreotide Injection is 120 mg administered every 4 weeks by deep subcutaneous injection. If patients are already being treated with Lanreotide Injection for GEP-NETs, do not administer an additional dose for the treatment of carcinoid syndrome.
2.3Dosage Adjustment in Renal Impairment Acromegaly The recommended starting dosa… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 60 mg/0.2 mL, 90 mg/0.3 mL, and 120 mg/0.5 mL sterile, single-dose, prefilled syringes fitted with an automatic needle guard. The prefilled syringes contain a white to pale yellow, semi-solid formulation. Injection: 60 mg/0.2 mL, 90 mg/0.3 mL, and 120 mg/0.5 mL single-dose prefilled syringes ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lanreotide Injection is contraindicated in patients with history of a hypersensitivity to lanreotide. Allergic reactions (including angioedema and anaphylaxis) have been reported following administration of lanreotide [see Adverse Reactions ( 6.3 )]. Hypersensitivity to lanreotide. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cholelithiasis and Complications of Cholelithiasis: Monitor periodically. Discontinue if complications of cholelithiasis are suspected. Gallstones may occur; consider periodic monitoring.
( 5.1 ) Hyperglycemia and Hypoglycemia: Glucose monitoring is recommended and antidiabetic treatment adjusted accordingly. ( 5.2 , 7.1 ) Cardiovascular Abnormalities: Decrease in heart rate may occur. Use with caution in at-risk patients.
( 5.3 ) Thyroid Function Abnormalities: Decreases in thyroid function may occur; perform tests where clinically indicated. ( 5.4 ) Steatorrhea and Malabsorption of Dietary Fats: New onset steatorrhea, stool discoloration, loose stools, abdominal bloating, and weight loss may occur. If new occurrence or worsening of these symptoms are reported, evaluate for potential pancreatic exocrine insufficiency.
( 5.6 )
5.1Cholelithiasis and Complications of Cholelithiasis Lanreotide Injection may reduce gallbladder motility and lead to gallstone formation; therefore, patients may need to be monitored periodically [see Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.2 )] . There have been postmarketing reports of cholelithiasis (gallstones) resulting in complications, including cholecystitis, cholangitis, and pancreatitis, and requiring cholecystectomy in patients taking Lanreotide Injection. If complications of cholelithiasis are suspected, discontinue Lanreotide Injection and treat appropriately.
5.2Hyperglycemia and Hypoglycemia Pharmacological studies in animals and humans show that lanreotide, like somatostatin and other somatostatin analogs, inhibits the secretion of insulin and glucagon. Hence, patients treated with Lanreotide Injection may experience hypoglycemia or hyperglycemia. Blood glucose levels should be monitored when lanreotide treatment is initiated, or when the dose is altered, and antidiabetic treatment should be adjusted accordingly [see Adverse Reactions ( 6.1 )].
5.3Cardiovascular Abnormalities The most common overall cardiac adverse reactions observed in three pooled Lanreotide Injection cardiac studies in patients with acromegaly were sinus bradycardia (12/217, 5.5%), bradycardia (6/217, 2.8%), and hypertension (12/217, 5.5%) [see Adverse Reactions ( 6.1 )]. In 81 patients with baseline heart rates of 60 beats per minute (bpm) or greater treated with Lanreotide Injection in Study 3, the incidence of heart rate less than 60 bpm was 23% (19/81) as compared to 16% (15/94) of placebo treated patients; 10 patients (12%) had documented heart rates less than 60 bpm on more than one visit.
The incidence of documented episodes of heart rate less than 50 bpm as well as the incidence of bradycardia reported as an adverse event was 1% in each treatment group. Initiate appropriate medical management in patients who develop symptomatic bradycardia. In patients without underlying cardiac disease, Lanreotide Injection may lead to a decrease in heart rate without necessarily reaching the threshold of bradycardia.
In patients suffering from cardiac disorders prior to Lanreotide Injection treatment, sinus bradycardia may occur. Care should be taken when initiating treatment with Lanreotide Injection in patients with bradycardia.
5.4Thyroid Function Abnormalities Slight decreases in thyroid function have been seen during treatment with lanreotide in acromegalic patients, though clinical hypothyroidism is rare (less than 1%). Thyroid function tests are recommended where clinically indicated.
5.5Monitoring: Laboratory Tests Acromegaly: Serum GH and IGF-1 levels are useful markers of the disease and the effectiveness of treatment [see Dosage and Administration ( 2.2 )].
5.6Steatorrhea and Malabsorption of Dietary Fats New onset steatorrhea, stool discoloration and loose stools have been reported in patients receiving somatostatin analogs, including lanreotide injection. Somatostatin analogs reversibly inhibit secretion of pancreatic enzymes and bile acids, which may result in mal… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions to Lanreotide Injection are discussed in greater detail in other sections of the labeling: Cholelithiasis and Complications of Cholelithiasis [see Warnings and Precautions ( 5.1 )] Hyperglycemia and Hypoglycemia [see Warnings and Precautions ( 5.2 )] Cardiovascular Abnormalities [see Warnings and Precautions ( 5.3 )] Thyroid Function Abnormalities [see Warnings and Precautions ( 5.4 )] Steatorrhea and Malabsorption of Dietary Fats [see Warnings and Precautions ( 5.6 )] Most common adverse reactions are: Acromegaly (>5%): diarrhea, cholelithiasis, abdominal pain, nausea and injection site reactions.
( 6.1 ) GEP-NET (>10%): abdominal pain, musculoskeletal pain, vomiting, headache, injection site reaction, hyperglycemia, hypertension, and cholelithiasis. ( 6.1 ) Carcinoid Syndrome : (≥5% and at least 5% greater than placebo): headache, dizziness and muscle spasm. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Cipla Ltd.
Inc. at 1-866-604-3268 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Acromegaly The data described below reflect exposure to Lanreotide Injection in 416 acromegalic patients in seven studies. One study was a fixed-dose pharmacokinetic study.
The other six studies were open-label or extension studies, one had a placebo-controlled, run-in period, and another had an active control. The population was mainly Caucasian (329/353, 93%) with a median age of 53 years of age (range 19 to 84 years). Fifty-four subjects (13%) were age 66 to 74 and 18 subjects (4.3%) were 75 years of age and older.
Patients were evenly matched for sex (205 males and 211 females). The median average monthly dose was 91.2 mg (e.g., 90 mg injected via the deep subcutaneous route every 4 weeks) over 385 days with a median cumulative dose of 1290 mg. Of the patients reporting acromegaly, severity at baseline (N=265), serum GH levels were less than 10 ng/mL for 69% (183/265) of the patients and 10 ng/mL or greater for 31% (82/265) of the patients.
The most commonly reported adverse reactions reported by greater than 5% of patients who received Lanreotide Injection (N=416) in the overall pooled safety studies in acromegaly patients were gastrointestinal disorders (diarrhea, abdominal pain, nausea, constipation, flatulence, vomiting, loose stools), cholelithiasis, and injection site reactions. Tables 1 and 2 present adverse reaction data from clinical studies with Lanreotide Injection in acromegalic patients. The tables include data from a single clinical study and pooled data from seven clinical studies.
Adverse Reactions in Parallel Fixed-Dose Phase of Study 1 The incidence of treatment-emergent adverse reactions for Lanreotide Injection 60, 90, and 120 mg by dose as reported during the first 4 months (fixed-dose phase) of Study 1 [see Clinical Studies ( 14.1 )] are provided in Table 1. Table 1: Adverse Reactions at an Incidence of Greater than 5% with LANREOTIDE ACETATE Overall and Occurring at Higher Rate than Placebo: Placebo-Controlled and Fixed-Dose Phase of Study 1 By Dose A patient is counted only once for each body system and preferred term.
Dictionary = WHOART. Placebo-Controlled Double-Blind Phase Weeks 0 to 4 Fixed-Dose Phase Double-Blind + Single-Blind Weeks 0 to 20 Body System Preferred Term Placebo (N=25) LANREOTIDE ACETATE Overall (N=83) LANREOTIDE ACETATE 60 mg (N=34) LANREOTIDE ACETATE 90 mg (N=36) LANREOTIDE ACETATE 120 mg (N=37) LANREOTIDE ACETATE Overall (N=107) N (%) N (%) N (%) N (%) N (%) N (%) Gastrointestinal System Disorders 1 (4%) 30 (36%) 12 (35%) 21 (58%) 27 (73%) 60 (56%) Diarrhea Abdominal pain Flatulence 0 1 (4%) 0 26 (31%) 6 (7%) 5 (6%) 9 (26%) 3 (9%) 0 (0%) 15 (42%… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Cyclosporine: Lanreotide Injection may decrease the absorption of cyclosporine. Dosage adjustment of cyclosporine may be needed. ( 7.2 ) Bromocriptine: Lanreotide Injection may increase the absorption of bromocriptine. ( 7.3 ) Bradycardia-Inducing Drugs (e.g., beta-blockers): Lanreotide Injection may decrease heart rate. Dosage adjustment of the coadministered drug may be necessary. ( 7.3 )
7.1Insulin and Oral Hypoglycemic Drugs Lanreotide, like somatostatin and other somatostatin analogs, inhibits the secretion of insulin and glucagon. Therefore, blood glucose levels should be monitored when Lanreotide Injection treatment is initiated or when the dose is altered, and antidiabetic treatment should be adjusted accordingly [see Warnings and Precautions ( 5.2 )].
7.2Cyclosporine Concomitant administration of cyclosporine with Lanreotide Injection may decrease the absorption of cyclosporine, and therefore, may necessitate adjustment of cyclosporine dose to maintain therapeutic drug concentrations. [see Clinical Pharmacology ( 12.3 )]
7.3Bromocriptine Limited published data indicate that concomitant administration of a somatostatin analog and bromocriptine may increase the absorption of bromocriptine [see Clinical Pharmacology ( 12.3 )] .
7.4Bradycardia-Inducing Drugs Concomitant administration of bradycardia-inducing drugs (e.g., beta-blockers) may have an additive effect on the reduction of heart rate associated with lanreotide. Dosage adjustments of concomitant drugs may be necessary.
7.5Drug Metabolism Interactions The limited published data available indicate that somatostatin analogs may decrease the metabolic clearance of compounds known to be metabolized by cytochrome P450 enzymes, which may be due to the suppression of growth hormone. Since it cannot be excluded that Lanreotide Injection may have this effect, avoid other drugs mainly metabolized by CYP3A4 and which have a low therapeutic index (e.g., quinidine, terfenadine). Drugs metabolized by the liver may be metabolized more slowly during Lanreotide Injection treatment and dose reductions of the concomitantly administered medications should be considered [see Clinical Pharmacology ( 12.3 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise women not to breastfeed during treatment and for 6 months after the last dose. ( 8.2 )
8.1Pregnancy Risk Summary Limited available data based on postmarketing case reports with Lanreotide Injection use in pregnant women are not sufficient to determine a drug-associated risk of adverse developmental outcomes. In animal reproduction studies, decreased embryo/fetal survival was observed in pregnant rats and rabbits at subcutaneous doses 5- and 2-times the maximum recommended human dose (MRHD) of 120 mg, respectively (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data A reproductive study in pregnant rats given 30 mg/kg of lanreotide by subcutaneous injection every 2 weeks (5 times the human dose, based on body surface area comparisons) resulted in decreased embryo/fetal survival.
A study in pregnant rabbits given subcutaneous injections of 0.45 mg/kg/day (2 times the human therapeutic exposures at the maximum recommended dose of 120 mg, based on comparisons of relative body surface area) shows decreased fetal survival and increased fetal skeletal/ soft tissue abnormalities.
8.2Lactation Risk Summary There is no information available on the presence of lanreotide in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production. Studies show that lanreotide acetate administered subcutaneously passes into the milk of lactating rats; however, due to specifies- specific differences in lactation physiology, animal data may not reliably predict drug levels in human milk . Because of the potential for serious adverse reactions in breastfed infants from Lanreotide Injection, including effects on glucose metabolism and bradycardia, advise women not to breastfeed during treatment with Lanreotide Injection and for 6 months (6 half-lives) following the last dose.
8.3Females and Males of Reproductive Potential Infertility Females Based on results from animal studies conducted in female rats, Lanreotide Injection may reduce fertility in females of reproductive potential [see Nonclinical Toxicology ( 13.1 )].
8.4Pediatric Use The safety and effectiveness of Lanreotide Injection in pediatric patients have not been established.
8.5Geriatric Use No overall differences in safety or effectiveness were observed between elderly patients with acromegaly compared with younger patients and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Studies 3 and 4, conducted in patients with neuroendocrine tumors, did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
8.6Renal Impairment Acromegaly Lanreotide has been studied in patients with end-stage renal function on dialysis, but has not been studied in patients with mild, moderate, or severe renal impairment. It is recommended that patients with moderate or severe renal impairment receive a starting dose of lanreotide of 60 mg. Caution should be exercised when considering patients with moderate or severe renal impairment for an extended dosing interval of Lanreotide Injection… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data based on postmarketing case reports with Lanreotide Injection use in pregnant women are not sufficient to determine a drug-associated risk of adverse developmental outcomes. In animal reproduction studies, decreased embryo/fetal survival was observed in pregnant rats and rabbits at subcutaneous doses 5- and 2-times the maximum recommended human dose (MRHD) of 120 mg, respectively (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data A reproductive study in pregnant rats given 30 mg/kg of lanreotide by subcutaneous injection every 2 weeks (5 times the human dose, based on body surface area comparisons) resulted in decreased embryo/fetal survival.
A study in pregnant rabbits given subcutaneous injections of 0.45 mg/kg/day (2 times the human therapeutic exposures at the maximum recommended dose of 120 mg, based on comparisons of relative body surface area) shows decreased fetal survival and increased fetal skeletal/ soft tissue abnormalities.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Lanreotide Injection in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety or effectiveness were observed between elderly patients with acromegaly compared with younger patients and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Studies 3 and 4, conducted in patients with neuroendocrine tumors, did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lanreotide, the active component of Lanreotide acetate is an octapeptide analog of natural somatostatin. The mechanism of action of lanreotide is believed to be similar to that of natural somatostatin.
12.2Pharmacodynamics Lanreotide has a high affinity for human somatostatin receptors (SSTR) 2 and 5 and a reduced binding affinity for human SSTR1, 3, and 4. Activity at human SSTR2 and 5 is the primary mechanism believed responsible for GH inhibition. Like somatostatin, lanreotide is an inhibitor of various endocrine, neuroendocrine, exocrine, and paracrine functions.
The primary pharmacodynamic effect of lanreotide is a reduction of GH and/or IGF-1 levels enabling normalization of levels in acromegalic patients [see Clinical Studies ( 14.1 )] . In acromegalic patients, lanreotide reduces GH levels in a dose-dependent way. After a single injection of Lanreotide acetate, plasma GH levels fall rapidly and are maintained for at least 28 days.
Lanreotide inhibits the basal secretion of motilin, gastric inhibitory peptide, and pancreatic polypeptide, but has no significant effect on the secretion of secretin. Lanreotide inhibits postprandial secretion of pancreatic polypeptide, gastrin, and cholecystokinin (CCK). In healthy subjects, lanreotide produces a reduction and a delay in postprandial insulin secretion, resulting in transient, mild glucose intolerance.
Lanreotide inhibits meal-stimulated pancreatic secretions, and reduces duodenal bicarbonate and amylase concentrations, and produces a transient reduction in gastric acidity. Lanreotide has been shown to inhibit gallbladder contractility and bile secretion in healthy subjects [see Warnings and Precautions ( 5.1 )] . In healthy subjects, lanreotide inhibits meal-induced increases in superior mesenteric artery and portal venous blood flow, but has no effect on basal or meal-stimulated renal blood flow.
Lanreotide has no effect on renal plasma flow or renal vascular resistance. However, a transient decrease in glomerular filtration rate (GFR) and filtration fraction has been observed after a single injection of lanreotide. In healthy subjects, non-significant reductions in glucagon levels were seen after lanreotide administration.
In diabetic non-acromegalic subjects receiving a continuous infusion (21-day) of lanreotide, serum glucose concentrations were temporarily decreased by 20% to 30% after the start and end of the infusion. Serum glucose concentrations returned to normal levels within 24 hours. A significant decrease in insulin concentrations was recorded between baseline and Day 1 only [see Warnings and Precautions ( 5.2 )] .
Lanreotide inhibits the nocturnal increase in thyroid-stimulating hormone (TSH) seen in healthy subjects. Lanreotide reduces prolactin levels in acromegalic patients treated on a long-term basis [see Warnings and Precautions ( 5.4 )] .
12.3Pharmacokinetics Lanreotide acetate is thought to form a drug depot at the injection site due to the interaction of the formulation with physiological fluids. The most likely mechanism of drug release is a passive diffusion of the precipitated drug from the depot towards the surrounding tissues, followed by the absorption to the bloodstream. After a single, deep subcutaneous administration, the mean absolute bioavailability of Lanreotide acetate in healthy subjects was 73.4, 69.0, and 78.4% for the 60 mg, 90 mg, and 120 mg doses, respectively.
Mean C max values ranged from 4.3 to 8.4 ng/mL during the first day. Single-dose linearity was demonstrated with respect to AUC and C max , and showed high inter-subject variability. Lanreotide acetate showed sustained release of lanreotide with a half-life of 23 to 30 days.
Mean serum concentrations were > 1 ng/mL throughout 28 days at 90 mg and 120 mg and > 0.9 ng/mL at 60 mg. In studies evaluating excretion, <5% of lanreotide was excreted in urine and less than 0.5% was recovered unchanged in feces, indicative of some bil… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lanreotide, the active component of Lanreotide acetate is an octapeptide analog of natural somatostatin. The mechanism of action of lanreotide is believed to be similar to that of natural somatostatin.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Lanreotide Injection is supplied in strengths of 60 mg/0.2 mL, 90 mg/0.3 mL, and 120 mg/0.5 mL as a white to pale yellow, semi-solid formulation in a single, sterile, prefilled, ready-to-use, polypropylene syringe (fitted with an automatic needle guard) fitted with a 20 mm needle covered by a sheath. Each prefilled syringe is sealed in a laminated pouch and packed in a carton. NDC 69097-907-67 60 mg/0.2 mL, sterile, prefilled syringe NDC 69097-908-67 90 mg/0.3 mL, sterile, prefilled syringe NDC 69097-906-67 120 mg/0.5 mL, sterile, prefilled syringe Storage and Handling Store Lanreotide Injection in the refrigerator at 2°C to 8°C (36°F to 46°F).
Protect from light. Store in the original package.
📋 Description ▾
11 DESCRIPTION Lanreotide Injection 60 mg/0.2 mL, 90 mg/0.3 mL, and 120 mg/0.5 mL is a prolonged-release formulation for deep subcutaneous injection. It contains the drug substance lanreotide acetate, a synthetic octapeptide with a biological activity similar to naturally occurring somatostatin, water for injection and acetic acid (for pH adjustment). Lanreotide Injection is available as sterile, ready-to-use, single-dose prefilled syringes containing lanreotide acetate supersaturated bulk solution of 24.6% w/w lanreotide base.
Each syringe contains: LANREOTIDE ACETATE LANREOTIDE ACETATE LANREOTIDE ACETATE 60 mg/0.2 mL 90 mg/0.3 mL 120 mg/0.5 mL Lanreotide acetate 74.9 mg 108.2 mg 141.5 mg Acetic Acid q.s. q.s. q.s. Water for injection 196.8 mg 284.5 mg 372.1 mg Total Weight 273.9 mg 395.9 mg 517.8 mg Lanreotide acetate is a synthetic cyclical octapeptide analog of the natural hormone, somatostatin. Lanreotide acetate is chemically known as [cyclo S-S]-3-(2-naphthyl)-D-alanyl-L-cysteinyl-L- tyrosyl-D-tryptophyl-L-lysyl-L-valyl-L-cysteinyl-L-threoninamide, acetate salt.
Its molecular weight is 1096.34 (base) and its amino acid sequence is: The Lanreotide Injection in the prefilled syringe is a white to pale yellow, semi-solid formulation. structure
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Lanreotide acetate is thought to form a drug depot at the injection site due to the interaction of the formulation with physiological fluids. The most likely mechanism of drug release is a passive diffusion of the precipitated drug from the depot towards the surrounding tissues, followed by the absorption to the bloodstream. After a single, deep subcutaneous administration, the mean absolute bioavailability of Lanreotide acetate in healthy subjects was 73.4, 69.0, and 78.4% for the 60 mg, 90 mg, and 120 mg doses, respectively.
Mean C max values ranged from 4.3 to 8.4 ng/mL during the first day. Single-dose linearity was demonstrated with respect to AUC and C max , and showed high inter-subject variability. Lanreotide acetate showed sustained release of lanreotide with a half-life of 23 to 30 days.
Mean serum concentrations were > 1 ng/mL throughout 28 days at 90 mg and 120 mg and > 0.9 ng/mL at 60 mg. In studies evaluating excretion, <5% of lanreotide was excreted in urine and less than 0.5% was recovered unchanged in feces, indicative of some biliary excretion. Acromegaly In a repeat-dose administration pharmacokinetics (PK) study in acromegalic patients, rapid initial release was seen giving peak levels during the first day after administration.
At doses of Lanreotide acetate between 60 and 120 mg, linear pharmacokinetics were observed in acromegalic patients. At steady state, mean C max values were 3.8 ± 0.5, 5.7 ± 1.7, and 7.7 ± 2.5 ng/mL, increasing linearly with dose. The mean accumulation ratio index was 2.7, which is in line with the range of values for the half-life of Lanreotide acetate.
The steady- state trough serum lanreotide concentrations in patients receiving Lanreotide acetate every 28 days were 1.8 ± 0.3; 2.5 ± 0.9 and 3.8 ± 1.0 ng/mL at 60 mg, 90 mg, and 120 mg doses, respectively. A limited initial burst effect and a low peak-to-trough fluctuation (81% to 108%) of the serum concentration at the plateau were observed. For the same doses, similar values were obtained in clinical studies after at least four administrations (2.3 ± 0.9, 3.2 ± 1.1, and 4.0 ± 1.4 ng/mL, respectively).
Pharmacokinetic data from studies evaluating extended dosing use of Lanreotide Injection 120 mg demonstrated mean steady-state, C min values between 1.6 and 2.3 ng/mL for the 8- and 6-week treatment interval, respectively. Gastroenteropancreatic Neuroendocrine Tumors In patients with GEP-NETs treated with Lanreotide Injection 120 mg every 4 weeks, steady state concentrations were reached after 4 to 5 injections and the mean trough serum lanreotide concentrations at steady state ranged from 5.3 to 8.6 ng/mL. Specific Populations Lanreotide Injection has not been studied in specific populations.
However, the pharmacokinetics of lanreotide in renal impaired, hepatic impaired, and geriatric subjects were evaluated after IV administration of lanreotide immediate release formulation (IRF) at 7 mcg/kg dose. Geriatric Studies in healthy elderly subjects showed an 85% increase in half-life and a 65% increase in mean residence time (MRT) of lanreotide compared to those seen in healthy young subjects; however, there was no change in either AUC or C max of lanreotide in elderly as compared to healthy young subjects. Age has no effect on clearance of lanreotide based on population PK analysis in patients with GEP-NET which included 122 patients aged 65 to 85 years with neuroendocrine tumors.
Renal Impairment An approximate 2-fold decrease in total serum clearance of lanreotide, with a consequent 2 fold increase in half-life and AUC was observed. Patients with acromegaly and with moderate to severe renal impairment should begin treatment with Lanreotide Injection 60 mg. Caution should be exercised when considering patients with moderate or severe renal impairment for an extended dosing interval of Lanreotide Injection 120 mg every 6 or 8 weeks.
Mild (CLcr 60-89 mL/min) or moderate (CLcr 30-59 mL/min) renal impairment has no e… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Lanreotide has a high affinity for human somatostatin receptors (SSTR) 2 and 5 and a reduced binding affinity for human SSTR1, 3, and 4. Activity at human SSTR2 and 5 is the primary mechanism believed responsible for GH inhibition. Like somatostatin, lanreotide is an inhibitor of various endocrine, neuroendocrine, exocrine, and paracrine functions.
The primary pharmacodynamic effect of lanreotide is a reduction of GH and/or IGF-1 levels enabling normalization of levels in acromegalic patients [see Clinical Studies ( 14.1 )] . In acromegalic patients, lanreotide reduces GH levels in a dose-dependent way. After a single injection of Lanreotide acetate, plasma GH levels fall rapidly and are maintained for at least 28 days.
Lanreotide inhibits the basal secretion of motilin, gastric inhibitory peptide, and pancreatic polypeptide, but has no significant effect on the secretion of secretin. Lanreotide inhibits postprandial secretion of pancreatic polypeptide, gastrin, and cholecystokinin (CCK). In healthy subjects, lanreotide produces a reduction and a delay in postprandial insulin secretion, resulting in transient, mild glucose intolerance.
Lanreotide inhibits meal-stimulated pancreatic secretions, and reduces duodenal bicarbonate and amylase concentrations, and produces a transient reduction in gastric acidity. Lanreotide has been shown to inhibit gallbladder contractility and bile secretion in healthy subjects [see Warnings and Precautions ( 5.1 )] . In healthy subjects, lanreotide inhibits meal-induced increases in superior mesenteric artery and portal venous blood flow, but has no effect on basal or meal-stimulated renal blood flow.
Lanreotide has no effect on renal plasma flow or renal vascular resistance. However, a transient decrease in glomerular filtration rate (GFR) and filtration fraction has been observed after a single injection of lanreotide. In healthy subjects, non-significant reductions in glucagon levels were seen after lanreotide administration.
In diabetic non-acromegalic subjects receiving a continuous infusion (21-day) of lanreotide, serum glucose concentrations were temporarily decreased by 20% to 30% after the start and end of the infusion. Serum glucose concentrations returned to normal levels within 24 hours. A significant decrease in insulin concentrations was recorded between baseline and Day 1 only [see Warnings and Precautions ( 5.2 )] .
Lanreotide inhibits the nocturnal increase in thyroid-stimulating hormone (TSH) seen in healthy subjects. Lanreotide reduces prolactin levels in acromegalic patients treated on a long-term basis [see Warnings and Precautions ( 5.4 )] .
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Acromegaly The effect of Lanreotide Injection on reducing GH and IGF-levels and control of symptoms in patients with acromegaly was studied in 2 long-term, multiple-dose, randomized, multicenter studies. Study 1 This 1-year study included a 4-week, double-blind, placebo-controlled phase; a 16-week single-blind, fixed-dose phase; and a 32-week, open-label, dose-titration phase. Patients with active acromegaly, based on biochemical tests and medical history, entered a 12-week washout period if there was previous treatment with a somatostatin analog or a dopaminergic agonist.
Upon entry, patients were randomly allocated to receive a single, deep subcutaneous injection of Lanreotide Injection 60, 90, or 120 mg or placebo. Four weeks later, patients entered a fixed-dose phase where they received 4 injections of Lanreotide Injection followed by a dose-titration phase of 8 injections for a total of 13 injections over 52 weeks (including the placebo phase). Injections were given at 4-week intervals.
During the dose-titration phase of the study, the dose was titrated twice (every fourth injection), as needed, according to individual GH and IGF-1 levels. A total of 108 patients (51 males, 57 females) were enrolled in the initial placebo-controlled phase of the study. Half (54/108) of the patients had never been treated with a somatostatin analog or dopamine agonist, or had stopped treatment for at least 3 months prior to their participation in the study and were required to have a mean GH level greater than 5 ng/mL at their first visit.
The other half of the patients had received prior treatment with a somatostatin analog or a dopamine agonist before study entry and at study entry were required to have a mean GH concentration greater than 3 ng/mL and at least a 100% increase in mean GH concentration after washout of medication. One hundred and seven (107) patients completed the placebo-controlled phase, 105 patients completed the fixed-dose phase, and 99 patients completed the dose-titration phase. Patients not completing withdrew due to adverse events (5) or lack of efficacy (4).
In the double-blind phase of Study 1, a total of 52 (63%) of the 83 lanreotide-treated patients had a greater than 50% decrease in mean GH from baseline to Week 4, including 52%, 44%, and 90% of patients in the 60, 90, and 120 mg groups, respectively, compared to placebo (0%, 0/25). In the fixed- dose phase at Week 16, 72% of all 107 lanreotide-treated patients had a decrease from baseline in mean GH of greater than 50%, including 68% (23/34), 64% (23/36), and 84% (31/37) of patients in the 60, 90, and 120 mg lanreotide treatment groups, respectively.
Efficacy achieved in the first 16 weeks was maintained for the duration of the study (see Table 4). Table 4: Overall Efficacy Results Based on GH and IGF-1 Levels by Treatment Phase in Study 1 1 n=105, 2 n=102, 3 Age-adjusted *Last Observation Carried Forward Baseline N=107 Before Titration 1 (16 weeks) N=107 Before Titration 2 (32 weeks) N=105 Last Value Available* N=107 GH ≤5.0 ng/mL Number of Responders (%) 20 (19%) 72 (67%) 76 (72%) 74 (69%) ≤2.5 ng/mL Number of Responders (%) 0 (0%) 52 (49%) 59 (56%) 55 (51%) ≤1.0 ng/mL Number of Responders (%) 0 (0%) 15 (14%) 18 (17%) 17 (16%) Median GH ng/mL 10.27 2.53 2.20
2.43GH Reduction Median % Reduction - 75.5 78.2
75.5IGF-1 Normal 3 Number of Responders (%) 9 (8%) 58 (54%) 57 (54%) 62 (58%) Median IGF-1 ng/mL 775.0 332.0 1 316.5 2 326.0 IGF-1 Reduction Median % Reduction - 52.3 1 54.5 2
55.4IGF-1 Normal 3 + GH ≤2.5 ng/mL Number of Responders (%) 0 (0%) 41 (38%) 46 (44%) 44 (41%) Study 2 This was a 48-week, open-label, uncontrolled, multicenter study that enrolled patients who had an IGF- 1 concentration 1.3 times or greater than the upper limit of the normal age- adjusted range. Patients receiving treatment with a somatostatin analog (other than Lanreotide Injection) or a dopaminergic agonist had to attain this IGF-1 concentration after a… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Standard lifetime carcinogenicity bioassays were conducted in mice and rats. Mice were given daily subcutaneous doses of lanreotide at 0.5, 1.5, 5, 10, and 30 mg/kg for 104 weeks. Cutaneous and subcutaneous tumors of fibrous connective tissues at the injection sites were observed at the high dose of 30 mg/kg/day.
Fibrosarcomas in both genders and malignant fibrous histiocytomas were observed in males at 30 mg/kg/day resulting in exposures 3 times higher than the clinical therapeutic exposure at the maximum therapeutic dose of 120 mg given by monthly subcutaneous injection based on the AUC values. Rats were given daily subcutaneous doses of lanreotide at 0.1, 0.2, and 0.5 mg/ kg for 104 weeks. Increased cutaneous and subcutaneous tumors of fibrous connective tissues at the injection sites were observed at the dose of 0.5 mg/kg/day resulting in exposures less than the clinical therapeutic exposure at 120 mg given by monthly subcutaneous injection.
The increased incidence of injection site tumors in rodents is likely related to the increased dosing frequency (daily) in animals compared to monthly dosing in humans and therefore may not be clinically relevant. Lanreotide was not genotoxic in tests for gene mutations in a bacterial mutagenicity (Ames) assay, or mouse lymphoma cell assay with or without metabolic activation. Lanreotide was not genotoxic in tests for the detection of chromosomal aberrations in a human lymphocyte and in vivo mouse micronucleus assay.
In a fertility study conducted with lanreotide in rats, reduced female fecundity was observed at estimated exposure corresponding to approximately 10-fold the plasma exposure at the MRHD of 120 mg. The fertility of male rats was unaffected by the treatment up to an estimated exposure corresponding to approximately 11-fold the plasma exposure at the MRHD of 120 mg.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Standard lifetime carcinogenicity bioassays were conducted in mice and rats. Mice were given daily subcutaneous doses of lanreotide at 0.5, 1.5, 5, 10, and 30 mg/kg for 104 weeks. Cutaneous and subcutaneous tumors of fibrous connective tissues at the injection sites were observed at the high dose of 30 mg/kg/day.
Fibrosarcomas in both genders and malignant fibrous histiocytomas were observed in males at 30 mg/kg/day resulting in exposures 3 times higher than the clinical therapeutic exposure at the maximum therapeutic dose of 120 mg given by monthly subcutaneous injection based on the AUC values. Rats were given daily subcutaneous doses of lanreotide at 0.1, 0.2, and 0.5 mg/ kg for 104 weeks. Increased cutaneous and subcutaneous tumors of fibrous connective tissues at the injection sites were observed at the dose of 0.5 mg/kg/day resulting in exposures less than the clinical therapeutic exposure at 120 mg given by monthly subcutaneous injection.
The increased incidence of injection site tumors in rodents is likely related to the increased dosing frequency (daily) in animals compared to monthly dosing in humans and therefore may not be clinically relevant. Lanreotide was not genotoxic in tests for gene mutations in a bacterial mutagenicity (Ames) assay, or mouse lymphoma cell assay with or without metabolic activation. Lanreotide was not genotoxic in tests for the detection of chromosomal aberrations in a human lymphocyte and in vivo mouse micronucleus assay.
In a fertility study conducted with lanreotide in rats, reduced female fecundity was observed at estimated exposure corresponding to approximately 10-fold the plasma exposure at the MRHD of 120 mg. The fertility of male rats was unaffected by the treatment up to an estimated exposure corresponding to approximately 11-fold the plasma exposure at the MRHD of 120 mg.
📄 Patient Package Insert ▾
Patient Information Lanreotide (lan-REE-oh-tide) (lanreotide) injection Read this Patient Information before you receive your first Lanreotide Injection and before each injection. There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or your treatment.
What is Lanreotide injection? Lanreotide injection is a prescription medicine used for: the long-term treatment of people with acromegaly when: surgery or radiotherapy have not worked well enough or they are not able to have surgery or radiotherapy. the treatment of adults with a type of cancer known as neuroendocrine tumors, from the gastrointestinal tract or the pancreas (GEP-NETs) that has spread or cannot be removed by surgery. the treatment of adults with carcinoid syndrome to reduce the need for the use of short-acting somatostatin medicine It is not known if Lanreotide injection is safe and effective in children.
Who should not receive Lanreotide injection? Do not receive Lanreotide injection if you are allergic to lanreotide. What should I tell my healthcare provider before receiving Lanreotide Injection?
Before you receive Lanreotide Injection, tell your healthcare provider about all of your medical conditions, including if you: have gallbladder problems have diabetes have heart problems have thyroid problems have kidney problems have liver problems are pregnant or plan to become pregnant. It is not known if Lanreotide injection will harm your unborn baby are breastfeeding or plan to breastfeed. It is not known if Lanreotide Injection passes into your breast milk.
You should not breastfeed if you receive Lanreotide Injection and for 6 months after your last dose of Lanreotide Injection are a female who can become pregnant. Lanreotide Injection may affect fertility in females and may affect your ability to become pregnant. Talk to your healthcare provider if this is a concern for you Tell your healthcare provider about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements.
Lanreotide Injection and other medicines may affect each other, causing side effects. Lanreotide Injection may affect the way other medicines work, and other medicines may affect how Lanreotide Injection works. Your dose of Lanreotide Injection or your other medicines may need to be changed.
Especially tell your healthcare provider if you take: insulin or other diabetes medicines cyclosporine (Gengraf, Neoral, or Sandimmune) medicines that lower your heart rate such as beta blockers How will I receive Lanreotide injection? You will receive a Lanreotide Injection every 4 weeks in your healthcare provider’s office Your healthcare provider may change your dose of Lanreotide Injection or the length of time between your injections. Your healthcare provider will tell you how long you need to receive Lanreotide Injection Lanreotide Injection is injected deep under the skin of the upper outer area of your buttock.
Your injection site should change (alternate) between your right and left buttock from one injection of Lanreotide Injection to the next During your treatment with Lanreotide Injection for acromegaly, your healthcare provider may do certain blood tests to see if Lanreotide Injection is working What should I avoid while receiving Lanreotide injection? Lanreotide injection can cause dizziness. If you have dizziness, do not drive a car or operate machinery.
What are the possible side effects of Lanreotide Injection? Lanreotide Injection may cause serious side effects, including: Gallstones (cholelithiasis) and complications that can happen if you have gallstones. Gallstones are a serious but common side effect in people who take Lanreotide Injection and have acromegaly and GEP-NET.
Your healthcare provider may check your gallbladder before and during treatment with Lanreotide Injection. Possible complications of gallstones include inflammation and infectio… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE IMPORTANT If you have any questions about this medication or procedure, call 1-866- 604-3268. Before You Begin Injection 1. Please read both sides of these Instructions for Use before using the pre-filled syringe.
FOLLOW THIS PROCEDURE EXACTLY, AS IT MAY DIFFER FROM YOUR PAST EXPERIENCE. 2. Lanreotide Injection should be administered by a Healthcare Professional.
3. If this pre-filled syringe is dropped or damaged in any way, please contact 1-866-604-3268 . A.
Storage of Lanreotide Injection When you receive the medication, follow these steps for storing Lanreotide Injection. Important: Lanreotide Injection MUST BE REFRIGERATED. DO NOT ALLOW IT TO REACH ROOM TEMPERATURE UNTIL READY TO USE.
A1. Remove box from cold pack. Do not open box.
A2. Check the following: a. Box does not look damaged b.
Expiration date has not passed. c. Dose is as prescribed 60 mg, or 90 mg, or 120 mg Note: Call 1-866-604-3268 if you have any questions. A3.
Place unopened box in your refrigerator. DO NOT PLACE IN FREEZER. B.
Prepare to Inject B1. Confirm that date of this injection is as prescribed. B2.
Remove box from refrigerator. Open box and remove contents. B3.
Confirm that pouch is sealed and not damaged. B4. Check that the dose is as prescribed and the expiration date has not passed.
B5. Let pouch sit for 30 MINUTES to reach room temperature. or DO NOT OPEN the pouch until ready to inject. Injection of cold medication may be painful.
Note: Product left in its sealed pouch at room temperature (not to exceed 104° F or 40 °C) for up to 72 hours may be returned to the refrigerator for continued storage and use at a later time. B6. Find a clean, comfortable area for the patient to relax during procedure.
It’s important that the patient remains as still as possible during the injection. B7. The person administering the injection must wash his/her hands with soap and water.
Follow the doctor or institution’s policy on the use of surgical gloves during this procedure. B8. Tear open pouch along dotted line starting at the notch.
B9. Do the following: a. Prior to administration, inspect the LANREOTIDE INJECTION syringe visually for particulate matter and discoloration.
Do not administer if particulate matter or discoloration is observed. The content of the prefilled syringe is a semi-solid phase having a gel-like appearance, with viscous characteristics and a color varying from white to pale yellow. The supersaturated solution can also contain micro bubbles that can clear up during injection.
These differences are normal and do not interfere with the quality of the product. b. Confirm that expiration date on the prefilled syringe has not passed. c. Make sure it is the right dosage: 60 mg, or 90 mg, or 120 mg. d.
Set device aside on the empty pouch. Note: Call 1-866-604-3268 if you have any questions. B10.
Choose which side of the buttocks to inject. Switch sides with each injection. Avoid areas with moles, scar tissue, reddened skin, or skin that feels bumpy.
Important: ONLY inject in one of the areas marked OK in the picture (upper outer quadrants of the right or left buttocks). B11. Clean area to be injected.
C. Inject Important: This is a single-use pre-filled syringe with a retractable needle. ALL the medication must be injected during this use.
If you drop or damage this pre-filled syringe in any way, please call 1-866-604-3268. Follow these injection instructions exactly! This procedure may be different from your past experience.
C1. BEFORE injecting, REMOVE the pre-filled syringe from its tray. Discard tray.
C2. REMOVE NEEDLE CAP HOLD PRE-FILLED SYRINGE BY THE SYRINGE BODY and PULL OFF the needle cap to remove it. DO NOT HOLD the pre-filled syringe by the plunger.
Discard needle cap. C3. Hold pre-filled syringe by the syringe body.
The pre-filled syringe is now ready for injection. C4. FLATTEN injection area using the thumb and index finger of your other hand to stretch the skin.
DO NOT pinch skin. C5. Insert needle PERPENDICULA… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings & Precautions, Steatorrhea and Malabsorption of Dietary Fats ( 5.6 ) 07/2024
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Rx Only NDC 69097-907-67 Lanreotide Injection 60 mg*/0.2 mL For deep subcutaneous injection For Single dose only. Discard unused portion. Lanreotide Injection should be administered by a healthcare professional.
Leave at room temperature for 30 minutes before administration. Cipla Carton Label Pouch Label Pouch Sticker Label Syringe Label Rx Only NDC 69097-908-67 Lanreotide Injection 90 mg*/0.3 mL For deep subcutaneous injection For Single dose only. Discard unused portion.
Lanreotide Injection should be administered by a healthcare professional. Leave at room temperature for 30 minutes before administration. Cipla Carton Label Pouch Label Pouch Sticker Label Syringe Label Rx Only NDC 69097-906-67 Lanreotide Injection 120 mg*/0.5 mL For deep subcutaneous injection For Single dose only.
Discard unused portion. Lanreotide Injection should be administered by a healthcare professional. Leave at room temperature for 30 minutes before administration.
Cipla Carton Label Pouch Label Pouch Sticker Label Syringe Label carton label_60mg pouch label_60mg pouch sticker label_60mg syringe label_60mg carton label_90mg pouch label_90mg pouch sticker label_90mg syringe label_90mg carton label_120mg pouch label_120mg pouch sticker label_120mg syringe label_120mg
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |