
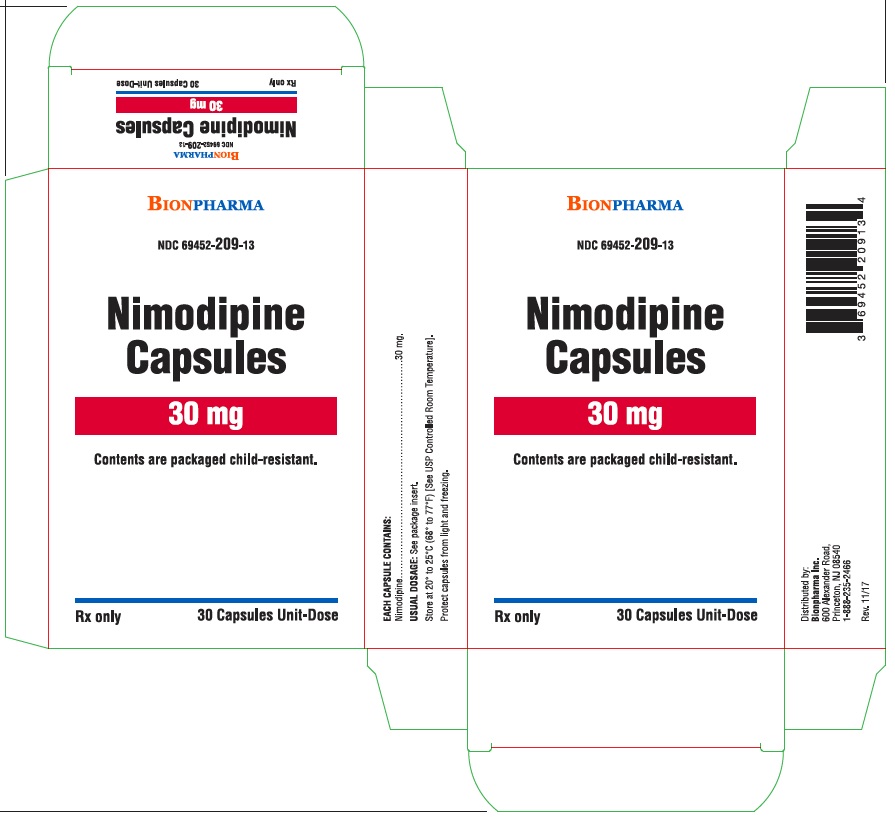
Nimodipine 30 mg Capsule, Liquid Filled — NDC 69452-209-13 (Billing 69452-0209-13)
This is a package of Nimodipine 30 mg Capsule, Liquid Filled from BIONPHARMA INC., marketed since Nov 2017 and currently FDA-listed; retail pharmacies pay about $1.37 per unit (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 69452-209-13 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 69452 labeler · 209 product · 13 package
- Package marketed since
- Nov 21, 2017
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6945220913 4
- Medicaid fills, this package
- 184 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 000579
- GCN: 02440
- GPI-14 (Medi-Span): 34000022000120
- HICL (First Databank): 000184
- AHFS class code: 24:28.08.00
- RxCUI (RxNorm): 198037
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Nimodipine is used to decrease brain damage that may be caused by a subarachnoid hemorrhage (bleeding in the space surrounding the brain that occurs when a weakened blood vessel in the brain bursts). Nimodipine is in a class of medications called calcium channel blockers. It works by relaxing blood vessels in the brain to allow more blood to flow to damaged areas.
Read the full MedlinePlus article ↗- Nimodipine is given specifically after a subarachnoid hemorrhage — that's when an aneurysm in the brain ruptures and bleeds into the space around the brain. After that kind of blee...
- What exactly is nimodipine being used for in my (or my family member's) care?
- It's a lot, yes — and there's a real pharmacological reason. Nimodipine is eliminated from the body relatively quickly, so blood levels drop fast between doses. Taking it every 4 h...
- Why does it have to be taken every 4 hours? That's a lot.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nimodipine — tap one for details:
Nimodipine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.370 | $41.09 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | $1.74 | $52.27 / 30 capsules |
| Medicare drug plans payPart D · Q2 2026 | $2.28 | $68.46 / 30 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 69452-0209-13 You're viewing this Main listing | 3 BLISTER PACK in 1 CARTON / 10 CAPSULE, LIQUID FILLED in 1 BLISTER PACK | $1.37 / ea | $41.08 | 2017-11-21 | — | Active |
| 69452-0209-20 69452-209-20 | 10 BLISTER PACK in 1 CARTON / 10 CAPSULE, LIQUID FILLED in 1 BLISTER PACK | $1.37 / ea | $136.95 | 2017-11-21 | — | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($1.37 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 69% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Nimodipine 30 mg Capsule, Liquid Filled?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| nimodipine 30 mg 23155-0512-00 | Heritage | 10 capsules | $1.369 | AB | Availability likely | — |
| Nimodipine 30 mgthis 69452-0209-13 | BIONPHARMA | 10 capsules | $1.369 | AB | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Nimodipine inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII AV092KU4JH
A natural oil extracted from peppermint plants. It's used as a flavoring agent to mask bitter tastes and add a refreshing mint flavor to medicines, making them easier to take.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from BIONPHARMA INC. labeler code 69452
- ivabradine 5 mg Tablet, Film Coated NDC 69452-190-17
- ivabradine 7.5 mg Tablet, Film Coated NDC 69452-191-17
- Ibuprofen, Diphenhydramine HCl 200 mg; 25 mg Capsule, Liquid Filled NDC 69452-205-04
- Doxylamine succinate and Pyridoxine hydrochloride 10 mg; 10 mg Tablet, Delayed Release NDC 69452-206-20
- Calcitriol .25 ug Capsule, Liquid Filled NDC 69452-207-13
- Calcitriol .5 ug Capsule, Liquid Filled NDC 69452-208-13
- Loperamide hydrochloride and Simethicone 2 mg; 125 mg Tablet NDC 69452-210-04
- Loratadine 10 mg Capsule, Liquid Filled NDC 69452-211-03
- Ibuprofen 200 mg Capsule, Liquid Filled NDC 69452-212-90
- Rufinamide 40 mg/mL Suspension NDC 69452-223-84
- Progesterone 100 mg Capsule NDC 69452-233-20
- Progesterone 200 mg Capsule NDC 69452-234-20
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
DO NOT ADMINISTER NIMODIPINE INTRAVENOUSLY OR BY OTHER PARENTERAL ROUTES. DEATHS AND SERIOUS, LIFE THREATENING ADVERSE EVENTS HAVE OCCURRED WHEN THE CONTENTS OF NIMODIPINE CAPSULES HAVE BEEN INJECTED PARENTERALLY (See WARNINGS and DOSAGE AND ADMINISTRATION).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Nimodipine is indicated for the improvement of neurological outcome by reducing the incidence and severity of ischemic deficits in patients with subarachnoid hemorrhage from ruptured intracranial berry aneurysms regardless of their post-ictus neurological condition (i.e., Hunt and Hess Grades I-V).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION DO NOT ADMINISTER NIMODIPINE CAPSULES INTRAVENOUSLY OR BY OTHER PARENTERAL ROUTES (see WARNINGS ). If Nimodipine is inadvertently administered intravenously, clinically significant hypotension may require cardiovascular support with pressor agents. Specific treatments for calcium channel blocker overdose should also be given promptly.
Nimodipine is given orally in the form of soft gelatin 30 mg capsules for subarachnoid hemorrhage. The recommended oral dose is 60 mg (two 30 mg capsules) every 4 hours for 21 consecutive days. In general, the capsules should be swallowed whole with a little liquid, preferably not less than one hour before or two hours after meals.
Grapefruit juice is to be avoided (See PRECAUTIONS, Drug Interactions ). Oral nimodipine therapy should commence as soon as possible within 96 hours of the onset of subarachnoid hemorrhage. If the capsule cannot be swallowed, e.g., at the time of surgery, or if the patient is unconscious, a hole should be made in both ends of the capsule with an 18 gauge needle, and the contents of the capsule extracted into a syringe.
A parenteral syringe can be used to extract the liquid inside the capsule, but the liquid should always be transferred to a syringe that cannot accept a needle and that is designed for administration orally or via a naso-gastric tube or PEG. To help minimize administration errors, it is recommended that the syringe used for administration be labeled “Not for IV Use”. The contents should then be emptied into the patient’s in situ naso-gastric tube and washed down the tube with 30 mL of normal saline (0.9%).
Severely disturbed liver function, particularly liver cirrhosis, may result in an increased bioavailability of nimodipine due to a decreased first pass capacity and a reduced metabolic clearance. The reduction in blood pressure and other adverse effects may be more pronounced in these patients. Dosage should be reduced to one 30 mg capsule every 4 hours with close monitoring of blood pressure and heart rate; if necessary, discontinuation of the treatment should be considered.
Strong inhibitors of CYP3A4 should not be administered concomitantly with nimodipine (See CONTRAINDICATIONS ). Strong inducers of CYP3A4 should generally not be administered with nimodipine (See WARNINGS ). Patients on moderate and weak inducers of CYP3A4 should be closely monitored for lack of effectiveness, and a nimodipine dose increase may be required.
Patients on moderate and weak CYP3A4 inhibitors may require a nimodipine dose reduction in case of hypotension (See PRECAUTIONS, Drug Interactions ).
⛔ Contraindications ▾
CONTRAINDICATIONS The concomitant use of nimodipine with strong inhibitors of CYP3A4 such as some macrolide antibiotics (e.g., clarithromycin, telithromycin), some anti-HIV protease inhibitors (e.g., delaviridine, indinavir, nelfinavir, ritonavir, saquinavir), some azole antimycotics (e.g., ketoconazole, itraconazole, voriconazole) and some antidepressants (e.g., nefazadone) is contraindicated because of a risk of significant hypotension (See PRECAUTIONS, Drug Interactions ).
⚠️ Warnings ▾
WARNINGS DEATH DUE TO INADVERTENT INTRAVENOUS ADMINISTRATION: DO NOT ADMINISTER NIMODIPINE INTRAVENOUSLY OR BY OTHER PARENTERAL ROUTES. DEATHS AND SERIOUS, LIFE THREATENING ADVERSE EVENTS, INCLUDING CARDIAC ARREST, CARDIOVASCULAR COLLAPSE, HYPOTENSION, AND BRADYCARDIA, HAVE OCCURRED WHEN THE CONTENTS OF NIMODIPINE CAPSULES HAVE BEEN INJECTED PARENTERALLY (SEE DOSAGE AND ADMINISTRATION ). Reduced Efficacy with CYP3A4 Inducers: Concomitant use of strong CYP3A4 inducers (e.g. rifampin, phenobarbital, phenytoin, carbamazepine, St John’s wort) and nimodipine should generally be avoided, as nimodipine plasma concentration and efficacy may be very significantly reduced (see PRECAUTIONS, Drug Interactions ).
Moderate and weak inducers of CYP3A4 may also reduce the efficacy of nimodipine to a lesser extent. Patients on these should be closely monitored for lack of effectiveness, and a nimodipine dosage increase may be required. Moderate and weak CYP3A4 inhibitors include, for example: amprenavir, aprepitant, armodafinil, bosentan, efavirenz, etravirine, echinacea, modafinil, nafcillin, pioglitazone, prednisone and rufinamide.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse experiences were reported by 92 of 823 patients with subarachnoid hemorrhage (11.2%) who were given nimodipine. The most frequently reported adverse experience was decreased blood pressure in 4.4% of these patients. Twenty-nine of 479 (6.1%) placebo treated patients also reported adverse experiences.
The events reported with a frequency greater than 1% are displayed below by dose. DOSE q4h Number of Patients (%) Nimodipine Sign/Symptom 0.35 mg/kg (n=82) 30 mg (n=71) 60 mg (n=494) 90 mg (n=172) 120 mg (n=4) Placebo (n=479) Decreased Blood Pressure 1 (1.2) 0 19 (3.8) 14 (8.1) 2 (50.0) 6 (1.2) Abnormal Liver Function Test 1 (1.2) 0 2 (0.4) 1 (0.6) 0 7 (1.5) Edema 0 0 2 (0.4) 2 (1.2) 0 3 (0.6) Diarrhea 0 3 (4.2) 0 3 (1.7) 0 3 (0.6) Rash 2 (2.4) 0 3 (0.6) 2 (1.2) 0 3 (0.6) Headache 0 1 (1.4) 6 (1.2) 0 0 1 (0.2) Gastrointestinal Symptoms 2 (2.4) 0 0 2 (1.2) 0 0 Nausea 1 (1.2) 1 (1.4) 6 (1.2) 1 (0.6) 0 0 Dyspnea 1 (1.2) 0 0 0 0 0 EKG Abnormalities 0 1 (1.4) 0 1 (0.6) 0 0 Tachycardia 0 1 (1.4) 0 0 0 0 Bradycardia 0 0 5 (1.0) 1 (0.6) 0 0 Muscle Pain/Cramp 0 1 (1.4) 1 (0.2) 1 (0.6) 0 0 Acne 0 1 (1.4) 0 0 0 0 Depression 0 1 (1.4) 0 0 0 0 There were no other adverse experiences reported by the patients who were given 0.35 mg/kg q4h, 30 mg q4h or 120 mg q4h.
Adverse experiences with an incidence rate of less than 1% in the 60 mg q4h dose group were: hepatitis; itching; gastrointestinal hemorrhage; thrombocytopenia; anemia; palpitations; vomiting; flushing; diaphoresis; wheezing; phenytoin toxicity; lightheadedness; dizziness; rebound vasospasm; jaundice; hypertension; hematoma. Adverse experiences with an incidence rate less than 1% in the 90 mg q4h dose group were: itching, gastrointestinal hemorrhage; thrombocytopenia; neurological deterioration; vomiting; diaphoresis; congestive heart failure; hyponatremia; decreasing platelet count; disseminated intravascular coagulation; deep vein thrombosis.
As can be seen from the table, side effects that appear related to nimodipine use based on increased incidence with higher dose or a higher rate compared to placebo control, included decreased blood pressure, edema and headaches which are known pharmacologic actions of calcium channel blockers. It must be noted, however, that SAH is frequently accompanied by alterations in consciousness which lead to an under reporting of adverse experiences. Patients who received nimodipine in clinical trials for other indications reported flushing (2.1%), headache (4.1%) and fluid retention (0.3%), typical responses to calcium channel blockers.
As a calcium channel blocker, nimodipine may have the potential to exacerbate heart failure in susceptible patients or to interfere with A-V conduction, but these events were not observed. No clinically significant effects on hematologic factors, renal or hepatic function or carbohydrate metabolism have been causally associated with oral nimodipine. Isolated cases of non-fasting elevated serum glucose levels (0.8%), elevated LDH levels (0.4%), decreased platelet counts (0.3%), elevated alkaline phosphatase levels (0.2%) and elevated SGPT levels (0.2%) have been reported rarely.
To report SUSPECTED ADVERSE REACTIONS, contact Bionpharma Inc. at 1-888-235-BION or 1-888-235-2466 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Nimodipine is metabolized via the cytochrome P450 3A4 system located both in the intestinal mucosa and in the liver. Drugs that are known to either inhibit or to induce this enzyme system may therefore alter the first pass or the clearance of nimodipine. In addition, the blood pressure lowering effects of antihypertensives could be enhanced when taken concomitantly with nimodipine.
🤰 Pregnancy ▾
Pregnancy Pregnancy Category C. Nimodipine has been shown to have a teratogenic effect in Himalayan rabbits. Incidences of malformations and stunted foetuses were increased at oral doses of 1 and 10 mg/kg/day administered (by gavage) from day 6 through day 18 of pregnancy but not at 3 mg/kg/day in one of two identical rabbit studies.
In the second study an increased incidence of stunted fetuses was seen at 1 mg/kg/day but not at higher doses. Nimodipine was embryotoxic, causing resorption and stunted growth of fetuses, in Long Evans rats at 100 mg/kg/day administered by gavage from day 6 through day 15 of pregnancy. In two other rat studies, doses of 30 mg/kg/day nimodipine administered by gavage from day 16 of gestation and continued until sacrifice (day 20 of pregnancy or day 21 post partum) were associated with higher incidences of skeletal variatio n, stunted fetuses and stillbirths but no malformations.
There are no adequate and well controlled studies in pregnant women to directly assess the effect on human fetuses. Nimodipine should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in children have not been established.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of nimodipine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dosing in elderly patients should be cautious, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE There have been no reports of overdosage from the oral administration of nimodipine. Symptoms of overdosage would be expected to be related to cardiovascular effects such as excessive peripheral vasodilation with marked systemic hypotension. Clinically significant hypotension due to nimodipine overdosage may require active cardiovascular support with pressor agents.
Specific treatments for calcium channel blocker overdose should also be given promptly. Since nimodipine is highly protein-bound, dialysis is not likely to be of benefit.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Nimodipine is a calcium channel blocker. The contractile processes of smooth muscle cells are dependent upon calcium ions, which enter these cells during depolarization as slow ionic transmembrane currents. Nimodipine inhibits calcium ion transfer into these cells and thus inhibits contractions of vascular smooth muscle.
In animal experiments, nimodipine had a greater effect on cerebral arteries than on arteries elsewhere in the body perhaps because it is highly lipophilic, allowing it to cross the blood-brain barrier; concentrations of nimodipine as high as 12.5 ng/mL have been detected in the cerebrospinal fluid of nimodipine-treated subarachnoid hemorrhage (SAH) patients. The precise mechanism of action of nimodipine in humans is unknown. Although the clinical studies described below demonstrate a favorable effect of nimodipine on the severity of neurological deficits caused by cerebral vasospasm following SAH, there is no arteriographic evidence that the drug either prevents or relieves the spasm of these arteries.
However, whether or not the arteriographic methodology utilized was adequate to detect a clinically meaningful effect, if any, on vasospasm is unknown. Pharmacokinetics and Metabolism In man, nimodipine is rapidly absorbed after oral administration, and peak concentrations are generally attained within one hour. The terminal elimination half-life is approximately 8 to 9 hours but earlier elimination rates are much more rapid, equivalent to a half-life of 1 to 2 hours; a consequence is the need for frequent (every 4 hours) dosing.
There were no signs of accumulation when nimodipine was given three times a day for seven days. Nimodipine is over 95% bound to plasma proteins. The binding was concentration independent over the range of 10 ng/mL to 10 μg/mL.
Nimodipine is eliminated almost exclusively in the form of metabolites and less than 1% is recovered in the urine as unchanged drug. Numerous metabolites, all of which are either inactive or considerably less active than the parent compound, have been identified. The metabolism of nimodipine is mediated by CYP3A4.
Because of a high first-pass metabolism, the bioavailability of nimodipine averages 13% after oral administration. The bioavailability is significantly increased in patients with hepatic cirrhosis, with C max approximately double that in normals which necessitates lowering the dose in this group of patients (see DOSAGE AND ADMINISTRATION ). In a study of 24 healthy male volunteers, administration of nimodipine capsules following a standard breakfast resulted in a 68% lower peak plasma concentration and 38% lower bioavailability relative to dosing under fasted conditions.
In a single parallel-group study involving 24 elderly subjects (aged 59 to 79) and 24 younger subjects (aged 22 to 40), the observed AUC and C max of nimodipine was approximately 2-fold higher in the elderly population compared to the younger study subjects following oral administration (given as a single dose of 30 mg and dosed to steady-state with 30 mg t.i.d. for 6 days). The clinical response to these age-related pharmacokinetic differences, however, was not considered significant. (See PRECAUTIONS, Geriatric Use .) Clinical Trials Nimodipine has been shown, in 4 randomized, double-blind, placebo-controlled trials, to reduce the severity of neurological deficits resulting from vasospasm in patients who have had a recent subarachnoid hemorrhage (SAH).
The trials used doses ranging from 20 to 30 mg to 90 mg every 4 hours, with drug given for 21 days in 3 studies, and for at least 18 days in the other. Three of the four trials followed patients for 3 to 6 months. Three of the trials studied relatively well patients, with all or most patients in Hunt and Hess Grades I - III (essentially free of focal deficits after the initial bleed) the fourth studied much sicker patients, Hunt and Hess Grades III - V.
Two studies, one U.S., one French, were sim… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action Nimodipine is a calcium channel blocker. The contractile processes of smooth muscle cells are dependent upon calcium ions, which enter these cells during depolarization as slow ionic transmembrane currents. Nimodipine inhibits calcium ion transfer into these cells and thus inhibits contractions of vascular smooth muscle.
In animal experiments, nimodipine had a greater effect on cerebral arteries than on arteries elsewhere in the body perhaps because it is highly lipophilic, allowing it to cross the blood-brain barrier; concentrations of nimodipine as high as 12.5 ng/mL have been detected in the cerebrospinal fluid of nimodipine-treated subarachnoid hemorrhage (SAH) patients. The precise mechanism of action of nimodipine in humans is unknown. Although the clinical studies described below demonstrate a favorable effect of nimodipine on the severity of neurological deficits caused by cerebral vasospasm following SAH, there is no arteriographic evidence that the drug either prevents or relieves the spasm of these arteries.
However, whether or not the arteriographic methodology utilized was adequate to detect a clinically meaningful effect, if any, on vasospasm is unknown.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Nimodipine Capsules 30 mg - Oblong, white opaque, soft gelatin capsules in Unit-Dose Package of 30 NDC 69452-209-13 Unit-Dose Package of 100 NDC 69452-209-20 Printed NM1 in black ink. The capsules should be stored in the manufacturer’s original package. Store at 20°to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Capsules should be protected from light and freezing. Distributed by: Bionpharma Inc. Princeton, NJ 08540 Rev. 09/22
📋 Description ▾
DESCRIPTION Nimodipine belongs to the class of pharmacological agents known as calcium channel blockers. Nimodipine is isopropyl 2 -methoxyethyl 1,4 –dihydro -2,6 –dimethyl -4-(m-nitrophenyl) -3,5-pyridinedicarboxylate. It has a molecular weight of 418.5 and a molecular formula of C 21 H 26 N 2 O 7 .
The structural formula is: Nimodipine is a yellow crystalline substance, practically insoluble in water. Nimodipine capsules are formulated as soft gelatin capsules for oral administration. Each liquid filled capsule contains 30 mg of nimodipine.
In addition the capsules contain the following inactive ingredients: gelatin, glycerin, hypromellose, iron oxide black, kosher glycerin, mannitol, peppermint oil, polyethylene glycol, propylene glycol, sorbitol, sorbitol anhydrides and titanium dioxide. Structural Formula
⚠️ Precautions ▾
PRECAUTIONS General Blood Pressure: Nimodipine has the hemodynamic effects expected of a calcium channel blocker, although they are generally not marked. However, intravenous administration of the contents of nimodipine capsules has resulted in serious adverse consequences including death, cardiac arrest, cardiovascular collapse, hypotension, and bradycardia. In patients with subarachnoid haemorrhage given nimodipine in clinical studies, about 5% were reported to have had lowering of the blood pressure and about 1% left the study because of this (not all could be attributed to nimodipine).
Nevertheless, blood pressure should be carefully monitored during treatment with nimodipine based on its known pharmacology and the known effects of calcium channel blockers. (see WARNINGS and DOSAGE AND ADMINISTRATION ). Hepatic Disease: The metabolism of nimodipine is decreased in patients with impaired hepatic function.
Such patients should have their blood pressure and pulse rate monitored closely and should be given a lower dose (see DOSAGE AND ADMINISTRATION ). Intestinal pseudo-obstruction and ileus have been reported rarely in patients treated with nimodipine. A causal relationship has not been established.
The condition has responded to conservative management. Laboratory Test Interactions None known. Drug Interactions Nimodipine is metabolized via the cytochrome P450 3A4 system located both in the intestinal mucosa and in the liver.
Drugs that are known to either inhibit or to induce this enzyme system may therefore alter the first pass or the clearance of nimodipine. In addition, the blood pressure lowering effects of antihypertensives could be enhanced when taken concomitantly with nimodipine. Inducers of CYP3A4 Nimodipine plasma concentration and efficacy may be significantly reduced when concomitantly administered with strong CYP3A4 inducers.
Therefore strong CYP3A4 inducers (e.g. rifampin, carbamazepine, phenobarbital, phenytoin, St. John’s Wort) should generally not be administered concomitantly with nimodipine (see WARNINGS ). Other moderate and weak inducers of CYP3A4 may also reduce the efficacy of nimodipine, although the magnitude of decrease in nimodipine plasma concentrations is not known.
Patients on these should be closely monitored for lack of effectiveness, and a nimodipine dosage increase may be required. Moderate and weak CYP3A4 inducers include: amprenavir, aprepitant, armodafinil, bosentan, efavirenz, etravirine, Echinacea, modafinil, nafcillin, pioglitazone, prednisone and rufinamide. Inhibitors of CYP3A4 Nimodipine plasma concentration can be significantly increased when concomitantly administered with strong inhibitors of the CYP3A4 system.
As a consequence, the blood pressure lowering effect may be increased. Therefore strong CYP3A4 inhibitors should not be coadministered with nimodipine (See CONTRAINDICATIONS ). Strong CYP3A4 inhibitors include some members of the following classes: - macrolide antibiotics (e.g., clarithromycin, telithromycin,), - HIV protease inhibitors (e.g., delavirdine, indinavir, nelfinavir, ritonavir, saquinavir), - azole antimycotics (e.g., ketoconazole, itraconazole, voriconazole), - antidepressants (e.g. nefazodone) - grapefruit juice: after intake of grapefruit juice and nimodipine, the blood pressure lowering effect may last for at least 4 days after the last ingestion of grapefruit juice.
Ingestion of grapefruit / grapefruit juice is therefore not recommended while taking nimodipine (See DOSAGE AND ADMINISTRATION ). Nimodipine plasma concentration can also be increased in the presence of moderate and weak inhibitors of CYP3A4. If nimodipine is concomitantly administered with these drugs, blood pressure should be monitored, and a reduction of the nimodipine dose may be necessary.
Moderate and weak CYP3A4 inhibitors include amprenavir, aprepitant, atazanavir, amiodarone, alprozalam, cyclosporine, cimetidine, erythromycin, fluconazole, fluoxetine, isoniazid, oral contraceptives, q… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Nimodipine and/or its metabolites have been shown to appear in rat milk at concentrations much higher than in maternal plasma. It is not known whether the drug is excreted in human milk. Because many drugs are excreted in human milk, nursing mothers are advised not to breast feed their babies when taking the drug.
🧬 Pharmacokinetics ▾
Pharmacokinetics and Metabolism In man, nimodipine is rapidly absorbed after oral administration, and peak concentrations are generally attained within one hour. The terminal elimination half-life is approximately 8 to 9 hours but earlier elimination rates are much more rapid, equivalent to a half-life of 1 to 2 hours; a consequence is the need for frequent (every 4 hours) dosing. There were no signs of accumulation when nimodipine was given three times a day for seven days.
Nimodipine is over 95% bound to plasma proteins. The binding was concentration independent over the range of 10 ng/mL to 10 μg/mL. Nimodipine is eliminated almost exclusively in the form of metabolites and less than 1% is recovered in the urine as unchanged drug.
Numerous metabolites, all of which are either inactive or considerably less active than the parent compound, have been identified. The metabolism of nimodipine is mediated by CYP3A4. Because of a high first-pass metabolism, the bioavailability of nimodipine averages 13% after oral administration.
The bioavailability is significantly increased in patients with hepatic cirrhosis, with C max approximately double that in normals which necessitates lowering the dose in this group of patients (see DOSAGE AND ADMINISTRATION ). In a study of 24 healthy male volunteers, administration of nimodipine capsules following a standard breakfast resulted in a 68% lower peak plasma concentration and 38% lower bioavailability relative to dosing under fasted conditions. In a single parallel-group study involving 24 elderly subjects (aged 59 to 79) and 24 younger subjects (aged 22 to 40), the observed AUC and C max of nimodipine was approximately 2-fold higher in the elderly population compared to the younger study subjects following oral administration (given as a single dose of 30 mg and dosed to steady-state with 30 mg t.i.d. for 6 days).
The clinical response to these age-related pharmacokinetic differences, however, was not considered significant. (See PRECAUTIONS, Geriatric Use .)
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE There have been no reported instances of drug abuse or dependence with nimodipine
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility In a two-year study, higher incidences of adenocarcinoma of the uterus and Leydig-cell adenoma of the testes were observed in rats given a diet containing 1800 ppm nimodipine (equivalent to 91 to 121 mg/kg/day nimodipine) than in placebo controls. The differences were not statistically significant, however, and the higher rates were well within historical control range for these tumors in the Wistar strain. Nimodipine was found not to be carcinogenic in a 91-week mouse study but the high dose of 1800 ppm nimodipine-in-feed (546 to 774 mg/kg/day) shortened the life expectancy of the animals.
Mutagenicity studies, including the Ames, micronucleus and dominant lethal tests were negative. Nimodipine did not impair the fertility and general reproductive performance of male and female Wistar rats following oral doses of up to 30 mg/kg/day when administered daily for more than 10 weeks in the males and 3 weeks in the females prior to mating and continued to day 7 of pregnancy. This dose in a rat is about 4 times the equivalent clinical dose of 60 mg q4h in a 50 kg patient.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL BIONPHARMA NDC 69452-209-13 Nimodipine Capsules 30 mg Contents are packaged child-resistant. Rx only 30 Capsules Unit-Dose 30's Carton
BIONPHARMA NDC 69452-209-20 Nimodipine Capsules 30 mg Contents are packaged child-resistant. Rx only 100 Capsules Unit-Dose image002