
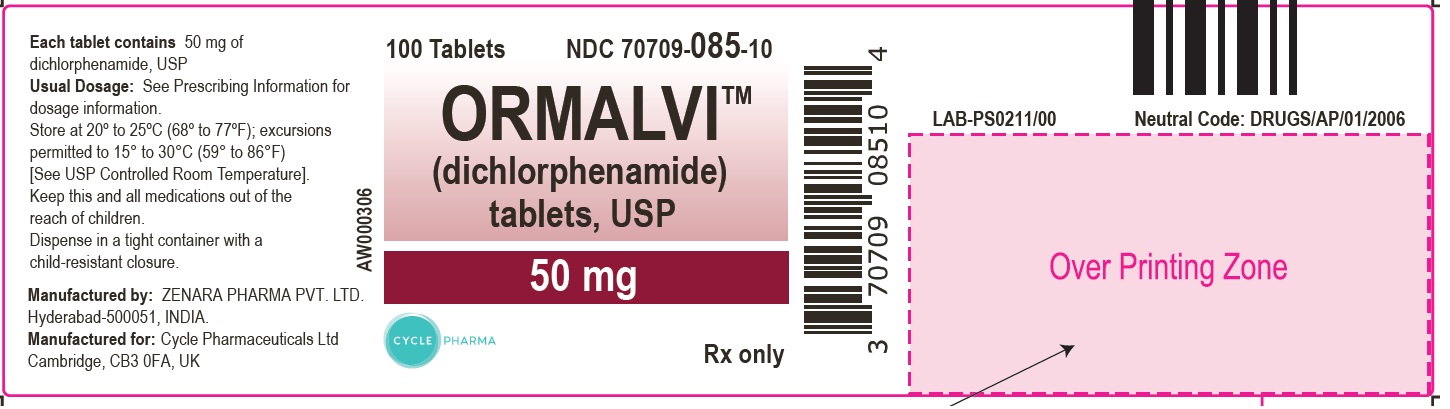
ORMALVI Dichlorphenamide 50 mg Tablet, 100-count — NDC 70709-085-10 (Billing 70709-0085-10)
This is a package of 100 tablets of ORMALVI Dichlorphenamide 50 mg Tablet from Cycle Pharmaceuticals Ltd., marketed since Mar 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 70709-085-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70709 labeler · 085 product · 10 package
- Package marketed since
- Mar 15, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 100 EA per package
- Barcode (UPC)
- 0370709085104
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 074933
- GCN: 39804
- GPI-14 (Medi-Span): 37100020000305
- HICL (First Databank): 003642
- AHFS class code: 92:26.00.00
- RxCUI (RxNorm): 197594
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Carbonic Anhydrase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Dichlorphenamide — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $328.24 | $32,824.40 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70709-0085-10 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 2024-03-15 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Dichlorphenamide 50 mg 13668-0676-01 | Torrent | 100 tablets | — | AB | FDA listed | — |
| Dichlorphenamide 50 mg 16571-0242-01 | Rising | 100 tablets | — | AB | FDA listed | — |
| Ormalvi 50 mgthis 70709-0085-10 | Cycle | 100 tablets | — | AB | FDA listed | — |
| Keveyis 50 mg 72065-0001-01 | Xeris | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Cycle Pharmaceuticals Ltd. labeler code 70709
- NITYR Nitisinone 10 mg Tablet NDC 70709-000-60
- NITYR Nitisinone 2 mg Tablet NDC 70709-002-60
- NITYR Nitisinone 5 mg Tablet NDC 70709-005-60
- SAJAZIR ICATIBANT 30 mg/3mL Injection NDC 70709-013-01
- TASCENSO ODT Fingolimod Lauryl Sulfate .25 mg Tablet, Orally Disintegrating NDC 70709-062-30
- TASCENSO ODT Fingolimod Lauryl Sulfate .5 mg Tablet, Orally Disintegrating NDC 70709-065-30
- AAGYLUR Penicillamine 250 mg Capsule NDC 70709-102-10
- Harliku nitisinone 2 mg Tablet NDC 70709-112-60
- Venxxiva tiopronin 100 mg Tablet, Delayed Release NDC 70709-121-30
- Venxxiva tiopronin 300 mg Tablet, Delayed Release NDC 70709-123-90
- Phyrago dasatinib 20 mg Tablet NDC 70709-151-20
- Phyrago dasatinib 50 mg Tablet NDC 70709-152-50
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ORMALVI is indicated for the treatment of primary hyperkalemic periodic paralysis, primary hypokalemic periodic paralysis, and related variants. ORMALVI is an oral carbonic anhydrase inhibitor indicated for the treatment of primary hyperkalemic periodic paralysis, primary hypokalemic periodic paralysis, and related variants ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Initiate dosing at 50 mg by mouth once or twice daily ( 2.1 ) • Titrate up or down dose based on individual response ( 2.1 ) • The minimum recommended dosage is 50 mg daily, and the maximum recommended dosage is 200 mg daily ( 2.1 ) • Evaluate response to ORMALVI after 2 months of treatment ( 2.2 )
2.1Dosage Information Initiate dosing at 50 mg by mouth once or twice daily. The dosage may be increased or decreased based on individual response, at weekly intervals (or sooner in case of adverse reaction). The minimum recommended total daily dosage is 50 mg, and the maximum recommended total daily dosage is 200 mg.
2.2Monitoring to Assess Effectiveness Primary hyperkalemic periodic paralysis, primary hypokalemic periodic paralysis, and related variants are a heterogeneous group of conditions, for which the response to ORMALVI may vary. Therefore, prescribers should evaluate the patient's response to ORMALVI after 2 months of treatment to decide whether ORMALVI should be continued.
2.3Monitoring to Assess Safety Baseline and periodic measurements of serum potassium and sodium bicarbonate during ORMALVI treatment is recommended [see Warnings and Precautions ( 5.3 , 5.4 )] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS White to off-white, round shaped, flat faced beveled edged tablet, scored on one side, engraved with ‘ZD’ above the score and ‘50’ below the score, the other side is plain. Tablets: 50 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ORMALVI is contraindicated in the following circumstances: Hypersensitivity to dichlorphenamide or other sulfonamides [see Warnings and Precautions ( 5.1 )] Concomitant use of ORMALVI and high dose aspirin [see Warnings and Precautions ( 5.2 ) and Drug Interactions ( 7.1 )] Severe pulmonary disease, limiting compensation to metabolic acidosis caused by ORMALVI [see Warnings and Precautions ( 5.4 )] Hepatic insufficiency: ORMALVI may aggravate hepatic encephalopathy. Hepatic insufficiency ( 4 ) Severe pulmonary obstruction ( 4 ) Hypersensitivity to dichlorphenamide or other sulfonamides ( 4 ) Concomitant use with high dose aspirin ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity and Other Life-Threatening Reactions: discontinue ORMALVI at the first appearance of skin rash or any sign of immune-mediated or idiosyncratic adverse reaction ( 5.1 ) Hypokalemia: baseline and periodic measurements of serum potassium are recommended; if hypokalemia develops or persists, consider reducing the dose or discontinuing ORMALVI and correcting potassium levels ( 5.3 ) Metabolic acidosis: baseline and periodic measurements of serum bicarbonate are recommended; if metabolic acidosis develops or persists, consider reducing the dose or discontinuing ORMALVI ( 5.4 ) Falls: consider reducing the dose or discontinuing ORMALVI in patients who experience falls ( 5.5 )
5.1Hypersensitivity and Other Life-threatening Reactions Fatalities associated with the administration of sulfonamides have occurred because of adverse reactions including Stevens-Johnson syndrome, toxic epidermal necrolysis, fulminant hepatic necrosis, agranulocytosis, aplastic anemia, and other blood dyscrasias. Pulmonary involvement can occur in isolation or as part of a systemic reaction. ORMALVI should be discontinued at the first appearance of skin rash or any sign of immune-mediated or other life-threatening adverse reaction.
5.2Concomitant Use of Aspirin or Other Salicylates Carbonic anhydrase inhibitors, including ORMALVI, can cause metabolic acidosis [see Warnings and Precautions ( 5.4 )] , which can increase the risk of salicylate toxicity. Anorexia, tachypnea, lethargy, and coma have been reported with concomitant use of dichlorphenamide and high-dose aspirin. Therefore, the concomitant use of ORMALVI and high-dose aspirin is contraindicated.
Patients with concomitant use of ORMALVI and low-dose aspirin should be carefully monitored.
5.3Hypokalemia ORMALVI increases potassium excretion and can cause hypokalemia. The risk of hypokalemia is greater when ORMALVI is used in patients with conditions associated with hypokalemia (e.g., adrenocortical excess, renal tubular acidosis type 1 and 2), and in patients receiving other drugs that may cause hypokalemia [see Drug Interactions ( 7.3 )]. Baseline and periodic measurements of serum potassium during ORMALVI treatment is recommended.
If hypokalemia develops or persists, consideration should be given to reducing the dose or discontinuing ORMALVI and correction of potassium levels.
5.4Metabolic Acidosis ORMALVI can cause hyperchloremic non-anion gap metabolic acidosis. Concomitant use of ORMALVI with other drugs that cause metabolic acidosis may increase the severity of acidosis. Concomitant use of ORMALVI in compensated patients with respiratory acidosis, such as in advanced lung diseases, may lead to respiratory decompensation.
Baseline and periodic measurements of serum bicarbonate during ORMALVI treatment are recommended. If metabolic acidosis develops or persists, consideration should be given to reducing the dose or discontinuing ORMALVI [see Drug Interactions ( 7.4) ].
5.5Falls ORMALVI increases the risk of falls. The risk of falls is greater in the elderly and with higher doses of ORMALVI. Consider dose reduction or discontinuation of ORMALVI in patients who experience falls while treated with ORMALVI.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in labeling: Hypersensitivity and Other Life-Threatening Reactions [see Warnings and Precautions ( 5.1 )] Hypokalemia [see Warnings and Precautions ( 5.3 )] Metabolic Acidosis [see Warnings and Precautions ( 5.4 )] Falls [ see Warnings and Precautions ( 5.5 )] Most common adverse reactions (incidence at least 10% and greater than placebo) include paresthesias, cognitive disorder, dysgeusia, and confusional state ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Cycle Pharmaceuticals Ltd at 1-857-437-3969 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In a 9-week randomized controlled trial in adults with hyperkalemic or hypokalemic periodic paralysis (Study 1), the most common adverse reactions in patients treated with dichlorphenamide, with rates greater than placebo, were paresthesia, cognitive disorder, dysgeusia, and confusional state.
The mean dose of dichlorphenamide was 94 mg/day in patients with hypokalemic periodic paralysis and 82 mg/day in patients with hyperkalemic periodic paralysis. Table 1 lists the incidence of adverse reactions that occurred in 5% of patients treated with dichlorphenamide and more commonly than in patients treated with placebo in Study 1. Table 1: Adverse Reactions in Patients Treated with Dichlorphenamide with Incidence 5% and more common than in Patients Treated with Placebo in Study 1 Adverse Reaction Dichlorphenamide N = 36 (%) Placebo N = 29 (%) Nervous system disorders Paresthesia 44 14 Cognitive disorder 1 14 7 Dysgeusia 14 0 Confusional state 11 0 Headache 8 7 Hypoesthesia 8 0 Lethargy 8 0 Dizziness 6 0 Gastrointestinal disorders Diarrhea 6 3 Nausea 6 0 General disorders and administration site conditions Fatigue 8 0 Malaise 6 0 Investigations Weight decreased 6 0 Musculoskeletal and connective tissue disorders Muscle spasms 8 0 Arthralgia 6 3 Muscle twitching 6 0 Respiratory Dyspnea 6 0 Pharyngolaryngeal pain 6 0 Skin Rash 8 0 Pruritus 6 0 1 Cognitive disorder combined cases with the preferred terms of cognitive disorder, disturbance in attention, and mental impairment.
6.2Postmarketing Experience Adverse reactions have been identified during postapproval use of dichlorphenamide. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The following are adverse reactions which have been reported during postapproval use of dichlorphenamide and were serious or are not reported in the previous section of labeling [see Clinical Trials Experience ( 6.1 ) ] : amnesia, cardiac failure, condition aggravated, convulsion, hallucination, nephrolithiasis, pancytopenia, psychotic disorder, renal tubular necrosis, stupor, syncope, tremor.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Aspirin: anorexia, tachypnea, lethargy, and coma have been reported with concomitant use of dichlorphenamide and high-dose aspirin. The concomitant use of ORMALVI and high-dose aspirin is contraindicated. ORMALVI should be used with caution in patients receiving lower doses of aspirin ( 4 , 5.2 , 7.1 )
7.1Aspirin and Other Salicylates Carbonic anhydrase inhibitors, including ORMALVI, can cause metabolic acidosis [see Warning and Precautions ( 5.2 , 5.4 )] , which can increase the risk of salicylate toxicity. Anorexia, tachypnea, lethargy, and coma have been reported with concomitant use of dichlorphenamide and high-dose aspirin. Therefore, concomitant use of ORMALVI and high-dose aspirin is contraindicated.
Patients with concomitant use of ORMALVI and low-dose aspirin should be carefully monitored [see Contraindications ( 4 ) and Warnings and Precautions ( 5.2 )].
7.2Drugs that are Substrates of Organic Anion Transporter1 (OAT1) In vitro , dichlorphenamide is an inhibitor of OAT1 transporters. The concomitant administration of ORMALVI may increase the plasma exposures of OAT1 substrates. Use of ORMALVI with drugs that are sensitive to OAT1 inhibition (e.g., methotrexate, famotidine, oseltamivir) is not recommended [see Clinical Pharmacology ( 12.3 )].
7.3Drugs that Cause Hypokalemia The risk of hypokalemia is greater with coadministration of ORMALVI and other drugs that can cause hypokalemia (e.g., loop diuretics, thiazide diuretics, laxatives, antifungals, penicillins, and theophylline) [see Warnings and Precautions ( 5.3 )].
7.4Drugs that Cause Metabolic Acidosis Coadministration of ORMALVI and other drugs that can cause metabolic acidosis may increase the severity of the acidosis [see Warnings and Precautions ( 5.4 )].
7.5Drugs that are Inhibitors of OAT1 or OAT3 An in vitro transporter study indicated that dichlorphenamide is a substrate of human transporters OAT1 and OAT3 [see Clinical Pharmacology ( 12.3 )] . Therefore, signs of dichlorphenamide toxicity should be monitored when administered with OAT1 or OAT3 inhibitors.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm ( 8.1 )
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of ORMALVI in pregnant women. A no-effect dose has not been established. Dichlorphenamide was teratogenic when administered orally to pregnant rats.
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4%, and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal adverse reactions ORMALVI treatment can cause metabolic acidosis [see Warnings and Precautions ( 5.4 )] .
The effect of dichlorphenamide-induced metabolic acidosis has not been studied in pregnancy; however, metabolic acidosis in pregnancy (due to other causes) can cause decreased fetal growth, decreased fetal oxygenation, and fetal death, and may affect the fetus’ ability to tolerate labor. Pregnant patients should be monitored for metabolic acidosis and treated as in the nonpregnant state. Newborns of mothers treated with ORMALVI should be monitored for metabolic acidosis because of possible occurrence of transient metabolic acidosis following birth.
Labor or Delivery Although the effect of ORMALVI on labor and delivery in humans has not been established, the development of dichlorphenamide-induced metabolic acidosis in the mother and/or in the fetus might affect the fetus’ ability to tolerate labor. Data Animal Data Teratogenic effects (fetal limb reduction defects) were reported following oral administration of dichlorphenamide to pregnant rats during organogenesis at 350 mg/kg, or 17 times the maximum recommended human dose (200 mg/day) on a body surface area (mg/m 2 ) basis.
A no-effect dose for adverse effects on embryofetal development has not been established.
8.2Lactation Risk Summary There are no data on the presence of dichlorphenamide in human milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for ORMALVI and any potential adverse effects on the breastfed infant from ORMALVI or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness of ORMALVI in pediatric patients have not been established.
8.5Geriatric Use The risk of falls and of metabolic acidosis are greater in elderly patients [see Warnings and Precautions ( 5.4 , 5.5 )].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of ORMALVI in pregnant women. A no-effect dose has not been established. Dichlorphenamide was teratogenic when administered orally to pregnant rats.
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4%, and 15% to 20%, respectively. Clinical Considerations Fetal/Neonatal adverse reactions ORMALVI treatment can cause metabolic acidosis [see Warnings and Precautions ( 5.4 )] .
The effect of dichlorphenamide-induced metabolic acidosis has not been studied in pregnancy; however, metabolic acidosis in pregnancy (due to other causes) can cause decreased fetal growth, decreased fetal oxygenation, and fetal death, and may affect the fetus’ ability to tolerate labor. Pregnant patients should be monitored for metabolic acidosis and treated as in the nonpregnant state. Newborns of mothers treated with ORMALVI should be monitored for metabolic acidosis because of possible occurrence of transient metabolic acidosis following birth.
Labor or Delivery Although the effect of ORMALVI on labor and delivery in humans has not been established, the development of dichlorphenamide-induced metabolic acidosis in the mother and/or in the fetus might affect the fetus’ ability to tolerate labor. Data Animal Data Teratogenic effects (fetal limb reduction defects) were reported following oral administration of dichlorphenamide to pregnant rats during organogenesis at 350 mg/kg, or 17 times the maximum recommended human dose (200 mg/day) on a body surface area (mg/m 2 ) basis.
A no-effect dose for adverse effects on embryofetal development has not been established.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of ORMALVI in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use The risk of falls and of metabolic acidosis are greater in elderly patients [see Warnings and Precautions ( 5.4 , 5.5 )].
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms of overdosage or toxicity may include drowsiness, anorexia, nausea, vomiting, dizziness, ataxia, tremor, and tinnitus. In the event of overdosage, induce emesis or perform gastric lavage. The electrolyte disturbances most likely to be encountered from overdosage are hypokalemia and hyperchloremic metabolic acidosis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Dichlorphenamide is a carbonic anhydrase inhibitor. However, the precise mechanism by which dichlorphenamide exerts its therapeutic effects in patients with primary periodic paralysis is unknown.
12.2Pharmacodynamics ORMALVI can cause metabolic acidosis, which can increase the risk of salicylate toxicity with coadministration [see Warnings and Precautions ( 5.2 )] . ORMALVI-induced metabolic acidosis can also increase in severity with coadministration of other drugs that cause metabolic acidosis [see Warnings and Precautions ( 5.4 )].
12.3Pharmacokinetics After single-dose administration in healthy subjects in fasted state, dichlorphenamide C max and AUC increased in a dose-proportional manner within the range of 25 mg to 400 mg (2 times the maximum recommended dose). The steady-state is expected to be achieved within 10 days of twice-daily dosing. Absorption The median time to reach maximum concentration (T max ) of dichlorphenamide was about 1.5 to 3 hours postdose after both single and multiple dose administrations.
Distribution The plasma protein binding of dichlorphenamide is approximately 88%. Elimination Following a single-dose administration, mean terminal half-life was in the range of 32 to 66 hours. Metabolism Dichlorphenamide is not a substrate for CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6 and CYP3A4 isoforms when tested in vitro .
Drug Interaction Studies In vitro Assessment of Drug Interactions Drug-Metabolizing Enzyme Inhibition Dichlorphenamide is not an inhibitor for CYP1A2, 2B6, 2C8, 2C9, 2C19, 2D6, or 3A4 enzymes when tested in vitro. Drug-Metabolizing Enzyme Induction Dichlorphenamide is not an inducer for CYP1A2, 2B6, or 3A4 enzymes when tested in vitro . In vitro Assessment of Transporter-Drug Interactions Dichlorphenamide is neither a substrate nor inhibitor for p-gp, BCRP, OATP1B1, OATP1B3, OAT2, OAT4, OCT1, OCT2, MATE1, or MATE2-K when tested in vitro .
Dichlorphenamide is not an inhibitor of OAT3, but is an inhibitor of OAT1 based on in vitro studies [see Drug Interactions ( 7.4 )]. Dichlorphenamide is a substrate for transporters OAT1 and OAT3 based on in vitro studies [see Drug Interactions ( 7.2 )]. In Vivo Drug Interactions The use of dichlorphenamide in combination with high-dose aspirin is contraindicated as it may lead to salicylate toxicity.
The mechanism(s) of this interaction is not known. Specific Populations Geriatrics The pharmacokinetics of dichlorphenamide in the elderly has not been determined.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Dichlorphenamide is a carbonic anhydrase inhibitor. However, the precise mechanism by which dichlorphenamide exerts its therapeutic effects in patients with primary periodic paralysis is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each ORMALVI (dichlorphenamide) tablet USP, 50 mg is white to off-white, round shaped, flat faced beveled edged tablet, scored on one side, engraved with ‘ZD’ above the score and ‘50’ below the score, the other side is plain. ORMALVI (dichlorphenamide) tablets are supplied as follows: Bottles of 100 NDC 70709-085-10 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION ORMALVI tablets, USP contain dichlorphenamide, an oral carbonic anhydrase inhibitor. Dichlorphenamide, USP a dichlorinated benzenedisulfonamide, is known chemically as 4, 5–dichloro-1,3-benzenedisulfonamide. Its empirical formula is C 6 H 6 Cl 2 N 2 O 4 S 2 and its structural formula is: Dichlorphenamide USP is a white or practically white, crystalline powder with a molecular weight of 305.16.
It is very slightly soluble in water but soluble in dilute solutions of alkali carbonate and hydroxide. ORMALVI (dichlorphenamide) tablets, USP are supplied as tablets, for oral administration, each containing 50 mg dichlorphenamide. Inactive ingredients are lactose monohydrate, partially pregelatinized starch and magnesium stearate.
FDA approved dissolution test specifications differ from USP. image description
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Worsening of Symptoms Advise patients to notify their physician if they experience acute worsening of symptoms of periodic paralysis. Hypersensitivity and Other Life-threatening Reactions Inform patients that hypersensitivity and immune mediated reactions can occur with ORMALVI and could be fatal. Advise patients to discontinue ORMALVI and notify their healthcare provider immediately if they develop a rash or signs and symptoms of anaphylaxis or other life-threatening reactions [see Warnings and Precautions ( 5.1 )].
Drug Interactions Instruct patients to notify their healthcare provider of all of the drugs and over-the-counter medications that they take and to not take aspirin or other salicylates without first discussing with their healthcare provider [see Drug Interactions ( 7.1 , 7.2 , 7.3 , 7.4 )]. Metabolic Acidosis Instruct patients to contact their healthcare provider immediately if they develop possible manifestations of metabolic acidosis (e.g., fast breathing, fatigue/tiredness, loss of appetite, or irregular heartbeat or palpitations) [see Warnings and Precautions ( 5.4 )].
Falls Inform patients that ORMALVI can increase their risk of falls [see Warnings and Precautions ( 5.5 )]. Cognitive Impairment Advise patients to notify their healthcare provider if they experience symptoms of cognitive impairment including confusion and memory lapse [see Adverse Reactions ( 6.1 )]. Driving and Operating Machinery ORMALVI may cause drowsiness/fatigue in some patients [see Adverse Reactions ( 6.1 )].
Caution patients on the potential for impaired ability to drive and operate machinery.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics After single-dose administration in healthy subjects in fasted state, dichlorphenamide C max and AUC increased in a dose-proportional manner within the range of 25 mg to 400 mg (2 times the maximum recommended dose). The steady-state is expected to be achieved within 10 days of twice-daily dosing. Absorption The median time to reach maximum concentration (T max ) of dichlorphenamide was about 1.5 to 3 hours postdose after both single and multiple dose administrations.
Distribution The plasma protein binding of dichlorphenamide is approximately 88%. Elimination Following a single-dose administration, mean terminal half-life was in the range of 32 to 66 hours. Metabolism Dichlorphenamide is not a substrate for CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6 and CYP3A4 isoforms when tested in vitro .
Drug Interaction Studies In vitro Assessment of Drug Interactions Drug-Metabolizing Enzyme Inhibition Dichlorphenamide is not an inhibitor for CYP1A2, 2B6, 2C8, 2C9, 2C19, 2D6, or 3A4 enzymes when tested in vitro. Drug-Metabolizing Enzyme Induction Dichlorphenamide is not an inducer for CYP1A2, 2B6, or 3A4 enzymes when tested in vitro . In vitro Assessment of Transporter-Drug Interactions Dichlorphenamide is neither a substrate nor inhibitor for p-gp, BCRP, OATP1B1, OATP1B3, OAT2, OAT4, OCT1, OCT2, MATE1, or MATE2-K when tested in vitro .
Dichlorphenamide is not an inhibitor of OAT3, but is an inhibitor of OAT1 based on in vitro studies [see Drug Interactions ( 7.4 )]. Dichlorphenamide is a substrate for transporters OAT1 and OAT3 based on in vitro studies [see Drug Interactions ( 7.2 )]. In Vivo Drug Interactions The use of dichlorphenamide in combination with high-dose aspirin is contraindicated as it may lead to salicylate toxicity.
The mechanism(s) of this interaction is not known. Specific Populations Geriatrics The pharmacokinetics of dichlorphenamide in the elderly has not been determined.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics ORMALVI can cause metabolic acidosis, which can increase the risk of salicylate toxicity with coadministration [see Warnings and Precautions ( 5.2 )] . ORMALVI-induced metabolic acidosis can also increase in severity with coadministration of other drugs that cause metabolic acidosis [see Warnings and Precautions ( 5.4 )].
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of dichlorphenamide was evaluated in two clinical studies, Study 1 and Study 2. Study 1 Study 1 was a 9-week, double-blind, placebo-controlled multi-center study. Study 1 consisted of two substudies: a substudy in patients with hypokalemic periodic paralysis (n=44), and a substudy in patients with hyperkalemic periodic paralysis (n=21).
The primary efficacy endpoint in both substudies was the average number of self-reported attacks of muscle weakness per week over the final 8 weeks of the trial. Withdrawal from the study for acute severe worsening (increase in attack frequency or severity) was also assessed as an endpoint. In Study 1, the dose of dichlorphenamide was 50 mg b.i.d. for treatment-naïve patients.
Patients already on dichlorphenamide prior to the study continued on the same dose while on dichlorphenamide during the study. In patients taking acetazolamide prior to the study, the dose of dichlorphenamide was set at 20% of the acetazolamide dose. Dose reduction for tolerability was permitted.
Hypokalemic Periodic Paralysis Substudy of Study 1 In the hypokalemic periodic paralysis substudy, median age of patients was 45 years and 73% of patients were male. Patients treated with dichlorphenamide (n=24) had 2.2 fewer attacks per week than patients (n=20) treated with placebo (p=0.02). None of the patients randomized to dichlorphenamide reached the endpoint of withdrawal from the study for acute worsening, vs. five patients randomized to placebo.
The mean dose of dichlorphenamide at Week 9 was 94 mg/day. Hyperkalemic Periodic Paralysis Substudy of Study 1 In the Hyperkalemic Periodic Paralysis substudy, median age of patients was 43 years and 43% of patients were male. During the double-blind treatment period, patients treated with dichlorphenamide (n=12) had 3.9 fewer attacks per week than patients (n=9) treated with placebo (p=0.08).
None of the patients randomized to dichlorphenamide reached the endpoint of withdrawal from the study for acute worsening, vs. two patients randomized to placebo. The mean dose of dichlorphenamide at Week 9 was 82 mg/day. Study 2 Study 2 was a 35-week, double-blind, placebo-controlled, multi-center, two-period crossover study.
Study 2 also consisted of two substudies: a substudy in patients with hypokalemic periodic paralysis (n=42), and a substudy in patients with hyperkalemic periodic paralysis (n=31), including patients with Paramyotonia Congenita. The primary endpoint in the hypokalemic periodic paralysis substudy was the incidence of acute intolerable worsening (based on attack frequency or severity) necessitating withdrawal. The primary endpoint in the hyperkalemic periodic paralysis substudy was the average number of self-reported attacks of muscle weakness per week.
Dosing was determined similarly to Study 1. Hypokalemic Periodic Paralysis Substudy of Study 2 The hypokalemic periodic paralysis substudy included patients with a mean age of 38 years; 79% of patients were male. Acute intolerable worsening was observed in 2 patients on dichlorphenamide vs.
11 patients on placebo (p=0.02). The mean dose of dichlorphenamide at the end of the study was 96 mg/day. Hyperkalemic Periodic Paralysis Substudy of Study 2 The hyperkalemic periodic paralysis substudy included patients with a mean age of 37 years; and 79% of patients were male.
Patients treated had 2.3 fewer attacks per week on dichlorphenamide than on placebo (p=0.006). The mean dose of dichlorphenamide at the end of the study was 73 mg/day.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Studies to assess the carcinogenic potential of dichlorphenamide have not been conducted. Mutagenesis Studies to assess the genotoxicity of dichlorphenamide have not been conducted. Impairment of Fertility Studies to assess the effects of dichlorphenamide on fertility have not been conducted.
📄 Package Label / Principal Display Panel ▾
ORMALVI TM (dichlorphenamide) 50 mg tablets, 100s Count image description
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |