
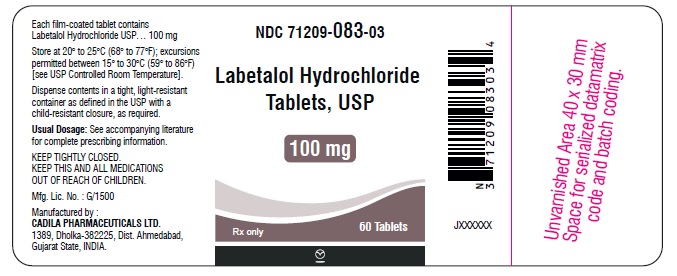
Labetalol Hydrochloride 100 mg Tablet, Film Coated, 100-count
Other active recalls for Labetalol Hydrochloride (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Labetalol is used to lower high blood pressure (hypertension). The tablet form is for ongoing daily management of hypertension, and can be used on its own or with other blood press...
- Please don't stop labetalol on your own, even if you feel great — this is really important. Stopping suddenly, especially if you have coronary artery disease (even undiagnosed), ca...
- Is it okay to stop taking labetalol if I feel fine?
- Yes, this is a known effect. Labetalol lowers blood pressure more when you're standing than lying down, which can cause lightheadedness when you get up quickly — especially 2 to 4...
Patient education
Supplement & herbal interactions
Labetalol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1818 | $18.18 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Labetalol Hydrochloride 100 mg 71247-0126-01 | Innogenix, | 100 tablets | $0.083 | AB | FDA listed | — |
| Labetalol hydrochloride 100 mg 00591-0605-01 | Actavis | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 00904-7451-61 | Major | 1 tablet | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 23155-0723-01 | Heritage | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 58657-0602-01 | Method | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 58657-0906-01 | Method | 1 tablet | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 60687-0439-01 | American | 1 tablet | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 62135-0791-60 | Chartwell | 60 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 68001-0381-00 | BluePoint | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 68001-0700-00 | BluePoint | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 68382-0798-01 | Zydus | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 72603-0902-01 | NorthStar | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 72888-0120-01 | Advagen | 100 tablets | $0.085 | AB | Availability likely | — |
| Labetalol Hydrochloride 100 mg 00615-8512-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 10135-0711-01 | Marlex | 100 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 29300-0252-01 | Unichem | 100 tablets | — | — | FDA listed | — |
| Labetalol Hydrochloride 100 mg 33342-0515-11 | Macleods | 100 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 42806-0327-01 | Epic | 100 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 50090-6741-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 50090-7457-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 50090-7458-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 51407-0614-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 51655-0322-25 | Northwind | 60 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 55154-0181-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 55154-8192-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 60760-0784-90 | St. | 90 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 60760-0991-90 | St. | 90 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 63629-1161-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 63629-1162-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 67296-2156-01 | Redpharm | 15 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 70377-0060-11 | Biocon | 30 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 70518-3499-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 70518-4201-00 | REMEDYREPACK | 180 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 70771-1163-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Labetalol hydrochloride 100 mg 71205-0095-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mgthis 71209-0083-05 | Cadila | 100 tablets | — | AB | FDA listed | — |
| Labetalol HCL 100 mg 71335-2145-01 | Bryant | 30 tablets | — | — | Discontinued | — |
| Labetalol Hydrochloride 100 mg 71335-2475-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 71335-3065-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 72162-1675-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 82804-0289-90 | Proficient | 90 tablets | — | AB | FDA listed | — |
| Labetalol Hydrochloride 100 mg 67046-1693-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71209-0083-03 | 60 TABLET, FILM COATED in 1 BOTTLE (71209-083-03) | 2018-06-30 | Active |
| 71209-0083-05 You're viewing this | 100 TABLET, FILM COATED in 1 BOTTLE (71209-083-05) | 2022-11-24 | Active |
| 71209-0083-10 | 500 TABLET, FILM COATED in 1 BOTTLE (71209-083-10) | 2022-11-24 | Active |
| 71209-0083-11 | 1000 TABLET, FILM COATED in 1 BOTTLE (71209-083-11) | 2018-06-30 | Active |
You're viewing one of 4 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71209-0083-05?
What is the difference between NDC 71209-0083-05 and NDC 71209-0083-03?
What NDC number is used to bill for this package of Labetalol Hydrochloride 100 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE Labetalol hydrochloride tablets, are indicated in the management of hypertension. Labetalol hydrochloride tablets may be used alone or in combination with other antihypertensive agents, especially thiazide and loop diuretics.
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION DOSAGE MUST BE INDIVIDUALIZED. The recommended initial dosage is 100 mg twice daily whether used alone or added to a diuretic regimen. After 2 or 3 days, using standing blood pressure as an indicator, dosage may be titrated in increments of 100 mg b.i.d. every 2 or 3 days.
The usual maintenance dosage of labetalol hydrochloride tablets is between 200 mg and 400 mg twice daily. Since the full antihypertensive effect of labetalol hydrochloride tablets are usually seen within the first 1 to 3 hours of the initial dose or dose increment, the assurance of a lack of an exaggerated hypotensive response can be clinically established in the office setting. The antihypertensive effects of continued dosing can be measured at subsequent visits, approximately 12 hours after a dose, to determine whether further titration is necessary.
Patients with severe hypertension may require from 1,200 mg to 2,400 mg per day, with or without thiazide diuretics. Should side effects (principally nausea or dizziness) occur with these doses administered b.i.d. (twice daily), the same total daily dose administered t.i.d.
(three times daily) may improve tolerability and facilitate further titration. Titration increments should not exceed 200 mg b.i.d. (twice daily).
When a diuretic is added, an additive antihypertensive effect can be expected. In some cases this may necessitate a labetalol hydrochloride tablet dosage adjustment. As with most antihypertensive drugs, optimal dosages of labetalol hydrochloride tablets are usually lower in patients also receiving a diuretic.
When transferring patients from other antihypertensive drugs, labetalol hydrochloride tablets should be introduced as recommended and the dosage of the existing therapy progressively decreased. Elderly Patients As in the general patient population, labetalol therapy may be initiated at 100 mg twice daily and titrated upwards in increments of 100 mg b.i.d. as required for control of blood pressure. Since some elderly patients eliminate labetalol more slowly, however, adequate control of blood pressure may be achieved at a lower maintenance dosage compared to the general population.
The majority of elderly patients will require between 100 mg and 200 mg b.i.d.
⛔ Contraindications ▾
CONTRAINDICATIONS Labetalol hydrochloride is contraindicated in bronchial asthma, overt cardiac failure, greater-than-first-degree heart block, cardiogenic shock, severe bradycardia, other conditions associated with severe and prolonged hypotension, and in patients with a history of hypersensitivity to any component of the product (see WARNINGS). Beta-blockers, even those with apparent cardioselectivity, should not be used in patients with a history of obstructive airway disease, including asthma.
⚠️ Warnings ▾
WARNINGS Hepatic Injury Severe hepatocellular injury, confirmed by rechallenge in at least one case, occurs rarely with labetalol therapy. The hepatic injury is usually reversible, but hepatic necrosis and death have been reported. Injury has occurred after both short- and long-term treatment and may be slowly progressive despite minimal symptomatology.
Similar hepatic events have been reported with a related research compound, dilevalol HCl, including two deaths. Dilevalol HCl is one of the four isomers of labetalol hydrochloride. Thus, for patients taking labetalol, periodic determination of suitable hepatic laboratory tests would be appropriate.
Appropriate laboratory testing should be done at the first symptom or sign of liver dysfunction (e.g., pruritus, dark urine, persistent anorexia, jaundice, right upper quadrant tenderness, or unexplained “flu-like” symptoms). If the patient has laboratory evidence of liver injury or jaundice, labetalol should be stopped and not restarted. Cardiac Failure Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure.
Beta-blockade carries a potential hazard of further depressing myocardial contractility and precipitating more severe failure. Although beta-blockers should be avoided in overt congestive heart failure, if necessary, labetalol hydrochloride can be used with caution in patients with a history of heart failure who are well compensated. Congestive heart failure has been observed in patients receiving labetalol hydrochloride.
Labetalol hydrochloride does not abolish the inotropic action of digitalis on heart muscle. In Patients Without a History of Cardiac Failure In patients with latent cardiac insufficiency, continued depression of the myocardium with beta-blocking agents over a period of time can, in some cases, lead to cardiac failure. At the first sign or symptom of impending cardiac failure, patients should be fully digitalized and/or be given a diuretic, and the response should be observed closely.
If cardiac failure continues, despite adequate digitalization and diuretic, therapy with labetalol hydrochloride should be withdrawn (gradually, if possible). Exacerbation of Ischemic Heart Disease Following Abrupt Withdrawal Angina pectoris has not been reported upon labetalol hydrochloride discontinuation. However, hypersensitivity to catecholamines has been observed in patients withdrawn from beta-blocker therapy; exacerbation of angina and, in some cases, myocardial infarction have occurred after abrupt discontinuation of such therapy.
When discontinuing chronically administered labetalol hydrochloride, particularly in patients with ischemic heart disease, the dosage should be gradually reduced over a period of 1 to 2 weeks and the patient should be carefully monitored. If angina markedly worsens or acute coronary insufficiency develops, therapy with labetalol hydrochloride should be reinstituted promptly, at least temporarily, and other measures appropriate for the management of unstable angina should be taken. Patients should be warned against interruption or discontinuation of therapy without the physician’s advice.
Because coronary artery disease is common and may be unrecognized, it may be prudent not to discontinue therapy with labetalol hydrochloride abruptly in patients being treated for hypertension. Nonallergic Bronchospasm (e.g., Chronic Bronchitis and Emphysema) Patients with bronchospastic disease should, in general, not receive beta-blockers . Labetalol hydrochloride may be used with caution, however, in patients who do not respond to, or cannot tolerate, other antihypertensive agents.
It is prudent, if labetalol hydrochloride is used, to use the smallest effective dose, so that inhibition of endogenous or exogenous beta-agonists is minimized. Pheochromocytoma Labetalol hydrochloride has been shown to be effective in lowering blood pressure and relieving symptoms in patients with pheochromocytoma. However, paradox…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Most adverse effects are mild and transient and occur early in the course of treatment. In controlled clinical trials of 3 to 4 months’ duration, discontinuation of labetalol hydrochloride due to one or more adverse effects was required in 7% of all patients. In these same trials, other agents with solely beta- blocking activity used in the control groups led to discontinuation in 8% to 10% of patients, and a centrally acting alpha-agonist led to discontinuation in 30% of patients.
The incidence rates of adverse reactions listed in the following table were derived from multicenter, controlled clinical trials comparing labetalol hydrochloride, placebo, metoprolol, and propranolol over treatment periods of 3 and 4 months. Where the frequency of adverse effects for labetalol hydrochloride and placebo is similar, causal relationship is uncertain. The rates are based on adverse reactions considered probably drug related by the investigator.
If all reports are considered, the rates are somewhat higher (e.g., dizziness, 20%; nausea, 14%; fatigue, 11%), but the overall conclusions are unchanged. Labetalol Hydrochloride (N=227) % Placebo (N=98) % Propranolol (N=84) % Metoprolol (N=49) % Body as a whole Fatigue 5 0 12 12 Asthenia 1 1 1 0 Headache 2 1 1 2 Gastrointestinal Nausea 6 1 1 2 Vomiting <1 0 0 0 Dyspepsia 3 1 1 0 Abdominal pain 0 0 1 2 Diarrhea <1 0 2 0 Taste distortion 1 0 0 0 Central and Peripheral Nervous Systems Dizziness 11 3 4 4 Paresthesia <1 0 0 0 Drowsiness <1 2 2 2 Autonomic Nervous System Nasal stuffiness 3 0 0 0 Ejaculation failure 2 0 0 0 Impotence 1 0 1 3 Increased sweating <1 0 0 0 Cardiovascular Edema 1 0 0 0 Postural hypotension 1 0 0 0 Bradycardia 0 0 5 12 Respiratory Dyspnea 2 0 1 2 Skin Rash 1 0 0 0 Special Senses Vision abnormality 1 0 0 0 Vertigo 2 1 0 0 The adverse effects were reported spontaneously and are representative of the incidence of adverse effects that may be observed in a properly selected hypertensive patient population, i.e., a group excluding patients with bronchospastic disease, overt congestive heart failure, or other contraindications to beta-blocker therapy.
Clinical trials also included studies utilizing daily doses up to 2,400 mg in more severely hypertensive patients. Certain of the side effects increased with increasing dose, as shown in the following table that depicts the entire U.S. therapeutic trials data base for adverse reactions that are clearly or possibly dose related. Labetalol Hydrochloride Daily Dose (mg) 200 300 400 600 800 900 1,200 1,600 2,400 Number of Patients 522 181 606 608 503 117 411 242 175 Dizziness (%) 2 3 3 3 5 1 9 13 16 Fatigue 2 1 4 4 5 3 7 6 10 Nausea <1 0 1 2 4 0 7 11 19 Vomiting 0 0 <1 <1 <1 0 1 2 3 Dyspepsia 1 0 2 1 1 0 2 2 4 Paresthesias 2 0 2 2 1 1 2 5 5 Nasal Stuffiness 1 1 2 2 2 2 4 5 6 Ejaculation Failure 0 2 1 2 3 0 4 3 5 Impotence 1 1 1 1 2 4 3 4 3 Edema 1 0 1 1 1 0 1 2 2 In addition, a number of other less common adverse events have been reported: Body as a Whole : Fever.
Cardiovascular : Hypotension, and rarely, syncope, bradycardia, heart block. Central and Peripheral Nervous Systems : Paresthesia, most frequently described as scalp tingling. In most cases, it was mild and transient and usually occurred at the beginning of treatment.
Collagen Disorders : Systemic lupus erythematosus, positive antinuclear factor. Eyes : Dry eyes. Immunological System : Antimitochondrial antibodies.
Liver and Biliary System : Hepatic necrosis, hepatitis, cholestatic jaundice, elevated liver function tests. Musculoskeletal System : Muscle cramps, toxic myopathy. Respiratory System : Bronchospasm.
Skin and Appendages : Rashes of various types, such as generalized maculopapular, lichenoid, urticarial, bullous lichen planus, psoriaform, and facial erythema; Peyronie’s disease, reversible alopecia. Urinary System : Difficulty in micturition, including acute urinary bladder retention. Hypersensitivity : Rare reports of hypersensitivity (e.g., rash, u…
🔄 Drug Interactions ▾
DRUG INTERACTIONS In one survey, 2.3% of patients taking labetalol hydrochloride in combination with tricyclic antidepressants experienced tremor, as compared to 0.7% reported to occur with labetalol hydrochloride alone. The contribution of each of the treatments to this adverse reaction is unknown, but the possibility of a drug interaction cannot be excluded. Drugs possessing beta-blocking properties can blunt the bronchodilator effect of beta-receptor agonist drugs in patients with bronchospasm; therefore, doses greater than the normal anti-asthmatic dose of beta-agonist bronchodilator drugs may be required.
Cimetidine has been shown to increase the bioavailability of labetalol hydrochloride. Since this could be explained either by enhanced absorption or by an alteration of hepatic metabolism of labetalol hydrochloride, special care should be used in establishing the dose required for blood pressure control in such patients. Synergism has been shown between halothane anesthesia and intravenously administered labetalol hydrochloride.
During controlled hypotensive anesthesia using labetalol hydrochloride in association with halothane, high concentrations (3% or above) of halothane should not be used because the degree of hypotension will be increased and because of the possibility of a large reduction in cardiac output and an increase in central venous pressure. The anesthesiologist should be informed when a patient is receiving labetalol hydrochloride. Labetalol hydrochloride blunts the reflex tachycardia produced by nitroglycerin without preventing its hypotensive effect.
If labetalol hydrochloride is used with nitroglycerin in patients with angina pectoris, additional antihypertensive effects may occur. Care should be taken if labetalol is used concomitantly with calcium antagonists of the verapamil type. Both digitalis glycosides and beta-blockers slow atrioventricular conduction and decrease heart rate.
Concomitant use can increase the risk of bradycardia. Risk of Anaphylactic Reaction While taking beta-blockers, patients with a history of severe anaphylactic reaction to a variety of allergens may be more reactive to repeated challenge, either accidental, diagnostic, or therapeutic. Such patients may be unresponsive to the usual doses of epinephrine used to treat allergic reaction.
🔄 Drug / Laboratory Test Interactions ▾
DRUG & OR LABORATORY TEST INTERACTIONS The presence of labetalol metabolites in the urine may result in falsely elevated levels of urinary catecholamines, metanephrine, normetanephrine, and vanillylmandelic acid when measured by fluorimetric or photometric methods. In screening patients suspected of having a pheochromocytoma and being treated with labetalol hydrochloride, a specific method, such as a high performance liquid chromatographic assay with solid phase extraction (e.g., J. Chromatogr 385:241, 1987) should be employed in determining levels of catecholamines.
Labetalol hydrochloride has also been reported to produce a false-positive test for amphetamine when screening urine for the presence of drugs using the commercially available assay methods TOXI-LAB ® A (thin-layer chromatographic assay) and EMIT-d.a.u. ® (radioenzymatic assay). When patients being treated with labetalol have a positive urine test for amphetamine using these techniques, confirmation should be made by using more specific methods, such as a gas chromatographic-mass spectrometer technique.
🤰 Pregnancy ▾
PREGNANCY Teratogenic Effects Pregnancy Category C Teratogenic studies were performed with labetalol in rats and rabbits at oral doses up to approximately six and four times the maximum recommended human dose (MRHD), respectively. No reproducible evidence of fetal malformations was observed. Increased fetal resorptions were seen in both species at doses approximating the MRHD.
A teratology study performed with labetalol in rabbits at intravenous doses up to 1.7 times the MRHD revealed no evidence of drug-related harm to the fetus. There are no adequate and well-controlled studies in pregnant women. Labetalol should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Nonteratogenic Effects Hypotension, bradycardia, hypoglycemia, and respiratory depression have been reported in infants of mothers who were treated with labetalol hydrochloride for hypertension during pregnancy. Oral administration of labetalol to rats during late gestation through weaning at doses of two to four times the MRHD caused a decrease in neonatal survival.
🧒 Pediatric Use ▾
PEDIATRIC USE Safety and effectiveness in pediatric patients have not been established. Elderly Patients As in the general population, some elderly patients (60 years of age and older) have experienced orthostatic hypotension, dizziness, or lightheadedness during treatment with labetalol. Because elderly patients are generally more likely than younger patients to experience orthostatic symptoms, they should be cautioned about the possibility of such side effects during treatment with labetalol.
🆘 Overdosage ▾
OVERDOSAGE Overdosage with labetalol hydrochloride causes excessive hypotension that is posture sensitive and, sometimes, excessive bradycardia. Patients should be placed supine and their legs raised, if necessary, to improve the blood supply to the brain. If overdosage with labetalol hydrochloride follows oral ingestion, gastric lavage or pharmacologically induced emesis (using syrup of ipecac) may be useful for removal of the drug shortly after ingestion.
The following additional measures should be employed if necessary: Excessive bradycardia -administer atropine or epinephrine. Cardiac failure -administer a digitalis glycoside and a diuretic. Dopamine or dobutamine may also be useful.
Hypotension -administer vasopressors, e.g., norepinephrine. There is pharmacologic evidence that norepinephrine may be the drug of choice. Bronchospasm -administer epinephrine and/or an aerosolized beta 2 -agonist.
Seizures - administer diazepam. In severe beta-blocker overdose resulting in hypotension and/or bradycardia, glucagon has been shown to be effective when administered in large doses (5 mg to 10 mg rapidly over 30 seconds, followed by continuous infusion of 5 mg per hour that can be reduced as the patient improves). Neither hemodialysis nor peritoneal dialysis removes a significant amount of labetalol hydrochloride from the general circulation (<1%).
The oral LD 50 value of labetalol hydrochloride in the mouse is approximately 600 mg/kg and in the rat is >2 g/kg. The intravenous LD 50 in these species is 50 mg/kg to 60 mg/kg.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Labetalol hydrochloride combines both selective, competitive, alpha 1 -adrenergic blocking and nonselective, competitive, beta-adrenergic blocking activity in a single substance. In man, the ratios of alpha- to beta-blockade have been estimated to be approximately 1:3 and 1:7 following oral and intravenous (IV) administration, respectively.Beta 2 -agonist activity has been demonstrated in animals with minimal beta 1 -agonist (ISA) activity detected. In animals, at doses greater than those required for alpha- or beta-adrenergic blockade, a membrane-stabilizing effect has been demonstrated.
Pharmacodynamics The capacity of labetalol hydrochloride to block alpha receptors in man has been demonstrated by attenuation of the pressor effect of phenylephrine and by a significant reduction of the pressor response caused by immersing the hand in ice-cold water (“cold pressor test”). Labetalol hydrochloride’s beta 1 - receptor blockade in man was demonstrated by a small decrease in the resting heart rate, attenuation of tachycardia produced by isoproterenol or exercise, and by attenuation of the reflex tachycardia to the hypotension produced by amyl nitrite.Beta 2 -receptor blockade was demonstrated by inhibition of the isoproterenol-induced fall in diastolic blood pressure.
Both the alpha- and beta-blocking actions of orally administered labetalol hydrochloride contribute to a decrease in blood pressure in hypertensive patients. Labetalol hydrochloride consistently, in dose-related fashion, blunted increases in exercise-induced blood pressure and heart rate, and in their double product. The pulmonary circulation during exercise was not affected by labetalol hydrochloride dosing.
Single oral doses of labetalol hydrochloride administered to patients with coronary artery disease had no significant effect on sinus rate, intraventricular conduction, or QRS duration. The atrioventricular (A-V) conduction time was modestly prolonged in two of seven patients. In another study, intravenous (IV) labetalol hydrochloride slightly prolonged A-V nodal conduction time and atrial effective refractory period with only small changes in heart rate.
The effects on A-V nodal refractoriness were inconsistent. Labetalol hydrochloride produces dose-related falls in blood pressure without reflex tachycardia and without significant reduction in heart rate, presumably through a mixture of its alpha-blocking and beta-blocking effects. Hemodynamic effects are variable with small, nonsignificant changes in cardiac output seen in some studies but not others, and small decreases in total peripheral resistance.
Elevated plasma renins are reduced. Doses of labetalol hydrochloride that controlled hypertension did not affect renal function in mildly to severely hypertensive patients with normal renal function. Due to the alpha 1 -receptor blocking activity of labetalol hydrochloride, blood pressure is lowered more in the standing than in the supine position, and symptoms of postural hypotension (2%), including rare instances of syncope, can occur.
Following oral administration, when postural hypotension has occurred, it has been transient and is uncommon when the recommended starting dose and titration increments are closely followed (see DOSAGE AND ADMINISTRATION). Symptomatic postural hypotension is most likely to occur 2 to 4 hours after a dose, especially following the use of large initial doses or upon large changes in dose. The peak effects of single oral doses of labetalol hydrochloride occur within 2 to 4 hours.
The duration of effect depends upon dose, lasting at least 8 hours following single oral doses of 100 mg and more than 12 hours following single oral doses of 300 mg. The maximum, steady-state blood pressure response upon oral, twice-a-day dosing occurs within 24 to 72 hours. The antihypertensive effect of labetalol has a linear correlation with the logarithm of labetalol plasma concentration, and there is also a linear correlation be…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Labetalol hydrochloride tablets, USP for oral administration, are available as: 100 mg : White, round, film coated tablets debossed with “C and 82”on either side of the breakline on one side and plain on the other side and supplied as: NDC 71209-083-03 bottles of 60 NDC 71209-083-05 bottles of 100 NDC 71209-083-10 bottles of 500 NDC 71209-083-11 bottles of 1000 200 mg : White, round, film coated tablets debossed with “C and 83”on either side of the breakline on one side and plain on the other side and supplied as: NDC 71209-084-03 bottles of 60 NDC 71209-084-05 bottles of 100 NDC 71209-084-10 bottles of 500 NDC 71209-084-11 bottles of 1000 300 mg : White, round, film coated tablets debossed with “C84” on one side and plain on the other side and supplied as: NDC 71209-085-03 bottles of 60 NDC 71209-085-05 bottles of 100 NDC 71209-085-10 bottles of 500 NDC 71209-085-11 bottles of 1000 Labetalol hydrochloride tablets, USP should be stored at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
Dispense in a tight, light-resistant container as defined in the USP with a child-resistant closure as required. To report SUSPECTED ADVERSE REACTIONS, contact Cadila Pharmaceuticals Limited at 1-202-355-9785 (Fax 1-202-355-9784), or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . Trademarks are the property of their respective owners.
Manufactured by: Cadila Pharmaceuticals Limited 1389, Dholka, District - Ahmedabad, Gujarat State, INDIA. Rev.09/2022
📋 Description ▾
DESCRIPTION Labetalol hydrochloride tablets, USP are an adrenergic receptor blocking agent that has both selective alpha 1 -adrenergic and nonselective beta-adrenergic receptor blocking actions in a single substance. Labetalol hydrochloride, USP is a racemate, chemically designated as 2-hydroxy-5-[1-hydroxy-2-[(1-methyl-3-phenylpropyl)amino]ethyl] benzamide monohydrochloride, and it has the following structure: Labetalol hydrochloride, USP has the molecular formula C 19 H 24 N 2 O 3 •HCl and a molecular weight of 364.87.
It has two asymmetric centers and therefore exists as a molecular complex of two diastereoisomeric pairs. Dilevalol, the R,R’ stereoisomer, makes up 25% of racemic labetalol. Labetalol hydrochloride, USP is a white to off-white powder, soluble in water and in alcohol.
Insoluble in ether and in chloroform. Labetalol hydrochloride tablets, USP for oral administration, contains 100 mg, 200 mg or 300 mg of labetalol hydrochloride USP. In addition, each tablet contains the following inactive ingredients: colloidal silicon dioxide, corn starch, hydroxypropyl methyl cellulose, lactose monohydrate, magnesium stearate, opadry white, polysorbate, and sodium starch glycolate (potato).
Opadry white contains hypromellose, polyethylene glycol, titanium dioxide, and talc. labetalol-spl-strc
💬 Information for Patients ▾
INFORMATION FOR PATIENTS As with all drugs with beta-blocking activity, certain advice to patients being treated with labetalol hydrochloride is warranted. This information is intended to aid in the safe and effective use of this medication. It is not a disclosure of all possible adverse or intended effects.
While no incident of the abrupt withdrawal phenomenon (exacerbation of angina pectoris) has been reported with labetalol hydrochloride, dosing with labetalol hydrochloride should not be interrupted or discontinued without a physician’s advice. Patients being treated with labetalol hydrochloride should consult a physician at any signs or symptoms of impending cardiac failure or hepatic dysfunction (see WARNINGS). Also, transient scalp tingling may occur, usually when treatment with labetalol hydrochloride is initiated (see ADVERSE REACTIONS ).