
Plerixafor 24 mg/1.2mL Solution, 1 vial — NDC 71288-155-01 (Billing 71288-0155-01)
This is a package of 1 vial of Plerixafor 24 mg/1.2mL Solution from Meitheal Pharmaceuticals Inc., marketed since Jul 2023 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 064684
- GCN: 16124
- GPI-14 (Medi-Span): 82502060002020
- HICL (First Databank): 036021
- AHFS class code: 20:16.00.00
- RxCUI (RxNorm): 828700
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Hematopoietic Stem Cell Mobilizer class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Plerixafor injection is used along with a granulocyte-colony stimulating factor (G-CSF) medication such as filgrastim (Neupogen) or pegfilgrastim (Neulasta) to prepare the blood for an autologous stem cell transplant (procedure in which certain blood cells are removed from the body and then returned to the body after chemotherapy and/or radiation) in patients with non-Hodgkin's lymphoma (NHL; cancer that begins in a type of white blood cells that normally fights infection) or multiple myeloma (a type of cancer of the bone marrow). Plerixafor injection is in a class of medications called hemato...
Read the full MedlinePlus article ↗- It helps move stem cells from your bone marrow into your blood so they can be collected. Those cells are later given back to you in an autologous transplant. It's used with filgras...
- It's an injection under your skin. You'll have filgrastim daily for 4 days first. Then you get plerixafor about 11 hours before each collection session, for up to 4 days in a row.
- Diarrhea, nausea, tiredness, headache, dizziness, and soreness or redness where the shot goes in are common. Joint pain and vomiting can happen too. Most are mild to moderate.
- Tell them right away about hives, swelling, trouble breathing, or feeling faint. Also report pain in the left upper belly or shoulder, which could mean a spleen problem. You'll be...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2562 | $28.489 / J2562 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 71288-0155-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / 1.2 mL in 1 VIAL, SINGLE-DOSE | 2023-07-24 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mozobil 24 mg/1.2mL 00024-5862-01 | Sanofi-Aventis | 1 vial | — | AP | FDA listed | — |
| Plerixafor 20 mg/mL 25021-0416-01 | Sagent | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 31722-0373-31 | Camber | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 43598-0308-23 | Dr. | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 55150-0356-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 65219-0284-12 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 68083-0155-01 | Gland | 1 vial | — | AP | FDA listed | — |
| plerixafor 24 mg/1.2mL 70121-1694-02 | Amneal | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 70710-1208-01 | Zydus | 1 vial | — | — | FDA listed | — |
| Plerixafor 24 mg/1.2mL 70771-1776-01 | Zydus | 1 vial | — | — | FDA listed | — |
| Plerixafor 24 mg/1.2mLthis 71288-0155-01 | Meitheal | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 72162-2642-02 | Bryant | 1 vial | — | AP | FDA listed | — |
| Plerixafor 24 mg/1.2mL 72205-0249-01 | Novadoz | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
5.9 mg / 1.2 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Plerixafor Injection is indicated in combination with filgrastim to mobilize hematopoietic stem cells (HSCs) to the peripheral blood for collection and subsequent autologous transplantation in patients with non-Hodgkin’s lymphoma (NHL) or multiple myeloma (MM). Plerixafor Injection, a hematopoietic stem cell mobilizer, is indicated in combination with filgrastim to mobilize hematopoietic stem cells (HSCs) to the peripheral blood for collection and subsequent autologous transplantation in patients with non-Hodgkin’s lymphoma or multiple myeloma.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Initiate plerixafor injection treatment after the patient has received filgrastim once daily for 4 days. ( 2.1 ) Repeat plerixafor injection dose up to 4 consecutive days. ( 2.1 ) Dose based on patient weight Less than or equal to 83 kg: 20 mg dose or select dose based on 0.24 mg/kg actual body weight.
( 2.1 ) Greater than 83 kg: select dose based on 0.24 mg/kg actual body weight. ( 2.1 ) Administer by subcutaneous injection approximately 11 hours prior to initiation of apheresis. ( 2.1 ) Renal impairment: If creatinine clearance is ≤50 mL/min, decrease dose by one-third to 0.16 mg/kg.
( 2.3 )
2.1Recommended Dosage and Administration Begin treatment with plerixafor injection after the patient has received filgrastim once daily for 4 days [see Dosage and Administration (2.2) ] . Administer plerixafor injection approximately 11 hours prior to initiation of each apheresis for up to 4 consecutive days. The recommended dose of plerixafor injection by subcutaneous injection is based on body weight: 20 mg fixed dose or 0.24 mg/kg of body weight for patients weighing less than or equal to 83 kg [see Clinical Pharmacology (12.3) ] .
0.24mg/kg of body weight for patients weighing greater than 83 kg Use the patient’s actual body weight to calculate the volume of plerixafor injection to be administered. Each vial delivers 1.2 mL of 20 mg per mL solution, and the volume to be administered to patients should be calculated from the following equation: 0.012 × patient’s actual body weight (in kg) = volume to be administered (in mL) In clinical studies, plerixafor injection dose has been calculated based on actual body weight in patients up to 175% of ideal body weight.
Plerixafor injection dose and treatment of patients weighing more than 175% of ideal body weight have not been investigated. Based on increasing exposure with increasing body weight, the plerixafor injection dose should not exceed 40 mg/day [see Clinical Pharmacology (12.3) ] . Vials should be inspected visually for particulate matter and discoloration prior to administration and should not be used if there is particulate matter or if the solution is discolored.
Discard unused portion.
2.2Recommended Concomitant Medications Administer daily morning doses of filgrastim 10 mcg/kg for 4 days prior to the first evening dose of plerixafor injection and on each day prior to apheresis [see Clinical Studies (14) ] .
2.3Dose Modifications in Renal Impairment In patients with moderate and severe renal impairment (estimated creatinine clearance (CL CR ) less than or equal to 50 mL/min), reduce the dose of plerixafor injection by one-third based on body weight category as shown in Table 1 . If CL CR is less than or equal to 50 mL/min the dose should not exceed 27 mg/day, as the mg/kg-based dosage results in increased plerixafor exposure with increasing body weight [see Clinical Pharmacology (12.3) ] . Similar systemic exposure is predicted if the dose is reduced by one-third in patients with moderate and severe renal impairment compared with subjects with normal renal function [see Clinical Pharmacology (12.3) ] .
Table 1: Recommended Dosage of Plerixafor Injection in Patients with Renal Impairment Estimated Creatinine Clearance (mL/min) Dose Body Weight less than or equal to 83 kg Body Weight greater than 83 kg and less than 160 kg greater than 50 20 mg or 0.24 mg/kg once daily 0.24 mg/kg once daily (not to exceed 40 mg/day) less than or equal to 50 13 mg or 0.16 mg/kg once daily 0.16 mg/kg once daily (not to exceed 27 mg/day) The following (Cockcroft-Gault) formula may be used to estimate CL CR : Males: Creatinine clearance (mL/min) = weight (kg) × (140 – age in years) 72 × serum creatinine (mg/dL) Females: Creatinine clearance (mL/min) = 0.85 × value calculated for males There is insufficient information to make dosage recommendations in patients on hemodialysis.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 24 mg per 1.2 mL (20 mg per mL) sterile, clear, colorless to pale yellow solution in a single-dose vial. Injection: 24 mg per 1.2 mL (20 mg per mL) in a single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Plerixafor is contraindicated in patients with a history of hypersensitivity to plerixafor [see Warnings and Precautions (5.1) ] . Anaphylactic shock has occurred with use of plerixafor. History of hypersensitivity to plerixafor. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Anaphylactic Shock and Serious Hypersensitivity Reactions have occurred. Monitor patients during and after completion of plerixafor administration. ( 5.1 ) Tumor Cell Mobilization in Leukemia Patients: plerixafor may mobilize leukemic cells and should not be used in leukemia patients.
( 5.2 ) Hematologic Effects: Increased circulating leukocytes and decreased platelet counts have been observed. Monitor blood cell counts and platelet counts during plerixafor use. ( 5.3 ) Potential for Tumor Cell Mobilization: Tumor cells may be released from marrow during HSC mobilization with plerixafor and filgrastim.
Effect of reinfusion of tumor cells is unknown. ( 5.4 ) Splenic Rupture: Evaluate patients who report left upper abdominal and/or scapular or shoulder pain. ( 5.5 ) Embryo-Fetal Toxicity: Can cause fetal harm.
Advise women not to become pregnant when taking plerixafor. ( 5.6 , 8.1 )
5.1Anaphylactic Shock and Hypersensitivity Reactions Serious hypersensitivity reactions, including anaphylactic-type reactions, some of which have been life-threatening with clinically significant hypotension and shock have occurred in patients receiving plerixafor [see Adverse Reactions (6.2) ] . Observe patients for signs and symptoms of hypersensitivity during and after plerixafor administration for at least 30 minutes and until clinically stable following completion of each administration. Only administer plerixafor when personnel and therapies are immediately available for the treatment of anaphylaxis and other hypersensitivity reactions.
In clinical studies, mild or moderate allergic reactions occurred within approximately 30 minutes after plerixafor administration in less than 1% of patients [see Adverse Reactions (6.1) ] .
5.2Tumor Cell Mobilization in Leukemia Patients For the purpose of HSC mobilization, plerixafor may cause mobilization of leukemic cells and subsequent contamination of the apheresis product. Therefore, plerixafor is not intended for HSC mobilization and harvest in patients with leukemia.
5.3Hematologic Effects Leukocytosis Administration of plerixafor in conjunction with filgrastim increases circulating leukocytes as well as HSC populations. Monitor white blood cell counts during plerixafor use [see Adverse Reactions (6.1) ] . Thrombocytopenia Thrombocytopenia has been observed in patients receiving plerixafor. Monitor platelet counts in all patients who receive plerixafor and then undergo apheresis.
5.4Potential for Tumor Cell Mobilization When plerixafor is used in combination with filgrastim for HSC mobilization‚ tumor cells may be released from the marrow and subsequently collected in the leukapheresis product. The effect of potential reinfusion of tumor cells has not been well-studied.
5.5Splenic Enlargement and Rupture Higher absolute and relative spleen weights associated with extramedullary hematopoiesis were observed following prolonged (2 to 4 weeks) daily plerixafor SC administration in rats at doses approximately 4-fold higher than the recommended human dose based on body surface area. The effect of plerixafor on spleen size in patients was not specifically evaluated in clinical studies. Cases of splenic enlargement and/or rupture have been reported following the administration of plerixafor in conjunction with filgrastim.
Evaluate individuals receiving plerixafor in combination with filgrastim who report left upper abdominal pain and/or scapular or shoulder pain for splenic integrity.
5.6Embryo-Fetal Toxicity Based on findings from animal reproduction studies, plerixafor can cause fetal harm when administered to a pregnant woman. Plerixafor administration to pregnant rats during organogenesis resulted in embryo-fetal mortality, structural abnormalities, and alterations to growth at exposures approximately 10 times the exposure at the recommended human dose. Advise pregnant women of the potential risk to the fetus.
Advise females of reproductive potential to use an effective for… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed elsewhere in the labeling: Anaphylactic shock and hypersensitivity reactions [see Warnings and Precautions (5.1) ] Potential for tumor cell mobilization in leukemia patients [see Warnings and Precautions (5.2) ] Increased circulating leukocytes and decreased platelet counts [see Warnings and Precautions (5.3) ] Potential for tumor cell mobilization [see Warnings and Precautions (5.4) ] Splenic enlargement [see Warnings and Precautions (5.5) ] Most common adverse reactions (≥10%): diarrhea, nausea, fatigue, injection site reactions, headache, arthralgia, dizziness, and vomiting.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Meitheal Pharmaceuticals, Inc. at 1-844-824-8426 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The most common adverse reactions (≥10%) reported in patients who received plerixafor in conjunction with filgrastim regardless of causality and more frequent with plerixafor than placebo during HSC mobilization and apheresis were diarrhea, nausea, fatigue, injection site reactions, headache, arthralgia, dizziness, and vomiting.
Safety data for plerixafor in combination with filgrastim were obtained from two randomized placebo-controlled studies (301 patients) and 10 uncontrolled studies (242 patients). Patients were primarily treated with plerixafor at daily doses of 0.24 mg/kg SC. Median exposure to plerixafor in these studies was 2 days (range 1 to 7 days).
In the two randomized studies in patients with NHL and MM, a total of 301 patients were treated in the plerixafor and filgrastim group and 292 patients were treated in the placebo and filgrastim group. Patients received daily morning doses of filgrastim 10 mcg/kg for 4 days prior to the first dose of plerixafor 0.24 mg/kg SC or placebo and on each morning prior to apheresis. The adverse reactions that occurred in ≥5% of the patients who received plerixafor regardless of causality and were more frequent with plerixafor than placebo during HSC mobilization and apheresis are shown in Table 2.
Table 2: Adverse Reactions in ≥5% of Non-Hodgkin's Lymphoma and Multiple Myeloma Patients Receiving Plerixafor and More Frequent than Placebo during HSC Mobilization and Apheresis a Grades based on criteria from the World Health Organization (WHO) Percent of Patients (%) Plerixafor and Filgrastim (n=301) Placebo and Filgrastim (n=292) All Grades a Grade 3 Grade 4 All Grades Grade 3 Grade 4 Gastrointestinal disorders Diarrhea 37 <1 0 17 0 0 Nausea 34 1 0 22 0 0 Vomiting 10 <1 0 6 0 0 Flatulence 7 0 0 3 0 0 General disorders and administration site conditions Injection site reactions 34 0 0 10 0 0 Fatigue 27 0 0 25 0 0 Musculoskeletal and connective tissue disorders Arthralgia 13 0 0 12 0 0 Nervous system disorders Headache 22 <1 0 21 1 0 Dizziness 11 0 0 6 0 0 Psychiatric disorders Insomnia 7 0 0 5 0 0 In the randomized studies, 34% of patients with NHL or MM had mild to moderate injection site reactions at the site of subcutaneous administration of plerixafor.
These included erythema, hematoma, hemorrhage, induration, inflammation, irritation, pain, paresthesia, pruritus, rash, swelling, and urticaria. Mild to moderate allergic reactions were observed in less than 1% of patients within approximately 30 min after plerixafor administration, including one or more of the following: urticaria (n=2), periorbital swelling (n=2), dyspnea (n=1) or hypoxia (n=1). Symptoms generally responded to treatments (e.g., antihistamines, corticosteroids, hydration or supplemental oxygen) or resolved spontaneously.
Vasovagal reactions, orthostatic hypotension, and/or syncope can occur following subcutaneou… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Limited available data with plerixafor use in pregnant women are insufficient to inform a drug-associated risk of adverse developmental outcomes. In animal reproduction studies, subcutaneous administration of plerixafor to pregnant rats during organogenesis at doses 10 times the maximum recommended human doses resulted in embryo-fetal mortality, structural abnormalities, and alterations to growth [see Data ] . Advise pregnant women of the potential risk to the fetus.
Advise women of reproductive potential to avoid becoming pregnant while receiving treatment with plerixafor [see Warnings and Precautions (5.6) ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The background risk of major birth defects and miscarriages for the indicated population is unknown. Data Animal data Plerixafor administered to pregnant rats induced embryo-fetal toxicity, including fetal death, increased resorptions and postimplantation loss, decreased fetal weights, anophthalmia, shortened digits, cardiac interventricular septal defect, ringed aorta, globular heart, hydrocephaly, dilatation of olfactory ventricles, and retarded skeletal development. Embryo-fetal toxicities occurred mainly at a dose of 90 mg/m 2 (approximately 10 times the recommended human dose of 0.24 mg/kg when compared on a mg/m 2 basis).
8.2Lactation Risk Summary There are no data on the presence of plerixafor in human milk, the effect on the breastfed child, or the effect on milk production. Because of the potential serious adverse reactions in the breastfed child, advise females that breastfeeding is not recommended during treatment with plerixafor and for one week after the final dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify pregnancy status in females of reproductive potential prior to initiating plerixafor [see Use in Specific Populations (8.1) ] . Contraception Females Plerixafor can cause embryo-fetal harm when administered to pregnant women [see Use in Specific Populations (8.1) ] . Advise females of reproductive potential to use effective contraception during treatment with plerixafor and for one week after the final dose.
Males Males treated with plerixafor should use effective contraception during treatment and for one week after cessation of treatment.
8.4Pediatric Use The safety and effectiveness of plerixafor have not been established in pediatric patients. Effectiveness was not demonstrated in a single phase 1/2 randomized, open-label, comparative study of plerixafor plus standard regimens for mobilization of hematopoietic stem cells to the peripheral blood for collection and subsequent autologous transplantation. Forty-five pediatric patients ages 1 to <17 years with solid tumors or lymphoma were randomized 2:1 to plerixafor in addition to standard mobilization regimens (N=30) or standard mobilization regimens alone (N=15) (comparator arm).
No new safety signals were observed in pediatric patients in this trial. The day prior to the first apheresis, median peripheral blood CD34+ counts were 35 × 10 6 cells/L in the comparator arm and 15 × 10 6 cells/L in the plerixafor arm. On the day of the first apheresis, median peripheral blood CD34+ counts were 64 × 10 6 cells/L in the comparator arm and 77 × 10 6 cells/L in the plerixafor arm.
Plerixafor exposure, shown as AUC, in pediatric patients aged 12 to 18 years was within the range of values previously observed in adults, while the AUC of plerixafor in pediatric patients aged 2 to 12 years was 67% to 87% of that observed in adults, given the same adult dose (0.24 mg/kg).
8.5Geriatric Use Of the total number of subjects in controlled clinical studies of plerixafor, 24… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data with plerixafor use in pregnant women are insufficient to inform a drug-associated risk of adverse developmental outcomes. In animal reproduction studies, subcutaneous administration of plerixafor to pregnant rats during organogenesis at doses 10 times the maximum recommended human doses resulted in embryo-fetal mortality, structural abnormalities, and alterations to growth [see Data ] . Advise pregnant women of the potential risk to the fetus.
Advise women of reproductive potential to avoid becoming pregnant while receiving treatment with plerixafor [see Warnings and Precautions (5.6) ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The background risk of major birth defects and miscarriages for the indicated population is unknown. Data Animal data Plerixafor administered to pregnant rats induced embryo-fetal toxicity, including fetal death, increased resorptions and postimplantation loss, decreased fetal weights, anophthalmia, shortened digits, cardiac interventricular septal defect, ringed aorta, globular heart, hydrocephaly, dilatation of olfactory ventricles, and retarded skeletal development. Embryo-fetal toxicities occurred mainly at a dose of 90 mg/m 2 (approximately 10 times the recommended human dose of 0.24 mg/kg when compared on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of plerixafor have not been established in pediatric patients. Effectiveness was not demonstrated in a single phase 1/2 randomized, open-label, comparative study of plerixafor plus standard regimens for mobilization of hematopoietic stem cells to the peripheral blood for collection and subsequent autologous transplantation. Forty-five pediatric patients ages 1 to <17 years with solid tumors or lymphoma were randomized 2:1 to plerixafor in addition to standard mobilization regimens (N=30) or standard mobilization regimens alone (N=15) (comparator arm).
No new safety signals were observed in pediatric patients in this trial. The day prior to the first apheresis, median peripheral blood CD34+ counts were 35 × 10 6 cells/L in the comparator arm and 15 × 10 6 cells/L in the plerixafor arm. On the day of the first apheresis, median peripheral blood CD34+ counts were 64 × 10 6 cells/L in the comparator arm and 77 × 10 6 cells/L in the plerixafor arm.
Plerixafor exposure, shown as AUC, in pediatric patients aged 12 to 18 years was within the range of values previously observed in adults, while the AUC of plerixafor in pediatric patients aged 2 to 12 years was 67% to 87% of that observed in adults, given the same adult dose (0.24 mg/kg).
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in controlled clinical studies of plerixafor, 24% were 65 and over, while 0.8% were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Since plerixafor is mainly excreted by the kidney, no dose modifications are necessary in elderly individuals with normal renal function.
In general, care should be taken in dose selection for elderly patients due to the greater frequency of decreased renal function with advanced age. Dosage adjustment in elderly patients with CL CR less than or equal to 50 mL/min is recommended [see Dosage and Administration (2.3) and Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE Based on limited data at doses above the recommended dose of 0.24 mg/kg SC, the frequency of gastrointestinal disorders, vasovagal reactions, orthostatic hypotension, and/or syncope may be higher.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Plerixafor is an inhibitor of the CXCR4 chemokine receptor and blocks binding of its cognate ligand, stromal cell-derived factor-1α (SDF-1α). SDF-1α and CXCR4 are recognized to play a role in the trafficking and homing of human hematopoietic stem cells (HSCs) to the marrow compartment. Once in the marrow, stem cell CXCR4 can act to help anchor these cells to the marrow matrix, either directly via SDF-1α or through the induction of other adhesion molecules.
Treatment with plerixafor resulted in leukocytosis and elevations in circulating hematopoietic progenitor cells in mice, dogs and humans. CD34+ cells mobilized by plerixafor were capable of engraftment with long-term repopulating capacity up to one year in canine transplantation models.
12.2Pharmacodynamics Data on the fold increase in peripheral blood CD34+ cell count (cells/mcL) by apheresis day were evaluated in two placebo-controlled clinical studies in patients with NHL and MM (Study 1 and Study 2, respectively). The fold increase in CD34+ cell count (cells/mcL) over the 24-hour period starting from the day prior to the first apheresis and ending the next morning just before the first apheresis is summarized in Table 3 . During this 24-hour period, a single dose of plerixafor or placebo was administered 10 to 11 hours prior to apheresis.
Table 3: Fold Increase in Peripheral Blood CD34+ Cell Count Following Pretreatment with Filgrastim and Administration of Plerixafor Study Plerixafor and Filgrastim Placebo and Filgrastim Median Mean (SD) Median Mean (SD) Study 1 5.0 6.1 (5.4) 1.4 1.9 (1.5) Study 2 4.8 6.4 (6.8) 1.7 2.4 (7.3) In pharmacodynamic studies of plerixafor in healthy volunteers, peak mobilization of CD34+ cells was observed between 6 and 9 hours after administration. In pharmacodynamic studies of plerixafor in conjunction with filgrastim in healthy volunteers, a sustained elevation in the peripheral blood CD34+ count was observed from 4 to 18 hours after plerixafor administration with a peak CD34+ count between 10 and 14 hours.
QT/QTc Prolongation There is no indication of a QT/QTc prolonging effect of plerixafor in single doses up to 0.40 mg/kg. In a randomized, double-blind, crossover study, 48 healthy subjects were administered a single subcutaneous dose of plerixafor (0.24 mg/kg and 0.40 mg/kg) and placebo. Peak concentrations for 0.40 mg/kg plerixafor were approximately 1.8-fold higher than the peak concentrations following the 0.24 mg/kg single subcutaneous dose.
12.3Pharmacokinetics The single-dose pharmacokinetics of plerixafor 0.24 mg/kg were evaluated in patients with NHL and MM following pretreatment with filgrastim (10 mcg/kg once daily for 4 consecutive days). Plerixafor exhibits linear kinetics between the 0.04 mg/kg to 0.24 mg/kg dose range. The pharmacokinetics of plerixafor was similar across clinical studies in healthy subjects who received plerixafor alone and NHL and MM patients who received plerixafor in combination with filgrastim.
A population pharmacokinetic analysis incorporated plerixafor data from 63 subjects (NHL patients, MM patients, subjects with varying degrees of renal impairment, and healthy subjects) who received a single SC dose (0.04 mg/kg to 0.24 mg/kg) of plerixafor. A two-compartment disposition model with first order absorption and elimination was found to adequately describe the plerixafor concentration-time profile. Significant relationships between clearance and creatinine clearance (CL CR ), as well as between central volume of distribution and body weight were observed.
The distribution half-life (t 1/2α ) was estimated to be 0.3 hours and the terminal population half-life (t 1/2β ) was 5.3 hours in patients with normal renal function. The population pharmacokinetic analysis showed that the mg/kg-based dosage results in an increased plerixafor exposure (AUC 0-24h ) with increasing body weight. In order to compare the pharmacokinetics and pharmacodynamics of plerixa… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Plerixafor is an inhibitor of the CXCR4 chemokine receptor and blocks binding of its cognate ligand, stromal cell-derived factor-1α (SDF-1α). SDF-1α and CXCR4 are recognized to play a role in the trafficking and homing of human hematopoietic stem cells (HSCs) to the marrow compartment. Once in the marrow, stem cell CXCR4 can act to help anchor these cells to the marrow matrix, either directly via SDF-1α or through the induction of other adhesion molecules.
Treatment with plerixafor resulted in leukocytosis and elevations in circulating hematopoietic progenitor cells in mice, dogs and humans. CD34+ cells mobilized by plerixafor were capable of engraftment with long-term repopulating capacity up to one year in canine transplantation models.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Plerixafor Injection is a sterile, preservative-free, clear, colorless to pale yellow solution supplied in a 2 mL clear glass vial as follows: NDC Plerixafor Injection (20 mg per mL) Package Factor 71288- 155 -01 24 mg per 1.2 mL Single-Dose Vial 1 vial per carton Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature.] Discard unused portion. Sterile, Nonpyrogenic, Preservative-free. The container closure is not made with natural rubber latex.
📋 Description ▾
11 DESCRIPTION Plerixafor Injection is a sterile, preservative-free, clear, colorless to pale yellow, isotonic solution for subcutaneous injection. Each mL of the sterile solution contains 20 mg of plerixafor. Each single-dose vial is filled to deliver 1.2 mL of the sterile solution that contains 24 mg of plerixafor and 5.9 mg of sodium chloride in Water for Injection adjusted to a pH of 6.0 to 7.5 with hydrochloric acid and with sodium hydroxide, if required.
Plerixafor is a hematopoietic stem cell mobilizer with a chemical name 1,4-Bis((1,4,8,11-tetraazacyclotetradecan-1-yl)methyl)benzene. It has the molecular formula C 28 H 54 N 8 . The molecular weight of plerixafor is 502.78 g/mol.
The structural formula is provided in Figure 1. Figure 1: Structural Formula Plerixafor is a white to off-white crystalline solid. It is hygroscopic.
Plerixafor has a typical melting point of 131.5°C. The partition coefficient of plerixafor between 1-octanol and pH 7 aqueous buffer is <0.1. Structural formula
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The single-dose pharmacokinetics of plerixafor 0.24 mg/kg were evaluated in patients with NHL and MM following pretreatment with filgrastim (10 mcg/kg once daily for 4 consecutive days). Plerixafor exhibits linear kinetics between the 0.04 mg/kg to 0.24 mg/kg dose range. The pharmacokinetics of plerixafor was similar across clinical studies in healthy subjects who received plerixafor alone and NHL and MM patients who received plerixafor in combination with filgrastim.
A population pharmacokinetic analysis incorporated plerixafor data from 63 subjects (NHL patients, MM patients, subjects with varying degrees of renal impairment, and healthy subjects) who received a single SC dose (0.04 mg/kg to 0.24 mg/kg) of plerixafor. A two-compartment disposition model with first order absorption and elimination was found to adequately describe the plerixafor concentration-time profile. Significant relationships between clearance and creatinine clearance (CL CR ), as well as between central volume of distribution and body weight were observed.
The distribution half-life (t 1/2α ) was estimated to be 0.3 hours and the terminal population half-life (t 1/2β ) was 5.3 hours in patients with normal renal function. The population pharmacokinetic analysis showed that the mg/kg-based dosage results in an increased plerixafor exposure (AUC 0-24h ) with increasing body weight. In order to compare the pharmacokinetics and pharmacodynamics of plerixafor following 0.24 mg/kg-based and fixed (20 mg) doses, a follow-up trial was conducted in patients with NHL (N=61) who were treated with 0.24 mg/kg or 20 mg of plerixafor.
The trial was conducted in patients weighing 70 kg or less. The fixed 20 mg dose showed 1.43-fold higher exposure (AUC 0-10h ) than the 0.24 mg/kg dose ( Table 4 ). The fixed 20 mg dose also showed numerically higher response rate (5.2% [60.0% vs 54.8%] based on the local lab data and 11.7% [63.3% vs 51.6%] based on the central lab data) in attaining the target of ≥5 × 10 6 CD34+ cells/kg than the mg/kg-based dose.
However, the median time to reach ≥5 × 10 6 CD34+ cells/kg was 3 days for both treatment groups, and the safety profile between the groups was similar. Based on these results, further analysis was conducted by FDA reviewers and a body weight of 83 kg was selected as an appropriate cut-off point to transition patients from fixed to weight based dosing. Table 4: Systemic Exposure (AUC 0-10h ) Comparisons of Fixed and Weight-Based Regimens Regimen Geometric Mean AUC Fixed 20 mg (n=30) 3991.2 0.24 mg/kg (n=31) 2792.7 Ratio (90% CI) 1.43 (1.32,1.54) There is limited experience with the 0.24 mg/kg dose of plerixafor in patients weighing above 160 kg.
Therefore, the dose should not exceed that of a 160 kg patient (i.e., 40 mg/day if CL CR is greater than 50 mL/min and 27 mg/day if CL CR is less than or equal to 50 mL/min) [see D osage and Administration (2.1 , 2.3 )] . Absorption Peak plasma concentrations occurred at approximately 30 to 60 minutes after a SC dose. Distribution Plerixafor is bound to human plasma proteins up to 58%.
The apparent volume of distribution of plerixafor in humans is
0.3L/kg demonstrating that plerixafor is largely confined to, but not limited to, the extravascular fluid space. Metabolism The metabolism of plerixafor was evaluated with in vitro assays. Plerixafor is not metabolized as shown in assays using human liver microsomes or human primary hepatocytes and does not exhibit inhibitory activity in vitro towards the major drug metabolizing cytochrome P450 enzymes (1A2, 2A6, 2B6, 2C8, 2C9, 2C19, 2D6, 2E1 and 3A4/5).
In in vitro studies with human hepatocytes, plerixafor does not induce CYP1A2, CYP2B6, or CYP3A4 enzymes. These findings suggest that plerixafor has a low potential for involvement in cytochrome P450-dependent drug-drug interactions. Elimination The major route of elimination of plerixafor is urinary.
Following a 0.24 mg/kg dose in healthy volunteers with normal renal fu… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Data on the fold increase in peripheral blood CD34+ cell count (cells/mcL) by apheresis day were evaluated in two placebo-controlled clinical studies in patients with NHL and MM (Study 1 and Study 2, respectively). The fold increase in CD34+ cell count (cells/mcL) over the 24-hour period starting from the day prior to the first apheresis and ending the next morning just before the first apheresis is summarized in Table 3 . During this 24-hour period, a single dose of plerixafor or placebo was administered 10 to 11 hours prior to apheresis.
Table 3: Fold Increase in Peripheral Blood CD34+ Cell Count Following Pretreatment with Filgrastim and Administration of Plerixafor Study Plerixafor and Filgrastim Placebo and Filgrastim Median Mean (SD) Median Mean (SD) Study 1 5.0 6.1 (5.4) 1.4 1.9 (1.5) Study 2 4.8 6.4 (6.8) 1.7 2.4 (7.3) In pharmacodynamic studies of plerixafor in healthy volunteers, peak mobilization of CD34+ cells was observed between 6 and 9 hours after administration. In pharmacodynamic studies of plerixafor in conjunction with filgrastim in healthy volunteers, a sustained elevation in the peripheral blood CD34+ count was observed from 4 to 18 hours after plerixafor administration with a peak CD34+ count between 10 and 14 hours.
QT/QTc Prolongation There is no indication of a QT/QTc prolonging effect of plerixafor in single doses up to 0.40 mg/kg. In a randomized, double-blind, crossover study, 48 healthy subjects were administered a single subcutaneous dose of plerixafor (0.24 mg/kg and 0.40 mg/kg) and placebo. Peak concentrations for 0.40 mg/kg plerixafor were approximately 1.8-fold higher than the peak concentrations following the 0.24 mg/kg single subcutaneous dose.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy and safety of plerixafor in conjunction with filgrastim in non-Hodgkin’s lymphoma (NHL) Study AMD 3100-3101 (referred to as study 1) ( NCT00103610 ) and multiple myeloma (MM) Study AMD 3100-3102 (referred to as study 2) ( NCT00103662 ) were evaluated in two placebo-controlled studies (Studies 1 and 2). Patients were randomized to receive either plerixafor 0.24 mg/kg or placebo on each evening prior to apheresis. Patients received daily morning doses of filgrastim 10 mcg/kg for 4 days prior to the first dose of plerixafor or placebo and on each morning prior to apheresis.
Two hundred and ninety-eight (298) NHL patients were included in the primary efficacy analyses for Study 1. The mean age was 55 years (range 29-75) and 58 years (range 22-75) in the plerixafor and placebo groups, respectively, and 93% of subjects were Caucasian. In study 2, 302 patients with MM were included in the primary efficacy analyses.
The mean age (58 years) and age range (28-75) were similar in the plerixafor and placebo groups, and 81% of subjects were Caucasian. In Study 1, 59% of NHL patients who were mobilized with plerixafor and filgrastim collected ≥5 × 10 6 CD34+ cells/kg from the peripheral blood in four or fewer apheresis sessions, compared with 20% of patients who were mobilized with placebo and filgrastim (p <0.001). Other CD34+ cell mobilization outcomes showed similar findings ( Table 5 ).
Table 5: Study 1 Efficacy Results - CD34+ Cell Mobilization in NHL Patients a p-value calculated using Pearson’s Chi-Squared test Efficacy Endpoint Plerixafor and Filgrastim (n=150) Placebo and Filgrastim (n=148) p-value a Patients achieving ≥5 × 10 6 cells/kg in ≤4 apheresis days 89 (59%) 29 (20%) <0.001 Patients achieving ≥2 × 10 6 cells/kg in ≤4 apheresis days 130 (87%) 70 (47%) <0.001 The median number of days to reach ≥5 × 10 6 CD34+ cells/kg was 3 days for the plerixafor group and not evaluable for the placebo group.
Table 6 presents the proportion of patients who achieved ≥5 × 10 6 CD34+ cells/kg by apheresis day. Table 6: Study 1 Efficacy Results - Proportion of Patients Who Achieved ≥5 × 10 6 CD34+ cells/kg by Apheresis Day in NHL Patients a Percents determined by Kaplan Meier method b n includes all patients who received at least one day of apheresis Days Proportion a in Plerixafor and Filgrastim (n=147 b ) Proportion a in Placebo and Filgrastim (n=142 b ) 1 27.9% 4.2% 2 49.1% 14.2% 3 57.7% 21.6% 4 65.6% 24.2% In Study 2, 72% of MM patients who were mobilized with plerixafor and filgrastim collected ≥6 × 10 6 CD34+ cells/kg from the peripheral blood in two or fewer apheresis sessions, compared with 34% of patients who were mobilized with placebo and filgrastim (p <0.001).
Other CD34+ cell mobilization outcomes showed similar findings ( Table 7 ). Table 7: Study 2 Efficacy Results - CD34+ Cell Mobilization in Multiple Myeloma Patients a p-value calculated using Pearson’s Chi-Squared test Efficacy Endpoint Plerixafor and Filgrastim (n=148) Placebo and Filgrastim (n=154) p-value a Patients achieving ≥6 × 10 6 cells/kg in ≤2 apheresis days 106 (72%) 53 (34%) <0.001 Patients achieving ≥6 × 10 6 cells/kg in ≤4 apheresis days 112 (76%) 79 (51%) <0.001 Patients achieving ≥2 × 10 6 cells/kg in ≤4 apheresis days 141 (95%) 136 (88%) 0.028 The median number of days to reach ≥6 × 10 6 CD34+ cells/kg was 1 day for the plerixafor group and 4 days for the placebo group.
Table 8 presents the proportion of patients who achieved ≥6 × 10 6 CD34+ cells/kg by apheresis day. Table 8: Study 2 - Proportion of Patients Who Achieved ≥6 × 10 6 CD34+ cells/kg by Apheresis Day in MM Patients a Percents determined by Kaplan Meier method b n includes all patients who received at least one day of apheresis Days Proportion a in Plerixafor and Filgrastim (n=144 b ) Proportion a in Placebo and Filgrastim (n=150 b ) 1 54.2% 17.3% 2 77.9% 35.3% 3 86.8% 48.9% 4 86.8% 55.9% Multiple factors can influence time to engraftment and graft durability follow… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with plerixafor have not been conducted. Plerixafor was not genotoxic in an in vitro bacterial mutation assay (Ames test in Salmonella ), an in vitro chromosomal aberration test using V79 Chinese hamster cells, or an in vivo bone marrow micronucleus test in rats after subcutaneous doses up to 25 mg/kg (150 mg/m 2 ). The effect of plerixafor on human fertility is unknown.
The effect of plerixafor on male fertility was not studied in designated reproductive toxicology studies. The staging of spermatogenesis measured in a 28-day repeated dose toxicity study in rats revealed no abnormalities considered to be related to plerixafor. No histopathological evidence of toxicity to male or female reproductive organs was observed in 28-day repeated dose toxicity studies.
No adverse effects on estrus or reproductive indices were observed in an investigative fertility study in female rats administered plerixafor at doses up to 90 mg/m 2 (15mg/kg/day) or approximately 10 times the recommended human dose of 0.24 mg/kg when compared on a mg/m 2 basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with plerixafor have not been conducted. Plerixafor was not genotoxic in an in vitro bacterial mutation assay (Ames test in Salmonella ), an in vitro chromosomal aberration test using V79 Chinese hamster cells, or an in vivo bone marrow micronucleus test in rats after subcutaneous doses up to 25 mg/kg (150 mg/m 2 ). The effect of plerixafor on human fertility is unknown.
The effect of plerixafor on male fertility was not studied in designated reproductive toxicology studies. The staging of spermatogenesis measured in a 28-day repeated dose toxicity study in rats revealed no abnormalities considered to be related to plerixafor. No histopathological evidence of toxicity to male or female reproductive organs was observed in 28-day repeated dose toxicity studies.
No adverse effects on estrus or reproductive indices were observed in an investigative fertility study in female rats administered plerixafor at doses up to 90 mg/m 2 (15mg/kg/day) or approximately 10 times the recommended human dose of 0.24 mg/kg when compared on a mg/m 2 basis.
📄 Package Label / Principal Display Panel ▾
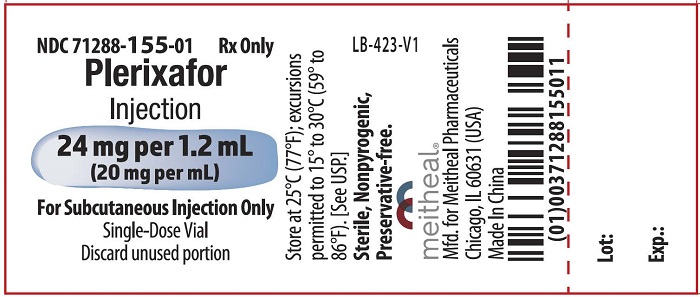
PRINCIPAL DISPLAY PANEL – Plerixafor Injection 24 mg per 1.2 mL Vial Label NDC 71288- 155 -01 Rx Only Plerixafor Injection 24 mg per 1.2 mL (20 mg per mL) For Subcutaneous Injection Only Single-Dose Vial Discard unused portion PRINCIPAL DISPLAY PANEL – Plerixafor Injection 24 mg per 1.2 mL Vial Label
PRINCIPAL DISPLAY PANEL – Plerixafor Injection 24 mg per 1.2 mL Carton NDC 71288- 155 -01 Rx Only Plerixafor Injection 24 mg per 1.2 mL (20 mg per mL) For Subcutaneous Injection Only 1 Single-Dose Vial Discard unused portion See package insert for dosage and administration. PRINCIPAL DISPLAY PANEL – Plerixafor Injection 24 mg per 1.2 mL Carton
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |