
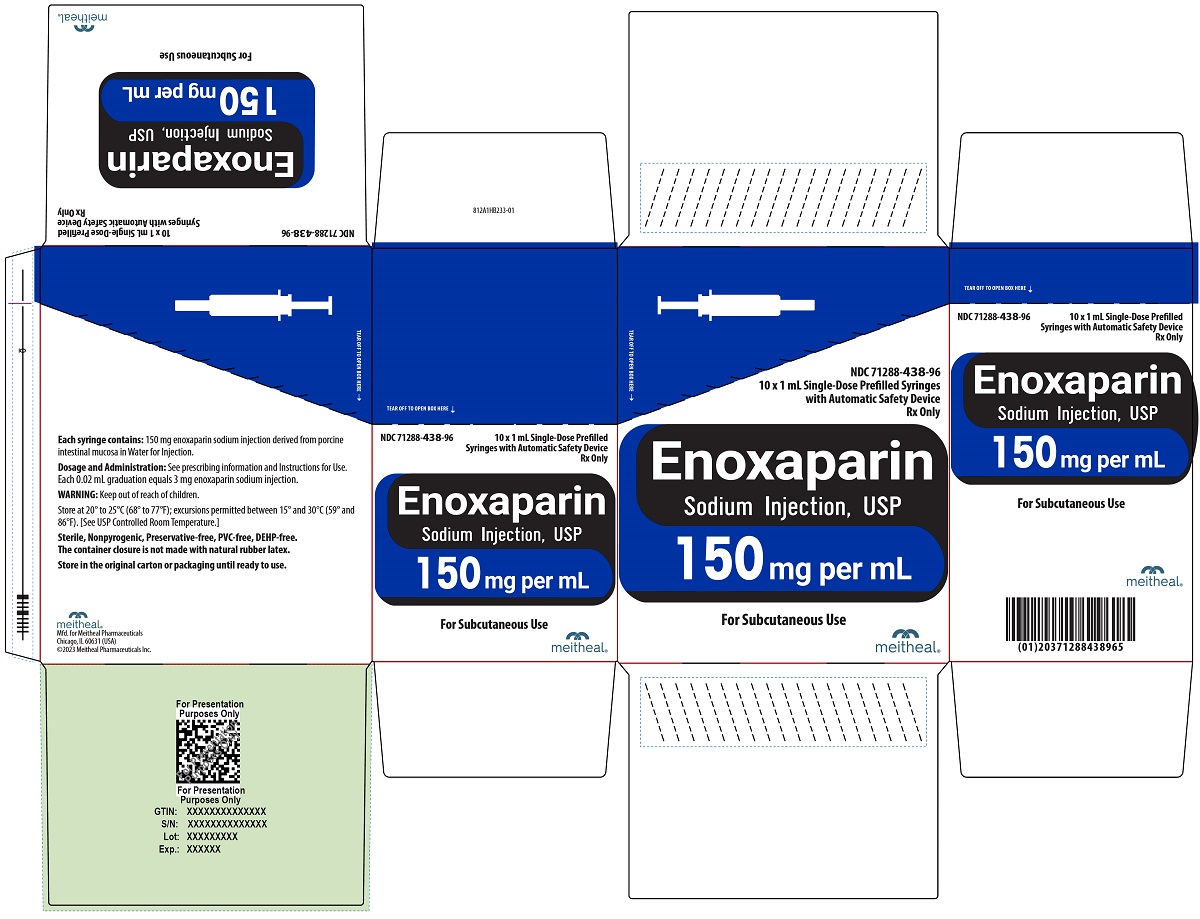
Enoxaparin Sodium 150 mg/mL Injection, 10 syringes — NDC 71288-438-96 (Billing 71288-0438-96)
This is a package of 10 syringes of Enoxaparin Sodium 150 mg/mL Injection from Meitheal Pharmaceuticals Inc., marketed since Dec 2019 and currently FDA-listed; retail pharmacies pay about $8.90 per mL (NADAC).
Other active recalls for Enoxaparin Sodium (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 044668
- GCN: 42071
- GPI-14 (Medi-Span): 8310102010E565
- HICL (First Databank): 007878
- AHFS class code: 20:12.04.16
- RxCUI (RxNorm): 854228
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Low Molecular Weight Heparin class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Enoxaparin is used to prevent and treat deep vein thrombosis (DVT; blood clots that form in the veins, typically in the legs). It is also used to prevent complications from angina (chest pain) and heart attacks. Enoxaparin is in a class of medications called low molecular weight heparins. It works by stopping the formation of substances that cause clots.
Read the full MedlinePlus article ↗- It is a blood thinner that helps prevent and treat deep vein thrombosis, a clot in a deep vein. It is also used in unstable angina and certain heart attacks. Your prescriber choose...
- It is an injection, usually under the skin, and some uses involve an injection into a vein. How often depends on why you need it. Follow your prescriber’s directions and the produc...
- Bruising, injection site pain, nausea and diarrhea are common. Some people have bleeding or a lower blood count. Call your doctor if bleeding seems unusual or won’t stop.
- Yes. If you have an epidural or spinal procedure, bleeding near the spine can rarely cause permanent paralysis. Report new numbness, leg weakness or bladder or bowel changes right...
Patient education
Supplement & herbal interactions
Enoxaparin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $8.904 | $89.04 / 10 ml |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $10.33 | $103.33 / 10 ml |
| Medicare Part B allowsASP · J1650 | $0.536 / J1650 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 71288-0438-96 You're viewing this | 10 SYRINGE in 1 CARTON / 1 mL in 1 SYRINGE | $8.90 / mL | $89.04 | 2019-12-01 | — | Active |
| 71288-0438-94 71288-438-94 Main listing | 10 SYRINGE in 1 CARTON / 1 mL in 1 SYRINGE | $8.90 / mL | $89.04 | 2019-12-01 | — | Active |
This pack has the lowest per-mL cost of the 2 priced pack sizes ($8.90 NADAC).
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 71288-0438-94?
What NDC number is used to bill for this package of Enoxaparin Sodium 150 mg/mL Injection?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Enoxaparin Sodium 150 mg/mL 00548-5607-00 | Amphastar | 10 syringes | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mL 00781-3299-69 | Sandoz | 10 syringes | $8.904 | AP | Availability likely | — |
| Enoxaparin sodium 150 mg/mL 00955-1015-10 | Sanofi-Aventis | 10 cellos | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mL 16714-0066-10 | NorthStar | 10 syringes | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mL 63323-0589-94 | Fresenius | 1 syringe | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mL 68001-0639-42 | BluePoint | 10 syringes | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mL 70710-1763-06 | Zydus | 10 syringes | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mLthis 71288-0438-96 | Meitheal | 10 syringes | $8.904 | AP | Availability likely | — |
| enoxaparin sodium 150 mg/mL 71839-0116-10 | BE | 10 syringes | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mL 81952-0135-06 | Hepalink | 10 syringes | $8.904 | AP | Availability likely | — |
| Enoxaparin Sodium 150 mg/mL 25021-0411-70 | Sagent | 10 syringes | $10.417 | AP | Availability likely | +17% |
| Enoxaparin Sodium 150 mg/mL 00781-3298-68 | Sandoz | 10 syringes | $10.417 | AP | Availability likely | +17% |
| Enoxaparin Sodium 150 mg/mL 71288-0437-94 | Meitheal | 10 syringes | $10.417 | AP | Availability likely | +17% |
| Enoxaparin Sodium 150 mg/mL 68001-0638-42 | BluePoint | 10 syringes | $10.417 | AP | Availability likely | +17% |
| Enoxaparin Sodium 150 mg/mL 16714-0056-10 | NorthStar | 10 syringes | $10.417 | AP | Availability likely | +17% |
| Enoxaparin Sodium 150 mg/mL 00548-5606-00 | Amphastar | 10 syringes | $10.417 | AP | Availability likely | +17% |
| Enoxaparin Sodium 150 mg/mL 68001-0463-42 | BluePoint | 10 syringes | $10.626 | AP | Availability likely | +19% |
| Enoxaparin Sodium 150 mg/mL 68001-0462-42 | BluePoint | 10 syringes | $11.810 | AP | Availability likely | +33% |
| Enoxaparin Sodium 150 mg/mL 72603-0225-10 | NorthStar | 10 syringes | $14.739 | AP | FDA listed | +66% |
| Lovenox 150 mg/mL 00075-2915-01 | Sanofi-Aventis | 10 cellos | — | AP | FDA listed | — |
| Lovenox 150 mg/mL 00075-8025-10 | Sanofi-Aventis | 10 cellos | — | AP | FDA listed | — |
| Enoxaparin Sodium 150 mg/mL 11797-0763-06 | Italfarmaco | 10 syringes | — | AP | FDA listed | — |
| enoxaparin sodium 150 mg/mL 28955-0107-10 | Hebei | 10 syringes | — | AP | FDA listed | — |
| Enoxaparin Sodium 150 mg/mL 63323-0537-94 | Fresenius | 10 cellos | — | AP | FDA listed | — |
| Enoxaparin Sodium 150 mg/mL 68083-0640-10 | Gland | 10 syringes | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SPINAL/EPIDURAL HEMATOMAS Epidural or spinal hematomas may occur in patients who are anticoagulated with low molecular weight heparins (LMWH) or heparinoids and are receiving neuraxial anesthesia or undergoing spinal puncture. These hematomas may result in long-term or permanent paralysis. Consider these risks when scheduling patients for spinal procedures.
Factors that can increase the risk of developing epidural or spinal hematomas in these patients include: Use of indwelling epidural catheters Concomitant use of other drugs that affect hemostasis, such as non-steroidal anti-inflammatory drugs (NSAIDs), platelet inhibitors, and other anticoagulants A history of traumatic or repeated epidural or spinal punctures A history of spinal deformity or spinal surgery Optimal timing between the administration of enoxaparin sodium injection and neuraxial procedures is not known Monitor patients frequently for signs and symptoms of neurological impairment.
If neurological compromise is noted, urgent treatment is necessary. Consider the benefits and risks before neuraxial intervention in patients anticoagulated or to be anticoagulated for thromboprophylaxis [see Warnings and Precautions ( 5.1 ) and Drug Interactions ( 7 )] . WARNING: SPINAL/EPIDURAL HEMATOMAS See full prescribing information for complete boxed warning.
Epidural or spinal hematomas may occur in patients who are anticoagulated with low molecular weight heparins (LMWH) or heparinoids and are receiving neuraxial anesthesia or undergoing spinal puncture. These hematomas may result in long-term or permanent paralysis. Consider these risks when scheduling patients for spinal procedures.
Factors that can increase the risk of developing epidural or spinal hematomas in these patients include: Use of indwelling epidural catheters Concomitant use of other drugs that affect hemostasis, such as non-steroidal anti-inflammatory drugs (NSAIDs), platelet inhibitors, and other anticoagulants A history of traumatic or repeated epidural or spinal punctures A history of spinal deformity or spinal surgery Optimal timing between the administration of enoxaparin sodium injection and neuraxial procedures is not known Monitor patients frequently for signs and symptoms of neurological impairment.
If neurological compromise is noted, urgent treatment is necessary. ( 5.1 , 7 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Enoxaparin Sodium Injection is a low molecular weight heparin (LMWH) indicated for: Prophylaxis of deep vein thrombosis (DVT) in abdominal surgery, hip replacement surgery, knee replacement surgery, or medical patients with severely restricted mobility during acute illness ( 1.1 ) Inpatient treatment of acute DVT with or without pulmonary embolism ( 1.2 ) Outpatient treatment of acute DVT without pulmonary embolism ( 1.2 ) Prophylaxis of ischemic complications of unstable angina and non-Q-wave myocardial infarction (MI) ( 1.3 ) Treatment of acute ST-segment elevation myocardial infarction (STEMI) managed medically or with subsequent percutaneous coronary intervention (PCI) ( 1.4 )
1.1Prophylaxis of Deep Vein Thrombosis Enoxaparin Sodium Injection is indicated for the prophylaxis of deep vein thrombosis (DVT), which may lead to pulmonary embolism (PE): in patients undergoing abdominal surgery who are at risk for thromboembolic complications [see Clinical Studies ( 14.1 )] in patients undergoing hip replacement surgery, during and following hospitalization in patients undergoing knee replacement surgery in medical patients who are at risk for thromboembolic complications due to severely restricted mobility during acute illness
1.2Treatment of Acute Deep Vein Thrombosis Enoxaparin Sodium Injection is indicated for: the inpatient treatment of acute deep vein thrombosis with or without pulmonary embolism , when administered in conjunction with warfarin sodium the outpatient treatment of acute deep vein thrombosis without pulmonary embolism , when administered in conjunction with warfarin sodium
1.3Prophylaxis of Ischemic Complications of Unstable Angina and Non-Q-Wave Myocardial Infarction Enoxaparin Sodium Injection is indicated for the prophylaxis of ischemic complications of unstable angina and non-Q-wave myocardial infarction, when concurrently administered with aspirin.
1.4Treatment of Acute ST-Segment Elevation Myocardial Infarction Enoxaparin Sodium Injection, when administered concurrently with aspirin, has been shown to reduce the rate of the combined endpoint of recurrent myocardial infarction or death in patients with acute ST-segment elevation myocardial infarction (STEMI) receiving thrombolysis and being managed medically or with percutaneous coronary intervention (PCI).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION See full prescribing information for dosing and administration information. ( 2 )
2.1Pretreatment Evaluation Evaluate all patients for a bleeding disorder before starting enoxaparin sodium injection treatment, unless treatment is urgently needed.
2.2Adult Dosage Abdominal Surgery The recommended dose of enoxaparin sodium injection is 40 mg by subcutaneous injection once a day (with the initial dose given 2 hours prior to surgery) in patients undergoing abdominal surgery who are at risk for thromboembolic complications. The usual duration of administration is 7 to 10 days [see Clinical Studies ( 14.1 )] . Hip or Knee Replacement Surgery The recommended dose of enoxaparin sodium injection is 30 mg every 12 hours administered by subcutaneous injection in patients undergoing hip or knee replacement surgery.
Administer the initial dose 12 to 24 hours after surgery, provided that hemostasis has been established. The usual duration of administration is 7 to 10 days [see Clinical Studies ( 14.2 )] . A dose of enoxaparin sodium injection of 40 mg once a day subcutaneously may be considered for hip replacement surgery for up to 3 weeks.
Administer the initial dose 12 (±3) hours prior to surgery. Medical Patients during Acute Illness The recommended dose of enoxaparin sodium injection is 40 mg once a day administered by subcutaneous injection for medical patients at risk for thromboembolic complications due to severely restricted mobility during acute illness. The usual duration of administration is 6 to 11 days [see Clinical Studies ( 14.3 )] .
Treatment of Deep Vein Thrombosis with or without Pulmonary Embolism The recommended dose of enoxaparin sodium injection is 1 mg/kg every 12 hours administered subcutaneously in patients with acute deep vein thrombosis without pulmonary embolism, who can be treated at home in an outpatient setting. The recommended dose of enoxaparin sodium injection is 1 mg/kg every 12 hours administered subcutaneously or 1.5 mg/kg once a day administered subcutaneously at the same time every day for inpatient (hospital) treatment of patients with acute deep vein thrombosis with pulmonary embolism or patients with acute deep vein thrombosis without pulmonary embolism (who are not candidates for outpatient treatment).
In both outpatient and inpatient (hospital) treatments, initiate warfarin sodium therapy when appropriate (usually within 72 hours of enoxaparin sodium injection). Continue enoxaparin sodium injection for a minimum of 5 days and until a therapeutic oral anticoagulant effect has been achieved (International Normalization Ratio 2 to 3). The average duration of administration is 7 days [see Clinical Studies ( 14.4 )] .
Unstable Angina and Non-Q-Wave Myocardial Infarction The recommended dose of enoxaparin sodium injection is 1 mg/kg administered subcutaneously every 12 hours in conjunction with oral aspirin therapy (100 to 325 mg once daily) in patients with unstable angina or non-Q-wave myocardial infarction. Treat with enoxaparin sodium injection for a minimum of 2 days and continue until clinical stabilization. The usual duration of treatment is 2 to 8 days [see Warnings and Precautions ( 5.2 ) and Clinical Studies ( 14.5 )] .
Treatment of Acute ST-Segment Elevation Myocardial Infarction The recommended dose of enoxaparin sodium injection is a single intravenous bolus of 30 mg plus a 1 mg/kg subcutaneous dose followed by 1 mg/kg administered subcutaneously every 12 hours (maximum 100 mg for the first two doses only, followed by 1 mg/kg dosing for the remaining doses) in patients with acute ST-segment elevation myocardial infarction. Reduce the dosage in patients ≥75 years of age [see Dosage and Administration ( 2.4 )] . Unless contraindicated, administer aspirin to all patients as soon as they are identified as having STEMI and continue dosing with 75 to 325 mg once daily.
When administered in conjunction with a thrombolytic (fibrin specific or non–fibrin specific), admi… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Enoxaparin Sodium Injection, USP is a colorless or light yellow transparent liquid available in two concentrations: 100 mg per mL Concentration – Single-Dose Prefilled Syringes – Single-Dose Graduated Prefilled Syringes 30 mg per 0.3 mL, 40 mg per 0.4 mL 60 mg per 0.6 mL, 80 mg per 0.8 mL, 100 mg per mL 150 mg per mL Concentration – Single-Dose Graduated Prefilled Syringes 120 mg per 0.8 mL, 150 mg per mL 100 mg per mL concentration ( 3 ): Single-dose prefilled syringes: 30 mg per 0.3 mL, 40 mg per 0.4 mL Single-dose graduated prefilled syringes: 60 mg per 0.6 mL, 80 mg per 0.8 mL, 100 mg per mL 150 mg per mL concentration ( 3 ): Single-dose graduated prefilled syringes: 120 mg per 0.8 mL, 150 mg per mL
⛔ Contraindications ▾
4 CONTRAINDICATIONS Enoxaparin sodium is contraindicated in patients with: Active major bleeding History of immune-mediated heparin-induced thrombocytopenia (HIT) within the past 100 days or in the presence of circulating antibodies [see Warnings and Precautions ( 5.4 )] Known hypersensitivity to enoxaparin sodium (e.g., pruritus, urticaria, anaphylactic/anaphylactoid reactions) [see Adverse Reactions ( 6.2 )] Known hypersensitivity to heparin or pork products Active major bleeding ( 4 ) History of heparin-induced thrombocytopenia (HIT) within the past 100 days or in the presence of circulating antibodies ( 4 ) Hypersensitivity to enoxaparin sodium ( 4 ) Hypersensitivity to heparin or pork products ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Increased Risk of Hemorrhage: Monitor for signs of bleeding. ( 5.1 , 5.2 , 5.3 ) Risk of Heparin-Induced Thrombocytopenia with or without Thrombosis. ( 5.4 ) Thrombocytopenia: Monitor platelet count closely.
( 5.5 ) Interchangeability with other heparins: Do not exchange with heparin or other LMWHs. ( 5.6 ) Increased Risk of Thrombosis in Pregnant Women with Mechanical Prosthetic Heart Valves: Women and their fetuses may be at increased risk. Monitor more frequently and adjust dosage as needed.
( 5.7 )
5.1Increased Risk of Hemorrhage Cases of epidural or spinal hemorrhage and subsequent hematomas have been reported with the use of enoxaparin sodium injection and epidural or spinal anesthesia/analgesia or spinal puncture procedures, resulting in long-term or permanent paralysis. The risk of these events is higher with the use of postoperative indwelling epidural catheters, with the concomitant use of additional drugs affecting hemostasis such as NSAIDs, with traumatic or repeated epidural or spinal puncture, or in patients with a history of spinal surgery or spinal deformity [see Boxed Warning , Adverse Reactions ( 6.2 ) and Drug Interactions ( 7 )] .
To reduce the potential risk of bleeding associated with the concurrent use of enoxaparin sodium injection and epidural or spinal anesthesia/analgesia or spinal puncture, consider the pharmacokinetic profile of enoxaparin sodium injection [see Clinical Pharmacology ( 12.3 )] . Placement or removal of an epidural catheter or lumbar puncture is best performed when the anticoagulant effect of enoxaparin sodium injection is low; however, the exact timing to reach a sufficiently low anticoagulant effect in each patient is not known.
Placement or removal of a catheter should be delayed for at least 12 hours after administration of lower doses (30 mg once or twice daily or 40 mg once daily) of enoxaparin sodium injection and at least 24 hours after the administration of higher doses (0.75 mg/kg twice daily, 1 mg/kg twice daily, or 1.5 mg/kg once daily) of enoxaparin sodium injection. Anti-Xa levels are still detectable at these time points, and these delays are not a guarantee that neuraxial hematoma will be avoided. Patients receiving the 0.75 mg/kg twice-daily dose or the 1 mg/kg twice-daily dose should not receive the second enoxaparin sodium injection dose in the twice-daily regimen to allow a longer delay before catheter placement or removal.
Likewise, although a specific recommendation for timing of a subsequent enoxaparin sodium injection dose after catheter removal cannot be made, consider delaying this next dose for at least four hours, based on a benefit-risk assessment considering both the risk for thrombosis and the risk for bleeding in the context of the procedure and patient risk factors. For patients with creatinine clearance <30 mL/minute, additional considerations are necessary because elimination of enoxaparin sodium injection is more prolonged; consider doubling the timing of removal of a catheter, at least 24 hours for the lower prescribed dose of enoxaparin sodium injection (30 mg once daily) and at least 48 hours for the higher dose (1 mg/kg/day) [see Clinical Pharmacology ( 12.3 )] .
Should the physician decide to administer anticoagulation in the context of epidural or spinal anesthesia/analgesia or lumbar puncture, frequent monitoring must be exercised to detect any signs and symptoms of neurological impairment such as midline back pain, sensory and motor deficits (numbness or weakness in lower limbs), and bowel and/or bladder dysfunction. Instruct patients to report immediately if they experience any of the above signs or symptoms. If signs or symptoms of spinal hematoma are suspected, initiate urgent diagnosis and treatment including consideration for spinal cord decompression even though such treatment may not prevent or reverse neurological sequelae.
Use enoxaparin sodium injection with extreme caution in conditions with increased… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are also discussed in other sections of the labeling: Spinal/epidural hematomas [see Boxed Warning and Warnings and Precautions ( 5.1 )] Increased Risk of Hemorrhage [see Warnings and Precautions ( 5.1 )] Thrombocytopenia [see Warnings and Precautions ( 5.5 )] Most common adverse reactions (>1%) were bleeding, anemia, thrombocytopenia, elevation of serum aminotransferase, diarrhea, nausea, ecchymosis, fever, edema, peripheral edema, dyspnea, confusion, and injection site pain.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Meitheal Pharmaceuticals Inc. at 1-844-824-8426 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. During clinical development for the approved indications, 15,918 patients were exposed to enoxaparin sodium. These included 1,228 for prophylaxis of deep vein thrombosis following abdominal surgery in patients at risk for thromboembolic complications, 1,368 for prophylaxis of deep vein thrombosis following hip or knee replacement surgery, 711 for prophylaxis of deep vein thrombosis in medical patients with severely restricted mobility during acute illness, 1,578 for prophylaxis of ischemic complications in unstable angina and non-Q-wave myocardial infarction, 10,176 for treatment of acute ST-elevation myocardial infarction, and 857 for treatment of deep vein thrombosis with or without pulmonary embolism.
Enoxaparin sodium doses in the clinical trials for prophylaxis of deep vein thrombosis following abdominal or hip or knee replacement surgery or in medical patients with severely restricted mobility during acute illness ranged from 40 mg subcutaneously once daily to 30 mg subcutaneously twice daily. In the clinical studies for prophylaxis of ischemic complications of unstable angina and non-Q-wave myocardial infarction doses were 1 mg/kg every 12 hours and in the clinical studies for treatment of acute ST-segment elevation myocardial infarction enoxaparin sodium doses were a 30 mg intravenous bolus followed by 1 mg/kg every 12 hours subcutaneously.
Hemorrhage The following rates of major bleeding events have been reported during clinical trials with enoxaparin sodium (see Tables 2 to 7 ). Table 2: Major Bleeding Episodes following Abdominal and Colorectal Surgery* Indications Dosing Regimen Enoxaparin Sodium 40 mg daily subcutaneously Heparin 5,000 U q8h subcutaneously Abdominal Surgery n=555 23 (4%) n=560 16 (3%) Colorectal Surgery n=673 28 (4%) n=674 21 (3%) * Bleeding complications were considered major: (1) if the hemorrhage caused a significant clinical event, or (2) if accompanied by a hemoglobin decrease ≥2 g/dL or transfusion of 2 or more units of blood products.
Retroperitoneal, intraocular, and intracranial hemorrhages were always considered major. Table 3: Major Bleeding Episodes following Hip or Knee Replacement Surgery* * Bleeding complications were considered major: (1) if the hemorrhage caused a significant clinical event, or (2) if accompanied by a hemoglobin decrease ≥2 g/dL or transfusion of 2 or more units of blood products. Retroperitoneal and intracranial hemorrhages were always considered major.
In the knee replacement surgery trials, intraocular hemorrhages were also considered major hemorrhages. † Enoxaparin sodium 30 mg every 12 hours subcutaneously initiated 12 to 24 hours after surgery and continued for up to 14 days after surgery ‡ Enoxaparin sodium 40 mg subcutaneously once a day initiated up to 12 hours prior to surgery and continued for up to 7 days after surgery § Enoxaparin sodium 40 mg subcutaneously once a day for up to 21 days after discharge Indications Dosing Regimen Enoxaparin Sodium 40 mg daily subcutaneous… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Whenever possible, agents which may enhance the risk of hemorrhage should be discontinued prior to initiation of enoxaparin sodium therapy. These agents include medications such as: anticoagulants, platelet inhibitors including acetylsalicylic acid, salicylates, NSAIDs (including ketorolac tromethamine), dipyridamole, or sulfinpyrazone. If coadministration is essential, conduct close clinical and laboratory monitoring [see Warnings and Precautions ( 5.1 )] .
Discontinue agents which may enhance hemorrhage risk prior to initiation of enoxaparin sodium or conduct close clinical and laboratory monitoring. ( 2.6 , 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Severe Renal Impairment: Adjust dose for patients with creatinine clearance <30 mL/min. ( 2.3 , 8.7 ) Geriatric Patients: Monitor for increased risk of bleeding. ( 8.5 ) Low-Weight Patients: Observe for signs of bleeding. ( 8.8 )
8.1Pregnancy Risk Summary Placental transfer of enoxaparin was observed in the animal studies. Human data from a retrospective cohort study, which included 693 live births, suggest that enoxaparin does not increase the risk of major developmental abnormalities (see Data ) . Based on animal data, enoxaparin sodium injection is not predicted to increase the risk of major developmental abnormalities (see Data ) .
Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Pregnancy alone confers an increased risk for thromboembolism that is even higher for women with thromboembolic disease and certain high risk pregnancy conditions. While not adequately studied, pregnant women with mechanical prosthetic heart valves may be at even higher risk for thrombosis [see Warnings and Precautions ( 5.7 ) and Use in Specific Populations ( 8.6 )] . Pregnant women with thromboembolic disease, including those with mechanical prosthetic heart valves and those with inherited or acquired thrombophilias, have an increased risk of other maternal complications and fetal loss regardless of the type of anticoagulant used.
All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Pregnant women receiving enoxaparin sodium injection should be carefully monitored for evidence of bleeding or excessive anticoagulation. Consideration for use of a shorter acting anticoagulant should be specifically addressed as delivery approaches [see Boxed Warning ] .
Hemorrhage can occur at any site and may lead to death of mother and/or fetus. Pregnant women should be apprised of the potential hazard to the fetus and the mother if enoxaparin sodium injection is administered during pregnancy. It is not known if monitoring of anti-Factor Xa activity and dose adjustment (by weight or anti-Factor Xa activity) of enoxaparin sodium injection affect the safety and the efficacy of the drug during pregnancy.
Data Human Data There are no adequate and well-controlled studies in pregnant women. A retrospective study reviewed the records of 604 women who used enoxaparin sodium injection during pregnancy. A total of 624 pregnancies resulted in 693 live births.
There were 72 hemorrhagic events (11 serious) in 63 women. There were 14 cases of neonatal hemorrhage. Major congenital anomalies in live births occurred at rates (2.5%) similar to background rates.
There have been postmarketing reports of fetal death when pregnant women received enoxaparin sodium injection. Causality for these cases has not been determined. Insufficient data, the underlying disease, and the possibility of inadequate anticoagulation complicate the evaluation of these cases.
A clinical study using enoxaparin sodium injection in pregnant women with mechanical prosthetic heart valves has been conducted [see Warnings and Precautions ( 5.7 )] . Animal Data Teratology studies have been conducted in pregnant rats and rabbits at subcutaneous doses of enoxaparin up to 15 times the recommended human dose (by comparison with 2 mg/kg as the maximum recommended daily dose). There was no evidence of teratogenic effects or fetotoxicity due to enoxaparin.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
8.2Lactation Risk Summary It is unknown whether enoxaparin sodium is excreted in human mil… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Placental transfer of enoxaparin was observed in the animal studies. Human data from a retrospective cohort study, which included 693 live births, suggest that enoxaparin does not increase the risk of major developmental abnormalities (see Data ) . Based on animal data, enoxaparin sodium injection is not predicted to increase the risk of major developmental abnormalities (see Data ) .
Adverse outcomes in pregnancy occur regardless of the health of the mother or the use of medications. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Pregnancy alone confers an increased risk for thromboembolism that is even higher for women with thromboembolic disease and certain high risk pregnancy conditions. While not adequately studied, pregnant women with mechanical prosthetic heart valves may be at even higher risk for thrombosis [see Warnings and Precautions ( 5.7 ) and Use in Specific Populations ( 8.6 )] . Pregnant women with thromboembolic disease, including those with mechanical prosthetic heart valves and those with inherited or acquired thrombophilias, have an increased risk of other maternal complications and fetal loss regardless of the type of anticoagulant used.
All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Pregnant women receiving enoxaparin sodium injection should be carefully monitored for evidence of bleeding or excessive anticoagulation. Consideration for use of a shorter acting anticoagulant should be specifically addressed as delivery approaches [see Boxed Warning ] .
Hemorrhage can occur at any site and may lead to death of mother and/or fetus. Pregnant women should be apprised of the potential hazard to the fetus and the mother if enoxaparin sodium injection is administered during pregnancy. It is not known if monitoring of anti-Factor Xa activity and dose adjustment (by weight or anti-Factor Xa activity) of enoxaparin sodium injection affect the safety and the efficacy of the drug during pregnancy.
Data Human Data There are no adequate and well-controlled studies in pregnant women. A retrospective study reviewed the records of 604 women who used enoxaparin sodium injection during pregnancy. A total of 624 pregnancies resulted in 693 live births.
There were 72 hemorrhagic events (11 serious) in 63 women. There were 14 cases of neonatal hemorrhage. Major congenital anomalies in live births occurred at rates (2.5%) similar to background rates.
There have been postmarketing reports of fetal death when pregnant women received enoxaparin sodium injection. Causality for these cases has not been determined. Insufficient data, the underlying disease, and the possibility of inadequate anticoagulation complicate the evaluation of these cases.
A clinical study using enoxaparin sodium injection in pregnant women with mechanical prosthetic heart valves has been conducted [see Warnings and Precautions ( 5.7 )] . Animal Data Teratology studies have been conducted in pregnant rats and rabbits at subcutaneous doses of enoxaparin up to 15 times the recommended human dose (by comparison with 2 mg/kg as the maximum recommended daily dose). There was no evidence of teratogenic effects or fetotoxicity due to enoxaparin.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of enoxaparin sodium in pediatric patients have not been established. Enoxaparin sodium is not approved for use in neonates or infants.
🧓 Geriatric Use ▾
8.5Geriatric Use Prevention of Deep Vein Thrombosis in Hip, Knee and Abdominal Surgery; Treatment of Deep Vein Thrombosis, Prevention of Ischemic Complications of Unstable Angina and Non-Q-Wave Myocardial Infarction Over 2800 patients, 65 years and older, have received enoxaparin sodium in clinical trials. The efficacy of enoxaparin sodium in the geriatric (≥65 years) was similar to that seen in younger patients (<65 years). The incidence of bleeding complications was similar between geriatric and younger patients when 30 mg every 12 hours or 40 mg once a day doses of enoxaparin sodium were employed.
The incidence of bleeding complications was higher in geriatric patients as compared to younger patients when enoxaparin sodium was administered at doses of 1.5 mg/kg once a day or 1 mg/kg every 12 hours. The risk of enoxaparin sodium-associated bleeding increased with age. Serious adverse events increased with age for patients receiving enoxaparin sodium.
Other clinical experience (including postmarketing surveillance and literature reports) has not revealed additional differences in the safety of enoxaparin sodium between geriatric and younger patients. Careful attention to dosing intervals and concomitant medications (especially antiplatelet medications) is advised. Enoxaparin sodium should be used with care in geriatric patients who may show delayed elimination of enoxaparin.
Monitoring of geriatric patients with low body weight (<45 kg) and those predisposed to decreased renal function should be considered [see Warnings and Precautions ( 2.6 ) and Clinical Pharmacology ( 12.3 )] . Treatment of Acute ST-Segment Elevation Myocardial Infarction In the clinical study for treatment of acute ST-segment elevation myocardial infarction, there was no evidence of difference in efficacy between patients ≥75 years of age (n=1241) and patients less than 75 years of age (n=9015). Patients ≥75 years of age did not receive a 30 mg intravenous bolus prior to the normal dosage regimen and had their subcutaneous dose adjusted to 0.75 mg/kg every 12 hours [see Dosage and Administration ( 2.4 )] .
The incidence of bleeding complications was higher in patients ≥65 years of age as compared to younger patients (<65 years).
🆘 Overdosage ▾
10 OVERDOSAGE Accidental overdosage following administration of enoxaparin sodium may lead to hemorrhagic complications. Injected enoxaparin sodium may be largely neutralized by the slow intravenous injection of protamine sulfate (1% solution). The dose of protamine sulfate should be equal to the dose of enoxaparin sodium injected: 1 mg protamine sulfate should be administered to neutralize 1 mg enoxaparin sodium, if enoxaparin sodium was administered in the previous 8 hours.
An infusion of 0.5 mg protamine per 1 mg of enoxaparin sodium may be administered if enoxaparin sodium was administered greater than 8 hours previous to the protamine administration, or if it has been determined that a second dose of protamine is required. The second infusion of 0.5 mg protamine sulfate per 1 mg of enoxaparin sodium may be administered if the aPTT measured 2 to 4 hours after the first infusion remains prolonged. If at least 12 hours have elapsed since the last enoxaparin sodium injection, protamine administration may not be required; however, even with higher doses of protamine, the aPTT may remain more prolonged than following administration of heparin.
In all cases, the anti-Factor Xa activity is never completely neutralized (maximum about 60%). Particular care should be taken to avoid overdosage with protamine sulfate. Administration of protamine sulfate can cause severe hypotensive and anaphylactoid reactions.
Because fatal reactions, often resembling anaphylaxis, have been reported with protamine sulfate, it should be given only when resuscitation techniques and treatment of anaphylactic shock are readily available. For additional information consult the labeling of protamine sulfate injection products.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Enoxaparin is a low molecular weight heparin which has antithrombotic properties.
12.2Pharmacodynamics In humans, enoxaparin given at a dose of 1.5 mg/kg subcutaneously is characterized by a higher ratio of anti-Factor Xa to anti-Factor IIa activity (mean ±SD, 14.0±3.1) (based on areas under anti-Factor activity versus time curves) compared to the ratios observed for heparin (mean ±SD, 1.22±0.13). Increases of up to 1.8 times the control values were seen in the thrombin time (TT) and the activated partial thromboplastin time (aPTT). Enoxaparin at a 1 mg/kg dose (100 mg/mL concentration), administered subcutaneously every 12 hours to patients in a large clinical trial resulted in aPTT values of 45 seconds or less in the majority of patients (n=1607).
A 30 mg intravenous bolus immediately followed by a 1 mg/kg subcutaneous administration resulted in aPTT postinjection values of 50 seconds. The average aPTT prolongation value on Day 1 was about 16% higher than on Day 4.
12.3Pharmacokinetics Absorption Pharmacokinetic trials were conducted using the 100 mg/mL formulation. Maximum anti-Factor Xa and anti-thrombin (anti-Factor IIa) activities occur 3 to 5 hours after subcutaneous injection of enoxaparin. Mean peak anti-Factor Xa activity was
0.16IU/mL (1.58 mcg/mL) and
0.38IU/mL (3.83 mcg/mL) after the 20 mg and the 40 mg clinically tested subcutaneous doses, respectively. Mean (n=46) peak anti-Factor Xa activity was
1.1IU/mL at steady state in patients with unstable angina receiving 1 mg/kg subcutaneously every 12 hours for 14 days. Mean absolute bioavailability of enoxaparin, after 1.5 mg/kg given subcutaneously, based on anti-Factor Xa activity is approximately 100% in healthy subjects. A 30 mg intravenous bolus immediately followed by 1 mg/kg subcutaneously every 12 hours provided initial peak anti-Factor Xa levels of
1.16IU/mL (n=16) and average exposure corresponding to 84% of steady-state levels. Steady state is achieved on the second day of treatment. Enoxaparin pharmacokinetics appears to be linear over the recommended dosage ranges [see Dosage and Administration ( 2 )] .
After repeated subcutaneous administration of 40 mg once daily and 1.5 mg/kg once-daily regimens in healthy volunteers, the steady state is reached on day 2 with an average exposure ratio about 15% higher than after a single dose. Steady-state enoxaparin activity levels are well predicted by single-dose pharmacokinetics. After repeated subcutaneous administration of the 1 mg/kg twice-daily regimen, the steady state is reached from day 4 with mean exposure about 65% higher than after a single dose and mean peak and trough levels of about 1.2 and
0.52IU/mL, respectively. Based on enoxaparin sodium pharmacokinetics, this difference in steady state is expected and within the therapeutic range. Although not studied clinically, the 150 mg/mL concentration of enoxaparin sodium is projected to result in anticoagulant activities similar to those of 100 mg/mL and 200 mg/mL concentrations at the same enoxaparin dose.
When a daily 1.5 mg/kg subcutaneous injection of enoxaparin sodium was given to 25 healthy male and female subjects using a 100 mg/mL or a 200 mg/mL concentration the following pharmacokinetic profiles were obtained (see Table 13 ). Table 13: Pharmacokinetic Parameters* After 5 Days of 1.5 mg/kg Subcutaneous Once-Daily Doses of Enoxaparin Sodium Using 100 mg/mL or 200 mg/mL Concentrations * Means ±SD at Day 5 and 90% Confidence Interval (CI) of the ratio † Median (range) Concentration Anti-Xa Anti-IIa Heptest aPTT A max (IU/mL or Δ sec) 100 mg/mL 1.37 (±0.23) 0.23 (±0.05) 105 (±17) 19 (±5) 200 mg/mL 1.45 (±0.22) 0.26 (±0.05) 111 (±17) 22 (±7) 90% CI 102% to 110% 102% to 111% t max † (h) 100 mg/mL 3 (2 to 6) 4 (2 to 5) 2.5 (2 to 4.5) 3 (2 to 4.5) 200 mg/mL 3.5 (2 to 6) 4.5 (2.5 to 6) 3.3 (2 to 5) 3 (2 to 5) AUC (ss) (h*IU/mL or h* Δ sec) 100 mg/mL 14.26 (±2.93) 1.54 (±0.61) 1321 (±219) 200 mg/mL 15.… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Enoxaparin is a low molecular weight heparin which has antithrombotic properties.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Enoxaparin Sodium Injection, USP is supplied in two concentrations (see table 26 and 27). Table 26: 100 mg per mL Concentration * Strength represents the number of milligrams of enoxaparin sodium in Water for Injection. Enoxaparin Sodium Injection, USP 30 mg and 40 mg prefilled syringes, and 60 mg, 80 mg, and 100 mg graduated prefilled syringes each contain 10 mg enoxaparin sodium per 0.1 mL Water for Injection. † Approximate anti-Factor Xa activity based on reference to the W.H.O.
First International Low Molecular Weight Heparin Reference Standard. ‡ Each Enoxaparin Sodium Injection, USP prefilled syringe is for single, one-time use only and is affixed with a 27 gauge x 1/2 inch needle. NDC Strength* Anti-Xa Activity † Label Color Package Factor 71288- 432-92 30 mg per 0.3 mL Single-Dose Prefilled Syringe with Automatic Safety Device ‡ 3,000 IU Light Blue 10 syringes per carton 71288- 433-92 40 mg per 0.4 mL Single-Dose Prefilled Syringe with Automatic Safety Device ‡ 4,000 IU Yellow 10 syringes per carton 71288- 434-92 60 mg per 0.6 mL Single-Dose Graduated Prefilled Syringe with Automatic Safety Device ‡ 6,000 IU Orange 10 syringes per carton 71288- 435-92 80 mg per 0.8 mL Single-Dose Graduated Prefilled Syringe with Automatic Safety Device ‡ 8,000 IU Brown 10 syringes per carton 71288- 436-92 100 mg per mL Single-Dose Graduated Prefilled Syringe with Automatic Safety Device ‡ 10,000 IU Gray 10 syringes per carton Table 27: 150 mg per mL Concentration * Strength represents the number of milligrams of enoxaparin sodium in Water for Injection.
Enoxaparin Sodium Injection, USP 120 mg and 150 mg graduated prefilled syringes contain 15 mg enoxaparin sodium per 0.1 mL Water for Injection. † Approximate anti-Factor Xa activity based on reference to the W.H.O. First International Low Molecular Weight Heparin Reference Standard. ‡ Each Enoxaparin Sodium Injection, USP graduated prefilled syringe is for single, one-time use only and is affixed with a 27 gauge x 1/2 inch needle. NDC Strength* Anti-Xa Activity † Label Color Package Factor 71288- 437-94 120 mg per 0.8 mL Single-Dose Graduated Prefilled Syringe with Automatic Safety Device ‡ 12,000 IU Purple 10 syringes per carton 71288- 438-96 150 mg per mL Single-Dose Graduated Prefilled Syringe with Automatic Safety Device ‡ 15,000 IU Navy Blue 10 syringes per carton Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° and 30°C (59° and 86°F). [See USP Controlled Room Temperature.] Store in the original carton or packaging until ready to use.
WARNING: Keep out of the reach of children. Sterile, Nonpyrogenic, Preservative-free, PVC-free, DEHP-free. The container closure is not made with natural rubber latex.
📦 Storage and Handling ▾
Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° and 30°C (59° and 86°F). [See USP Controlled Room Temperature.] Store in the original carton or packaging until ready to use. WARNING: Keep out of the reach of children. Sterile, Nonpyrogenic, Preservative-free, PVC-free, DEHP-free. The container closure is not made with natural rubber latex.
📋 Description ▾
11 DESCRIPTION Enoxaparin Sodium Injection, USP is a sterile aqueous solution containing enoxaparin sodium, a low molecular weight heparin. The pH of the injection is 5.5 to 7.5. Enoxaparin sodium is obtained by alkaline depolymerization of heparin benzyl ester derived from porcine intestinal mucosa.
Its structure is characterized by a 2-O-sulfo-4-enepyranosuronic acid group at the non-reducing end and a 2-N,6-O-disulfo-D-glucosamine at the reducing end of the chain. About 20% (ranging between 15% and 25%) of the enoxaparin structure contains a 1,6-anhydro derivative on the reducing end of the polysaccharide chain. The drug substance is the sodium salt.
The average molecular weight is about 4,500 daltons. The molecular weight distribution is: <2,000 daltons ≤20% 2,000 to 8,000 daltons ≥68% >8,000 daltons ≤18% STRUCTURAL FORMULA * X = Percent of polysaccharide chain containing 1,6-anhydro derivative on the reducing end R X*=15 to 25% n=0 to 20 100-X H n=1 to 21 Enoxaparin Sodium Injection, USP 100 mg per mL Concentration contains 10 mg enoxaparin sodium (approximate anti-Factor Xa activity of 1,000 IU [with reference to the W.H.O. First International Low Molecular Weight Heparin Reference Standard]) per 0.1 mL Water for Injection.
Enoxaparin Sodium Injection, USP 150 mg per mL Concentration contains 15 mg enoxaparin sodium (approximate anti-Factor Xa activity of 1,500 IU [with reference to the W.H.O. First International Low Molecular Weight Heparin Reference Standard]) per 0.1 mL Water for Injection. The Enoxaparin Sodium Injection, USP prefilled syringes and graduated prefilled syringes are preservative-free and intended for use only as a single-dose injection [see Dosage and Administration ( 2 ) and How Supplied/Storage and Handling ( 16 )] . structural formula 1 structural formula 2
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Instructions for Use ). If patients have had neuraxial anesthesia or spinal puncture, and particularly, if they are taking concomitant NSAIDs, platelet inhibitors, or other anticoagulants, advise them to watch for signs and symptoms of spinal or epidural hematoma, such as tingling, numbness (especially in the lower limbs) and muscular weakness. Instruct the patient to seek immediate medical attention if any of these symptoms occur.
Inform patients: of the instructions for injecting enoxaparin sodium if they continue enoxaparin sodium therapy after discharge from the hospital. that it may take them longer than usual to stop bleeding. that they may bruise and/or bleed more easily when they use enoxaparin sodium. that they should report any unusual bleeding, bruising, or signs of thrombocytopenia (such as a rash of dark red spots under the skin) to their physician [see Warnings and Precautions ( 5.1 , 5.5 )] . to tell their physicians and dentists they are taking enoxaparin sodium and/or any other product known to affect bleeding before any surgery is scheduled and before any new drug is taken [see Warnings and Precautions ( 5.1 , 5.3 )] . to tell their physicians and dentists of all medications they are taking, including those obtained without a prescription, such as aspirin or other NSAIDs [see Drug Interactions ( 7 )] . meitheal ® Mfd. for Meitheal Pharmaceuticals Chicago, IL 60631 (USA) ©2022 Meitheal Pharmaceuticals Inc.
Mfd. by Nanjing King-Friend Biochemical Pharmaceutical Co., Ltd. Nanjing, China 210061 October 2022 8A1CB23-00
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Pharmacokinetic trials were conducted using the 100 mg/mL formulation. Maximum anti-Factor Xa and anti-thrombin (anti-Factor IIa) activities occur 3 to 5 hours after subcutaneous injection of enoxaparin. Mean peak anti-Factor Xa activity was
0.16IU/mL (1.58 mcg/mL) and
0.38IU/mL (3.83 mcg/mL) after the 20 mg and the 40 mg clinically tested subcutaneous doses, respectively. Mean (n=46) peak anti-Factor Xa activity was
1.1IU/mL at steady state in patients with unstable angina receiving 1 mg/kg subcutaneously every 12 hours for 14 days. Mean absolute bioavailability of enoxaparin, after 1.5 mg/kg given subcutaneously, based on anti-Factor Xa activity is approximately 100% in healthy subjects. A 30 mg intravenous bolus immediately followed by 1 mg/kg subcutaneously every 12 hours provided initial peak anti-Factor Xa levels of
1.16IU/mL (n=16) and average exposure corresponding to 84% of steady-state levels. Steady state is achieved on the second day of treatment. Enoxaparin pharmacokinetics appears to be linear over the recommended dosage ranges [see Dosage and Administration ( 2 )] .
After repeated subcutaneous administration of 40 mg once daily and 1.5 mg/kg once-daily regimens in healthy volunteers, the steady state is reached on day 2 with an average exposure ratio about 15% higher than after a single dose. Steady-state enoxaparin activity levels are well predicted by single-dose pharmacokinetics. After repeated subcutaneous administration of the 1 mg/kg twice-daily regimen, the steady state is reached from day 4 with mean exposure about 65% higher than after a single dose and mean peak and trough levels of about 1.2 and
0.52IU/mL, respectively. Based on enoxaparin sodium pharmacokinetics, this difference in steady state is expected and within the therapeutic range. Although not studied clinically, the 150 mg/mL concentration of enoxaparin sodium is projected to result in anticoagulant activities similar to those of 100 mg/mL and 200 mg/mL concentrations at the same enoxaparin dose.
When a daily 1.5 mg/kg subcutaneous injection of enoxaparin sodium was given to 25 healthy male and female subjects using a 100 mg/mL or a 200 mg/mL concentration the following pharmacokinetic profiles were obtained (see Table 13 ). Table 13: Pharmacokinetic Parameters* After 5 Days of 1.5 mg/kg Subcutaneous Once-Daily Doses of Enoxaparin Sodium Using 100 mg/mL or 200 mg/mL Concentrations * Means ±SD at Day 5 and 90% Confidence Interval (CI) of the ratio † Median (range) Concentration Anti-Xa Anti-IIa Heptest aPTT A max (IU/mL or Δ sec) 100 mg/mL 1.37 (±0.23) 0.23 (±0.05) 105 (±17) 19 (±5) 200 mg/mL 1.45 (±0.22) 0.26 (±0.05) 111 (±17) 22 (±7) 90% CI 102% to 110% 102% to 111% t max † (h) 100 mg/mL 3 (2 to 6) 4 (2 to 5) 2.5 (2 to 4.5) 3 (2 to 4.5) 200 mg/mL 3.5 (2 to 6) 4.5 (2.5 to 6) 3.3 (2 to 5) 3 (2 to 5) AUC (ss) (h*IU/mL or h* Δ sec) 100 mg/mL 14.26 (±2.93) 1.54 (±0.61) 1321 (±219) 200 mg/mL 15.43 (±2.96) 1.77 (±0.67) 1401 (±227) 90% CI 105% to 112% 103% to 109% Distribution The volume of distribution of anti-Factor Xa activity is about
4.3L. Elimination Following intravenous dosing, the total body clearance of enoxaparin is 26 mL/min. After intravenous dosing of enoxaparin labeled with the gamma-emitter, 99m Tc, 40% of radioactivity and 8 to 20% of anti-Factor Xa activity were recovered in urine in 24 hours.
Elimination half-life based on anti-Factor Xa activity was 4.5 hours after a single subcutaneous dose to about 7 hours after repeated dosing. Significant anti-Factor Xa activity persists in plasma for about 12 hours following a 40 mg subcutaneous once a day dose. Following subcutaneous dosing, the apparent clearance (CL/F) of enoxaparin is approximately 15 mL/min.
Metabolism Enoxaparin sodium is primarily metabolized in the liver by desulfation and/or depolymerization to lower molecular weight species with much reduced biological potency. Renal clearance of active fragments represents about 10% of the… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In humans, enoxaparin given at a dose of 1.5 mg/kg subcutaneously is characterized by a higher ratio of anti-Factor Xa to anti-Factor IIa activity (mean ±SD, 14.0±3.1) (based on areas under anti-Factor activity versus time curves) compared to the ratios observed for heparin (mean ±SD, 1.22±0.13). Increases of up to 1.8 times the control values were seen in the thrombin time (TT) and the activated partial thromboplastin time (aPTT). Enoxaparin at a 1 mg/kg dose (100 mg/mL concentration), administered subcutaneously every 12 hours to patients in a large clinical trial resulted in aPTT values of 45 seconds or less in the majority of patients (n=1607).
A 30 mg intravenous bolus immediately followed by a 1 mg/kg subcutaneous administration resulted in aPTT postinjection values of 50 seconds. The average aPTT prolongation value on Day 1 was about 16% higher than on Day 4.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Prophylaxis of Deep Vein Thrombosis following Abdominal Surgery in Patients at Risk for Thromboembolic Complications Abdominal surgery patients at risk include those who are over 40 years of age, obese, undergoing surgery under general anesthesia lasting longer than 30 minutes or who have additional risk factors such as malignancy or a history of deep vein thrombosis (DVT) or pulmonary embolism (PE). In a double-blind, parallel group study of patients undergoing elective cancer surgery of the gastrointestinal, urological, or gynecological tract, a total of 1116 patients were enrolled in the study, and 1115 patients were treated.
Patients ranged in age from 32 to 97 years (mean age 67 years) with 52.7% men and 47.3% women. Patients were 98% Caucasian, 1.1% Black, 0.4% Asian and 0.4% others. Enoxaparin sodium 40 mg subcutaneously, administered once a day, beginning 2 hours prior to surgery and continuing for a maximum of 12 days after surgery, was comparable to heparin 5,000 U every 8 hours subcutaneously in reducing the risk of DVT.
The efficacy data are provided below (see Table 14 ). Table 14: Efficacy of Enoxaparin Sodium in the Prophylaxis of Deep Vein Thrombosis following Abdominal Surgery * VTE = Venous thromboembolic events which included DVT, PE, and death considered to be thromboembolic in origin † CI = Confidence Interval Indication Dosing Regimen Enoxaparin Sodium 40 mg daily subcutaneously n (%) Heparin 5,000 U q8h subcutaneously n (%) All Treated Abdominal Surgery Patients 555 (100) 560 (100) Treatment Failures Total VTE* (%) 56 (10.1) (95% CI † : 8 to 13) 63 (11.3) (95% CI: 9 to 14) DVT Only (%) 54 (9.7) (95% CI: 7 to 12) 61 (10.9) (95% CI: 8 to 13) In a second double-blind, parallel group study, enoxaparin sodium 40 mg subcutaneously once a day was compared to heparin 5,000 U every 8 hours subcutaneously in patients undergoing colorectal surgery (one-third with cancer).
A total of 1347 patients were randomized in the study and all patients were treated. Patients ranged in age from 18 to 92 years (mean age 50.1 years) with 54.2% men and 45.8% women. Treatment was initiated approximately 2 hours prior to surgery and continued for approximately 7 to 10 days after surgery.
The efficacy data are provided below (see Table 15 ). Table 15: Efficacy of Enoxaparin Sodium in the Prophylaxis of Deep Vein Thrombosis following Colorectal Surgery * VTE = Venous thromboembolic events which included DVT, PE, and death considered to be thromboembolic in origin † CI = Confidence Interval Indication Dosing Regimen Enoxaparin Sodium 40 mg daily subcutaneously n (%) Heparin 5,000 U q8h subcutaneously n (%) All Treated Colorectal Surgery Patients 673 (100) 674 (100) Treatment Failures Total VTE* (%) 48 (7.1) (95% CI † : 5 to 9) 45 (6.7) (95% CI: 5 to 9) DVT Only (%) 47 (7.0) (95% CI: 5 to 9) 44 (6.5) (95% CI: 5 to 8)
14.2Prophylaxis of Deep Vein Thrombosis following Hip or Knee Replacement Surgery Enoxaparin sodium has been shown to reduce the risk of postoperative deep vein thrombosis (DVT) following hip or knee replacement surgery. In a double-blind study, enoxaparin sodium 30 mg every 12 hours subcutaneously was compared to placebo in patients with hip replacement. A total of 100 patients were randomized in the study and all patients were treated.
Patients ranged in age from 41 to 84 years (mean age 67.1 years) with 45% men and 55% women. After hemostasis was established, treatment was initiated 12 to 24 hours after surgery and was continued for 10 to 14 days after surgery. The efficacy data are provided below (see Table 16 ).
Table 16: Efficacy of Enoxaparin Sodium in the Prophylaxis of Deep Vein Thrombosis following Hip Replacement Surgery * p value versus placebo = 0.0002 † p value versus placebo = 0.0134 Indication Dosing Regimen Enoxaparin Sodium 30 mg q12h subcutaneously n (%) Placebo q12h subcutaneously n (%) All Treated Hip Replacement Patients 50 (100) 50 (100) Treatment Failures Total DVT (%) 5 (1… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No long-term studies in animals have been performed to evaluate the carcinogenic potential of enoxaparin. Enoxaparin was not mutagenic in in vitro tests, including the Ames test, mouse lymphoma cell forward mutation test, and human lymphocyte chromosomal aberration test, and the in vivo rat bone marrow chromosomal aberration test. Enoxaparin was found to have no effect on fertility or reproductive performance of male and female rats at subcutaneous doses up to 20 mg/kg/day or 141 mg/m 2 /day.
The maximum human dose in clinical trials was 2.0 mg/kg/day or 78 mg/m 2 /day (for an average body weight of 70 kg, height of 170 cm, and body surface area of 1.8 m 2 ).
13.2Animal Toxicology and/or Pharmacology A single subcutaneous dose of 46.4 mg/kg enoxaparin was lethal to rats. The symptoms of acute toxicity were ataxia, decreased motility, dyspnea, cyanosis, and coma.
13.3Reproductive and Developmental Toxicology Teratology studies have been conducted in pregnant rats and rabbits at subcutaneous doses of enoxaparin up to 30 mg/kg/day corresponding to 211 mg/m 2 /day and 410 mg/m 2 /day in rats and rabbits respectively. There was no evidence of teratogenic effects or fetotoxicity due to enoxaparin.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No long-term studies in animals have been performed to evaluate the carcinogenic potential of enoxaparin. Enoxaparin was not mutagenic in in vitro tests, including the Ames test, mouse lymphoma cell forward mutation test, and human lymphocyte chromosomal aberration test, and the in vivo rat bone marrow chromosomal aberration test. Enoxaparin was found to have no effect on fertility or reproductive performance of male and female rats at subcutaneous doses up to 20 mg/kg/day or 141 mg/m 2 /day.
The maximum human dose in clinical trials was 2.0 mg/kg/day or 78 mg/m 2 /day (for an average body weight of 70 kg, height of 170 cm, and body surface area of 1.8 m 2 ).
📄 Patient Package Insert ▾
INSTRUCTIONS FOR USE ENOXAPARIN SODIUM (ee nox” a par’ in soe’ dee um) INJECTION for subcutaneous use Single-dose prefilled syringe This Instructions for Use contains information on how to prepare and inject Enoxaparin Sodium Injection prefilled syringe. Read this Instructions for Use before using the Enoxaparin Sodium Injection prefilled syringe and each time you get a new prescription. There may be new information.
Do not inject yourself or someone else until you have been shown how to inject Enoxaparin Sodium Injection. Your healthcare provider can show you or your caregiver how to prepare and inject a dose of Enoxaparin Sodium Injection. Call your healthcare provider if you have any questions.
Important information: Your healthcare provider will tell you the prescribed dose that you should take and how often you will need to inject Enoxaparin Sodium Injection. If your dose is based on your body weight, your dose of Enoxaparin Sodium Injection might be less than what is in the prefilled syringe. Enoxaparin Sodium Injection is injected as a subcutaneous (under the skin) injection only.
Do not inject Enoxaparin Sodium Injection into muscle. Do not use the Enoxaparin Sodium Injection prefilled syringe if the needle cap is missing or not securely attached. Do not remove the needle cap until just before you give the injection.
Do not touch the syringe plunger rod until you are ready to inject. Do not pull back on the plunger rod at any time. Do not get rid of any air bubble(s) in the Enoxaparin Sodium Injection prefilled syringe.
This can lead to a loss of the medicine. To avoid bruising, do not rub the injection site after you have injected yourself. To protect from needle-stick injuries, each prefilled syringe has a safety system that covers the needle after injection.
Throw away (dispose of) the used Enoxaparin Sodium Injection prefilled syringe and needle cap right away after use, even if there is medicine left in the prefilled syringe. See “ Step 13: Dispose of used Enoxaparin Sodium Injection prefilled syringes and needle caps ” below. Enoxaparin Sodium Injection is for one time use only.
Do not reuse an Enoxaparin Sodium Injection prefilled syringe. Storing Enoxaparin Sodium Injection prefilled syringes: Store Enoxaparin Sodium Injection prefilled syringes at 77°F (25°C). Store Enoxaparin Sodium Injection prefilled syringes in the original carton or packaging until ready to use.
Keep Enoxaparin Sodium Injection and all medicines out of the reach of children. Parts of Enoxaparin Sodium Injection prefilled syringe: Preparing to inject Enoxaparin Sodium Injection: Step 1: Gather the following supplies for your injection (see Figure A ) : 1 Enoxaparin Sodium Injection prefilled syringe 1 alcohol wipe* 1 cotton ball or gauze* a small adhesive bandage, if needed* a sharps disposal container* (see Step 13) *Items not included. Figure A Step 2: Wash your hands well with soap and water.
Step 3: Preparing a dose of Enoxaparin Sodium Injection Take the prefilled syringe out of the package. Open the packaging by peeling the lid at the arrow as directed. Take the prefilled syringe out of the plastic container by holding the middle of the syringe body (see Figure B ).
Do not remove the prefilled syringe by pulling on the plunger rod or the needle cap as this may damage the syringe. Do not pull off the needle cap until you are ready to inject. Do not use the Enoxaparin Sodium Injection prefilled syringe if it has been dropped on a hard surface or damaged.
Figure B Step 4: Check the Enoxaparin Sodium Injection prefilled syringe When you receive your Enoxaparin Sodium Injection syringes, always check to see that: you have the correct medicine and dose. the expiration date on the prefilled syringe has not passed (see Figure C ). Do not use the Enoxaparin Sodium Injection prefilled syringe if the expiration date has passed. Figure C Step 5: Check the medicine Look at the medicine inside the Enoxaparin Sodium Injection prefilled syringe: The… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
Principal Display Panel – Enoxaparin Sodium Injection, USP 30 mg Blister Pack Label NDC 71288- 432 -91 Rx Only Enoxaparin Sodium Injection, USP 30 mg per 0.3 mL For Subcutaneous Injection One 0.3 mL Single-Dose Prefilled Syringe with Automatic Safety Device Principal Display Panel – Enoxaparin Sodium Injection, USP 30 mg Blister Pack Label
Principal Display Panel – Enoxaparin Sodium Injection, USP 30 mg Carton NDC 71288- 432 -92 10 x 0.3 mL Single-Dose Prefilled Syringes with Automatic Safety Device Rx Only Enoxaparin Sodium Injection, USP 30 mg per 0.3 mL For Subcutaneous Injection Principal Display Panel – Enoxaparin Sodium Injection, USP 30 mg Carton
Principal Display Panel – Enoxaparin Sodium Injection, USP 40 mg Blister Pack Label NDC 71288- 433 -91 Rx Only Enoxaparin Sodium Injection, USP 40 mg per 0.4 mL For Subcutaneous Injection One 0.4 mL Single-Dose Prefilled Syringe with Automatic Safety Device Principal Display Panel – Enoxaparin Sodium Injection, USP 40 mg Blister Pack Label
Principal Display Panel – Enoxaparin Sodium Injection, USP 40 mg Carton NDC 71288- 433 -92 10 x 0.4 mL Single-Dose Prefilled Syringes with Automatic Safety Device Rx Only Enoxaparin Sodium Injection, USP 40 mg per 0.4 mL For Subcutaneous Injection Principal Display Panel – Enoxaparin Sodium Injection, USP 40 mg Carton
Principal Display Panel – Enoxaparin Sodium Injection, USP 60 mg Blister Pack Label NDC 71288- 434 -91 Rx Only Enoxaparin Sodium Injection, USP 60 mg per 0.6 mL For Subcutaneous Injection One 0.6 mL Single-Dose Prefilled Syringe with Automatic Safety Device Principal Display Panel – Enoxaparin Sodium Injection, USP 60 mg Blister Pack Label
Principal Display Panel – Enoxaparin Sodium Injection, USP 60 mg Carton NDC 71288- 434 -92 10 x 0.6 mL Single-Dose Prefilled Syringes with Automatic Safety Device Rx Only Enoxaparin Sodium Injection, USP 60 mg per 0.6 mL For Subcutaneous Injection Principal Display Panel – Enoxaparin Sodium Injection, USP 60 mg Carton
Principal Display Panel – Enoxaparin Sodium Injection, USP 80 mg Blister Pack Label NDC 71288- 435 -91 Rx Only Enoxaparin Sodium Injection, USP 80 mg per 0.8 mL For Subcutaneous Injection One 0.8 mL Single-Dose Prefilled Syringe with Automatic Safety Device Principal Display Panel – Enoxaparin Sodium Injection, USP 80 mg Blister Pack Label
Principal Display Panel – Enoxaparin Sodium Injection, USP 80 mg Carton NDC 71288- 435 -92 10 x 0.8 mL Single-Dose Prefilled Syringes with Automatic Safety Device Rx Only Enoxaparin Sodium Injection, USP 80 mg per 0.8 mL For Subcutaneous Injection Principal Display Panel – Enoxaparin Sodium Injection, USP 80 mg Carton
Principal Display Panel – Enoxaparin Sodium Injection, USP 100 mg Blister Pack Label NDC 71288- 436 -91 Rx Only Enoxaparin Sodium Injection, USP 100 mg per mL For Subcutaneous Injection One 1 mL Single-Dose Prefilled Syringe with Automatic Safety Device Principal Display Panel – Enoxaparin Sodium Injection, USP 100 mg Blister Pack Label
Principal Display Panel – Enoxaparin Sodium Injection, USP 100 mg Carton NDC 71288- 436 -92 10 x 1 mL Single-Dose Prefilled Syringes with Automatic Safety Device Rx Only Enoxaparin Sodium Injection, USP 100 mg per mL For Subcutaneous Injection Principal Display Panel – Enoxaparin Sodium Injection, USP 100 mg Carton
Principal Display Panel – Enoxaparin Sodium Injection, USP 120 mg Blister Pack Label NDC 71288- 437 -93 Rx Only Enoxaparin Sodium Injection, USP 120 mg per 0.8 mL For Subcutaneous Injection One 0.8 mL Single-Dose Prefilled Syringe with Automatic Safety Device Principal Display Panel – Enoxaparin Sodium Injection, USP 120 mg Blister Pack Label
Principal Display Panel – Enoxaparin Sodium Injection, USP 120 mg Carton NDC 71288- 437 -94 10 x 0.8 mL Single-Dose Prefilled Syringes with Automatic Safety Device Rx Only Enoxaparin Sodium Injection, USP 120 mg per 0.8 mL For Subcutaneous Injection Principal Display Panel – Enoxaparin Sodium Injection, USP 120 mg Carton
Principal Displa… [Excerpted — this section continues on DailyMed.]