
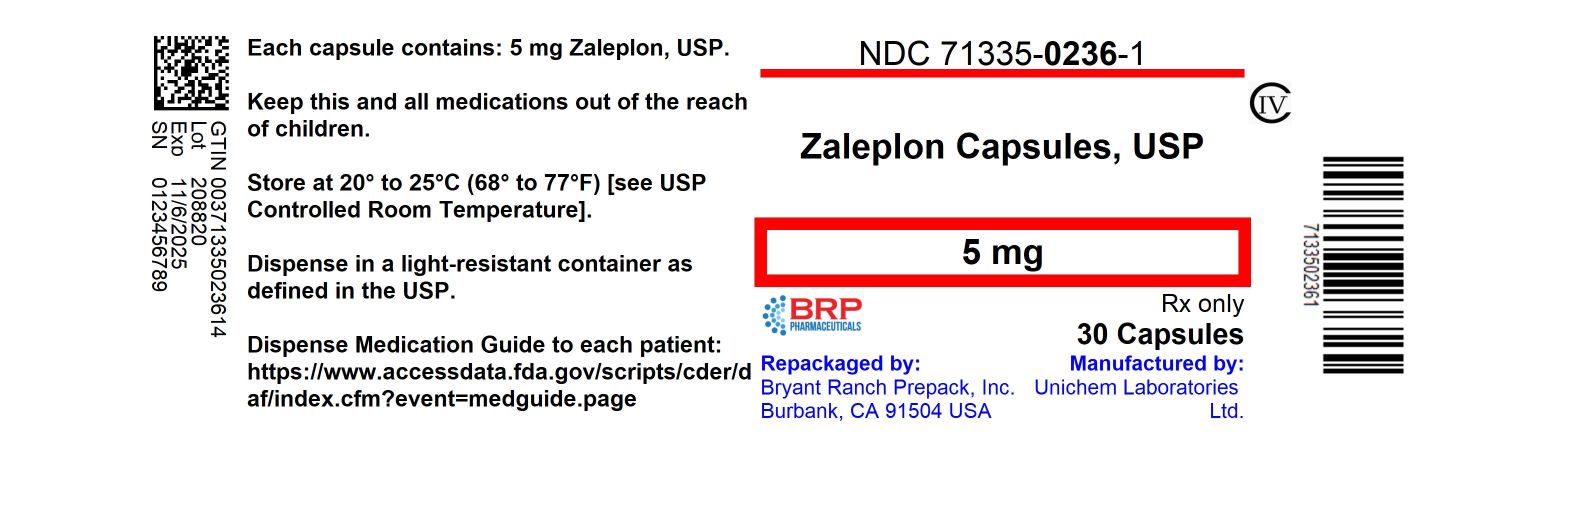
zaleplon 5 mg Capsule, 20-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the gamma-Aminobutyric Acid A Receptor Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Zaleplon is used on a short-term basis to treat insomnia (difficulty falling asleep). Zaleplon does not help you to stay asleep longer or decrease the number of times that you awaken during the night. Zaleplon is in a class of medications called hypnotics. It works by slowing activity in the brain to allow sleep.
Read the full MedlinePlus article ↗- Zaleplon is designed specifically to help you fall asleep faster, not to keep you asleep longer. Studies have shown it reduces the time it takes to drift off, but it hasn't been pr...
- What exactly does zaleplon do — will it keep me asleep all night?
- Take zaleplon right before you get into bed, or after you've already gone to bed but can't fall asleep. Try to take it on an empty stomach or with a very light snack. A heavy, high...
- When should I take it, and does it matter if I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Zaleplon — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII I753WB2F1M
FD&C Yellow No. 5 is a synthetic yellow colorant approved by the FDA. It is added to medicines to make pills, tablets, or liquids visually distinct and easier to identify.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3373 | $6.75 / 20 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Zaleplon 5 mg 00054-0084-25 | Hikma | 100 capsules | $0.144 | AB | Availability likely | — |
| zaleplon 5 mg 29300-0131-01 | Unichem | 100 capsules | $0.144 | AB | Availability likely | — |
| Zaleplon 5 mg 57237-0239-01 | Rising | 100 capsules | $0.144 | AB | Availability likely | — |
| Zaleplon 5 mg 65862-0214-01 | Aurobindo | 100 capsules | $0.144 | AB | Availability likely | — |
| Zaleplon 5 mg 69452-0364-20 | Bionpharma | 100 capsules | $0.144 | AB | Availability likely | — |
| Zaleplon 5 mg 43063-0505-30 | PD-Rx | 30 capsules | — | AB | FDA listed | — |
| zaleplon 5 mgthis 71335-0236-04 | Bryant | 20 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-0236-01 | 30 CAPSULE in 1 BOTTLE (71335-0236-1) | 2019-05-08 | Active |
| 71335-0236-02 | 60 CAPSULE in 1 BOTTLE (71335-0236-2) | 2018-03-23 | Active |
| 71335-0236-03 | 90 CAPSULE in 1 BOTTLE (71335-0236-3) | 2021-12-27 | Active |
| 71335-0236-04 You're viewing this | 20 CAPSULE in 1 BOTTLE (71335-0236-4) | 2021-12-27 | Active |
| 71335-0236-05 | 28 CAPSULE in 1 BOTTLE (71335-0236-5) | 2021-12-27 | Active |
You're viewing the smallest of 5 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-0236-04?
What is the difference between NDC 71335-0236-04 and NDC 71335-0236-05?
What NDC number is used to bill for this package of zaleplon 5 mg Capsule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: COMPLEX SLEEP BEHAVIORS Complex sleep behaviors including sleep-walking, sleep-driving, and engaging in other activities while not fully awake may occur following use of zaleplon. Some of these events may result in serious injuries, including death. Discontinue zaleplon immediately if a patient experiences a complex sleep behavior (see CONTRAINDICATIONS and Complex Sleep Behaviors under WARNINGS).
Zaleplon capsules are a federally controlled substance (C-IV) because it can be abused or lead to dependence. Keep zaleplon capsules in a safe place to prevent misuse and abuse. Selling or giving away zaleplon capsules may harm others, and is against the law. Tell your doctor if you have ever abused or been dependent on alcohol, prescription medicines or street drugs.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Zaleplon capsules are indicated for the short-term treatment of insomnia. Zaleplon capsules have been shown to decrease the time to sleep onset for up to 30 days in controlled clinical studies (see Clinical Trials under CLINICAL PHARMACOLOGY ). It has not been shown to increase total sleep time or decrease the number of awakenings.
The clinical trials performed in support of efficacy ranged from a single night to 5 weeks in duration. The final formal assessments of sleep latency were performed at the end of treatment.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The dose of zaleplon capsules should be individualized. The recommended dose of zaleplon capsules for most nonelderly adults is 10 mg. For certain low weight individuals, 5 mg may be a sufficient dose.
Although the risk of certain adverse events associated with the use of zaleplon capsules appears to be dose dependent, the 20 mg dose has been shown to be adequately tolerated and may be considered for the occasional patient who does not benefit from a trial of a lower dose. Doses above 20 mg have not been adequately evaluated and are not recommended. Zaleplon capsules should be taken immediately before bedtime or after the patient has gone to bed and has experienced difficulty falling asleep (see PRECAUTIONS ).
Taking zaleplon capsules with or immediately after a heavy, high-fat meal results in slower absorption and would be expected to reduce the effect of zaleplon capsules on sleep latency (see Pharmacokinetics under CLINICAL PHARMACOLOGY ). Special Populations Elderly patients and debilitated patients appear to be more sensitive to the effects of hypnotics, and respond to 5 mg of zaleplon capsules. The recommended dose for these patients is therefore 5 mg.
Doses over 10 mg are not recommended. Hepatic insufficiency: Patients with mild to moderate hepatic impairment should be treated with zaleplon capsules 5 mg because clearance is reduced in this population. Zaleplon capsules are not recommended for use in patients with severe hepatic impairment.
Renal insufficiency: No dose adjustment is necessary in patients with mild to moderate renal impairment. Zaleplon capsules have not been adequately studied in patients with severe renal impairment. An initial dose of 5 mg should be given to patients concomitantly taking cimetidine because zaleplon clearance is reduced in this population (see Drug Interactions under PRECAUTIONS ).
⛔ Contraindications ▾
CONTRAINDICATIONS Zaleplon is contraindicated in patients: who have experienced complex sleep behaviors after taking zaleplon (see WARNINGS ) with hypersensitivity to zaleplon or any excipients in the formulation (see PRECAUTIONS )
⚠️ Warnings ▾
WARNINGS Complex Sleep Behaviors Complex sleep behaviors including sleep-walking, sleep-driving, and engaging in other activities while not fully awake may occur following the first or any subsequent use of zaleplon. Patients can be seriously injured or injure others during complex sleep behaviors. Such injuries may result in a fatal outcome. a.
Other complex sleep behaviors (e.g., preparing and eating food, making phone calls, or having sex) have also been reported. Patients usually do not remember these events. Post-marketing reports have shown that complex sleep behaviors may occur with zaleplon alone at recommended dosages, with or without the concomitant use of alcohol or other central nervous system (CNS) depressants.
CNS-Depressant Effects and Next-Day Impairment Zaleplon, like other hypnotics, has CNS-depressant effects. Because of the rapid onset of action, zaleplon should only be ingested immediately prior to going to bed or after the patient has gone to bed and has experienced difficulty falling asleep . Coadministration with other CNS depressants (e.g., benzodiazepines, opioids, tricyclic antidepressants, alcohol) increases the risk of CNS depression.
Dosage adjustments of zaleplon and of other concomitant CNS depressants may be necessary when zaleplon is administered with such agents because of the potentially additive effects. The use of zaleplon with other sedative-hypnotics at bedtime or the middle of the night is not recommended (see DOSAGE AND ADMINISTRATION ). The risk of next-day psychomotor impairment, including impaired driving, is increased if zaleplon is taken with less than a full night of sleep remaining (7 to 8 hours); if a higher than the recommended dose is taken; if coadministered with other CNS depressants or alcohol; or if coadministered with other drugs that increase the blood levels of zaleplon.
Patients should be warned against driving and other activities requiring complete mental alertness if zaleplon is taken in these circumstances (see DOSAGE AND ADMINISTRATION and Clinical Trials under CLINICAL PHARMACOLOGY ). Vehicle drivers and machine operators should be warned that, as with other hypnotics, there may be a possible risk of adverse reactions including drowsiness, prolonged reaction time, dizziness, sleepiness, blurred/double vision, reduced alertness, and impaired driving the morning after therapy. In order to minimize this risk a full night of sleep (7-8 hours) is recommended.
Because zaleplon can cause drowsiness and a decreased level of consciousness, patients, particularly the elderly, are at higher risk of falls. Need to Evaluate for Co-morbid Diagnoses Because sleep disturbances may be the presenting manifestation of a physical and/or psychiatric disorder, symptomatic treatment of insomnia should be initiated only after a careful evaluation of the patient. The failure of insomnia to remit after 7 to 10 days of treatment may indicate the presence of a primary psychiatric and/or medical illness that should be evaluated.
Worsening of insomnia or the emergence of new thinking or behavior abnormalities may be the consequence of an unrecognized psychiatric or physical disorder. Such findings have emerged during the course of treatment with sedative/hypnotic drugs, including zaleplon. Because some of the important adverse effects of zaleplon appear to be dose-related, it is important to use the lowest possible effective dose, especially in the elderly (see DOSAGE AND ADMINISTRATION ).
Severe Anaphylactic and Anaphylactoid Reactions Rare cases of angioedema involving the tongue, glottis or larynx have been reported in patients after taking the first or subsequent doses of sedative-hypnotics, including zaleplon. Some patients have had additional symptoms such as dyspnea, throat closing, or nausea and vomiting that suggest anaphylaxis. Some patients have required medical therapy in the emergency department.
If angioedema involves the tongue, glottis or larynx, airway obstruction may occur…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The premarketing development program for zaleplon included zaleplon exposures in patients and/or normal subjects from 2 different groups of studies: approximately 900 normal subjects in clinical pharmacology/pharmacokinetic studies; and approximately 2,900 exposures from patients in placebo-controlled clinical effectiveness studies, corresponding to approximately 450 patient exposure years. The conditions and duration of treatment with zaleplon varied greatly and included (in overlapping categories) open-label and double-blind phases of studies, inpatients and outpatients, and short-term or longer-term exposure.
Adverse reactions were assessed by collecting adverse events, results of physical examinations, vital signs, weights, laboratory analyses, and ECGs. Adverse events during exposure were obtained primarily by general inquiry and recorded by clinical investigators using terminology of their own choosing. Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse events without first grouping similar types of events into a smaller number of standardized event categories.
In the tables and tabulations that follow, COSTART terminology has been used to classify reported adverse events. The stated frequencies of adverse events represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse event of the type listed. An event was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation.
Adverse Findings Observed in Short-Term, Placebo-Controlled Trials Adverse Events Associated With Discontinuation of Treatment In premarketing placebo-controlled, parallel-group phase 2 and phase 3 clinical trials, 3.1% of 744 patients who received placebo and 3.7% of 2,149 patients who received zaleplon discontinued treatment because of an adverse clinical event. This difference was not statistically significant. No event that resulted in discontinuation occurred at a rate of ≥1%.
Adverse Events Occurring at an Incidence of 1% or More Among Zaleplon 20 mg-Treated Patients Table 1 enumerates the incidence of treatment-emergent adverse events for a pool of three 28-night and one 35-night placebo-controlled studies of zaleplon at doses of 5 mg or 10 mg and 20 mg. The table includes only those events that occurred in 1% or more of patients treated with zaleplon 20 mg and that had a higher incidence in patients treated with zaleplon 20 mg than in placebo-treated patients. The prescriber should be aware that these figures cannot be used to predict the incidence of adverse events in the course of usual medical practice where patient characteristics and other factors differ from those which prevailed in the clinical trials.
Similarly, the cited frequencies cannot be compared with figures obtained from other clinical investigations involving different treatments, uses, and investigators. The cited figures, however, do provide the prescribing physician with some basis for estimating the relative contribution of drug and non-drug factors to the adverse event incidence rate in the population studied. Table 1 Incidence (%) of Treatment-Emergent Adverse Events in Long-Term (28 and 35 Nights) Placebo-Controlled Clinical Trials of Zaleplon a a Events for which the incidence for zaleplon 20 mg-treated patients was at least 1% and greater than the incidence among placebo-treated patients.
Incidence greater than 1% has been rounded to the nearest whole number. Body System Placebo Zaleplon 5 mg or 10 mg Zaleplon 20 mg Preferred Term (n=344) (n=569) (n=297) Body as a whole Abdominal pain 3 6 6 Asthenia 5 5 7 Headache 35 30 42 Malaise <1 <1 2 Photosensitivity reaction <1 <1 1 Digestive system Anorexia <1 <1 2 Colitis 0 0 1 Nausea 7 6 8 Metabolic and nutritional Peripheral edema <1 <1 1 Nervous system Amnesia 1 2 4 Confusion <1 <1 1 Depersonalization <1 <1 2 Dizziness 7 7 9 Hallucin…
🔄 Drug Interactions ▾
Drug Interactions As with all drugs, the potential exists for interaction with other drugs by a variety of mechanisms. CNS-Active Drugs Ethanol: Zaleplon 10 mg potentiated the CNS-impairing effects of ethanol 0.75 g/kg on balance testing and reaction time for 1 hour after ethanol administration and on the digit symbol substitution test (DSST), symbol copying test, and the variability component of the divided attention test for 2.5 hours after ethanol administration. The potentiation resulted from a CNS pharmacodynamic interaction; zaleplon did not affect the pharmacokinetics of ethanol.
Imipramine: Coadministration of single doses of zaleplon 20 mg and imipramine 75 mg produced additive effects on decreased alertness and impaired psychomotor performance for 2 to 4 hours after administration. The interaction was pharmacodynamic with no alteration of the pharmacokinetics of either drug. Paroxetine: Coadministration of a single dose of zaleplon 20 mg and paroxetine 20 mg daily for 7 days did not produce any interaction on psychomotor performance.
Additionally, paroxetine did not alter the pharmacokinetics of zaleplon, reflecting the absence of a role of CYP2D6 in zaleplon 's metabolism. Thioridazine: Coadministration of single doses of zaleplon 20 mg and thioridazine 50 mg produced additive effects on decreased alertness and impaired psychomotor performance for 2 to 4 hours after administration. The interaction was pharmacodynamic with no alteration of the pharmacokinetics of either drug.
Venlafaxine: Coadministration of a single dose of zaleplon 10 mg and multiple doses of venlafaxine ER (extended release) 150 mg did not result in any significant changes in the pharmacokinetics of either zaleplon or venlafaxine. In addition, there was no pharmacodynamic interaction as a result of coadministration of zaleplon and venlafaxine ER. Promethazine: Coadministration of a single dose of zaleplon and promethazine (10 and 25 mg, respectively) resulted in a 15% decrease in maximal plasma concentrations of zaleplon, but no change in the area under the plasma concentration-time curve.
However, the pharmacodynamics of coadministration of zaleplon and promethazine have not been evaluated. Caution should be exercised when these 2 agents are coadministered. Drugs That Induce CYP3A4 Rifampin: CYP3A4 is ordinarily a minor metabolizing enzyme of zaleplon.
Multiple-dose administration of the potent CYP3A4 inducer rifampin (600 mg every 24 hours, q24h, for 14 days), however, reduced zaleplon C max and AUC by approximately 80%. The coadministration of a potent CYP3A4 enzyme inducer, although not posing a safety concern, thus could lead to ineffectiveness of zaleplon. An alternative non-CYP3A4 substrate hypnotic agent may be considered in patients taking CYP3A4 inducers such as rifampin, phenytoin, carbamazepine, and phenobarbital.
Drugs That Inhibit CYP3A4 CYP3A4 is a minor metabolic pathway for the elimination of zaleplon because the sum of desethylzaleplon (formed via CYP3A4 in vitro) and its metabolites, 5-oxo-desethylzaleplon and 5-oxo-desethylzaleplon glucuronide, account for only 9% of the urinary recovery of a zaleplon dose. Coadministration of single, oral doses of zaleplon with erythromycin (10 mg and 800 mg respectively), a strong, selective CYP3A4 inhibitor, produced a 34% increase in zaleplon's maximal plasma concentrations and a 20% increase in the area under the plasma concentration-time curve.
The magnitude of interaction with multiple doses of erythromycin is unknown. Other strong selective CYP3A4 inhibitors such as ketoconazole can also be expected to increase the exposure of zaleplon. A routine dosage adjustment of zaleplon is not considered necessary.
Drugs That Inhibit Aldehyde Oxidase The aldehyde oxidase enzyme system is less well studied than the cytochrome P450 enzyme system. Diphenhydramine: Diphenhydramine is reported to be a weak inhibitor of aldehyde oxidase in rat liver, but its inhibitory effects in human liver are not kno…
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of zaleplon in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use A total of 628 patients in double-blind, placebo-controlled, parallel-group clinical trials who received zaleplon were at least 65 years of age; of these, 311 received 5 mg and 317 received 10 mg. In both sleep laboratory and outpatient studies, elderly patients with insomnia responded to a 5 mg dose with a reduced sleep latency, and thus 5 mg is the recommended dose in this population. During short-term treatment (14 night studies) of elderly patients with zaleplon, no adverse event with a frequency of at least 1% occurred at a significantly higher rate with either 5 mg or 10 mg zaleplon than with placebo.
🆘 Overdosage ▾
OVERDOSAGE Signs and Symptoms Signs and symptoms of overdose effects of CNS depressants can be expected to present as exaggerations of the pharmacological effects noted in preclinical testing. Overdose is usually manifested by degrees of central nervous system depression ranging from drowsiness to coma. In mild cases, symptoms include drowsiness, mental confusion, and lethargy; in more serious cases, symptoms may include ataxia, hypotonia, hypotension, respiratory depression, rarely coma, and very rarely death.
Loss of consciousness, in addition to signs and symptoms consistent with CNS depressants as described above, have been reported following zaleplon overdose. Individuals have fully recovered from zaleplon overdoses of greater than 200 mg (10 times the maximum recommended dose of zaleplon). Rare instances of fatal outcomes following overdose with zaleplon, most often associated with overdose of additional CNS depressants, have been reported.
Recommended Treatment General symptomatic and supportive measures should be used along with immediate gastric lavage where appropriate. Intravenous fluids should be administered as needed. Animal studies suggest that flumazenil is an antagonist to zaleplon.
However, there is no pre-marketing clinical experience with the use of flumazenil as an antidote to a zaleplon overdose. As in all cases of drug overdose, respiration, pulse, blood pressure, and other appropriate signs should be monitored and general supportive measures employed. Hypotension and CNS depression should be monitored and treated by appropriate medical intervention.
Poison Control Center As with the management of all overdosage, the possibility of multiple drug ingestion should be considered. The physician may wish to consider contacting a poison control center for up-to-date information on the management of hypnotic drug product overdosage.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacodynamics and Mechanism of Action While zaleplon is a hypnotic agent with a chemical structure unrelated to benzodiazepines, barbiturates, or other drugs with known hypnotic properties, it interacts with the gamma-aminobutyric acid-benzodiazepine (GABA-BZ) receptor complex. Subunit modulation of the GABA-BZ receptor chloride channel macromolecular complex is hypothesized to be responsible for some of the pharmacological properties of benzodiazepines, which include sedative, anxiolytic, muscle relaxant, and anticonvulsive effects in animal models.
Other nonclinical studies have also shown that zaleplon binds selectively to the brain omega-1 receptor situated on the alpha subunit of the GABA A /chloride ion channel receptor complex and potentiates t-butyl-bicyclophosphorothionate (TBPS) binding. Studies of binding of zaleplon to recombinant GABA A receptors ( α 1 β 1 γ 2 [omega-1] and α 2 β 1 γ 2 [omega-2]) have shown that zaleplon has a low affinity for these receptors, with preferential binding to the omega-1 receptor. Pharmacokinetics The pharmacokinetics of zaleplon have been investigated in more than 500 healthy subjects (young and elderly), nursing mothers, and patients with hepatic disease or renal disease.
In healthy subjects, the pharmacokinetic profile has been examined after single doses of up to 60 mg and once-daily administration at 15 mg and 30 mg for 10 days. Zaleplon was rapidly absorbed with a time to peak concentration (t max ) of approximately 1 hour and a terminal-phase elimination half-life (t 1/2 ) of approximately 1 hour. Zaleplon does not accumulate with once-daily administration and its pharmacokinetics are dose proportional in the therapeutic range.
Absorption Zaleplon is rapidly and almost completely absorbed following oral administration. Peak plasma concentrations are attained within approximately 1 hour after oral administration. Although zaleplon is well absorbed, its absolute bioavailability is approximately 30% because it undergoes significant presystemic metabolism.
Distribution Zaleplon is a lipophilic compound with a volume of distribution of approximately
1.4L/kg following intravenous (IV) administration, indicating substantial distribution into extravascular tissues. The in vitro plasma protein binding is approximately 60%±15% and is independent of zaleplon concentration over the range of 10 ng/mL to 1000 ng/mL. This suggests that zaleplon disposition should not be sensitive to alterations in protein binding.
The blood to plasma ratio for zaleplon is approximately 1, indicating that zaleplon is uniformly distributed throughout the blood with no extensive distribution into red blood cells. Metabolism After oral administration, zaleplon is extensively metabolized, with less than 1% of the dose excreted unchanged in urine. Zaleplon is primarily metabolized by aldehyde oxidase to form 5-oxo-zaleplon.
Zaleplon is metabolized to a lesser extent by cytochrome P450 (CYP) 3A4 to form desethylzaleplon, which is quickly converted, presumably by aldehyde oxidase, to 5-oxo-desethylzaleplon. These oxidative metabolites are then converted to glucuronides and eliminated in urine. All of zaleplon's metabolites are pharmacologically inactive.
Elimination After either oral or IV administration, zaleplon is rapidly eliminated with a mean t 1/2 of approximately 1 hour. The oral-dose plasma clearance of zaleplon is about 3 L/h/kg and the IV zaleplon plasma clearance is approximately 1 L/h/kg. Assuming normal hepatic blood flow and negligible renal clearance of zaleplon, the estimated hepatic extraction ratio of zaleplon is approximately 0.7, indicating that zaleplon is subject to high first-pass metabolism.
After administration of a radiolabeled dose of zaleplon, 70% of the administered dose is recovered in urine within 48 hours (71% recovered within 6 days), almost all as zaleplon metabolites and their glucuronides. An additional 17% is recovered in feces within 6 days, most as 5-ox…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Zaleplon capsules USP 5 mg are available as hard gelatin capsules with light blue cap and light blue body imprinted with "U" on cap and "131" on the body in black ink along the horizontal axis. NDC: 71335-0236-1: 30 Capsules in a BOTTLE NDC: 71335-0236-2: 60 Capsules in a BOTTLE NDC: 71335-0236-3: 90 Capsules in a BOTTLE NDC: 71335-0236-4: 20 Capsules in a BOTTLE NDC: 71335-0236-5: 28 Capsules in a BOTTLE Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📦 Storage and Handling ▾
STORAGE CONDITIONS Store at controlled room temperature, 20°C to 25°C (68°F to 77°F) [see USP]. Dispense in a light-resistant container as defined in the USP. Additional Medication Guide's can be obtained by calling Unichem at 1-866- 562-4616. 06-R-10/2020
📋 Description ▾
DESCRIPTION Zaleplon is a nonbenzodiazepine hypnotic from the pyrazolopyrimidine class. The chemical name of zaleplon is N-[3-(3-cyanopyrazolo[1,5-a]pyrimidin-7-yl)phenyl]-N-ethylacetamide. Its molecular formula is C 17 H 15 N 5 O, and its molecular weight is 305.34.
The structural formula is shown below. Zaleplon Zaleplon is a white to off-white powder that is practically insoluble in water and sparingly soluble in alcohol or propylene glycol. Its partition coefficient in octanol/water is constant (log PC = 1.23) over the pH range of 1 to 7.
Zaleplon capsules USP contain zaleplon as the active ingredient. Inactive ingredients consist of microcrystalline cellulose, pregelatinized starch, colloidal silicon dioxide, sodium lauryl sulfate, magnesium stearate, lactose, gelatin, titanium dioxide, FD&C blue #1, FD&C red #40 and black iron oxide. The 5 mg capsules also contain FD&C yellow #5.
Meets USP Dissolution Test 2.
💬 Information for Patients ▾
Information for Patients A patient Medication Guide is also available for zaleplon. The prescriber or health professional should instruct patients, their families, and their caregivers to read the Medication Guide and should assist them in understanding its contents. Patients should be given the opportunity to discuss the contents of the Medication Guide and to obtain answers to any questions that they may have.
Instruct patients and their families that zaleplon may cause complex sleep behaviors, including sleep-walking, sleep-driving, preparing and eating food, making phone calls, or having sex while not being fully awake. Serious injuries and death have occurred during complex sleep behavior episodes. Tell patients to discontinue zaleplon and notify their healthcare provider immediately if they develop any of these symptoms (see BOXED WARNING and WARNINGS ).
Advise patients that increased drowsiness and decreased consciousness may increase the risk of falls in some patients (see WARNINGS ).
💬 Medication Guide ▾
MEDICATION GUIDE Zaleplon Capsules USP C-IV (zal' e plon) Read this Medication Guide before you start taking zaleplon capsules and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking to your doctor about your medical condition or treatment.
You and your doctor should talk about zaleplon capsules when you start taking it and at regular checkups. What is the most important information I should know about zaleplon capsules? Zaleplon capsules may cause serious side effects including complex sleep behaviors that may cause serious injury and death..
After taking zaleplon capsules, you may get up out of bed while not being fully awake and do an activity that you do not know you are doing (complex sleep behaviors). The next morning, you may not remember that you did anything during the night. These activities may occur with zaleplon capsules whether or not you drink alcohol or take other medicines that make you sleepy.
Reported activities include: driving a car ("sleep-driving") making and eating food talking on the phone having sex sleep-walking Important: 1. Take zaleplon capsules exactly as prescribed Do not take more zaleplon capsules than prescribed. Take zaleplon capsules right before you get in bed, not sooner.
2. Do not take zaleplon capsules if you: have ever experienced a complex sleep behavior (such as driving a car, making and eating food, talking on the phone or having sex while not fully awake) after taking zaleplon capsules drink alcohol take other medicines that can make you sleepy. Talk to your doctor about all of your medicines.
Your doctor will tell you if you can take zaleplon capsules with your other medicines cannot get a full night's sleep 3. Stop taking zaleplon capsules and call your doctor right away if you find out that you have done any of the above activities after taking zaleplon capsules. What are zaleplon capsules?
Zaleplon capsules are a sedative-hypnotic (sleep) medicine. Zaleplon capsules are used in adults for the short-term treatment of the symptom of trouble falling asleep from insomnia. Zaleplon does not treat other symptoms of insomnia which include waking up too early in the morning and waking up often during the night.
Zaleplon capsules are not for children.