
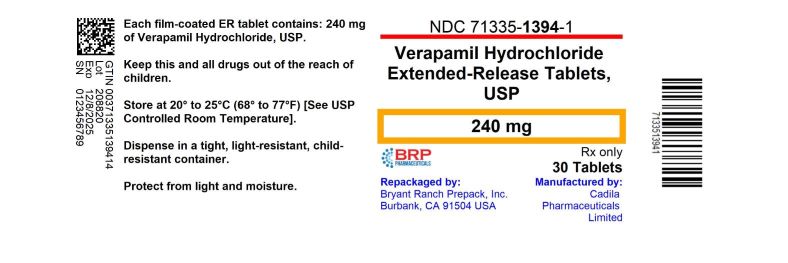
VERAPAMIL HYDROCHLORIDE 240 mg Tablet, 90-count
Other active recalls for Verapamil Hydrochloride (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcium Channel Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Verapamil is used to treat high blood pressure and to control angina (chest pain). The immediate-release tablets are also used alone or with other medications to prevent and treat irregular heartbeats. Verapamil is in a class of medications called calcium-channel blockers. It works by relaxing the blood vessels so the heart does not have to pump as hard. It also increases the supply of blood and oxygen to the heart and slows electrical activity in the heart to control the heart rate. High blood pressure is a common condition and when not treated, can cause damage to the brain, heart, blood ves...
Read the full MedlinePlus article ↗- That depends on why your doctor prescribed it. Verapamil can treat three main problems: high blood pressure, angina (chest pain from the heart not getting enough blood), and certai...
- What exactly is verapamil treating in my body?
- Yes, and it depends on your specific formulation. If you have the extended-release tablets, take them in the morning with food. If you have the extended-release PM capsules, take t...
- Does it matter when I take verapamil or whether I take it with food?
Patient education
Supplement & herbal interactions
Verapamil may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3453 | $31.08 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Verapamil hydrochloride 240 mg 68382-0563-01 | Zydus | 100 tablets | $0.165 | AB | Availability likely | — |
| verapamil hydrochloride 240 mg 68462-0260-01 | Glenmark | 100 tablets | $0.165 | AB | Availability likely | — |
| Verapamil Hydrochloride 240 mg 50090-4582-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| verapamil hydrochloride 240 mg 51655-0956-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Verapamil Hydrochloride 240 mg 51655-0984-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| verapamil hydrochloride 240 mg 55289-0723-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| verapamil hydrochloride 240 mg 66267-0212-30 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Verapamil Hydrochloride 240 mg 68071-3435-00 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Verapamil Hydrochloride 240 mg 68788-9790-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| verapamil hydrochloride 240 mg 70518-1326-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Verapamil hydrochloride 240 mg 70771-1955-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| verapamil hydrochloride 240 mg 71205-0017-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Verapamil Hydrochloride 240 mg 71209-0048-05 | Cadila | 100 tablets | — | AB | FDA listed | — |
| Verapamil Hydrochloride 240 mgthis 71335-1394-02 | Bryant | 90 tablets | — | AB | Discontinued | — |
| verapamil hydrochloride 240 mg 71610-0268-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1394-01 | 30 TABLET in 1 BOTTLE (71335-1394-1) | 2022-02-09 | Discontinued by firm |
| 71335-1394-02 You're viewing this | 90 TABLET in 1 BOTTLE (71335-1394-2) | 2022-02-09 | Discontinued by firm |
| 71335-1394-03 | 60 TABLET in 1 BOTTLE (71335-1394-3) | 2022-02-09 | Discontinued by firm |
| 71335-1394-04 | 10 TABLET in 1 BOTTLE (71335-1394-4) | 2022-02-09 | Active |
| 71335-1394-05 | 100 TABLET in 1 BOTTLE (71335-1394-5) | 2022-02-09 | Active |
You're viewing one of 5 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1394-02?
What is the difference between NDC 71335-1394-02 and NDC 71335-1394-04?
What NDC number is used to bill for this package of VERAPAMIL HYDROCHLORIDE 240 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Verapamil hydrochloride extended-release tablets is indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including this drug.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Essential hypertension The dose of verapamil hydrochloride extended-release tablets should be individualized by titration and the drug should be administered with food. Initiate therapy with 180 mg of sustained-release verapamil HCl, verapamil hydrochloride extended-release tablets, given in the morning. Lower initial doses of 120 mg a day may be warranted in patients who may have an increased response to verapamil (eg, the elderly or small people).
Upward titration should be based on therapeutic efficacy and safety evaluated weekly and approximately 24 hours after the previous dose. The antihypertensive effects of verapamil hydrochloride extended-release tablets are evident within the first week of therapy. If adequate response is not obtained with 180 mg of verapamil hydrochloride extended-release tablets, the dose may be titrated upward in the following manner: a) 240 mg each morning, b) 180 mg each morning plus 180 mg each evening; or 240 mg each morning plus 120 mg each evening, c) 240 mg every 12 hours.
When switching from immediate-release verapamil hydrochloride tablets to verapamil hydrochloride extended-release tablets, the total daily dose in milligrams may remain the same.
⛔ Contraindications ▾
CONTRAINDICATIONS Verapamil HCl tablets are contraindicated in: Severe left ventricular dysfunction (see WARNINGS ) Hypotension (systolic pressure less than 90 mm Hg) or cardiogenic shock Sick sinus syndrome (except in patients with a functioning artificial ventricular pacemaker) Second- or third-degree AV block (except in patients with a functioning artificial ventricular pacemaker) Patients with atrial flutter or atrial fibrillation and an accessory bypass tract (eg, Wolff-Parkinson-White, Lown-Ganong-Levine syndromes) (see WARNINGS ) Patients with known hypersensitivity to verapamil hydrochloride
⚠️ Warnings ▾
WARNINGS Heart failure Verapamil has a negative inotropic effect, which in most patients is compensated by its afterload reduction (decreased systemic vascular resistance) properties without a net impairment of ventricular performance. In clinical experience with 4,954 patients, 87 (1.8%) developed congestive heart failure or pulmonary edema. Verapamil should be avoided in patients with severe left ventricular dysfunction (eg, ejection fraction less than 30%) or moderate to severe symptoms of cardiac failure and in patients with any degree of ventricular dysfunction if they are receiving a beta-adrenergic blocker (see PRECAUTIONS, Drug interactions ).
Patients with milder ventricular dysfunction should, if possible, be controlled with optimum doses of digitalis and/or diuretics before verapamil treatment. (Note interactions with digoxin under PRECAUTIONS) Hypotension Occasionally, the pharmacologic action of verapamil may produce a decrease in blood pressure below normal levels, which may result in dizziness or symptomatic hypotension. The incidence of hypotension observed in 4,954 patients enrolled in clinical trials was 2.5%.
In hypertensive patients, decreases in blood pressure below normal are unusual. Tilt-table testing (60 degrees) was not able to induce orthostatic hypotension. Elevated liver enzymes Elevations of transaminases with and without concomitant elevations in alkaline phosphatase and bilirubin have been reported.
Such elevations have sometimes been transient and may disappear even in the face of continued verapamil treatment. Several cases of hepatocellular injury related to verapamil have been proven by rechallenge; half of these had clinical symptoms (malaise, fever, and/or right upper quadrant pain) in addition to elevation of SGOT, SGPT, and alkaline phosphatase. Periodic monitoring of liver function in patients receiving verapamil is therefore prudent.
Accessory bypass tract (Wolff-Parkinson-White or Lown-Ganong-Levine) Some patients with paroxysmal and/or chronic atrial fibrillation or atrial flutter and a coexisting accessory AV pathway have developed increased antegrade conduction across the accessory pathway bypassing the AV node, producing a very rapid ventricular response or ventricular fibrillation after receiving intravenous verapamil (or digitalis). Although a risk of this occurring with oral verapamil has not been established, such patients receiving oral verapamil may be at risk and its use in these patients is contraindicated (see CONTRAINDICATIONS ).
Treatment is usually DC-cardioversion. Cardioversion has been used safely and effectively after oral verapamil hydrochloride tablets. Atrioventricular block The effect of verapamil on AV conduction and the SA node may cause asymptomatic first-degree AV block and transient bradycardia, sometimes accompanied by nodal escape rhythms.
PR-interval prolongation is correlated with verapamil plasma concentrations, especially during the early titration phase of therapy. Higher degrees of AV block, however, were infrequently (0.8%) observed. Marked first-degree block or progressive development to second- or third-degree AV block, requires a reduction in dosage or, in rare instances, discontinuation of verapamil HCl and institution of appropriate therapy, depending upon the clinical situation.
Patients with hypertrophic cardiomyopathy (IHSS) In 120 patients with hypertrophic cardiomyopathy (most of them refractory or intolerant to propranolol) who received therapy with verapamil at doses up to 720 mg/day, a variety of serious adverse effects were seen. Three patients died in pulmonary edema; all had severe left ventricular outflow obstruction and a past history of left ventricular dysfunction. Eight other patients had pulmonary edema and/or severe hypotension; abnormally high (greater than 20 mm Hg) pulmonary wedge pressure and a marked left ventricular outflow obstruction were present in most of these patients.
Concomitant administration of quinidine (see…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Serious adverse reactions are uncommon when verapamil therapy is initiated with upward dose titration within the recommended single and total daily dose. See WARNINGS for discussion of heart failure, hypotension, elevated liver enzymes, AV block, and rapid ventricular response. Reversible (upon discontinuation of verapamil) non-obstructive, paralytic ileus has been infrequently reported in association with the use of verapamil.
The following reactions to orally administered verapamil occurred at rates greater than 1.0% or occurred at lower rates but appeared clearly drug-related in clinical trials in 4,954 patients: Constipation 7.3% Dyspnea 1.4% Dizziness 3.3% Bradycardia Nausea 2.7% (HR <50/min) 1.4% Hypotension 2.5% AV block Headache 2.2% (total 1°, 2°, 3°) 1.2% Edema 1.9% (2° and 3°) 0.8% CHF, Pulmonary edema 1.8% Rash 1.2% Fatigue 1.7% Flushing 0.6% Elevated liver enzymes (see WARNINGS ) In clinical trials related to the control of ventricular response in digitalized patients who had atrial fibrillation or flutter, ventricular rates below 50/min at rest occurred in 15% of patients and asymptomatic hypotension occurred in 5% of patients.
The following reactions, reported in 1% or less of patients, occurred under conditions (open trials, marketing experience) where a causal relationship is uncertain; they are listed to alert the physician to a possible relationship: Cardiovascular: angina pectoris, atrioventricular dissociation, chest pain, claudication, myocardial infarction, palpitations, purpura (vasculitis), syncope. Digestive system: diarrhea, dry mouth, gastrointestinal distress, gingival hyperplasia. Hemic and lymphatic: ecchymosis or bruising.
Nervous system: cerebrovascular accident, confusion, equilibrium disorders, insomnia, muscle cramps, paresthesia, psychotic symptoms, shakiness, somnolence. Skin: arthralgia and rash, exanthema, hair loss, hyperkeratosis, macules, sweating, urticaria, Stevens-Johnson syndrome, erythema multiforme. Special senses: blurred vision, tinnitus.
Urogenital: gynecomastia, galactorrhea/hyperprolactinemia, increased urination, spotty menstruation, impotence. Treatment of acute cardiovascular adverse reactions The frequency of cardiovascular adverse reactions that require therapy is rare; hence, experience with their treatment is limited. Whenever severe hypotension or complete AV block occurs following oral administration of verapamil, the appropriate emergency measures should be applied immediately; eg, intravenously administered norepinephrine bitartrate, atropine sulfate, isoproterenol HCl (all in the usual doses), or calcium gluconate (10% solution).
In patients with hypertrophic cardiomyopathy (IHSS), alpha-adrenergic agents (phenylephrine HCl, metaraminol bitartrate, or methoxamine HCl) should be used to maintain blood pressure, and isoproterenol and norepinephrine should be avoided. If further support is necessary, dopamine HCl or dobutamine HCl may be administered. Actual treatment and dosage should depend on the severity of the clinical situation and the judgment and experience of the treating physician.
🔄 Drug Interactions ▾
Drug interactions Cytochrome inducers/inhibitors In vitro metabolic studies indicate that verapamil is metabolized by cytochrome P450 CYP3A4, CYP1A2, CYP2C8, CYP2C9, and CYP2C18. Clinically significant interactions have been reported with inhibitors of CYP3A4 (e.g., erythromycin, ritonavir) causing elevation of plasma levels of verapamil while inducers of CYP3A4 (e.g., rifampin) have caused a lowering of plasma levels of verapamil. HMG-CoA reductase inhibitors The use of HMG-CoA reductase inhibitors that are CYP3A4 substrates in combination with verapamil has been associated with reports of myopathy/rhabdomyolysis.
Co-administration of multiple doses of 10 mg of verapamil with 80 mg simvastatin resulted in exposure to simvastatin 2.5-fold that following simvastatin alone. Limit the dose of simvastatin in patients on verapamil to 10 mg daily. Limit the daily dose of lovastatin to 40 mg.
Lower starting and maintenance doses of other CYP3A4 substrates (e.g., atorvastatin) may be required as verapamil may increase the plasma concentration of these drugs. Ivabradine Concurrent use of verapamil increases exposure to ivabradine and may exacerbate bradycardia and conduction disturbances. Avoid co-administration of verapamil and ivabradine.
Beta-blockers Concomitant therapy with beta-adrenergic blockers and verapamil may result in additive negative effects on heart rate, atrioventricular conduction and/or cardiac contractility. The combination of sustained-release verapamil and beta-adrenergic blocking agents has not been studied. However, there have been reports of excessive bradycardia and AV block, including complete heart block, when the combination has been used for the treatment of hypertension.
For hypertensive patients, the risks of combined therapy may outweigh the potential benefits. The combination should be used only with caution and close monitoring. Asymptomatic bradycardia (36 beats/min) with a wandering atrial pacemaker has been observed in a patient receiving concomitant timolol (a beta-adrenergic blocker) eyedrops and oral verapamil.
A decrease in metoprolol and propranolol clearance has been observed when either drug is administered concomitantly with verapamil. A variable effect has been seen when verapamil and atenolol were given together. Digitalis Clinical use of verapamil in digitalized patients has shown the combination to be well tolerated if digoxin doses are properly adjusted.
However, chronic verapamil treatment can increase serum digoxin levels by 50% to 75% during the first week of therapy, and this can result in digitalis toxicity. In patients with hepatic cirrhosis the influence of verapamil on digoxin kinetics is magnified. Verapamil may reduce total body clearance and extrarenal clearance of digitoxin by 27% and 29%, respectively.
Maintenance and digitalization doses should be reduced when verapamil is administered, and the patient should be carefully monitored to avoid over- or under- digitalization. Whenever over-digitalization is suspected, the daily dose of digitalis should be reduced or temporarily discontinued. On discontinuation of verapamil hydrochloride tablets use, the patient should be reassessed to avoid under-digitalization.
Antihypertensive agents Verapamil administered concomitantly with oral antihypertensive agents (eg, vasodilators, angiotensin-converting enzyme inhibitors, diuretics, beta-blockers) will usually have an additive effect on lowering blood pressure. Patients receiving these combinations should be appropriately monitored. Concomitant use of agents that attenuate alpha-adrenergic function with verapamil may result in a reduction in blood pressure that is excessive in some patients.
Such an effect was observed in one study following the concomitant administration of verapamil and prazosin. Antiarrhythmic agents Disopyramide Until data on possible interactions between verapamil and disopyramide phosphate are obtained, disopyramide should not be administered within 48 hours b…
🤰 Pregnancy ▾
Pregnancy Reproduction studies have been performed in rabbits and rats at oral doses up to 1.5 (15 mg/kg/day) and 6 (60 mg/kg/day) times the human oral daily dose, respectively, and have revealed no evidence of teratogenicity. In the rat, however, this multiple of the human dose was embryocidal and retarded fetal growth and development, probably because of adverse maternal effects reflected in reduced weight gains of the dams. This oral dose has also been shown to cause hypotension in rats.
There are no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Verapamil crosses the placental barrier and can be detected in umbilical vein blood at delivery.
🧒 Pediatric Use ▾
Pediatric use Safety and efficacy of verapamil hydrochloride extended-release tablets in pediatric patients below the age of 18 years have not been established.
🆘 Overdosage ▾
OVERDOSAGE Overdose with verapamil may lead to pronounced hypotension, bradycardia, and conduction system abnormalities (eg, junctional rhythm with AV dissociation and high degree AV block, including asystole). Other symptoms secondary to hypoperfusion (eg, metabolic acidosis, hyperglycemia, hyperkalemia, renal dysfunction, and convulsions) may be evident. Treat all verapamil overdoses as serious and maintain observation for at least 48 hours (especially verapamil hydrochloride extended-release tablets), preferably under continuous hospital care.
Delayed pharmacodynamic consequences may occur with the sustained-release formulation. Verapamil is known to decrease gastrointestinal transit time. In overdose, verapamil hydrochloride extended-release tablets have occasionally been reported to form concretions within the stomach or intestines.
These concretions have not been visible on plain radiographs of the abdomen, and no medical means of gastrointestinal emptying is of proven efficacy in removing them. Endoscopy might reasonably be considered in cases of massive overdose when symptoms are unusually prolonged. Treatment of overdosage should be supportive.
Beta-adrenergic stimulation or parenteral administration of calcium solutions may increase calcium ion flux across the slow channel and have been used effectively in treatment of deliberate overdosage with verapamil. Continued treatment with large doses of calcium may produce a response. In a few reported cases, overdose with calcium channel blockers that was initially refractory to atropine became more responsive to this treatment when the patients received large doses (close to 1 g/hr for more than 24 hr) of calcium chloride.
Verapamil cannot be removed by hemodialysis. Clinically significant hypotensive reactions or high degree AV block should be treated with vasopressor agents or cardiac pacing, respectively. Asystole should be handled by the usual measures including cardiopulmonary resuscitation.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Verapamil HCl is a calcium ion influx inhibitor (slow-channel blocker or calcium ion antagonist) that exerts its pharmacologic effects by modulating the influx of ionic calcium across the cell membrane of the arterial smooth muscle as well as in conductile and contractile myocardial cells. Mechanism of action Essential hypertension Verapamil exerts antihypertensive effects by decreasing systemic vascular resistance, usually without orthostatic decreases in blood pressure or reflex tachycardia; bradycardia (rate less than 50 beats/min) is uncommon (1.4%).
During isometric or dynamic exercise, verapamil hydrochloride does not alter systolic cardiac function in patients with normal ventricular function. Verapamil hydrochloride does not alter total serum calcium levels. However, one report suggested that calcium levels above the normal range may alter the therapeutic effect of verapamil hydrochloride.
Other pharmacologic actions of verapamil hydrochloride include the following Verapamil hydrochloride dilates the main coronary arteries and coronary arterioles, both in normal and ischemic regions, and is a potent inhibitor of coronary artery spasm, whether spontaneous or ergonovine-induced. This property increases myocardial oxygen delivery in patients with coronary artery spasm and is responsible for the effectiveness of verapamil hydrochloride in vasospastic (Prinzmetal's or variant) as well as unstable angina at rest.
Whether this effect plays any role in classical effort angina is not clear, but studies of exercise tolerance have not shown an increase in the maximum exercise rate–pressure product, a widely accepted measure of oxygen utilization. This suggests that, in general, relief of spasm or dilation of coronary arteries is not an important factor in classical angina. Verapamil hydrochloride regularly reduces the total systemic resistance (afterload) against which the heart works both at rest and at a given level of exercise by dilating peripheral arterioles.
Electrical activity through the AV node depends, to a significant degree, upon calcium influx through the slow channel. By decreasing the influx of calcium, verapamil hydrochloride prolongs the effective refractory period within the AV node and slows AV conduction in a rate-related manner. Normal sinus rhythm is usually not affected, but in patients with sick sinus syndrome, verapamil hydrochloride may interfere with sinus-node impulse generation and may induce sinus arrest or sinoatrial block.
Atrioventricular block can occur in patients without preexisting conduction defects (see WARNINGS ). Verapamil hydrochloride does not alter the normal atrial action potential or intraventricular conduction time, but depresses amplitude, velocity of depolarization, and conduction in depressed atrial fibers. Verapamil hydrochloride may shorten the antegrade effective refractory period of the accessory bypass tract.
Acceleration of ventricular rate and/or ventricular fibrillation has been reported in patients with atrial flutter or atrial fibrillation and a coexisting accessory AV pathway following administration of verapamil (see WARNINGS ). Verapamil hydrochloride has a local anesthetic action that is 1.6 times that of procaine on an equimolar basis. It is not known whether this action is important at the doses used in man.
Pharmacokinetics and metabolism With the immediate-release formulation, more than 90% of the orally administered dose of verapamil hydrochloride is absorbed. Because of rapid biotransformation of verapamil during its first pass through the portal circulation, bioavailability ranges from 20% to 35%. Peak plasma concentrations are reached between 1 and 2 hours after oral administration.
Chronic oral administration of 120 mg of verapamil HCl every 6 hours resulted in plasma levels of verapamil ranging from 125 to 400 ng/mL, with higher values reported occasionally. A nonlinear correlation between the verapamil dose administered and verapamil…
🧬 Mechanism of Action ▾
Mechanism of action Essential hypertension Verapamil exerts antihypertensive effects by decreasing systemic vascular resistance, usually without orthostatic decreases in blood pressure or reflex tachycardia; bradycardia (rate less than 50 beats/min) is uncommon (1.4%). During isometric or dynamic exercise, verapamil hydrochloride does not alter systolic cardiac function in patients with normal ventricular function. Verapamil hydrochloride does not alter total serum calcium levels.
However, one report suggested that calcium levels above the normal range may alter the therapeutic effect of verapamil hydrochloride. Other pharmacologic actions of verapamil hydrochloride include the following Verapamil hydrochloride dilates the main coronary arteries and coronary arterioles, both in normal and ischemic regions, and is a potent inhibitor of coronary artery spasm, whether spontaneous or ergonovine-induced. This property increases myocardial oxygen delivery in patients with coronary artery spasm and is responsible for the effectiveness of verapamil hydrochloride in vasospastic (Prinzmetal's or variant) as well as unstable angina at rest.
Whether this effect plays any role in classical effort angina is not clear, but studies of exercise tolerance have not shown an increase in the maximum exercise rate–pressure product, a widely accepted measure of oxygen utilization. This suggests that, in general, relief of spasm or dilation of coronary arteries is not an important factor in classical angina. Verapamil hydrochloride regularly reduces the total systemic resistance (afterload) against which the heart works both at rest and at a given level of exercise by dilating peripheral arterioles.
Electrical activity through the AV node depends, to a significant degree, upon calcium influx through the slow channel. By decreasing the influx of calcium, verapamil hydrochloride prolongs the effective refractory period within the AV node and slows AV conduction in a rate-related manner. Normal sinus rhythm is usually not affected, but in patients with sick sinus syndrome, verapamil hydrochloride may interfere with sinus-node impulse generation and may induce sinus arrest or sinoatrial block.
Atrioventricular block can occur in patients without preexisting conduction defects (see WARNINGS ). Verapamil hydrochloride does not alter the normal atrial action potential or intraventricular conduction time, but depresses amplitude, velocity of depolarization, and conduction in depressed atrial fibers. Verapamil hydrochloride may shorten the antegrade effective refractory period of the accessory bypass tract.
Acceleration of ventricular rate and/or ventricular fibrillation has been reported in patients with atrial flutter or atrial fibrillation and a coexisting accessory AV pathway following administration of verapamil (see WARNINGS ). Verapamil hydrochloride has a local anesthetic action that is 1.6 times that of procaine on an equimolar basis. It is not known whether this action is important at the doses used in man.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Verapamil hydrochloride extended-release tablets, USP 240 mg are supplied as light blue, capsule shaped, bevelled edged, scored, film coated tablets debossed with C 77 on one side and plain on other side. NDC: 71335-1394-1: 30 Tablets in a BOTTLE NDC: 71335-1394-2: 90 Tablets in a BOTTLE NDC: 71335-1394-3: 60 Tablets in a BOTTLE NDC: 71335-1394-4: 10 Tablets in a BOTTLE NDC: 71335-1394-5: 100 Tablets in a BOTTLE Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature] and protect from light and moisture.
Dispense in tight, light-resistant containers. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504 NDC: 71335-1394-1: 30 Tablets in a BOTTLE NDC: 71335-1394-2: 90 Tablets in a BOTTLE NDC: 71335-1394-3: 60 Tablets in a BOTTLE NDC: 71335-1394-4: 10 Tablets in a BOTTLE
📋 Description ▾
DESCRIPTION Verapamil hydrochloride extended-release tablets, USP is a calcium ion influx inhibitor (slow-channel blocker or calcium ion antagonist). Verapamil hydrochloride extended-release tablets, USP is available for oral administration as light blue, oval shaped, scored, film coated tablets containing 240 mg of verapamil hydrochloride USP; as light blue, capsule shaped, bevelled edged, scored, film coated tablets containing 180 mg of verapamil hydrochloride USP. The tablets are designed for sustained release of the drug in the gastrointestinal tract; sustained-release characteristics are not altered when the tablet is divided in half.
The structural formula of verapamil HCl USP is: C 27 H 38 N 2 O 4 ∙ HCl M.W.=491.08 Benzeneacetonitrile, α-[3-[[2-(3,4-dimethoxyphenyl)ethyl]methylamino] propyl]-3,4-dimethoxy-α-(1-methylethyl) hydrochloride Verapamil HCl, USP is an almost white, crystalline powder, practically free of odor, with a bitter taste. It is soluble in water, chloroform, and methanol. Verapamil HCl, USP is not chemically related to other cardioactive drugs.
Inactive ingredients include colloidal silicon dioxide, hypromellose, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polyvinylpyrrolidone, sodium alginate, and film coating contains FD&C Blue No. 1 Brilliant Blue FCF aluminum lake, hypromellose, iron oxide yellow, titanium dioxide and triacetin. Verapamil hydrochloride extended-release tablets USP, 180 mg and 240 mg meet USP Dissolution Test 3.