
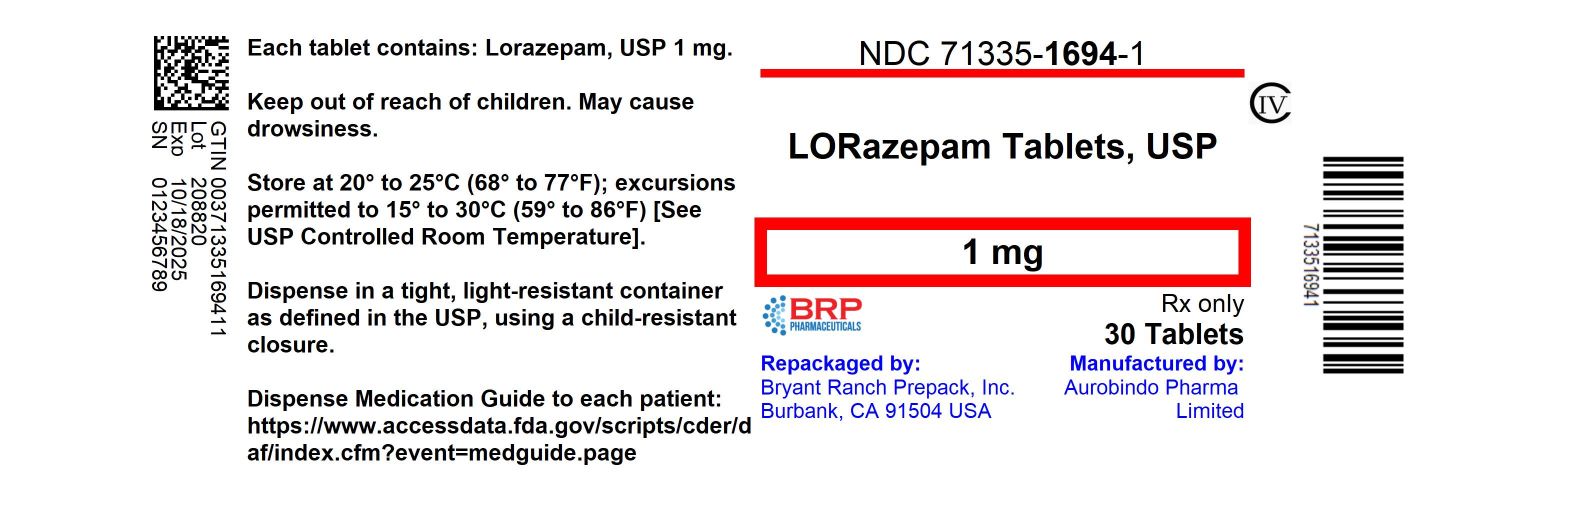
Lorazepam 1 mg Tablet, 50-count
Other active recalls for Lorazepam (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Lorazepam is mainly prescribed for anxiety disorders — it can calm anxious feelings and physical tension, especially for short periods. In tablet or liquid form, it's used for ongo...
- Yes, drowsiness is one of the most common effects — and for many people that's actually part of how it helps with anxiety. You may also notice some unsteadiness, dizziness, or mild...
- Will lorazepam make me feel really drowsy?
- No — please avoid alcohol completely while you're on lorazepam. Both alcohol and lorazepam slow down your central nervous system, and together they can make that effect dangerously...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lorazepam — tap one for details:
Lorazepam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1178 | $5.89 / 50 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lorazepam 1 mg 00093-3426-01 | Teva | 100 tablets | $0.036 | AB | Availability likely | — |
| Lorazepam 1 mg 00904-6008-60 | Major | 100 tablets | $0.036 | AB | Discontinued | — |
| Lorazepam 1 mg 13107-0084-01 | Aurolife | 100 tablets | $0.036 | AB | Availability likely | — |
| Lorazepam 1 mg 60687-0831-01 | American | 100 tablets | $0.036 | AB | Availability likely | — |
| Lorazepam 1 mg 63304-0773-01 | SUN | 100 tablets | $0.036 | AB | Availability likely | — |
| Lorazepam 1 mg 64980-0628-01 | Rising | 100 tablets | $0.036 | AB | Availability likely | — |
| Lorazepam 1 mg 69315-0905-01 | Leading | 100 tablets | $0.036 | AB | Availability likely | — |
| Ativan 1 mg 00187-0064-01 | Bausch | 100 tablets | $44.095 | AB | FDA listed | — |
| Lorazepam 1 mg 50090-5508-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 50090-5509-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 50090-5562-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 50090-5563-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 51407-0997-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 54348-0049-01 | PharmPak, | 1 tablet | — | AB | FDA listed | — |
| Lorazepam 1 mg 58118-1095-08 | Clinical | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 62135-0862-01 | Chartwell | 100 tablets | — | — | FDA listed | — |
| Lorazepam 1 mg 62559-0196-01 | ANI | 100 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 67046-0230-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 67296-2238-02 | Redpharm | 5 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 68071-3227-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 68071-3242-03 | NuCare | 3 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 68071-4918-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 68071-5022-05 | NuCare | 15 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 68071-5250-02 | NuCare | 20 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 68788-7428-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 70518-0275-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 70518-0486-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 70518-2186-02 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Lorazepam 1 mg 70518-2442-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Lorazepam 1 mg 70518-3423-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Lorazepam 1 mg 70518-3870-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Lorazepam 1 mg 70518-4276-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 71205-0235-02 | Proficient | 2 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 71335-1467-00 | Bryant | 10 tablets | — | AB | Discontinued | — |
| Lorazepam 1 mgthis 71335-1694-06 | Bryant | 50 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 71610-0122-10 | Aphena | 10 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 71610-0229-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 71610-0255-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 71610-0674-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 71610-0828-10 | Aphena | 10 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 72789-0226-04 | PD-Rx | 4 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 72789-0356-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 76420-0873-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 80425-0465-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 60760-0948-02 | St. | 2 tablets | — | AB | FDA listed | — |
| Lorazepam 1 mg 68788-4180-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1694-00 | 10 TABLET in 1 BOTTLE (71335-1694-0) | 2022-09-26 | Active |
| 71335-1694-01 | 30 TABLET in 1 BOTTLE (71335-1694-1) | 2021-03-18 | Active |
| 71335-1694-02 | 120 TABLET in 1 BOTTLE (71335-1694-2) | 2022-09-26 | Active |
| 71335-1694-03 | 15 TABLET in 1 BOTTLE (71335-1694-3) | 2022-03-21 | Active |
| 71335-1694-04 | 14 TABLET in 1 BOTTLE (71335-1694-4) | 2022-09-26 | Active |
| 71335-1694-05 | 90 TABLET in 1 BOTTLE (71335-1694-5) | 2021-01-29 | Active |
| 71335-1694-06 You're viewing this | 50 TABLET in 1 BOTTLE (71335-1694-6) | 2022-09-26 | Active |
| 71335-1694-07 | 60 TABLET in 1 BOTTLE (71335-1694-7) | 2021-12-13 | Active |
| 71335-1694-08 | 45 TABLET in 1 BOTTLE (71335-1694-8) | 2022-09-26 | Active |
| 71335-1694-09 | 100 TABLET in 1 BOTTLE (71335-1694-9) | 2022-09-26 | Active |
You're viewing one of 10 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1694-06?
What is the difference between NDC 71335-1694-06 and NDC 71335-1694-00?
What NDC number is used to bill for this package of Lorazepam 1 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS • Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required.
Follow patients for signs and symptoms of respiratory depression and sedation (see WARNINGS and PRECAUTIONS ). • The use of benzodiazepines, including lorazepam, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes. Before prescribing lorazepam and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (see WARNINGS ). • The continued use of benzodiazepines, including lorazepam may lead to clinically significant physical dependence.
The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose. Abrupt discontinuation or rapid dosage reduction of lorazepam after continued use may precipitate acute withdrawal reactions, which can be life-threatening. To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage ( DOSAGE AND ADMINISTRATION and WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Lorazepam tablets are indicated for the management of anxiety disorders or for the short-term relief of the symptoms of anxiety or anxiety associated with depressive symptoms. Anxiety or tension associated with the stress of everyday life usually does not require treatment with an anxiolytic. The effectiveness of lorazepam tablets in long-term use, that is, more than 4 months, has not been assessed by systematic clinical studies.
The physician should periodically reassess the usefulness of the drug for the individual patient.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Lorazepam tablets are administered orally. For optimal results, dose, frequency of administration, and duration of therapy should be individualized according to patient response. To facilitate this, 0.5 mg, 1 mg, and 2 mg tablets are available.
The usual range is 2 to 6 mg/day given in divided doses, the largest dose being taken before bedtime, but the daily dosage may vary from 1 to 10 mg/day. For anxiety, most patients require an initial dose of 2 to 3 mg/day given two times a day or three times a day. For insomnia due to anxiety or transient situational stress, a single daily dose of 2 to 4 mg may be given, usually at bedtime.
For elderly or debilitated patients, an initial dosage of 1 to 2 mg/day in divided doses is recommended, to be adjusted as needed and tolerated. The dosage of lorazepam tablets should be increased gradually when needed to help avoid adverse effects. When higher dosage is indicated, the evening dose should be increased before the daytime doses.
Discontinuation or Dosage Reduction of Lorazepam Tablets To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam tablets or reduce the dosage. If a patient develops withdrawal reactions, consider pausing the taper or increasing the dosage to the previous tapered dosage level. Subsequently decrease the dosage more slowly (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE: Dependence).
⛔ Contraindications ▾
CONTRAINDICATIONS Lorazepam is contraindicated in patients with: • hypersensitivity to benzodiazepines or to any components of the formulation • acute narrow-angle glaucoma.
⚠️ Warnings ▾
WARNINGS Risks from Concomitant Use with Opioids Concomitant use of benzodiazepines, including lorazepam, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs in patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe lorazepam concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. In patients already receiving an opioid analgesic, prescribe a lower initial dose of lorazepam than indicated in the absence of an opioid and titrate based on clinical response. If an opioid is initiated in a patient already taking lorazepam, prescribe a lower initial dose of the opioid and titrate based upon clinical response.
Advise both patients and caregivers about the risks of respiratory depression and sedation when lorazepam is used with opioids. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see PRECAUTIONS : Drug Interactions). Abuse, Misuse, and Addiction The use of benzodiazepines, including lorazepam, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death.
Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death (see DRUG ABUSE AND DEPENDENCE : Abuse). Before prescribing lorazepam and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (e.g., using a standardized screening tool).
Use of lorazepam, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of lorazepam along with monitoring for signs and symptoms of abuse, misuse, and addiction. Prescribe the lowest effective dosage; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug. If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
Dependence and Withdrawal Reactions To reduce the risk of withdrawal reactions, use a gradual taper to discontinue lorazepam or reduce the dosage (a patient-specific plan should be used to taper the dose) (see DOSAGE AND ADMINSTRATION : Discontinuation or Dosage Reduction of lorazepam). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines, including lorazepam, may lead to clinically significant physical dependence.
Abrupt discontinuation or rapid dosage reduction of lorazepam after continued use, or administration of flumazenil (a benzodiazepine antagonist) may precipitate acute withdrawal reactions, which can be life-threatening (e.g., seizures) (see DRUG ABUSE AND DEPENDENCE : Dependence). Protracted Withdrawal Syndrome In some cases, benzodiazepine users have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months (see DRUG ABUSE AND DEPENDENCE : Dependence ). Pre-existing depression may emerge or worsen during use of benzodiazepines including lorazepam.
Lorazepam is not recommended for use in patients wi…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Most adverse reactions to benzodiazepines, including CNS effects and respiratory depression, are dose dependent, with more severe effects occurring with high doses. In a sample of about 3500 patients treated for anxiety, the most frequent adverse reaction to lorazepam was sedation (15.9%), followed by dizziness (6.9%), weakness (4.2%), and unsteadiness (3.4%). The incidence of sedation and unsteadiness increased with age.
Other adverse reactions to benzodiazepines, including lorazepam are fatigue, drowsiness, amnesia, memory impairment, confusion, disorientation, depression, unmasking of depression, disinhibition, euphoria, suicidal ideation/attempt, ataxia, asthenia, extrapyramidal symptoms, convulsions/seizures, tremor, vertigo, eye function/visual disturbance(including diplopia and blurred vision), dysarthria/slurred speech, change in libido, impotence, decreasedorgasm; headache, coma; respiratory depression, apnea, worsening of sleep apnea, worsening of obstructive pulmonary disease; gastrointestinal symptoms including nausea, change in appetite, constipation, jaundice, increase in bilirubin, increase in liver transaminases, increase in alkaline phosphatase; hyper sensitivity reactions, anaphylactoid reactions; dermatological symptoms, allergic skin reactions, alopecia; syndrome of in appropriate antidiuretic hormone (SIADH), hyponatremia; thrombocytopenia, agranulocytosis, pancytopenia; hypothermia; and autonomic manifestations.
Paradoxical reactions, including anxiety, excitation, agitation, hostility, aggression, rage, sleep disturbances/insomnia, sexual arousal, and hallucinations may occur. Small decreases in blood pressure and hypotension may occur but are usually not clinically significant, probably being related to the relief of anxiety produced by lorazepam. To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions The concomitant use of benzodiazepines and opioids increases the risk of respiratory depression because of actions at different receptor sites in the CNS that control respiration. Benzodiazepines interact at GABA A sites and opioids interact primarily at mu receptors. When benzodiazepines and opioids are combined, the potential for benzodiazepines to significantly worsen opioid-related respiratory depression exists.
Limit dosage and duration of concomitant use of benzodiazepines and opioids and monitor patients closely for respiratory depression and sedation. The benzodiazepines, including lorazepam, produce increased CNS-depressant effects when administered with other CNS depressants such as alcohol, barbiturates, antipsychotics, sedative/hypnotics, anxiolytics, antidepressants, narcotic analgesics, sedative antihistamines, anticonvulsants, and anesthetics. Concomitant use of clozapine and lorazepam may produce marked sedation, excessive salivation, hypotension, ataxia, delirium, and respiratory arrest.
Concurrent administration of lorazepam with valproate results in increased plasma concentrations and reduced clearance of lorazepam. Lorazepam dosage should be reduced to approximately 50% when coadministered with valproate. Concurrent administration of lorazepam with probenecid may result in a more rapid onset or prolonged effect of lorazepam due to increased half-life and decreased total clearance.
L orazepam dosage needs to be reduced by approximately 50% when coadministered with probenecid. The effects of probenecid and valproate on lorazepam may be due to inhibition of glucuronidation. Administration of theophylline or aminophylline may reduce the sedative effects of benzodiazepines, including lorazepam.
🤰 Pregnancy ▾
Pregnancy Reproductive studies in animals were performed in mice, rats, and two strains of rabbits. Occasional anomalies (reduction of tarsals, tibia, metatarsals, malrotated limbs, gastroschisis, malformed skull, and microphthalmia) were seen in drug-treated rabbits without relationship to dosage. Although all of these anomalies were not present in the concurrent control group, they have been reported to occur randomly in historical controls.
At doses of 40 mg/kg and higher, there was evidence of fetal resorption and increased fetal loss in rabbits which was not seen at lower doses. The clinical significance of the above findings is not known. However, an increased risk of congenital malformations associated with the use of minor tranquilizers (chlordiazepoxide, diazepam, and meprobamate) during the first trimester of pregnancy has been suggested in several studies.
Because the use of these drugs is rarely a matter of urgency, the use of lorazepam during this period should be avoided. The possibility that a woman of childbearing potential may be pregnant at the time of institution of therapy should be considered. Patients should be advised that if they become pregnant, they should communicate with their physician about the desirability of discontinuing the drug.
In humans, blood levels obtained from umbilical cord blood indicate placental transfer of lorazepam and lorazepam glucuronide.Infants of mothers who ingested benzodiazepines for several weeks or more preceding delivery have been reported to have withdrawal symptoms during the postnatal period. Symptoms such as hypoactivity, hypotonia, hypothermia, respiratory depression, apnea, feeding problems, and impaired etabolic response to cold stress shave been reported in neonates born of mothers who have received benzodiazepines during the late phase of pregnancy or at delivery.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of lorazepam generally were not adequate to determine whether subjects aged 65 and over respond differently than younger subjects; however, the incidence of sedation and unsteadiness was observed to increase with age ( see ADVERSE REACTIONS). Age does not appear to have a significant effect on lorazepam kinetics (see CLINICAL PHARMACOLOGY). Clinical circumstances, some of which may be more common in the elderly, such as hepatic or renal impairment, should be considered.
Greater sensitivity (e.g., sedation) of some older individuals cannot be ruled out. In general, dose selection for an elderly patient should be cautious, and lower doses may be sufficient in these patients (see DOSAGE AND ADMINISTRATION).
🆘 Overdosage ▾
OVERDOSAGE In postmarketing experience, overdose with lorazepam has occurred predominantly in combination with alcohol and/or other drugs. Therefore, in the management of overdosage, it should be borne in mind that multiple agents may have been taken. Symptoms Overdosage of benzodiazepines is usually manifested by varying degrees of CNS depression ranging from drowsiness to coma.
In mild cases, symptoms include drowsiness, mental confusion, paradoxical reactions, dysarthria, and lethargy. In more serious cases, and especially when other drugs or alcohol were ingested, symptoms may include ataxia, hypotonia, hypotension, cardiovascular depression, respiratory depression, hypnotic state, coma, and death. Management General supportive and symptomatic measures are recommended; vital signs must be monitored, and the patient closely observed.
When there is a risk of aspiration, induction of emesis is not recommended. Gastric lavage may be indicated if performed soon after ingestion or in symptomatic patients. Administration of activated charcoal may also limit drug absorption.
Hypotension, though unlikely, usually may be controlled with norepinephrine bitartrate injection. Lorazepam is poorly dialyzable. Lorazepam glucuronide, the inactive metabolite, may be highly dialyzable.
The benzodiazepine antagonist flumazenil may be used in hospitalized patients as an adjunct to, not as a substitute for, proper management of benzodiazepine overdose. The prescriber should be aware of a risk of seizure in association with flumazenil treatment, particularly in long-term benzodiazepine users and in cyclic antidepressant overdose . The complete flumazenil package insert including CONTRAINDICATIONS, WARNINGS, and PRECAUTIONS sections should be consulted prior to use.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Studies in healthy volunteers show that in single high doses lorazepam has a tranquilizing action on the central nervous system with no appreciable effect on the respiratory or cardiovascular systems. Lorazepam is readily absorbed with an absolute bioavailability of 90%. Peak concentrations in plasma occur approximately 2 hours following administration.
The peak plasma level of lorazepam from a 2 mg dose is approximately 20 ng/mL. The mean half-life of unconjugated lorazepam in human plasma is about 12 hours and for its major metabolite, lorazepam glucuronide, about 18 hours. At clinically relevant concentrations, lorazepam is approximately 85% bound to plasma proteins. lorazepam is rapidly conjugated at its 3-hydroxy group into lorazepam glucuronide which is then excreted in the urine.
Lorazepam glucuronide has no demonstrable central nervous system (CNS) activity in animals. The plasma levels of lorazepam are proportional to the dose given. There is no evidence of accumulation of lorazepam on administration up to 6 months.
Studies comparing young and elderly subjects have shown that advancing age does not have a significant effect on the pharmacokinetics of lorazepam. However, in one study involving single intravenous doses of 1.5 to 3 mg of Lorazepam injection, mean total body clearance of lorazepam decreased by 20% in 15 elderly subjects of 60 to 84 years of age compared to that in 15 younger subjects of 19 to 38 years of age.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED NDC: 71335-1694-1: 30 Tablets in a BOTTLE NDC: 71335-1694-2: 120 Tablets in a BOTTLE NDC: 71335-1694-3: 15 Tablets in a BOTTLE NDC: 71335-1694-4: 14 Tablets in a BOTTLE NDC: 71335-1694-5: 90 Tablets in a BOTTLE NDC: 71335-1694-6: 50 Tablets in a BOTTLE NDC: 71335-1694-7: 60 Tablets in a BOTTLE NDC: 71335-1694-8: 45 Tablets in a BOTTLE NDC: 71335-1694-9: 100 Tablets in a BOTTLE NDC: 71335-1694-0: 10 Tablets in a BOTTLE
📋 Description ▾
DESCRIPTION Lorazepam USP, an antianxiety agent, has the chemical formula, 7-chloro-5-( o -chlorophenyl)-1,3-dihydro-3-hydroxy-2 H -1,4-benzodiazepin-2-one: It is a nearly white powder almost insoluble in water. Each lorazepam tablet USP, to be taken orally, contains 0.5 mg, 1 mg, or 2 mg of lorazepam USP. The inactive ingredients present are anhydrous lactose, magnesium stearate, microcrystalline cellulose, and polacriline potassium. Chemical-Structure
💬 Information for Patients ▾
Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide). Risks from Concomitant Use with Opioids Advise both patients and caregivers about the risks of potentially fatal respiratory depression and sedation when lorazepam is used with opioids and not to use such drugs concomitantly unless supervised by a health care provider. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined ( see WARNINGS : Risks from Concomitant Use of Opioids and PRECAUTIONS : Drug Interactions).
Abuse, Misuse, and Addiction Inform patients that the use of lorazepam even at recommended doses, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances. Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug ( see WARNINGS: Abuse Misuse, and Addiction and DRUG ABUSE AND DEPENDENCE ).
Withdrawal Reactions Inform patients that the continued use of lorazepam may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of lorazepam may precipitate acute withdrawal reactions, which can be life-threatening. Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months. Instruct patients that discontinuation or dosage reduction of lorazepam may require a slow taper (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE ).