
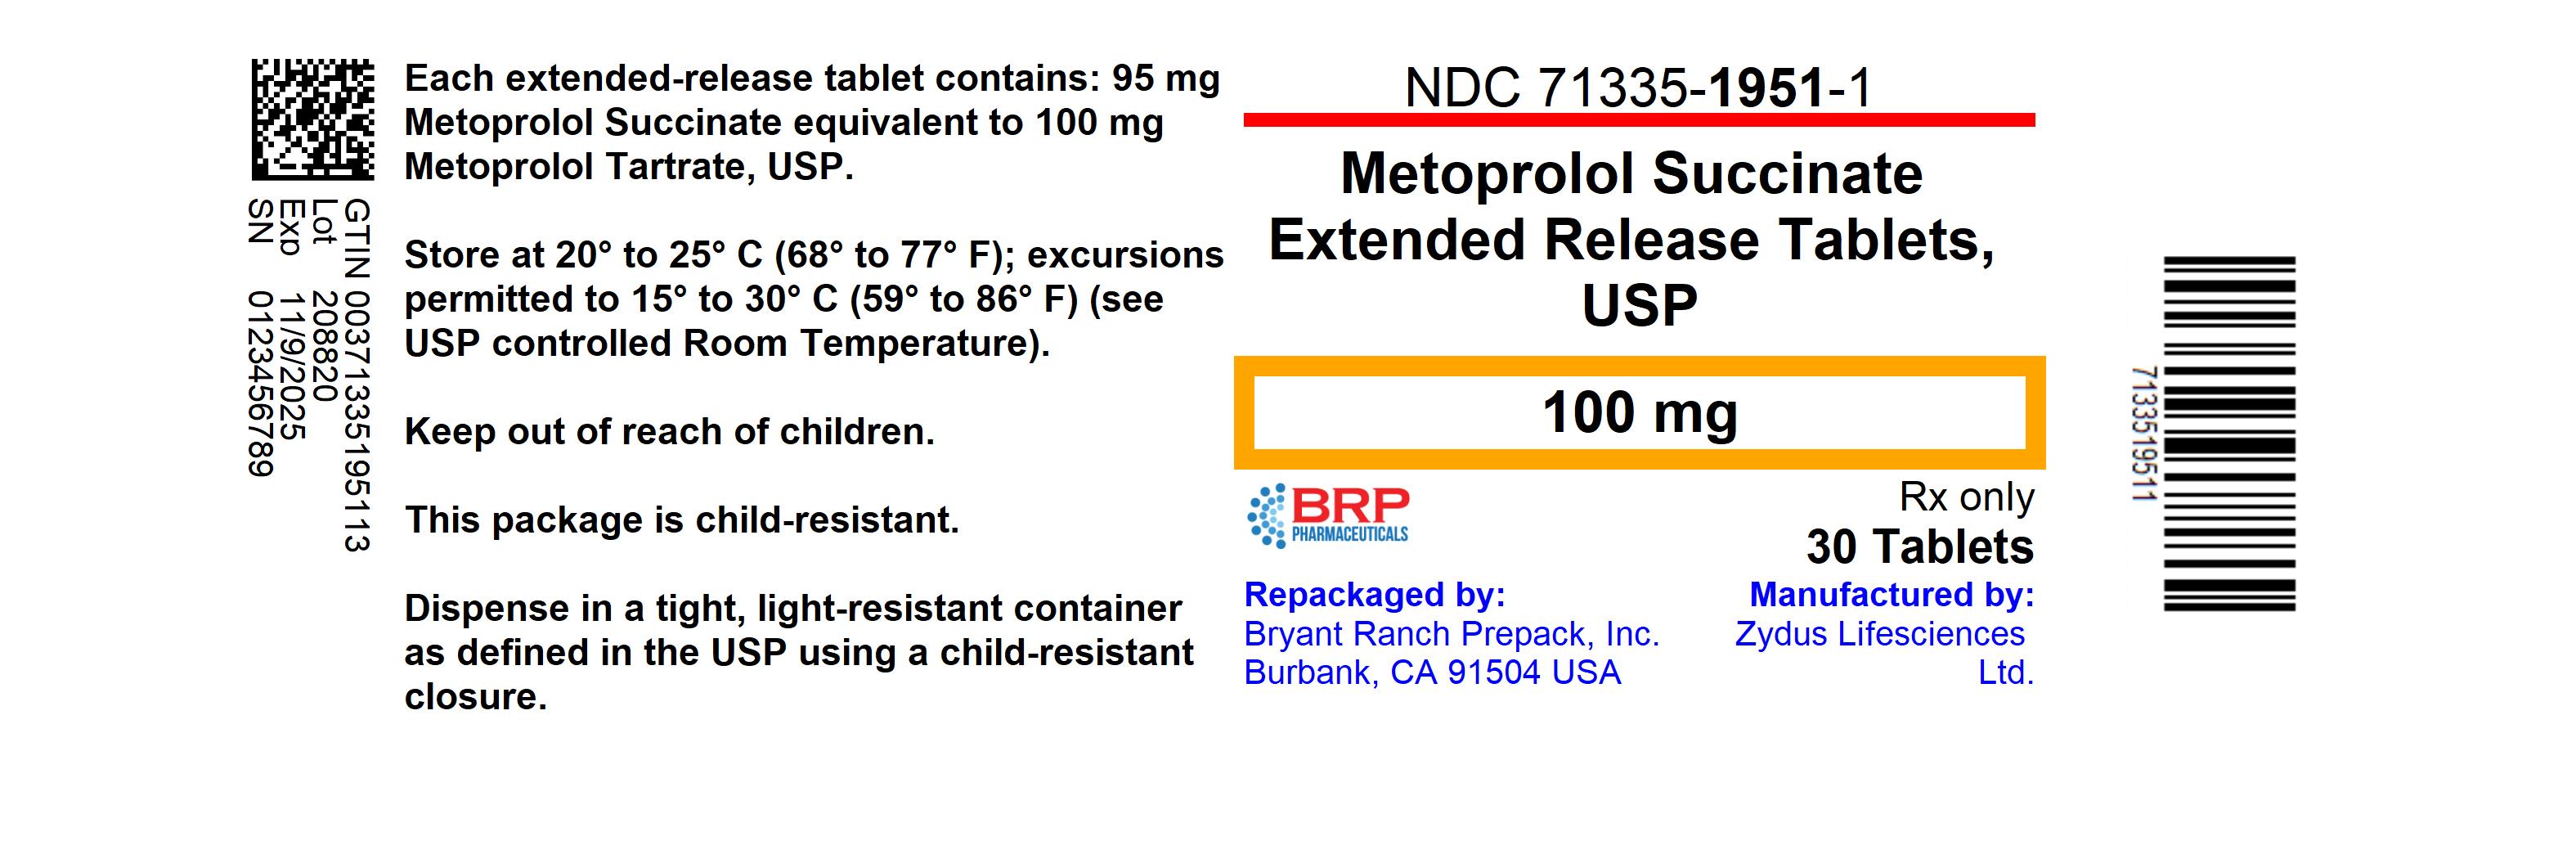
metoprolol succinate 100 mg Tablet, Extended Release, 60-count
Other active recalls for Metoprolol Succinate (different manufacturers) — 5 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Metoprolol is used to treat high blood pressure, angina (chest pain) and heart failure. Metoprolol also is used to improve survival after a heart attack . Metoprolol is in a class of medications called beta blockers. It works by relaxing blood vessels and slowing heart rate to improve blood flow and decrease blood pressure.
Read the full MedlinePlus article ↗- That depends on why you were prescribed it. Metoprolol is a beta-blocker, which means it slows your heart rate and reduces the workload on your heart. Depending on your formulation...
- What exactly is metoprolol supposed to do for me?
- Please don't stop suddenly — this is one of the most important things to know about this drug. Stopping metoprolol abruptly, especially if you have any heart disease, can cause you...
- Can I stop taking metoprolol if I feel fine or if it makes me tired?
Patient education
Supplement & herbal interactions
Metoprolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 3DYK7UYZ62
Ethylcellulose is a plant-fiber derivative used as a binder and film-coating agent in tablets and capsules. It helps hold ingredients together and can create a protective coating that controls how quickly the medicine dissolves.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII NPU9M2E6L8
Methylcellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and a viscosity builder in liquid formulations.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2385 | $14.31 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Metoprolol Succinate 100 mg 68001-0358-00 | BluePoint | 100 tablets | $0.082 | AB | FDA listed | — |
| Metoprolol succinate 100 mg 70436-0166-01 | Slate | 100 tablets | $0.086 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 00904-6324-61 | Major | 1 tablet | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 27808-0304-01 | Cranbury | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 31722-0591-01 | Camber | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 42806-0726-01 | Epic | 100 tablets | $0.091 | AB | Availability likely | — |
| metoprolol succinate 100 mg 45963-0677-11 | Actavis | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 50268-0542-15 | AvPAK | 1 tablet | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 50742-0617-01 | Ingenus | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 55111-0468-01 | Dr. | 100 tablets | $0.091 | — | Availability likely | — |
| Metoprolol Succinate 100 mg 60687-0413-01 | American | 1 tablet | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 67877-0592-01 | Ascend | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 68001-0470-00 | BluePoint | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 68001-0502-00 | BluePoint | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 68001-0686-00 | BluePoint | 100 tablets | $0.091 | AB | Availability likely | — |
| metoprolol succinate 100 mg 68382-0566-01 | Zydus | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 70010-0782-01 | Granules | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 72516-0032-01 | Oryza | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 72603-0144-01 | Northstar | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 75907-0345-01 | Dr. | 100 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 82009-0115-05 | Quallent | 500 tablets | $0.091 | AB | Availability likely | — |
| Metoprolol Succinate 100 mg 75834-0292-00 | Nivagen | 1000 tablets | $0.097 | — | Discontinued | — |
| Toprol Xl 100 mg 70842-0112-02 | Melinta | 100 tablets | $2.079 | AB | Availability likely | — |
| Metoprolol succinate 100 mg 00615-7825-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 43063-0841-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| metoprolol succinate 100 mg 50090-5411-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 50090-5720-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 50090-5721-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 50090-6260-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 50090-7069-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 50090-7070-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 51407-0405-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| metoprolol succinate 100 mg 51655-0193-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 51655-0888-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 53401-0014-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 55154-4347-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 55154-7279-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| metoprolol succinate 100 mg 60760-0663-90 | St. | 90 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 60760-0994-90 | ST. | 90 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 61919-0334-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 62207-0131-49 | Granules | 1000 tablets | — | — | FDA listed | — |
| Metoprolol succinate 100 mg 63187-0768-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 63629-8865-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 63629-9171-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 63629-9172-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 68001-0119-00 | BluePoint | 100 tablets | — | AB | FDA listed | — |
| metoprolol succinate 100 mg 68071-2651-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 68071-5282-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 68788-8448-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 69097-0408-02 | Cipla | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 70518-2080-01 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| metoprolol succinate 100 mg 70518-3122-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 70518-4190-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 70518-4407-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 70518-4456-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 70518-4533-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| metoprolol succinate 100 mg 70771-1340-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 71205-0336-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 71205-0683-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| metoprolol succinate 100 mg 71205-0801-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 71335-0167-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| metoprolol succinate 100 mgthis 71335-1951-06 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 71335-2945-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 71335-9706-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 71610-0484-45 | Aphena | 45 tablets | — | AB | Discontinued | — |
| Metoprolol Succinate 100 mg 71610-0558-45 | Aphena | 45 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 71765-0007-01 | Zhejiang | 100 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 72162-1858-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 72516-0027-01 | Oryza | 100 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 82804-0279-90 | Proficient | 90 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 82868-0079-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Metoprolol Succinate 100 mg 67046-1686-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 71335-3167-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Metoprolol succinate 100 mg 67296-2321-03 | Redpharm | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1951-01 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (71335-1951-1) | 2021-12-17 | Active |
| 71335-1951-02 | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE (71335-1951-2) | 2021-09-14 | Active |
| 71335-1951-03 | 120 TABLET, EXTENDED RELEASE in 1 BOTTLE (71335-1951-3) | 2022-09-19 | Active |
| 71335-1951-04 | 20 TABLET, EXTENDED RELEASE in 1 BOTTLE (71335-1951-4) | 2022-09-19 | Active |
| 71335-1951-05 | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (71335-1951-5) | 2022-09-19 | Active |
| 71335-1951-06 You're viewing this | 60 TABLET, EXTENDED RELEASE in 1 BOTTLE (71335-1951-6) | 2021-10-13 | Active |
| 71335-1951-07 | 10 TABLET, EXTENDED RELEASE in 1 BOTTLE (71335-1951-7) | 2022-09-19 | Active |
You're viewing one of 7 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1951-06?
What is the difference between NDC 71335-1951-06 and NDC 71335-1951-07?
What NDC number is used to bill for this package of metoprolol succinate 100 mg Tablet, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Metoprolol succinate extended-release tablets, are a beta-adrenergic blocker indicated for the treatment of: Hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and non-fatal cardiovascular events, primarily strokes and myocardial infarctions. (1.1) Angina Pectoris.
(1.2) Heart Failure, to reduce the risk of cardiovascular mortality and heart failure hospitalizations in patients with heart failure (1.3)
1.1Hypertension Metoprolol succinate extended-release tablets are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure lowers the risk of fatal and non-fatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including metoprolol.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Metoprolol succinate extended-release tablets may be administered with other antihypertensive agents.
1.2Angina Pectoris Metoprolol succinate extended-release tablets are indicated in the long-term treatment of angina pectoris, to reduce angina attacks and to improve exercise tolerance.
1.3Heart Failure Metoprolol succinate extended-release tablets are is indicated to reduce the risk of cardiovascular mortality and heart-failure hospitalization in patients with heart failure.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administer once daily. Titrate at weekly or longer intervals as needed and tolerated. (2) Hypertension: Starting dose is 25 to 100 mg. (2.1) Angina Pectoris: Starting dose is 100 mg. (2.2) Heart Failure: Starting dose is 12.5 or 25 mg. (2.3) Switching from immediate-release metoprolol to metoprolol succinate extended-release tablets: use the same total daily dose of metoprolol succinate extended-release tablets. (2)
2.1Hypertension Adults: The usual initial dosage is 25 to 100 mg daily in a single dose. Adjust dosage at weekly (or longer) intervals until optimum blood pressure reduction is achieved. In general, the maximum effect of any given dosage level will be apparent after 1 week of therapy.
Dosages above 400 mg per day have not been studied. Pediatric Hypertensive Patients ≥ 6 Years of age: A pediatric clinical hypertension study in patients 6 to 16 years of age did not meet its primary endpoint (dose response for reduction in SBP); however some other endpoints demonstrated effectiveness [see Use in Specific Populations (8.4) ] . If selected for treatment, the recommended starting dose of metoprolol succinate extended-release tablets is 1 mg/kg once daily, but the maximum initial dose should not exceed 50 mg once daily.
Adjust dosage according to blood pressure response. Doses above 2 mg/kg (or in excess of 200 mg) once daily have not been studied in pediatric patients [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.3) ]. Metoprolol succinate extended-release tablets has not been studied in pediatric patients < 6 years of age [see Use in Specific Populations (8.4)].
2.2Angina Pectoris Individualize the dosage of metoprolol succinate extended-release tablets. The usual initial dosage is 100 mg daily, given in a single dose. Gradually increase the dosage at weekly intervals until optimum clinical response has been obtained or there is a pronounced slowing of the heart rate.
Dosages above 400 mg per day have not been studied. If treatment is to be discontinued, reduce the dosage gradually over a period of 1 to 2 weeks [see Warnings and Precautions (5)] .
2.3Heart Failure Dosage must be individualized and closely monitored during up-titration. Prior to initiation of metoprolol succinate extended-release tablets, stabilize the dose of other heart failure drug therapy. The recommended starting dose of metoprolol succinate extended-release tablets is 25 mg once daily for two weeks in patients with NYHA Class II heart failure and 12.5 mg once daily in patients with more severe heart failure.
Double the dose every two weeks to the highest dosage level tolerated by the patient or up to 200 mg of metoprolol succinate extended-release tablets. Initial difficulty with titration should not preclude later attempts to introduce metoprolol succinate extended-release tablets. If patients experience symptomatic bradycardia, reduce the dose of metoprolol succinate.
If transient worsening of heart failure occurs, consider treating with increased doses of diuretics, lowering the dose of metoprolol succinate extended-release tablets or temporarily discontinuing it. The dose of metoprolol succinate should not be increased until symptoms of worsening heart failure have been stabilized.
2.4Administration Metoprolol succinate extended-release tablets are scored and can be divided; however, do not crush or chew the whole or half tablet.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Metoprolol succinate extended-release tablets (metoprolol succinate): 25 mg, 50 mg, 100 mg, and 200 mg. (3) 25 mg tablets: White to off-white color, oval shaped, biconvex coated tablets, debossed with "564" on one side and break line on the other side. 50 mg tablets: White to off-white color, round shaped, biconvex coated tablets, debossed with "565" on one side and break line on the other side.
100 mg tablets: White to off-white color, round shaped, biconvex coated tablets, debossed with "566" on one side and break line on other side. 200 mg tablets: White to off-white color, oval shaped, biconvex coated tablets, debossed with "5" and "67" on either side of break line and plain on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Known hypersensitivity to product components. (4) Severe bradycardia: Greater than first degree heart block, or sick sinus syndrome without a pacemaker. (4) Cardiogenic shock or decompensated heart failure.
(4) Metoprolol succinate extended-release tablets are contraindicated in severe bradycardia, second or third-degree heart block, cardiogenic shock, decompensated heart failure, sick sinus syndrome (unless a permanent pacemaker is in place), and in patients who are hypersensitive to any component of this product.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Abrupt cessation may exacerbate myocardial ischemia. ( 5.1 ) Heart Failure: Worsening cardiac failure may occur. ( 5.2 ) Bronchospastic Disease: Avoid beta-blockers.
( 5.3 ) Concomitant use of glycosides, clonidine, diltiazem and verapamil with beta-blockers can increase the risk of bradycardia. ( 5.4 ) Pheochromocytoma: Initiate therapy with an alpha-blocker. ( 5.5 ) Major Surgery: Avoid initiation of high-dose extended-release metoprolol in patients undergoing non-cardiac surgery.
Do not routinely withdraw chronic beta blocker therapy prior to surgery. ( 5.6 , 6.1 ) Hypoglycemia: May increase risk for hypoglycemia and mask early warning signs. ( 5.7 ) Thyrotoxicosis: Abrupt withdrawal in patients with thyrotoxicosis might precipitate a thyroid storm.
( 5.8 ) Peripheral Vascular Disease: Can aggravate symptoms of arterial insufficiency. ( 5.9 ) Patients may be unresponsive to the usual doses of epinephrine used to treat allergic reaction. ( 5.10 )
5.1Abrupt Cessation of Therapy Following abrupt cessation of therapy with certain beta-blocking agents, exacerbations of angina pectoris and, in some cases, myocardial infarction have occurred. When discontinuing chronically administered metoprolol succinate extended-release tablets, particularly in patients with ischemic heart disease, gradually reduce the dosage over a period of 1 to 2 weeks and monitor the patient. If angina markedly worsens or acute coronary ischemia develops, promptly reinstate metoprolol succinate extended-release tablets, and take measures appropriate for the management of unstable angina.
Warn patients not to interrupt therapy without their physician's advice. Because coronary artery disease is common and may be unrecognized, avoid abruptly discontinuing metoprolol succinate extended-release tablets in patients treated only for hypertension.
5.2Heart Failure Worsening cardiac failure may occur during up-titration of metoprolol succinate extended-release tablets. If such symptoms occur, increase diuretics and restore clinical stability before advancing the dose of metoprolol succinate extended-release tablets [see Dosage and Administration (2)] . It may be necessary to lower the dose of metoprolol succinate extended-release tablets or temporarily discontinue it.
Such episodes do not preclude subsequent successful titration of metoprolol succinate extended-release tablets.
5.3Bronchospastic Disease Patients with bronchospastic diseases should, in general, not receive beta-blockers. Because of its relative beta 1 -cardioselectivity, however, metoprolol succinate extended-release tablets may be used in patients with bronchospastic disease who do not respond to, or cannot tolerate, other antihypertensive treatment. Because beta 1 -selectivity is not absolute, use the lowest possible dose of metoprolol succinate extended-release tablets.
Bronchodilators, including beta 2 -agonists, should be readily available or administered concomitantly [see Dosage and Administration (2)] .
5.4Bradycardia Bradycardia, including sinus pause, heart block, and cardiac arrest have occurred with the use of metoprolol succinate extended-release tablets. Patients with first-degree atrioventricular block, sinus node dysfunction, conduction disorders (including Wolff- Parkinson-White) or on concomitant drugs that cause bradycardia [see Drug Interactions (7.3) ], may be at increased risk. Monitor heart rate in patients receiving metoprolol succinate extended-release tablets.
If severe bradycardia develops, reduce or stop metoprolol succinate extended-release tablets.
5.5Pheochromocytoma If metoprolol succinate extended-release tablets are used in the setting of pheochromocytoma, it should be given in combination with an alpha-blocker, and only after the alpha blocker has been initiated. Administration of beta-blockers alone in the setting of pheochromocytoma has been associated with a paradoxical increase in blood pressure due to the attenuation of beta-med…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions: tiredness, dizziness, depression, shortness of breath, bradycardia, hypotension, diarrhea, pruritus, rash. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Zydus Pharmaceuticals (USA) Inc. at 1-877-993-8779 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. The following adverse reactions are described elsewhere in labeling: Worsening angina or myocardial infarction [see Warnings and Precautions (5)].
Worsening heart failure [see Warnings and Precautions (5)]. Worsening AV block [see Contraindications (4)].
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The adverse reaction information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates. Hypertension and Angina: Most adverse reactions have been mild and transient.
The most common (>2%) adverse reactions are tiredness, dizziness, depression, diarrhea, shortness of breath, bradycardia, and rash. Heart Failure: In the MERIT-HF study comparing metoprolol succinate extended-release tablets in daily doses up to 200 mg (mean dose 159 mg once-daily; n=1990) to placebo (n=2001), 10.3% of metoprolol succinate patients discontinued for adverse reactions vs. 12.2% of placebo patients.
The table below lists adverse reactions in the MERIT-HF study that occurred at an incidence of ≥ 1% in the metoprolol succinate extended-release tablets group and greater than placebo by more than 0.5%, regardless of the assessment of causality. Adverse Reactions Occurring in the MERIT-HF Study at an Incidence ≥ 1 % in the Metoprolol Succinate Extended-Release Tablets Group and Greater Than Placebo by More Than 0.5 % Metoprolol Succinate Extended-Release Tablets n=1990 % of patients Placebo n=2001 % of patients Dizziness/vertigo 1.8 1 Bradycardia 1.5
0.4Post-operative Adverse Events: In a randomized, double blind, placebo-controlled trial of 8351 patients with or at risk for atherosclerotic disease undergoing non-vascular surgery and who were not taking beta–blocker therapy, metoprolol succinate extended-release tablets 100 mg was started 2 to 4 hours prior to surgery then continued for 30 days at 200 mg per day. Metoprolol succinate extended-release tablets use was associated with a higher incidence of bradycardia (6.6% vs 2.4%; HR 2.74; 95% CI 2.19, 3.43), hypotension (15% vs.
9.7%; HR 1.55; 95% CI 1.37, 1.74), stroke (1% vs 0.5%; HR 2.17; 95% CI 1.26, 3.74) and death (3.1% vs 2.3%; HR 1.33; 95% CI 1.03, 1.74) compared to placebo.
6.2Post-Marketing Experience The following adverse reactions have been identified during post-approval use of metoprolol succinate extended-release tablets or immediate-release metoprolol. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cardiovascular: Cold extremities, arterial insufficiency (usually of the Raynaud type), palpitations, peripheral edema, syncope, chest pain, and hypotension.
Respiratory: Wheezing (bronchospasm), dyspnea. Central Nervous System: Confusion, short-term memory loss, headache, somnolence, nightmares, insomnia, anxiety/nervousness, hallucinations, paresthesia. Gastrointestinal: Nausea, dry mouth, constipation, flatulence, heartburn, hepatitis, vomiting.
Hypersensitive Reactions: Pruritus. Miscellaneous: Musculoskeletal pain, arthralgia, blurred vision, decreased libido, male impotence, tinnitus, reversible alopecia, agranulocytosis, dry eyes, worsening of psoriasis, Peyronie's disease, sweating, photosensitivity, taste disturbance. Potential Adverse Reactions: In addition, there are adverse reactions not…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Catecholamine-depleting drugs may have an additive effect when given with beta-blocking agents. (7.1) CYP2D6 Inhibitors are likely to increase metoprolol concentration. (7.2) Beta-blockers including metoprolol, may exacerbate the rebound hypertension that can follow the withdrawal of clonidine. (7.3)
7.1Catecholamine Depleting Drugs Catecholamine depleting drugs (e.g., reserpine, monoamine oxidase (MAO) inhibitors) may have an additive effect when given with beta-blocking agents. Observe patients treated with metoprolol succinate extended-release tablets plus a catecholamine depletor for evidence of hypotension or marked bradycardia, which may produce vertigo, syncope, or postural hypotension.
7.2CYP2D6 Inhibitors Drugs that are strong inhibitors of CYP2D6 such as quinidine, fluoxetine, paroxetine, and propafenone were shown to double metoprolol concentrations. While there is no information about moderate or weak inhibitors, these too are likely to increase metoprolol concentration. Increases in plasma concentration decrease the cardioselectivity of metoprolol [see Clinical Pharmacology (12.3) ].
Monitor patients closely, when the combination cannot be avoided.
7.3Digitalis, Clonidine, and Calcium Channel Blockers Digitalis glycosides, clonidine, diltiazem, and verapamil slow atrioventricular conduction and decrease heart rate. Concomitant use with beta-blockers can increase the risk of bradycardia. If clonidine and a beta blocker, such as metoprolol are co-administered, withdraw the beta-blocker several days before the gradual withdrawal of clonidine because beta-blockers may exacerbate the rebound hypertension that can follow the withdrawal of clonidine.
If replacing clonidine by beta-blocker therapy, delay the introduction of beta-blockers for several days after clonidine administration has stopped.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic Impairment: Consider initiating metoprolol succinate therapy at low doses and gradually increase dosage to optimize therapy, while monitoring closely for adverse events. (8.6)
8.1Pregnancy Risk Summary Untreated hypertension and heart failure during pregnancy can lead to adverse outcomes for the mother and the fetus (see Clinical Considerations). Available data from published observational studies have not demonstrated a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes with metoprolol use during pregnancy. However, there are inconsistent reports of intrauterine growth restriction, preterm birth, and perinatal mortality with maternal use of beta-blockers, including metoprolol, during pregnancy ( see Data ).
In animal reproduction studies, metoprolol has been shown to increase post-implantation loss and decrease neonatal survival in rats at oral dosages of 500 mg/kg/day, approximately 24 times the daily dose of 200 mg in a 60-kg patient on a mg/m 2 basis. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical consideration Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Stroke volume and heart rate increase during pregnancy, increasing cardiac output, especially during the first trimester. There is a risk for preterm birth with pregnant women with chronic heart failure in 3rd trimester of pregnancy.
Fetal/Neonatal adverse reactions Metoprolol crosses the placenta. Neonates born to mothers who are receiving metoprolol during pregnancy, may be at risk for hypotension, hypoglycemia, bradycardia, and respiratory depression. Observe neonates and manage accordingly.
Data Human Data Data from published observational studies did not demonstrate an association of major congenital malformations and use of metoprolol in pregnancy. The published literature has reported inconsistent findings of intrauterine growth retardation, preterm birth, and perinatal mortality with maternal use of metoprolol during pregnancy; however, these studies have methodological limitations hindering interpretation. Methodological limitations include retrospective design, concomitant use of other medications, and other unadjusted confounders that may account for the study findings including the underlying disease in the mother.
These observational studies cannot definitively establish or exclude any drug-associated risk during pregnancy. Animal Data Metoprolol has been shown to increase post-implantation loss and decrease neonatal survival in rats at oral dosages of 500 mg/kg/day, i.e., 24 times, on a mg/m 2 basis, the daily dose of 200 mg in a 60-kg patient. No fetal abnormalities were observed when pregnant rats received metoprolol orally up to a dose of 200 mg/kg/day, i.e., 10 times, the daily dose of 200 mg in a 60-kg patient.
8.2Lactation Risk Summary Limited available data from published literature report that metoprolol is present in human milk. The estimated daily infant dose of metoprolol received from breastmilk ranges from 0.05 mg to less than 1 mg. The estimated relative infant dosage was 0.5% to 2% of the mother's weight-adjusted dosage (see Data). No adverse reactions of metoprolol on the breastfed infant have been identified. There is no information r…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Untreated hypertension and heart failure during pregnancy can lead to adverse outcomes for the mother and the fetus (see Clinical Considerations). Available data from published observational studies have not demonstrated a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes with metoprolol use during pregnancy. However, there are inconsistent reports of intrauterine growth restriction, preterm birth, and perinatal mortality with maternal use of beta-blockers, including metoprolol, during pregnancy ( see Data ).
In animal reproduction studies, metoprolol has been shown to increase post-implantation loss and decrease neonatal survival in rats at oral dosages of 500 mg/kg/day, approximately 24 times the daily dose of 200 mg in a 60-kg patient on a mg/m 2 basis. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical consideration Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Stroke volume and heart rate increase during pregnancy, increasing cardiac output, especially during the first trimester. There is a risk for preterm birth with pregnant women with chronic heart failure in 3rd trimester of pregnancy.
Fetal/Neonatal adverse reactions Metoprolol crosses the placenta. Neonates born to mothers who are receiving metoprolol during pregnancy, may be at risk for hypotension, hypoglycemia, bradycardia, and respiratory depression. Observe neonates and manage accordingly.
Data Human Data Data from published observational studies did not demonstrate an association of major congenital malformations and use of metoprolol in pregnancy. The published literature has reported inconsistent findings of intrauterine growth retardation, preterm birth, and perinatal mortality with maternal use of metoprolol during pregnancy; however, these studies have methodological limitations hindering interpretation. Methodological limitations include retrospective design, concomitant use of other medications, and other unadjusted confounders that may account for the study findings including the underlying disease in the mother.
These observational studies cannot definitively establish or exclude any drug-associated risk during pregnancy. Animal Data Metoprolol has been shown to increase post-implantation loss and decrease neonatal survival in rats at oral dosages of 500 mg/kg/day, i.e., 24 times, on a mg/m 2 basis, the daily dose of 200 mg in a 60-kg patient. No fetal abnormalities were observed when pregnant rats received metoprolol orally up to a dose of 200 mg/kg/day, i.e., 10 times, the daily dose of 200 mg in a 60-kg patient.
🧒 Pediatric Use ▾
8.4Pediatric Use One hundred forty-four hypertensive pediatric patients aged 6 to 16 years were randomized to placebo or to one of three dose levels of metoprolol succinate (0.2, 1 or 2 mg/kg once daily) and followed for 4 weeks. The study did not meet its primary endpoint (dose response for reduction in SBP). Some pre-specified secondary endpoints demonstrated effectiveness including: Dose-response for reduction in DBP, 1 mg/kg vs. placebo for change in SBP, and 2 mg/kg vs. placebo for change in SBP and DBP.
The mean placebo corrected reductions in SBP ranged from 3 to 6 mmHg, and DBP from 1 to 5 mmHg. Mean reduction in heart rate ranged from 5 to 7 bpm but considerably greater reductions were seen in some individuals [see Dosage and Administration (2.1)] . No clinically relevant differences in the adverse event profile were observed for pediatric patients aged 6 to 16 years as compared with adult patients.
Safety and effectiveness of metoprolol succinate extended-release tablets have not been established in patients < 6 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of metoprolol succinate in hypertension did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience in hypertensive patients has not identified differences in responses between elderly and younger patients. Of the 1,990 patients with heart failure randomized to metoprolol succinate in the MERIT-HF trial, 50% (990) were 65 years of age and older and 12% (238) were 75 years of age and older.
There were no notable differences in efficacy or the rate of adverse reactions between older and younger patients. In general, use a low initial starting dose in elderly patients given their greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Signs and Symptoms - Overdosage of metoprolol succinate extended-release tablets may lead to severe bradycardia, hypotension, and cardiogenic shock. Clinical presentation can also include atrioventricular block, heart failure, bronchospasm, hypoxia, impairment of consciousness/coma, nausea and vomiting. Treatment – Consider treating the patient with intensive care.
Patients with myocardial infarction or heart failure may be prone to significant hemodynamic instability. Beta-blocker overdose may result in significant resistance to resuscitation with adrenergic agents, including beta-agonists. On the basis of the pharmacologic actions of metoprolol, employ the following measures: Hemodialysis is unlikely to make a useful contribution to metoprolol elimination [see Clinical Pharmacology (12.3) ].
Bradycardia: Evaluate the need for atropine, adrenergic-stimulating drugs, or pacemaker to treat bradycardia and conduction disorders. Hypotension: Treat underlying bradycardia. Consider intravenous vasopressor infusion, such as dopamine or norepinephrine.
Heart failure and shock: May be treated when appropriate with suitable volume expansion, injection of glucagon (if necessary, followed by an intravenous infusion of glucagon), intravenous administration of adrenergic drugs such as dobutamine, with α1 receptor agonistic drugs added in presence of vasodilation. Bronchospasm: Can usually be reversed by bronchodilators.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Metoprolol is a beta 1 -selective (cardioselective) adrenergic receptor blocking agent. This preferential effect is not absolute, however, and at higher plasma concentrations, metoprolol also inhibits beta 2 -adrenoreceptors, chiefly located in the bronchial and vascular musculature. Metoprolol has no intrinsic sympathomimetic activity, and membrane-stabilizing activity is detectable only at plasma concentrations much greater than required for beta-blockade.
Animal and human experiments indicate that metoprolol slows the sinus rate and decreases AV nodal conduction. The relative beta 1 -selectivity of metoprolol has been confirmed by the following: (1) In normal subjects, metoprolol is unable to reverse the beta 2 -mediated vasodilating effects of epinephrine. This contrasts with the effect of nonselective beta-blockers, which completely reverse the vasodilating effects of epinephrine.
(2) In asthmatic patients, metoprolol reduces FEV1 and FVC significantly less than a nonselective beta-blocker, propranolol, at equivalent beta 1 -receptor blocking doses. Hypertension: The mechanism of the antihypertensive effects of beta-blocking agents has not been elucidated. However, several possible mechanisms have been proposed: (1) competitive antagonism of catecholamines at peripheral (especially cardiac) adrenergic neuron sites, leading to decreased cardiac output; (2) a central effect leading to reduced sympathetic outflow to the periphery; and (3) suppression of renin activity.
Angina Pectoris: By blocking catecholamine-induced increases in heart rate, in velocity and extent of myocardial contraction, and in blood pressure, metoprolol reduces the oxygen requirements of the heart at any given level of effort, thus making it useful in the long-term management of angina pectoris. Heart Failure: The precise mechanism for the beneficial effects of beta-blockers in heart failure has not been elucidated.
12.2Pharmacodynamics Clinical pharmacology studies have confirmed the beta-blocking activity of metoprolol in man, as shown by (1) reduction in heart rate and cardiac output at rest and upon exercise, (2) reduction of systolic blood pressure upon exercise, (3) inhibition of isoproterenol-induced tachycardia, and (4) reduction of reflex orthostatic tachycardia. The relationship between plasma metoprolol levels and reduction in exercise heart rate is independent of the pharmaceutical formulation. Beta 1 -blocking effects in the range of 30 to 80% of the maximal effect (approximately 8 to 23% reduction in exercise heart rate) correspond to metoprolol plasma concentrations from 30 to 540 nmol/L.
The relative beta 1 -selectivity of metoprolol diminishes and blockade of beta 2 -adrenoceptors increases at plasma concentration above 300 nmol/L. In five controlled studies in normal healthy subjects, extended-release metoprolol succinate administered once a day, and immediate-release metoprolol administered once to four times a day, provided comparable total beta 1 -blockade over 24 hours (area under the beta 1 -blockade versus time curve) in the dose range 100 to 400 mg. In another controlled study, 50 mg once daily for each product, extended-release metoprolol succinate produced significantly higher total beta 1 -blockade over 24 hours than immediate-release metoprolol.
For extended-release metoprolol succinate, the percent reduction in exercise heart rate was relatively stable throughout the entire dosage interval and the level of beta 1 -blockade increased with increasing doses from 50 to 300 mg daily. A controlled cross-over study in heart failure patients compared the plasma concentrations and beta 1 -blocking effects of 50 mg immediate-release metoprolol administered t.i.d., and 100 mg and 200 mg extended-release metoprolol succinate once daily. Extended-release metoprolol succinate 200 mg once daily produced a larger effect on suppression of exercise-induced and Holter-monitored heart rate ov…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Metoprolol is a beta 1 -selective (cardioselective) adrenergic receptor blocking agent. This preferential effect is not absolute, however, and at higher plasma concentrations, metoprolol also inhibits beta 2 -adrenoreceptors, chiefly located in the bronchial and vascular musculature. Metoprolol has no intrinsic sympathomimetic activity, and membrane-stabilizing activity is detectable only at plasma concentrations much greater than required for beta-blockade.
Animal and human experiments indicate that metoprolol slows the sinus rate and decreases AV nodal conduction. The relative beta 1 -selectivity of metoprolol has been confirmed by the following: (1) In normal subjects, metoprolol is unable to reverse the beta 2 -mediated vasodilating effects of epinephrine. This contrasts with the effect of nonselective beta-blockers, which completely reverse the vasodilating effects of epinephrine.
(2) In asthmatic patients, metoprolol reduces FEV1 and FVC significantly less than a nonselective beta-blocker, propranolol, at equivalent beta 1 -receptor blocking doses. Hypertension: The mechanism of the antihypertensive effects of beta-blocking agents has not been elucidated. However, several possible mechanisms have been proposed: (1) competitive antagonism of catecholamines at peripheral (especially cardiac) adrenergic neuron sites, leading to decreased cardiac output; (2) a central effect leading to reduced sympathetic outflow to the periphery; and (3) suppression of renin activity.
Angina Pectoris: By blocking catecholamine-induced increases in heart rate, in velocity and extent of myocardial contraction, and in blood pressure, metoprolol reduces the oxygen requirements of the heart at any given level of effort, thus making it useful in the long-term management of angina pectoris. Heart Failure: The precise mechanism for the beneficial effects of beta-blockers in heart failure has not been elucidated.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Metoprolol Succinate Extended-release Tablets USP, 100 mg are white to off-white color, round shaped, biconvex coated tablets, debossed with "566" on one side and break line on other side and are supplied as follows: NDC: 71335-1951-1: 30 Tablets in a BOTTLE NDC: 71335-1951-2: 90 Tablets in a BOTTLE NDC: 71335-1951-3: 120 Tablets in a BOTTLE NDC: 71335-1951-4: 20 Tablets in a BOTTLE NDC: 71335-1951-5: 100 Tablets in a BOTTLE NDC: 71335-1951-6: 60 Tablets in a BOTTLE NDC: 71335-1951-7: 10 Tablets in a BOTTLE Storage Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Dispense in a tight container (USP). Repackaged/Relabeled by: Bryant Ranch Prepack Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Metoprolol succinate, is a beta 1 -selective (cardioselective) adrenoceptor blocking agent, for oral administration, available as extended release tablets. Metoprolol succinate has been formulated to provide a controlled and predictable release of metoprolol for once-daily administration. The tablets comprise a multiple unit system containing metoprolol succinate extended-release tablets in a multitude of controlled release pellets.
Each pellet acts as a separate drug delivery unit and is designed to deliver metoprolol continuously over the dosage interval. The tablets contain 23.75, 47.5, 95 and 190 mg of metoprolol succinate equivalent to 25, 50, 100 and 200 mg of metoprolol tartrate, respectively. Its chemical name is (±)1- (isopropyl amino)-3-[p-(2-methoxyethyl) phenoxy]-2-propanol succinate (2:1) (salt).
Its structural formula is: Metoprolol succinate, USP is a white to off white powder with a molecular weight of 652.8. It is freely soluble in water; soluble in methanol; sparingly soluble in alcohol and slightly soluble in isopropyl alcohol. Each metoprolol succinate extended-release tablet intended for oral administration contains metoprolol succinate equivalent to 25 mg, 50 mg, 100 mg or 200 mg of metoprolol tartrate.
In addition, each tablet contains the following inactive ingredients: Colloidal silicon dioxide, croscarmellose sodium, ethyl cellulose, glycerin, hypromellose, magnesium stearate, methyl cellulose, microcrystalline cellulose, polyethylene glycol, povidone and talc. Additionally, each metoprolol succinate extended-release tablets contain opadry II white 03B28796 which contains hypromellose, polyethylene glycol and titanium dioxide. Meets USP Dissolution Test 4.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to take metoprolol succinate extended-release tablets regularly and continuously, as directed, preferably with or immediately following meals. If a dose is missed, the patient should take only the next scheduled dose (without doubling it). Patients should not interrupt or discontinue metoprolol succinate extended-release tablets without consulting the physician.
Advise patients (1) to avoid operating automobiles and machinery or engaging in other tasks requiring alertness until the patient's response to therapy with metoprolol succinate extended-release tablets has been determined; (2) to contact the physician if any difficulty in breathing occurs; (3) to inform the physician or dentist before a type of surgery that he or she is taking metoprolol succinate extended-release tablets. Heart failure patients should be advised to consult their physician if they experience signs or symptoms of worsening heart failure such as weight gain or increasing shortness of breath.
Risk of hypoglycemia Inform patients or caregivers that there is a risk of hypoglycemia when metoprolol succinate extended-release tablets are given to patients who are fasting or who are vomiting. Instruct patients or caregivers how to monitor for signs of hypoglycemia. [see Warnings and Precautions ( 5.7 )]. Manufactured by: Zydus Lifesciences Ltd., Ahmedabad, India Distributed by: Zydus Pharmaceuticals (USA) Inc.
Pennington, NJ 08534 Rev.: 10/23