
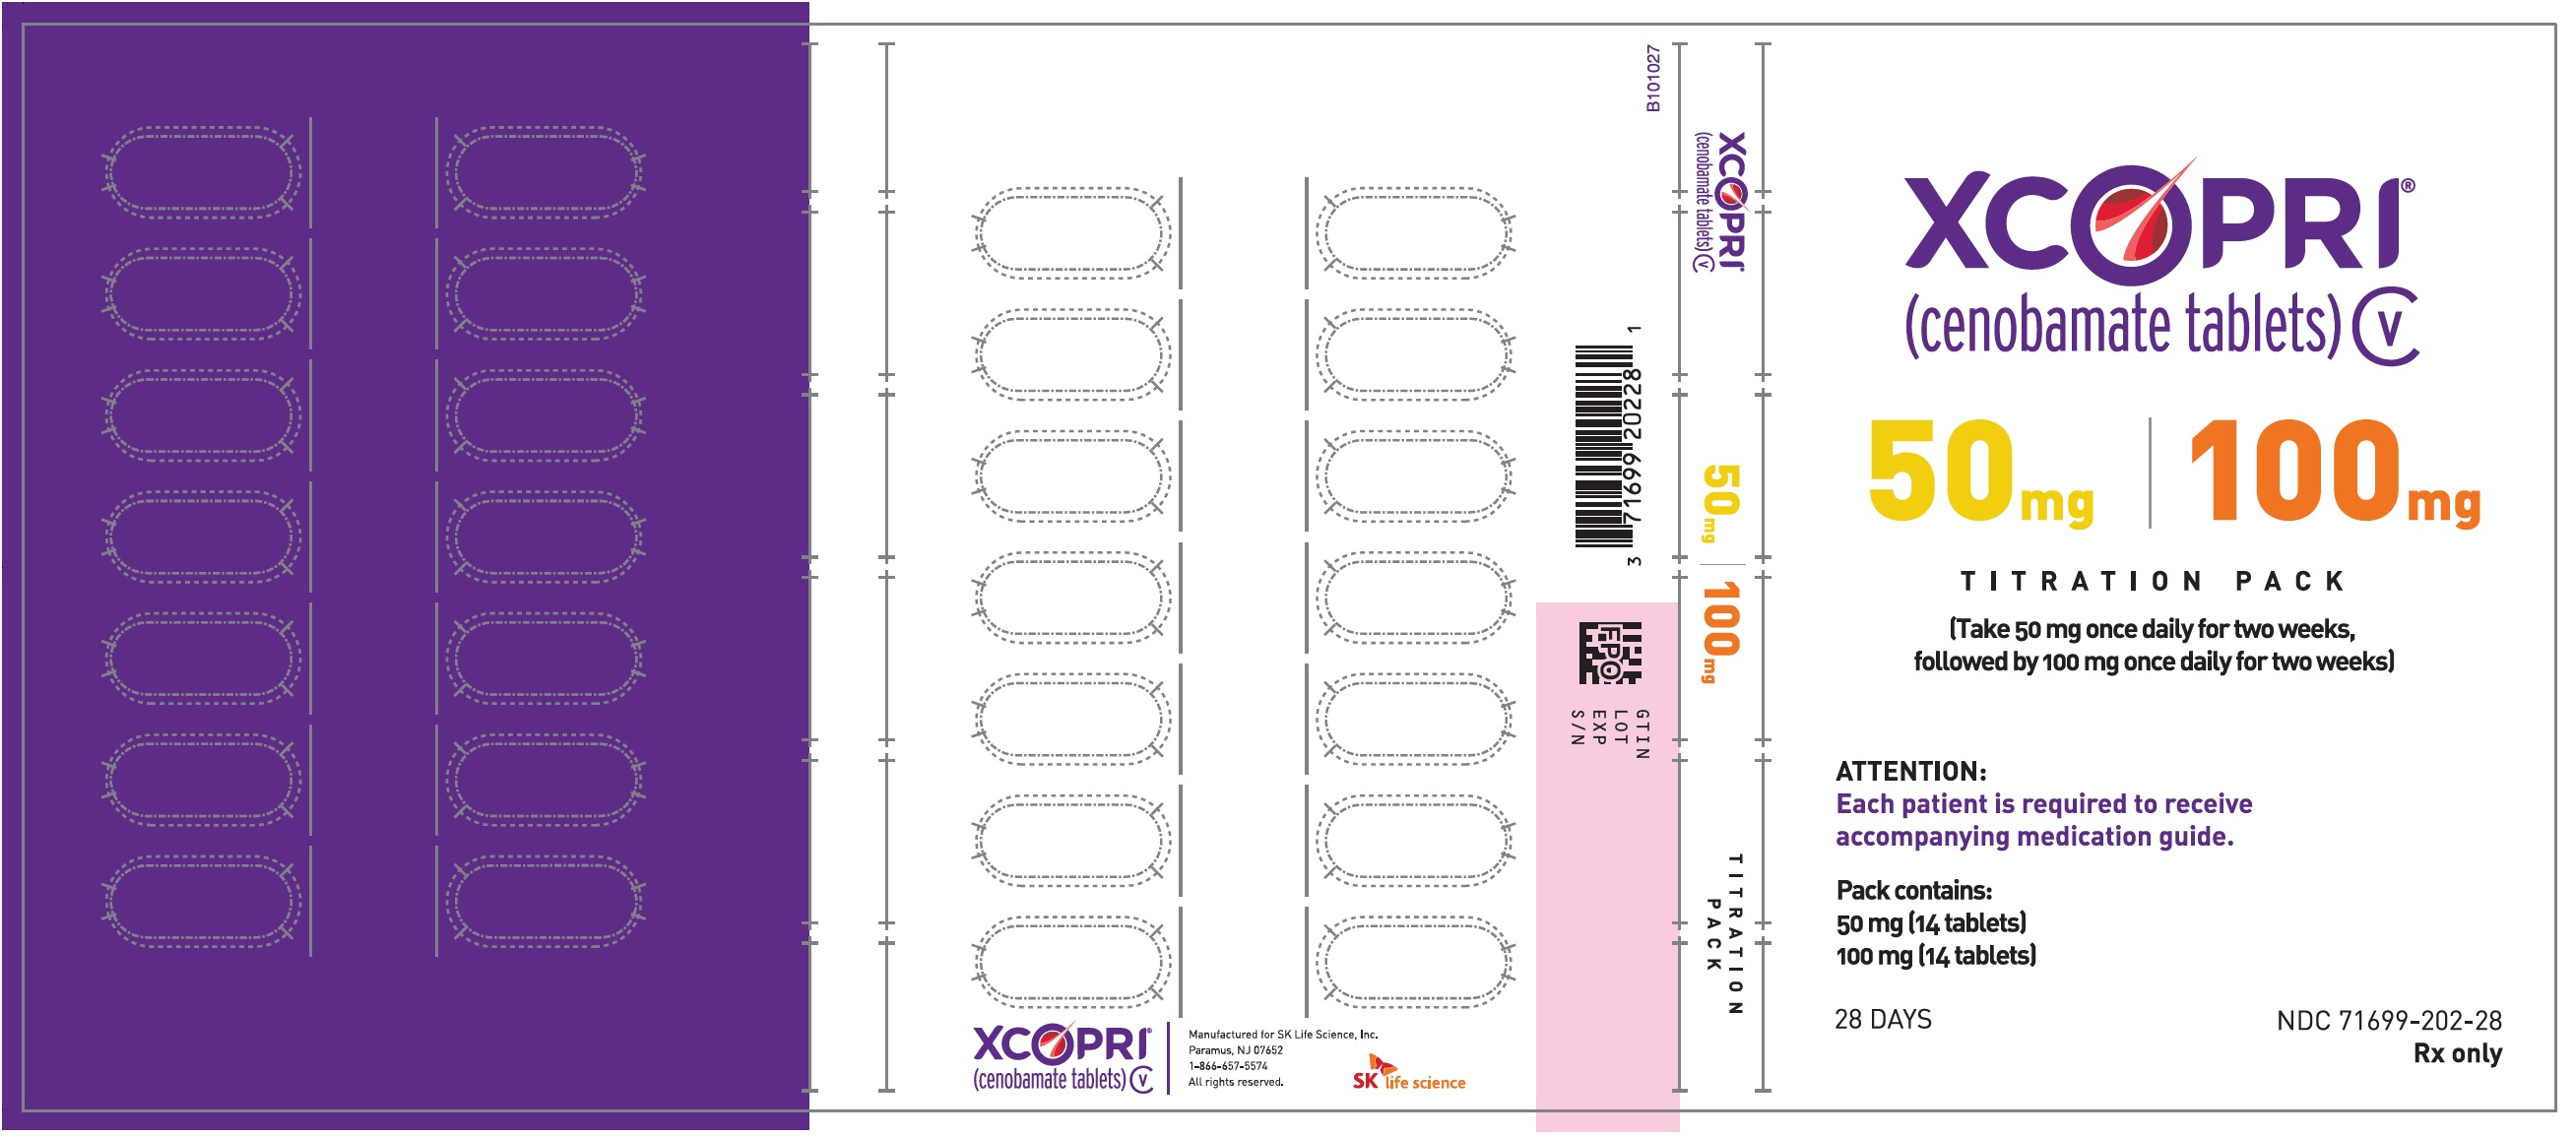
Xcopri Titration Pack cenobamate Kit — NDC 71699-202-28 (Billing 71699-0202-28)
This is a package of Xcopri Titration Pack cenobamate Kit from SK Life Science, Inc., marketed since Mar 2020 and currently FDA-listed; retail pharmacies pay about $42.71 per unit (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 71699-202-28 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 71699 labeler · 202 product · 28 package
- Package marketed since
- Mar 12, 2020
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC)
- 0371699025309, 0371699050998, 0371699150308, 0371699200300 +3 more
- Medicaid fills, this package
- 2,809 prescriptions in the last four reported quarters
- FDA record last changed
- Sep 10, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 080536
- GCN: 47413
- HICL (First Databank): 046241
- AHFS class code: 28:12.24.00
- RxCUI (RxNorm): 2265695
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Other antiepileptics class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Cenobamate, sold as Xcopri, treats partial-onset seizures in adults. These are seizures that begin in one part of the brain. Your prescriber will tailor how you use it.
- Raising the dose slowly lowers the chance of a serious allergic reaction called DRESS. Cases, including one death, happened with fast increases. Please stick to the schedule your p...
- Sleepiness, dizziness, tiredness, double vision, and headache are the most common. Be careful with driving until you know how it affects you. Call your doctor if these are hard to...
- Call for fever with a rash, swollen glands, or facial swelling. Also call for yellow skin or eyes, dark urine, upper right belly pain, or unexplained nausea and vomiting. Tell them...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cenobamate — tap one for details:
Cenobamate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $42.715 | — |
| Medicaid paysCMS SDUD · 12 mo | $1,179.77 | — |
| Medicare drug plans payPart D · Q2 2026 | $42.94 | — |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 71699-0202-28 You're viewing this Main listing | 1 KIT in 1 CARTON * 1 TABLET, FILM COATED in 1 BLISTER PACK * 1 TABLET, FILM COATED in 1 BLISTER PACK | 2020-03-12 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Xcopri Titration Pack 71699-0201-28 | SK | 1 tablet | $3.910 | — | Availability likely | save 91% |
| Xcopri Maintenance Pack 71699-0104-56 | SK | 1 tablet | $21.369 | — | Availability likely | save 50% |
| Xcopri Maintenance Pack 71699-0103-56 | SK | 1 tablet | $42.699 | — | Availability likely | +0% |
| Xcopri Titration Packthis 71699-0202-28 | SK | 1 tablet | $42.715 | — | Availability likely | — |
| Xcopri Titration Pack 71699-0203-28 | SK | 1 tablet | $42.910 | — | Availability likely | +0% |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11654133 ↗ | Method of use | U-3610 | Jun 16, 2039 |
| US 11654133 ↗ | Method of use | U-3610 | Jun 16, 2039 |
| US 11654133 ↗ | Method of use | U-3610 | Jun 16, 2039 |
| US 11654133 ↗ | Method of use | U-3610 | Jun 16, 2039 |
| US 11654133 ↗ | Method of use | U-3610 | Jun 16, 2039 |
| US 11654133 ↗ | Method of use | U-3610 | Jun 16, 2039 |
| US 7598279 ↗ | Drug substance | — | Oct 30, 2032 |
| US 7598279 ↗ | Drug substance | — | Oct 30, 2032 |
| US 7598279 ↗ | Drug substance | — | Oct 30, 2032 |
| US 7598279 ↗ | Drug substance | — | Oct 30, 2032 |
| US 7598279 ↗ | Drug substance | — | Oct 30, 2032 |
| US 7598279 ↗ | Drug substance | — | Oct 30, 2032 |
Is there a generic version of XCOPRI 50-100 MG TITRATION PAK?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from SK Life Science, Inc. labeler code 71699
- Xcopri cenobamate 100 mg Tablet, Film Coated NDC 71699-100-30
- Xcopri Maintenance Pack cenobamate Kit NDC 71699-103-56
- Xcopri Maintenance Pack cenobamate Kit NDC 71699-104-56
- Xcopri cenobamate 150 mg Tablet, Film Coated NDC 71699-150-30
- Xcopri cenobamate 200 mg Tablet, Film Coated NDC 71699-200-30
- Xcopri Titration Pack cenobamate Kit NDC 71699-201-28
- Xcopri Titration Pack cenobamate Kit NDC 71699-203-28
- Xcopri cenobamate 12.5 mg Tablet NDC 71699-204-14
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE XCOPRI is indicated for the treatment of partial-onset seizures in adult patients. XCOPRI is indicated for the treatment of partial-onset seizures in adult patients. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Prior to initiating XCOPRI, obtain serum transaminases (ALT and AST) and total bilirubin, if not recently available (i.e., within 3 months), to establish baseline liver function. ( 2.1 , 5.4 ) The recommended initial dosage of XCOPRI is 12.5 mg once daily, titrated to the recommended maintenance dosage of 200 mg once daily. The recommended titration schedule should not be exceeded.
The maximum dosage is 400 mg once daily. ( 2.2 ) Hepatic impairment: For patients with mild or moderate hepatic impairment, the maximum recommended dosage is 200 mg once daily. ( 2.3 , 8.7 , 12.3 ) XCOPRI can be taken whole or the tablets can be crushed.
The crushed tablet can be mixed with water and either administered by mouth as an oral suspension or administered via a nasogastric tube. ( 2.4 )
2.1Assessments Prior to Initiating XCOPRI Liver Function Tests Prior to initiating XCOPRI, obtain serum transaminases (ALT and AST) and total bilirubin, if not recently available (i.e., within 3 months), to establish baseline liver function [see Warnings and Precautions ( 5.4 )] . For patients with baseline hepatic impairment, dosage modifications are recommended [see Dosage and Administration ( 2.3 )] .
2.2Recommended Dosage Monotherapy and Adjunctive Therapy XCOPRI is administered orally once daily with or without food. The recommended dosage and titration, which should not be exceeded because of the potential for serious adverse reactions [see Warnings and Precautions ( 5.2 )] , is included in Table 1 . Table 1: Recommended Dosage for Partial-Onset Seizures in Adults Initial Dosage Week 1 and 2 12.5 mg once daily Titration Regimen Week 3 and 4 25 mg once daily Week 5 and 6 50 mg once daily Week 7 and 8 100 mg once daily Week 9 and 10 150 mg once daily Maintenance Dosage Week 11 and thereafter 200 mg once daily Maximum Dosage If needed based on clinical response and tolerability, dose may be increased above 200 mg by increments of 50 mg once daily every two weeks to 400 mg.
400 mg once daily
2.3Recommended Dosage in Patients with Hepatic Impairment For patients with mild to moderate (Child-Pugh Class A to B) hepatic impairment, the maximum recommended dosage is 200 mg once daily [see Use in Specific Populations ( 8.7 )] . XCOPRI is not recommended for use in patients with severe (Child-Pugh Class C) hepatic impairment [see Dosage and Administration ( 2.1 ) and see Clinical Pharmacology ( 12.3 )] .
2.4Administration Instructions XCOPRI can be taken whole or the tablets can be crushed. The crushed tablet can be mixed with water and either administered by mouth as an oral suspension or administered via a nasogastric tube, as described below [see Clinical Pharmacology ( 12.3 )]. Administration of Crushed Tablets by Mouth as Oral Suspension Crush the appropriate number of tablet(s) for the prescribed dose.
In a cup, combine the crushed tablet(s) and 25 mL of water. Swirl to suspend the crushed tablet(s). Drink the suspension immediately.
Do not store the tablet-water mixture for later use. To ensure no tablet residue is left in the container, rinse the container with 25 mL of water and drink. Visually confirm that no particles are left in the container.
If particles remain, repeat step 5. Administration of Crushed Tablets via Nasogastric (NG) Tube Crush the appropriate number of tablet(s) for the prescribed dose. In an appropriate container, combine the crushed tablet(s) and 25 mL of water.
Swirl to suspend the crushed tablet(s). Ensuring no particles are left in the container, instill the suspension with a syringe into the NG tube. Refill the catheter-tip syringe again with 10 mL of water, swirl gently, and administer.
Visually confirm that no particles are left in the syringe. If particles remain, repeat step 5.
2.5Discontinuation of XCOPRI If XCOPRI is discontinued, the dosage should be gradually reduced over a period of at least 2 weeks, unless safety concerns require abrupt withdrawal [see Warnings and Precautions ( 5.1 ,… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS XCOPRI tablets are available in the following strengths, shapes, colors, and tablet markings (Table 2). Table 2: XCOPRI Tablet Presentations Tablet Strength Tablet Color/Shape Tablet Markings 12.5 mg Uncoated round white to off-white tablets SK on one side and 12 on the other side 25 mg Film coated round brown tablets SK on one side and 25 on the other side 50 mg Film coated round yellow tablets SK on one side and 50 on the other side 100 mg Film coated round brown tablets SK on one side and 100 on the other side 150 mg Film coated round light orange tablets SK on one side and 150 on the other side 200 mg Film coated modified oval light orange tablets SK on one side and 200 on the other side Tablets: 12.5 mg, 25 mg, 50 mg, 100 mg, 150 mg, and 200 mg.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS XCOPRI is contraindicated in patients with: Hypersensitivity to cenobamate or any of the inactive ingredients in XCOPRI [see Warnings and Precautions ( 5.1 ) and Description ( 11 )] Familial Short QT syndrome [see Warnings and Precautions ( 5.2 )] Hypersensitivity to cenobamate or any of the inactive ingredients in XCOPRI. ( 4 ) Familial Short QT syndrome. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multi-Organ Hypersensitivity: Discontinue if no alternate etiology. ( 5.1 ) QT Shortening: Use caution when administering XCOPRI with other drugs that shorten the QT interval ( 5.2 ) Suicidal Behavior and Ideation: Monitor patients for suicidal behavior and ideation. ( 5.3 ) Liver Injury: Clinically significant liver injury has occurred.
Obtain serum transaminases (ALT and AST) and total bilirubin before initiating XCOPRI, and during treatment if clinically indicated. Discontinue XCOPRI in patients with evidence of liver injury in the absence of an alternative etiology. ( 5.4 ) Neurological Adverse Reactions: Monitor for somnolence and fatigue and advise patients not to drive or operate machinery until they have gained sufficient experience on XCOPRI.
Concomitant use with other CNS depressants or alcohol may have additive effects. ( 5.5 ) Withdrawal of Antiepileptic Drugs: XCOPRI should be gradually withdrawn to minimize the potential of increased seizure frequency. ( 5.6 )
5.1Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), also known as multiorgan hypersensitivity, has been reported in patients taking XCOPRI. DRESS has occurred, including one fatality, when XCOPRI was titrated rapidly (weekly or faster titration). No cases of DRESS were reported in an open-label safety study of 1339 partial-onset seizure patients when XCOPRI was initiated at 12.5 mg once daily and titrated every two weeks.
This finding does not establish that the risk of DRESS is prevented by a slower titration; however, XCOPRI should be initiated at 12.5 mg once daily and titrated every two weeks [see Dosage and Administration ( 2.2 )] . DRESS typically, although not exclusively, presents with fever, rash, lymphadenopathy, and/or facial swelling, in association with other organ system involvement, such as hepatitis, nephritis, hematological abnormalities, myocarditis, or myositis sometimes resembling an acute viral infection. Eosinophilia is often present.
This disorder is variable in its expression, and other organ systems not noted here may be involved. It is important to note that early manifestations of hypersensitivity, such as fever or lymphadenopathy, may be present even though rash is not evident. If such signs or symptoms are present, the patient should be evaluated immediately.
XCOPRI should be discontinued immediately and not restarted if an alternative etiology for the signs or symptoms cannot be established [see Contraindications ( 4 )] .
5.2QT Shortening In a placebo-controlled study of the QT interval, a higher percentage of subjects who took XCOPRI (31% at 200 mg and 66% at 500 mg) had a QT shortening of greater than 20 msec compared to placebo (6-17%). Reductions of the QTc interval below 300 msec were not observed [see Clinical Pharmacology ( 12.2 )] . Familial Short QT syndrome is associated with an increased risk of sudden death and ventricular arrhythmias, particularly ventricular fibrillation.
Such events in this syndrome are believed to occur primarily when the corrected QT interval falls below 300 msec. Nonclinical data also indicate that QT shortening is associated with ventricular fibrillation. Patients with Familial Short QT syndrome should not be treated with XCOPRI [see Contraindications ( 4 )] .
Caution should be used when administering XCOPRI and other drugs that shorten the QT interval as there may be a synergistic effect on the QT interval that would increase the QT shortening risk.
5.3Suicidal Behavior and Ideation Antiepileptic drugs (AEDs), including XCOPRI, increase the risk of suicidal thoughts or behavior in patients taking these drugs for any indication. Patients treated with any AED for any indication should be monitored for the emergence or worsening of depression, suicidal thoughts or behavior, and/or any unusual changes i… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described in more detail in the Warnings and Precautions section of the labeling: Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions ( 5.1 )] QT Shortening [see Warnings and Precautions ( 5.2 )] Suicidal Behavior and Ideation [see Warnings and Precautions ( 5.3 )] Liver Injury [see Warnings and Precautions ( 5.4 )] Neurological Adverse Reactions [see Warnings and Precautions ( 5.5 )] Withdrawal of Antiepileptic Drugs [see Warnings and Precautions ( 5.6 )] The most common adverse reactions in patients receiving XCOPRI (at least 10% for XCOPRI and more frequently than placebo) include somnolence, dizziness, fatigue, diplopia, and headache.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact SK Life Science, Inc. at 1-866-657-5574 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions and for varying durations, adverse reaction frequencies observed in the clinical trials of a drug cannot be directly compared with frequencies in the clinical trials of another drug and may not reflect the frequencies observed in practice. In all controlled and uncontrolled trials performed in adult partial-onset seizure patients, XCOPRI was administered as adjunctive therapy to 1944 patients. Of these patients, 1575 were treated for at least 6 months, 710 for at least 12 months, 349 for at least 24 months, and 320 for at least 36 months.
A total of 658 patients (442 patients treated with XCOPRI and 216 patients treated with placebo) constituted the safety population in the pooled analysis of placebo-controlled studies in patients with partial-onset seizures (Studies 1 and 2) [see Clinical Studies ( 14 )] . The adverse reactions presented in Table 4 are based on this safety population; the median length of treatment in these studies was 18 weeks. Of the patients in those studies, approximately 49% were male, 76% were Caucasian, and the mean age was 39 years.
In Study 1 and Study 2, adverse events occurred in 77% of patients treated with XCOPRI and 68% treated with placebo. Table 4 gives the incidence of adverse reactions that occurred in subjects with partial-onset seizures in any XCOPRI treatment group and for which the incidence was greater than placebo during the controlled clinical trials. The most common adverse reactions that occurred in XCOPRI-treated patients (incidence at least 10% and greater than placebo) were somnolence, dizziness, fatigue, diplopia, and headache.
The discontinuation rates because of adverse events were 11%, 9%, and 21% for patients randomized to receive XCOPRI at doses of 100 mg/day, 200 mg/day, and 400 mg/day, respectively, compared to 4% in patients randomized to receive placebo. The adverse reactions most commonly (1% or greater in any XCOPRI treatment group, and greater than placebo) leading to discontinuation, in descending order of frequency, were ataxia, dizziness, somnolence, diplopia, nystagmus, and vertigo. Table 4: Adverse Reactions in Pooled Placebo-Controlled Adjunctive Therapy Studies in Patients with Partial-Onset Seizures with XCOPRI Frequency in Any Treatment Arm Greater Than 1% Over Placebo * Reported as an adverse reaction; see Laboratory Abnormalities for ALT changes from collected laboratory values Adverse Reaction XCOPRI Placebo 100mg 200mg 400mg n = 108 % n= 223 % n=111 % n=216 % Cardiac Disorders Palpitations 0 0 2 0 Ear and Labyrinth Disorders Vertigo 1 1 6 1 Eye Disorders Diplopia 6 7 15 2 Vision Blurred 2 2 4 0 Gastrointestinal Disorders Nausea 6 6 9 3 Constipation 2 4 8 0 Diarrhea 1 3 5 0 Vomiting 2 4 5 0 Dry Mouth 1 1 3 0 Abdominal Pain 2 2 1 0 Dyspepsia 2 2 0 0 Infections and Infestations Nasopharyngitis 2 4 5 3 Pharyngitis 1 2 0 0 Urinary Tract Infection 2 5 0 2 Injury, Poisoning and Procedural Complications Head Injury 1 0 2 0 Investigations Alanine Aminotrans… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Phenytoin: Gradually decrease phenytoin dosage by up to 50%. ( 7.1 ) Phenobarbital and Clobazam: Reduce dosage as needed when used concomitantly with XCOPRI. ( 7.1 ) Lamotrigine, Carbamazepine: Increase dosage as needed when used concomitantly with XCOPRI.
( 7.1 ) CYP2B6 and CYP3A Substrates: Increase dosage as needed when used concomitantly with XCOPRI. ( 7.1 ) CYP2C19 Substrates: Reduce dosage as needed when used concomitantly with XCOPRI. ( 7.1 ) Oral Contraceptives: Effectiveness of hormonal oral contraceptives may be reduced when administered concomitantly with XCOPRI.
Women should use additional or alternative non-hormonal birth control. ( 7.1 )
7.1Effect of XCOPRI on Other Drugs Table 5 summarizes the effect of XCOPRI on other drugs [see Clinical Pharmacology ( 12.3 )] . Table 5: Pharmacokinetic Drug Interactions Drug or Substrate Type Effect of XCOPRI on Drug or Substrate Clinical Recommendation Antiepileptic Drugs lamotrigine ↓ plasma concentrations Because of a potential for reduced efficacy of these drugs, increase the dosage of lamotrigine or carbamazepine, as needed, when used concomitantly with XCOPRI. carbamazepine ↓ plasma concentrations phenytoin ↑ plasma concentrations Because of a potential 2-fold increase in phenytoin levels, gradually decrease phenytoin dosage by up to 50% as XCOPRI is being titrated. phenobarbital ↑ plasma concentrations Because of a potential for an increase in the risk of adverse reactions from these drugs, consider a reduction in dosage of phenobarbital or clobazam, as clinically appropriate, when used concomitantly with XCOPRI. desmethylclobazam, the active metabolite of clobazam ↑ plasma concentrations CYP2B6 Substrates ↓ plasma concentrations Because of a potential for reduced efficacy of these drugs, increase the dosage of CYP2B6 or CYP3A4 substrates, as needed, when used concomitantly with XCOPRI.
CYP3A Substrates ↓ plasma concentrations Oral contraceptives ↓ plasma concentrations Because of the potential for reduced efficacy of oral contraceptives, women should use additional or alternative non-hormonal birth control while taking XCOPRI. CYP2C19 Substrates ↑ plasma concentrations Because of a potential for an increase in the risk of adverse reactions from these drugs, consider a reduction in dosage of CYP2C19 substrates, as clinically appropriate, when used concomitantly with XCOPRI.
7.2Drug that Shorten the QT Interval XCOPRI can shorten the QT interval; therefore, caution should be used when administering XCOPRI and other drugs that shorten the QT interval [see Warnings and Precautions ( 5.2 ) and Clinical Pharmacology ( 12.2 )].
7.3CNS Depressants and Alcohol Concomitant use of XCOPRI with other CNS depressants, including alcohol, may increase the risk of neurological adverse reactions, including sedation and somnolence [see Warnings and Precautions ( 5.5 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 ) Renal Impairment: Use with caution and dosage reduction may be considered in patients with mild to moderate (CLcr 30 to < 90 mL/min) and severe (CLcr < 30 mL/min) renal impairment. Use not recommended in end-stage renal disease (CLcr < 15 mL/min) undergoing dialysis.
( 8.6 ) Hepatic Impairment: Use with caution in patients with mild to moderate hepatic impairment; lower maximum dosage and additional dosage reduction may be considered. Use of XCOPRI in patients with severe hepatic impairment is not recommended. ( 2.2 , 8.7 , 12.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as XCOPRI, during pregnancy. Encourage women who are taking XCOPRI during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling the toll-free number 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary There are no adequate data on the developmental risk associated with the use of XCOPRI in pregnant women.
In animal studies, administration of cenobamate during pregnancy or throughout pregnancy and lactation resulted in adverse effects on development (increased embryofetal mortality, decreased fetal and offspring body weights, neurobehavioral and reproductive impairment in offspring) at clinically relevant drug exposures [see Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Data Animal Data Oral administration of cenobamate (0, 10, 30, or 60 mg/kg/day) to pregnant rats during the period of organogenesis resulted in increased embryofetal mortality, reduced fetal body weights, and incomplete fetal skeletal ossification at the highest dose tested, which was associated with maternal toxicity. There was a small increase in visceral malformations at the high dose; however, teratogenic potential could not be fully evaluated because of the high rate of embryofetal deaths, which resulted in an inadequate number of fetuses examined.
Maternal plasma exposure (AUC) at the no-effect dose for adverse effects on embryofetal development (30 mg/kg/day) was less than that in humans at the maximum recommended human dose (MRHD) of 400 mg. Oral administration of cenobamate (0, 4, 12, or 36 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality at the highest dose tested, which was associated with maternal toxicity. Maternal plasma exposure at the no-effect dose (12 mg/kg/day) for adverse effects on embryofetal development was less than that in humans at the MRHD.
When cenobamate (0, 11, 22, or 44 mg/kg/day) was orally administered to female rats throughout pregnancy and lactation, neurobehavioral impairment (learning and memory deficit and increased auditory startle response) was observed in the offspring at all doses and decreased preweaning body weight gain and adverse effects on reproductive function (decreased numbers of corpora lutea, implantations, and live fetuses) were seen in the offspring at the high dose. Maternal plasma exposure at the lowest effect dose (11 mg/kg/day) for adverse effects on pre- and postnatal development was less than that in humans at the MRHD.
8.2Lactation Risk Summary There are no data available on the presence of cenobamate in human milk, the effects on the breastfed infant, or the effects of the drug on milk production. Cenobamate was present in rat milk at concentrations similar to those in maternal plasma. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for XCOPRI and any potential adverse effects on the breastfed… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), such as XCOPRI, during pregnancy. Encourage women who are taking XCOPRI during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling the toll-free number 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary There are no adequate data on the developmental risk associated with the use of XCOPRI in pregnant women.
In animal studies, administration of cenobamate during pregnancy or throughout pregnancy and lactation resulted in adverse effects on development (increased embryofetal mortality, decreased fetal and offspring body weights, neurobehavioral and reproductive impairment in offspring) at clinically relevant drug exposures [see Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Data Animal Data Oral administration of cenobamate (0, 10, 30, or 60 mg/kg/day) to pregnant rats during the period of organogenesis resulted in increased embryofetal mortality, reduced fetal body weights, and incomplete fetal skeletal ossification at the highest dose tested, which was associated with maternal toxicity. There was a small increase in visceral malformations at the high dose; however, teratogenic potential could not be fully evaluated because of the high rate of embryofetal deaths, which resulted in an inadequate number of fetuses examined.
Maternal plasma exposure (AUC) at the no-effect dose for adverse effects on embryofetal development (30 mg/kg/day) was less than that in humans at the maximum recommended human dose (MRHD) of 400 mg. Oral administration of cenobamate (0, 4, 12, or 36 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality at the highest dose tested, which was associated with maternal toxicity. Maternal plasma exposure at the no-effect dose (12 mg/kg/day) for adverse effects on embryofetal development was less than that in humans at the MRHD.
When cenobamate (0, 11, 22, or 44 mg/kg/day) was orally administered to female rats throughout pregnancy and lactation, neurobehavioral impairment (learning and memory deficit and increased auditory startle response) was observed in the offspring at all doses and decreased preweaning body weight gain and adverse effects on reproductive function (decreased numbers of corpora lutea, implantations, and live fetuses) were seen in the offspring at the high dose. Maternal plasma exposure at the lowest effect dose (11 mg/kg/day) for adverse effects on pre- and postnatal development was less than that in humans at the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Juvenile Animal Toxicity Data Cenobamate was administered orally to juvenile rats from postnatal day (PND) 7 to 70. To maintain consistent plasma drug exposures, doses were increased during the dosing period, up to 120 and 80 mg/kg/day in males and females, respectively.
Adverse effects included mortality, delayed sexual maturation, neurological (decreased grip strength) and neurobehavioral (learning and memory deficits) impairment, decreased sperm count, decreased brain weight, and ocular histopathology. Recovery from these effects was observed following discontinuation of dosing. Overall, a no-effect dose for adverse effects on postnatal development was not identified.
At the lowest doses tested, plasma cenobamate exposures (AUC) were less than that in humans at the maximum recommended human dose (MRHD) of 400 mg.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of XCOPRI did not include sufficient numbers of patients aged 65 and over to determine the safety and efficacy of XCOPRI in the elderly population. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology ( 12.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE There is limited clinical experience with XCOPRI overdose in humans. There is no specific antidote for overdose with XCOPRI. In the event of overdose, standard medical practice for the management of any overdose should be used.
An adequate airway, oxygenation and ventilation should be ensured; monitoring of cardiac rate and rhythm and vital signs is recommended. A certified poison control center should be contacted for updated information on the management of overdose with XCOPRI. There are no data on the removal of XCOPRI using dialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism by which cenobamate exerts its therapeutic effects in patients with partial-onset seizures is unknown. Cenobamate has been demonstrated to reduce repetitive neuronal firing by inhibiting voltage-gated sodium currents. It is also a positive allosteric modulator of the γ-aminobutyric acid (GABA A ) ion channel.
12.2Pharmacodynamics Interactions with Alcohol No clinically significant differences on objective attention, psychomotor performance, and memory tests, in addition to other subjective CNS tests, were observed following concomitant use of XCOPRI and ethanol (preparation of 40% ethanol in orange juice dosed at 0.7 g/kg for males and 0.57 g/kg for females) in healthy subjects. Cardiac Electrophysiology In a placebo-controlled QT study in healthy volunteers, dose-dependent shortening of the QTcF interval has been observed with XCOPRI [see Warnings and Precautions ( 5.2 )] .
The mean ΔΔQTc is -11 [-13, -8] msec for 200 mg once daily and -18 [-22, -15] msec for 500 mg once daily (1.25 times the maximum recommended dosage). A higher percentage of XCOPRI-treated subjects (31% at 200 mg and 66% at 500 mg) had a QT shortening of greater than 20 msec compared to placebo (6-17%). Reductions of the QTc interval below 300 msec were not observed.
12.3Pharmacokinetics Cenobamate AUC increases in a greater than dose-proportional manner following single oral doses from 5 to 750 mg (0.0125 to 1.88 times the maximum recommended dosage). Cenobamate C max increases in a dose proportional manner. Steady-state plasma concentrations are attained after approximately two weeks of once daily dosing.
The pharmacokinetics of cenobamate are similar when used as monotherapy or as adjunctive therapy for the treatment of partial-onset seizures, except plasma cenobamate multiple-dose exposure (C max , AUC) decreased with co-administration of phenytoin by 27-28%. Absorption At least 88% of XCOPRI is absorbed following oral administration, with median T max ranging from 1 to 4 hours. Plasma C max and AUC for XCOPRI crushed tablets mixed in water, administered either orally or through a nasogastric tube, were similar to whole tablets.
The median T max for crushed tablets is 0.5 hours. Effect of Food No clinically significant differences in cenobamate pharmacokinetics were observed following administration of a high-fat meal (800 -1000 calories with 50% fat). Distribution The apparent volume of distribution (Vd/F) of cenobamate after oral administration of XCOPRI is approximately 40-50 L.
Plasma protein binding of cenobamate is 60% and independent of concentration in vitro . Cenobamate primarily binds with human albumin protein. Elimination The apparent terminal half-life of cenobamate is 50-60 hours and apparent oral clearance is approximately 0.45-0.63 L/hour over a dose range from 100 mg/day to 400 mg/day.
Metabolism Cenobamate is extensively metabolized. The primary metabolic pathways are by glucuronidation via UGT2B7 and to a lesser extent by UGT2B4, and by oxidation via CYP2E1, CYP2A6, CYP2B6, and to a lesser extent by CYP2C19 and CYP3A4/5. Following administration of radiolabeled cenobamate, unchanged cenobamate accounted for greater than 98% of the total AUC of radioactivity in plasma.
Unchanged cenobamate accounted for 6.8% of the dose which was mainly excreted in the urine (6.4%). Excretion Following administration of radiolabeled cenobamate, a mean of 93.0% of the total radioactive dose was recovered in urine (87.8%) and feces (5.2%). More than 50% of the radioactivity was excreted within 72 hours of dosing.
Specific Populations No clinically significant differences in the pharmacokinetics of cenobamate were observed based on age based on data from subjects age 18 years to 77 years, sex, or race/ethnicity based on data from subjects categorized as Asian, Black, Caucasian, Hispanic, or Other. Patients with Renal Impairment Cenobamate plasma AUC was 1.4 fold to 1.5 fold higher i… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism by which cenobamate exerts its therapeutic effects in patients with partial-onset seizures is unknown. Cenobamate has been demonstrated to reduce repetitive neuronal firing by inhibiting voltage-gated sodium currents. It is also a positive allosteric modulator of the γ-aminobutyric acid (GABA A ) ion channel.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied XCOPRI tablets are supplied in the following configurations: Bottles; 30 count Strength NDC Number Tablet Description (Color, Shape, Markings) 25 mg 71699-025-30 Film coated round brown tablets with SK on one side and 25 on the other side 50 mg 71699-050-30 Film coated round yellow tablets with SK on one side and 50 on the other side 100 mg 71699-100-30 Film coated round brown tablets with SK on one side and 100 on the other side 150 mg 71699-150-30 Film coated round light orange tablets with SK on one side and 150 on the other side 200 mg 71699-200-30 Film coated modified oval light orange tablets with SK on one side and 200 on the other side Titration Blister Packs; 14-Day Daily Dose NDC Number Supplied As [strength(quantity)] Tablet Description (Color, Shape, Markings) 12.5 mg per day for 14 days 71699-204-14 12.5 mg (14-count) Uncoated round white to off-white tablets with SK on one side and 12 on the other side Titration Blister Packs; 28-Day Daily Dose NDC Number Supplied As [strength(quantity)] Tablet Description (Color, Shape, Markings) 12.5 mg per day for 14 days, then 25 mg per day for 14 days 71699-201-28 12.5 mg (14-count) Uncoated round white to off-white tablets with SK on one side and 12 on the other side 25 mg (14-count) Film coated round brown tablets with SK on one side and 25 on the other side 50 mg per day for 14 days, then 100 mg per day for 14 days 71699-202-28 50 mg (14-count) Film coated round yellow tablets with SK on one side and 50 on the other side 100 mg (14-count) Film coated round brown tablets with SK on one side and 100 on the other side 150 mg per day for 14 days, then 200 mg per day for 14 days 71699-203-28 150 mg (14-count) Film coated round light orange tablets with SK on one side and 150 on the other side 200 mg (14-count) Film coated modified oval light orange tablets with SK on one side and 200 on the other side Maintenance Blister Packs; 28-Day Daily Dose NDC Number Supplied As [strength(quantity)] Tablet Description (Color, Shape, Markings) 250 mg per day 71699-104-56 100 mg (28-count) Film coated round brown tablets with SK on one side and 100 on the other side 150 mg (28-count) Film coated round light orange tablets with SK on one side and 150 on the other side 350 mg per day 71699-103-56 150 mg (28-count) Film coated round light orange tablets with SK on one side and 150 on the other side 200 mg (28-count) Film coated modified oval light orange tablets with SK on one side and 200 on the other side
16.2Storage and Handling Store XCOPRI tablets at 20°C to 25°C (68°F to 77°F) with excursions permitted to 15°C to 30°C (59°F to 86°F) (See USP Controlled Room Temperature) .
📦 Storage and Handling ▾
16.1How Supplied XCOPRI tablets are supplied in the following configurations: Bottles; 30 count Strength NDC Number Tablet Description (Color, Shape, Markings) 25 mg 71699-025-30 Film coated round brown tablets with SK on one side and 25 on the other side 50 mg 71699-050-30 Film coated round yellow tablets with SK on one side and 50 on the other side 100 mg 71699-100-30 Film coated round brown tablets with SK on one side and 100 on the other side 150 mg 71699-150-30 Film coated round light orange tablets with SK on one side and 150 on the other side 200 mg 71699-200-30 Film coated modified oval light orange tablets with SK on one side and 200 on the other side Titration Blister Packs; 14-Day Daily Dose NDC Number Supplied As [strength(quantity)] Tablet Description (Color, Shape, Markings) 12.5 mg per day for 14 days 71699-204-14 12.5 mg (14-count) Uncoated round white to off-white tablets with SK on one side and 12 on the other side Titration Blister Packs; 28-Day Daily Dose NDC Number Supplied As [strength(quantity)] Tablet Description (Color, Shape, Markings) 12.5 mg per day for 14 days, then 25 mg per day for 14 days 71699-201-28 12.5 mg (14-count) Uncoated round white to off-white tablets with SK on one side and 12 on the other side 25 mg (14-count) Film coated round brown tablets with SK on one side and 25 on the other side 50 mg per day for 14 days, then 100 mg per day for 14 days 71699-202-28 50 mg (14-count) Film coated round yellow tablets with SK on one side and 50 on the other side 100 mg (14-count) Film coated round brown tablets with SK on one side and 100 on the other side 150 mg per day for 14 days, then 200 mg per day for 14 days 71699-203-28 150 mg (14-count) Film coated round light orange tablets with SK on one side and 150 on the other side 200 mg (14-count) Film coated modified oval light orange tablets with SK on one side and 200 on the other side Maintenance Blister Packs; 28-Day Daily Dose NDC Number Supplied As [strength(quantity)] Tablet Description (Color, Shape, Markings) 250 mg per day 71699-104-56 100 mg (28-count) Film coated round brown tablets with SK on one side and 100 on the other side 150 mg (28-count) Film coated round light orange tablets with SK on one side and 150 on the other side 350 mg per day 71699-103-56 150 mg (28-count) Film coated round light orange tablets with SK on one side and 150 on the other side 200 mg (28-count) Film coated modified oval light orange tablets with SK on one side and 200 on the other side
16.2Storage and Handling Store XCOPRI tablets at 20°C to 25°C (68°F to 77°F) with excursions permitted to 15°C to 30°C (59°F to 86°F) (See USP Controlled Room Temperature) .
📋 Description ▾
11 DESCRIPTION The chemical name of XCOPRI (cenobamate) is [(1 R )-1-(2-Chlorophenyl)-2-(tetrazol-2-yl) ethyl] carbamate. Its molecular formula is C 10 H 10 ClN 5 O 2 and its molecular weight is 267.67 g/mol. The chemical structure is: Cenobamate is a white to off-white crystalline powder.
It is slightly soluble in aqueous solutions (water 1.7 mg/mL) and has higher solubility in organic solvents like ethanol (209.4 mg/mL). XCOPRI tablets are for oral administration and contain the following inactive ingredients: colloidal silicon dioxide, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and sodium starch glycolate and film coating agents specified below: 12.5 mg tablets: Not applicable, since 12.5 mg tablets are uncoated. 25 mg and 100 mg tablets: FD&C Blue# 2/indigo carmine aluminum lake, iron oxide red, iron oxide yellow, polyethylene glycol 3350, polyvinyl alcohol-part hydrolyzed, talc, and titanium dioxide.
50 mg tablets: iron oxide yellow, polyethylene glycol 3350, polyvinyl alcohol-part hydrolyzed, talc, and titanium dioxide. 150 mg and 200 mg tablets: iron oxide red, iron oxide yellow, polyethylene glycol 3350, polyvinyl alcohol-part hydrolyzed, talc, and titanium dioxide. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). DRESS/Multi-organ Hypersensitivity Instruct patients and caregivers that a fever or rash associated with signs of other organ system involvement (e.g., lymphadenopathy, hepatic dysfunction) may be drug-related and should be reported to their healthcare provider immediately. XCOPRI should be discontinued immediately if a serious hypersensitivity reaction is suspected [see Warnings and Precautions ( 5.1 )] .
QT Shortening Instruct patients to inform their healthcare provider of all of the medications, over-the-counter medications, and herbal supplements that they are taking. Instruct patients to notify their healthcare provider if they have any symptoms of shortening of the QT interval, including prolonged heart palpitations or a loss of consciousness [see Warnings and Precautions ( 5.2 )] . Suicidal Behavior and Ideation Counsel patients, their caregivers, and/or families that antiepileptic drugs, including XCOPRI, may increase the risk of suicidal thoughts and behavior, and advise patients to be alert for the emergence or worsening of symptoms of depression; unusual changes in mood or behavior; or suicidal thoughts, behavior, or thoughts about self-harm.
Advise patients, their caregivers, and/or families to report behaviors of concern immediately to a healthcare provider [see Warnings and Precautions ( 5.3 )] . Liver Injury: Inform patients that liver injury has been reported with XCOPRI. Instruct patients treated with XCOPRI to promptly report any symptoms that may indicate liver injury, including unexplained nausea, vomiting, right upper quadrant abdominal pain, fatigue, anorexia, jaundice, or dark urine.
Discuss with patients that a blood test should be obtained before they start therapy if one has not been done within the prior 3 months, and that blood tests will be obtained during treatment if clinically indicated [see Warnings and Precautions ( 5.4 )]. Neurological Adverse Reactions Counsel patients that XCOPRI causes somnolence, fatigue, dizziness, and gait disturbance. These adverse reactions, if observed, are more likely to occur early in treatment but can occur at any time.
Advise patients not to drive or operate machinery until they have gained sufficient experience on XCOPRI to gauge whether it adversely affects their ability to drive or operate machinery and that other CNS depressants or alcohol may have additive effects [see Warnings and Precautions ( 5.5 )] . Withdrawal of XCOPRI Advise patients not to discontinue use of XCOPRI without consulting with their healthcare provider. XCOPRI should normally be gradually withdrawn to reduce the potential for increased seizure frequency and status epilepticus [see Warnings and Precautions ( 5.6 )] .
Contraceptives Counsel females of reproductive potential that XCOPRI may decrease the efficacy of oral contraceptives and advise them to use additional or alternative non-hormonal birth control [see Drug Interactions ( 7.1 )] . Pregnancy Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during XCOPRI therapy. Encourage patients to enroll in the North American Antiepileptic Drug Pregnancy Registry if they become pregnant.
This registry is collecting information about the safety of antiepileptic drugs during pregnancy [see Use in Specific Populations ( 8.1 )] . Dosing Instructions Counsel patients that XCOPRI may be taken any time with or without food. Instruct patients that XCOPRI tablets can be taken whole or crushed.
The crushed tablet can be mixed with water and either administered by mouth as an oral suspension or administered via a nasogastric (NG) tube. Counsel patients administering XCOPRI as an oral suspension or via NG tube on appropriate preparation and administration instructions [see Dosage and Administration ( 2.3 )] . Abuse and Dependence Advise patients that XCOPRI is a federally controlled su… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 8/2025 MEDICATION GUIDE XCOPRI ® (ex-koh-pree) (cenobamate) tablets, for oral use, CV What is the most important information I should know about XCOPRI?
XCOPRI can cause serious side effects, including: Serious or life threatening allergic reactions which may affect organs and other parts of your body like the liver or blood cells. You may or may not have a rash with these types of reactions. Call your healthcare provider right away and go to the nearest emergency room if you have any of the following: swelling of your face, eyes, lips, or tongue trouble swallowing or breathing a skin rash hives fever, swollen glands, or sore throat that does not go away or comes and goes painful sores in the mouth or around your eyes yellowing of your skin or eyes unusual bruising or bleeding severe fatigue or weakness severe muscle pain frequent infections that do not go away These symptoms may be the first signs of a serious reaction.
A healthcare provider should examine you to decide if you should continue taking XCOPRI. Problems with the electrical system of the heart (QT shortening). Call your healthcare provider if you have symptoms of QT shortening including fast heartbeat (heart palpitations) that last a long time or fainting.
Like other antiepileptic drugs, XCOPRI may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood Suicidal thoughts or actions may be caused by things other than medicines.
If you have suicidal thoughts or actions, your healthcare provider may check for other causes. How can I watch for early symptoms of suicidal thoughts and actions? Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings.
Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms. Do not stop taking XCOPRI without first talking to your healthcare provider.
Stopping XCOPRI suddenly can cause serious problems. Stopping a seizure medicine suddenly can cause seizures that will not stop (status epilepticus). XCOPRI is a federally controlled substance (CV) because it can be abused or lead to dependence.
Keep XCOPRI in a safe place to prevent misuse and abuse. Tell your healthcare provider if you have ever abused or been dependent on alcohol, prescription medicines, or street drugs. Selling or giving away XCOPRI may harm others and is against the law.
What is XCOPRI? XCOPRI is a prescription medicine used to treat partial-onset seizures in adults. It is not known if XCOPRI is safe and effective in children.
Do not take XCOPRI if you: are allergic to cenobamate, any of the other ingredients in XCOPRI. See the end of this Medication Guide for a complete list of ingredients in XCOPRI. have a genetic problem (called familial short QT syndrome) that affects the electrical system of the heart. Before taking XCOPRI, tell your healthcare provider about all your medical conditions, including if you: have or had depression, mood problems, or suicidal thoughts or actions. have liver, kidney, or blood problems. have had an allergic reaction to a medicine which caused a rash or affected internal organs, like the liver or blood cells. use birth control medicine.
XCOPRI may cause your birth control medicine to be less effective. Talk to your healthcare provider about the best birth control method to use while takin… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Cenobamate AUC increases in a greater than dose-proportional manner following single oral doses from 5 to 750 mg (0.0125 to 1.88 times the maximum recommended dosage). Cenobamate C max increases in a dose proportional manner. Steady-state plasma concentrations are attained after approximately two weeks of once daily dosing.
The pharmacokinetics of cenobamate are similar when used as monotherapy or as adjunctive therapy for the treatment of partial-onset seizures, except plasma cenobamate multiple-dose exposure (C max , AUC) decreased with co-administration of phenytoin by 27-28%. Absorption At least 88% of XCOPRI is absorbed following oral administration, with median T max ranging from 1 to 4 hours. Plasma C max and AUC for XCOPRI crushed tablets mixed in water, administered either orally or through a nasogastric tube, were similar to whole tablets.
The median T max for crushed tablets is 0.5 hours. Effect of Food No clinically significant differences in cenobamate pharmacokinetics were observed following administration of a high-fat meal (800 -1000 calories with 50% fat). Distribution The apparent volume of distribution (Vd/F) of cenobamate after oral administration of XCOPRI is approximately 40-50 L.
Plasma protein binding of cenobamate is 60% and independent of concentration in vitro . Cenobamate primarily binds with human albumin protein. Elimination The apparent terminal half-life of cenobamate is 50-60 hours and apparent oral clearance is approximately 0.45-0.63 L/hour over a dose range from 100 mg/day to 400 mg/day.
Metabolism Cenobamate is extensively metabolized. The primary metabolic pathways are by glucuronidation via UGT2B7 and to a lesser extent by UGT2B4, and by oxidation via CYP2E1, CYP2A6, CYP2B6, and to a lesser extent by CYP2C19 and CYP3A4/5. Following administration of radiolabeled cenobamate, unchanged cenobamate accounted for greater than 98% of the total AUC of radioactivity in plasma.
Unchanged cenobamate accounted for 6.8% of the dose which was mainly excreted in the urine (6.4%). Excretion Following administration of radiolabeled cenobamate, a mean of 93.0% of the total radioactive dose was recovered in urine (87.8%) and feces (5.2%). More than 50% of the radioactivity was excreted within 72 hours of dosing.
Specific Populations No clinically significant differences in the pharmacokinetics of cenobamate were observed based on age based on data from subjects age 18 years to 77 years, sex, or race/ethnicity based on data from subjects categorized as Asian, Black, Caucasian, Hispanic, or Other. Patients with Renal Impairment Cenobamate plasma AUC was 1.4 fold to 1.5 fold higher in subjects with mild (CLcr 60 to less than 90 mL/min) and moderate (CLcr 30 to less than 60 mL/min) following a single oral 200 mg dose of XCOPRI compared to healthy controls.
In subjects with severe (CLcr less than 30 mL/min) renal impairment, cenobamate plasma AUC did not change significantly compared to healthy controls following single oral 100 mg dose of XCOPRI [see Use in Specific Populations ( 8.6 )] . The effect of hemodialysis on cenobamate pharmacokinetics has not been studied. Patients with Hepatic Impairment Cenobamate plasma AUC was 1.9-fold, 2.3-fold, and 4.2-fold higher in subjects with mild (5-6 points, Child-Pugh Class A), moderate (7-9 points, Child-Pugh Class B), and severe (10-15 points, Child-Pugh Class C) hepatic impairment, respectively, following a single oral 200 mg dose of XCOPRI in subjects with mild and moderate hepatic impairment and 100 mg dose of XCOPRI in subjects with severe hepatic impairment compared to matched healthy controls [see Dosage and Administration ( 2.2 ) and Use in Specific Populations ( 8.7 )] .
Drug Interaction Studies Clinical Studies Alcohol No clinically significant pharmacokinetic differences were observed for either cenobamate or alcohol when administered concomitantly. AEDs Multiple doses of concomitant XCOPRI 200 mg once daily increased phenytoin mean C… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Interactions with Alcohol No clinically significant differences on objective attention, psychomotor performance, and memory tests, in addition to other subjective CNS tests, were observed following concomitant use of XCOPRI and ethanol (preparation of 40% ethanol in orange juice dosed at 0.7 g/kg for males and 0.57 g/kg for females) in healthy subjects. Cardiac Electrophysiology In a placebo-controlled QT study in healthy volunteers, dose-dependent shortening of the QTcF interval has been observed with XCOPRI [see Warnings and Precautions ( 5.2 )] .
The mean ΔΔQTc is -11 [-13, -8] msec for 200 mg once daily and -18 [-22, -15] msec for 500 mg once daily (1.25 times the maximum recommended dosage). A higher percentage of XCOPRI-treated subjects (31% at 200 mg and 66% at 500 mg) had a QT shortening of greater than 20 msec compared to placebo (6-17%). Reductions of the QTc interval below 300 msec were not observed.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of XCOPRI for the treatment of partial-onset seizures was established in two multicenter, randomized, double-blind, placebo-controlled studies in adult patients (Study 1 and Study 2). Patients enrolled in the studies had partial-onset seizures with or without secondary generalization and were not adequately controlled with 1 to 3 concomitant AEDs. During an 8-week baseline period, patients were required to have at least 3 or 4 partial-onset seizures per 28 days on average with no seizure-free period exceeding 3 to 4 weeks.
In these studies, patients had a mean duration of epilepsy of approximately 24 years and median baseline seizure frequency of 8.5 seizures per 28 days. More than 80% of patients were taking 2 or more concomitant AEDs. Study 1 ( NCT01397968 ) compared doses of XCOPRI 200 mg/day with placebo.
Study 2 ( NCT01866111 ) compared doses of XCOPRI 100 mg/day, 200 mg/day, and 400 mg/day with placebo. Both studies had an 8-week baseline period to establish a baseline seizure frequency, following which patients were randomized to a treatment arm. Patients entered a treatment period consisting of an initial titration phase (6 weeks), and a subsequent maintenance phase (6 weeks for Study 1 and 12 weeks for Study 2).
In Study 1, patients were started on a daily dose of 50 mg (a higher starting dose than currently recommended) and subsequently increased by 50 mg/day every two weeks, until the final daily target dose of 200 mg/day was achieved. In Study 2, patients were started on a daily dose of 50 mg (a higher starting dose than currently recommended) and subsequently increased by 50 mg/day every week (a faster titration than currently recommended) until 100 mg/day or 200 mg/day was reached and then increased by 100 mg/day every week in patients randomized to 400 mg/day [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.1 ), and Adverse Reactions ( 6.1 )] .
The primary efficacy outcome in Study 1 and Study 2 was the percent change from baseline in seizure frequency per 28 days in the treatment period. Table 6 summarizes the results of the primary endpoint for XCOPRI in each study. Table 6: Percent Change from Baseline in Seizure Frequency per 28 Days in the Treatment Period (Study 1 and Study 2) * A negative percent change from baseline in seizure frequency indicates reduction in seizure frequency from baseline. ** Statistically significant compared to placebo N Median Percent Change from Baseline in Seizure Frequency per 28 Days (%) * p-value (Compared to Placebo) Study 1 Placebo 108 -21.5 -- XCOPRI 200 mg/day 113 -55.6 <0.0001 ** Study 2 Placebo 106 -24.3 -- XCOPRI 100 mg/day 108 -36.3 0.006 ** XCOPRI 200 mg/day 109 -55.2 <0.001 ** XCOPRI 400 mg/day 111 -55.3 <0.001 ** Figure 1 and Figure 2 show the proportion of patients with different percent reductions during the maintenance phase over baseline in Study 1 and Study 2, respectively.
Patients in whom the seizure frequency increased are shown in the left-most column as “worse.” Patients in whom the seizure frequency decreased are shown in the remaining four categories. Figure 1: Proportion of Patients Exhibiting Different Percent Reductions During the Maintenance Phase over Baseline in Study 1 Figure 2: Proportion of Patients Exhibiting Different Percent Reductions During the Maintenance Phase over Baseline in Study 2 In Study 2, 4 of 102 (4%) patients in the XCOPRI 100 mg/day group, 11 of 98 (11%) patients in the XCOPRI 200 mg/day group, and 20 of 95 (21%) patients in the XCOPRI 400 mg/day group and 1 of 102 (1%) of patients in the placebo group reported no partial seizures during the maintenance phase.
Figure 1 Figure 2
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance XCOPRI contains cenobamate and is listed as a Schedule V controlled substance.
9.2Abuse Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects. In a human abuse potential study conducted in recreational sedative abusers (n=39), single doses of XCOPRI (200 mg and 400 mg) were compared to placebo. XCOPRI at single doses of 400 mg produced responses on positive subjective measures such as “Drug Liking,” “Overall Drug Liking,” “Take Drug Again,” and “Good Drug Effects” that were statistically greater than the responses produced on these measures by placebo.
In this study, euphoric mood occurred at greater extent with XCOPRI (400 mg) (8%) than with placebo (0%). Phase 1 multiple ascending dose studies in healthy subjects showed rates of euphoria and feeling drunk of about 3% and disturbance in attention of about 5% in subjects who received supratherapeutic doses of cenobamate, but these adverse events were absent in the placebo group. In Phase 2 and 3 studies in subjects with epilepsy, euphoric mood, confusional state, and sedation occurred at low rates in subjects who received XCOPRI (0.5-2.5%).
9.3Dependence Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Clinical studies in healthy subjects indicate that XCOPRI may cause physical dependence and lead to a withdrawal syndrome characterized by insomnia, decreased appetite, depressed mood, tremor, and amnesia. XCOPRI should be withdrawn gradually [see Warnings and Precautions ( 5.6 )] .
🔒 Controlled Substance ▾
9.1Controlled Substance XCOPRI contains cenobamate and is listed as a Schedule V controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Oral administration of cenobamate (0, 5, 15, or 35 mg/kg/day) to Tg.rasH2 mice for up to 26 weeks did not result in an increase in tumors. Oral administration of cenobamate (0, 4, 8, or 20 mg/kg/day) to male and female rats for up to 87 or 90 weeks, respectively, did not result in an increase in tumors. Plasma exposure at the highest dose tested in rats was less than that in humans at the maximum recommended human dose (MRHD) of 400 mg/day.
Mutagenesis Cenobamate was negative for genotoxicity in in vitro (Ames, mouse lymphoma) and in vivo (rat bone marrow micronucleus) assays. Impairment of Fertility Oral administration of cenobamate (0, 11, 22, or 44 mg/kg/day) to male and female rats prior to and throughout mating and continuing in females to Gestation Day 6 did not produce adverse effects on fertility, general reproductive performance, or early embryonic development. Plasma exposure (AUC) at the highest dose tested in rats was less than that in humans at the MRHD.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Oral administration of cenobamate (0, 5, 15, or 35 mg/kg/day) to Tg.rasH2 mice for up to 26 weeks did not result in an increase in tumors. Oral administration of cenobamate (0, 4, 8, or 20 mg/kg/day) to male and female rats for up to 87 or 90 weeks, respectively, did not result in an increase in tumors. Plasma exposure at the highest dose tested in rats was less than that in humans at the maximum recommended human dose (MRHD) of 400 mg/day.
Mutagenesis Cenobamate was negative for genotoxicity in in vitro (Ames, mouse lymphoma) and in vivo (rat bone marrow micronucleus) assays. Impairment of Fertility Oral administration of cenobamate (0, 11, 22, or 44 mg/kg/day) to male and female rats prior to and throughout mating and continuing in females to Gestation Day 6 did not produce adverse effects on fertility, general reproductive performance, or early embryonic development. Plasma exposure (AUC) at the highest dose tested in rats was less than that in humans at the MRHD.
📄 Recent Major Changes ▾
Dosage and Administration ( 2.1 ) 8/2025 Dosage and Administration ( 5.4 ) 8/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - NDC: 71699-050-30 - 50 mg 30-count Bottle Label 50 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-050-30 - 50 mg 30-count Bottle Label 50 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-050-99 - 50 mg 30-count Bottle Label 50 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-100-30 - 100 mg 30-count Bottle Label 100 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-100-30 - 100 mg 30-count Bottle Label 100 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-150-30 - 150 mg 30-count Bottle Label 150 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-150-30 - 150 mg 30-count Bottle Label 150 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-200-30 - 200 mg 30-count Bottle Label 200 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-200-30 - 200 mg 30-count Bottle Label 200 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-201-28 - 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Front) 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Back)
PRINCIPAL DISPLAY PANEL - NDC: 71699-201-28 - 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Back) 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Back)
PRINCIPAL DISPLAY PANEL - NDC: 71699-202-28 - 50 mg 14-count and 100 mg 14-count Titration Pack Label (Front) 50 mg 14-count and 100 mg 14-count Titration Pack Label (Front)
PRINCIPAL DISPLAY PANEL - NDC: 71699-202-28 - 50 mg 14-count and 100 mg 14-count Titration Pack Label (Back) 50 mg 14-count and 100 mg 14-count Titration Pack Label (Back)
PRINCIPAL DISPLAY PANEL - NDC: 71699-203-28 - 150 mg 14-count and 200 mg 14-count Titration Pack Label (Front) 150 mg 14-count and 200 mg 14-count Titration Pack Label (Front)
PRINCIPAL DISPLAY PANEL - NDC: 71699-203-28 - 150 mg 14-count and 200 mg 14-count Titration Pack Label (Back) 150 mg 14-count and 200 mg 14-count Titration Pack Label (Back)
PRINCIPAL DISPLAY PANEL - NDC: 71699-103-56 - 200 mg 28-count and 150 mg 28-count Maintenance Pack (Front) 150 mg 28-count and 200 mg 28-count Maintenance Pack (Front)
PRINCIPAL DISPLAY PANEL - NDC: 71699-103-56 - 200 mg 28-count and 150 mg 28-count Maintenance Pack (Back) 150 mg 28-count and 200 mg 28-count Maintenance Pack (Back)
PRINCIPAL DISPLAY PANEL - NDC: 71699-104-56 - 150 mg 28-count and 100 mg 28-count Maintenance Pack (Front) 150 mg 28-count and 100 mg 28-count Maintenance Pack (Front)
PRINCIPAL DISPLAY PANEL - NDC: 71699-104-56 - 150 mg 28-count and 100 mg 28-count Maintenance Pack (Back) 150 mg 28-count and 100 mg 28-count Maintenance Pack (Back)
PRINCIPAL DISPLAY PANEL - NDC: 71699-999-99 - 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Front) 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Front)
PRINCIPAL DISPLAY PANEL - NDC: 71699-999-99 - 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Back) 12.5 mg 14-count and 25 mg 14-count Titration Pack Label (Back)
PRINCIPAL DISPLAY PANEL - NDC: 71699-025-30 - 25 mg 30-count Bottle Label 25 mg 30-count Bottle Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-204-14 - 12.5 mg 14-count Titration Pack Label (Front) 12.5 mg 14-count Titration Pack Label
PRINCIPAL DISPLAY PANEL - NDC: 71699-204-14 - 12.5 mg 14-count Titration Pack Label (Back) 12.5 mg 14-count Titration Pack Label
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |