
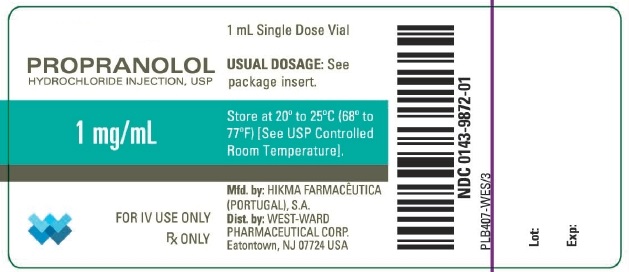
Propranolol Hydrochloride 1 mg/mL Injection, 1 vial
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Please don't stop propranolol on your own — even if you feel great. Stopping suddenly, especially if you have angina or any underlying heart disease, can cause a dangerous rebound...
- Can I stop taking propranolol if I feel fine and my blood pressure is under control?
- Bronchial asthma is actually a contraindication for propranolol, meaning it should not be used if you have asthma. Propranolol blocks receptors in your airways that help keep them...
- I have asthma — is it safe for me to take propranolol?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Propranolol Hydrochloride — tap one for details:
Propranolol Hydrochloride may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Propranolol Hydrochloride 1 mg/mL 00143-9872-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Propranolol 1 mg/mL 00404-9999-01 | Henry | 1 vial | — | AP | FDA listed | — |
| Propranolol Hydrochloride 1 mg/mL 51662-1338-01 | HF | 1 ml | — | AP | FDA listed | — |
| Propranolol 1 mg/mL 51662-1700-01 | HF | 1 ml | — | AP | FDA listed | — |
| Propranolol 1 mg/mL 63323-0604-01 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Propranolol Hydrochloride 1 mg/mLthis 71872-7096-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Propranolol 1 mg/mL 71872-7195-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Propranolol 1 mg/mL 84549-0604-01 | ProPharma | 1 ml | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71872-7096-01 You're viewing this | 1 VIAL in 1 BAG (71872-7096-1) / 1 mL in 1 VIAL | 2018-03-30 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Cardiac Arrhythmias Intravenous administration is usually reserved for life-threatening arrhythmias or those occurring under anesthesia. 1. Supraventricular arrhythmias Intravenous propranolol is indicated for the short-term treatment of supraventricular tachycardia, including Wolff‑Parkinson‑White syndrome and thyrotoxicosis, to decrease ventricular rate.
Use in patients with atrial flutter or atrial fibrillation should be reserved for arrythmias unresponsive to standard therapy or when more prolonged control is required. Reversion to normal sinus rhythm has occasionally been observed, predominantly in patients with sinus or atrial tachycardia. 2.
Ventricular tachycardias With the exception of those induced by catecholamines or digitalis, propranolol is not the drug of first choice. In critical situations when cardioversion techniques or other drugs are not indicated or are not effective, propranolol may be considered. If, after consideration of the risks involved, propranolol is used, it should be given intravenously in low dosage and very slowly, as the failing heart requires some sympathetic drive for maintenance of myocardial tone (see DOSAGE AND ADMINISTRATION ).
Some patients may respond with complete reversion to normal sinus rhythm, but reduction in ventricular rate is more likely. Ventricular arrhythmias do not respond to propranolol as predictably as do the supraventricular arrhythmias. Intravenous propranolol is indicated for the treatment of persistent premature ventricular extrasystoles that impair the well‑being of the patient and do not respond to conventional measures.
3. Tachyarrhythmias of digitalis intoxication Intravenous propranolol is indicated to control ventricular rate in life-threatening digitalis-induced arrhythmias. Severe bradycardia may occur (see OVERDOSAGE ).
4. Resistant tachyarrhythmias due to excessive catecholamine action during anesthesia Intravenous propranolol is indicated to abolish tachyarrhythmias due to excessive catecholamine action during anesthesia when other measures fail. These arrhythmias may arise because of release of endogenous catecholamines or administration of catecholamines.
All general inhalation anesthetics produce some degree of myocardial depression. Therefore, when propranolol is used to treat arrhythmias during anesthesia, it should be used with extreme caution, usually with constant monitoring of the ECG and central venous pressure (see WARNINGS ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. The usual dose is 1 to 3 mg administered under careful monitoring, such as electrocardiography and central venous pressure. The rate of administration should not exceed 1 mg (1 mL) per minute to diminish the possibility of lowering blood pressure and causing cardiac standstill.
Sufficient time should be allowed for the drug to reach the site of action even when a slow circulation is present. If necessary, a second dose may be given after two minutes. Thereafter, additional drug should not be given in less than four hours.
Additional propranolol hydrochloride should not be given when the desired alteration in rate or rhythm is achieved. Transfer to oral therapy as soon as possible.
⛔ Contraindications ▾
CONTRAINDICATIONS Propranolol is contraindicated in 1) cardiogenic shock; 2) sinus bradycardia and greater than first-degree block; 3) bronchial asthma; and 4) in patients with known hypersensitivity to propranolol hydrochloride.
⚠️ Warnings ▾
WARNINGS Cardiac Failure Sympathetic stimulation may be a vital component supporting circulatory function in patients with congestive heart failure, and its inhibition by beta blockade may precipitate more severe failure. Although beta‑blockers should be avoided in overt congestive heart failure, some have been shown to be highly beneficial when used with close follow-up in patients with a history of failure who are well compensated and are receiving additional therapies, including diuretics as needed. Beta-adrenergic blocking agents do not abolish the inotropic action of digitalis on heart muscle.
Nonallergic Bronchospasm (e.g., Chronic Bronchitis, Emphysema) In general, patients with bronchospastic lung disease should not receive beta blockers. Propranolol should be administered with caution in this setting since it may block bronchodilation produced by endogenous and exogenous catecholamine stimulation of beta-receptors. Major Surgery The necessity or desirability of withdrawal of beta-blocking therapy prior to major surgery is controversial.
It should be noted, however, that the impaired ability of the heart to respond to reflex adrenergic stimuli in propranolol-treated patients might augment the risks of general anesthesia and surgical procedures. Propranolol is a competitive inhibitor of beta-receptor agonists, and its effects can be reversed by administration of such agents, e.g., dobutamine or isoproterenol. However, such patients may be subject to protracted severe hypotension.
Diabetes and Hypoglycemia Beta-adrenergic blockade may prevent the appearance of certain premonitory signs and symptoms (pulse rate and pressure changes) of acute hypoglycemia, especially in labile insulin-dependent diabetics. In these patients, it may be more difficult to adjust the dosage of insulin. Propranolol therapy, particularly in infants and children, diabetic or not, has been associated with hypoglycemia especially during fasting, as in preparation for surgery.
Hypoglycemia has been reported after prolonged physical exertion and in patients with renal insufficiency. Thyrotoxicosis Beta-adrenergic blockade may mask certain clinical signs of hyperthyroidism. Therefore, abrupt withdrawal of propranolol may be followed by an exacerbation of symptoms of hyperthyroidism, including thyroid storm.
Propranolol may change thyroid-function tests, increasing T 4 and reverse T 3 , and decreasing T 3 . Wolff-Parkinson-White Syndrome Beta-adrenergic blockade in patients with Wolff-Parkinson-White syndrome and tachycardia has been associated with severe bradycardia requiring treatment with a pacemaker. In one case this resulted after an initial 5 mg dose of intravenous propranolol.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In a series of 225 patients, there were 6 deaths (see CLINICAL STUDIES ). Cardiovascular events (hypotension, congestive heart failure, bradycardia, and heart block) were the most common. The only other event reported by more than one patient was nausea.
Other adverse events for intravenous propranolol, reported during post-marketing surveillance include cardiac arrest, dyspnea, and cutaneous ulcers. The following adverse events have been reported with use of formulations of sustained- or immediate-release oral propranolol and may be expected with intravenous propranolol. Cardiovascular Bradycardia; congestive heart failure; intensification of AV block; hypotension; paresthesia of hands; thrombocytopenic purpura; arterial insufficiency, usually of the Raynaud type.
Central Nervous System Light-headedness; mental depression manifested by insomnia, lassitude, weakness, fatigue; reversible mental depression progressing to catatonia; visual disturbances; hallucinations; vivid dreams; an acute reversible syndrome characterized by disorientation for time and place, short-term memory loss, emotional lability, slightly clouded sensorium, and decreased performance on neuropsychometrics. For immediate‑release formulations, fatigue, lethargy, and vivid dreams appear dose-related. Gastrointestinal Nausea, vomiting, epigastric distress, abdominal cramping, diarrhea, constipation, mesenteric arterial thrombosis, ischemic colitis.
Allergic Pharyngitis and agranulocytosis; erythematous rash, fever combined with aching and sore throat; laryngospasm, and respiratory distress. Respiratory Bronchospasm. Hematologic Agranulocytosis, nonthrombocytopenic purpura, thrombocytopenic purpura.
Autoimmune In extremely rare instances, systemic lupus erythematosus has been reported. Miscellaneous Alopecia, LE-like reactions, psoriaform rashes, dry eyes, male impotence, and Peyronie’s disease have been reported rarely. Oculomucocutaneous reactions involving the skin, serous membranes and conjunctivae reported for a beta-blocker (practolol) have not been associated with propranolol.
To report SUSPECTED ADVERSE REACTIONS, contact West-ward Pharmaceutical Corp. at 1-877-233-2001 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
Drug Interactions Interactions with Substrates, Inhibitors or Inducers of Cytochrome P-450 Enzymes Because propranolol’s metabolism involves multiple pathways in the cytochrome P-450 system (CYP2D6, 1A2, 2C19), administration of propranolol with drugs that are metabolized by, or affect the activity (induction or inhibition) of one or more of these pathways may lead to clinically relevant drug interactions (see PRECAUTIONS, Drug Interactions ). Substrates or Inhibitors of CYP2D6 Blood levels of propranolol may be increased by administration of propranolol with substrates or inhibitors of CYP2D6, such as amiodarone, cimetidine, delavirdine, fluoxetine, paroxetine, quinidine, and ritonavir.
No interactions were observed with either ranitidine or lansoprazole. Substrates or Inhibitors of CYP1A2 Blood levels of propranolol may be increased by administration of propranolol with substrates or inhibitors of CYP1A2, such as imipramine, cimetidine, ciprofloxacin, fluvoxamine, isoniazid, ritonavir, theophylline, zileuton, zolmitriptan, and rizatriptan. Substrates or Inhibitors of CYP2C19 Blood levels of propranolol may be increased by administration of propranolol with substrates or inhibitors of CYP2C19, such as fluconazole, cimetidine, fluoxetine, fluvoxamine, teniposide, and tolbutamide.
No interaction was observed with omeprazole. Inducers of Hepatic Drug Metabolism Blood levels of propranolol may be decreased by administration of propranolol with inducers such as rifampin and ethanol. Cigarette smoking also induces hepatic metabolism and has been shown to increase up to 100% the clearance of propranolol, resulting in decreased plasma concentrations.
Cardiovascular Drugs Antiarrhythmics The AUC of propafenone is increased by more than 200% with co-administration of propranolol. The metabolism of propranolol is reduced by co-administration of quinidine, leading to a 2- to 3-fold increased blood concentrations and greater beta-blockade. The metabolism of lidocaine is inhibited by co-administration of propranolol, resulting in a 25% increase in lidocaine concentrations.
Calcium Channel Blockers The mean C max and AUC of propranolol are increased respectively, by 50% and 30% by co-administration of nisoldipine and by 80% and 47%, by co-administration of nicardipine. The mean values of C max and AUC of nifedipine are increased by 64% and 79%, respectively, by co-administration of propranolol. Propranolol does not affect the pharmacokinetics of verapamil and norverapamil.
Verapamil does not affect the pharmacokinetics of propranolol. Non-Cardiovascular Drugs Migraine Drugs Administration of zolmitriptan or rizatriptan with propranolol resulted in increased concentrations of zolmitriptan (AUC increased by 56% and C max by 37%) or rizatriptan (the AUC and C max were increased by 67% and 75%, respectively). Theophylline Co-administration of theophylline with propranolol decreases theophylline clearance by 33% to 52%.
Benzodiazepines Propranolol can inhibit the metabolism of diazepam, resulting in increased concentrations of diazepam and its metabolites. Diazepam does not alter the pharmacokinetics of propranolol. The pharmacokinetics of oxazepam, triazolam, lorazepam, and alprazolam are not affected by co-administration of propranolol.
Neuroleptic Drugs Co-administration of propranolol at doses greater than or equal to 160 mg/day resulted in increased thioridazine plasma concentrations ranging from 50% to 370% and increased thioridazine metabolites concentrations ranging from 33% to 210%. Co-administration of chlorpromazine with propranolol resulted in increased plasma levels of both drugs (70% increase in propranolol concentrations). Anti-Ulcer Drugs Co-administration of propranolol with cimetidine, a non-specific CYP450 inhibitor, increased propranolol concentrations by about 40%.
Co‑administration with aluminum hydroxide gel (1200 mg) resulted in a 50% decrease in propranolol concentrations. Co-administration of metoclopramide with propran…
👥 Use in Specific Populations ▾
Special Populations Pediatric The pharmacokinetics of propranolol have not been investigated in patients under 18 years of age. Propranolol injection is not recommended for treatment of cardiac arrhythmias in pediatric patients. Geriatric Elevated propranolol plasma concentrations, a longer mean elimination half-life (254 vs.
152 minutes), and decreased systemic clearance (8 vs. 13 mL/kg/min) have been observed in elderly subjects when compared to young subjects. However, the apparent volume of distribution seems to be similar in elderly and young subjects.
These findings suggest that dose adjustment of propranolol injection may be required for elderly patients (see PRECAUTIONS ). Gender Intravenously administered propranolol was evaluated in 5 women and 6 men. When adjusted for weight, there were no gender-related differences in elimination half-life, volume of distribution, protein binding, or systemic clearance.
Obesity In a study of intravenously administered propranolol, obese subjects had a higher AUC (161 versus 109 hr·mcg/L) and lower total clearance than did non-obese subjects. Propranolol plasma protein binding was similar in both groups. Renal Insufficiency The pharmacokinetics of propranolol and its metabolites were evaluated in 15 subjects with varying degrees of renal function after propranolol administration via the intravenous and oral routes.
When compared with normal subjects, an increase in fecal excretion of propranolol conjugates was observed in patients with increased renal impairment. Propranolol was also evaluated in 5 patients with chronic renal failure, 6 patients on regular dialysis, and 5 healthy subjects, following a single oral dose of 40 mg of propranolol. The peak plasma concentrations (C max ) of propranolol in the chronic renal failure group were 2- to 3-fold higher (161 ng/mL) than those observed in the dialysis patients (47 ng/mL) and in the healthy subjects (26 ng/mL).
Propranolol plasma clearance was also reduced in the patients with chronic renal failure. Chronic renal failure has been associated with a decrease in drug metabolism via downregulation of hepatic cytochrome P-450 activity. Hepatic Insufficiency Propranolol is extensively metabolized by the liver.
In a study conducted in 6 normal subjects and 20 patients with chronic liver disease, including hepatic cirrhosis, 40 mg of R-propranolol was administered intravenously. Compared to normal subjects, patients with chronic liver disease had decreased clearance of propranolol, increased volume of distribution, decreased protein-binding, and considerable variation in half-life. Caution should be exercised when propranolol is used in this population.
Consideration should be given to lowering the dose of intravenous propranolol in patients with hepatic insufficiency (see PRECAUTIONS ). Thyroid Dysfunction No pharmacokinetic changes were observed in hyperthyroid or hypothyroid patients when compared to their corresponding euthyroid state. Dosage adjustment does not seem necessary in either patient population based on pharmacokinetic findings.
🤰 Pregnancy ▾
Pregnancy Pregnancy Category C In a series of reproductive and developmental toxicology studies, propranolol hydrochloride was given to rats by gavage or in the diet throughout pregnancy and lactation. At doses of 150 mg/kg/day, but not at doses of 80 mg/kg/day (equivalent to the MRHD on a body surface area basis), treatment was associated with embryotoxicity (reduced litter size and increased resorption rates) as well as neonatal toxicity (deaths). Propranolol hydrochloride also was administered (in the feed) to rabbits (throughout pregnancy and lactation) at doses as high as 150 mg/kg/day (about 5 times the maximum recommended human oral daily dose).
No evidence of embryo or neonatal toxicity was noted. There are no adequate and well-controlled studies in pregnant women. Intrauterine growth retardation has been reported for neonates whose mothers received propranolol hydrochloride during pregnancy.
Neonates whose mothers received propranolol hydrochloride at parturition have exhibited bradycardia, hypoglycemia, and respiratory depression. Adequate facilities for monitoring such infants at birth should be available. Propranolol should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric The pharmacokinetics of propranolol have not been investigated in patients under 18 years of age. Propranolol injection is not recommended for treatment of cardiac arrhythmias in pediatric patients.
Pediatric Use Safety and effectiveness of propranolol in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Elevated propranolol plasma concentrations, a longer mean elimination half-life (254 vs. 152 minutes), and decreased systemic clearance (8 vs. 13 mL/kg/min) have been observed in elderly subjects when compared to young subjects. However, the apparent volume of distribution seems to be similar in elderly and young subjects. These findings suggest that dose adjustment of propranolol injection may be required for elderly patients (see PRECAUTIONS ).
Geriatric Use Clinical studies of intravenous propranolol did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Elderly subjects have decreased clearance and a longer mean elimination half‑life. These findings suggest that dose adjustment of propranolol injection may be required for elderly patients (see CLINICAL PHARMACOLOGY, Special Populations, Geriatric ).
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of the decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE Propranolol is not significantly dialyzable. In the event of overdose or exaggerated response, the following measures should be employed: Hypotension and bradycardia have been reported following propranolol overdose and should be treated appropriately. Glucagon can exert potent inotropic and chronotropic effects and may be particularly useful for the treatment of hypotension or depressed myocardial function after a propranolol overdose.
Glucagon should be administered as 50-150 mcg/kg intravenously followed by continuous drip of 1-5 mg/hour for positive chronotropic effect. Isoproterenol, dopamine, or phosphodiesterase inhibitors may also be useful. Epinephrine, however, may provoke uncontrolled hypertension.
Bradycardia can be treated with atropine or isoproterenol. Serious bradycardia may require temporary cardiac pacing. The electrocardiogram, pulse, blood pressure, neurobehavioral status and intake and output balance must be monitored.
Isoproterenol and aminophylline may be useful for bronchospasm.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY General Propranolol is a nonselective beta-adrenergic receptor blocking agent possessing no other autonomic nervous system activity. It specifically competes with beta-adrenergic receptor stimulating agents for available receptor sites. When access to beta‑receptor sites is blocked by propranolol, chronotropic, inotropic, and vasodilator responses to beta-adrenergic stimulation are decreased proportionately.
At doses greater than required for beta blockade, propranolol also exerts a quinidine-like or anesthetic-like membrane action, which affects the cardiac action potential. The significance of the membrane action in the treatment of arrhythmias is uncertain. Mechanism of Action The effects of propranolol are due to selective blockade of beta-adrenergic receptors, leaving alpha-adrenergic responses intact.
There are two well-characterized subtypes of beta receptors (beta 1 and beta 2 ); propranolol interacts with both subtypes equally. Beta 1 -adrenergic receptors are found primarily in the heart. Blockade of cardiac beta 1 -adrenergic receptors leads to a decrease in the activity of both normal and ectopic pacemaker cells and a decrease in A-V nodal conduction velocity.
All of these actions can contribute to antiarrhythmic activity and control of ventricular rate during arrhythmias. Blockade of cardiac beta 1 ‑adrenergic receptors also decreases the myocardial force of contraction and may provoke cardiac decompensation in patients with minimal cardiac reserve. Beta 2 -adrenergic receptors are found predominantly in smooth muscle–vascular, bronchial, gastrointestinal and genitourinary.
Blockade of these receptors results in constriction. Clinically, propranolol may exacerbate respiratory symptoms in patients with obstructive pulmonary diseases such as asthma and emphysema (see CONTRAINDICATIONS and WARNINGS ). Propranolol’s beta blocking effects are attributable to its S(-) enantiomer.
Pharmacokinetics and Drug Metabolism Distribution Propranolol has a distribution half-life (T½ alpha) of 5-10 minutes and a volume of distribution of about 4 to 5 L/kg. Approximately 90% of circulating propranolol is bound to plasma proteins. The binding is enantiomer-selective.
The S-isomer is preferentially bound to alpha 1 glycoprotein and the R-isomer is preferentially bound to albumin. Metabolism and Elimination The elimination half-life (T½ beta) is between 2 and 5.5 hours. Propranolol is extensively metabolized with most metabolites appearing in the urine.
The major metabolites include propranolol glucuronide, naphthyloxylactic acid, and glucuronic acid and sulfate conjugates of 4-hydroxy propranolol. Following single-dose intravenous administration, side-chain oxidative products account for approximately 40% of the metabolites, direct conjugation products account for approximately 45-50% of metabolites, and ring oxidative products account for approximately 10-15% of metabolites. Of these, only the primary ring oxidative product (4-hydroxypropranolol) possesses beta-adrenergic receptor blocking activity.
In vitro studies have indicated that the aromatic hydroxylation of propranolol is catalyzed mainly by polymorphic CYP2D6. Side‑chain oxidation is mediated mainly by CYP1A2 and to some extent by CYP2D6. 4-hydroxy propranolol is a weak inhibitor of CYP2D6.
Pharmacodynamics As propranolol concentration increases, so does its beta-blocking effect, as evidenced by a reduction in exercise-induced tachycardia (n = 6 normal volunteers). Special Populations Pediatric The pharmacokinetics of propranolol have not been investigated in patients under 18 years of age. Propranolol injection is not recommended for treatment of cardiac arrhythmias in pediatric patients.
Geriatric Elevated propranolol plasma concentrations, a longer mean elimination half-life (254 vs. 152 minutes), and decreased systemic clearance (8 vs. 13 mL/kg/min) have been observed in elderly subjects when compared to young subjects.
However, the apparent volume…
🧬 Mechanism of Action ▾
Mechanism of Action The effects of propranolol are due to selective blockade of beta-adrenergic receptors, leaving alpha-adrenergic responses intact. There are two well-characterized subtypes of beta receptors (beta 1 and beta 2 ); propranolol interacts with both subtypes equally. Beta 1 -adrenergic receptors are found primarily in the heart.
Blockade of cardiac beta 1 -adrenergic receptors leads to a decrease in the activity of both normal and ectopic pacemaker cells and a decrease in A-V nodal conduction velocity. All of these actions can contribute to antiarrhythmic activity and control of ventricular rate during arrhythmias. Blockade of cardiac beta 1 ‑adrenergic receptors also decreases the myocardial force of contraction and may provoke cardiac decompensation in patients with minimal cardiac reserve.
Beta 2 -adrenergic receptors are found predominantly in smooth muscle–vascular, bronchial, gastrointestinal and genitourinary. Blockade of these receptors results in constriction. Clinically, propranolol may exacerbate respiratory symptoms in patients with obstructive pulmonary diseases such as asthma and emphysema (see CONTRAINDICATIONS and WARNINGS ).
Propranolol’s beta blocking effects are attributable to its S(-) enantiomer.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Each mL contains 1 mg of Propranolol Hydrochloride, USP in Water for Injection, USP. The pH is adjusted with anhydrous Citric Acid, USP. Supplied as: 1 mL vials in boxes of 10 (NDC 0143-9872-10).
Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Protect from freezing or excessive heat. Manufactured by: HIKMA FARMACÊUTICA (PORTUGAL), S.A.
Estrada do Rio da Mó, 8, 8A e 8B – Fervença – 2705-906 Terrugem SNT, PORTUGAL Distributed by: WEST-WARD PHARMACEUTICAL CORP. Eatontown, NJ 07724 USA Rev.: 05/2015 PIN166-WES/4
📋 Description ▾
DESCRIPTION Propranolol Hydrochloride, USP is a synthetic beta-adrenergic receptor blocking agent chemically described as (+)-1-(isopropylamino)-3-(1-naphthyloxy)-2-propanol hydrochloride. Its structural formula is: C 16 H 21 NO 2 •HCl Propranolol Hydrochloride, USP is a stable, white, crystalline solid which is readily soluble in water and ethanol. Its molecular weight is 295.80.
Propranolol Hydrochloride Injection, USP is available as a sterile injectable solution for intravenous administration. Each mL contains 1 mg of Propranolol Hydrochloride, USP in Water for Injection, USP. The pH is adjusted with anhydrous Citric Acid, USP.
Structural Formula