
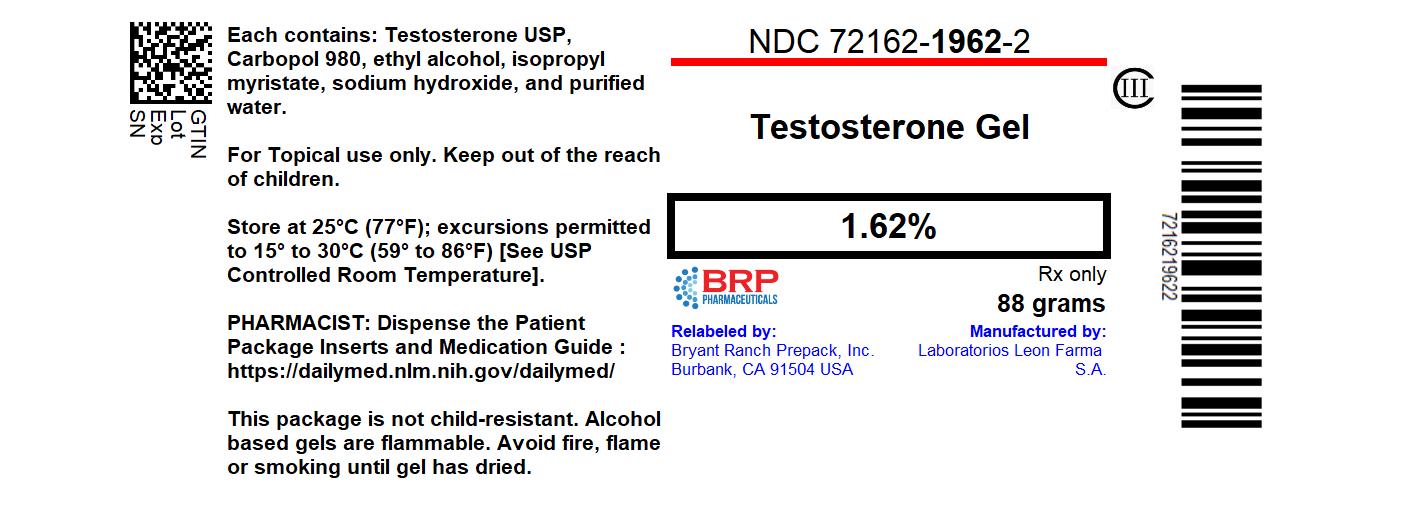
Testosterone 20.25 mg/1.25g Gel, Metered
Other active recalls for Testosterone (different manufacturers) — 4 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Androgen class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Testosterone topical is used to treat low or no testosterone levels in men. Testosterone is in a class of medications called androgenic hormones. Testosterone is a male sex hormone responsible for development and functioning of male sexual organs and typical male characteristics. Testosterone topical works by replacing the testosterone that is normally produced by the body.
Read the full MedlinePlus article ↗- Testosterone replacement is specifically for men whose bodies aren't making enough testosterone because of a medical condition — like a problem with the testes themselves (primary...
- What exactly is testosterone replacement therapy for — do I really need it?
- Yes, this is a serious concern. Children who accidentally touch the gel on your skin or clothing can absorb testosterone and develop early puberty signs — things like pubic hair gr...
- I use the gel — do I really need to worry about my kids or partner being exposed to it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Testosterone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 4Q93RCW27E
A synthetic polymer made from acrylic acid that's crosslinked for stability. It acts as a thickener and gelling agent in creams and gels, helping the medicine spread evenly and maintain its texture.
-
UNII 0RE8K4LNJS
Isopropyl myristate is an oily liquid made from coconut or palm oil. It's used in medicines as an emollient and penetration enhancer to help the medicine absorb through skin or improve spreadability in topical products.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.7534 | $66.30 / 88 g |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Testosterone 16.2 mg/g 00591-2924-18 | Actavis | 1 bottle | $0.472 | AB | Availability likely | — |
| Testosterone 16.2 mg/g 21922-0030-20 | Encube | 1 bottle | $0.472 | AB | Availability likely | — |
| testosterone 16.2 mg/g 45802-0754-01 | Padagis | 1 bottle | $0.472 | AB | Availability likely | — |
| Testosterone 16.2 mg/g 66993-0951-88 | Prasco | 1 bottle | $0.472 | AB | Availability likely | — |
| Testosterone 16.2 mg/g 68180-0941-11 | Lupin | 1 bottle | $0.472 | AB | Availability likely | — |
| Testosterone 20.25 mg/1.25g 69238-1013-02 | Amneal | 1 bottle | $0.472 | AB | Availability likely | — |
| Testosterone 20.25 mg/1.25g 70700-0112-21 | Xiromed, | 1 bottle | $0.472 | AB | Availability likely | — |
| Testosterone 20.25 mg/1.25g 72603-0265-01 | Northstar | 1 bottle | $0.472 | AB | Availability likely | — |
| Testosterone 1.62 mg/g 43598-0304-88 | Dr. | 1 bottle | $0.603 | AB | FDA listed | — |
| AndroGel 16.2 mg/g 17139-0562-88 | ASCEND | 1 bottle | — | AB | Discontinued | — |
| Testosterone 16.2 mg/g 62332-0552-88 | Alembic | 1 bottle | — | — | FDA listed | — |
| Testosterone 20.25 mg/1.25g 63629-2352-01 | Bryant | 1 bottle | — | AB | FDA listed | — |
| testosterone 16.2 mg/g 63629-8455-01 | Bryant | 1 bottle | — | AB | FDA listed | — |
| testosterone 16.2 mg/g 71335-2742-01 | Bryant | 1 bottle | — | AB | FDA listed | — |
| testosterone 16.2 mg/g 72162-1426-02 | Bryant | 1 bottle | — | AB | FDA listed | — |
| Testosterone 20.25 mg/1.25gthis 72162-1962-02 | Bryant | 1 bottle | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72162-1962-02 You're viewing this | 1 BOTTLE, PUMP in 1 CARTON (72162-1962-2) / 88 g in 1 BOTTLE, PUMP | 2024-02-07 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE Virilization has been reported in children who were secondarily exposed to testosterone gel [see Warnings and Precautions ( 5.2 ) and Adverse Reactions ( 6.2 )]. Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel [see Dosage and Administration ( 2.2 ) and Warnings and Precautions ( 5.2 )]. Healthcare providers should advise patients to strictly adhere to recommended instructions for use [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.2 ) and Patient Counseling Information ( 17 )].
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE See full prescribing information for complete boxed warning. Virilization has been reported in children who were secondarily exposed to testosterone gel ( 5.2 , 6.2 ) Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel ( 2.2 , 5.2 ). Healthcare providers should advise patients to strictly adhere to recommended instructions for use ( 2.2 , 5.2 , 17 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Testosterone gel, 1.62% is indicated for replacement therapy in adult males for conditions associated with a deficiency or absence of endogenous testosterone: Primary hypogonadism (congenital or acquired): testicular failure due to conditions such as cryptorchidism, bilateral torsion, orchitis, vanishing testis syndrome, orchiectomy, Klinefelter's syndrome, chemotherapy, or toxic damage from alcohol or heavy metals. These men usually have low serum testosterone concentrations and gonadotropins (follicle-stimulating hormone [FSH], luteinizing hormone [LH]) above the normal range.
Hypogonadotropic hypogonadism (congenital or acquired): gonadotropin or luteinizing hormone releasing hormone (LHRH) deficiency or pituitary-hypothalamic injury from tumors, trauma, or radiation. These men have low testosterone serum concentrations, but have gonadotropins in the normal or low range. Limitations of use: Safety and efficacy of testosterone gel, 1.62% in men with “age-related hypogonadism” (also referred to as “late-onset hypogonadism”) have not been established.
Safety and efficacy of testosterone gel, 1.62% in males less than 18 years old have not been established [see Use in Specific Populations ( 8.4 )] . Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure [see Indications and Usage ( 1 ), and Clinical Pharmacology ( 12.3 )]. Testosterone gel, 1.62% is indicated for replacement therapy in males for conditions associated with a deficiency or absence of endogenous testosterone: Primary hypogonadism (congenital or acquired) ( 1 ) Hypogonadotropic hypogonadism (congenital or acquired) ( 1 ) Limitations of use: Safety and efficacy of testosterone gel, 1.62% in men with “age-related hypogonadism” have not been established.
( 1 ) Safety and efficacy of testosterone gel, 1.62% in males less than 18 years old have not been established. ( 1 , 8.4 ) Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure. ( 1 , 12.3 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Dosage and Administration for testosterone gel, 1.62% differs from testosterone gel, 1%. For dosage and administration of Testosterone Gel, 1% refer to its full prescribing information. ( 2 ) Prior to initiating Testosterone Gel, 1.62%, confirm the diagnosis of hypogonadism by ensuring that serum testosterone concentrations have been measured in the morning on at least two separate days and that these serum testosterone concentrations are below the normal range.
Dosage and Administration for testosterone gel, 1.62% differs from testosterone gel, 1%. For dosage and administration of testosterone gel, 1% refer to its full prescribing information. ( 2 ) Prior to initiating testosterone gel, 1.62%, confirm the diagnosis of hypogonadism by ensuring that serum testosterone has been measured in the morning on at least two separate days and that these concentrations are below the normal range.
( 2 ) Starting dose of testosterone gel, 1.62% is 40.5 mg of testosterone (2 pump actuations), applied topically once daily in the morning. ( 2.1 ) Apply to clean, dry, intact skin of the shoulders and upper arms. Do not apply testosterone gel, 1.62% to any other parts of the body including the abdomen, genitals, chest, armpits (axillae), or knees.
( 2.2 , 12.3 ) Dose adjustment: Testosterone gel, 1.62% can be dose adjusted between a minimum of 20.25 mg of testosterone (1 pump actuation) and a maximum of 81 mg of testosterone (4 pump actuations). The dose should be titrated based on the pre-dose morning serum testosterone concentration at approximately 14 days and 28 days after starting treatment or following dose adjustment. Additionally, serum testosterone concentration should be assessed periodically thereafter.
( 2.1 ) Patients should wash hands immediately with soap and water after applying testosterone gel, 1.62% and cover the application site(s) with clothing after the gel has dried. Wash the application site thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated. ( 2.2 )
2.1Dosing and Dose Adjustment The recommended starting dose of testosterone gel, 1.62% is 40.5 mg of testosterone (2 pump actuations) applied topically once daily in the morning to the shoulders and upper arms. The dose can be adjusted between a minimum of 20.25 mg of testosterone (1 pump actuation) and a maximum of 81 mg of testosterone (4 pump actuations). To ensure proper dosing, the dose should be titrated based on the pre-dose morning serum testosterone concentration from a single blood draw at approximately 14 days and 28 days after starting treatment or following dose adjustment.
In addition, serum testosterone concentration should be assessed periodically thereafter. Table 1 describes the dose adjustments required at each titration step. Table 1: Dose Adjustment Criteria Pre-Dose Morning Total Serum Testosterone Concentration Dose Titration Greater than 750 ng/dL Decrease daily dose by 20.25 mg (1 pump actuation) Equal to or greater than 350 and equal to or less than 750 ng/dL No change: continue on current dose Less than 350 ng/dL Increase daily dose by 20.25 mg (1 pump actuation) The application site and dose of testosterone gel, 1.62% are not interchangeable with other topical testosterone products.
2.2Administration Instructions Testosterone gel, 1.62% should be applied to clean, dry, intact skin of the upper arms and shoulders. Do not apply testosterone gel, 1.62% to any other parts of the body, including the abdomen, genitals, chest, armpits (axillae), or knees [see Clinical Pharmacology ( 12.3 )] . Area of application should be limited to the area that will be covered by the patient's short sleeve t-shirt.
Patients should be instructed to use the palm of the hand to apply testosterone gel, 1.62% and spread across the maximum surface area as directed in Table 2 and in Figure 1 . Table 2: Application Sites for Testosterone Gel, 1.62% , Pump Tota…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Testosterone gel, 1.62% for topical use only, is available as follows: A metered-dose pump. Each pump actuation delivers 20.25 mg of testosterone in 1.25 g of gel. Testosterone gel, 1.62% for topical use is available as follows: a metered-dose pump that delivers 20.25 mg testosterone per actuation. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Testosterone gel, 1.62% is contraindicated in men with carcinoma of the breast or known or suspected carcinoma of the prostate [see Warnings and Precautions ( 5.1 ) and Adverse Reactions ( 6.1 )]. Testosterone gel, 1.62% is contraindicated in women who are pregnant. Testosterone gel, 1.62% can cause virilization of the female fetus when administered to a pregnant woman.
Pregnant women need to be aware of the potential for transfer of testosterone from men treated with testosterone gel, 1.62%. If a pregnant woman is exposed to testosterone gel, 1.62%, she should be apprised of the potential hazard to the fetus [see Warnings and Precautions ( 5.2 ) and Use in Specific Populations ( 8.1 )] . Men with carcinoma of the breast or known or suspected prostate cancer ( 4 , 5.1 ) Women who are pregnant.
Testosterone may cause fetal harm ( 4 , 8.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Monitor patients with benign prostatic hyperplasia (BPH) for worsening of signs and symptoms of BPH ( 5.1 ) Avoid unintentional exposure of women or children to testosterone gel, 1.62%. Secondary exposure to testosterone can produce signs of virilization. Testosterone gel, 1.62% should be discontinued until the cause of virilization is identified ( 5.2 ) Venous thromboembolism (VTE), including deep vein thrombosis (DVT) and pulmonary embolism (PE) have been reported in patients using testosterone products.
Evaluate patients with signs or symptoms consistent with DVT or PE. ( 5.4 ) Some postmarketing studies have shown an increased risk of myocardial infarction and stroke associated with use of testosterone replacement therapy. ( 5.5 ) Exogenous administration of androgens may lead to azoospermia ( 5.8 ) Edema with or without congestive heart failure (CHF) may be a complication in patients with preexisting cardiac, renal, or hepatic disease ( 5.10 ) Sleep apnea may occur in those with risk factors ( 5.12 ) Monitor serum testosterone, prostate specific antigen (PSA), hemoglobin, hematocrit, liver function tests and lipid concentrations periodically ( 5.1 , 5.3 , 5.9 , 5.13 ) Testosterone gel, 1.62% is flammable until dry ( 5.16 )
5.1Worsening of Benign Prostatic Hyperplasia (BPH) and Potential Risk of Prostate Cancer Patients with BPH treated with androgens are at an increased risk for worsening of signs and symptoms of BPH. Monitor patients with BPH for worsening signs and symptoms. Patients treated with androgens may be at increased risk for prostate cancer.
Evaluation of patients for prostate cancer prior to initiating and during treatment with androgens is appropriate [see Contraindications ( 4 )] .
5.2Potential for Secondary Exposure to Testosterone Cases of secondary exposure resulting in virilization of children have been reported in postmarketing surveillance of testosterone gel products. Signs and symptoms have included enlargement of the penis or clitoris, development of pubic hair, increased erections and libido, aggressive behavior, and advanced bone age. In most cases, these signs and symptoms regressed with removal of the exposure to testosterone gel.
In a few cases, however, enlarged genitalia did not fully return to age-appropriate normal size, and bone age remained modestly greater than chronological age. The risk of transfer was increased in some of these cases by not adhering to precautions for the appropriate use of the topical testosterone product. Children and women should avoid contact with unwashed or unclothed application sites in men using testosterone gel, 1.62% [see Dosage and Administration ( 2.2 ), Use in Specific Populations ( 8.1 ) and Clinical Pharmacology ( 12.3 )].
Inappropriate changes in genital size or development of pubic hair or libido in children, or changes in body hair distribution, significant increase in acne, or other signs of virilization in adult women should be brought to the attention of a physician and the possibility of secondary exposure to testosterone gel should also be brought to the attention of a physician. Testosterone gel should be promptly discontinued until the cause of virilization has been identified.
5.3Polycythemia Increases in hematocrit, reflective of increases in red blood cell mass, may require lowering or discontinuation of testosterone. Check hematocrit prior to initiating treatment. It would also be appropriate to re-evaluate the hematocrit 3 to 6 months after starting treatment, and then annually.
If hematocrit becomes elevated, stop therapy until hematocrit decreases to an acceptable concentration. An increase in red blood cell mass may increase the risk of thromboembolic events.
5.4Venous Thromboembolism There have been postmarketing reports of venous thromboembolic events, including deep vein thrombosis (DVT) and pulmonary embolism (PE), in patients using testosterone products such as testosterone gel, 1.62%. Evaluate pati…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reaction (incidence ≥ 5%) is an increase in prostate specific antigen (PSA). ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Xiromed, LLC. at 844-XIROMED (844-947-6633) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Testosterone gel, 1.62% was evaluated in a two-phase, 364-day, controlled clinical study. The first phase was a multi-center, randomized, double-blind, parallel-group, placebo-controlled period of 182 days, in which 234 hypogonadal men were treated with testosterone gel, 1.62% and 40 received placebo.
Patients could continue in an open-label, non-comparative, maintenance period for an additional 182 days [see Clinical Studies ( 14.1 )]. The most common adverse reaction reported in the double-blind period was increased prostate specific antigen (PSA) reported in 26 testosterone gel, 1.62%-treated patients (11.1%). In 17 patients, increased PSA was considered an adverse event by meeting one of the two pre-specified criteria for abnormal PSA values, defined as (1) average serum PSA >4 ng/mL based on two separate determinations, or (2) an average change from baseline in serum PSA of greater than 0.75 ng/mL on two determinations.
During the 182-day, double-blind period of the clinical trial, the mean change in serum PSA value was 0.14 ng/mL for patients receiving testosterone gel, 1.62% and -0.12 ng/mL for the patients in the placebo group. During the double-blind period, seven patients had a PSA value >4.0 ng/mL, four of these seven patients had PSA less than or equal to 4.0 ng/mL upon repeat testing. The other three patients did not undergo repeat PSA testing.
During the 182-day, open-label period of the study, the mean change in serum PSA values was 0.10 ng/mL for both patients continuing on active therapy and patients transitioning onto active from placebo. During the open-label period, three patients had a serum PSA value > 4.0 ng/mL, two of whom had a serum PSA less than or equal to 4.0 ng/mL upon repeated testing. The other patient did not undergo repeat PSA testing.
Among previous placebo patients, 3 of 28 (10.7%), had increased PSA as an adverse event in the open-label period. Table 4 shows adverse reactions reported by >2% of patients in the 182-day, double-blind period of the testosterone gel, 1.62% clinical trial and more frequent in the testosterone gel, 1.62% treated group versus placebo. Table 4: Adverse Reactions Reported in >2% of Patients in the 182-Day, Double-Blind Period of Testosterone Gel, 1.62% Clinical Trial Number (%) of Patients Adverse Reaction Testosterone Gel, 1.62% N=234 Placebo N=40 PSA increased* 26 (11.1%) 0% Emotional lability** 6 (2.6%) 0% Hypertension 5 (2.1%) 0% Hematocrit or hemoglobin increased 5 (2.1%) 0% Contact dermatitis*** 5 (2.1%) 0% * PSA increased includes: PSA values that met pre-specified criteria for abnormal PSA values (an average change from baseline > 0.75 ng/mL and/or an average PSA value >4.0 ng/mL based on two measurements) as well as those reported as adverse events. ** Emotional lability includes: mood swings, affective disorder, impatience, anger, and aggression. *** Contact dermatitis includes: 4 patients with dermatitis at non-application sites.
Other adverse reactions occurring in less than or equal to 2% of testosterone gel, 1.62%-treated patients and more frequently than placebo included: frequent urination, and hyperlipidemia. In the open-label period of the study (N=191), the most commonly reported adverse reaction (experienced by greater than 2% of patients) was increased PSA (n=13; 6.2%) and sinusitis. Other adverse reactions reported by less than or equal to 2% of patients included increased hemoglobin or hem…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Androgens may decrease blood glucose and therefore may decrease insulin requirements in diabetic patients ( 7.1 ) Changes in anticoagulant activity may be seen with androgens. More frequent monitoring of International Normalized Ratio (INR) and prothrombin time is recommended ( 7.2 ) Use of testosterone with adrenocorticotrophic hormone (ACTH) or corticosteroids may result in increased fluid retention. Use with caution, particularly in patients with cardiac, renal, or hepatic disease ( 7.3 )
7.1Insulin Changes in insulin sensitivity or glycemic control may occur in patients treated with androgens. In diabetic patients, the metabolic effects of androgens may decrease blood glucose and, therefore, may decrease insulin requirements.
7.2Oral Anticoagulants Changes in anticoagulant activity may be seen with androgens, therefore more frequent monitoring of international normalized ratio (INR) and prothrombin time are recommended in patients taking anticoagulants, especially at the initiation and termination of androgen therapy.
7.3Corticosteroids The concurrent use of testosterone with adrenocorticotropic hormone (ACTH) or corticosteroids may result in increased fluid retention and requires careful monitoring particularly in patients with cardiac, renal or hepatic disease.
7.1Insulin Changes in insulin sensitivity or glycemic control may occur in patients treated with androgens. In diabetic patients, the metabolic effects of androgens may decrease blood glucose and, therefore, may decrease insulin requirements.
7.2Oral Anticoagulants Changes in anticoagulant activity may be seen with androgens, therefore more frequent monitoring of international normalized ratio (INR) and prothrombin time are recommended in patients taking anticoagulants, especially at the initiation and termination of androgen therapy.
7.3Corticosteroids The concurrent use of testosterone with adrenocorticotropic hormone (ACTH) or corticosteroids may result in increased fluid retention and requires careful monitoring particularly in patients with cardiac, renal or hepatic disease.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS There are insufficient long-term safety data in geriatric patients using testosterone gel, 1.62% to assess the potential risks of cardiovascular disease and prostate cancer. ( 8.5 )
8.1Pregnancy Risk Summary Testosterone gel, 1.62% is contraindicated pregnant women. Testosterone is teratogenic and may cause fetal harm when administered to a pregnanat woman based on data from animal studies and its mechanism of action [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.1 )] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in femail and male offspring. These studies did not meet current standards for nonclinical develpment toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased ano-genital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
8.2Lactation Risk Summary Testosterone gel, 1.62% is not indicated for use in women.
8.3Females and Males of Reproductive Potential Infertility Testis disorder, testicular atrophy, and oligospermia have been identified during use of AndroGel 1.62% [see Adverse Reactions ( 6.1 , 6.2 )] . During treatment with large doses of exogenous androgens, including testosterone gel, 1.62%, spermatogenesis may be suppressed through feedback inhibition of the hypothalamic-pituitary-testicular axis [see Warnings and Precautions ( 5.8 )] . Reduced fertility is observed in some men taking testosterone replacement therapy.
Testicular atrophy, subfertility, and infertility have also been reported in men who abuse anabolic androgenic steroids [see Drug Abuse and Dependence ( 9.2 )] . With either type of use, the impact on fertility may be irreversible.
8.4Pediatric Use The safety and effectiveness of testosterone gel, 1.62% in pediatric patients less than 18 years old has not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
8.5Geriatric Use There have not been sufficient numbers of geriatric patients involved in controlled clinical studies utilizing testosterone gel, 1.62% to determine whether efficacy in those over 65 years of age differs from younger subjects. Of the 234 patients enrolled in the clinical trial utilizing testosterone gel, 1.62%, 21 were over 65 years of age. Additionally, there is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer.
Geriatric patients treated with androgens may also be at risk for worsening of signs and symptoms of BPH.
8.6Renal Impairment No studies were conducted involving patients with renal impairment.
8.7Hepatic Impairment No studies were conducted in patients with hepatic impairment.
8.6Renal Impairment No studies were conducted involving patients with renal impairment.
8.7 Hepatic Impairment No…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Testosterone gel, 1.62% is contraindicated pregnant women. Testosterone is teratogenic and may cause fetal harm when administered to a pregnanat woman based on data from animal studies and its mechanism of action [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.1 )] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in femail and male offspring. These studies did not meet current standards for nonclinical develpment toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased ano-genital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of testosterone gel, 1.62% in pediatric patients less than 18 years old has not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
🧓 Geriatric Use ▾
8.5Geriatric Use There have not been sufficient numbers of geriatric patients involved in controlled clinical studies utilizing testosterone gel, 1.62% to determine whether efficacy in those over 65 years of age differs from younger subjects. Of the 234 patients enrolled in the clinical trial utilizing testosterone gel, 1.62%, 21 were over 65 years of age. Additionally, there is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer.
Geriatric patients treated with androgens may also be at risk for worsening of signs and symptoms of BPH.
🆘 Overdosage ▾
10 OVERDOSAGE There is a single report of acute overdosage after parenteral administration of an approved testosterone product in the literature. This subject had serum testosterone concentrations of up to 11,400 ng/dL, which were implicated in a cerebrovascular accident. There were no reports of overdosage in the testosterone gel, 1.62% clinical trial.
Treatment of overdosage would consist of discontinuation of testosterone gel, 1.62%, washing the application site with soap and water, and appropriate symptomatic and supportive care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT), are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of prostate, seminal vesicles, penis and scrotum; the development of male hair distribution, such as facial, pubic, chest and axillary hair; laryngeal enlargement; vocal chord thickening; and alterations in body musculature and fat distribution.
Testosterone and DHT are necessary for the normal development of secondary sex characteristics. Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has two main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, whereas secondary hypogonadism is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted using testosterone gel, 1.62%.
12.3Pharmacokinetics Absorption Testosterone gel, 1.62% delivers physiologic amounts of testosterone, producing circulating testosterone concentrations that approximate normal levels (300 – 1000 ng/dL) seen in healthy men. Testosterone gel, 1.62% provides continuous transdermal delivery of testosterone for 24 hours following once daily application to clean, dry, intact skin of the shoulders and upper arms. Average serum testosterone concentrations over 24 hours (C avg ) observed when testosterone gel, 1.62% was applied to the upper arms/shoulders were comparable to average serum testosterone concentrations (C avg ) when testosterone gel, 1.62% was applied using a rotation method utilizing the abdomen and upper arms/shoulders.
The rotation of abdomen and upper arms/shoulders was a method used in the pivotal clinical trial [see Clinical Studies ( 14.1 )] . Figure 2: Mean (±SD) Serum Total Testosterone Concentrations on Day 7 in Patients Following Testosterone Gel, 1.62% Once-Daily Application of 81 mg of Testosterone (N=33) for 7 Days Distribution Circulating testosterone is primarily bound in the serum to sex hormone-binding globulin (SHBG) and albumin. Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free) and the rest is loosely bound to albumin and other proteins.
Metabolism Testosterone is metabolized to various 17-keto steroids through two different pathways. The major active metabolites of testosterone are estradiol and DHT. Excretion There is considerable variation in the half-life of testosterone concentration as reported in the literature, ranging from 10 to 100 minutes.
About 90% of a dose of testosterone given intramuscularly is excreted in the urine as glucuronic acid and sulfuric acid conjugates of testosterone and its metabolites. About 6% of a dose is excreted in the feces, mostly in the unconjugated form. Inactivation of testosterone occurs primarily in the liver.
When testosterone gel, 1.62% treatment is discontinued, serum testosterone concentrations return to approximately baseline concentrations within 48-72 hours after administration of the last dose. Potential for testosterone transfer The potential for testosterone transfer following administration of testosterone gel, 1.62% when it was applied only to upper arms/shoulders was evaluated in two clinical studies of males dosed with testosterone gel, 1.62% and their untreated female partners. In one study, 8 male subjects applied a single dose of testosterone gel, 1.62% 81 mg to their shoulders and upper arms.
Two (2) hours after application, female subjects rubbed their hands, wrists, arms, and shoulders to the application site of the male subjects for 15 minutes. Serum concentrations of testosterone were monitored in female subjects for 24 hours after contact occurred. After direct skin-to-skin contact with the site of application, me…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT), are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of prostate, seminal vesicles, penis and scrotum; the development of male hair distribution, such as facial, pubic, chest and axillary hair; laryngeal enlargement; vocal chord thickening; and alterations in body musculature and fat distribution.
Testosterone and DHT are necessary for the normal development of secondary sex characteristics. Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has two main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, whereas secondary hypogonadism is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Testosterone gel, 1.62% is supplied in non-aerosol, metered-dose pumps that deliver 20.25 mg of testosterone per complete pump actuation. The pumps are composed of plastic and stainless steel and an LDPE/aluminum foil inner liner encased in rigid plastic with a polypropylene cap. Each 88 g metered-dose pump is capable of dispensing 75 g of gel or 60-metered pump actuations; each pump actuation dispenses 1.25 g of gel.
NDC Number Package Size 72162-1962- 2 88 g pump (each pump dispenses 60 metered pump actuations with each pump actuation containing 20.25 mg of testosterone in 1.25 g of gel) Store at controlled room temperature 20°-25°C (68°-77°F); excursions permitted to 15°- 30°C (59°- 86°F) [see USP Controlled Room Temperature]. Used testosterone gel, 1.62% pumps should be discarded in household trash in a manner that prevents accidental application or ingestion by children or pets. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Testosterone gel, 1.62% for topical use is a clear, colorless gel containing testosterone. Testosterone is an androgen. Testosterone gel, 1.62% is available in a metered-dose pump.
The active pharmacologic ingredient in testosterone gel, 1.62% is testosterone. Testosterone USP is a white to almost white powder chemically described as 17-beta hydroxyandrost-4-en-3-one. The structural formula is: The inactive ingredients in testosterone gel, 1.62% are: carbopol 980, ethyl alcohol, isopropyl myristate, purified water, and sodium hydroxide.
Alcohol 74% v/v.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Use in Men with Known or Suspected Prostate or Breast Cancer Men with known or suspected prostate or breast cancer should not use testosterone gel, 1.62% [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )] .
17.2Potential for Secondary Exposure to Testosterone and Steps to Prevent Secondary Exposure Secondary exposure to testosterone in children and women can occur with the use of testosterone gel in men [see Warnings and Precautions ( 5.2 )]. Cases of secondary exposure to testosterone have been reported in children. Physicians should advise patients of the reported signs and symptoms of secondary exposure, which may include the following: In children: unexpected sexual development including inappropriate enlargement of the penis or clitoris, premature development of pubic hair, increased erections, and aggressive behavior.
In women: changes in hair distribution, increase in acne, or other signs of testosterone effects. The possibility of secondary exposure to testosterone gel should be brought to the attention of a healthcare provider. Testosterone gel, 1.62% should be promptly discontinued until the cause of virilization is identified.
Strict adherence to the following precautions is advised to minimize the potential for secondary exposure to testosterone from testosterone gel, 1.62% in men [see Medication Guide ] : Children and women should avoid contact with unwashed or unclothed application site(s) of men using AndroGel 1.62%. Patients using AndroGel 1.62% should apply the product as directed and strictly adhere to the following: Wash hands with soap and water immediately after application. Cover the application site(s) with clothing after the gel has dried.
Wash the application site(s) thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated. In the event that unwashed or unclothed skin to which AndroGel 1.62% has been applied comes in contact with the skin of another person, the general area of contact on the other person should be washed with soap and water as soon as possible [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.2 ) and Clinical Pharmacology ( 12.3 )] .
17.3Potential Adverse Reactions with Androgens Patients should be informed that treatment with androgens may lead to adverse reactions which include: Changes in urinary habits such as increased urination at night, trouble starting the urine stream, passing urine many times during the day, having an urge to go to the bathroom right away, having a urine accident, being unable to pass urine and weak urine flow. Breathing disturbances, including those associated with sleep, or excessive daytime sleepiness. Too frequent or persistent erections of the penis.
Nausea, vomiting, changes in skin color, or ankle swelling.
17.4Patients Should Be Advised of the Following Instructions for Use Read the Medication Guide before starting testosterone gel, 1.62% therapy and to reread it each time the prescription is renewed. Testosterone gel, 1.62% should be applied and used appropriately to maximize the benefits and to minimize the risk of secondary exposure in children and women. Keep testosterone gel, 1.62% out of the reach of children.
Testosterone gel, 1.62% is an alcohol based product and is flammable; therefore avoid fire, flame or smoking until the gel has dried. It is important to adhere to all recommended monitoring. Report any changes in their state of health, such as changes in urinary habits, breathing, sleep, and mood.
Testosterone Gel, 1.62% is prescribed to meet the patient's specific needs; therefore, the patient should never share testosterone gel, 1.62% with anyone. Wait 2 hours before swimming or washing following application of testosterone gel, 1.62%. This will ensure that the greatest amount of testosterone gel, 1.62% is absorbed into their system.
Manufactured for: Xiromed, LLC Florham Park, NJ…
💬 Medication Guide ▾
MEDICATION GUIDE TESTOSTERONE (TES TOS' TER ONE) GEL, 1.62%, CIII for topical use What is the most important information I should know about TESTOSTERONE GEL, 1.62%? 1. TESTOSTERONE GEL, 1.62% can transfer from your body to others including, children and women.
Children and women should avoid contact with the unwashed or not covered (unclothed) areas where TESTOSTERONE GEL, 1.62% has been applied to your skin. Early signs and symptoms of puberty have occurred in young children who have come in direct contact with testosterone by touching areas where men have used TESTOSTERONE GEL, 1.62%. Children Signs and symptoms of early puberty in a child when they come in direct contact with TESTOSTERONE GEL, 1.62% may include: Abnormal sexual changes: enlarged penis or clitoris. early growth of hair near the vagina or around the penis (pubic hair). erections or acting out sexual urges (sex drive).
Behavior problems: acting aggressively, behaving in an angry or violent way. Women Signs and symptoms in women when they come in direct contact with TESTOSTERONE GEL, 1.62% may include: changes in body hair. an abnormal increase in pimples (acne). Stop using TESTOSTERONE GEL, 1.62% and call your healthcare provider right away if you see any signs and symptoms in a child or a woman that may have happened through accidental touching of the area where you have applied TESTOSTERONE GEL, 1.62%.
2. To lower the risk of transfer of TESTOSTERONE GEL, 1.62% from your body to others, follow these important instructions: Apply TESTOSTERONE GEL, 1.62% only to your shoulders and upper arms that will be covered by a short sleeve t-shirt. Wash your hands right away with soap and water after applying TESTOSTERONE GEL, 1.62%.
After the gel has dried, cover the application area with clothing. Keep the area covered until you have washed the application area well or have showered. If you expect to have skin-to-skin contact with another person, first wash the application area well with soap and water.
If a woman or child touches the area where you have applied TESTOSTERONE GEL, 1.62%, that area on the child or woman should be washed well with soap and water right away. What is TESTOSTERONE GEL, 1.62%? TESTOSTERONE GEL, 1.62% is a prescription medicine that contains testosterone.
TESTOSTERONE GEL, 1.62% is used to treat adult males who have low or no testosterone due to certain medical conditions. Your healthcare provider will test your blood before you start and while you are taking TESTOSTERONE GEL, 1.62%. It is not known if TESTOSTERONE GEL, 1.62% is safe or effective to treat men who have low testosterone due to aging.
It is not known if TESTOSTERONE GEL, 1.62% is safe or effective in children younger than 18 years old. Improper use of TESTOSTERONE GEL, 1.62% may affect bone growth in children. TESTOSTERONE GEL, 1.62% is a controlled substance (CIII) because it contains testosterone that can be a target for people who abuse prescription medicines.
Keep your TESTOSTERONE GEL, 1.62% in a safe place to protect it. Never give your TESTOSTERONE GEL, 1.62% to anyone else, even if they have the same symptoms you have. Selling or giving away this medicine may harm others and is against the law.TESTOSTERONE GEL, 1.62% is not meant for use in women.
Do not use TESTOSTERONE GEL, 1.62% if you: have breast cancer. have or might have prostate cancer. are pregnant. TESTOSTERONE GEL, 1.62% may harm your unborn baby. Women who are pregnant should avoid contact with the area of skin where TESTOSTERONE GEL, 1.62% has been applied.
Before you use TESTOSTERONE GEL, 1.62%, tell your healthcare provider about all of your medical conditions, including if you: have breast cancer. have or might have prostate cancer. have urinary problems due to an enlarged prostate. have heart problems. have kidney or liver problems. have problems breathing while you sleep (sleep apnea). Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines,…