
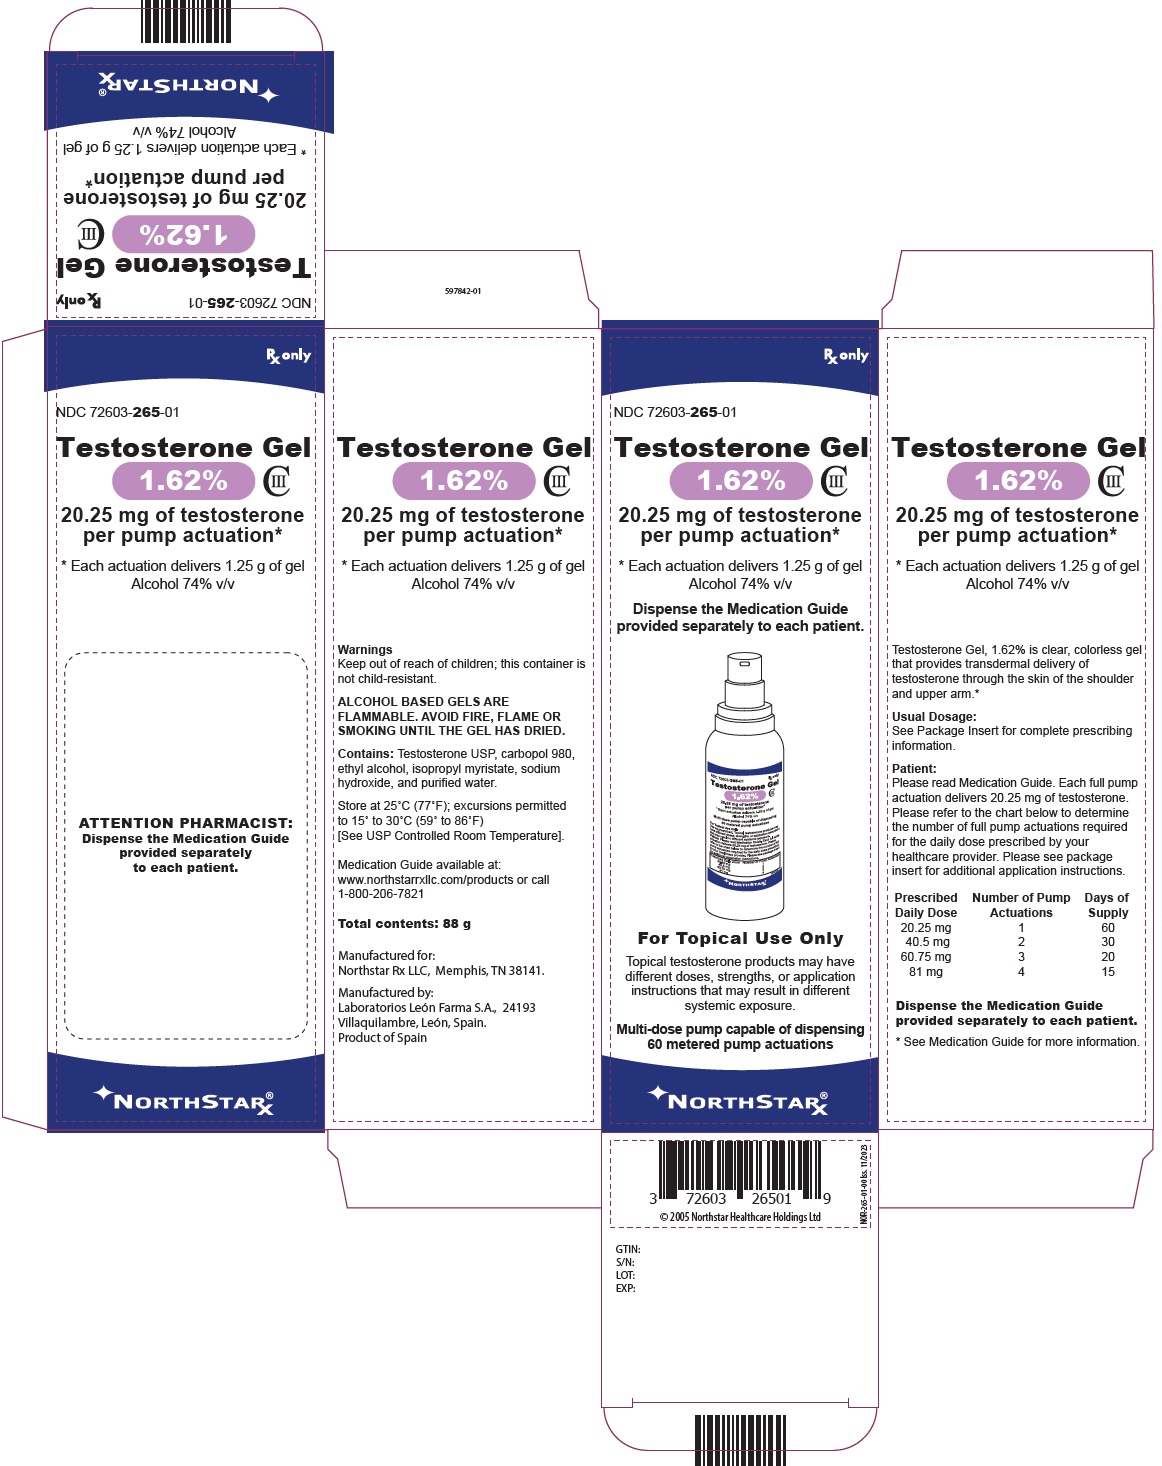
Testosterone 20.25 mg/1.25g Gel, Metered — NDC 72603-265-01 (Billing 72603-0265-01)
This is a package of Testosterone 20.25 mg/1.25g Gel, Metered from Northstar Rx LLC, marketed since Jan 2024 and currently FDA-listed; retail pharmacies pay about $0.4670 per g (NADAC). It is this product's only package size.
Other active recalls for Testosterone (different manufacturers) — 4 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067366
- GCN: 29905
- GPI-14 (Medi-Span): 23100030004050
- HICL (First Databank): 001403
- AHFS class code: 68:08.00.00
- RxCUI (RxNorm): 1597076
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Androgen class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Testosterone topical is used to treat low or no testosterone levels in men. Testosterone is in a class of medications called androgenic hormones. Testosterone is a male sex hormone responsible for development and functioning of male sexual organs and typical male characteristics. Testosterone topical works by replacing the testosterone that is normally produced by the body.
Read the full MedlinePlus article ↗- It's for adult men whose bodies make too little testosterone, called hypogonadism. Your doctor should confirm this with morning blood tests on at least two different days before st...
- Testosterone gel can pass to others through skin contact. Children and women should avoid touching unwashed or unclothed application sites, and you should follow the instructions f...
- How do I keep my family safe if I use a gel?
- Common ones include a higher PSA, mood changes, acne, higher blood pressure and skin irritation. Your doctor will check blood tests such as PSA and blood counts and monitor your bl...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Testosterone — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.467 | $41.10 / 88 g |
| Medicaid paysCMS SDUD · 12 mo | $0.6148 | $54.10 / 88 g |
| Medicare drug plans payPart D · Q2 2026 | $0.7534 | $66.30 / 88 g |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72603-0265-01 You're viewing this Main listing | 1 BOTTLE, PUMP in 1 CARTON / 88 g in 1 BOTTLE, PUMP | 2024-01-24 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Testosterone 16.2 mg/g 00591-2924-18 | Actavis | 1 bottle | $0.467 | AB | Availability likely | — |
| Testosterone 16.2 mg/g 21922-0030-20 | Encube | 1 bottle | $0.467 | AB | Availability likely | — |
| testosterone 16.2 mg/g 45802-0754-01 | Padagis | 1 bottle | $0.467 | AB | Availability likely | — |
| Testosterone 16.2 mg/g 66993-0951-88 | Prasco | 1 bottle | $0.467 | AB | Availability likely | — |
| Testosterone 16.2 mg/g 68180-0941-11 | Lupin | 1 bottle | $0.467 | AB | Availability likely | — |
| Testosterone 20.25 mg/1.25g 69238-1013-02 | Amneal | 1 bottle | $0.467 | AB | Availability likely | — |
| Testosterone 20.25 mg/1.25g 70700-0112-21 | Xiromed, | 1 bottle | $0.467 | AB | Availability likely | — |
| Testosterone 20.25 mg/1.25gthis 72603-0265-01 | Northstar | 1 bottle | $0.467 | AB | Availability likely | — |
| Testosterone 1.62 mg/g 43598-0304-88 | Dr. | 1 bottle | $0.603 | AB | FDA listed | +29% |
| AndroGel 16.2 mg/g 17139-0562-88 | ASCEND | 1 bottle | — | AB | Discontinued | — |
| Testosterone 16.2 mg/g 62332-0552-88 | Alembic | 1 bottle | — | — | FDA listed | — |
| Testosterone 20.25 mg/1.25g 63629-2352-01 | Bryant | 1 bottle | — | AB | FDA listed | — |
| testosterone 16.2 mg/g 63629-8455-01 | Bryant | 1 bottle | — | AB | FDA listed | — |
| testosterone 16.2 mg/g 71335-2742-01 | Bryant | 1 bottle | — | AB | FDA listed | — |
| testosterone 16.2 mg/g 72162-1426-02 | Bryant | 1 bottle | — | AB | FDA listed | — |
| Testosterone 20.25 mg/1.25g 72162-1962-02 | Bryant | 1 bottle | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 4Q93RCW27E
A synthetic polymer made from acrylic acid that's crosslinked for stability. It acts as a thickener and gelling agent in creams and gels, helping the medicine spread evenly and maintain its texture.
-
UNII 0RE8K4LNJS
Isopropyl myristate is an oily liquid made from coconut or palm oil. It's used in medicines as an emollient and penetration enhancer to help the medicine absorb through skin or improve spreadability in topical products.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE Virilization has been reported in children who were secondarily exposed to testosterone gel [see Warnings and Precautions ( 5.1 ) and Adverse Reactions ( 6.2 )]. Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel [see Dosage and Administration ( 2.2 ) and Warnings and Precautions ( 5.1 )]. Healthcare providers should advise patients to strictly adhere to recommended instructions for use [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.1 ) and Patient Counseling Information ( 17 )].
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE See full prescribing information for complete boxed warning. Virilization has been reported in children who were secondarily exposed to testosterone gel ( 5.2 , 6.2 ). Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel ( 2.2 , 5.2 ).
Healthcare providers should advise patients to strictly adhere to recommended instructions for use ( 2.2 , 5.2 , 17 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Testosterone gel, 1.62% is indicated for replacement therapy in adult males for conditions associated with a deficiency or absence of endogenous testosterone: Primary hypogonadism (congenital or acquired): testicular failure due to conditions such as cryptorchidism, bilateral torsion, orchitis, vanishing testis syndrome, orchiectomy, Klinefelter's syndrome, chemotherapy, or toxic damage from alcohol or heavy metals. These men usually have low serum testosterone concentrations and gonadotropins (follicle-stimulating hormone [FSH], luteinizing hormone [LH]) above the normal range.
Hypogonadotropic hypogonadism (congenital or acquired): gonadotropin or luteinizing hormone-releasing hormone (LHRH) deficiency or pituitary-hypothalamic injury from tumors, trauma, or radiation. These men have low testosterone serum concentrations, but have gonadotropins in the normal or low range. Limitations of use: Safety and efficacy of testosterone gel, 1.62% in men with “age-related hypogonadism” (also referred to as “late-onset hypogonadism”) have not been established.
Safety and efficacy of testosterone gel, 1.62% in males less than 18 years old have not been established [see Use in Specific Populations ( 8.4 )] . Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure [see Indications and Usage ( 1 ), and Clinical Pharmacology ( 12.3 )]. Testosterone gel, 1.62% is indicated for replacement therapy in males for conditions associated with a deficiency or absence of endogenous testosterone: Primary hypogonadism (congenital or acquired) ( 1 ) Hypogonadotropic hypogonadism (congenital or acquired) ( 1 ) Limitations of use: Safety and efficacy of testosterone gel, 1.62% in men with “age-related hypogonadism” have not been established.
( 1 ) Safety and efficacy of testosterone gel, 1.62% in males less than 18 years old have not been established. ( 1 , 8.4 ) Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure. ( 1 , 12.3 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Dosage and Administration for testosterone gel, 1.62% differs from testosterone gel, 1%. For dosage and administration of testosterone gel, 1% refer to its full prescribing information. ( 2 ) Prior to initiating testosterone gel, 1.62%, confirm the diagnosis of hypogonadism by ensuring that serum testosterone concentrations have been measured in the morning on at least two separate days and that these serum testosterone concentrations are below the normal range.
Dosage and Administration for testosterone gel, 1.62% differs from testosterone gel, 1%. For dosage and administration of testosterone gel, 1% refer to its full prescribing information. ( 2 ) Prior to initiating testosterone gel, 1.62%, confirm the diagnosis of hypogonadism by ensuring that serum testosterone has been measured in the morning on at least two separate days and that these concentrations are below the normal range ( 2 ).
Starting dose of testosterone gel, 1.62% is 40.5 mg of testosterone (2 pump actuations), applied topically once daily in the morning. ( 2.1 ) Apply to clean, dry, intact skin of the shoulders and upper arms. Do not apply testosterone gel, 1.62% to any other parts of the body including the abdomen, genitals, chest, armpits (axillae), or knees.
( 2.2 , 12.3 ) Dose adjustment: Testosterone gel, 1.62% can be dose adjusted between a minimum of 20.25 mg of testosterone (1 pump actuation) and a maximum of 81 mg of testosterone (4 pump actuations). The dose should be titrated based on the pre-dose morning serum testosterone concentration at approximately 14 days and 28 days after starting treatment or following dose adjustment. Additionally, serum testosterone concentration should be assessed periodically thereafter.
( 2.1 ) Patients should wash their hands immediately with soap and water after applying testosterone gel, 1.62% and cover the application site(s) with clothing after the gel has dried. Wash the application site thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated. ( 2.2 )
2.1Dosing and Dose Adjustment The recommended starting dose of testosterone gel, 1.62% is 40.5 mg of testosterone (2 pump actuations) applied topically once daily in the morning to the shoulders and upper arms. The dose can be adjusted between a minimum of 20.25 mg of testosterone (1 pump actuation) and a maximum of 81 mg of testosterone (4 pump actuations). To ensure proper dosing, the dose should be titrated based on the pre-dose morning serum testosterone concentration from a single blood draw at approximately 14 days and 28 days after starting treatment or following dose adjustment.
In addition, serum testosterone concentration should be assessed periodically thereafter. Table 1 describes the dose adjustments required at each titration step. Table 1: Dose Adjustment Criteria Pre-Dose Morning Total Serum Testosterone Concentration Dose Titration Greater than 750 ng/dL Decrease daily dose by 20.25 mg (1 pump actuation) Equal to or greater than 350 and equal to or less than 750 ng/dL No change: continue on current dose Less than 350 ng/dL Increase daily dose by 20.25 mg (1 pump actuation) The application site and dose of testosterone gel, 1.62% are not substitutable-with other topical testosterone products.
2.2Administration Instructions Testosterone gel, 1.62% should be applied to clean, dry, intact skin of the upper arms and shoulders. Do not apply testosterone gel, 1.62% to any other parts of the body, including the abdomen, genitals, chest, armpits (axillae), or knees [see Clinical Pharmacology ( 12.3 )] . Area of application should be limited to the area that will be covered by the patient's short sleeve t-shirt.
Patients should be instructed to use the palm of the hand to apply testosterone gel, 1.62% and spread across the maximum surface area as directed in Table 2 (for pump) and in Figure 1 . Table 2: Application Sites for Testosterone Gel, 1.… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Testosterone gel, 1.62% for topical use only, is available as follows: A metered-dose pump. Each pump actuation delivers 20.25 mg of testosterone in 1.25 g of gel. Testosterone gel, 1.62% for topical use is available as follows: a metered-dose pump that delivers 20.25 mg testosterone per actuation. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Testosterone gel, 1.62% is contraindicated in men with carcinoma of the breast or known or suspected carcinoma of the prostate [see Warnings and Precautions ( 5.1 ) and Adverse Reactions ( 6.1 )]. Testosterone gel, 1.62% is contraindicated in women who are pregnant. Testosterone gel, 1.62% can cause virilization of the female fetus when administered to a pregnant woman.
Pregnant women need to be aware of the potential for transfer of testosterone from men treated with testosterone gel, 1.62%. If a pregnant woman is exposed to testosterone gel, 1.62%, she should be apprised of the potential hazard to the fetus [see Warnings and Precautions ( 5.2 ) and Use in Specific Populations ( 8.1 )] . Men with carcinoma of the breast or known or suspected prostate cancer ( 4 , 5.1 ) Women who are pregnant.
Testosterone may cause fetal harm ( 4 , 8.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Worsening of Benign Prostatic Hyperplasia (BPH) and Potential Risk of Prostate Cancer: Monitor patients with benign prostatic hyperplasia (BPH) for worsening of signs and symptoms of BPH. ( 5.1 ) Potential for Secondary Exposure to Testosterone: Avoid unintentional exposure of women or children to testosterone gel, 1.62%. Secondary exposure to testosterone can produce signs of virilization.
Testosterone gel, 1.62% should be discontinued until the cause of virilization is identified. ( 5.2 ) Venous Thromboembolism (VTE): VTE, including deep vein thrombosis (DVT) and pulmonary embolism (PE) have been reported in patients using testosterone products. Evaluate patients with signs or symptoms consistent with DVT or PE.
( 5.4 ) Blood Pressure Increases: Testosterone gel, 1.62% can increase blood pressure, which can increase cardiovascular risk over time. Measure blood pressure periodically. Not recommended for use in men with uncontrolled hypertension ( 5.5 ) Potential for Adverse Effects on Spermatogenesis: Exogenous administration of androgens may lead to azoospermia.
( 5.8 ) Edema: Edema, with or without congestive heart failure (CHF), may be a complication in patients with preexisting cardiac, renal, or hepatic disease. ( 5.10 , 6.2 ) Sleep apnea: Sleep apnea may occur in those with risk factors. ( 5.12 ) Monitor serum testosterone, prostate specific antigen (PSA), hemoglobin, hematocrit, liver function tests, and lipid concentrations periodically.
( 5.1 , 5.3 , 5.9 , 5.13 ) Flammability: Testosterone gel, 1.62% is flammable until dry. ( 5.16 )
5.1Potential for Secondary Exposure to Testosterone Cases of secondary exposure resulting in virilization of children have been reported in postmarketing surveillance. Signs and symptoms have included enlargement of the penis or clitoris, development of pubic hair, increased erections and libido, aggressive behavior, and advanced bone age. In most cases, these signs and symptoms regressed with removal of the exposure to testosterone gel.
In a few cases, however, enlarged genitalia did not fully return to age-appropriate normal size, and bone age remained modestly greater than chronological age. The risk of transfer was increased in some of these cases by not adhering to precautions for the appropriate use of the topical testosterone product. Children and women should avoid contact with unwashed or unclothed application sites in men using testosterone gel, 1.62% [see Dosage and Administration ( 2.2 ), Use in Specific Populations ( 8.1 ) and Clinical Pharmacology ( 12.3 )].
Inappropriate changes in genital size or development of pubic hair or libido in children, or changes in body hair distribution, significant increase in acne, or other signs of virilization in adult women should be brought to the attention of a physician and the possibility of secondary exposure to testosterone gel should also be brought to the attention of a physician. Testosterone gel should be promptly discontinued until the cause of virilization has been identified.
5.2Polycythemia Increases in hematocrit, reflective of increases in red blood cell mass, may require lowering or discontinuation of testosterone. Check hematocrit prior to initiating treatment. It would also be appropriate to re-evaluate the hematocrit 3 to 6 months after starting treatment, and then annually.
If hematocrit becomes elevated, stop therapy until hematocrit decreases to an acceptable concentration. An increase in red blood cell mass may increase the risk of thromboembolic events.
5.3Venous Thromboembolism There have been postmarketing reports of venous thromboembolic events (VTE), including deep vein thrombosis (DVT) and pulmonary embolism (PE), in patients using testosterone products such as testosterone gel, 1.62%. In the Testosterone Replacement therapy for Assessment of long-term Vascular Events and efficacy ResponSE in hypogonadal men (TRAVERSE) Study, a randomized, double-blind, placebo-controlled, cardiova… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reaction (incidence ≥ 5%) is an increase in prostate specific antigen (PSA). ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Northstar Rx LLC at 1-800-206-7821 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Testosterone gel, 1.62% was evaluated in a two-phase, 364-day, controlled clinical study. The first phase was a multi-center, randomized, double-blind, parallel-group, placebo-controlled period of 182 days, in which 234 hypogonadal men were treated with testosterone gel, 1.62% and 40 received placebo.
Patients could continue in an open-label, non-comparative, maintenance period for an additional 182 days [see Clinical Studies ( 14.1 )]. The most common adverse reaction reported in the double-blind period was increased prostate specific antigen (PSA) reported in 26 testosterone gel, 1.62%-treated patients (11.1%). In 17 patients, increased PSA was considered an adverse event by meeting one of the two pre-specified criteria for abnormal PSA values, defined as (1) average serum PSA >4 ng/mL based on two separate determinations, or (2) an average change from baseline in serum PSA of greater than 0.75 ng/mL on two determinations.
During the 182-day, double-blind period of the clinical trial, the mean change in serum PSA value was 0.14 ng/mL for patients receiving testosterone gel, 1.62% and -0.12 ng/mL for the patients in the placebo group. During the double-blind period, seven patients had a PSA value >4.0 ng/mL, four of these seven patients had PSA less than or equal to 4.0 ng/mL upon repeat testing. The other three patients did not undergo repeat PSA testing.
During the 182-day, open-label period of the study, the mean change in serum PSA values was 0.10 ng/mL for both patients continuing on active therapy and patients transitioning onto active from placebo. During the open-label period, three patients had a serum PSA value > 4.0 ng/mL, two of whom had a serum PSA less than or equal to 4.0 ng/mL upon repeated testing. The other patient did not undergo repeat PSA testing.
Among previous placebo patients, 3 of 28 (10.7%), had increased PSA as an adverse event in the open-label period. Table 4 shows adverse reactions reported by >2% of patients in the 182-day, double-blind period of the testosterone gel, 1.62% clinical trial and more frequent in the testosterone gel, 1.62% treated group versus placebo. Table 4: Adverse Reactions Reported in >2% of Patients in the 182-Day, Double-Blind Period of Testosterone Gel, 1.62% Clinical Trial Number (%) of Patients Adverse Reaction Testosterone Gel, 1.62% N=234 Placebo N=40 PSA increased* 26 (11.1%) 0% Emotional lability** 6 (2.6%) 0% Hypertension 5 (2.1%) 0% Hematocrit or hemoglobin increased 5 (2.1%) 0% Contact dermatitis*** 5 (2.1%) 0% * PSA increased includes: PSA values that met pre-specified criteria for abnormal PSA values (an average change from baseline > 0.75 ng/mL and/or an average PSA value >4.0 ng/mL based on two measurements) as well as those reported as adverse events. ** Emotional lability includes: mood swings, affective disorder, impatience, anger, and aggression. *** Contact dermatitis includes: 4 patients with dermatitis at non-application sites.
Other adverse reactions occurring in less than or equal to 2% of testosterone gel, 1.62%-treated patients and more frequently than placebo included: frequent urination, and hyperlipidemia. In the open-label period of the study (N=191), the most commonly reported adverse reaction (experienced by greater than 2% of patients) was increased PSA (n=13; 6.2%) and sinusitis. Other adverse reactions reported by less than or equal to 2% of patients included increased hemoglobin or hematocrit,… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Androgens may decrease blood glucose and therefore may decrease insulin requirements in diabetic patients ( 7.1 ) Changes in anticoagulant activity may be seen with androgens. More frequent monitoring of International Normalized Ratio (INR) and prothrombin time is recommended ( 7.2 ) Use of testosterone with adrenocorticotrophic hormone (ACTH) or corticosteroids may result in increased fluid retention. Use with caution, particularly in patients with cardiac, renal, or hepatic disease ( 7.3 )
7.1Insulin Changes in insulin sensitivity or glycemic control may occur in patients treated with androgens. In diabetic patients, the metabolic effects of androgens may decrease blood glucose and, therefore, may decrease insulin requirements.
7.2Oral Anticoagulants Changes in anticoagulant activity may be seen with androgens, therefore more frequent monitoring of international normalized ratio (INR) and prothrombin time are recommended in patients taking anticoagulants, especially at the initiation and termination of androgen therapy.
7.3Corticosteroids The concurrent use of testosterone with adrenocorticotropic hormone (ACTH) or corticosteroids may result in increased fluid retention and requires careful monitoring particularly in patients with cardiac, renal or hepatic disease.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS There are insufficient long-term safety data in geriatric patients using testosterone gel, 1.62% to assess the potential risks of cardiovascular disease and prostate cancer. ( 8.5 )
8.1Pregnancy Risk Summary Testosterone gel, 1.62% is contraindicated in pregnant women. Testosterone is teratogenic and may cause fetal harm when administered to a pregnant woman based on data from animal studies and its mechanism of action [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.1 )] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies did not meet current standards for nonclinical development toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased ano-genital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
8.2Lactation Risk Summary Testosterone gel, 1.62% is not indicated for use in women.
8.3Females and Males of Reproductive Potential Infertility Testis disorder, testicular atrophy, and oligospermia have been identified during use of testosterone gel, 1.62% [see Adverse Reactions ( 6.1 , 6.2 )] . During treatment with large doses of exogenous androgens, including testosterone gel, 1.62%, spermatogenesis may be suppressed through feedback inhibition of the hypothalamic-pituitary-testicular axis [see Warnings and Precautions ( 5.8 )] . Reduced fertility is observed in some men taking testosterone replacement therapy.
Testicular atrophy, subfertility, and infertility have also been reported in men who abuse anabolic androgenic steroids [see Drug Abuse and Dependence ( 9.2 )] . With either type of use, the impact on fertility may be irreversible.
8.4Pediatric Use The safety and effectiveness of testosterone gel, 1.62% in pediatric patients less than 18 years old has not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
8.5Geriatric Use There have not been sufficient numbers of geriatric patients involved in controlled clinical studies utilizing testosterone gel, 1.62% to determine whether efficacy in those over 65 years of age differs from younger subjects. Of the 234 patients enrolled in the clinical trial utilizing testosterone gel, 1.62%, 21 were over 65 years of age. Additionally, there is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer.
Geriatric patients treated with androgens may also be at risk for worsening of signs and symptoms of BPH.
8.6Renal Impairment No studies were conducted involving patients with renal impairment.
8.7Hepatic Impairment No studies were conducted in patients with hepatic impairment.
8.6Renal Impairment No studies were conducted involving patients with renal impairment.
8.7Hepatic I… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Testosterone gel, 1.62% is contraindicated in pregnant women. Testosterone is teratogenic and may cause fetal harm when administered to a pregnant woman based on data from animal studies and its mechanism of action [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.1 )] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies did not meet current standards for nonclinical development toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased ano-genital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of testosterone gel, 1.62% in pediatric patients less than 18 years old has not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
🧓 Geriatric Use ▾
8.5Geriatric Use There have not been sufficient numbers of geriatric patients involved in controlled clinical studies utilizing testosterone gel, 1.62% to determine whether efficacy in those over 65 years of age differs from younger subjects. Of the 234 patients enrolled in the clinical trial utilizing testosterone gel, 1.62%, 21 were over 65 years of age. Additionally, there is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer.
Geriatric patients treated with androgens may also be at risk for worsening of signs and symptoms of BPH.
🆘 Overdosage ▾
10 OVERDOSAGE There is a single report of acute overdosage after parenteral administration of an approved testosterone product in the literature. This subject had serum testosterone concentrations of up to 11,400 ng/dL, which were implicated in a cerebrovascular accident. There were no reports of overdosage in the testosterone gel, 1.62% clinical trial.
Treatment of overdosage would consist of discontinuation of testosterone gel, 1.62%, washing the application site with soap and water, and appropriate symptomatic and supportive care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT), are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of prostate, seminal vesicles, penis and scrotum; the development of male hair distribution, such as facial, pubic, chest and axillary hair; laryngeal enlargement; vocal cord thickening; and alterations in body musculature and fat distribution.
Testosterone and DHT are necessary for the normal development of secondary sex characteristics. Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has two main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, whereas secondary hypogonadism is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted using testosterone gel, 1.62%.
12.3Pharmacokinetics Absorption Testosterone gel, 1.62% delivers physiologic amounts of testosterone, producing circulating testosterone concentrations that approximate normal levels (300 – 1000 ng/dL) seen in healthy men. Testosterone gel, 1.62% provides continuous topical delivery of testosterone for 24 hours following once daily application to clean, dry, intact skin of the shoulders and upper arms. Average serum testosterone concentrations over 24 hours (C avg ) observed when testosterone gel, 1.62% was applied to the upper arms/shoulders were comparable to average serum testosterone concentrations (C avg ) when testosterone gel, 1.62% was applied using a rotation method utilizing the abdomen and upper arms/shoulders.
The rotation of abdomen and upper arms/shoulders was a method used in the pivotal clinical trial [see Clinical Studies ( 14.1 )] . Figure 2: Mean (±SD) Serum Total Testosterone Concentrations on Day 7 in Patients Following Testosterone Gel, 1.62% Once-Daily Application of 81 mg of Testosterone (N=33) for 7 Days Distribution Circulating testosterone is primarily bound in the serum to sex hormone-binding globulin (SHBG) and albumin. Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free) and the rest is loosely bound to albumin and other proteins.
Metabolism Testosterone is metabolized to various 17-keto steroids through two different pathways. The major active metabolites of testosterone are estradiol and DHT. Excretion There is considerable variation in the half-life of testosterone concentration as reported in the literature, ranging from 10 to 100 minutes.
About 90% of a dose of testosterone given intramuscularly is excreted in the urine as glucuronic acid and sulfuric acid conjugates of testosterone and its metabolites. About 6% of a dose is excreted in the feces, mostly in the unconjugated form. Inactivation of testosterone occurs primarily in the liver.
When testosterone gel, 1.62% treatment is discontinued, serum testosterone concentrations return to approximately baseline concentrations within 48-72 hours after administration of the last dose. Potential for testosterone transfer The potential for testosterone transfer following administration of testosterone gel, 1.62% when it was applied only to upper arms/shoulders was evaluated in two clinical studies of males dosed with testosterone gel, 1.62% and their untreated female partners. In one study, 8 male subjects applied a single dose of testosterone gel, 1.62% 81 mg to their shoulders and upper arms.
Two (2) hours after application, female subjects rubbed their hands, wrists, arms, and shoulders to the application site of the male subjects for 15 minutes. Serum concentrations of testosterone were monitored in female subjects for 24 hours after contact occurred. After direct skin-to-skin contact with the site of application, mean te… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT), are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of prostate, seminal vesicles, penis and scrotum; the development of male hair distribution, such as facial, pubic, chest and axillary hair; laryngeal enlargement; vocal cord thickening; and alterations in body musculature and fat distribution.
Testosterone and DHT are necessary for the normal development of secondary sex characteristics. Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has two main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, whereas secondary hypogonadism is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Testosterone gel, 1.62% is supplied in non-aerosol, metered-dose pumps that deliver 20.25 mg of testosterone per complete pump actuation. The pumps are composed of plastic and stainless steel and an LDPE/aluminum foil inner liner encased in rigid plastic with a polypropylene cap. Each 88 g metered-dose pump is capable of dispensing 75 g of gel or 60-metered pump actuations; each pump actuation dispenses 1.25 g of gel.
NDC Number Package Size 72603-265-01 88 g pump (each pump dispenses 60 metered pump actuations with each pump actuation containing 20.25 mg of testosterone in 1.25 g of gel) Store at controlled room temperature 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Used testosterone gel, 1.62% pumps should be discarded in household trash in a manner that prevents accidental application or ingestion by children or pets.
📋 Description ▾
11 DESCRIPTION Testosterone gel, 1.62% for topical use is a clear, colorless gel containing testosterone. Testosterone is an androgen. Testosterone gel, 1.62% is available in a metered-dose pump.
The active pharmacologic ingredient in testosterone gel, 1.62% is testosterone. Testosterone USP is a white to almost white powder chemically described as 17-beta hydroxyandrost-4-en-3-one. The structural formula is: The inactive ingredients in testosterone gel, 1.62% are: carbopol 980, ethyl alcohol, isopropyl myristate, purified water, and sodium hydroxide.
Alcohol 74% v/v.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Patients should be informed of the following:
17.1Use in Men with Known or Suspected Prostate or Breast Cancer Men with known or suspected prostate or breast cancer should not use testosterone gel, 1.62% [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )] .
17.2Potential for Secondary Exposure to Testosterone and Steps to Prevent Secondary Exposure Secondary exposure to testosterone in children and women can occur with the use of testosterone gel in men [see Warnings and Precautions ( 5.2 )]. Cases of secondary exposure to testosterone have been reported in children. Physicians should advise patients of the reported signs and symptoms of secondary exposure, which may include the following: In children: unexpected sexual development including inappropriate enlargement of the penis or clitoris, premature development of pubic hair, increased erections, and aggressive behavior.
In women: changes in hair distribution, increase in acne, or other signs of testosterone effects. The possibility of secondary exposure to testosterone gel should be brought to the attention of a healthcare provider. Testosterone gel, 1.62% should be promptly discontinued until the cause of virilization is identified.
Strict adherence to the following precautions is advised to minimize the potential for secondary exposure to testosterone from testosterone gel, 1.62% in men [see Medication Guide ] : Children and women should avoid contact with unwashed or unclothed application site(s) of men using testosterone gel, 1.62%. Patients using testosterone gel, 1.62% should apply the product as directed and strictly adhere to the following: Wash hands with soap and water immediately after application. Cover the application site(s) with clothing after the gel has dried.
Wash the application site(s) thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated. In the event that unwashed or unclothed skin to which testosterone gel, 1.62% has been applied comes in contact with the skin of another person, the general area of contact on the other person should be washed with soap and water as soon as possible [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.2 ) and Clinical Pharmacology ( 12.3 )] .
17.3Potential for Venous Thromboembolism Inform patients that testosterone gel, 1.62% can cause venous thromboembolism. Advise patients of the signs and symptoms of venous thromboembolism, which may include the following: lower limb pain, edema, or erythema; and dyspnea or chest pain. Advise patients to promptly report the signs and symptoms of venous thromboembolism, discontinue use of testosterone gel, 1.62%, and seek urgent medical care.
17.4Potential for Increase in Blood Pressure Inform patients that testosterone gel, 1.62% can increase BP which can increase cardiovascular risk over time. Instruct patients about the importance of monitoring BP periodically while on testosterone gel, 1.62%. If BP increases while on testosterone gel, 1.62%, antihypertensive medications may need to be started, added, or adjusted to control BP, or testosterone gel, 1.62% may need to be discontinued.
17.5Potential Adverse Reactions with Androgens Patients should be informed that treatment with androgens may lead to adverse reactions which include: Changes in urinary habits such as increased urination at night, trouble starting the urine stream, passing urine many times during the day, having an urge to go to the bathroom right away, having a urine accident, being unable to pass urine and weak urine flow. Breathing disturbances, including those associated with sleep, or excessive daytime sleepiness. Too frequent or persistent erections of the penis.
Nausea, vomiting, changes in skin color, or ankle swelling.
17.6Patients Should Be Advised of the Following Instruct… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE TESTOSTERONE (TES TOS' TER ONE) GEL, 1.62%, CIII for topical use What is the most important information I should know about TESTOSTERONE GEL, 1.62%? 1. TESTOSTERONE GEL, 1.62% can transfer from your body to others including, children and women.
Children and women should avoid contact with the unwashed or not covered (unclothed) areas where TESTOSTERONE GEL, 1.62% has been applied to your skin. Early signs and symptoms of puberty have occurred in young children who have come in direct contact with testosterone by touching areas where men have used TESTOSTERONE GEL, 1.62%. Children Signs and symptoms of early puberty in a child when they come in direct contact with TESTOSTERONE GEL, 1.62% may include: Abnormal sexual changes: enlarged penis or clitoris. early growth of hair near the vagina or around the penis (pubic hair). erections or acting out sexual urges (sex drive).
Behavior problems: acting aggressively, behaving in an angry or violent way. Women Signs and symptoms in women when they come in direct contact with TESTOSTERONE GEL, 1.62% may include: changes in body hair. an abnormal increase in pimples (acne). Stop using TESTOSTERONE GEL, 1.62% and call your healthcare provider right away if you see any signs and symptoms in a child or a woman that may have happened through accidental touching of the area where you have applied TESTOSTERONE GEL, 1.62%.
2. To lower the risk of transfer of TESTOSTERONE GEL, 1.62% from your body to others, follow these important instructions: Apply TESTOSTERONE GEL, 1.62% only to your shoulders and upper arms that will be covered by a short sleeve t-shirt. Wash your hands right away with soap and water after applying TESTOSTERONE GEL, 1.62%.
After the gel has dried, cover the application area with clothing. Keep the area covered until you have washed the application area well or have showered. If you expect to have skin-to-skin contact with another person, first wash the application area well with soap and water.
If a child or woman touches the area where you have applied TESTOSTERONE GEL, 1.62%, that area on the child or woman should be washed well with soap and water right away. What is TESTOSTERONE GEL, 1.62%? TESTOSTERONE GEL, 1.62% is a prescription medicine that contains testosterone.
TESTOSTERONE GEL, 1.62% is used to treat adult males who have low or no testosterone due to certain medical conditions. Your healthcare provider will test your blood before you start and while you are using TESTOSTERONE GEL, 1.62%. It is not known if TESTOSTERONE GEL, 1.62% is safe or effective to treat men who have low testosterone due to aging.
It is not known if TESTOSTERONE GEL, 1.62% is safe or effective in children younger than 18 years old. Improper use of TESTOSTERONE GEL, 1.62% may affect bone growth in children. TESTOSTERONE GEL, 1.62% is a controlled substance (CIII) because it contains testosterone that can be a target for people who abuse prescription medicines.
Keep your TESTOSTERONE GEL, 1.62% in a safe place to protect it. Never give your TESTOSTERONE GEL, 1.62% to anyone else, even if they have the same symptoms you have. Selling or giving away this medicine may harm others and is against the law.
TESTOSTERONE GEL, 1.62% is not meant for use in women. Do not use TESTOSTERONE GEL, 1.62% if you: have breast cancer. have or might have prostate cancer. are pregnant. TESTOSTERONE GEL, 1.62% may harm your unborn baby.
Women who are pregnant should avoid contact with the area of skin where TESTOSTERONE GEL, 1.62% has been applied. Before using TESTOSTERONE GEL, 1.62%, tell your healthcare provider about all of your medical conditions, including if you: have breast cancer. have or might have prostate cancer. have urinary problems due to an enlarged prostate. have heart problems. have high blood pressure or are being treated for high blood pressure. have kidney or liver problems. have problems breathing while you sleep (sleep apnea).
Tell your healthcare provider about all the medic… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Testosterone gel, 1.62% delivers physiologic amounts of testosterone, producing circulating testosterone concentrations that approximate normal levels (300 – 1000 ng/dL) seen in healthy men. Testosterone gel, 1.62% provides continuous topical delivery of testosterone for 24 hours following once daily application to clean, dry, intact skin of the shoulders and upper arms. Average serum testosterone concentrations over 24 hours (C avg ) observed when testosterone gel, 1.62% was applied to the upper arms/shoulders were comparable to average serum testosterone concentrations (C avg ) when testosterone gel, 1.62% was applied using a rotation method utilizing the abdomen and upper arms/shoulders.
The rotation of abdomen and upper arms/shoulders was a method used in the pivotal clinical trial [see Clinical Studies ( 14.1 )] . Figure 2: Mean (±SD) Serum Total Testosterone Concentrations on Day 7 in Patients Following Testosterone Gel, 1.62% Once-Daily Application of 81 mg of Testosterone (N=33) for 7 Days Distribution Circulating testosterone is primarily bound in the serum to sex hormone-binding globulin (SHBG) and albumin. Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free) and the rest is loosely bound to albumin and other proteins.
Metabolism Testosterone is metabolized to various 17-keto steroids through two different pathways. The major active metabolites of testosterone are estradiol and DHT. Excretion There is considerable variation in the half-life of testosterone concentration as reported in the literature, ranging from 10 to 100 minutes.
About 90% of a dose of testosterone given intramuscularly is excreted in the urine as glucuronic acid and sulfuric acid conjugates of testosterone and its metabolites. About 6% of a dose is excreted in the feces, mostly in the unconjugated form. Inactivation of testosterone occurs primarily in the liver.
When testosterone gel, 1.62% treatment is discontinued, serum testosterone concentrations return to approximately baseline concentrations within 48-72 hours after administration of the last dose. Potential for testosterone transfer The potential for testosterone transfer following administration of testosterone gel, 1.62% when it was applied only to upper arms/shoulders was evaluated in two clinical studies of males dosed with testosterone gel, 1.62% and their untreated female partners. In one study, 8 male subjects applied a single dose of testosterone gel, 1.62% 81 mg to their shoulders and upper arms.
Two (2) hours after application, female subjects rubbed their hands, wrists, arms, and shoulders to the application site of the male subjects for 15 minutes. Serum concentrations of testosterone were monitored in female subjects for 24 hours after contact occurred. After direct skin-to-skin contact with the site of application, mean testosterone C avg and C max in female subjects increased by 280% and 267%, respectively, compared to mean baseline testosterone concentrations.
In a second study evaluating transfer of testosterone, 12 male subjects applied a single dose of testosterone gel, 1.62% 81 mg to their shoulders and upper arms. Two (2) hours after application, female subjects rubbed their hands, wrists, arms, and shoulders to the application site of the male subjects for 15 minutes while the site of application was covered by a t-shirt. When a t-shirt was used to cover the site of application, mean testosterone C avg and C max in female subjects increased by 6% and 11%, respectively, compared to mean baseline testosterone concentrations.
A separate study was conducted to evaluate the potential for testosterone transfer from 16 males dosed with testosterone gel, 1.62% 81 mg when it was applied to abdomen only for 7 days, a site of application not approved for testosterone gel, 1.62%. Two (2) hours after application to the males on each day, the female subjects rubbed their abdomens for 15 minutes to the abdomen of the… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted using testosterone gel, 1.62%.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Clinical Trials in Hypogonadal Males Testosterone gel, 1.62% was evaluated in a multi-center, randomized, double-blind, parallel-group, placebo-controlled study (182-day double-blind period) in 274 hypogonadal men with body mass index (BMI) 18-40 kg/m 2 and 18-80 years of age (mean age 53.8 years). The patients had an average serum testosterone concentration of <300 ng/dL, as determined by two morning samples collected on the same visit. Patients were Caucasian 83%, Black 13%, Asian or Native American 4%.
7.5% of patients were Hispanic. Patients were randomized to receive active treatment or placebo using a rotation method utilizing the abdomen and upper arms/shoulders for 182 days. All patients were started at a daily dose of 40.5 mg (two pump actuations) testosterone gel, 1.62% or matching placebo on Day 1 of the study.
Patients returned to the clinic on Day 14, Day 28, and Day 42 for predose serum total testosterone assessments. The patient's daily dose was titrated up or down in 20.25 mg increments if the predose serum testosterone value was outside the range of 350-750 ng/dL. The study included four active testosterone gel, 1.62% doses: 20.25 mg, 40.5 mg, 60.75 mg, and 81 mg daily.
The primary endpoint was the percentage of patients with C avg within the normal range of 300-1000 ng/dL on Day 112. In patients treated with testosterone gel, 1.62%, 81.6% (146/179) had C avg within the normal range at Day 112. The secondary endpoint was the percentage of patients, with C max above three pre-determined limits.
The percentages of patients with C max greater than 1500 ng/dL, and between 1800 and 2499 ng/dL on Day 112 were 11.2% and 5.5%, respectively. Two patients had a C max >2500 ng/dL on Day 112 (2510 ng/dL and 2550 ng/dL, respectively); neither of these 2 patients demonstrated an abnormal C max on prior or subsequent assessments at the same dose. Patients could agree to continue in an open-label, active treatment maintenance period of the study for an additional 182 days.
Dose titrations on Days 14, 28, and 42 resulted in final doses of 20.25 mg – 81 mg on Day 112 as shown in Table 6 . Table 6: Mean (SD) Testosterone Concentrations (C avg and C max ) by final dose on Days 112 and 364 Parameter Final Dose on Day 112 Placebo (n=27) 20.25 mg (n=12) 40.5 mg (n=34) 60.75 mg (n=54) 81 mg (n=79) All Active (n=179) C avg (ng/dL) 303 (135) 457 (275) 524 (228) 643 (285) 537 (240) 561 (259) C max (ng/dL) 450 (349) 663 (473) 798 (439) 958 (497) 813 (479) 845 (480) Final Dose on Day 364 20.25 mg (n=7) 40.5 mg (n=26) 60.75 mg (n=29) 81 mg (n=74) Continuing Active (n=136) C avg (ng/dL) 386 (130) 474 (176) 513 (222) 432 (186) 455 (192) C max (ng/dL) 562 (187) 715 (306) 839 (568) 649 (329) 697 (389) Figure 3 summarizes the pharmacokinetic profile of total testosterone in patients completing 112 days of testosterone gel, 1.62% treatment administered as a starting dose of 40.5 mg of testosterone (2 pump actuations) for the initial 14 days followed by possible titration according to the follow-up testosterone measurements.
Figure 3: Mean (±SD) Steady-State Serum Total Testosterone Concentrations on Day 112 Efficacy was maintained in the group of men that received testosterone gel, 1.62% for one full year. In that group, 78% (106/136) had average serum testosterone concentrations in the normal range at Day 364. Figure 4 summarizes the mean total testosterone profile for these patients on Day 364.
Figure 4: Mean (±SD) Steady-State Serum Total Testosterone Concentrations on Day 364 The mean estradiol and DHT concentration profiles paralleled the changes observed in testosterone. The levels of LH and FSH decreased with testosterone treatment. The decreases in levels of LH and FSH are consistent with reports published in the literature of long-term treatment with testosterone.
14.1Clinical Trials in Hypogonadal Males Testosterone gel, 1.62% was evaluated in a multi-center, randomized, double-blind, parallel-group, placebo-… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Testosterone gel, 1.62% contains testosterone, a Schedule III controlled substance in the Controlled Substances Act.
9.2Abuse Drug abuse is intentional non-therapeutic use of a drug, even once, for its rewarding psychological and physiological effects. Abuse and misuse of testosterone are seen in male and female adults and adolescents. Testosterone, often in combination with other anabolic androgenic steroids (AAS), and not obtained by prescription through a pharmacy, may be abused by athletes and bodybuilders.
There have been reports of misuse by men taking higher doses of legally obtained testosterone than prescribed and continuing testosterone despite adverse events or against medical advice. Abuse-Related Adverse Reactions Serious adverse reactions have been reported in individuals who abuse anabolic androgenic steroids and include cardiac arrest, myocardial infarction, hypertrophic cardiomyopathy, congestive heart failure, cerebrovascular accident, hepatotoxicity, and serious psychiatric manifestations, including major depression, mania, paranoia, psychosis, delusions, hallucinations, hostility and aggression.
The following adverse reactions have also been reported in men: transient ischemic attacks, convulsions, hypomania, irritability, dyslipidemias, testicular atrophy, subfertility, and infertility. The following additional adverse reactions have been reported in women: hirsutism, virilization, deepening of voice, clitoral enlargement, breast atrophy, male-pattern baldness, and menstrual irregularities. The following adverse reactions have been reported in male and female adolescents: premature closure of bony epiphyses with termination of growth, and precocious puberty.
Because these reactions are reported voluntarily from a population of uncertain size and may include abuse of other agents, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
9.3Dependence Behaviors Associated with Addiction Continued abuse of testosterone and other anabolic steroids, leading to addiction is characterized by the following behaviors: Taking greater dosages than prescribed Continued drug use despite medical and social problems due to drug use Spending significant time to obtain the drug when supplies of the drug are interrupted Giving a higher priority to drug use than other obligations Having difficulty in discontinuing the drug despite desires and attempts to do so Experiencing withdrawal symptoms upon abrupt discontinuation of use Physical dependence is characterized by withdrawal symptoms after abrupt drug discontinuation or a significant dose reduction of a drug.
Individuals taking supratherapeutic doses of testosterone may experience withdrawal symptoms lasting for weeks or months which include depressed mood, major depression, fatigue, craving, restlessness, irritability, anorexia, insomnia, decreased libido and hypogonadotropic hypogonadism. Drug dependence in individuals using approved doses of testosterone for approved indications has not been documented.
🔒 Controlled Substance ▾
9.1Controlled Substance Testosterone gel, 1.62% contains testosterone, a Schedule III controlled substance in the Controlled Substances Act.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Testosterone has been tested by subcutaneous injection and implantation in mice and rats. In mice, the implant induced cervical-uterine tumors which metastasized in some cases. There is suggestive evidence that injection of testosterone into some strains of female mice increases their susceptibility to hepatoma.
Testosterone is also known to increase the number of tumors and decrease the degree of differentiation of chemically induced carcinomas of the liver in rats. Mutagenesis Testosterone was negative in the in vitro Ames and in the in vivo mouse micronucleus assays. Impairment of Fertility The administration of exogenous testosterone has been reported to suppress spermatogenesis in rats, dogs, and non-human primates, which was reversible on cessation of the treatment.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Testosterone has been tested by subcutaneous injection and implantation in mice and rats. In mice, the implant induced cervical-uterine tumors which metastasized in some cases. There is suggestive evidence that injection of testosterone into some strains of female mice increases their susceptibility to hepatoma.
Testosterone is also known to increase the number of tumors and decrease the degree of differentiation of chemically induced carcinomas of the liver in rats. Mutagenesis Testosterone was negative in the in vitro Ames and in the in vivo mouse micronucleus assays. Impairment of Fertility The administration of exogenous testosterone has been reported to suppress spermatogenesis in rats, dogs, and non-human primates, which was reversible on cessation of the treatment.
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE TESTOSTERONE (TES TOS' TER ONE) GEL, 1.62%, CIII for topical use Read this Instructions for Use for TESTOSTERONE GEL, 1.62% before you start using it and each time you get a refill. There may be new information. This leaflet does not take the place of talking to your healthcare provider about your medical condition or treatment.
Applying TESTOSTERONE GEL, 1.62%: TESTOSTERONE GEL, 1.62% comes in a pump. Before applying TESTOSTERONE GEL, 1.62% make sure that your shoulders and upper arms are clean, dry, and that there is no broken skin. TESTOSTERONE GEL, 1.62% is to be applied to the area of your shoulders and upper arms that will be covered by a short sleeve t-shirt (See Figure A).
Do not apply TESTOSTERONE GEL, 1.62% to any other parts of your body such as your stomach area (abdomen), penis, scrotum, chest, armpits (axillae), or knees. (Figure A) If you are using TESTOSTERONE GEL, 1.62% pump: Before using a new bottle of TESTOSTERONE GEL, 1.62% for the first time, you will need to remove the cap and then prime the pump. To prime the TESTOSTERONE GEL, 1.62% pump, slowly push the pump all the way down 3 times, over the sink drain.
Do not use any TESTOSTERONE GEL, 1.62% that came out while priming. Wash it down the sink to avoid accidental exposure to others. Your TESTOSTERONE GEL, 1.62% pump is now ready to use.
Remove the cap from the pump. Then, put the spout opening at the top of the pump where the medicine comes out over the palm of your hand and slowly push the pump all the way down. Apply TESTOSTERONE GEL, 1.62% to the application site.
You may also apply TESTOSTERONE GEL, 1.62% directly to the application site. Your healthcare provider will tell you the number of times to press the pump for each dose. Wash your hands with soap and water right away.
Find Your Dose as Prescribed by Your Healthcare Provider Application Method 1 pump 20.25 mg Apply 1 pump of TESTOSTERONE GEL, 1.62% to 1 upper arm and shoulder. 2 pumps 40.5 mg Apply 1 pump of TESTOSTERONE GEL, 1.62% to 1 upper arm and shoulder and then apply 1 pump of TESTOSTERONE GEL, 1.62% to the opposite upper arm and shoulder. 3 pumps 60.75 mg Apply 2 pumps of TESTOSTERONE GEL, 1.62% to 1 upper arm and shoulder and then apply 1 pump of TESTOSTERONE GEL, 1.62% to the opposite upper arm and shoulder.
4 pumps 81 mg Apply 2 pumps of TESTOSTERONE GEL, 1.62% to 1 upper arm and shoulder and then apply 2 pumps of TESTOSTERONE GEL, 1.62% to the opposite upper arm and shoulder. How should I store TESTOSTERONE GEL, 1.62%? Store TESTOSTERONE GEL, 1.62% at room temperature between 68ºF to 77ºF (20ºC to 25ºC).
When it is time to throw away the pump, safely throw away used TESTOSTERONE GEL, 1.62% in household trash. Be careful to prevent accidental exposure of children or pets. Keep TESTOSTERONE GEL, 1.62% away from fire.
Keep TESTOSTERONE GEL, 1.62% and all medicines out of the reach of children. This Instructions for Use has been approved by the U.S. Food and Drug Administration.
Revised: 07/2025 NOR-PI-265-01
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES SECTION Warnings and Precautions, Venous Thromboembolism ( 5.3 ) 07/2025 Warnings and Precautions, Blood Pressure Increases ( 5.5 ) 07/2025 Warnings and Precautions, Cardiovascular Risk ( 5.5 ) Removed 07/2025
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL PRINCIPAL DISPLAY PANEL - 88g Bottle Carton