
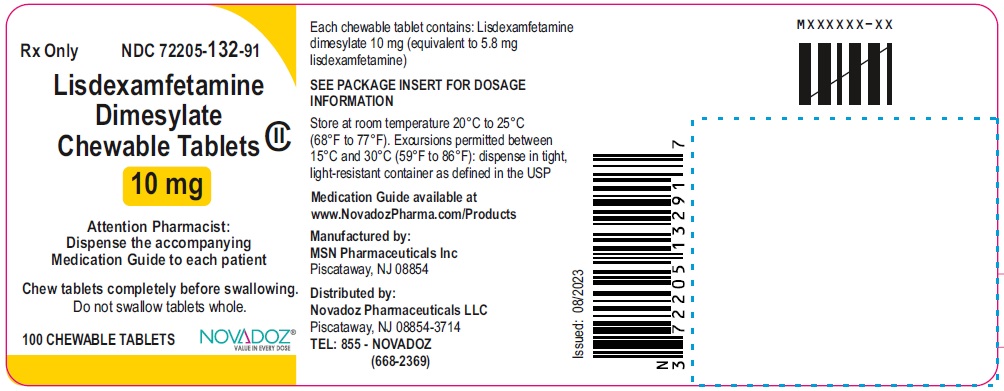
Lisdexamfetamine dimesylate 60 mg Tablet, Chewable, 100-count
Other active recalls for Lisdexamfetamine Dimesylate (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Central Nervous System Stimulant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Lisdexamfetamine is used to treat two conditions: ADHD in adults and kids age 6 and older, and moderate to severe binge eating disorder in adults. It's not approved for weight loss...
- What exactly is lisdexamfetamine used for?
- The most common ones are decreased appetite, trouble sleeping, dry mouth, nausea, and weight loss. Some people also feel jittery or anxious, especially early on. Most of these tend...
- What are the most common side effects I should expect?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3.510 | $351.02 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $6.82 | $682.37 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $8.65 | $864.80 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lisdexamfetamine Dimesylate 60 mg 00406-5129-01 | SpecGx | 100 tablets | $3.510 | AB | Availability likely | — |
| lisdexamfetamine dimesylate 60 mg 00480-9744-01 | Teva | 100 tablets | $3.510 | AB | Availability likely | — |
| Lisdexamfetamine Dimesylate 60 mg 31722-0326-01 | Camber | 100 tablets | $3.510 | AB | Availability likely | — |
| Lisdexamfetamine Dimesylate 60 mg 57664-0088-88 | Sun | 100 tablets | $3.510 | AB | Availability likely | — |
| Lisdexamfetamine dimesylate 60 mg 70010-0219-01 | Granules | 100 tablets | $3.510 | AB | Availability likely | — |
| Lisdexamfetamine dimesylate 60 mgthis 72205-0137-91 | Novadoz | 100 tablets | $3.510 | AB | Availability likely | — |
| Vyvanse 60 mg 59417-0120-01 | Takeda | 100 tablets | $12.358 | AB | Availability likely | +252% |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72205-0137-91 You're viewing this | 100 TABLET, CHEWABLE in 1 BOTTLE (72205-137-91) | 2024-02-17 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE, MISUSE, AND ADDICTION Lisdexamfetamine dimesylate has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including lisdexamfetamine dimesylate, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection. Before prescribing lisdexamfetamine dimesylate, assess each patient’s risk for abuse, misuse, and addiction.
Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout lisdexamfetamine dimesylate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction [see Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2) ] . WARNING: ABUSE, MISUSE, AND ADDICTION See full prescribing information for complete boxed warning .
Lisdexamfetamine dimesylate has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including lisdexamfetamine dimesylate, can result in overdose and death ( 5.1 , 9.2 , 10 ): Before prescribing lisdexamfetamine dimesylate, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug.
Throughout treatment, reassess each patient’s risk and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lisdexamfetamine dimesylate chewable tablets are indicated for the treatment of: Attention Deficit Hyperactivity Disorder (ADHD) in adults and pediatric patients 6 years and older [ see Clinical Studies (14.1) ] Moderate to severe binge eating disorder (BED) in adults [ see Clinical Studies (14.2) ]. Limitations of Use : Pediatric patients with ADHD younger than 6 years of age experienced more long-term weight loss than patients 6 years and older [ see Use in Specific Populations (8.4) ] . Lisdexamfetamine dimesylate chewable tablets are not indicated or recommended for weight loss.
Use of other sympathomimetic drugs for weight loss has been associated with serious cardiovascular adverse events. The safety and effectiveness of lisdexamfetamine dimesylate chewable tablets for the treatment of obesity have not been established [ see Warnings and Precautions (5.2) ] . Lisdexamfetamine dimesylate chewable tablets are a central nervous system (CNS) stimulant indicated for the treatment of ( 1 ): Attention Deficit Hyperactivity Disorder (ADHD) in adults and pediatric patients 6 years and older Moderate to severe binge eating disorder (BED) in adults Limitations of Use : Pediatric patients with ADHD younger than 6 years of age experienced more long-term weight loss than patients 6 years and older ( 8.4 ) Lisdexamfetamine dimesylate chewable tablets are not indicated for weight loss.
Use of other sympathomimetic drugs for weight loss has been associated with serious cardiovascular adverse events. The safety and effectiveness of lisdexamfetamine dimesylate chewable tablets for the treatment of obesity have not been established ( 5.2 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Indicated Population Initial Dose Titration Schedule Recommended Dose Maximum Dose ADHD (Adults and pediatric patients 6 years and older) ( 2.2 ) 30 mg every morning 10 mg or 20 mg weekly 30 mg to 70 mg per day 70 mg per day BED (Adults) ( 2.3 ) 30 mg every morning 20 mg weekly 50 mg to 70 mg per day 70 mg per day Prior to treatment, assess for presence of cardiac disease ( 2.4 ) Severe renal impairment: Maximum dose is 50 mg/day ( 2.5 ) End stage renal disease (ESRD): Maximum dose is 30 mg/day ( 2.5 )
2.1Pretreatment Screening Prior to treating patients with lisdexamfetamine dimesylate chewable tablets, assess: for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam) [see Warnings and Precautions (5.2) ] . the family history and clinically evaluate patients for motor or verbal tics or Tourette’s syndrome before initiating lisdexamfetamine dimesylate chewable tablets [see Warnings and Precautions (5.8) ].
2.2General Administration Information Take lisdexamfetamine dimesylate chewable tablets orally in the morning with or without food; avoid afternoon doses because of the potential for insomnia. Lisdexamfetamine dimesylate chewable tablets may be administered in one of the following ways: Information for lisdexamfetamine dimesylate chewable tablets : Lisdexamfetamine dimesylate chewable tablets must be chewed thoroughly before swallowing. VYVANSE capsules can be substituted with lisdexamfetamine dimesylate chewable tablets on a unit per unit/mg per mg basis (for example, 30 mg capsules for 30 mg chewable tablet) [ see Clinical Pharmacology (12.3) ].
Do not take anything less than one chewable tablet per day. A single dose should not be divided.
2.3Dosage for Treatment of ADHD The recommended starting dosage in adults and pediatric patients 6 years and older is 30 mg once daily in the morning. Dosage may be adjusted in increments of 10 mg or 20 mg at approximately weekly intervals up to maximum recommended dosage of 70 mg once daily [ see Clinical Studies (14.1) ].
2.4Dosage for Treatment of Moderate to Severe BED in Adults The recommended starting dosage in adults is 30 mg once daily to be titrated in increments of 20 mg at approximately weekly intervals to achieve the recommended target dose of 50 mg to 70 mg once daily. The maximum recommended dosage is 70 mg once daily [ see Clinical Studies (14.2) ]. Discontinue lisdexamfetamine dimesylate chewable tablets if binge eating does not improve.
2.5Dosage in Patients with Renal Impairment In patients with severe renal impairment (GFR 15 to < 30 mL/min/1.73 m 2 ), the maximum dosage should not exceed 50 mg once daily. In patients with end stage renal disease (ESRD, GFR < 15 mL/min/1.73 m 2 ), the maximum recommended dosage is 30 mg once daily [ see Use in Specific Populations (8.6) ].
2.6Dosage Modifications due to Drug Interactions Agents that alter urinary pH can impact urinary excretion and alter blood levels of amphetamine. Acidifying agents (e.g., ascorbic acid) decrease blood levels, while alkalinizing agents (e.g., sodium bicarbonate) increase blood levels. Adjust lisdexamfetamine dimesylate chewable tablets dosage accordingly [ see Drug Interactions (7.1) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lisdexamfetamine dimesylate chewable tablets : Chewable tablets 10 mg: White or off-white to mottled round shaped tablet debossed with 'm169' on one side and plain on the other side Chewable tablets 20 mg: White or off-white to mottled hexagonal shaped tablet debossed with 'm170' on one side and plain on the other side Chewable tablets 30 mg: White or off-white to mottled arc triangular shaped tablet debossed with 'm171' on one side and plain on the other side Chewable tablets 40 mg: White or off-white to mottled capsule shaped tablet debossed with 'm172' on one side and plain on the other side Chewable tablets 50 mg: White or off-white to mottled arc square shaped tablet debossed with 'm173' on one side and plain on the other side Chewable tablets 60 mg: White or off-white to mottled arc diamond shaped tablet debossed with 'm174' on one side and plain on the other side Chewable tablets: 10 mg, 20 mg, 30 mg, 40 mg, 50 mg, 60 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lisdexamfetamine dimesylate is contraindicated in patients with: Known hypersensitivity to amphetamine products or other ingredients of lisdexamfetamine dimesylate. Anaphylactic reactions, Stevens-Johnson Syndrome, angioedema, and urticaria have been observed in postmarketing reports [ see Adverse Reactions (6.2) ] . Patients taking monoamine oxidase inhibitors (MAOIs), or within 14 days of stopping MAOIs (including MAOIs such as linezolid or intravenous methylene blue), because of an increased risk of hypertensive crisis [ see Warnings and Precautions (5.7) and Drug Interactions (7.1) ].
Known hypersensitivity to amphetamine products or other ingredients in lisdexamfetamine dimesylate ( 4 ) Use with monoamine oxidase (MAO) inhibitor, or within 14 days of the last MAO inhibitor dose ( 4 , 7.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risks to Patients with Serious Cardiac Disease: Avoid use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease ( 5.2 ) Increased Blood Pressure and Heart Rate: Monitor blood pressure and pulse. ( 5.3 ) Psychiatric Adverse Reactions: Prior to initiating lisdexamfetamine dimesylate, screen patients for risk factors for developing a manic episode. If new psychotic or manic symptoms occur, consider discontinuing lisdexamfetamine dimesylate.
( 5.4 ) Long-Term Suppression of Growth in Pediatric Patients: Closely monitor growth (height and weight) in pediatric patients. Pediatric patients not growing or gaining height or weight as expected may need to have their treatment interrupted. ( 5.5 ) Peripheral Vasculopathy, including Raynaud’s phenomenon: Careful observation for digital changes is necessary during lisdexamfetamine dimesylate treatment.
Further clinical evaluation (e.g., rheumatology referral) may be appropriate for patients who develop signs or symptoms of peripheral vasculopathy. ( 5.6 ) Serotonin Syndrome: Increased risk when coadministered with serotonergic agents (e.g., SSRIs, SNRIs, triptans), but also during overdosage situations. If it occurs, discontinue lisdexamfetamine dimesylate and initiate supportive treatment ( 4 , 5.7 , 10 ) Motor and Verbal Tics, and Worsening of Tourette’s Syndrome: Before initiating lisdexamfetamine dimesylate, assess the family history and clinically evaluate patients for tics or Tourette’s syndrome.
Regularly monitor patients for the emergence or worsening of tics or Tourette’s syndrome. Discontinue treatment if clinically appropriate. ( 5.8 )
5.1Abuse, Misuse, and Addiction Lisdexamfetamine dimesylate has a high potential for abuse and misuse. The use of lisdexamfetamine dimesylate exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. lisdexamfetamine dimesylate can be diverted for non-medical use into illicit channels or distribution [see Drug Abuse and Dependence (9.2) ] . Misuse and abuse of CNS stimulants, including lisdexamfetamine dimesylate, can result in overdose and death [see Overdosage (10) ] , and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
Before prescribing lisdexamfetamine dimesylate, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug. Advise patients to store lisdexamfetamine dimesylate in a safe place, preferably locked, and instruct patients to not give lisdexamfetamine dimesylate to anyone else.
Throughout lisdexamfetamine dimesylate treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction.
5.2Risks to Patients with Serious Cardiac Disease Sudden death has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who were treated with CNS stimulants at the recommended ADHD dosage. Avoid lisdexamfetamine dimesylate use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease
5.3Increased Blood Pressure and Heart Rate CNS stimulants cause an increase in blood pressure (mean increase about 2 to 4 mm Hg) and heart rate (mean increase about 3 to 6 bpm). Some patients may have larger increases. Monitor all lisdexamfetamine dimesylate-treated patients for potential tachycardia and hypertension.
5.4Psychiatric Adverse Reactions Exacerbation of Pre-existing Psychosis CNS stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with a pre-existing psychotic disorder. Induction of a Manic Episode in Patients with Bipolar Disorder…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Known hypersensitivity to amphetamine products or other ingredients of lisdexamfetamine dimesylate [ see Contraindications (4) ] Hypertensive Crisis When Used Concomitantly with Monoamine Oxidase Inhibitors [ see Contraindications (4) and Drug Interactions (7.1) ] Abuse, Misuse, and Addiction [ see Boxed Warning , Warnings and Precautions (5.1) , and Drug Abuse and Dependence (9.2 , 9.3) ] Risks to Patients with Serious Cardiac Disease [ see Warnings and Precautions (5.2) ] Increased Blood Pressure and Heart Rate [ see Warnings and Precautions (5.3) ] Psychiatric Adverse Reactions [ see Warnings and Precautions (5.4) ] Long-Term Suppression of Growth in Pediatric Patients [ see Warnings and Precautions (5.5) ] Peripheral Vasculopathy, including Raynaud’s phenomenon [ see Warnings and Precautions (5.6) ] Serotonin Syndrome [ see Warnings and Precautions (5.7) ] Motor and Verbal Tics, and Worsening of Tourette’s Syndrome [ see Warnings and Precautions (5.8) ] Most common adverse reactions (incidence ≥5% and at a rate at least twice placebo) in pediatric patients ages 6 to 17 years, and/or adults with ADHD were anorexia, anxiety, decreased appetite, decreased weight, diarrhea, dizziness, dry mouth, irritability, insomnia, nausea, upper abdominal pain, and vomiting ( 6.1 ) Most common adverse reactions (incidence ≥ 5% and at a rate at least twice placebo) in adults with BED were dry mouth, insomnia, decreased appetite, increased heart rate, constipation, feeling jittery, and anxiety ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Novadoz Pharmaceuticals LLC at 1-855-668-2369 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Attention Deficit Hyperactivity Disorder The safety data in this section is based on data from the 4-week controlled parallel-group clinical studies of lisdexamfetamine dimesylate in pediatric and adult patients with ADHD [ see Clinical Studies (14.1) ].
Adverse Reactions Associated with Discontinuation of Treatment in ADHD Clinical Trials In the controlled trial in pediatric patients ages 6 to 12 years (Study 1), 8% (18/218) of lisdexamfetamine dimesylate-treated patients discontinued due to adverse reactions compared to 0% (0/72) of placebo-treated patients. The most frequently reported adverse reactions (1% or more and twice rate of placebo) were ECG voltage criteria for ventricular hypertrophy, tic, vomiting, psychomotor hyperactivity, insomnia, decreased appetite and rash [2 instances for each adverse reaction, i.e., 2/218 (1%)].
Less frequently reported adverse reactions (less than 1% or less than twice rate of placebo) included abdominal pain upper, dry mouth, weight decreased, dizziness, somnolence, logorrhea, chest pain, anger and hypertension. In the controlled trial in pediatric patients ages 13 to 17 years (Study 4), 3% (7/233) of lisdexamfetamine dimesylate-treated patients discontinued due to adverse reactions compared to 1% (1/77) of placebo-treated patients. The most frequently reported adverse reactions (1% or more and twice rate of placebo) were decreased appetite (2/233; 1%) and insomnia (2/233; 1%).
Less frequently reported adverse reactions (less than 1% or less than twice rate of placebo) included irritability, dermatillomania, mood swings, and dyspnea. In the controlled adult trial (Study 7), 6% (21/358) of lisdexamfetamine dimesylate-treated patients discontinued due to adverse reactions compared to 2% (1/62) of placebo-treated patients. The most frequently reported adverse reactions (1% or more and twice rate of placebo) were insomnia (8/358; 2%), tachycardia (3/358; 1%), i…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Acidifying and Alkalinizing Agents: Agents that alter urinary pH can alter blood levels of amphetamine. Acidifying agents decrease amphetamine blood levels, while alkalinizing agents increase amphetamine blood levels. Adjust lisdexamfetamine dimesylate dosage accordingly ( 2.6 , 7.1 )
7.1Drugs Having Clinically Important Interactions with Amphetamines Table 5 Drugs having clinically important interactions with amphetamines. MAO Inhibitors (MAOI) Clinical Impact MAOI antidepressants slow amphetamine metabolism, increasing amphetamines effect on the release of norepinephrine and other monoamines from adrenergic nerve endings causing headaches and other signs of hypertensive crisis. Toxic neurological effects and malignant hyperpyrexia can occur, sometimes with fatal results.
Intervention Do not administer lisdexamfetamine dimesylate during or within 14 days following the administration of MAOI [ see Contraindications (4) ] . Serotonergic Drugs Clinical Impact The concomitant use of lisdexamfetamine dimesylate and serotonergic drugs increases the risk of serotonin syndrome. Intervention Initiate with lower doses and monitor patients for signs and symptoms of serotonin syndrome, particularly during lisdexamfetamine dimesylate initiation or dosage increase.
If serotonin syndrome occurs, discontinue lisdexamfetamine dimesylate and the concomitant serotonergic drug(s) [ see Warnings and Precautions (5.7) ] . CYP2D6 Inhibitors Clinical Impact The concomitant use of lisdexamfetamine dimesylate and CYP2D6 inhibitors may increase the exposure of dextroamphetamine, the active metabolite of lisdexamfetamine dimesylate compared to the use of the drug alone and increase the risk of serotonin syndrome. Intervention Initiate with lower doses and monitor patients for signs and symptoms of serotonin syndrome particularly during lisdexamfetamine dimesylate initiation and after a dosage increase.
If serotonin syndrome occurs, discontinue lisdexamfetamine dimesylate and the CYP2D6 inhibitor [ see Warnings and Precautions (5.7) and Overdosage (10) ] . Alkalinizing Agents Clinical Impact Urinary alkalinizing agents can increase blood levels and potentiate the action of amphetamine. Intervention Co-administration of lisdexamfetamine dimesylate and urinary alkalinizing agents should be avoided.
Acidifying Agents Clinical Impact Urinary acidifying agents can lower blood levels and efficacy of amphetamines. Intervention Increase dose based on clinical response. Tricyclic Antidepressants Clinical Impact May enhance the activity of tricyclic or sympathomimetic agents causing striking and sustained increases in the concentration of d-amphetamine in the brain; cardiovascular effects can be potentiated.
Intervention Monitor frequently and adjust or use alternative therapy based on clinical response.
7.2Drugs Having No Clinically Important Interactions with Lisdexamfetamine Dimesylate From a pharmacokinetic perspective, no dose adjustment of lisdexamfetamine dimesylate is necessary when lisdexamfetamine dimesylate is co-administered with guanfacine, venlafaxine, or omeprazole. In addition, no dose adjustment of guanfacine or venlafaxine is needed when lisdexamfetamine dimesylate is co-administered [ see Clinical Pharmacology (12.3) ]. From a pharmacokinetic perspective, no dose adjustment for drugs that are substrates of CYP1A2 (e.g., theophylline, duloxetine, melatonin), CYP2D6 (e.g., atomoxetine, desipramine, venlafaxine), CYP2C19 (e.g., omeprazole, lansoprazole, clobazam), and CYP3A4 (e.g., midazolam, pimozide, simvastatin) is necessary when lisdexamfetamine dimesylate is co-administered [ see Clinical Pharmacology (12.3) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy : May cause fetal harm ( 8.1 ) Lactation : Breastfeeding not recommended ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/clinical-and researchprograms/pregnancyregistry/adhdmedications/ . Risk Summary The limited available data from published literature and postmarketing reports on use of lisdexamfetamine dimesylate in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage.
Adverse pregnancy outcomes, including premature delivery and low birth weight, have been seen in infants born to mothers dependent on amphetamines [see Clinical Considerations]. In animal reproduction studies, lisdexamfetamine dimesylate (a prodrug of d-amphetamine) had no effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis. Pre- and postnatal studies were not conducted with lisdexamfetamine dimesylate.
However, amphetamine (d- to l- ratio of 3:1) administration to pregnant rats during gestation and lactation caused a decrease in pup survival and a decrease in pup body weight that correlated with a delay in developmental landmarks at clinically relevant doses of amphetamine. In addition, adverse effects on reproductive performance were observed in pups whose mothers were treated with amphetamine. Long-term neurochemical and behavioral effects have also been reported in animal developmental studies using clinically relevant doses of amphetamine [see Data].
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Amphetamines, such as lisdexamfetamine dimesylate, cause vasoconstriction and thereby may decrease placental perfusion. In addition, amphetamines can stimulate uterine contractions increasing the risk of premature delivery. Infants born to amphetamine-dependent mothers have an increased risk of premature delivery and low birth weight.
Monitor infants born to mothers taking amphetamines for symptoms of withdrawal such as feeding difficulties, irritability, agitation, and excessive drowsiness. Data Animal Data Lisdexamfetamine dimesylate had no apparent effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis at doses of up to 40 and 120 mg/kg/day, respectively. These doses are approximately 5.5 and 33 times, respectively, the maximum recommended human dose (MRHD) of 70 mg/day given to adults, on a mg/m 2 body surface area basis.
A study was conducted with amphetamine (d- to l- enantiomer ratio of 3:1) in which pregnant rats received daily oral doses of 2, 6, and 10 mg/kg from gestation day 6 to lactation day 20. All doses caused hyperactivity and decreased weight gain in the dams. A decrease in pup survival was seen at all doses.
A decrease in pup body weight was seen at 6 and 10 mg/kg which correlated with delays in developmental landmarks, such as preputial separation and vaginal opening. Increased pup locomotor activity was seen at 10 mg/kg on day 22 postpartum but not at 5 weeks postweaning. When pups were tested for reproductive performance at maturation, gestational weight gain, number of implantations, and number of delivered pups were decreased in the group whose mothers h…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Psychostimulants at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/clinical-and researchprograms/pregnancyregistry/adhdmedications/ . Risk Summary The limited available data from published literature and postmarketing reports on use of lisdexamfetamine dimesylate in pregnant women are not sufficient to inform a drug-associated risk for major birth defects and miscarriage.
Adverse pregnancy outcomes, including premature delivery and low birth weight, have been seen in infants born to mothers dependent on amphetamines [see Clinical Considerations]. In animal reproduction studies, lisdexamfetamine dimesylate (a prodrug of d-amphetamine) had no effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis. Pre- and postnatal studies were not conducted with lisdexamfetamine dimesylate.
However, amphetamine (d- to l- ratio of 3:1) administration to pregnant rats during gestation and lactation caused a decrease in pup survival and a decrease in pup body weight that correlated with a delay in developmental landmarks at clinically relevant doses of amphetamine. In addition, adverse effects on reproductive performance were observed in pups whose mothers were treated with amphetamine. Long-term neurochemical and behavioral effects have also been reported in animal developmental studies using clinically relevant doses of amphetamine [see Data].
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Amphetamines, such as lisdexamfetamine dimesylate, cause vasoconstriction and thereby may decrease placental perfusion. In addition, amphetamines can stimulate uterine contractions increasing the risk of premature delivery. Infants born to amphetamine-dependent mothers have an increased risk of premature delivery and low birth weight.
Monitor infants born to mothers taking amphetamines for symptoms of withdrawal such as feeding difficulties, irritability, agitation, and excessive drowsiness. Data Animal Data Lisdexamfetamine dimesylate had no apparent effects on embryo-fetal morphological development or survival when administered orally to pregnant rats and rabbits throughout the period of organogenesis at doses of up to 40 and 120 mg/kg/day, respectively. These doses are approximately 5.5 and 33 times, respectively, the maximum recommended human dose (MRHD) of 70 mg/day given to adults, on a mg/m 2 body surface area basis.
A study was conducted with amphetamine (d- to l- enantiomer ratio of 3:1) in which pregnant rats received daily oral doses of 2, 6, and 10 mg/kg from gestation day 6 to lactation day 20. All doses caused hyperactivity and decreased weight gain in the dams. A decrease in pup survival was seen at all doses.
A decrease in pup body weight was seen at 6 and 10 mg/kg which correlated with delays in developmental landmarks, such as preputial separation and vaginal opening. Increased pup locomotor activity was seen at 10 mg/kg on day 22 postpartum but not at 5 weeks postweaning. When pups were tested for reproductive performance at maturation, gestational weight gain, number of implantations, and number of delivered pups were decreased in the group whose mothers had been given 10 mg/kg.
A number of studies from the literature in rodents indicate that prenatal or early postnatal expo…
🧒 Pediatric Use ▾
8.4Pediatric Use ADHD Safety and effectiveness of lisdexamfetamine dimesylate have been established in pediatric patients with ADHD ages 6 to 17 years [ see Dosage and Administration (2.3) , Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.1) ]. Safety and effectiveness of lisdexamfetamine dimesylate have not been established in pediatric patients below the age of 6 years. Safety and efficacy of lisdexamfetamine dimesylate were evaluated in a double-blind, randomized, parallel-group, placebo-controlled, fixed-dose study in pediatric patients ages 4 to 5 years with ADHD, followed by a 1-year open-label extension study.
In these studies, patients experienced elevated rates of adverse reactions, including weight loss, decreased BMI, decreased appetite, insomnia, infections (upper respiratory and nasopharyngitis), irritability, and affect lability. With the same lisdexamfetamine dimesylate dose, mean steady state exposure of dextroamphetamine was approximately 44% higher in pediatric patients ages 4 to 5 years compared to the pediatric patients ages 6 to 11 years. BED Safety and effectiveness of lisdexamfetamine dimesylate have not been established in pediatric patients with BED less than 18 years of age.
Growth Suppression Growth should be monitored during treatment with stimulants, including lisdexamfetamine dimesylate, and pediatric patients who are not growing or gaining weight as expected may need to have their treatment interrupted [ see Warnings and Precautions (5.5) and Adverse Reactions (6.1) ]. Juvenile Animal Data Studies conducted in juvenile rats and dogs at clinically relevant doses showed growth suppression that partially or fully reversed in dogs and female rats but not in male rats after a four-week drug-free recovery period.
A study was conducted in which juvenile rats received oral doses of 4, 10, or 40 mg/kg/day of lisdexamfetamine dimesylate from day 7 to day 63 of age. These doses are approximately 0.3, 0.7, and 3 times the maximum recommended human daily dose of 70 mg on a mg/m 2 basis for a child. Dose-related decreases in food consumption, bodyweight gain, and crown-rump length were seen; after a four-week drug-free recovery period, bodyweights and crown-rump lengths had significantly recovered in females but were still substantially reduced in males.
Time to vaginal opening was delayed in females at the highest dose, but there were no drug effects on fertility when the animals were mated beginning on day 85 of age. In a study in which juvenile dogs received lisdexamfetamine dimesylate for 6 months beginning at 10 weeks of age, decreased bodyweight gain was seen at all doses tested (2, 5, and 12 mg/kg/day, which are approximately 0.5, 1, and 3 times the maximum recommended human daily dose on a mg/m 2 basis for a child). This effect partially or fully reversed during a four-week drug-free recovery period.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of lisdexamfetamine dimesylate did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience and pharmacokinetic data [ see Clinical Pharmacology (12.3) ] have not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should start at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop.
CNS effects including psychomotor agitation, confusion, and hallucinations. Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. Life-threatening hyperthermia (temperatures greater than 104°F) and rhabdomyolysis may develop.
Overdose Management Consider the possibility of multiple drug ingestion. The pharmacokinetic profile of lisdexamfetamine dimesylate should be considered when treating patients with overdose. Lisdexamfetamine and damphetamine are not dialyzable.
Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lisdexamfetamine is a prodrug of dextroamphetamine. Amphetamines are non-catecholamine sympathomimetic amines with CNS stimulant activity. The exact mode of therapeutic action in ADHD and BED is not known.
12.2Pharmacodynamics Amphetamines block the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space. The parent drug, lisdexamfetamine, does not bind to the sites responsible for the reuptake of norepinephrine and dopamine in vitro.
12.3Pharmacokinetics Pharmacokinetic studies after oral administration of lisdexamfetamine dimesylate have been conducted in healthy adult (capsule and chewable tablet formulations) and pediatric (6 to 12 years) patients with ADHD (capsule formulation). After single dose administration of lisdexamfetamine dimesylate, pharmacokinetics of dextroamphetamine was found to be linear between 30 mg and 70 mg in a pediatric study (6 to 12 years), and between 50 mg and 250 mg in an adult study. Dextroamphetamine pharmacokinetic parameters following administration of lisdexamfetamine dimesylate in adults exhibited low inter-subject (<25%) and intra-subject (<8%) variability.
There is no accumulation of lisdexamfetamine and dextroamphetamine at steady state in healthy adults. Absorption Capsule formulation Following single-dose oral administration of VYVANSE capsule (30 mg, 50 mg, or 70 mg) in patients ages 6 to 12 years with ADHD under fasted conditions, T max of lisdexamfetamine and dextroamphetamine was reached at approximately 1 hour and 3.5 hours post dose, respectively. Weight/Dose normalized AUC and C max values were the same in pediatric patients ages 6 to 12 years as the adults following single doses of 30 mg to 70 mg VYVANSE capsule.
Effect of food on capsule formulation Neither food (a high fat meal or yogurt) nor orange juice affects the observed AUC and C max of dextroamphetamine in healthy adults after single-dose oral administration of 70 mg of VYVANSE capsules. Food prolongs T max by approximately 1 hour (from 3.8 hours at fasted state to 4.7 hours after a high fat meal or to 4.2 hours with yogurt). After an 8-hour fast, the AUC for dextroamphetamine following oral administration of lisdexamfetamine dimesylate in solution and as intact capsules were equivalent.
Chewable Tablet formulation After a single dose administration of 60 mg lisdexamfetamine dimesylate chewable tablet in healthy subjects under fasted conditions, T max of lisdexamfetamine and dextroamphetamine was reached at approximately 1 hour and 4.4 hours post dose, respectively. Compared to 60 mg VYVANSE capsule, exposure (C max and AUC) to lisdexamfetamine was about 15% lower. The exposure (C max and AUC inf ) of dextroamphetamine is similar between lisdexamfetamine dimesylate chewable tablet and VYVANSE capsule.
Effect of food on tablet formulation Administration of 60 mg lisdexamfetamine dimesylate chewable tablet with food (a high-fat meal) decreases the exposure (C max and AUC inf ) of dextroamphetamine by about 5% to 7%, and prolongs mean T max by approximately 1 hour (from 3.9 hours at fasted state to 4.9 hours). Elimination Plasma concentrations of unconverted lisdexamfetamine are low and transient, generally becoming non-quantifiable by 8 hours after administration. The plasma elimination half-life of lisdexamfetamine typically averaged less than one hour in volunteers ages 6 years and older.
The plasma elimination half-life of dextroamphetamine was approximately 8.6 to 9.5 hours in pediatric patients 6 to 12 years and 10 to 11.3 hours in healthy adults. Metabolism Lisdexamfetamine is converted to dextroamphetamine and l-lysine primarily in blood due to the hydrolytic activity of red blood cells after oral administration of lisdexamfetamine dimesylate. In vitro data demonstrated that red blood cells have a high capacity for metabolism of lisdexamfetamine; substantial hydrolysis occurred…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lisdexamfetamine is a prodrug of dextroamphetamine. Amphetamines are non-catecholamine sympathomimetic amines with CNS stimulant activity. The exact mode of therapeutic action in ADHD and BED is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Lisdexamfetamine dimesylate chewable tablets : Lisdexamfetamine dimesylate chewable tablets 10 mg: White or off-white to mottled round shaped tablet debossed with 'm169' on one side and plain on the other side, bottles of 100, NDC 72205-132-91 Lisdexamfetamine dimesylate chewable tablets 20 mg: White or off-white to mottled hexagonal shaped tablet debossed with 'm170' on one side and plain on the other side, bottles of 100, NDC 72205-133-91 Lisdexamfetamine dimesylate chewable tablets 30 mg: White or off-white to mottled arc triangular shaped tablet debossed with 'm171' on one side and plain on the other side, bottles of 100, NDC 72205-134-91 Lisdexamfetamine dimesylate chewable tablets 40 mg: White or off-white to mottled capsule shaped tablet debossed with 'm172' on one side and plain on the other side, bottles of 100, NDC 72205-135-91 Lisdexamfetamine dimesylate chewable tablets 50 mg: White or off-white to mottled arc square shaped tablet debossed with 'm173' on one side and plain on the other side, bottles of 100, NDC 72205-136-91 Lisdexamfetamine dimesylate chewable tablets 60 mg: White or off-white to mottled arc diamond shaped tablet debossed with 'm174' on one side and plain on the other side, bottles of 100, NDC 72205-137-91
16.2Storage and Handling Dispense in a tight, light-resistant container as defined in the USP. Store at room temperature, 20ºC to 25ºC (68ºF to 77ºF). Excursions permitted between 15ºC and 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Lisdexamfetamine dimesylate chewable tablet, a CNS stimulant, is for once-a-day oral administration. The chemical designation for lisdexamfetamine dimesylate is (2S)-2,6-diamino-N-[(1S)-1-methyl-2-phenylethyl]-hexanamide dimethanesulfonate. The molecular formula is C 15 H 25 N 3 O•(CH 4 O 3 S) 2 , which corresponds to a molecular weight of 455.60.
The chemical structure is: Lisdexamfetamine dimesylate is a white to off-white powder that is soluble in water (792 mg/mL). Information for lisdexamfetamine dimesylate chewable tablets: Lisdexamfetamine dimesylate chewable tablets contain 10 mg, 20 mg, 30 mg, 40 mg, 50 mg, and 60 mg of lisdexamfetamine dimesylate (equivalent to 5.8 mg, 11.6 mg, 17.3 mg, 23.1 mg, 28.9 mg, and 34.7 mg of lisdexamfetamine). Inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, mannitol, microcrystalline cellulose and gaur gum, sucralose, N-C strawberry flavor art. lisdex-dimesy-chew-tabs-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Abuse, Misuse, and Addiction Educate patients and their families about the risks of abuse, misuse, and addiction of lisdexamfetamine dimesylate, which can lead to overdose and death, and proper disposal of any unused drug [see Warnings and Precautions (5.1) , Drug Abuse and Dependence (9.2) , Overdosage (10) ] . Advise patients to store lisdexamfetamine dimesylate in a safe place, preferably locked, and instruct patients to not give lisdexamfetamine dimesylate to anyone else.
Risks to Patients with Serious Cardiac Disease Advise patients that there are potential risks to patients with serious cardiac disease, including sudden death, with lisdexamfetamine dimesylate use. Instruct patients to contact a healthcare provider immediately if they develop symptoms such as exertional chest pain, unexplained syncope, or other symptoms suggestive of cardiac disease [see Warnings and Precautions (5.2) ]. Increased Blood Pressure and Heart Rate Instruct patients that lisdexamfetamine dimesylate can cause elevations of their blood pressure and pulse rate and they should be monitored for such effects.
Psychiatric Adverse Reactions Advise patients that lisdexamfetamine dimesylate at recommended doses may cause psychotic or manic symptoms even in patients without prior history of psychotic symptoms or mania [see Warnings and Precautions (5.4) ] . Long-Term Suppression of Growth in Pediatric Patients Advise patients that lisdexamfetamine dimesylate may cause slowing of growth including weight loss [see Warnings and Precautions (5.5) ]. Circulation problems in fingers and toes [Peripheral vasculopathy, including Raynaud’s phenomenon] Instruct patients beginning treatment with lisdexamfetamine dimesylate about the risk of peripheral vasculopathy, including Raynaud’s phenomenon, and associated signs and symptoms: fingers or toes may feel numb, cool, painful, and/or may change from pale, to blue, to red.
Instruct patients to report to their physician any new numbness, pain, skin color change, or sensitivity to temperature in fingers or toes. Instruct patients to call their physician immediately with any signs of unexplained wounds appearing on fingers or toes while taking lisdexamfetamine dimesylate. Further clinical evaluation (e.g., rheumatology referral) may be appropriate for certain patients [see Warnings and Precautions (5.6) ].
Serotonin Syndrome Caution patients about the risk of serotonin syndrome with concomitant use of lisdexamfetamine dimesylate and other serotonergic drugs including SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, St. John’s Wort, and with drugs that impair metabolism of serotonin (in particular MAOIs, both those intended to treat psychiatric disorders and also others such as linezolid [see Contraindications (4), Warnings and Precautions (5.7) and Drug Interactions (7.1) ] .
Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome. Concomitant Medications Advise patients to notify their physicians if they are taking, or plan to take, any prescription or over-the-counter drugs because there is a potential for interactions [see Drug Interactions (7.1) ]. Motor and Verbal Tics, and Worsening of Tourette’s Syndrome Advise patients that motor and verbal tics and worsening of Tourette’s Syndrome may occur during treatment with lisdexamfetamine dimesylate.
Instruct patients to notify their healthcare provider if emergence of new tics or worsening of tics or Tourette’s syndrome occurs [see Warnings and Precautions (5.8) ]. Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to lisdexamfetamine dimesylate during pregnancy [see Use in Specific Populations (8.1) ]. Pregnancy Advise patients of the poten…