
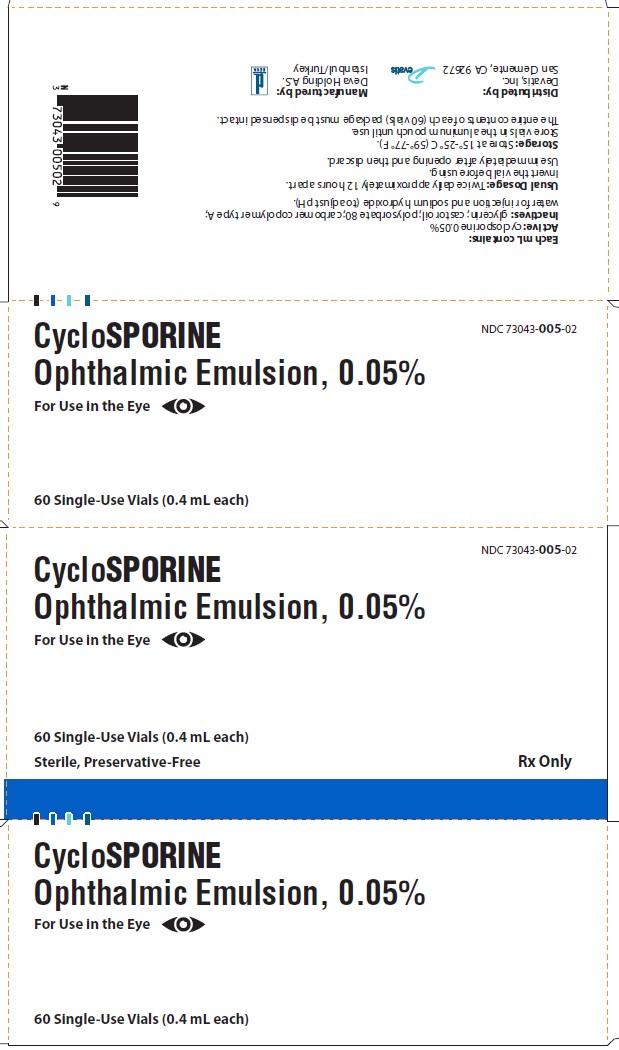
Cyclosporine .5 mg/mL Emulsion
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcineurin Inhibitor Immunosuppressant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ophthalmic cyclosporine is used to increase tear production in people with dry eye disease. Cyclosporine is in a class of medications called immunomodulators. It works by decreasing swelling in the eye to allow for tear production.
Read the full MedlinePlus article ↗- Cyclosporine levels in your blood can vary quite a bit, and both too much and too little can cause real problems — too high raises the risk of kidney damage, and too low means the...
- Why do I need blood tests so often while taking cyclosporine?
- No — grapefruit and grapefruit juice are a hard no with cyclosporine. They block a key enzyme in your body that normally clears cyclosporine, which can cause your blood levels to c...
- Can I eat grapefruit while taking cyclosporine?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cyclosporine — tap one for details:
Cyclosporine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 71DD5V995L
A synthetic polymer derived from acrylic acid, crosslinked to form a gel-like substance. It thickens formulations, improves texture, and helps distribute active ingredients evenly in topical products like creams and gels.
-
UNII D5340Y2I9G
Castor oil is a natural plant-based oil used in medicines as a lubricant, laxative agent, and solvent. It helps medicine ingredients dissolve or flow smoothly and can aid bowel movement in formulations designed for that purpose.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.924 | $55.44 / 60 vials |
| Medicaid paysCMS SDUD · 12 mo | $2.72 | $163.44 / 60 vials |
| Medicare drug plans payPart D · Q2 2026 | $3.98 | $238.91 / 60 vials |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cyclosporine .5 mg/mL 24979-0126-18 | Upsher-Smith | 60 vials | $0.924 | AB | Availability likely | — |
| Cyclosporine .5 mg/mLthis 73043-0005-02 | Devatis | 6 pouches | $0.924 | AB | Availability likely | — |
| Cyclosporine .5 mg/mL 00378-8760-58 | Mylan | 6 pouches | $1.240 | AB | Availability likely | +34% |
| Cyclosporine .5 mg/mL 00480-4076-30 | Teva | 6 pouches | $1.240 | AB | Availability likely | +34% |
| Cyclosporine .5 mg/mL 10702-0808-03 | KVK-TECH, | 30 vials | $1.240 | AB | Availability likely | +34% |
| Cyclosporine .5 mg/mL 60505-6202-01 | Apotex | 30 vials | $1.240 | AB | Availability likely | +34% |
| Cyclosporine .5 mg/mL 68180-0214-30 | Lupin | 30 vials | $1.240 | AB | Availability likely | +34% |
| Cyclosporine .5 mg/mL 71656-0012-30 | Saptalis | 6 pouches | $1.240 | AB | Availability likely | +34% |
| Restasis MultiDose .5 mg/mL 00023-5301-05 | Allergan, | 1 bottle | $112.318 | AB | Availability likely | +12056% |
| Restasis .5 mg/mL 00023-9163-12 | Allergan, | 5 vials | — | AB | FDA listed | — |
| Restasis .5 mg/mL 50090-4476-00 | A-S | 30 vials | — | AB | FDA listed | — |
| Cyclosporine .5 mg/mL 69238-1023-03 | Amneal | 3 pouches | — | AB | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 73043-0005-01 | 3 POUCH in 1 CARTON (73043-005-01) / 10 VIAL, SINGLE-USE in 1 POUCH / .4 mL in 1 VIAL, SINGLE-USE | $1.24 / ea | $37.19 | 2024-07-04 | Active |
| 73043-0005-02 You're viewing this | 6 POUCH in 1 CARTON (73043-005-02) / 10 VIAL, SINGLE-USE in 1 POUCH / .4 mL in 1 VIAL, SINGLE-USE | $0.9240 / ea | $55.44 | 2024-07-04 | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.9240 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 70% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 73043-0005-02?
What NDC number is used to bill for this package of Cyclosporine .5 mg/mL Emulsion?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Cyclosporine ophthalmic emulsion is indicated to increase tear production in patients whose tear production is presumed to be suppressed due to ocular inflammation associated with keratoconjunctivitis sicca. Increased tear production was not seen in patients currently taking topical anti-inflammatory drugs or using punctal plugs. Cyclosporine ophthalmic emulsion is a calcineurin inhibitor immunosuppressant indicated to increase tear production in patients whose tear production is presumed to be suppressed due to ocular inflammation associated with keratoconjunctivitis sicca.
Increased tear production was not seen in patients currently taking topical anti-inflammatory drugs or using punctal plugs. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Invert the unit dose vial a few times to obtain a uniform, white, opaque emulsion before using. Instill one drop of cyclosporine ophthalmic emulsion twice a day in each eye approximately 12 hours apart. Cyclosporine ophthalmic emulsion can be used concomitantly with lubricant eye drops, allowing a 15 minute interval between products.
Discard vial immediately after use. Instill one drop of cyclosporine ophthalmic emulsion twice a day in each eye approximately 12 hours apart.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ophthalmic emulsion containing cyclosporine 0.5 mg/mL Cyclosporine ophthalmic emulsion 0.5 mg/mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Cyclosporine ophthalmic emulsion is contraindicated in patients with known or suspected hypersensitivity to any of the ingredients in the formulation. •Hypersensitivity ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • To avoid the potential for eye injury and contamination, be careful not to touch the vial tip to your eye or other surfaces. ( 5.1 )
5.1Potential for Eye Injury and Contamination Be careful not to touch the vial tip to your eye or other surfaces to avoid potential for eye injury and contamination.
5.2Use with Contact Lenses Cyclosporine ophthalmic emulsion should not be administered while wearing contact lenses. Patients with decreased tear production typically should not wear contact lenses. If contact lenses are worn, they should be removed prior to the administration of the emulsion. Lenses may be reinserted 15 minutes following administration of cyclosporine ophthalmic emulsion.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: • Potential for Eye Injury and Contamination [ see Warnings and Precautions (5.1) ] The most common adverse reaction following the use of cyclosporine ophthalmic emulsion was ocular burning (17%). ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Devatis, Inc. at 1-833-534-4406 or [email protected] or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch or www.devatis.com.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In clinical trials, the most common adverse reaction following the use of cyclosporine ophthalmic emulsion was ocular burning (17%). Other reactions reported in 1% to 5% of patients included conjunctival hyperemia, discharge, epiphora, eye pain, foreign body sensation, pruritus, stinging, and visual disturbance (most often blurring).
6.2Post-marketing Experience The following adverse reactions have been identified during post approval use of cyclosporine ophthalmic emulsion. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Reported reactions have included: hypersensitivity (including eye swelling, urticaria, rare cases of severe angioedema, face swelling, tongue swelling, pharyngeal edema, and dyspnea); and superficial injury of the eye (from the vial tip touching the eye during administration).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Clinical administration of cyclosporine ophthalmic emulsion 0.05% is not detected systemically following topical ocular administration [ see Clinical Pharmacology (12.3) ], and maternal use is not expected to result in fetal exposure to the drug. Oral administration of cyclosporine to pregnant rats or rabbits did not produce teratogenicity at clinically relevant doses [ see Data ]. Data Animal Data At maternally toxic doses (30 mg/kg/day in rats and 100 mg/kg/day in rabbits), cyclosporine oral solution (USP) was teratogenic as indicated by increased pre- and postnatal mortality, reduced fetal weight and skeletal retardations.
These doses (normalized to body surface area) are 5,000 and 32,000 times greater, respectively, than the daily recommended human dose of one drop (approximately 28 mcL) of cyclosporine ophthalmic emulsion 0.05% twice daily into each eye of a 60 kg person (0.001 mg/kg/day), assuming that the entire dose is absorbed. No evidence of embryofetal toxicity was observed in rats or rabbits receiving cyclosporine during organogenesis at oral doses up to 17 mg/kg/day or 30 mg/kg/day, respectively. These doses in rats and rabbits are approximately 3,000 and 10,000 times greater, respectively, than the daily recommended human dose.
An oral dose of 45 mg/kg/day cyclosporine administered to rats from Day 15 of pregnancy until Day 21 postpartum produced maternal toxicity and an increase in postnatal mortality in offspring. This dose is 7,000 times greater than the daily recommended human dose. No adverse effects in dams or offspring were observed at oral doses up to 15 mg/kg/day (2,000 times greater than the daily recommended human dose).
8.2Lactation Risk Summary Cyclosporine is known to appear in human milk following systemic administration, but its presence in human milk following topical treatment has not been investigated. Although blood concentrations are undetectable following topical administration of cyclosporine ophthalmic emulsion [see Clinical Pharmacology (12.3) ] , caution should be exercised when cyclosporine ophthalmic emulsion is administered to a nursing woman. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for cyclosporine ophthalmic emulsion and any potential adverse effects on the breast-fed child from cyclosporine.
8.4Pediatric Use Safety and efficacy have not been established in pediatric patients below the age of 16.
8.5Geriatric Use No overall difference in safety or effectiveness has been observed between elderly and younger patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Clinical administration of cyclosporine ophthalmic emulsion 0.05% is not detected systemically following topical ocular administration [ see Clinical Pharmacology (12.3) ], and maternal use is not expected to result in fetal exposure to the drug. Oral administration of cyclosporine to pregnant rats or rabbits did not produce teratogenicity at clinically relevant doses [ see Data ]. Data Animal Data At maternally toxic doses (30 mg/kg/day in rats and 100 mg/kg/day in rabbits), cyclosporine oral solution (USP) was teratogenic as indicated by increased pre- and postnatal mortality, reduced fetal weight and skeletal retardations.
These doses (normalized to body surface area) are 5,000 and 32,000 times greater, respectively, than the daily recommended human dose of one drop (approximately 28 mcL) of cyclosporine ophthalmic emulsion 0.05% twice daily into each eye of a 60 kg person (0.001 mg/kg/day), assuming that the entire dose is absorbed. No evidence of embryofetal toxicity was observed in rats or rabbits receiving cyclosporine during organogenesis at oral doses up to 17 mg/kg/day or 30 mg/kg/day, respectively. These doses in rats and rabbits are approximately 3,000 and 10,000 times greater, respectively, than the daily recommended human dose.
An oral dose of 45 mg/kg/day cyclosporine administered to rats from Day 15 of pregnancy until Day 21 postpartum produced maternal toxicity and an increase in postnatal mortality in offspring. This dose is 7,000 times greater than the daily recommended human dose. No adverse effects in dams or offspring were observed at oral doses up to 15 mg/kg/day (2,000 times greater than the daily recommended human dose).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and efficacy have not been established in pediatric patients below the age of 16.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall difference in safety or effectiveness has been observed between elderly and younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Cyclosporine is an immunosuppressive agent when administered systemically. In patients whose tear production is presumed to be suppressed due to ocular inflammation associated with keratoconjunctivitis sicca, cyclosporine emulsion is thought to act as a partial immunomodulator. The exact mechanism of action is not known.
12.3Pharmacokinetics Blood cyclosporine A concentrations were measured using a specific high pressure liquid chromatography-mass spectrometry assay. Blood concentrations of cyclosporine, in all the samples collected, after topical administration of cyclosporine ophthalmic emulsion 0.05%, twice daily, in humans for up to 12 months, were below the quantitation limit of 0.1 ng/mL. There was no detectable drug accumulation in blood during 12 months of treatment with cyclosporine ophthalmic emulsion.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Cyclosporine is an immunosuppressive agent when administered systemically. In patients whose tear production is presumed to be suppressed due to ocular inflammation associated with keratoconjunctivitis sicca, cyclosporine emulsion is thought to act as a partial immunomodulator. The exact mechanism of action is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Cyclosporine ophthalmic emulsion is packaged in sterile, preservative-free single-use vials. Each vial contains 0.4 mL fill in a 0.9 mL LDPE vial; 10 vials are packaged in an aluminum pouch. There are 3 (30 vials) or 6 (60 vials) pouches packaged per carton.
The entire contents of each carton (30 vials or 60 vials) must be dispensed intact. 30 Vials 0.4 mL each – NDC 73043 005 01 60 Vials 0.4 mL each – NDC 73043 005 02 Storage : Store at 15°-25°C (59°-77°F).
📋 Description ▾
11 DESCRIPTION Cyclosporine ophthalmic emulsion 0.05% contains a topical calcineurin inhibitor immunosuppressant with anti-inflammatory effects. Cyclosporine’s chemical name is Cyclo[[( E )-(2 S ,3 R ,4 R )-3-hydroxy-4-methyl-2-(methylamino)-6-octenoyl]-L-2-aminobutyryl- N -methylglycyl- N -methyl-L-leucyl-L-valyl- N -methyl-L-leucyl-L-alanyl-D-alanyl- N -methyl-L-leucyl- N -methyl-L-leucyl- N -methyl-L-valyl] and it has the following structure: Structural Formula Formula: C 62 H 111 N 11 O 12 Mol. Wt.: 1202.6 Cyclosporine is fine white powder.
Cyclosporine ophthalmic emulsion appears as a white opaque to slightly translucent homogeneous emulsion. It has an osmolality of 230 to 320 mOsmol/kg and a pH of 6.5-8.0. Each mL of cyclosporine ophthalmic emulsion contains: Active: cyclosporine 0.05%.
Inactives: glycerin; castor oil; polysorbate 80; carbomer copolymer type A; water for injection; and sodium hydroxide to adjust pH. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Handling the Container Advise patients to not allow the tip of the vial to touch the eye or any surface, as this may contaminate the emulsion. Advise patients to not touch the vial tip to their eye to avoid the potential for injury to the eye [ see Warnings and Precautions (5.1) ] Use with Contact Lenses Cyclosporine ophthalmic emulsion should not be administered while wearing contact lenses. Patients with decreased tear production typically should not wear contact lenses.
Advise patients that if contact lenses are worn, they should be removed prior to the administration of the emulsion. Lenses may be reinserted 15 minutes following administration of cyclosporine ophthalmic emulsion [ see Warnings and Precautions (5.2) ]. Administration Advise patients that the emulsion from one individual single-use vial is to be used immediately after opening for administration to one or both eyes, and the remaining contents should be discarded immediately after administration.