
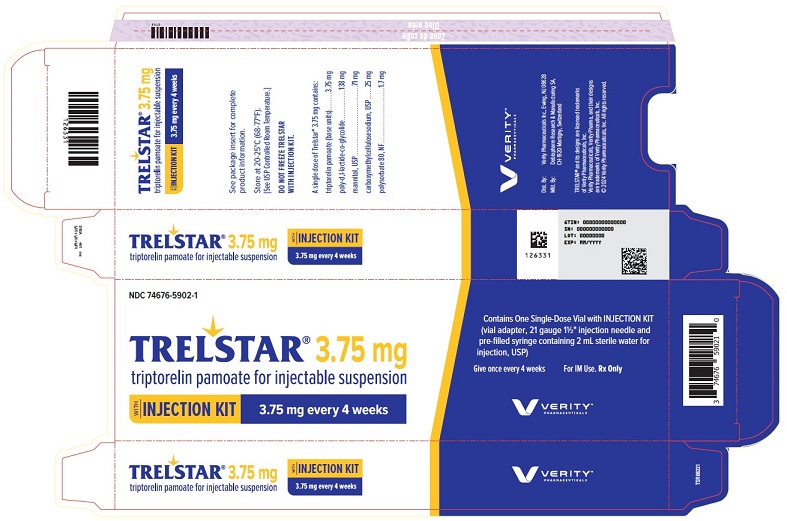
Trelstar triptorelin pamoate Kit — NDC 74676-5906-1 (Billing 74676-5906-01)
This is a package of Trelstar triptorelin pamoate Kit from Verity Pharmaceuticals Inc., marketed since Mar 2010 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 74676-5906-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 74676 labeler · 5906 product · 1 package
- Package marketed since
- Mar 11, 2010
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 7467659061 6
- Medicaid fills, this package
- 66 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 066266
- GCN: 28507
- GPI-14 (Medi-Span): 21405050201940
- HICL (First Databank): 023164
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 199821
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Gonadotropin Releasing Hormone Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Triptorelin injection is used to treat certain types of prostate cancer. It is also used to treat central precocious puberty (CPP; a condition causing children to enter puberty too soon, resulting in faster than normal bone growth and development of sexual characteristics). Triptorelin injection is in a class of medications called gonadotropin-releasing hormone (GnRH) agonists. It works by decreasing the amount of certain hormones in the body.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1,586.02 | — |
| Medicare drug plans payPart D · Q2 2026 | $5,614.96 | — |
| Medicare Part B allowsASP · J3315 | $466.365 / J3315 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 74676-5906-01 You're viewing this Main listing | 1 KIT in 1 CARTON * 2 mL in 1 VIAL, SINGLE-DOSE * 2 mL in 1 SYRINGE | 2010-03-11 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Trelstar 74676-5902-01 | Verity | 1 kit | — | — | FDA listed | — |
| Trelstar 74676-5904-01 | Verity | 1 kit | — | — | FDA listed | — |
| Trelstarthis 74676-5906-01 | Verity | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10166181 ↗ | Drug product | — | Jun 30, 2029 |
Is there a generic version of TRELSTAR 22.5 MG VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Verity Pharmaceuticals Inc. labeler code 74676
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TRELSTAR is indicated for the treatment of advanced prostate cancer [ see Clinical Studies (14) ]. TRELSTAR is a gonadotropin releasing hormone (GnRH) agonist indicated for the treatment of advanced prostate cancer. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION TRELSTAR is administered as a single intramuscular injection in either buttock. Due to different release characteristics, the dosage strengths are not additive and must be selected based upon the desired dosing schedule. ( 2.1 ) 3.75 mg every 4 weeks. ( 2.1 ) 11.25 mg every 12 weeks. ( 2.1 ) 22.5 mg every 24 weeks. ( 2.1 ) Trelstar injection kit
2.1Dosing Information TRELSTAR must be administered under the supervision of a physician. TRELSTAR is administered by a single intramuscular injection in either buttock. Dosing schedule depends on the product strength selected (Table 1).
The lyophilized microgranules are to be reconstituted in sterile water . No other diluent should be used. Table 1.
TRELSTAR Recommended Dosing Dosage 3.75 mg 11.25 mg 22.5 mg Recommended dose 1 injection every 4 weeks 1 injection every 12 weeks 1 injection every 24 weeks Due to different release characteristics, the dosage strengths are not additive and must be selected based upon the desired dosing schedule. The suspension should be administered within 2 minutes after reconstitution. As with other drugs administered by intramuscular injection, the injection site should be alternated periodically.
Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
2.2Reconstitution Instructions for TRELSTAR Important: Please read the instructions completely and prepare the patient before you begin the injection kit activation and drug administration procedure. *The strength indicated on the vial in the figure above is for representative purposes only. All three strengths of the Trelstar vial have their individual strengths indicated on the label. Users will see either 3.75 mg, 11.25 mg or 22.5 mg, with the corresponding duration of treatment (4, 12 or 24 weeks respectively).
Preparation and Activation Check that you are using the prescribed strength/dose (3.75 mg, 11.25 mg, or 22.5 mg) and that the expiry date has not passed, before preparation and activation. Wash your hands with soap and hot water and put on gloves immediately prior to preparing the injection. Place the sealed tray on a clean, flat surface that is covered with a sterile pad or cloth.
Peel the cover away from the tray and remove the injection kit components and TRELSTAR vial. General Instructions and Recommendations The product is a suspension of microgranules that can settle in the diluent. The final product to be administered is a suspension of microgranules with a milky, homogeneous appearance.
If the product settles in the vial, shake it again to resuspend the microgranules. If the microgranules settle in the syringe, this will block the needle during administration. It is very important to inject the product within 2 minutes following reconstitution in the vial.
If the product settles in the syringe, draw some air back into the syringe, shake it again, and expel the air (without priming the needle) before administering it. STEP 1 – PREPARE VIAL Remove the flip-off button cap from the vial, revealing the rubber stopper. Place the vial in a standing upright position on the prepared surface.
Disinfect the rubber stopper with the alcohol wipe. Discard the alcohol wipe and allow the stopper to dry. STEP 2 – APPLY VIAL ADAPTER Peel the cover away from the blister pack containing the vial adapter.
Do not remove the vial adapter from the blister pack . On a level surface, place the blister pack containing the vial adapter firmly on the vial top. Ensure the spike is centered and vertical when piercing the vial .
Push down gently until you feel it snap into place. Remove the blister pack from the vial adapter. STEP 3 – PREPARE SYRINGE AND CONNECT TO VIAL ADAPTER (a) Grasp the plastic ‘spin lock’ collar on the syringe barrel with index finger and thumb.
Unscrew and discard the gray rubber cap from the syringe barrel. (b) Maintaining your grip on the spin lock, attach the… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injectable suspension: 3.75 mg, 11.25 mg, 22.5 mg of slightly yellow lyophilized microgranules in a single-dose vial for reconstitution with an injection kit containing one syringe filled with sterile water for injection, a vial adapter to help with reconstitution, and one needle (see figure in section 2.2). For injectable suspension: 3.75 mg, 11.25 mg, 22.5 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Known hypersensitivity to triptorelin or any other component of the product, or other GnRH agonists or GnRH. ( 4 )
4.1Hypersensitivity TRELSTAR is contraindicated in individuals with a known hypersensitivity to triptorelin or any other component of the product, or other GnRH agonists or GnRH [ see Warnings and Precautions (5.1) ].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity: Anaphylactic shock, hypersensitivity, and angioedema have been reported. In the event of a reaction, discontinue TRELSTAR and initiate appropriate medical management. ( 5.1 ) Tumor Flare: Transient increase in serum testosterone levels can occur within the first few weeks of treatment.
This may worsen prostate cancer and result in spinal cord compression and urinary tract obstruction. Monitor patients at risk and manage as appropriate. ( 5.2 ) Metabolic Syndrome: The use of GnRH agonists may lead to an increased risk of metabolic changes such as hyperglycemia, diabetes, hyperlipidemia, and non-alcoholic fatty liver disease.
Monitor for signs and symptoms of metabolic syndrome including lipids, blood glucose level and/or HbA1c and manage according to institutional guidelines. ( 5.3 ) Cardiovascular Diseases: Increased risk of myocardial infarction, sudden cardiac death and stroke has been reported in men. Monitor for cardiovascular disease and manage according to current clinical practice.
( 5.4 ) Convulsions: Convulsions have occurred in patients treated with GnRH analogs (including TRELSTAR) with or without a history of predisposing factors. Manage patients who experience convulsions according to institutional guidelines. ( 5.5 ) Severe Cutaneous Adverse Reactions (SCARs): SCARs have been reported in patients receiving GnRH agonists, including triptorelin products.
Interrupt TRELSTAR if signs or symptoms of SCARs develop. Permanently discontinue TRELSTAR if SCARs are confirmed. ( 5.6 ) Effect on QT/QTc Interval: Androgen deprivation therapy may prolong the QT interval.
Consider risks and benefits. ( 5.7 ) Embryo-Fetal Toxicity: TRELSTAR may cause fetal harm. ( 5.10 , 8.1 )
5.1Hypersensitivity Reactions Anaphylactic shock, hypersensitivity, and angioedema related to TRELSTAR administration have been reported. In the event of a hypersensitivity reaction, discontinue TRELSTAR immediately and administer the appropriate supportive and symptomatic care.
5.2Tumor Flare Initially, triptorelin (TRELSTAR), like other GnRH agonists, causes a transient increase in serum testosterone levels [ see Clinical Pharmacology (12.2) ]. As a result, worsening signs and symptoms of prostate cancer during the first weeks of treatment have been reported with GnRH agonists. Patients may experience worsening of symptoms or onset of new symptoms, including bone pain, neuropathy, hematuria, or urethral or bladder outlet obstruction.
Closely monitor patients with metastatic vertebral lesions and/or with urinary tract obstruction during the first few weeks of therapy.
5.3Metabolic Syndrome The use of GnRH agonists (including TRELSTAR) may lead to metabolic changes such as hyperglycemia, diabetes mellitus, and hyperlipidemia. Non-alcoholic fatty liver disease, including cirrhosis, occurred in the post-marketing setting. Hyperglycemia may represent new-onset of diabetes mellitus or worsening of glycemic control in patients with pre-existing diabetes.
Monitor for changes in serum lipids, blood glucose and/or glycosylated hemoglobin (HbA1c) periodically in patients receiving TRELSTAR and manage according to institutional guidelines.
5.4Cardiovascular Diseases Increased risk of developing myocardial infarction, sudden cardiac death and stroke has been reported in association with the use of GnRH agonists (including TRELSTAR) in men. The risk appears low based on the reported odds ratios and should be evaluated carefully along with cardiovascular risk factors when determining a treatment for patients with prostate cancer. Monitor patients receiving TRELSTAR for symptoms and signs suggestive of development of cardiovascular disease and manage according to current institutional guidelines.
5.5Convulsions Convulsions have occurred in patients treated with GnRH analog (including TRELSTAR). These events included patients with risk factors for seizures such as a history of epilepsy, intracranial tumors or co-medication… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following is discussed in more detail in other sections of the labeling: Hypersensitivity Reactions [ see Warnings and Precautions ( 5.1 ) ] Tumor Flare [ see Warnings and Precautions ( 5.2 ) ]. Metabolic Syndrome [ see Warnings and Precautions ( 5.3 ) ] Cardiovascular Diseases [ see Warnings and Precautions ( 5.4 ) ]. Convulsions [ see Warnings and Precautions ( 5.5 ) ].
Severe Cutaneous Adverse Reactions [ see Warnings and Precautions ( 5.6 ) ]. Effect of QT/QTc Interval [ see Warnings and Precautions ( 5.7 ) ]. 3.75 mg: The most common adverse reactions (≥ 5%) during TRELSTAR 3.75 mg therapy included hot flushes, skeletal pain, impotence, and headache.
( 6.1 ) 11.25 mg: The most common adverse reactions (≥ 5%) during TRELSTAR 11.25 mg therapy included hot flushes, skeletal pain, headache, edema in legs, and leg pain. ( 6.1 ) 22.5 mg: The most common adverse reactions (≥ 5%) during TRELSTAR 22.5 mg therapy included hot flushes, erectile dysfunction, and testicular atrophy. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Verity Pharma at 1-844-837-4891 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of the three TRELSTAR formulations was evaluated in clinical trials involving patients with advanced prostate cancer. Mean testosterone levels increased above baseline during the first week following the initial injection, declining thereafter to baseline levels or below by the end of the second week of treatment.
The transient increase in testosterone levels may be associated with temporary worsening of disease signs and symptoms, including bone pain, neuropathy, hematuria, and urethral or bladder outlet obstruction. Spinal cord compression with weakness or paralysis of the lower extremities have occurred [ see Warnings and Precautions (5.2) ]. Adverse reactions reported for each of the three TRELSTAR formulations in the clinical trials, are presented in Table 2, Table 3, and Table 4.
The majority of adverse reactions related to TRELSTAR are a result of its pharmacological action, i.e., the induced variation in serum testosterone levels, either an increase in testosterone at the initiation of treatment, or a decrease in testosterone once castration is achieved. Local reactions at the injection site or allergic reactions may occur. The following adverse reactions were reported to have a possible or probable relationship to therapy as described by the treating physician in at least 1% of patients receiving TRELSTAR 3.75 mg.
Table 2. TRELSTAR 3.75 mg: Treatment-Related Adverse Reactions Reported by 1% or More of Patients During Treatment Adverse Reaction s * TRELSTAR 3.75 mg N = 140 N % Application Site Disorders Injection site pain 5
3.6 Body as a Whole Hot flush 82
58.6 Pain 3
2.1 Leg pain 3
2.1 Fatigue 3
2.1 Cardiovascular Disorders Hypertension 5
3.6 Central and Peripheral Nervous System Disorders Headache 7
5.0 Dizziness 2
1.4 Gastrointestinal Disorders Diarrhea 2
1.4 Vomiting 3
2.1 Musculoskeletal System Disorders Skeletal pain 17
12.1 Psychiatric Disorders Insomnia 3
2.1 Impotence 10
7.1 Emotional lability 2
1.4 Red Blood Cell Disorders Anemia 2
1.4 Skin and Appendages Disorders Pruritus 2
1.4 Urinary System Disorders Urinary tract infection 2
1.4Urinary retention 2 1.4 * Adverse reactions for TRELSTAR 3.75 mg are coded using the WHO Adverse Reactions Terminology (WHOART) The following adverse reactions were reported to have a possible or probable relationship to therapy as described by the treating physician in at least 1% of patients receiving TRELSTAR 11.25 mg. Table 3. TRELSTAR 11.25 mg: Treatment-Related Adverse Reactions Reported by 1% or More of Patients During Treatment Adverse Reac… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No drug-drug interaction studies involving TRELSTAR have been conducted. Human pharmacokinetic data with triptorelin suggest that C-terminal fragments produced by tissue degradation are either degraded completely within tissues, are rapidly degraded further in plasma, or cleared by the kidneys. Therefore, hepatic microsomal enzymes are unlikely to be involved in triptorelin metabolism.
However, in the absence of relevant data and as a precaution, hyperprolactinemic drugs should not be used concomitantly with TRELSTAR since hyperprolactinemia reduces the number of pituitary GnRH receptors.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and males of reproductive potential: TRELSTAR may impair fertility. ( 8.3 )
8.1Pregnancy Risk Summary Based on findings in animal studies and mechanism of action, TRELSTAR can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . Expected hormonal changes that occur with TRELSTAR treatment increase the risk for pregnancy loss. In animal developmental and reproductive toxicology studies, daily administration of triptorelin to pregnant rats during the period of organogenesis caused maternal toxicity and embryo-fetal toxicities, including loss of pregnancy, at doses as low as 0.2, 0.8, and 8 times the estimated human daily dose based on body surface area.
Advise pregnant patients and females of reproductive potential of the potential risk to the fetus. Data Animal Data Studies in pregnant rats administered triptorelin at doses of 2, 10, and 100 mcg/kg/day (approximately equivalent to 0.2, 0.8, and 8 times the estimated human daily dose based on body surface area) during the period of organogenesis demonstrated maternal toxicity and embryo-fetal toxicities. Embryo-fetal toxicities consisted of pre-implantation loss, increased resorption, and reduced mean number of viable fetuses at the high dose.
Teratogenic effects were not observed in viable fetuses in rats or mice. Doses administered to mice were 2, 20, and 200 mcg/kg/day (approximately equivalent to 0.1, 0.7, and 7 times the estimated human daily dose based on body surface area).
8.2Lactation The safety and efficacy of TRELSTAR have not been established in females. There are no data on the presence of triptorelin in human milk, the effects of the drug on milk production, or the effects of the drug on the breastfed child. Because of the potential for serious adverse reactions in a breastfed child from TRELSTAR, a decision should be made to either discontinue breastfeeding, or discontinue the drug taking into account the importance of the drug to the mother.
8.3Females and Males of Reproductive Potential Infertility Males Based on mechanism of action, TRELSTAR may impair fertility in males of reproductive potential [see Clinical Pharmacology ( 12.1 )] .
8.4Pediatric Use The safety and effectiveness of TRELSTAR in pediatric patients have not been established.
8.5Geriatric Use Prostate cancer occurs primarily in an older population. Clinical studies with TRELSTAR have been conducted primarily in patients ≥ 65 years [ see Clinical Pharmacology (12.3) and Clinical Studies (14) ].
8.6Renal Impairment Subjects with renal impairment had higher exposure than young healthy males [ see Clinical Pharmacology (12.3) ].
8.7Hepatic Impairment Subjects with hepatic impairment had higher exposure than young healthy males [ see Clinical Pharmacology (12.3) ].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animal studies and mechanism of action, TRELSTAR can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . Expected hormonal changes that occur with TRELSTAR treatment increase the risk for pregnancy loss. In animal developmental and reproductive toxicology studies, daily administration of triptorelin to pregnant rats during the period of organogenesis caused maternal toxicity and embryo-fetal toxicities, including loss of pregnancy, at doses as low as 0.2, 0.8, and 8 times the estimated human daily dose based on body surface area.
Advise pregnant patients and females of reproductive potential of the potential risk to the fetus. Data Animal Data Studies in pregnant rats administered triptorelin at doses of 2, 10, and 100 mcg/kg/day (approximately equivalent to 0.2, 0.8, and 8 times the estimated human daily dose based on body surface area) during the period of organogenesis demonstrated maternal toxicity and embryo-fetal toxicities. Embryo-fetal toxicities consisted of pre-implantation loss, increased resorption, and reduced mean number of viable fetuses at the high dose.
Teratogenic effects were not observed in viable fetuses in rats or mice. Doses administered to mice were 2, 20, and 200 mcg/kg/day (approximately equivalent to 0.1, 0.7, and 7 times the estimated human daily dose based on body surface area).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of TRELSTAR in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Prostate cancer occurs primarily in an older population. Clinical studies with TRELSTAR have been conducted primarily in patients ≥ 65 years [ see Clinical Pharmacology (12.3) and Clinical Studies (14) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Triptorelin is a synthetic decapeptide agonist analog of gonadotropin releasing hormone (GnRH). Comparative in vitro studies showed that triptorelin was 100-fold more active than native GnRH in stimulating luteinizing hormone release from monolayers of dispersed rat pituitary cells in culture and 20-fold more active than native GnRH in displacing 125 I-GnRH from pituitary receptor sites. In animal studies, triptorelin pamoate was found to have 13‑fold higher luteinizing hormone-releasing activity and 21-fold higher follicle-stimulating hormone-releasing activity compared to the native GnRH.
12.2Pharmacodynamics Following the first administration, there is a transient surge in circulating levels of luteinizing hormone (LH), follicle-stimulating hormone (FSH), testosterone, and estradiol [ see Adverse Reactions (6) ]. After chronic and continuous administration, usually 2 to 4 weeks after initiation of therapy, a sustained decrease in LH and FSH secretion and marked reduction of testicular steroidogenesis are observed. A reduction of serum testosterone concentration to a level typically seen in surgically castrated men is obtained.
Consequently, the result is that tissues and functions that depend on these hormones for maintenance become quiescent. These effects are usually reversible after cessation of therapy. Following a single intramuscular injection of TRELSTAR: TRELSTAR 3.75 mg : serum testosterone levels first increased, peaking on Day 4, and declined thereafter to low levels by Week 4 in healthy male volunteers.
TRELSTAR 11.25 mg : serum testosterone levels first increased, peaking on Days 2 – 3, and declined thereafter to low levels by Weeks 3 – 4 in men with advanced prostate cancer. TRELSTAR 22.5 mg : serum testosterone levels first increased, peaking on Day 3, and declined thereafter to low levels by Weeks 3 – 4 in men with advanced prostate cancer.
12.3Pharmacokinetics Results of pharmacokinetic investigations conducted in healthy men indicate that after intravenous bolus administration, triptorelin is distributed and eliminated according to a 3-compartment model and corresponding half-lives are approximately 6 minutes, 45 minutes, and 3 hours. Absorption Following a single intramuscular injection of TRELSTAR to patients with prostate cancer, mean peak serum concentrations of 28.4 ng/mL, 38.5 ng/mL, and 44.1 ng/mL occurred in 1 to 3 hours after the 3.75 mg, 11.25 mg, and 22.5 mg formulations, respectively.
Triptorelin did not accumulate over 9 months (3.75 mg and 11.25 mg) or 12 months (22.5 mg) of treatment. Distribution The volume of distribution following a single intravenous bolus dose of 0.5 mg of triptorelin peptide was 30 – 33 L in healthy male volunteers. There is no evidence that triptorelin, at clinically relevant concentrations, binds to plasma proteins.
Elimination Metabolism The metabolism of triptorelin in humans is unknown but is unlikely to involve hepatic microsomal enzymes (cytochrome P-450). The effect of triptorelin on the activity of other drug metabolizing enzymes is also unknown. Thus far, no metabolites of triptorelin have been identified.
Pharmacokinetic data suggest that C-terminal fragments produced by tissue degradation are either completely degraded in the tissues, or rapidly degraded in plasma, or cleared by the kidneys. Excretion Triptorelin is eliminated by both the liver and the kidneys. Following intravenous administration of 0.5 mg triptorelin peptide to six healthy male volunteers with a creatinine clearance of 149.9 mL/min, 41.7% of the dose was excreted in urine as intact peptide with a total triptorelin clearance of 211.9 mL/min.
This percentage increased to 62.3% in patients with liver disease who have a lower creatinine clearance (89.9 mL/min). It has also been observed that the nonrenal clearance of triptorelin (patient anuric, CI creat = 0) was 76.2 mL/min, thus indicating that the nonrenal elimination of triptorelin is ma… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Triptorelin is a synthetic decapeptide agonist analog of gonadotropin releasing hormone (GnRH). Comparative in vitro studies showed that triptorelin was 100-fold more active than native GnRH in stimulating luteinizing hormone release from monolayers of dispersed rat pituitary cells in culture and 20-fold more active than native GnRH in displacing 125 I-GnRH from pituitary receptor sites. In animal studies, triptorelin pamoate was found to have 13‑fold higher luteinizing hormone-releasing activity and 21-fold higher follicle-stimulating hormone-releasing activity compared to the native GnRH.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING TRELSTAR (triptorelin pamoate for injectable suspension) is supplied as a single dose vial with a Flip-Off cap containing sterile lyophilized triptorelin pamoate microgranules incorporated in a biodegradable copolymer of lactic and glycolic acids, with injection kit consisting of a vial adapter, a 21 gauge 1 ½” injection needle, and a pre-filled syringe containing sterile water for injection, USP, 2 mL. TRELSTAR 3.75 mg – NDC 74676-5902-1: 3.75 mg of slightly yellow microgranules provided in a vial with a violet flip-off cap with injection kit.
TRELSTAR 11.25 mg – NDC 74676-5904-1: 11.25 mg of slightly yellow microgranules provided in a vial with a yellow green flip-off cap with injection kit. TRELSTAR 22.5 mg – NDC 74676-5906-1: 22.5 mg of slightly yellow microgranules provided in a vial with a dark green flip-off cap with injection kit. Storage Store at 20-25°C (68-77°F). [See USP Controlled Room Temperature.] Do not freeze TRELSTAR.
📋 Description ▾
11 DESCRIPTION TRELSTAR is a white to slightly yellow lyophilized cake. When reconstituted, TRELSTAR has a milky appearance. It contains a pamoate salt of triptorelin, a synthetic decapeptide agonist analog of gonadotropin releasing hormone (GnRH).
The chemical name of triptorelin pamoate is 5-oxo-L-prolyl-L-histidyl-L-tryptophyl-L-seryl-L-tyrosyl-D-tryptophyl-L-leucyl-L-arginyl-L-prolylglycine amide (pamoate salt). The empirical formula is C 64 H 82 N 18 O 13 · C 23 H 16 O 6 and the molecular weight is 1699.9. The structural formula is: Structural formula for TRELSTAR (triptorelin pamoate).
The TRELSTAR products are sterile, lyophilized biodegradable microgranule formulations supplied as single dose vials. Refer to Table 5 for the composition of each TRELSTAR product. Table 5.
TRELSTAR Composition Ingredients TRELSTAR 3.75 mg TRELSTAR 11.25 mg TRELSTAR 22.5 mg triptorelin pamoate (base units) 3.75 mg 11.25 mg 22.5 mg poly- d,l -lactide-co-glycolide 138 mg 120 mg 183 mg mannitol, USP 71 mg 74 mg 74 mg carboxymethylcellulose sodium, USP 25 mg 26 mg 26 mg polysorbate 80, NF 1.7 mg 1.7 mg 1.7 mg When 2 mL sterile water is added to the vial containing TRELSTAR and mixed, a suspension is formed which is intended as an intramuscular injection. TRELSTAR is available in a vial plus a vial adapter, and a separate pre-filled syringe that contains sterile water for injection, USP, 2 mL.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Inform patients that if they have experienced hypersensitivity with other GnRH agonist drugs like TRELSTAR, TRELSTAR is contraindicated [see Contraindications (4) ]. Tumor Flare Inform patients that TRELSTAR can cause tumor flare during the first weeks of treatment. Inform patients that the increase in testosterone can cause an increase in urinary symptoms or pain.
Advise patients to contact their healthcare provider if urethral obstruction, spinal cord compression, paralysis, or new or worsened symptoms occur after beginning TRELSTAR treatment [see Warnings and Precautions (5.2) ]. Metabolic Syndrome Advise patients that there is an increased risk of metabolic changes such as hyperglycemia, diabetes, hyperlipidemia, and non-alcoholic fatty liver disease with TRELSTAR therapy. Inform patients that periodic monitoring for hyperglycemia and diabetes is required when being treated with TRELSTAR [see Warnings and Precautions (5.3) ].
Cardiovascular Disease Inform patients that there is an increased risk of myocardial infarction, sudden cardiac death, and stroke with TRELSTAR treatment. Advise patients to immediately report signs and symptoms associated with these events to their healthcare provider for evaluation [see Warnings and Precautions (5.4) ]. Convulsions Inform patients that there is an increased risk of convulsions with TRELSTAR treatment.
Advise patients to immediately contact their healthcare provider if they experience convulsions [see Warnings and Precautions ( 5.5 )] . Severe Cutaneous Adverse Reactions Inform patients that severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP), which may be life threatening or fatal, may occur during treatment with TRELSTAR. Advise patients to contact their healthcare provider or seek medical attention right away if they experience signs or symptoms of SCARs, e.g. a prodrome of fever, flu-like symptoms, mucosal lesions, progressive skin rash, or lymphadenopathy [see Warnings and Precautions ( 5.6 )].
Urogenital Disorders Advise patients that TRELSTAR may cause impotence. Infertility Inform patients that TRELSTAR may cause infertility [(see Use In Specific Populations (8.3) ]. Continuation of TRELSTAR Treatment Inform patients that TRELSTAR is usually continued, often with additional medication, after the development of metastatic castration-resistant prostate cancer [see Dosage and Administration (2.1) ].
For all medical inquiries contact: Verity Pharma, Medical Affairs 1-844-VERITY-1 (1-844-837-4891) Distributed by: Verity Pharmaceuticals, Inc. Ewing, NJ 08628 Manufactured by: Debiopharm Research & Manufacturing SA CH-1920 Martigny, Switzerland TRELSTAR® and its design are registered trademarks of Verity Pharmaceuticals, Inc. Verity Pharmaceuticals, Verity Pharma, and their designs are trademarks of Verity Pharmaceuticals, Inc. © 2026 Verity Pharmaceuticals Inc.
All rights reserved.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Results of pharmacokinetic investigations conducted in healthy men indicate that after intravenous bolus administration, triptorelin is distributed and eliminated according to a 3-compartment model and corresponding half-lives are approximately 6 minutes, 45 minutes, and 3 hours. Absorption Following a single intramuscular injection of TRELSTAR to patients with prostate cancer, mean peak serum concentrations of 28.4 ng/mL, 38.5 ng/mL, and 44.1 ng/mL occurred in 1 to 3 hours after the 3.75 mg, 11.25 mg, and 22.5 mg formulations, respectively.
Triptorelin did not accumulate over 9 months (3.75 mg and 11.25 mg) or 12 months (22.5 mg) of treatment. Distribution The volume of distribution following a single intravenous bolus dose of 0.5 mg of triptorelin peptide was 30 – 33 L in healthy male volunteers. There is no evidence that triptorelin, at clinically relevant concentrations, binds to plasma proteins.
Elimination Metabolism The metabolism of triptorelin in humans is unknown but is unlikely to involve hepatic microsomal enzymes (cytochrome P-450). The effect of triptorelin on the activity of other drug metabolizing enzymes is also unknown. Thus far, no metabolites of triptorelin have been identified.
Pharmacokinetic data suggest that C-terminal fragments produced by tissue degradation are either completely degraded in the tissues, or rapidly degraded in plasma, or cleared by the kidneys. Excretion Triptorelin is eliminated by both the liver and the kidneys. Following intravenous administration of 0.5 mg triptorelin peptide to six healthy male volunteers with a creatinine clearance of 149.9 mL/min, 41.7% of the dose was excreted in urine as intact peptide with a total triptorelin clearance of 211.9 mL/min.
This percentage increased to 62.3% in patients with liver disease who have a lower creatinine clearance (89.9 mL/min). It has also been observed that the nonrenal clearance of triptorelin (patient anuric, CI creat = 0) was 76.2 mL/min, thus indicating that the nonrenal elimination of triptorelin is mainly dependent on the liver. Specific Populations Age and Race The effects of age and race on triptorelin pharmacokinetics have not been systematically studied.
However, pharmacokinetic data obtained in young healthy male volunteers aged 20 to 22 years with an elevated creatinine clearance (approximately 150 mL/min) indicate that triptorelin was eliminated twice as fast in this young population as compared with patients with moderate renal insufficiency. This is related to the fact that triptorelin clearance is partly correlated to total creatinine clearance, which is well known to decrease with age [ see Use in Specific Populations ( 8.6 ) and ( 8.7 ) ]. Pediatric TRELSTAR has not been evaluated in patients less than 18 years of age [ see Use in Specific Populations (8.4) ].
Hepatic and Renal Impairment After an intravenous bolus injection of 0.5 mg triptorelin, the two distribution half-lives were unaffected by renal and hepatic impairment. However, renal insufficiency led to a decrease in total triptorelin clearance proportional to the decrease in creatinine clearance as well as increases in volume of distribution and consequently, an increase in elimination half-life (see Table 6). In subjects with hepatic insufficiency, a decrease in triptorelin clearance was more pronounced than that observed with renal insufficiency.
Due to minimal increases in the volume of distribution, the elimination half-life in subjects with hepatic insufficiency was similar to subjects with renal insufficiency. Subjects with renal or hepatic impairment had 2‑ to 4-fold higher exposure (AUC values) than young healthy males [ see Use in Specific Populations ( 8.6 ) and ( 8.7 ) ]. Table 6.
Pharmacokinetic Parameters (Mean ± SD) in Healthy Volunteers and Special Populations Following an IV Bolus Injection of 0.5 mg Triptorelin Group C max (ng/mL) AUC inf (h·ng/mL) Cl p (mL/min) Cl renal (mL/min) t 1/2 (h) Cl creat (mL/min) 6 healthy… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Following the first administration, there is a transient surge in circulating levels of luteinizing hormone (LH), follicle-stimulating hormone (FSH), testosterone, and estradiol [ see Adverse Reactions (6) ]. After chronic and continuous administration, usually 2 to 4 weeks after initiation of therapy, a sustained decrease in LH and FSH secretion and marked reduction of testicular steroidogenesis are observed. A reduction of serum testosterone concentration to a level typically seen in surgically castrated men is obtained.
Consequently, the result is that tissues and functions that depend on these hormones for maintenance become quiescent. These effects are usually reversible after cessation of therapy. Following a single intramuscular injection of TRELSTAR: TRELSTAR 3.75 mg : serum testosterone levels first increased, peaking on Day 4, and declined thereafter to low levels by Week 4 in healthy male volunteers.
TRELSTAR 11.25 mg : serum testosterone levels first increased, peaking on Days 2 – 3, and declined thereafter to low levels by Weeks 3 – 4 in men with advanced prostate cancer. TRELSTAR 22.5 mg : serum testosterone levels first increased, peaking on Day 3, and declined thereafter to low levels by Weeks 3 – 4 in men with advanced prostate cancer.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES TRELSTAR 3.75 mg TRELSTAR 3.75 mg was studied in a randomized, active control trial of 277 men with advanced prostate cancer. The clinical trial population consisted of 59.9% Caucasian, 39.3% Black, and 0.8% Other. There was no difference observed with triptorelin response between racial groups.
Men were between 47 and 89 years of age (mean = 71 years). Patients received either TRELSTAR 3.75 mg (N = 140) or an approved GnRH agonist monthly for 9 months. The primary efficacy endpoints were both achievement of castration by Day 29 and maintenance of castration from Day 57 through Day 253.
Castration levels of serum testosterone (≤ 1.735 nmol/L; equivalent to 50 ng/dL) in patients treated with TRELSTAR 3.75 mg were achieved at Day 29 in 125 of 137 (91.2%) patients and at Day 57 in 97.7% of patients. Maintenance of castration levels of serum testosterone from Day 57 through Day 253 was found in 96.2% of patients treated with TRELSTAR 3.75 mg. The presence of an acute-on-chronic flare phenomenon was also studied as a secondary efficacy endpoint.
Serum LH levels were measured at 2 hours after repeat TRELSTAR 3.75 mg administration on Days 85 and 169. One hundred twenty-four of the 126 evaluable patients (98.4%) on Day 85 had a serum LH level of ≤
1.0IU/L at 2 hours after dosing, indicating desensitization of the pituitary gonadotroph receptors. TRELSTAR 11.25 mg TRELSTAR 11.25 mg was studied in a randomized, active control trial of 346 men with advanced prostate cancer. The clinical trial population consisted of 48% Caucasian, 38% Black, and 15% Other.
There was no difference observed with triptorelin response between racial groups. Men were between 45 and 96 years of age (mean = 71 years). Patients received either TRELSTAR 11.25 mg (N = 174) every 12 weeks for a total of up to 3 doses (maximum treatment period of 253 days) or TRELSTAR 3.75 mg (N = 172) every 28 days for a total of up to 9 doses.
The primary efficacy endpoints were both achievement of castration by Day 29 and maintenance of castration from Day 57 through Day 253. Castration levels of serum testosterone (≤ 1.735 nmol/L; equivalent to 50 ng/dL) were achieved at Day 29 in 167 of 171 (97.7%) patients treated with TRELSTAR 11.25 mg, and maintenance of castration levels of serum testosterone from Day 57 through Day 253 was found in 94.4% of patients treated with TRELSTAR 11.25 mg. TRELSTAR 22.5 mg TRELSTAR 22.5 mg was studied in a non-comparative trial of 120 men with advanced prostate cancer.
The clinical trial population consisted of 64% Caucasian, 23% Black, and 13% Other, with a mean age of 71.1 years (range 51-93). Patients received TRELSTAR 22.5 mg (N = 120) every 24 weeks for a total of 2 doses (maximum treatment period of 337 days). The primary efficacy endpoints included achievement of castration by Day 29 and maintenance of castration from Day 57 through Day 337.
Castration levels of serum testosterone (≤ 1.735 nmol/L; equivalent to 50 ng/dL) were achieved at Day 29 in 97.5% (117 of 120) of patients treated with TRELSTAR 22.5 mg. Castration was maintained in 93.3% of patients in the period from Day 57 to Day 337. A summary of the clinical studies for TRELSTAR is provided in Table 7.
Table 7. Summary of TRELSTAR Clinical Studies Product Strength 3.75 mg 11.25 mg 22.5 mg Number of Patients 137 171 120 Treatment Schedule every 4 weeks every 12 weeks every 24 weeks Duration of Study 253 days 253 days 337 days Castration Rate * on Day 29, % (n/N) 91.2% (125/137) 97.7% (167/171) 97.5% (117/120) Rate of Castration Maintenance † from Days 57 – 253, % 96.2% 94.4% not applicable Rate of Castration Maintenance from Days 57 – 337, % (n/N) not applicable not applicable 93.3% (112/120) ‡ * Maintenance of castration was calculated using a frequency distribution. † Cumulative maintenance of castration was calculated using a survival analysis (Kaplan-Meier) technique. ‡ Calculation includes 5 patients who discontinued the study but who had castrate levels of… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In rats, triptorelin doses of 120, 600, and 3000 mcg/kg given every 28 days (approximately 0.3, 2, and 8 times the human monthly dose based on body surface area) resulted in increased mortality with a drug treatment period of 13 – 19 months. The incidences of benign and malignant pituitary tumors and histiosarcomas were increased in a dose-related manner. No oncogenic effect was observed in mice administered triptorelin for 18 months at doses up to 6000 mcg/kg every 28 days (approximately 8 times the human monthly dose based on body surface area).
Mutagenicity studies performed with triptorelin using bacterial and mammalian systems ( in vitro Ames test and chromosomal aberration test in CHO cells and an in vivo mouse micronucleus test) provided no evidence of mutagenic potential. After 60 days of subcutaneous treatment followed by a minimum of four estrus cycles prior to mating, triptorelin, at doses of 2, 20, and 200 mcg/kg/day in saline (approximately 0.2, 2, and 16 times the estimated human daily dose based on body surface area) or 2 monthly injections as slow release microspheres (~20 mcg/kg/day), had no effect on the fertility or general reproductive function of female rats.
No studies were conducted to assess the effect of triptorelin on male fertility.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In rats, triptorelin doses of 120, 600, and 3000 mcg/kg given every 28 days (approximately 0.3, 2, and 8 times the human monthly dose based on body surface area) resulted in increased mortality with a drug treatment period of 13 – 19 months. The incidences of benign and malignant pituitary tumors and histiosarcomas were increased in a dose-related manner. No oncogenic effect was observed in mice administered triptorelin for 18 months at doses up to 6000 mcg/kg every 28 days (approximately 8 times the human monthly dose based on body surface area).
Mutagenicity studies performed with triptorelin using bacterial and mammalian systems ( in vitro Ames test and chromosomal aberration test in CHO cells and an in vivo mouse micronucleus test) provided no evidence of mutagenic potential. After 60 days of subcutaneous treatment followed by a minimum of four estrus cycles prior to mating, triptorelin, at doses of 2, 20, and 200 mcg/kg/day in saline (approximately 0.2, 2, and 16 times the estimated human daily dose based on body surface area) or 2 monthly injections as slow release microspheres (~20 mcg/kg/day), had no effect on the fertility or general reproductive function of female rats.
No studies were conducted to assess the effect of triptorelin on male fertility.
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.6 ) 08/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL Trelstar 3.75 mg 3.75 mg every 4 weeks
Trelstar 3.75 mg Vial
PRINCIPAL DISPLAY PANEL Trelstar 11.25 mg 11.25 mg every 12 weeks
Trelstar 11.25 mg Vial
PRINCIPAL DISPLAY PANEL Trelstar 22.5 mg 22.5 mg every 24 weeks
Trelstar 22.5 mg Vial
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |