
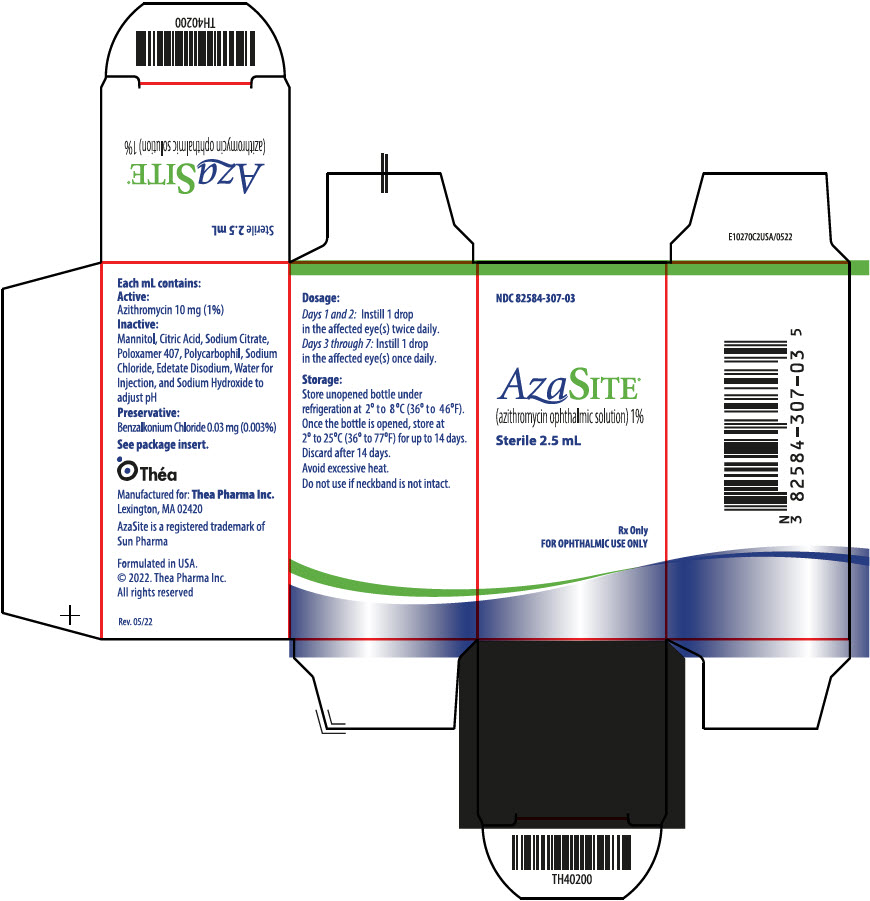
AZASITE azithromycin monohydrate 10 mg/mL Solution/ Drops, 1 bottle
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Macrolide Antimicrobial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Azithromycin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.03 mg / 1 mL
UNII F5UM2KM3W7
Benzalkonium chloride is a chemical compound that works as a preservative and antimicrobial agent in medications. It prevents bacterial and fungal growth in liquid formulations to keep the product safe during storage and use.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII TUF2IVW3M2
Poloxamer 407 is a synthetic polymer made from ethylene oxide and propylene oxide. In medicines, it acts as a thickener, emulsifier, and solubilizer to help mix ingredients and create the right texture.
-
UNII W25LM17A4W
Polycarbophil is a synthetic polymer that absorbs water and swells. It's used as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the digestive system.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 1Q73Q2JULR
Sodium citrate is a salt derived from citric acid. It works as a buffer to maintain the medicine's pH level and may also help improve taste or act as a preservative in the formulation.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $98.420 | $246.05 / 2.5 ml |
| Medicaid paysCMS SDUD · 12 mo | $102.14 | $255.35 / 2.5 ml |
| Medicare drug plans payPart D · Q2 2026 | $94.37 | $235.93 / 2.5 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Azasite 10 mg/mLthis 82584-0307-03 | Thea | 1 bottle | $98.420 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 82584-0307-02 | 1 BOTTLE, DROPPER in 1 CARTON (82584-307-02) / 2.5 mL in 1 BOTTLE, DROPPER | — | — | 2022-11-01 | Active |
| 82584-0307-03 You're viewing this | 1 BOTTLE, DROPPER in 1 CARTON (82584-307-03) / 2.5 mL in 1 BOTTLE, DROPPER | $98.42 / mL | $246.05 | 2022-11-01 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 82584-0307-03?
What is the difference between NDC 82584-0307-03 and NDC 82584-0307-02?
What NDC number is used to bill for this package of AZASITE azithromycin monohydrate 10 mg/mL Solution/ Drops?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE AzaSite ® is indicated for the treatment of bacterial conjunctivitis caused by susceptible isolates of the following microorganisms: CDC coryneform group G Efficacy for this organism was studied in fewer than 10 infections. Haemophilus influenzae Staphylococcus aureus Streptococcus mitis group Streptococcus pneumoniae AzaSite is a macrolide antimicrobial indicated for the treatment of bacterial conjunctivitis caused by susceptible isolates of the following microorganisms: CDC coryneform group G, Haemophilus influenzae, Staphylococcus aureus, Streptococcus mitis group, and Streptococcus pneumoniae.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dosage regimen for the treatment of bacterial conjunctivitis is: Instill 1 drop in the affected eye(s) twice daily, eight to twelve hours apart for the first two days and then instill 1 drop in the affected eye(s) once daily for the next five days. Instill 1 drop in the affected eye(s) twice daily, eight to twelve hours apart for the first two days and then instill 1 drop in the affected eye(s) once daily for the next five days. ( 2 )
2.1Recommended Dosage The recommended dosage for the treatment of bacterial conjunctivitis is: Instill 1 drop in the affected eye(s) twice daily, eight to twelve hours apart for the first two days and then instill 1 drop in the affected eye(s) once daily for the next five days.
2.2Administration Instructions Wash hands prior to using AzaSite. Invert the closed bottle (upside down) and shake once before each use. Remove the tan cap with the bottle still in the inverted position.
Tilt head back, and with bottle inverted, gently squeeze bottle to instill one drop into the affected eye(s). Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by AzaSite (azithromycin ophthalmic solution) or other antibacterial drugs in the future.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 2.5 mL of a 1% sterile topical ophthalmic solution. 2.5 mL of 1% sterile topical ophthalmic solution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Azasite is contraindicated in patients with hypersensitivity to any component of this product. Hypersensitivity ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS For topical ophthalmic use only. ( 5.1 ) Anaphylaxis and hypersensitivity have been reported with systemic use of azithromycin. ( 5.2 ) Growth of resistant organisms may occur with prolonged use. ( 5.3 ) Patients should not wear contact lenses if they have signs or symptoms of bacterial conjunctivitis. ( 5.4 )
5.1Topical Ophthalmic Use Only NOT FOR INJECTION. AzaSite is indicated for topical ophthalmic use only, and should not be administered systemically, injected subconjunctivally, or introduced directly into the anterior chamber of the eye.
5.2Anaphylaxis and Hypersensitivity with Systemic Use of Azithromycin In patients receiving systemically administered azithromycin, serious allergic reactions, including angioedema, anaphylaxis, and dermatologic reactions including Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported rarely in patients on azithromycin therapy. Although rare, fatalities have been reported. The potential for anaphylaxis or other hypersensitivity reactions should be considered based on known hypersensitivity to azithromycin when administered systemically.
5.3Growth of Resistant Organisms with Prolonged Use As with other anti-infectives, prolonged use may result in overgrowth of non-susceptible organisms, including fungi. If super-infection occurs, discontinue use and institute alternative therapy. Whenever clinical judgment dictates, the patient should be examined with the aid of magnification, such as slit-lamp biomicroscopy, and where appropriate, fluorescein staining.
5.4Contamination of the Applicator Tip Avoid contaminating the applicator tip by not allowing it to touch the eye, fingers or other sources.
5.5Avoidance of Contact Lenses Patients should be advised not to wear contact lenses if they have signs or symptoms of bacterial conjunctivitis.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in one clinical trial of a drug cannot be directly compared with the rates in the clinical trials of the same or another drug and may not reflect the rates observed in practice. The data described below reflect exposure to AzaSite in 698 patients. The population was between 1 and 87 years old with clinical signs and symptoms of bacterial conjunctivitis.
The most frequently reported ocular adverse reaction reported in patients receiving AzaSite was eye irritation. This reaction occurred in approximately 1 to 2% of patients. Other adverse reactions associated with the use of AzaSite were reported in less than 1% of patients and included ocular reactions (blurred vision, burning, stinging and irritation upon instillation, contact dermatitis, corneal erosion, dry eye, eye pain, itching, ocular discharge, punctate keratitis, visual acuity reduction) and non-ocular reactions (dysgeusia, facial swelling, hives, nasal congestion, periocular swelling, rash, sinusitis, urticaria).
Most common adverse reaction reported in patients was eye irritation (1 to 2% of patients). ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Thea Pharma Inc. at 1-833-838-4028 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . See 17 for PATIENT COUNSELING INFORMATION and FDA-approved patient labeling.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from published literature and postmarketing experience over several decades with azithromycin use in pregnant women have not identified any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes ( see Data ). Developmental toxicity studies with azithromycin in rats, mice, and rabbits showed no drug-induced fetal malformations at doses up to 200 mg/kg/day. The doses used in these studies were orders of magnitude in excess of the clinical exposure that would be possible following topical ocular administration of azithromycin.
( see Data ). The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data Available data from published observational studies, case series, and case reports over several decades do not suggest an increased risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes with oral or topical ophthalmic azithromycin use in pregnant women. Limitations of these data include the lack of randomization and inability to control for confounders such as underlying maternal disease and maternal use of concomitant medications.
Animal Data Azithromycin administered during the period of organogenesis did not cause fetal malformations in rats and mice at oral doses up to 200 mg/kg/day (moderately maternally toxic). Assuming 100% absorption from topical ocular exposure, this dose is hundreds of times daily dose that can be achieved with topical ophthalmic administration. In rabbits administered azithromycin at oral doses of 10, 20, and 40 mg/kg/day during organogenesis, reduced maternal body weight and food consumption were observed in all groups; no evidence of fetotoxicity or teratogenicity was observed at these doses, the highest of which is estimated to be at least 100 times topical ophthalmic dose assuming 100% absorption from ocular exposure.
In a pre- and postnatal development study, azithromycin was administered orally to pregnant rats from day 6 of pregnancy until weaning at doses of 50 or 200 mg/kg/day. Maternal toxicity (reduced food consumption and body weight gain; increased stress at parturition) was observed at the higher dose. Effects in the offspring were noted at 200 mg/kg/day during the postnatal development period (decreased viability, delayed developmental landmarks).
These effects were not observed in a pre- and postnatal rat study when up to 200 mg/kg/day of azithromycin was given orally beginning on day 15 of pregnancy until weaning. Assuming 100% absorption from topical ocular exposure, this dose is hundreds of times daily dose that can be achieved with topical ophthalmic administration.
8.2Lactation Risk Summary Azithromycin is present in human milk ( see Data ). Non-serious adverse reactions have been reported in breastfed infants after maternal administration of oral azithromycin. There are no available data on the effects of azithromycin on milk production.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for AzaSite and any potential adverse effects on the breastfed infant from AzaSite. Data Azithromycin breastmilk concentrations were measured in 20 women after receiving a single 2 g oral dose of azithromycin during labor. Breastmilk samples collected on days 3 and 6 postpartum as well as 2 and 4 weeks postpartum revealed the presence of azithromycin in breastmilk up to 4 weeks after dosing.
In another study, a single dose of azithromycin 500 mg was administered intravenously to 8 women prior to incision for cesarean section. Breastmilk (colostrum) samples obtained between…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published literature and postmarketing experience over several decades with azithromycin use in pregnant women have not identified any drug-associated risks for major birth defects, miscarriage, or adverse maternal or fetal outcomes ( see Data ). Developmental toxicity studies with azithromycin in rats, mice, and rabbits showed no drug-induced fetal malformations at doses up to 200 mg/kg/day. The doses used in these studies were orders of magnitude in excess of the clinical exposure that would be possible following topical ocular administration of azithromycin.
( see Data ). The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data Available data from published observational studies, case series, and case reports over several decades do not suggest an increased risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes with oral or topical ophthalmic azithromycin use in pregnant women. Limitations of these data include the lack of randomization and inability to control for confounders such as underlying maternal disease and maternal use of concomitant medications.
Animal Data Azithromycin administered during the period of organogenesis did not cause fetal malformations in rats and mice at oral doses up to 200 mg/kg/day (moderately maternally toxic). Assuming 100% absorption from topical ocular exposure, this dose is hundreds of times daily dose that can be achieved with topical ophthalmic administration. In rabbits administered azithromycin at oral doses of 10, 20, and 40 mg/kg/day during organogenesis, reduced maternal body weight and food consumption were observed in all groups; no evidence of fetotoxicity or teratogenicity was observed at these doses, the highest of which is estimated to be at least 100 times topical ophthalmic dose assuming 100% absorption from ocular exposure.
In a pre- and postnatal development study, azithromycin was administered orally to pregnant rats from day 6 of pregnancy until weaning at doses of 50 or 200 mg/kg/day. Maternal toxicity (reduced food consumption and body weight gain; increased stress at parturition) was observed at the higher dose. Effects in the offspring were noted at 200 mg/kg/day during the postnatal development period (decreased viability, delayed developmental landmarks).
These effects were not observed in a pre- and postnatal rat study when up to 200 mg/kg/day of azithromycin was given orally beginning on day 15 of pregnancy until weaning. Assuming 100% absorption from topical ocular exposure, this dose is hundreds of times daily dose that can be achieved with topical ophthalmic administration.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of AzaSite solution in pediatric patients have been established. The efficacy of AzaSite in treating bacterial conjunctivitis in pediatric patients has been demonstrated in controlled clinical trials [see Clinical Studies (14) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Azithromycin is a macrolide antibiotic [see Clinical Pharmacology (12.4) ] .
12.3Pharmacokinetics The plasma concentration of azithromycin following ocular administration of AzaSite (azithromycin ophthalmic solution) in humans is unknown. Based on the proposed dose of one drop to each eye (total dose of 100 mcL or 1 mg) and exposure information from systemic administration, the systemic concentration of azithromycin following ocular administration is estimated to be below quantifiable limits (≤10 ng/mL) at steady-state in humans, assuming 100% systemic availability.
12.4Microbiology Azithromycin acts by binding to the 50S ribosomal subunit of susceptible microorganisms and interfering with microbial protein synthesis. Azithromycin has been shown to be active against most isolates of the following microorganisms, both in vitro and clinically in conjunctival infections [see Indications and Usage (1) ] . CDC coryneform group G Efficacy for this organism was studied in fewer than 10 infections.
Haemophilus influenzae Staphylococcus aureus Streptococcus mitis group Streptococcus pneumoniae The following in vitro data are also available, but their clinical significance in ophthalmic infections is unknown. The safety and effectiveness of AzaSite in treating ophthalmological infections due to these microorganisms have not been established. The following microorganisms are considered susceptible when evaluated using systemic breakpoints.
However, a correlation between the in vitro systemic breakpoint and ophthalmological efficacy has not been established. This list of microorganisms is provided as an aid only in assessing the potential treatment of conjunctival infections. Azithromycin exhibits in vitro minimal inhibitory concentrations (MICs) of equal or less (systemic susceptible breakpoint) against most (≥90%) of isolates of the following ocular pathogens: Chlamydia pneumoniae Chlamydia trachomatis Legionella pneumophila Moraxella catarrhalis Mycoplasma hominis Mycoplasma pneumoniae Neisseria gonorrhoeae Peptostreptococcus species Streptococci (Groups C, F, G) Streptococcus pyogenes Streptococcus agalactiae Ureaplasma urealyticum Viridans group streptococci
🧬 Mechanism of Action ▾
12.1Mechanism of Action Azithromycin is a macrolide antibiotic [see Clinical Pharmacology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING AzaSite® is a sterile aqueous topical ophthalmic formulation of 1% azithromycin. NDC 82584-307-03: 2.5 mL in 5 mL bottle containing a total of 25 mg of azithromycin in a white, oblong, low-density polyethylene (LDPE) bottle, with a clear LDPE dropper tip, and a tan colored high density polyethylene (HDPE) eyedropper cap. A white tamper evident over-cap is provided.
Storage and Handling Store unopened bottle under refrigeration at 2° to 8°C (36° to 46°F). Once the bottle is opened, store at 2° to 25°C (36° to 77°F) for up to 14 days. Discard after the 14 days.
The white tamper evident over-cap can be thrown away. Retain the tan cap and keep the bottle tightly closed when not in use.
📦 Storage and Handling ▾
Storage and Handling Store unopened bottle under refrigeration at 2° to 8°C (36° to 46°F). Once the bottle is opened, store at 2° to 25°C (36° to 77°F) for up to 14 days. Discard after the 14 days. The white tamper evident over-cap can be thrown away. Retain the tan cap and keep the bottle tightly closed when not in use.
📋 Description ▾
11 DESCRIPTION AzaSite® (azithromycin ophthalmic solution) is a 1% sterile aqueous topical ophthalmic solution of azithromycin formulated in DuraSite ® (polycarbophil, edetate disodium, sodium chloride). AzaSite is an off-white, viscous liquid with an osmolality of approximately 290 mOsm/kg. Preservative: 0.003% benzalkonium chloride.
Inactives: mannitol, citric acid, sodium citrate, poloxamer 407, polycarbophil, edetate disodium (EDTA), sodium chloride, water for injection, and sodium hydroxide to adjust pH to 6.3. Azithromycin is a macrolide antibiotic with a 15-membered ring. Its chemical name is (2R,3S,4R,5R,8R,10R,11R,12S,13S,14R)-13-[(2,6-dideoxy-3-C-methyl-3-O-methyl-α-L-ribohexopyranosyl)oxy]-2-ethyl-3,4,10-trihydroxy-3,5,6,8,10,12,14-heptamethyl-11-[[3,4,6-trideoxy-3-(dimethylamino)-β-D-xylo-hexopyranosyl]oxy]-1-oxa-6-aza-cyclopentadecan-15-one, and the structural formula is: Azithromycin has a molecular weight of 749, and its empirical formula is C 38 H 72 N 2 O 12 .
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-Approved Patient Labeling ( Patient Information and Instructions for Use ). Avoiding Contamination of the Applicator Tip Advise patients to avoid contaminating the applicator tip by not allowing it to touch the eye, fingers or other sources. When to Seek Physician Advice Direct patients to discontinue use and contact a physician if any signs of an allergic reaction occur.
Tell patients that although it is common to feel better early in the course of the therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by AzaSite (azithromycin ophthalmic solution) or other antibacterial drugs in the future. Contact Lens Use Advise patients not to wear contact lenses if they have signs or symptoms of bacterial conjunctivitis.
Administration Instructions Advise patients to thoroughly wash hands prior to using AzaSite. Advise patients to invert the closed bottle (upside down) and shake once before each use. Remove cap with bottle still in the inverted position.
Tilt head back, and with bottle inverted, gently squeeze bottle to instill one drop into the affected eye(s).