
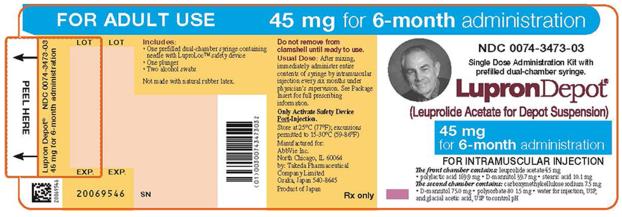
Lupron Depot leuprolide acetate Kit — NDC 0074-3473-03 (Billing 00074-3473-03)
This is a package of Lupron Depot leuprolide acetate Kit from AbbVie Inc., marketed since Dec 1995 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0074-3473-03 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0074 labeler · 3473 product · 03 package
- Package marketed since
- Dec 23, 1995
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0074347303 2
- Medicaid fills, this package
- 2,490 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067506
- GCN: 30083
- GPI-14 (Medi-Span): 21405010256450
- HICL (First Databank): 021102
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1115257
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Gonadotropin Releasing Hormone Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- That's a really common concern, and it's smart to ask. When you first start leuprolide, your testosterone levels actually spike for a week or two before the drug kicks in and bring...
- Why does my doctor say my symptoms might get worse right after starting leuprolide?
- Hot flashes are actually one of the most common side effects in men taking leuprolide — over half of men in clinical studies experienced them. Because leuprolide drops testosterone...
- Will I get hot flashes? I thought that was just a women's issue.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $3,127.85 | — |
| Medicare drug plans payPart D · Q2 2026 | $13,443.46 | — |
| Medicare Part B allowsASP · J9217 | $160.342 / J9217 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00074-3473-03 You're viewing this Main listing | 1 KIT in 1 CARTON * 1.5 mL in 1 SYRINGE * 1 SWAB in 1 PACKET | 1995-12-23 | — | Active |
| 00074-3473-55 0074-3473-55 | 1 KIT in 1 CELLO PACK * 1.5 mL in 1 SYRINGE * 1 SWAB in 1 PACKET * 1.5 mL in 1 SYRINGE * 1 SWAB in 1 PACKET | 2026-03-15 | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Lupron Depot leuprolide acetate Kit?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Leuprolide Acetate 00781-4003-32 | Sandoz | 1 kit | $197.606 | AP | Availability likely | — |
| Leuprolide Acetate 55150-0478-01 | Eugia | 1 kit | $197.606 | AP | Availability likely | — |
| leuprolide acetate 47335-0936-40 | Sun | 1 kit | $197.606 | AP | Availability likely | — |
| Leuprolide Acetate 70710-1769-03 | Zydus | 1 kit | $197.606 | AP | Availability likely | — |
| Leuprolide Acetate 72664-0611-28 | VGYAAN | 1 kit | $261.318 | AP | FDA listed | — |
| Lupron Depot 00074-3641-03 | AbbVie | 1 kit | $1,822.080 | — | Availability likely | — |
| Lupron Depot 00074-3642-03 | AbbVie | 1 kit | $2,174.170 | — | Availability likely | — |
| Lupron Depot 00074-3663-03 | AbbVie | 1 kit | $5,437.400 | — | Availability likely | — |
| Lupron Depot 00074-3346-03 | AbbVie | 1 kit | $6,516.300 | — | Availability likely | — |
| Lupron Depotthis 00074-3473-03 | AbbVie | 1 kit | — | — | FDA listed | — |
| Fensolvi 62935-0153-50 | TOLMAR | 1 kit | — | — | FDA listed | — |
| Lupron Depot-PED 00074-9694-03 | AbbVie | 1 kit | — | — | FDA listed | — |
| Lupron Depot-PED 00074-2108-03 | AbbVie | 1 kit | — | — | FDA listed | — |
| Lupron Depot-PED 00074-2440-03 | AbbVie | 1 kit | — | — | FDA listed | — |
| Lupron Depot 00074-3683-03 | AbbVie | 1 kit | — | — | FDA listed | — |
| Leuprolide Acetate Depot 69097-0909-50 | CIPLA | 1 kit | — | — | FDA listed | — |
| Lutrate Depot 83831-0134-01 | Avyxa | 1 kit | — | — | FDA listed | — |
| Lupron Depot-PED 00074-3575-01 | AbbVie | 1 kit | — | — | FDA listed | — |
| Leuprolide Acetate 70771-1687-03 | Zydus | 1 kit | — | AP | FDA listed | — |
| Lupron Depot-PED 00074-2282-03 | AbbVie | 1 kit | — | — | FDA listed | — |
| Lupron Depot-PED 00074-3779-03 | AbbVie | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8921326 ↗ | Method of use | U-1666 | Feb 5, 2031 |
| US 9617303 ↗ | Method of use | U-4001 | Mar 22, 2028 |
Is there a generic version of LUPRON DEPOT 45 MG 6 MONTH KIT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from AbbVie Inc. labeler code 00074
- Kaletra Lopinavir and Ritonavir 100 mg; 25 mg Tablet, Film Coated NDC 0074-3008-60
- Duopa Carbidopa and Levodopa 20 mg/mL; 4.63 mg/mL Suspension NDC 0074-3012-07
- Gengraf Cyclosporine 25 mg Capsule NDC 0074-3108-32
- Gengraf Cyclosporine 100 mg Capsule NDC 0074-3109-32
- Lupron Depot leuprolide acetate Kit NDC 0074-3346-03
- Norvir Ritonavir 100 mg Powder NDC 0074-3399-30
- Lupron Depot-PED leuprolide acetate Kit NDC 0074-3575-01
- Lupron Depot leuprolide acetate Kit NDC 0074-3641-03
- Lupron Depot leuprolide acetate Kit NDC 0074-3642-03
- Lupron Depot leuprolide acetate Kit NDC 0074-3663-03
- Lupron Depot leuprolide acetate Kit NDC 0074-3683-03
- Synthroid Levothyroxine Sodium 137 ug Tablet NDC 0074-3727-19
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE LUPRON DEPOT 7.5 mg for 1-month administration, 22.5 mg for 3-month administration, 30 mg for 4-month administration, and 45 mg for 6-month administration (leuprolide acetate) are indicated for the treatment of advanced prostate cancer. LUPRON DEPOT is a gonadotropin releasing hormone (GnRH) agonist indicated for: treatment of advanced prostate cancer. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION LUPRON DEPOT must be administered by a healthcare provider. In patients treated with GnRH analogues for prostate cancer, treatment is usually continued upon development of non-metastatic and metastatic castration-resistant prostate cancer. Table 1.
LUPRON DEPOT Recommended Dosing Dosage 7.5 mg for 1-Month Administration 22.5 mg for 3-Month Administration 30 mg for 4-Month Administration 45 mg for 6-Month Administration Recommended dose 1 injection every 4 weeks 1 injection every 12 weeks 1 injection every 16 weeks 1 injection every 24 weeks LUPRON DEPOT must be administered under the supervision of a physician. Due to different release characteristics, the dosage strengths are not additive and must be selected based upon the desired dosing schedule. ( 2 ) LUPRON DEPOT 7.5 mg for 1-month administration, given as a single intramuscular injection every 4 weeks.
( 2.1 ) LUPRON DEPOT 22.5 mg for 3-month administration, given as a single intramuscular injection every 12 weeks. ( 2.2 ) LUPRON DEPOT 30 mg for 4-month administration, given as a single intramuscular injection every 16 weeks. ( 2.3 ) LUPRON DEPOT 45 mg for 6-month administration, given as a single intramuscular injection every 24 weeks.
( 2.4 ) Figure 1 Figure 2 Figure 3 figure 4 figure 5 Figure 6 Figure 7
2.1LUPRON DEPOT 7.5 mg for 1-Month Administration The recommended dose of LUPRON DEPOT 7.5 mg for 1-month administration is one injection every 4 weeks. Do not use concurrently a fractional dose, or a combination of doses of this or any depot formulation due to different release characteristics. Incorporated in a depot formulation, the lyophilized microspheres must be reconstituted and should be administered every 4 weeks as a single intramuscular injection.
For optimal performance of the prefilled dual chamber syringe (PDS), read and follow the instructions in Section 2.5 .
2.2LUPRON DEPOT 22.5 mg for 3-Month Administration The recommended dose of LUPRON DEPOT 22.5 mg for 3-month administration is one injection every 12 weeks. Do not use concurrently a fractional dose, or a combination of doses of this or any depot formulation due to different release characteristics. Incorporated in a depot formulation, the lyophilized microspheres must be reconstituted and should be administered every 12 weeks as a single intramuscular injection.
For optimal performance of the prefilled dual chamber syringe (PDS), read and follow the instructions in Section 2.5 .
2.3LUPRON DEPOT 30 mg for 4-Month Administration The recommended dose of LUPRON DEPOT 30 mg for 4-month administration is one injection every 16 weeks. Do not use concurrently a fractional dose, or a combination of doses of this or any depot formulation due to different release characteristics. Incorporated in a depot formulation, the lyophilized microspheres must be reconstituted and should be administered every 16 weeks as a single intramuscular injection.
For optimal performance of the prefilled dual chamber syringe (PDS), read and follow the instructions in Section 2.5 .
2.4LUPRON DEPOT 45 mg for 6-Month Administration The recommended dose of LUPRON DEPOT 45 mg for 6-month administration is one injection every 24 weeks. Do not use concurrently a fractional dose, or a combination of doses of this or any depot formulation due to different release characteristics. Incorporated in a depot formulation, the lyophilized microspheres must be reconstituted and should be administered every 24 weeks as a single intramuscular injection.
For optimal performance of the prefilled dual chamber syringe (PDS), read and follow the instructions in Section 2.5 .
2.5Reconstitution and Administration for Injection of LUPRON DEPOT Reconstitute and administer the lyophilized microspheres as a single intramuscular injection. Inject the suspension immediately or discard if not used within two hours, because LUPRON DEPOT does not contain a preservative. 1. Visually inspect the LUPRON DEPOT powder. DO NOT USE the sy… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS LUPRON DEPOT 7.5 mg for 1-month administration, 22.5 mg for 3-month administration, 30 mg for 4-month administration, and 45 mg for 6-month administration are each supplied as a kit with a prefilled single-dose dual chamber syringe containing white lyophilized microsphere powder in one chamber and a clear, colorless diluent for reconstitution in the other chamber. 7.5 mg, 22.5 mg, 30 mg, and 45 mg injections in a kit with prefilled dual chamber syringe. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS LUPRON DEPOT is contraindicated in: Hypersensitivity LUPRON DEPOT is contraindicated in individuals with known hypersensitivity to GnRH agonists or any of the excipients in LUPRON DEPOT. Reports of anaphylactic reactions to GnRH agonists have been reported in the medical literature. Hypersensitivity to GnRH, GnRH agonist or any of the excipients in LUPRON DEPOT. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Tumor Flare: Increased serum testosterone (~ 50% above baseline) may occur when initiating treatment with LUPRON DEPOT. Monitor for worsening of prostate cancer symptoms during the first few weeks of treatment. Monitor patients for increased bone pain, neuropathy, hematuria, ureteral obstruction, and spinal cord compression.
Spinal cord compressions may contribute to paralysis with or without fatal complications. ( 5.1 ) Metabolic Syndrome: The use of GnRH agonists may lead to an increased risk of metabolic changes such as hyperglycemia, diabetes, hyperlipidemia, and non-alcoholic fatty liver disease. Monitor for signs and symptoms of metabolic syndrome including lipids, blood glucose level and/or HbA1c and manage according to current treatment guidelines.
( 5.2 ) Cardiovascular Diseases: Increased risk of myocardial infarction, sudden cardiac death and stroke has been reported in association with use of GnRH analogs in men. Monitor for cardiovascular disease and manage according to institutional guidelines. ( 5.3 ) Effect on QT/QTc Interval: Androgen deprivation therapy may prolong the QT interval.
Consider risks and benefits. ( 5.4 ) Convulsions have been observed in patients with or without a history of predisposing factors. Manage convulsions according to institutional guidelines.
( 5.5 ) Severe Cutaneous Adverse Reactions (SCARs), including Stevens-Johnson syndrome/toxic epidermal necrolysis (SJS/TEN), occurred in patients treated with LUPRON DEPOT. Interrupt LUPRON DEPOT if signs or symptoms of SCARs develop. Permanently discontinue if SCARs are confirmed.
( 5.6 ) Embryo-Fetal Toxicity: LUPRON DEPOT may cause fetal harm. ( 5.8 , 8.1 )
5.1Tumor Flare Initially, LUPRON DEPOT, like other GnRH agonists, causes increases in serum levels of testosterone to approximately 50% above baseline during the first weeks of treatment. Patients may experience worsening of symptoms or onset of new signs and symptoms during the first few weeks of treatment, including bone pain, neuropathy, hematuria, or bladder outlet obstruction. Spinal cord compression may contribute to paralysis with or without fatal complications.
Monitor patients for tumor flare symptoms during the first few weeks of treatment with LUPRON DEPOT. Closely monitor patients with metastatic vertebral lesions and/or with urinary tract obstruction for new or worsening symptoms.
5.2Metabolic Syndrome The use of GnRH agonists may lead to metabolic changes such as hyperglycemia, diabetes mellitus, and hyperlipidemia. Non-alcoholic fatty liver disease, including cirrhosis, occurred in the post-marketing setting. Hyperglycemia may represent new-onset diabetes mellitus or worsening of glycemic control in patients with pre-existing diabetes.
Monitor for changes in serum lipids, blood glucose and/or glycosylated hemoglobin (HbA1c) in patients receiving a GnRH agonist, and manage according to current treatment guidelines.
5.3Cardiovascular Diseases Increased risk of developing myocardial infarction, sudden cardiac death and stroke has been reported in association with use of GnRH agonists in men. The risk appears low based on the reported odds ratios, and should be evaluated carefully along with cardiovascular risk factors when determining a treatment for patients with prostate cancer. Patients receiving a GnRH agonist should be monitored for symptoms and signs suggestive of development of cardiovascular disease and be managed according to institutional guidelines.
5.4Effect on QT/QTc Interval Androgen deprivation therapy may prolong the QT/QTc interval. Providers should consider whether the benefits of androgen deprivation therapy outweigh the potential risks in patients with congenital long QT syndrome, congestive heart failure, frequent electrolyte abnormalities, and in patients taking drugs known to prolong the QT interval. Electrolyte abnormalities should be corrected.
Consider periodic monitoring of electrocardiograms and electrolytes.
5.5Convuls… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following is discussed in more detail in other sections of the labeling: Tumor Flare [see Warnings and Precautions ( 5.1 )] Metabolic Syndrome [see Warnings and Precautions ( 5.2 )] Cardiovascular Disease [see Warnings and Precautions ( 5.3 )] Effect on QT/QTc Interval [see Warnings and Precautions ( 5.4 )] Convulsions [see Warnings and Precautions ( 5.5 )] Severe Cutaneous Adverse Reactions [see Warnings and Precautions ( 5.6 )] Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
LUPRON DEPOT 7.5 mg for 1-month administration: The most common adverse reactions (>10%) were general pain, hot flashes/sweats, GI disorders, edema, respiratory disorder, urinary disorder. ( 6.1 ) LUPRON DEPOT 22.5 mg for 3-month administration: The most common adverse reactions (>10%) were general pain, injection site reaction, hot flashes/sweats, GI disorders, joint disorders, testicular atrophy, urinary disorders. ( 6.2 ) LUPRON DEPOT 30 mg for 4-month administration: The most common adverse reactions (>10%) were asthenia, flu syndrome, general pain, headache, injection site reaction, hot flashes/sweats, GI disorders, edema, skin reaction, urinary disorders.
( 6.3 ) LUPRON DEPOT 45 mg for 6-month administration: The most common adverse reactions (>10%) were hot flush, injection site pain, upper respiratory infection, and fatigue. ( 6.4 ) In postmarketing experience, mood swings, depression, rare reports of suicidal ideation and attempt, rare reports of pituitary apoplexy, and rare reports of serious drug-induced liver injury have been reported. ( 6.5 ) To report SUSPECTED ADVERSE REACTIONS, contact AbbVie Inc.at 1-800-633-9110 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1LUPRON DEPOT 7.5 mg for 1-Month Administration In the majority of patients testosterone levels increased above baseline during the first week, declining thereafter to baseline levels or below by the end of the second week of treatment. Potential exacerbations of signs and symptoms during the first few weeks of treatment is a concern in patients with vertebral metastases and/or urinary obstruction or hematuria which, if aggravated, may lead to neurological problems such as temporary weakness and/or paresthesia of the lower limbs or worsening of urinary symptoms [see Warnings and Precautions ( 5.1 )] .
In a clinical trial of LUPRON DEPOT 7.5 mg for 1-month administration, the following adverse reactions were reported in 5% or more of the patients during the initial 24-week treatment period. Table 2. Adverse Reactions Reported in ≥ 5% of Patients LUPRON DEPOT 7.5 mg for 1-Month Administration (N=56) N (%) Body As A Whole General pain 13 (23.2) Infection 3 (5.4) Cardiovascular System Hot flashes/sweats* 32 (57.1) Digestive System GI disorders 8 (14.3) Metabolic and Nutritional Disorders Edema 8 (14.3) Nervous System Libido decreased* 3 (5.4) Respiratory System Respiratory disorder 6 (10.7) Urogenital System Urinary disorder 7 (12.5) Impotence* 3 (5.4) Testicular atrophy* 3 (5.4) * Due to the expected physiologic effect of decreased testosterone levels.
In this same study, the following adverse reactions were reported in less than 5% of the patients on LUPRON DEPOT 7.5 mg for 1-month administration. Body As A Whole - asthenia, cellulitis, fever, headache, injection site reaction, neoplasm Cardiovascular System - angina, congestive heart failure Digestive System - anorexia, dysphagia, eructation, peptic ulcer Blood and Lymphatic System - ecchymosis Musculoskeletal System - myalgia Nervous System - agitation, insomnia/sleep disorders, neuromuscular disorders Respiratory System - emphysema, hemoptysis, lung edema, sputum increased Skin and Appendages - hair disorder, skin reaction Urogenital System - balanitis, breast enlargement, urinary tract infe… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Drug/Laboratory Test Interactions Administration of LUPRON DEPOT in therapeutic doses results in suppression of the pituitary-gonadal system. Normal function is usually restored within three months after treatment is discontinued. Due to the suppression of the pituitary-gonadal system by LUPRON DEPOT, diagnostic tests of pituitary gonadotropic and gonadal functions conducted during treatment and up to three months after discontinuation of LUPRON DEPOT may be affected.
🔄 Drug / Laboratory Test Interactions ▾
7.1Drug/Laboratory Test Interactions Administration of LUPRON DEPOT in therapeutic doses results in suppression of the pituitary-gonadal system. Normal function is usually restored within three months after treatment is discontinued. Due to the suppression of the pituitary-gonadal system by LUPRON DEPOT, diagnostic tests of pituitary gonadotropic and gonadal functions conducted during treatment and up to three months after discontinuation of LUPRON DEPOT may be affected.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and males of reproductive potential: LUPRON DEPOT may impair fertility. Counsel patients on pregnancy planning and prevention. ( 8.3 ) Pediatric: These LUPRON DEPOT formulations are not indicated for use in children.
See the LUPRON DEPOT PED ® prescribing information for the use of leuprolide acetate in children with central precocious puberty. Geriatric: This label reflects clinical trials for LUPRON DEPOT in prostate cancer in which the majority of the subjects studied were at least 65 years of age.
8.1Pregnancy Risk Summary Based on findings in animal studies and mechanism of action, LUPRON DEPOT may cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )] . There are no available data in pregnant women to inform the drug-associated risk. In animal developmental and reproductive toxicology studies, administration of a monthly formulation of leuprolide acetate on day 6 of pregnancy (sustained exposure was expected throughout the period of organogenesis) caused adverse embryo-fetal toxicity in animals at doses less than the human dose based on body surface area using an estimated daily dose (see data) .
Advise pregnant patients and females of reproductive potential of the potential risk to the fetus. Data Animal Data Major fetal malformations were observed in developmental and reproductive toxicology studies in rabbits after a single administration of the monthly formulation of leuprolide acetate on day 6 of pregnancy at doses of 0.00024, 0.0024, and 0.024 mg/kg (approximately 1/1600 to 1/16 the human dose based on body surface area using an estimated daily dose in animals and humans). Since a depot formulation was utilized in the study, a sustained exposure to leuprolide was expected throughout the period of organogenesis and to the end of gestation.
Similar studies in rats did not demonstrate an increase in fetal malformations, however, there was increased fetal mortality and decreased fetal weights with the two higher doses of the monthly formulation of leuprolide acetate in rabbits and with the highest dose (0.024 mg/kg) in rats.
8.2Lactation The safety and efficacy of LUPRON DEPOT have not been established in females. There is no information regarding the presence of LUPRON DEPOT in human milk, the effects on the breastfed child, or the effects on milk production. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in a breastfed child from LUPRON DEPOT, a decision should be made to discontinue breastfeeding or discontinue the drug, taking into account the importance of the drug to the mother.
8.3Females and Males of Reproductive Potential Infertility Males Based on findings in animals and mechanism of action, LUPRON DEPOT may impair fertility in males of reproductive potential [see Nonclinical Toxicology ( 13.1 )] .
8.4Pediatric Use See LUPRON DEPOT-PED ® (leuprolide acetate for depot suspension) labeling for the safety and effectiveness in children with central precocious puberty.
8.5Geriatric Use In the clinical trials for LUPRON DEPOT in prostate cancer 80% of the subjects studied were at least 65 years of age. Therefore, the labeling reflects the efficacy and safety of LUPRON DEPOT in this population.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings in animal studies and mechanism of action, LUPRON DEPOT may cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )] . There are no available data in pregnant women to inform the drug-associated risk. In animal developmental and reproductive toxicology studies, administration of a monthly formulation of leuprolide acetate on day 6 of pregnancy (sustained exposure was expected throughout the period of organogenesis) caused adverse embryo-fetal toxicity in animals at doses less than the human dose based on body surface area using an estimated daily dose (see data) .
Advise pregnant patients and females of reproductive potential of the potential risk to the fetus. Data Animal Data Major fetal malformations were observed in developmental and reproductive toxicology studies in rabbits after a single administration of the monthly formulation of leuprolide acetate on day 6 of pregnancy at doses of 0.00024, 0.0024, and 0.024 mg/kg (approximately 1/1600 to 1/16 the human dose based on body surface area using an estimated daily dose in animals and humans). Since a depot formulation was utilized in the study, a sustained exposure to leuprolide was expected throughout the period of organogenesis and to the end of gestation.
Similar studies in rats did not demonstrate an increase in fetal malformations, however, there was increased fetal mortality and decreased fetal weights with the two higher doses of the monthly formulation of leuprolide acetate in rabbits and with the highest dose (0.024 mg/kg) in rats.
🧒 Pediatric Use ▾
8.4Pediatric Use See LUPRON DEPOT-PED ® (leuprolide acetate for depot suspension) labeling for the safety and effectiveness in children with central precocious puberty.
🧓 Geriatric Use ▾
8.5Geriatric Use In the clinical trials for LUPRON DEPOT in prostate cancer 80% of the subjects studied were at least 65 years of age. Therefore, the labeling reflects the efficacy and safety of LUPRON DEPOT in this population.
🆘 Overdosage ▾
10 OVERDOSAGE There is no experience of overdosage in clinical trials. In rats, a single subcutaneous dose of 100 mg/kg (approximately 4,000 times the estimated daily human dose based on body surface area), resulted in dyspnea, decreased activity, and excessive scratching. In early clinical trials with daily subcutaneous leuprolide acetate, doses as high as 20 mg/day for up to two years caused no adverse effects differing from those observed with the 1 mg/day dose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Leuprolide acetate, a GnRH agonist, acts as an inhibitor of gonadotropin secretion. Animal studies indicate that following an initial stimulation, continuous administration of leuprolide acetate results in suppression of ovarian and testicular steroidogenesis. This effect was reversible upon discontinuation of drug therapy.
Administration of leuprolide acetate has resulted in inhibition of the growth of certain hormone dependent tumors (prostatic tumors in Noble and Dunning male rats and DMBA-induced mammary tumors in female rats) as well as atrophy of the reproductive organs.
12.2Pharmacodynamics In humans, administration of leuprolide acetate results in an initial increase in circulating concentrations of luteinizing hormone (LH) and follicle stimulating hormone (FSH), leading to a transient increase in concentrations of the gonadal steroids (testosterone and dihydrotestosterone in males, and estrone and estradiol in premenopausal females). However, continuous administration of leuprolide acetate results in decreased concentrations of LH and FSH. In males, testosterone is reduced to castrate concentrations.
In premenopausal females, estrogens are reduced to postmenopausal concentrations. These decreases occur within two to four weeks after initiation of treatment, and castrate concentrations of testosterone in prostatic cancer patients have been demonstrated for more than five years. Leuprolide acetate is not active when given orally.
12.3Pharmacokinetics Absorption LUPRON DEPOT 7.5 mg for 1-Month Administration Following a single injection of LUPRON DEPOT 7.5 mg for 1-month administration to patients, mean plasma measured concentrations were 20 ng/mL at 4 hours and 0.36 ng/mL at 4 weeks. However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. LUPRON DEPOT 22.5 mg for 3-Month Administration Following a single injection of LUPRON DEPOT 22.5 mg for 3-month administration in patients, mean peak plasma concentrations were 48.9 ng/mL at 4 hours and then declined to 0.67 ng/mL at 12 weeks.
Leuprolide appeared to be released at a constant rate following the onset of steady-state concentrations during the third week after dosing, providing steady plasma concentrations through the 12-week dosing interval. However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. The initial burst, followed by a decline to a steady-state concentration, was similar to the release pattern seen with the monthly formulation.
LUPRON DEPOT 30 mg for 4-Month Administration Following a single injection of LUPRON DEPOT 30 mg for 4-month administration in sixteen orchiectomized prostate cancer patients, mean plasma concentrations were 59.3 ng/mL at 4 hours and then declined to 0.30 ng/mL at 16 weeks. Mean plasma concentrations from weeks 3.5 to 16 was 0.44 ± 0.20 ng/mL (range: 0.20-1.06). Leuprolide appeared to be released at a constant rate following the onset of steady-state concentrations during the fourth week after dosing, providing steady plasma concentrations throughout the 16-week dosing interval.
However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. The initial burst, followed by a decline to a steady-state concentration, was similar to the release pattern seen with the other depot formulations. LUPRON DEPOT 45 mg for 6-Month Administration Following a single injection of LUPRON DEPOT 45 mg for 6-month administration in 26 prostate cancer patients, mean peak plasma concentration of 6.7 ng/mL was observed at 2 hours and then declined to 0.07 ng/mL at 24 weeks.
Leuprolide appeared to be released continuously following the onset of steady-state concentrations during the third week after dosing providing steady plasma concentrations through the 24-week dosing interval. The initi… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Leuprolide acetate, a GnRH agonist, acts as an inhibitor of gonadotropin secretion. Animal studies indicate that following an initial stimulation, continuous administration of leuprolide acetate results in suppression of ovarian and testicular steroidogenesis. This effect was reversible upon discontinuation of drug therapy.
Administration of leuprolide acetate has resulted in inhibition of the growth of certain hormone dependent tumors (prostatic tumors in Noble and Dunning male rats and DMBA-induced mammary tumors in female rats) as well as atrophy of the reproductive organs.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each LUPRON DEPOT kit contains: one prefilled dual-chamber syringe containing needle with LuproLoc® safety device one plunger two alcohol swabs a complete prescribing information enclosure Strength Frequency of Administration Description NDC Number 7.5 mg Every month Single-dose prefilled dual-chamber syringe containing sterile white lyophilized microspheres of leuprolide acetate incorporated in a biodegradable lactic acid/glycolic acid copolymer to be mixed with 1 mL of accompanying clear, colorless diluent.
0074-3642-03 0074-3642-55 22.5 mg Every 3 months Single-dose prefilled dual-chamber syringe containing sterile white lyophilized microspheres of leuprolide acetate incorporated in a biodegradable lactic acid polymer to be mixed with 1.5 mL of accompanying clear, colorless diluent. 0074-3346-03 0074-3346-55 30 mg Every 4 months Single-dose prefilled dual-chamber syringe containing sterile white lyophilized microspheres of leuprolide acetate incorporated in a biodegradable lactic acid polymer to be mixed with 1.5 mL of accompanying clear, colorless diluent.
0074-3683-03 0074-3683-55 45 mg Every 6 months Single-dose prefilled dual-chamber syringe containing sterile white lyophilized microspheres of leuprolide acetate incorporated in a biodegradable lactic acid polymer to be mixed with 1.5 mL of accompanying clear, colorless diluent. 0074-3473-03 0074-3473-55 Store between 20° to 25°C (68° to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Leuprolide acetate is a synthetic nonapeptide analog of naturally occurring gonadotropin-releasing hormone (GnRH). The analog possesses greater potency than the natural hormone. The chemical name is 5-oxo-L-prolyl-L-histidyl-L-tryptophyl-L-seryl-L-tyrosyl-D-leucyl-L-leucyl-L-arginyl-N-ethyl-L-prolinamide acetate (salt) with the following structural formula: LUPRON DEPOT 7.5 mg for 1-month administration is available in a prefilled dual-chamber syringe containing sterile lyophilized microspheres which, when mixed with diluent, becomes a suspension intended as a monthly intramuscular injection.
The front chamber of LUPRON DEPOT 7.5 mg for 1-month administration prefilled dual-chamber syringe contains leuprolide acetate (7.5 mg), purified gelatin (1.3 mg), DL-lactic and glycolic acids copolymer (66.2 mg), and D-mannitol (13.2 mg). The second chamber of diluent contains carboxymethylcellulose sodium (5 mg), D-mannitol (50 mg), polysorbate 80 (1 mg), water for injection, USP, and glacial acetic acid, USP to control pH. LUPRON DEPOT 22.5 mg for 3-month administration is available in a prefilled dual-chamber syringe containing sterile lyophilized microspheres which, when mixed with diluent, become a suspension intended as an intramuscular injection to be given ONCE EVERY 12 WEEKS .
The front chamber of LUPRON DEPOT 22.5 mg for 3-month administration prefilled dual-chamber syringe contains leuprolide acetate (22.5 mg), polylactic acid (198.6 mg) and D-mannitol (38.9 mg). The second chamber of diluent contains carboxymethylcellulose sodium (7.5 mg), D-mannitol (75.0 mg), polysorbate 80 (1.5 mg), water for injection, USP, and glacial acetic acid, USP to control pH. LUPRON DEPOT 30 mg for 4-month administration is available in a prefilled dual-chamber syringe containing sterile lyophilized microspheres which, when mixed with diluent, become a suspension intended as an intramuscular injection to be given ONCE EVERY 16 WEEKS .
The front chamber of LUPRON DEPOT 30 mg for 4-month administration prefilled dual-chamber syringe contains leuprolide acetate (30 mg), polylactic acid (264.8 mg) and D-mannitol (51.9 mg). The second chamber of diluent contains carboxymethylcellulose sodium (7.5 mg), D-mannitol (75.0 mg), polysorbate 80 (1.5 mg), water for injection, USP, and glacial acetic acid, USP to control pH. LUPRON DEPOT 45 mg for 6-month administration is available in a prefilled dual-chamber syringe containing sterile lyophilized microspheres which, when mixed with diluent, become a suspension intended as an intramuscular injection to be given ONCE EVERY 24 WEEKS .
The front chamber of LUPRON DEPOT 45 mg for 6-month administration prefilled dual-chamber syringe contains leuprolide acetate (45 mg), polylactic acid (169.9 mg), D-mannitol (39.7 mg), and stearic acid (10.1 mg). The second chamber of diluent contains carboxymethylcellulose sodium (7.5 mg), D-mannitol (75.0 mg), polysorbate 80 (1.5 mg), water for injection, USP, and glacial acetic acid, USP to control pH. Chemical structure of leuprolide acetate
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Inform patients that if they have experienced hypersensitivity with other GnRH agonist drugs like LUPRON DEPOT, LUPRON DEPOT is contraindicated [see Contraindications ( 4 )]. Tumor Flare Inform patients that LUPRON DEPOT can cause tumor flare during the first weeks of treatment. Inform patients that the increase in testosterone can cause an increase in urinary symptoms or pain.
Advise patients to contact their healthcare provider if bone pain, neuropathy, hematuria, bladder outlet obstruction, spinal cord compression, or new or worsened symptoms occur after beginning LUPRON DEPOT treatment [see Warnings and Precautions ( 5.1 )]. Metabolic Syndrome Advise patients that there is an increased risk of metabolic changes such as hyperglycemia, diabetes, hyperlipidemia, and non-alcoholic fatty liver disease with LUPRON DEPOT therapy. Inform patients that periodic monitoring for metabolic changes is required when being treated with LUPRON DEPOT [see Warnings and Precautions ( 5.2 )].
Cardiovascular Disease Inform patients that there is an increased risk of myocardial infarction, sudden cardiac death, and stroke with LUPRON DEPOT treatment. Advise patients to immediately report signs and symptoms associated with these events to their healthcare provider for evaluation [see Warnings and Precautions ( 5.3 )]. Severe Cutaneous Adverse Reactions Inform patients that severe cutaneous adverse reactions (SCARs), including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and acute generalized exanthematous pustulosis (AGEP), which may be life threatening or fatal, may occur during treatment with LUPRON DEPOT.
Advise patients to contact their healthcare provider or seek medical attention right away if they experience signs or symptoms of SCARs [see Warnings and Precautions ( 5.6 )] . Injection Site Reactions Inform patients and caregivers that injection site reactions such as pain, induration, abscess, and necrosis may occur with LUPRON DEPOT. Advise patients to contact their healthcare provider if they experience injection site reactions [see Adverse Reactions ( 6.4 , 6.5 )].
Urogenital Disorders Advise patients that LUPRON DEPOT may cause impotence [see Adverse Reactions ( 6 )] . Infertility Inform patients that LUPRON DEPOT may cause infertility [see Use in Specific Populations ( 8.3 )]. Continuation of LUPRON DEPOT Treatment Inform patients that LUPRON DEPOT is usually continued, often with additional medication, after the development of non-metastatic and metastatic castration-resistant prostate cancer [see Dosage and Administration ( 2.1 )].
Manufactured for AbbVie Inc. North Chicago, IL 60064 by Takeda Pharmaceutical Company Limited Osaka, Japan 540-8645 LUPRON DEPOT and its design are trademarks of AbbVie Endocrine Inc. © 2026 AbbVie. All rights reserved.
20098274
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption LUPRON DEPOT 7.5 mg for 1-Month Administration Following a single injection of LUPRON DEPOT 7.5 mg for 1-month administration to patients, mean plasma measured concentrations were 20 ng/mL at 4 hours and 0.36 ng/mL at 4 weeks. However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. LUPRON DEPOT 22.5 mg for 3-Month Administration Following a single injection of LUPRON DEPOT 22.5 mg for 3-month administration in patients, mean peak plasma concentrations were 48.9 ng/mL at 4 hours and then declined to 0.67 ng/mL at 12 weeks.
Leuprolide appeared to be released at a constant rate following the onset of steady-state concentrations during the third week after dosing, providing steady plasma concentrations through the 12-week dosing interval. However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. The initial burst, followed by a decline to a steady-state concentration, was similar to the release pattern seen with the monthly formulation.
LUPRON DEPOT 30 mg for 4-Month Administration Following a single injection of LUPRON DEPOT 30 mg for 4-month administration in sixteen orchiectomized prostate cancer patients, mean plasma concentrations were 59.3 ng/mL at 4 hours and then declined to 0.30 ng/mL at 16 weeks. Mean plasma concentrations from weeks 3.5 to 16 was 0.44 ± 0.20 ng/mL (range: 0.20-1.06). Leuprolide appeared to be released at a constant rate following the onset of steady-state concentrations during the fourth week after dosing, providing steady plasma concentrations throughout the 16-week dosing interval.
However, intact leuprolide and an inactive major metabolite could not be distinguished by the assay which was employed in the study. The initial burst, followed by a decline to a steady-state concentration, was similar to the release pattern seen with the other depot formulations. LUPRON DEPOT 45 mg for 6-Month Administration Following a single injection of LUPRON DEPOT 45 mg for 6-month administration in 26 prostate cancer patients, mean peak plasma concentration of 6.7 ng/mL was observed at 2 hours and then declined to 0.07 ng/mL at 24 weeks.
Leuprolide appeared to be released continuously following the onset of steady-state concentrations during the third week after dosing providing steady plasma concentrations through the 24-week dosing interval. The initial burst, followed by a decline to a steady-state concentration, was similar to the release pattern seen with the other depot formulations. In this study, mean plasma concentration-time profiles were similar after the first and second dose.
Distribution The mean steady-state volume of distribution of leuprolide following intravenous bolus administration to healthy male volunteers was 27 L. In vitro binding to human plasma proteins ranged from 43% to 49%. Elimination The mean systemic clearance of leuprolide following intravenous bolus administration to healthy male volunteers was
7.6L/h, and terminal elimination half-life was approximately 3 hours based on a two compartment model. Following administration of LUPRON DEPOT 3.75 mg to 3 patients, less than 5% of the dose was recovered as parent and M-I metabolite in the urine.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In humans, administration of leuprolide acetate results in an initial increase in circulating concentrations of luteinizing hormone (LH) and follicle stimulating hormone (FSH), leading to a transient increase in concentrations of the gonadal steroids (testosterone and dihydrotestosterone in males, and estrone and estradiol in premenopausal females). However, continuous administration of leuprolide acetate results in decreased concentrations of LH and FSH. In males, testosterone is reduced to castrate concentrations.
In premenopausal females, estrogens are reduced to postmenopausal concentrations. These decreases occur within two to four weeks after initiation of treatment, and castrate concentrations of testosterone in prostatic cancer patients have been demonstrated for more than five years. Leuprolide acetate is not active when given orally.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Figure 8 Figure 9 Figure 10 Figure 11
14.1LUPRON DEPOT 7.5 mg for 1-Month Administration In an open-label, non-comparative, multicenter clinical study of LUPRON DEPOT 7.5 mg for 1-month administration, 56 patients with stage D 2 prostatic adenocarcinoma and no prior systemic treatment were enrolled. The objectives were to determine if a 7.5 mg depot formulation of leuprolide injected once every 4 weeks would reduce and maintain serum testosterone to castrate range (≤50 ng/dL), to evaluate objective clinical response, and to assess the safety of the formulation.
During the initial 24 weeks, serum testosterone was measured weekly, biweekly, or every four weeks and objective tumor response assessments were performed at Weeks 12 and 24. Once the patient completed the initial 24-week treatment phase, treatment continued at the investigator’s discretion. Data from the initial 24-week treatment phase are summarized in this section.
In the majority of patients, serum testosterone increased by 50% or more above baseline during the first week of treatment. Serum testosterone suppressed to the castrate range within 30 days of the initial depot injection in 94% (51/54) of patients for whom testosterone suppression was achieved (2 patients withdrew prior to onset of suppression) and within 66 days in all 54 patients. Mean serum testosterone suppressed to castrate level by Week 3.
The median dosing interval between injections was 28 days. One escape from suppression (2 consecutive testosterone values greater than 50 ng/dL after achieving castrate level) was noted at Week 18, associated with a substantial dosing delay. In this patient, serum testosterone returned to the castrate range at the next monthly measurement.
Serum testosterone was minimally above the castrate range on a single occasion for 4 other patients. No clinical significance was attributed to these rises in testosterone. Figure 8.
LUPRON DEPOT 7.5 mg for 1-Month Administration Mean Serum Testosterone Concentrations Secondary efficacy endpoints evaluated included objective tumor response, assessed by clinical evaluations of tumor burden (complete response, partial response, objectively stable, and progression), as well as changes in local disease status, assessed by digital rectal examination, and changes in prostatic acid phosphatase (PAP). These evaluations were performed at Weeks 12 and 24. The objective tumor response analysis showed a “no progression” (i.e.
Complete or partial response, or stable disease) in 77% (40/52) of patients at Week 12, and in 84% (42/50) of patients at Week 24. Local disease improved or remained stable in all (42) patients evaluated at Week 12 and in 98% (41/42) of patients elevated at Week 24. PAP normalized or decreased at Week 12 and/or 24 in the majority of patients with elevated baseline PAP.
Periodic monitoring of serum testosterone and PSA levels is recommended, especially if the anticipated clinical or biochemical response to treatment has not been achieved. It should be noted that results of testosterone determinations are dependent on assay methodology. It is advisable to be aware of the type and precision of the assay methodology to make appropriate clinical and therapeutic decisions.
14.2LUPRON DEPOT 22.5 mg for 3-Month Administration In clinical studies, serum testosterone was suppressed to castrate within 30 days in 87 of 92 (95%) patients and within an additional two weeks in three patients. Two patients did not suppress for 15 and 28 weeks, respectively. Suppression was maintained in all of these patients with the exception of transient minimal testosterone elevations in one of them, and in another an increase in serum testosterone to above the castrate range was recorded during the 12 hour observation period after a subsequent injection.
This represents stimulation of gonadotropin secretion. Figure 9. LUPRON DEPOT 22.5 mg for 3-Month Administration Mean Serum Testosterone Concentrations An 85% rate of “no pro… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year carcinogenicity studies were conducted with leuprolide acetate in rats and mice. In rats, a dose-related increase of benign pituitary hyperplasia and benign pituitary adenomas was noted at 24 months when the drug was administered subcutaneously at daily doses (0.6 to 4 mg/kg). There was a significant but not dose-related increase of pancreatic islet-cell adenomas in females and of testicular interstitial cell adenomas in males (highest incidence in the low dose group).
In mice, no leuprolide acetate-induced tumors or pituitary abnormalities were observed at a dose as high as 60 mg/kg for two years. Patients have been treated with leuprolide acetate for up to three years with doses as high as 10 mg/day and for two years with doses as high as 20 mg/day without demonstrable pituitary abnormalities. Genotoxicity studies were conducted with leuprolide acetate using bacterial and mammalian systems.
These studies provided no evidence of mutagenic effects or chromosomal aberrations. Leuprolide may reduce male and female fertility. Administration of leuprolide acetate to male and female rats at dose of 0.024, 0.24, and 2.4 mg/kg as monthly depot formulation for up to 3 months (approximately as low as 1/30 of the human dose based on body surface area using an estimated daily dose in animals and humans) caused atrophy of the reproductive organs, and suppression of reproductive function.
These changes were reversible upon cessation of treatment.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year carcinogenicity studies were conducted with leuprolide acetate in rats and mice. In rats, a dose-related increase of benign pituitary hyperplasia and benign pituitary adenomas was noted at 24 months when the drug was administered subcutaneously at daily doses (0.6 to 4 mg/kg). There was a significant but not dose-related increase of pancreatic islet-cell adenomas in females and of testicular interstitial cell adenomas in males (highest incidence in the low dose group).
In mice, no leuprolide acetate-induced tumors or pituitary abnormalities were observed at a dose as high as 60 mg/kg for two years. Patients have been treated with leuprolide acetate for up to three years with doses as high as 10 mg/day and for two years with doses as high as 20 mg/day without demonstrable pituitary abnormalities. Genotoxicity studies were conducted with leuprolide acetate using bacterial and mammalian systems.
These studies provided no evidence of mutagenic effects or chromosomal aberrations. Leuprolide may reduce male and female fertility. Administration of leuprolide acetate to male and female rats at dose of 0.024, 0.24, and 2.4 mg/kg as monthly depot formulation for up to 3 months (approximately as low as 1/30 of the human dose based on body surface area using an estimated daily dose in animals and humans) caused atrophy of the reproductive organs, and suppression of reproductive function.
These changes were reversible upon cessation of treatment.
📚 References ▾
15 REFERENCES 1. “OSHA Hazardous Drugs.” OSHA. http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Recent Major Changes ▾
Dosage and Administration ( 2 ) 8/2025 Dosage Forms and Strengths ( 3 ) 8/2025
📄 Package Label / Principal Display Panel ▾
NDC 0074-3473-03 FOR ADULT USE 45 mg for 6-month administration Single Dose Administration Kit with prefilled dual-chamber syringe. Lupron Depot ® (Leuprolide Acetate for Depot Suspension) 45 mg for 6-month administration FOR INTRAMUSCULAR INJECTION The front chamber contains : leuprolide acetate 45 mg • polylactic acid 169.9 mg • D-mannitol 39.7 mg • stearic acid 10.1 mg The second chamber contains : carboxymethylcellulose sodium 7.5 mg • D-mannitol 75.0 mg • polysorbate 80 1.5 mg • water for injection, USP, and glacial acetic acid, USP to control pH Rx only NDC 0074-3473-03 FOR ADULT USE 45 mg for 6-month administration Single Dose Administration Kit with prefilled dual-chamber syringe.
LupronDepot® (Leuprolide Acetate for Depot Suspension) 45 mg for 6-month administration FOR INTRAMUSCULAR INJECTION The front chamber contains: leuprolide acetate 45 mg • polylactic acid 169.9 mg • D-mannitol 39.7 mg • stearic acid 10.1 mg The second chamber contains: carboxymethylcellulose sodium 7.5 mg • D-mannitol 75.0 mg • polysorbate 80 1.5 mg • water for injection, USP, and glacial acetic acid, USP to control pH Rx only
NDC 0074-3346-03 FOR ADULT USE 22.5 mg for 3-month Single Dose Administration Kit with prefilled dual-chamber syringe. Lupron Depot ® (Leuprolide Acetate for Depot Suspension) 22.5 mg for 3-month administration FOR INTRAMUSCULAR INJECTION The front chamber contains : leuprolide acetate 22.5 mg • polylactic acid 198.6 mg • D-mannitol 38.9 mg The second chamber contains : carboxymethylcellulose sodium 7.5 mg • D-mannitol 75.0 mg • polysorbate 80 1.5 mg • water for injection, USP, and glacial acetic acid, USP to control pH Rx only NDC 0074-3346-03 FOR ADULT USE 22.5 mg for 3-month Single Dose Administration Kit with prefilled dual-chamber syringe.
LupronDepot® (Leuprolide Acetate for Depot Suspension) 22.5 mg for 3-month administration FOR INTRAMUSCULAR INJECTION The front chamber contains: leuprolide acetate 22.5 mg • polylactic acid 198.6 mg • D-mannitol 38.9 mg The second chamber contains: carboxymethylcellulose sodium 7.5 mg • D-mannitol 75.0 mg • polysorbate 80 1.5 mg • water for injection, USP, and glacial acetic acid, USP to control pH Rx only
NDC 0074-3683-03 FOR ADULT USE 30 mg for 4-month administration Single Dose Administration Kit with prefilled dual-chamber syringe. Lupron Depot ® (Leuprolide Acetate for Depot Suspension) 30 mg for 4-month administration FOR INTRAMUSCULAR INJECTION The front chamber contains : leuprolide acetate 30 mg • polylactic acid 264.8 mg • D-mannitol 51.9 mg The second chamber contains : carboxymethylcellulose sodium 7.5 mg • D-mannitol 75.0 mg • polysorbate 80 1.5 mg • water for injection, USP, and glacial acetic acid, USP to control pH Rx only NDC 0074-3683-03 FOR ADULT USE 30 mg for 4-month administration Single Dose Administration Kit with prefilled dual-chamber syringe.
LupronDepot® (Leuprolide Acetate for Depot Suspension) 30 mg for 4-month administration FOR INTRAMUSCULAR INJECTION The front chamber contains: leuprolide acetate 30 mg • polylactic acid 264.8 mg • D-mannitol 51.9 mg The second chamber contains: carboxymethylcellulose sodium 7.5 mg • D-mannitol 75.0 mg • polysorbate 80 1.5 mg • water for injection, USP, and glacial acetic acid, USP to control pH Rx only
NDC 0074–3642–03 FOR ADULT USE 7.5 mg for 1–month administration Single Dose Administration Kit with prefilled dual-chamber syringe. Lupron Depot ® (Leuprolide Acetate for Depot Suspension) 7.5 mg for 1–month administration FOR INTRAMUSCULAR INJECTION The front chamber contains : leuprolide acetate 7.5 mg • purified gelatin 1.3 mg • DL-lactic and glycolic acids copolymer 66.2 mg • D-mannitol 13.2 mg The second chamber contains : carboxymethylcellulose sodium 5 mg • D-mannitol 50 mg • polysorbate 80 1 mg • water for injection, USP, and glacial acetic acid, USP to control pH Rx only NDC 0074–3642–03 FOR ADULT USE 7.5 mg for 1–month administration Single Dose Administration Kit with prefilled dual-chamber syringe.
Lu… [Excerpted — this section continues on DailyMed.]
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |