
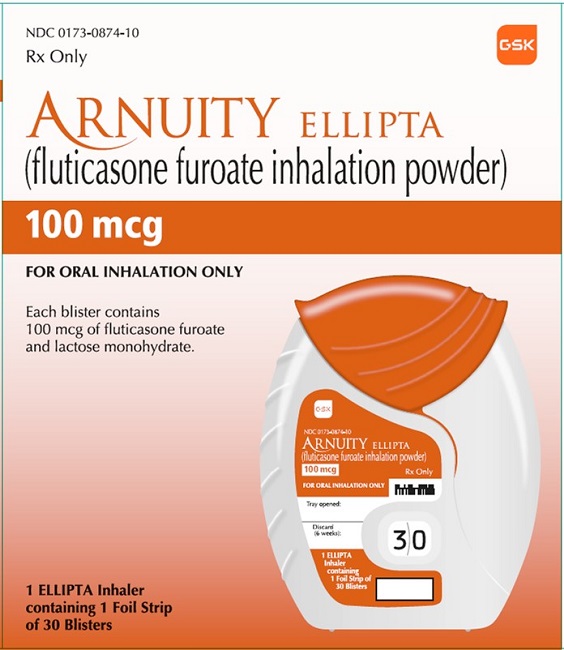
Arnuity Ellipta fluticasone furoate 100 ug Powder — NDC 0173-0874-10 (Billing 00173-0874-10)
This is a package of Arnuity Ellipta fluticasone furoate 100 ug Powder from GlaxoSmithKline LLC, marketed since Aug 2014 and currently FDA-listed; retail pharmacies pay about $6.65 per unit (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0173-0874-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0173 labeler · 0874 product · 10 package
- Package marketed since
- Aug 20, 2014
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0173087410 8
- Medicaid fills, this package
- 67,886 prescriptions in the last four reported quarters
- FDA record last changed
- Aug 20, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 072722
- GCN: 37007
- HICL (First Databank): 034756
- AHFS class code: 48:10.08.00
- RxCUI (RxNorm): 1547658
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. Inhalers and powders are for long-term asthma control, nasal sprays are for allergy or nasal symptoms, and skin products calm inflamed, itchy skin. Check...
- No. It does not relieve sudden breathing trouble. Use your rescue medicine as directed and call your doctor if episodes do not respond to it.
- Can I use my fluticasone inhaler for an asthma attack?
- Inhaled steroids can cause thrush, a yeast infection in the mouth and throat. Rinsing with water and spitting it out after each dose helps lower that risk.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Fluticasone furoate — tap one for details:
Fluticasone may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $6.647 | $199.40 / 30 powders |
| Medicaid paysCMS SDUD · 12 mo | $6.82 | $204.65 / 30 powders |
| Medicare drug plans payPart D · Q2 2026 | $6.68 | $200.50 / 30 powders |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00173-0874-10 You're viewing this Main listing | 1 INHALER in 1 CARTON / 30 POWDER in 1 INHALER | $6.65 / ea | $199.40 | 2014-08-20 | — | Active |
| 00173-0874-14 0173-0874-14 | 1 INHALER in 1 CARTON / 14 POWDER in 1 INHALER | $6.65 / ea | $93.09 | 2014-08-20 | — | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($6.65 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Arnuity Ellipta fluticasone furoate 100 ug Powder?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fluticasone Furoate Ellipta 100 ug 66993-0167-97 | Prasco | 1 inhaler | $4.284 | — | Availability likely | save 36% |
| Arnuity Ellipta 100 ugthis 00173-0874-10 | GlaxoSmithKline | 1 inhaler | $6.647 | — | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Code | What it grants | Expires |
|---|---|---|
| M-290 | New indication / labeling change (3-year) | Mar 1, 2026 |
Is there a generic version of ARNUITY ELLIPTA 100 MCG INH?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Fluticasone inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from GlaxoSmithKline LLC labeler code 00173
- LAMICTAL ODT lamotrigine Kit NDC 0173-0780-00
- Lamictal XR lamotrigine 250 mg Tablet, Film Coated, Extended Release NDC 0173-0781-00
- LAMICTAL lamotrigine Kit NDC 0173-0817-28
- Breo Ellipta fluticasone furoate and vilanterol trifenatate 100 ug; 25 ug Powder NDC 0173-0859-10
- Anoro Ellipta umeclidinium bromide and vilanterol trifenatate 62.5 ug; 25 ug Powder NDC 0173-0869-06
- Incruse Ellipta umeclidinium 62.5 ug Aerosol, Powder NDC 0173-0873-06
- Arnuity Ellipta fluticasone furoate 200 ug Powder NDC 0173-0876-10
- Nucala mepolizumab 100 mg/mL Injection, Powder, For Solution NDC 0173-0881-01
- Breo Ellipta fluticasone furoate and vilanterol trifenatate 200 ug; 25 ug Powder NDC 0173-0882-10
- Trelegy Ellipta fluticasone furoate, umeclidinium bromide and vilanterol trifenatate 100 ug; 62.5 ug; 25 ug Powder NDC 0173-0887-10
- Arnuity Ellipta fluticasone furoate 50 ug Powder NDC 0173-0888-10
- Krintafel tafenoquine succinate 150 mg Tablet, Film Coated NDC 0173-0889-13
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ARNUITY ELLIPTA is indicated for the maintenance treatment of asthma in adult and pediatric patients aged 5 years and older. Limitations of Use ARNUITY ELLIPTA is NOT indicated for the relief of acute bronchospasm. ARNUITY ELLIPTA is an inhaled corticosteroid indicated for the maintenance treatment of asthma in adult and pediatric patients aged 5 years and older.
( 1 ) Limitations of Use: Not indicated for relief of acute bronchospasm. ( 1 , 5.2 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • For oral inhalation only. ( 2.1 ) • Maintenance treatment of asthma in adult and pediatric patients aged 12 years and older: The starting dosage, 1 actuation of ARNUITY ELLIPTA 100 mcg or ARNUITY ELLIPTA 200 mcg once daily, is based on prior asthma therapy and disease severity. ( 2.2 ) • Maintenance treatment of asthma in pediatric patients aged 5 to 11 years: 1 actuation of ARNUITY ELLIPTA 50 mcg once daily. ( 2.2 )
2.1Administration • Administer 1 actuation of ARNUITY ELLIPTA once daily by oral inhalation. • After inhalation, the patient should rinse his/her mouth with water without swallowing to help reduce the risk of oropharyngeal candidiasis. • ARNUITY ELLIPTA should be used at the same time every day. Do not use ARNUITY ELLIPTA more than 1 time every 24 hours. • The maximum benefit may not be achieved for up to 2 weeks or longer after starting treatment. Individual patients may experience a variable time to onset and degree of symptom relief.
No dosage adjustment is required for geriatric patients, patients with renal impairment, or patients with mild hepatic impairment [see Clinical Pharmacology ( 12.3 )] .
2.2Recommended Dosage Adult and Pediatric Patients Aged 12 Years and Older The recommended starting dosage for adult and pediatric patients aged 12 years and older not on an inhaled corticosteroid (ICS) is fluticasone furoate 100 mcg (1 actuation of ARNUITY ELLIPTA 100 mcg) once daily by oral inhalation. • For other adult and pediatric patients aged 12 years and older, the recommended starting dosage should be based on previous asthma drug therapy and disease severity. • For adult and pediatric patients aged 12 years and older who do not respond to ARNUITY ELLIPTA 100 mcg after 2 weeks of therapy, replacement with ARNUITY ELLIPTA 200 mcg may provide additional asthma control. • The maximum recommended dosage in adult and pediatric patients aged 12 years and older is ARNUITY ELLIPTA 200 mcg once daily. • If asthma symptoms arise in the period between doses, an inhaled, short-acting beta 2 -agonist (rescue medicine, e.g., albuterol) should be used for immediate relief. • If a previously effective dosage regimen of ARNUITY ELLIPTA fails to provide adequate improvement in asthma control, the therapeutic regimen should be re-evaluated and additional therapeutic options (e.g., replacing the current strength of ARNUITY ELLIPTA with a higher strength, initiating an ICS and long-acting beta 2 -agonist [LABA] combination product, initiating oral corticosteroids) should be considered. • After asthma stability has been achieved, it is desirable to titrate to the lowest effective dosage to help reduce the possibility of adverse reactions.
Pediatric Patients Aged 5 to 11 Years The recommended dosage for pediatric patients aged 5 to 11 years is fluticasone furoate 50 mcg (1 actuation of ARNUITY ELLIPTA 50 mcg) once daily by oral inhalation [see Warnings and Precautions ( 5.10 )] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Inhalation powder: Plastic inhaler containing a foil blister strip of powder. Each blister contains fluticasone furoate 50 mcg, 100 mcg, or 200 mcg. Inhalation powder: A foil blister strip of powder formulation for oral inhalation. Each blister contains 50 mcg, 100 mcg, or 200 mcg of fluticasone furoate. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ARNUITY ELLIPTA is contraindicated in the following conditions: • Primary treatment of status asthmaticus or other acute episodes of asthma where intensive measures are required [see Warnings and Precautions ( 5.2 )] . • Severe hypersensitivity to milk proteins or demonstrated hypersensitivity to fluticasone furoate or any of the excipients [see Warnings and Precautions ( 5.8 ), Description ( 11 )] . • Primary treatment of status asthmaticus or acute episodes of asthma requiring intensive measures.
( 4 ) • Severe hypersensitivity to milk proteins ( 4 ) • Demonstrated hypersensitivity to any ingredients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Candida albicans infection of the mouth and pharynx may occur. Monitor patients periodically. Advise the patient to rinse his/her mouth with water without swallowing after inhalation to help reduce the risk.
( 5.1 ) • Do not use for relief of acute symptoms. Patients require immediate re-evaluation during rapidly deteriorating asthma. ( 5.2 ) • Potential worsening of infections (e.g., existing tuberculosis; fungal, bacterial, viral, or parasitic infections; ocular herpes simplex).
Use with caution in patients with these infections. More serious or even fatal course of chickenpox or measles can occur in susceptible patients. ( 5.3 ) • Risk of impaired adrenal function when transferring from systemic corticosteroids.
Wean patients slowly from systemic corticosteroids if transferring to ARNUITY ELLIPTA. ( 5.4 ) • Hypercorticism and adrenal suppression may occur with very high dosages or at the regular dosage in susceptible individuals. If such changes occur, discontinue ARNUITY ELLIPTA slowly.
( 5.5 ) • If paradoxical bronchospasm occurs, discontinue ARNUITY ELLIPTA and institute alternative therapy. ( 5.7 ) • Assess for decrease in bone mineral density initially and periodically thereafter. ( 5.9 ) • Monitor growth of pediatric patients.
( 5.10 ) • Glaucoma and cataracts may occur with long-term use of inhaled corticosteroids. Consider referral to an ophthalmologist in patients who develop ocular symptoms or use ARNUITY ELLIPTA long term. ( 5.11 )
5.1Oropharyngeal Candidiasis ARNUITY ELLIPTA contains fluticasone furoate, an ICS. Localized infections of the mouth and pharynx with Candida albicans have occurred in subjects treated with orally inhaled drug products containing fluticasone furoate. When such an infection develops, it should be treated with appropriate local or systemic (i.e., oral) antifungal therapy while treatment with ARNUITY ELLIPTA continues.
In some cases, therapy with ARNUITY ELLIPTA may need to be interrupted. Advise the patient to rinse his/her mouth with water without swallowing following administration of ARNUITY ELLIPTA to help reduce the risk of oropharyngeal candidiasis.
5.2Acute Asthma Episodes ARNUITY ELLIPTA is not indicated for the relief of acute symptoms, i.e., as rescue therapy for treatment of acute episodes of bronchospasm. ARNUITY ELLIPTA has not been studied in the relief of acute symptoms and extra doses should not be used for that purpose. Acute symptoms should be treated with an inhaled, short-acting beta 2 -agonist.
Instruct patients to contact their healthcare providers immediately if episodes of asthma not responsive to bronchodilators occur during the course of treatment with ARNUITY ELLIPTA. During such episodes, patients may require therapy with oral corticosteroids.
5.3Immunosuppression and Risk of Infections Persons who are using drugs that suppress the immune system, such as corticosteroids, including ARNUITY ELLIPTA, are more susceptible to infections than healthy individuals. Chickenpox and measles can have a more serious or even fatal course in susceptible children or adults using corticosteroids. In such children or adults who have not had these diseases or been properly immunized, particular care should be taken to avoid exposure.
How the dose, route, and duration of corticosteroid administration affect the risk of developing a disseminated infection is not known. The safety and effectiveness of ARNUITY ELLIPTA have not been established in pediatric patients less than 5 years of age and ARNUITY ELLIPTA is not indicated for use in this population. The contribution of the underlying disease and/or prior corticosteroid treatment to the risk is also not known.
If a patient is exposed to chickenpox, prophylaxis with varicella zoster immune globulin (VZIG) or pooled intravenous immunoglobulin (IVIG) may be indicated. If a patient is exposed to measles, prophylaxis with pooled intramuscular immunoglobulin (IG) may be indicated. (See the Prescribing In… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Systemic and local corticosteroid use may result in the following: • Oropharyngeal Candidiasis [see Warnings and Precautions ( 5.1 )] • Immunosuppression and Risk of Infections [see Warnings and Precautions ( 5.3 )] • Hypercorticism and Adrenal Suppression [see Warnings and Precautions ( 5.5 )] • Reduction in BMD [see Warnings and Precautions ( 5.9 )] • Growth Effects in Pediatrics [see Warnings and Precautions ( 5.10 )] • Glaucoma and Cataracts [see Warnings and Precautions ( 5.11 )] Most common adverse reactions reported in ≥5% of adult and pediatric subjects aged 12 years and older are nasopharyngitis, bronchitis, upper respiratory tract infection, and headache.
( 6.1 ) Most common adverse reactions reported in ≥3% of pediatric subjects aged 5 to 11 years are pharyngitis, bronchitis, and viral infection. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact GlaxoSmithKline at 1-888-825-5249 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adult and Pediatric Subjects Aged 12 Years and Older The safety of ARNUITY ELLIPTA was evaluated in 10 double-blind, parallel-group, controlled trials (7 with placebo) of 8 to 76 weeks’ duration that enrolled 6,219 subjects with asthma.
Doses of fluticasone furoate studied ranged from 25 to 800 mcg. ARNUITY ELLIPTA 100 mcg was studied in 1,663 subjects, and ARNUITY ELLIPTA 200 mcg was studied in 608 subjects. Subject ages ranged from 12 to 84 years, 65% were female, and 75% were Caucasian.
In these trials, the proportion of subjects who discontinued study treatment early due to adverse reactions was 2% for subjects treated with both ARNUITY ELLIPTA 100 mcg and ARNUITY ELLIPTA 200 mcg and ≤1% for placebo-treated subjects. Serious adverse events, whether considered drug-related or not by the investigators, that occurred in more than 1 subject and in a greater percentage of subjects treated with ARNUITY ELLIPTA than placebo included hypertension, abscess, breast cancer, traumatic limb amputation, subarachnoid hemorrhage, and intervertebral disc protrusion; all events occurred at rates ≤1%.
The incidence of adverse reactions associated with ARNUITY ELLIPTA 100 mcg is shown in Table 1 and is based on one 24-week trial (Trial 1) in adult and pediatric subjects aged 12 years and older with asthma. Table 1. Adverse Reactions with ARNUITY ELLIPTA 100 mcg with ≥3% Incidence and More Common than Placebo (Trial 1, Intent-to-Treat Population) Adverse Reaction ARNUITY ELLIPTA 100 mcg (n = 114) % Placebo (n = 115) % Nasopharyngitis 8 5 Bronchitis 7 6 Upper respiratory tract infection 6 5 Headache 6 4 Pharyngitis 4 3 Sinusitis 4 <1 Toothache 3 <1 Gastroenteritis viral 3 0 Oral candidiasis 3 0 Oropharyngeal candidiasis 3 0 Oropharyngeal pain 3 0 The incidence of adverse reactions associated with ARNUITY ELLIPTA 200 mcg is shown in Table 2 and is based on one 24-week trial (Trial 3) in adult and pediatric subjects aged 12 years and older with asthma.
This trial did not have a placebo arm. Table 2. Adverse Reactions with ARNUITY ELLIPTA 200 mcg with ≥3% Incidence (Trial 3, Safety Population) Adverse Reaction ARNUITY ELLIPTA 200 mcg (n = 119) % ARNUITY ELLIPTA 100 mcg (n = 119) % Nasopharyngitis 13 12 Headache 13 10 Bronchitis 7 12 Influenza 7 4 Upper respiratory tract infection 6 2 Sinusitis 4 7 Oropharyngeal pain 4 3 Pharyngitis 3 6 Back pain 3 3 Dysphonia 3 2 Oral candidiasis 3 <1 Procedural pain 3 <1 Rhinitis 3 <1 Throat irritation 3 <1 Abdominal pain 3 0 Cough 3 0 Adverse reactions observed in the other trials were consistent with those described in Tables 1 and 2.
Long-term Safety Long-term safety data are based on 2 trials in adult and pediatric subjects aged 12 years and older with asthm… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong cytochrome P450 3A4 inhibitors (e.g., ketoconazole): Use with caution. May cause systemic corticosteroid effects. ( 7.1 )
7.1Inhibitors of Cytochrome P450 3A4 Fluticasone furoate is a substrate of CYP3A4. Concomitant administration of the strong CYP3A4 inhibitor ketoconazole increases the systemic exposure to fluticasone furoate. Caution should be exercised when considering the coadministration of ARNUITY ELLIPTA with ketoconazole and other known strong CYP3A4 inhibitors [see Warnings and Precautions ( 5.6 ), Clinical Pharmacology ( 12.3 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic impairment: Fluticasone furoate systemic exposure may increase in patients with moderate or severe impairment. Monitor for systemic corticosteroid effects. ( 8.6 , 12.3 )
8.1Pregnancy Risk Summary There are insufficient data on the use of ARNUITY ELLIPTA in pregnant women to inform a drug-associated risk (see Clinical Considerations ). In animal reproduction studies, fluticasone furoate administered by inhalation to rats and rabbits during the period of organogenesis produced no fetal structural abnormalities. The highest fluticasone furoate doses in the rat and rabbit studies were 4 times and 1 time, respectively, the maximum recommended human daily inhalation dose (MRHDID) (see Data .).
The estimated risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryofetal Risk: In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal outcomes such as pre-eclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored and medication adjusted as necessary to maintain optimal control of asthma. Data Animal Data: Fluticasone Furoate : In 2 separate embryofetal developmental studies, pregnant rats and rabbits received fluticasone furoate during the period of organogenesis at doses up to approximately 4 and 1 times, respectively, the MRHDID (on a mcg/m 2 basis at maternal inhalation doses up to 91 and 8 mcg/kg/day, respectively). No evidence of structural abnormalities in fetuses was observed in either species.
In a perinatal and postnatal developmental study in rats, dams received fluticasone furoate during late gestation and lactation periods at doses up to approximately 1 time the MRHDID (on a mcg/m 2 basis at maternal inhalation doses up to 27 mcg/kg/day). No evidence of effects on offspring development was observed.
8.2Lactation Risk Summary There is no information available on the presence of fluticasone furoate in human milk, the effects on the breastfed child, or the effects on milk production. Low concentrations of other ICS have been detected in human milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for ARNUITY ELLIPTA and any potential adverse effects on the breastfed child from fluticasone furoate or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of ARNUITY ELLIPTA for maintenance treatment of asthma have been established in pediatric patients aged 5 years and older. Use of ARNUITY ELLIPTA for this indication in patients 12 years of age and older is supported by evidence from 4 adequate and well-controlled trials in adult and pediatric patients 12 years of age and older. Use of ARNUITY ELLIPTA for this indication in patients 5 to 11 years of age is supported by evidence from an adequate and well-controlled trial in patients 5 to 11 years of age [see Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 ), and Clinical Studies ( 14.2 )] .
The safety and effectiveness of ARNUITY ELLIPTA have not been established in pediatric patients less than 5 years of age. Effects on Growth Orally inhaled corticosteroids may cause a reduction in growth velocity when administered to pediatric patients. A reduction of growth velocity in these patients may occur as a result of poorly controlled asthma or from use of corticosteroids, including ICS.
The effects of long-term treatment of pediatric patients with ICS, including fluticasone furoate, on final adult height are not known. Controlled clinical trials have shown that ICS may cause a reduction in growth in children. In these trials, the mean reduction in g… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are insufficient data on the use of ARNUITY ELLIPTA in pregnant women to inform a drug-associated risk (see Clinical Considerations ). In animal reproduction studies, fluticasone furoate administered by inhalation to rats and rabbits during the period of organogenesis produced no fetal structural abnormalities. The highest fluticasone furoate doses in the rat and rabbit studies were 4 times and 1 time, respectively, the maximum recommended human daily inhalation dose (MRHDID) (see Data .).
The estimated risk of major birth defects and miscarriage for the indicated populations is unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryofetal Risk: In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal outcomes such as pre-eclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored and medication adjusted as necessary to maintain optimal control of asthma. Data Animal Data: Fluticasone Furoate : In 2 separate embryofetal developmental studies, pregnant rats and rabbits received fluticasone furoate during the period of organogenesis at doses up to approximately 4 and 1 times, respectively, the MRHDID (on a mcg/m 2 basis at maternal inhalation doses up to 91 and 8 mcg/kg/day, respectively). No evidence of structural abnormalities in fetuses was observed in either species.
In a perinatal and postnatal developmental study in rats, dams received fluticasone furoate during late gestation and lactation periods at doses up to approximately 1 time the MRHDID (on a mcg/m 2 basis at maternal inhalation doses up to 27 mcg/kg/day). No evidence of effects on offspring development was observed.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ARNUITY ELLIPTA for maintenance treatment of asthma have been established in pediatric patients aged 5 years and older. Use of ARNUITY ELLIPTA for this indication in patients 12 years of age and older is supported by evidence from 4 adequate and well-controlled trials in adult and pediatric patients 12 years of age and older. Use of ARNUITY ELLIPTA for this indication in patients 5 to 11 years of age is supported by evidence from an adequate and well-controlled trial in patients 5 to 11 years of age [see Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 ), and Clinical Studies ( 14.2 )] .
The safety and effectiveness of ARNUITY ELLIPTA have not been established in pediatric patients less than 5 years of age. Effects on Growth Orally inhaled corticosteroids may cause a reduction in growth velocity when administered to pediatric patients. A reduction of growth velocity in these patients may occur as a result of poorly controlled asthma or from use of corticosteroids, including ICS.
The effects of long-term treatment of pediatric patients with ICS, including fluticasone furoate, on final adult height are not known. Controlled clinical trials have shown that ICS may cause a reduction in growth in children. In these trials, the mean reduction in growth velocity was approximately 1 cm/year (range: 0.3 to 1.8 cm/year) and appears to be related to dose and duration of exposure.
This effect has been observed in the absence of laboratory evidence of HPA axis suppression, suggesting that growth velocity is a more sensitive indicator of systemic corticosteroid exposure in children than some commonly used tests of HPA axis function. The long-term effects of this reduction in growth velocity associated with orally inhaled corticosteroids, including the impact on final adult height, are unknown. The potential for “catch-up” growth following discontinuation of treatment with orally inhaled corticosteroids has not been adequately studied.
The growth of pediatric patients receiving orally inhaled corticosteroids, including ARNUITY ELLIPTA, should be monitored routinely (e.g., via stadiometry). The potential growth effects of prolonged treatment should be weighed against the clinical benefits obtained and the risks associated with alternative therapies. To minimize the systemic effects of orally inhaled corticosteroids, including ARNUITY ELLIPTA, each patient should be titrated to the lowest dose that effectively controls his/her symptoms.
A randomized, double-blind, parallel-group, multicenter, 1-year, placebo-controlled trial evaluated the effect of once-daily treatment with ARNUITY ELLIPTA 50 mcg on growth velocity assessed by stadiometry. The subjects were 457 prepubertal children (girls aged 5 to younger than 8 years and boys aged 5 to younger than 9 years). Mean growth velocity over the 52-week treatment period was lower in the subjects receiving ARNUITY ELLIPTA (5.90 cm/year) compared with placebo (6.06 cm/year).
The mean difference in growth velocity was -0.16 cm/year (95% CI: -0.46, 0.14) [see Warnings and Precautions ( 5.10 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use For the 4 confirmatory trials, 71 subjects were aged 65 years and older (56 of which were treated with ARNUITY ELLIPTA) and 5 were aged 75 years and older (1 of which was treated with ARNUITY ELLIPTA) [see Clinical Studies ( 14.2 )] . Based on available data, no adjustment of the dosage of ARNUITY ELLIPTA in geriatric patients is necessary, but greater sensitivity in some older individuals cannot be ruled out. Clinical trials of ARNUITY ELLIPTA did not include sufficient numbers of subjects aged 65 years and older to determine whether they respond differently from younger subjects.
Other reported clinical experience has not identified differences in responses between the elderly and younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE No human overdosage data have been reported for ARNUITY ELLIPTA. The potential for acute toxic corticosteroid effects following overdosage with ARNUITY ELLIPTA is low. Because of low systemic bioavailability (13.9%) and an absence of acute drug-related systemic findings in clinical trials, overdosage of fluticasone furoate is unlikely to require any treatment other than observation.
If used at excessive doses for prolonged periods, systemic effects such as hypercorticism may occur [see Warnings and Precautions ( 5.5 )] . Single- and repeat-dose trials of fluticasone furoate at doses of 50 to 4,000 mcg have been studied in human subjects. Decreases in mean serum cortisol were observed at dosages of 500 mcg or higher given once daily for 14 days.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Fluticasone furoate is a synthetic trifluorinated corticosteroid with anti‑inflammatory activity. Fluticasone furoate has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor that is approximately 29.9 times that of dexamethasone and 1.7 times that of fluticasone propionate. The clinical relevance of these findings is unknown.
The precise mechanism through which fluticasone furoate affects asthma symptoms is not known. Inflammation is an important component in the pathogenesis of asthma. Corticosteroids have been shown to have a wide range of actions on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, cytokines) involved in inflammation.
Specific effects of fluticasone furoate demonstrated in in vitro and in vivo models included activation of the glucocorticoid response element, inhibition of pro-inflammatory transcription factors such as NFkB, and inhibition of antigen-induced lung eosinophilia in sensitized rats. These anti-inflammatory actions of corticosteroids may contribute to their efficacy. Though effective for the treatment of asthma, corticosteroids may not affect symptoms immediately.
Individual patients will experience a variable time to onset and degree of symptom relief. Maximum benefit may not be achieved for 1 to 2 weeks or longer after starting treatment. When corticosteroids are discontinued, asthma stability may persist for several days or longer.
Trials in subjects with asthma have shown a favorable ratio between topical anti-inflammatory activity and systemic corticosteroid effects with recommended doses of orally inhaled fluticasone furoate. This is explained by a combination of a relatively high local anti-inflammatory effect, negligible oral systemic bioavailability (approximately 1.3%), and the minimal pharmacological activity of the metabolites detected in man.
12.2Pharmacodynamics The pharmacodynamics of fluticasone furoate was characterized in trials of fluticasone furoate given as a single component and also in trials of fluticasone furoate given in combination with vilanterol. Cardiac Electrophysiology A QT/QTc trial did not demonstrate an effect of fluticasone furoate administration on the QTc interval. The effect of a single dose of 4,000 mcg of orally inhaled fluticasone furoate on the QTc interval was evaluated over 24 hours in 40 healthy male and female subjects in a placebo- and positive-controlled (a single dose of 400 mg oral moxifloxacin) cross-over trial.
The QTcF maximal mean change from baseline following fluticasone furoate was similar to that observed with placebo with a treatment difference of 0.788 msec (90% CI: -1.802, 3.378). In contrast, moxifloxacin given as a 400-mg tablet resulted in prolongation of the QTcF maximal mean change from baseline compared with placebo with a treatment difference of 9.929 msec (90% CI: 7.339, 12.520). Hypothalamic-Pituitary-Adrenal Axis Effects Healthy Subjects: Inhaled fluticasone furoate at repeat doses up to 400 mcg was not associated with statistically significant decreases in serum or urinary cortisol in healthy subjects.
Decreases in serum and urine cortisol levels were observed at fluticasone furoate exposures several-fold higher than exposures observed at the therapeutic dose. Subjects with Asthma: A randomized, double-blind, parallel-group trial in 104 pediatric subjects with asthma (aged 5 to 11 years) showed no difference between once-daily treatment with ARNUITY ELLIPTA 50 mcg compared with placebo on serum cortisol weighted mean (0 to 24 hours) and serum cortisol AUC (0-24) following 6 weeks of treatment. A randomized, double-blind, parallel-group trial in 185 subjects with asthma aged 12 to 65 years showed no difference between once-daily treatment with fluticasone furoate/vilanterol 100/25 mcg or fluticasone furoate/vilanterol 200/25 mcg compared wit… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Fluticasone furoate is a synthetic trifluorinated corticosteroid with anti‑inflammatory activity. Fluticasone furoate has been shown in vitro to exhibit a binding affinity for the human glucocorticoid receptor that is approximately 29.9 times that of dexamethasone and 1.7 times that of fluticasone propionate. The clinical relevance of these findings is unknown.
The precise mechanism through which fluticasone furoate affects asthma symptoms is not known. Inflammation is an important component in the pathogenesis of asthma. Corticosteroids have been shown to have a wide range of actions on multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, cytokines) involved in inflammation.
Specific effects of fluticasone furoate demonstrated in in vitro and in vivo models included activation of the glucocorticoid response element, inhibition of pro-inflammatory transcription factors such as NFkB, and inhibition of antigen-induced lung eosinophilia in sensitized rats. These anti-inflammatory actions of corticosteroids may contribute to their efficacy. Though effective for the treatment of asthma, corticosteroids may not affect symptoms immediately.
Individual patients will experience a variable time to onset and degree of symptom relief. Maximum benefit may not be achieved for 1 to 2 weeks or longer after starting treatment. When corticosteroids are discontinued, asthma stability may persist for several days or longer.
Trials in subjects with asthma have shown a favorable ratio between topical anti-inflammatory activity and systemic corticosteroid effects with recommended doses of orally inhaled fluticasone furoate. This is explained by a combination of a relatively high local anti-inflammatory effect, negligible oral systemic bioavailability (approximately 1.3%), and the minimal pharmacological activity of the metabolites detected in man.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ARNUITY ELLIPTA 50 mcg is supplied as a disposable light grey and orange plastic inhaler containing a foil strip with 30 blisters (NDC 0173-0888-10). ARNUITY ELLIPTA 100 mcg is supplied as a disposable light grey and orange plastic inhaler containing a foil strip with 30 blisters (NDC 0173-0874-10) or 14 blisters (institutional pack) (NDC 0173-0874-14). ARNUITY ELLIPTA 200 mcg is supplied as a disposable light grey and orange plastic inhaler containing a foil strip with 30 blisters (NDC 0173-0876-10) or 14 blisters (institutional pack) (NDC 0173-0876-14).
The inhaler is packaged in a moisture-protective foil tray with a desiccant and a peelable lid. Store at room temperature between 68°F and 77°F (20°C and 25°C); excursions permitted from 59°F to 86°F (15°C to 30°C) [See USP Controlled Room Temperature]. Store in a dry place away from direct heat or sunlight.
Keep out of reach of children. ARNUITY ELLIPTA should be stored inside the unopened moisture-protective foil tray and only removed from the tray immediately before initial use. Discard ARNUITY ELLIPTA 6 weeks after opening the foil tray or when the counter reads “0” (after all blisters have been used), whichever comes first.
The inhaler is not reusable. Do not attempt to take the inhaler apart.
📋 Description ▾
11 DESCRIPTION ARNUITY ELLIPTA is an inhalation powder drug product for delivery of fluticasone furoate (an ICS) to patients by oral inhalation. Fluticasone furoate, a synthetic trifluorinated corticosteroid, has the chemical name (6α,11β,16α,17α)-6,9-difluoro-17-{[(fluoro-methyl)thio]carbonyl}-11-hydroxy-16-methyl-3-oxoandrosta-1,4-dien-17-yl 2-furancarboxylate and the following chemical structure: Fluticasone furoate is a white powder with a molecular weight of 538.6, and the empirical formula is C 27 H 29 F 3 O 6 S.
It is practically insoluble in water. ARNUITY ELLIPTA is a light grey and orange plastic inhaler containing a foil blister strip. Each blister on the strip contains a white powder blend of micronized fluticasone furoate (50, 100, or 200 mcg) and lactose monohydrate (12.45, 12.40, or 12.30 mg, respectively) for a total powder blend of 12.5 mg per blister.
The lactose monohydrate contains milk proteins. After the inhaler is activated, the powder within the blister is exposed and ready for dispersion into the airstream created by the patient inhaling through the mouthpiece. Under standardized in vitro test conditions, ARNUITY ELLIPTA 50 mcg, ARNUITY ELLIPTA 100 mcg, and ARNUITY ELLIPTA 200 mcg delivers 46, 90, and 182 mcg, respectively, of fluticasone furoate per dose when tested at a flow rate of 60 L/min for 4 seconds.
In adult subjects with asthma and a mean FEV 1 of
2.55L/sec (range: 1.63 to
3.97L/sec), mean peak inspiratory flow through the ELLIPTA inhaler was 103.2 L/min (range: 71.2 to 133.1 L/min). In pediatric subjects with asthma aged 5 to 11 years and a mean peak expiratory flow rate of 242 L/min (range: 130 to 420 L/min), mean peak inspiratory flow through the ELLIPTA inhaler was
51.8L/min (range: 26.8 to
89.9L/min). Therefore, the ELLIPTA inhaler is able to deliver the dose of fluticasone furoate in patients with asthma. The actual amount of drug delivered to the lung will depend on patient factors, such as inspiratory flow profile. fluticasone furoate chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Not for Acute Symptoms Inform patients that ARNUITY ELLIPTA is not meant to relieve acute symptoms of asthma and extra doses should not be used for that purpose. Advise patients to treat acute symptoms with an inhaled, short-acting beta 2 -agonist such as albuterol.
Provide patients with such medication and instruct them in how it should be used. Instruct patients to seek medical attention immediately if they experience any of the following: • Decreasing effectiveness of inhaled, short-acting beta 2 -agonists • Need for more inhalations than usual of inhaled, short-acting beta 2 -agonists • Significant decrease in lung function as outlined by the physician Advise patients not to increase the dose or frequency of ARNUITY ELLIPTA. The daily dosage of ARNUITY ELLIPTA should not exceed 1 inhalation.
If they miss a dose, instruct patients to take it as soon as they remember, not to exceed 1 inhalation per day. Advise patients to take their next dose at the same time they normally do and to not take 2 doses at 1 time. Tell patients they should not stop therapy with ARNUITY ELLIPTA without physician/provider guidance since symptoms may recur after discontinuation. [See Warnings and Precautions ( 5.2 ).] Oropharyngeal Candidiasis Inform patients that localized infections with Candida albicans occurred in the mouth and pharynx in some patients.
If oropharyngeal candidiasis develops, treat it with appropriate local or systemic (i.e., oral) antifungal therapy while still continuing therapy with ARNUITY ELLIPTA, but at times therapy with ARNUITY ELLIPTA may need to be temporarily interrupted under close medical supervision. Advise patients to rinse the mouth with water without swallowing after inhalation to help reduce the risk of thrush. [See Warnings and Precautions ( 5.1 ).] Immunosuppression and Risk of Infections Warn patients who are on immunosuppressant doses of corticosteroids to avoid exposure to chickenpox or measles and, if exposed, to consult their physicians without delay.
Inform patients of potential worsening of existing tuberculosis, fungal, bacterial, viral, or parasitic infections or ocular herpes simplex. [See Warnings and Precautions ( 5.3 ).] Hypercorticism and Adrenal Suppression Advise patients that ARNUITY ELLIPTA may cause systemic corticosteroid effects of hypercorticism and adrenal suppression. Additionally, inform patients that deaths due to adrenal insufficiency have occurred during and after transfer from systemic corticosteroids. Patients should taper slowly from systemic corticosteroids if transferring to ARNUITY ELLIPTA. [See Warnings and Precautions ( 5.5 ).] Hypersensitivity Reactions, including Anaphylaxis Advise patients that hypersensitivity reactions (e.g., anaphylaxis, angioedema, urticaria, flushing, allergic dermatitis, bronchospasm) may occur after administration of ARNUITY ELLIPTA.
Instruct patients to discontinue ARNUITY ELLIPTA if such reactions occur. There have been reports of anaphylactic reactions in patients with severe milk protein allergy after inhalation of other powder medications containing lactose; therefore, patients with severe milk protein allergy should not use ARNUITY ELLIPTA. [See Warnings and Precautions ( 5.8 ).] Reduction in Bone Mineral Density Advise patients who are at an increased risk for decreased BMD that the use of corticosteroids may pose an additional risk. [See Warnings and Precautions ( 5.9 )] Reduced Growth Velocity Inform patients that orally inhaled corticosteroids, including ARNUITY ELLIPTA, may cause a reduction in growth velocity when administered to pediatric patients.
Physicians should closely follow the growth of pediatric patients taking corticosteroids by any route. [See Warnings and Precautions ( 5.10 ).] Glaucoma and Cataracts Advise patients that long-term use of ICS may increase the risk of some eye problem… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of fluticasone furoate was characterized in trials of fluticasone furoate given as a single component and in trials of fluticasone furoate given in combination with vilanterol. Linear pharmacokinetics was observed for fluticasone furoate (200 to 800 mcg). On repeated once-daily inhalation administration, steady state of fluticasone furoate plasma concentration was achieved after 6 days, and the accumulation was up to 2.6-fold as compared with single dose.
Absorption Fluticasone furoate plasma levels may not predict therapeutic effect. Peak plasma concentrations are reached within 0.5 to 1 hour. Absolute bioavailability of fluticasone furoate when administrated by inhalation was 13.9%, primarily due to absorption of the inhaled portion of the dose delivered to the lung.
Oral bioavailability from the swallowed portion of the dose is low (approximately 1.3%) due to extensive first-pass metabolism. Systemic exposure (AUC) in subjects with asthma was 26% lower than observed in healthy subjects. Distribution Following intravenous administration to healthy subjects, the mean volume of distribution at steady state was 661 L.
Binding of fluticasone furoate to human plasma proteins was high (99.6%). Elimination Metabolism: Fluticasone furoate is cleared from systemic circulation principally by hepatic metabolism via CYP3A4 to metabolites with significantly reduced corticosteroid activity. There was no in vivo evidence for cleavage of the furoate moiety resulting in the formation of fluticasone.
Excretion: Fluticasone furoate and its metabolites are eliminated primarily in the feces, accounting for approximately 101% and 90% of the orally and intravenously administered doses, respectively. Urinary excretion accounted for approximately 1% and 2% of the orally and intravenously administered doses, respectively. Following repeat-dose inhaled administration, the plasma elimination phase half-life averaged 24 hours.
Specific Populations The effects of renal and hepatic impairment and other intrinsic factors on the pharmacokinetics of fluticasone furoate are shown in Figure 1 . Figure 1. Impact of Intrinsic Factors on the Pharmacokinetics (PK) of Fluticasone Furoate (FF) a Age, gender, and ethnicity comparison for ARNUITY ELLIPTA in adult and pediatric subjects aged 12 years and older with asthma. b Renal groups (fluticasone furoate/vilanterol 200 mcg/25 mcg) and hepatic groups (fluticasone furoate/vilanterol 200 mcg/25 mcg or fluticasone furoate/vilanterol 100 mcg/12.5 mcg) compared with healthy control group.
Pediatric Patients: A population pharmacokinetics analysis to assess impact of age on fluticasone furoate systemic exposure was conducted using combined data from clinical trials in pediatric subjects aged 5 to 11 years (n = 306). There was no relevant effect of age on the apparent clearance of fluticasone furoate. The rate and extent of fluticasone furoate systemic exposure at steady state in children aged 5 to 11 years were comparable to that observed in adult and pediatric subjects aged 12 years and older following dosing with fluticasone furoate 100 mcg monotherapy.
Racial or Ethnic Groups: Systemic exposure [AUC (0-24) ] to inhaled fluticasone furoate 200 mcg was 27% to 49% higher in healthy subjects of Japanese, Korean, and Chinese heritage compared with White subjects. Similar differences were observed for subjects with asthma ( Figure 1 ). However, there is no evidence that this higher exposure to fluticasone furoate results in clinically relevant effects on urinary cortisol excretion or on efficacy in these racial groups.
Patients with Hepatic Impairment: Following repeat dosing of fluticasone furoate/vilanterol 200/25 mcg (100/12.5 mcg in the severe impairment group) for 7 days, there was an increase of 34%, 83%, and 75% in fluticasone furoate systemic exposure (AUC) in subjects with mild, moderate, and severe hepatic impairment, respectively, compared with healthy subjects ( Figure 1… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The pharmacodynamics of fluticasone furoate was characterized in trials of fluticasone furoate given as a single component and also in trials of fluticasone furoate given in combination with vilanterol. Cardiac Electrophysiology A QT/QTc trial did not demonstrate an effect of fluticasone furoate administration on the QTc interval. The effect of a single dose of 4,000 mcg of orally inhaled fluticasone furoate on the QTc interval was evaluated over 24 hours in 40 healthy male and female subjects in a placebo- and positive-controlled (a single dose of 400 mg oral moxifloxacin) cross-over trial.
The QTcF maximal mean change from baseline following fluticasone furoate was similar to that observed with placebo with a treatment difference of 0.788 msec (90% CI: -1.802, 3.378). In contrast, moxifloxacin given as a 400-mg tablet resulted in prolongation of the QTcF maximal mean change from baseline compared with placebo with a treatment difference of 9.929 msec (90% CI: 7.339, 12.520). Hypothalamic-Pituitary-Adrenal Axis Effects Healthy Subjects: Inhaled fluticasone furoate at repeat doses up to 400 mcg was not associated with statistically significant decreases in serum or urinary cortisol in healthy subjects.
Decreases in serum and urine cortisol levels were observed at fluticasone furoate exposures several-fold higher than exposures observed at the therapeutic dose. Subjects with Asthma: A randomized, double-blind, parallel-group trial in 104 pediatric subjects with asthma (aged 5 to 11 years) showed no difference between once-daily treatment with ARNUITY ELLIPTA 50 mcg compared with placebo on serum cortisol weighted mean (0 to 24 hours) and serum cortisol AUC (0-24) following 6 weeks of treatment. A randomized, double-blind, parallel-group trial in 185 subjects with asthma aged 12 to 65 years showed no difference between once-daily treatment with fluticasone furoate/vilanterol 100/25 mcg or fluticasone furoate/vilanterol 200/25 mcg compared with placebo on serum cortisol weighted mean (0 to 24 hours), serum cortisol AUC (0-24) , and 24-hour urinary cortisol after 6 weeks of treatment, whereas prednisolone 10 mg given once daily for 7 days resulted in significant cortisol suppression.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The safety and efficacy of ARNUITY ELLIPTA were evaluated in 3,611 adult and pediatric subjects aged 12 years and older with asthma. The development program included 4 confirmatory trials of 3 and 6 months’ duration and 3 dose-ranging trials of 8 weeks’ duration. The efficacy of ARNUITY ELLIPTA is based primarily on the dose-ranging trials and the confirmatory trials described below.
One additional trial evaluated the safety and efficacy of ARNUITY ELLIPTA in 593 subjects aged 5 to 11 years.
14.1Dose-Ranging Trials Eight doses of fluticasone furoate ranging from 25 to 800 mcg once daily were evaluated in 3 randomized, double-blind, placebo-controlled, 8-week trials in adult and pediatric subjects aged 12 years and older with asthma. Across the 3 trials, subjects were uncontrolled at baseline on treatments of short-acting beta 2 -agonist and/or non-corticosteroid controller medications (Trial 687 NCT00603382), low-dose ICS (Trial 685 NCT00603278), or medium doses of ICS (Trial 684 NCT00603746). The trials in Figure 3 were dose-ranging trials of ARNUITY ELLIPTA not designed to provide comparative effectiveness data and should not be interpreted as evidence of superiority/inferiority to fluticasone propionate.
A dose-related increase in trough FEV1 at Week 8 was seen for doses from 25 to 200 mcg with no consistent additional benefit for doses above 200 mcg as seen in Figure 3 . To evaluate dosing frequency, a separate trial compared fluticasone furoate 200 mcg once daily, fluticasone furoate 100 mcg twice daily, fluticasone propionate 100 mcg twice daily, and fluticasone propionate 200 mcg once daily. The results supported the selection of the once-daily dosing frequency.
Figure 3. Dose-Ranging Trials FF = Fluticasone furoate, FP = Fluticasone propionate, OD = Once daily, BD = Twice daily. Figure 3
14.2Confirmatory Trials Adult and Pediatric Subjects Aged 12 Years and Older The clinical development program for ARNUITY ELLIPTA included 4 confirmatory trials in adult and pediatric subjects with asthma aged 12 years and older. The trials were designed to evaluate the safety and efficacy of ARNUITY ELLIPTA given once daily in the evening on lung function in subjects who were not controlled on their current treatments of ICS, or combination therapy consisting of an ICS plus a LABA. Study treatments were delivered as inhalation powders.
The primary endpoint in all trials was change from baseline in evening trough FEV 1 measured approximately 24 hours after the final dose of study medication. Trough FEV 1 (assessed at approximately 24 hours after the previous dose) was also assessed at clinic visits throughout the trials. Trials 2 and 4 had a co-primary endpoint of change from baseline in weighted mean serial FEV 1 measured after the final dose of study medication at 5, 15, and 30 minutes and 1, 2, 3, 4, 5, 12, 16, 20, 23, and 24 hours post-dose.
Clinical Trials with ARNUITY ELLIPTA 100 mcg: Trial 1 (NCT01159912) was a 24-week trial that evaluated the efficacy of ARNUITY ELLIPTA 100 mcg compared with placebo on lung function in subjects with asthma. Inhaled fluticasone propionate 250 mcg twice daily was included as an active control. Of the 343 subjects, 59% were female and 79% were Caucasian.
The mean age was 41 years. The trial included a 4-week run-in period during which the subjects were symptomatic while taking their usual low- to mid-dose ICS therapy (i.e., fluticasone propionate 100 to 500 mcg daily or equivalent). Mean baseline percent predicted FEV 1 was approximately 73% overall and was similar across the 3 treatment groups.
Thirty-five percent of subjects on placebo and 19% of subjects on ARNUITY ELLIPTA 100 mcg failed to complete the 24-week trial. The change in trough FEV 1 from baseline to Week 24, or the last available on-treatment visit prior to Week 24, was assessed to evaluate the efficacy of ARNUITY ELLIPTA 100 mcg. The mean change from baseline in trough FEV 1 was greater among subjects receivin… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Fluticasone furoate produced no treatment-related increases in the incidence of tumors in 2-year inhalation studies in rats and mice at inhaled doses up to 9 and 19 mcg/kg/day, respectively (less than the MRHDID on a mcg/m 2 basis). Fluticasone furoate did not induce gene mutation in bacteria or chromosomal damage in a mammalian cell mutation test in mouse lymphoma L5178Y cells in vitro . There was also no evidence of genotoxicity in the in vivo micronucleus test in rats.
No evidence of impairment of fertility was observed in male and female rats at inhaled fluticasone furoate doses up to 29 and 91 mcg/kg/day, respectively (approximately 1 and 4 times, respectively, the MRHDID for adults on a mcg/m 2 basis).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Fluticasone furoate produced no treatment-related increases in the incidence of tumors in 2-year inhalation studies in rats and mice at inhaled doses up to 9 and 19 mcg/kg/day, respectively (less than the MRHDID on a mcg/m 2 basis). Fluticasone furoate did not induce gene mutation in bacteria or chromosomal damage in a mammalian cell mutation test in mouse lymphoma L5178Y cells in vitro . There was also no evidence of genotoxicity in the in vivo micronucleus test in rats.
No evidence of impairment of fertility was observed in male and female rats at inhaled fluticasone furoate doses up to 29 and 91 mcg/kg/day, respectively (approximately 1 and 4 times, respectively, the MRHDID for adults on a mcg/m 2 basis).
📄 Patient Package Insert ▾
Patient Information ARNUITY ELLIPTA (ar-NEW-i-te e-LIP-ta) (fluticasone furoate inhalation powder) for oral inhalation use What is ARNUITY ELLIPTA? • ARNUITY ELLIPTA is an inhaled corticosteroid (ICS) medicine (fluticasone furoate). o ICS medicines such as fluticasone furoate help to decrease inflammation in the lungs. Inflammation in the lungs can lead to breathing problems. • ARNUITY ELLIPTA is not used to relieve sudden breathing problems and will not replace a rescue inhaler. • ARNUITY ELLIPTA is a prescription medicine used to prevent and control symptoms of asthma for better breathing.
It is not known if ARNUITY ELLIPTA is safe and effective in children younger than 5 years of age. Do not use ARNUITY ELLIPTA: • to treat sudden symptoms of asthma. • if you have a severe allergy to milk proteins. Ask your healthcare provider if you are not sure. • if you are allergic to fluticasone furoate or any of the ingredients in ARNUITY ELLIPTA.
See the end of this Patient Information for a complete list of ingredients in ARNUITY ELLIPTA. Before using ARNUITY ELLIPTA, tell your healthcare provider about all of your medical conditions, including if you: • have liver problems. • have weak bones (osteoporosis). • have an immune system problem. • have eye problems such as glaucoma, increased pressure in your eye, cataracts, or other changes in vision. • are allergic to milk proteins. • have any type of viral, bacterial, fungal, or parasitic infection. • are exposed to chickenpox or measles. • are pregnant or plan to become pregnant.
It is not known if ARNUITY ELLIPTA may harm your unborn baby. • are breastfeeding or plan to breastfeed. It is not known if the medicine in ARNUITY ELLIPTA passes into your breast milk and if it can harm your baby. Tell your healthcare provider about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements.
ARNUITY ELLIPTA and certain other medicines may interact with each other. This may cause serious side effects. Especially, tell your healthcare provider if you take antifungal, anti-HIV, or any other corticosteroid medicines.
Know the medicines you take. Keep a list of them to show your healthcare provider and pharmacist when you get a new medicine. How should I use ARNUITY ELLIPTA?
Read the step-by-step instructions for using ARNUITY ELLIPTA at the end of this Patient Information. • Do not use ARNUITY ELLIPTA unless your healthcare provider has taught you how to use the inhaler and you understand how to use it correctly. • ARNUITY ELLIPTA comes in 3 different strengths. Your healthcare provider prescribed the strength that is best for you. • Use ARNUITY ELLIPTA exactly as your healthcare provider tells you to use it. Do not use ARNUITY ELLIPTA more often than prescribed. • Children and adolescents may need help to use ARNUITY ELLIPTA. • Use 1 inhalation of ARNUITY ELLIPTA 1 time each day.
Use ARNUITY ELLIPTA at the same time each day. • If you miss a dose of ARNUITY ELLIPTA, take it as soon as you remember. Do not take more than 1 inhalation per day. Take your next dose at your usual time.
Do not take 2 doses at 1 time. • Do not stop using ARNUITY ELLIPTA unless told to do so by your healthcare provider because your symptoms might get worse. Your healthcare provider will change your medicines as needed. • ARNUITY ELLIPTA does not relieve sudden symptoms of asthma and you should not take extra doses of ARNUITY ELLIPTA to relieve these sudden symptoms. Always have a rescue inhaler with you to treat sudden symptoms.
If you do not have a rescue inhaler, call your healthcare provider to have one prescribed for you. • Call your healthcare provider or get medical care right away if: o your breathing problems get worse. o you need to use your rescue inhaler more often than usual. o your rescue inhaler does not work as well to relieve your symptoms. o your peak flow meter results decrease. Your healthcare provider will tell you the numbers that are right… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE ARNUITY ELLIPTA (ar-NEW-i-te e-LIP-ta) (fluticasone furoate inhalation powder) for oral inhalation use Read this before you start: • If you open and close the cover without inhaling the medicine, you will lose the dose. • The lost dose will be securely held inside the inhaler, but it will no longer be available to be inhaled. • It is not possible to accidentally take a double dose or an extra dose in 1 inhalation. Your ARNUITY ELLIPTA inhaler How to use your inhaler • ARNUITY ELLIPTA comes in a tray. • Peel back the lid to open the tray.
See Figure A . • The tray contains a desiccant to reduce moisture. Do not eat or inhale. Throw it away in the household trash out of reach of children and pets.
See Figure B . Figure A Figure B Important Notes: • Your inhaler contains 30 doses (14 doses if you have a 100-mcg or 200-mcg strength sample or institutional pack). • Each time you fully open the cover of the inhaler (you will hear a clicking sound), a dose is ready to be inhaled. This is shown by a decrease in the number on the counter. • If you open and close the cover without inhaling the medicine, you will lose the dose.
The lost dose will be held in the inhaler, but it will no longer be available to be inhaled. It is not possible to accidentally take a double dose or an extra dose in 1 inhalation. • Do not open the cover of the inhaler until you are ready to use it. To avoid wasting doses after the inhaler is ready, do not close the cover until after you have inhaled the medicine. • Write the “Tray opened” and “Discard” dates on the inhaler label.
The “Discard” date is 6 weeks from the date you open the tray. Check the counter. See Figure C.
Figure C • Before the inhaler is used for the first time, the counter should show the number 30 (14 if you have a 100-mcg or 200-mcg strength sample or institutional pack). This is the number of doses in the inhaler. • Each time you open the cover, you prepare 1 dose of medicine. • The counter counts down by 1 each time you open the cover. Prepare your dose: Wait to open the cover until you are ready to take your dose.
Figure D Step 1. Open the cover of the inhaler. See Figure D. • Slide the cover down to expose the mouthpiece.
You should hear a “click.” The counter will count down by 1 number. You do not need to shake this kind of inhaler. Your inhaler is now ready to use. • If the counter does not count down as you hear the click, the inhaler will not deliver the medicine.
Call your healthcare provider or pharmacist if this happens. Figure E Step 2. Breathe out.
See Figure E. • While holding the inhaler away from your mouth, breathe out (exhale) fully. Do not breathe out into the mouthpiece. Figure F Step 3.
Inhale your medicine. See Figure F. • Put the mouthpiece between your lips, and close your lips firmly around it. Your lips should fit over the curved shape of the mouthpiece. • Take 1 long, steady, deep breath in through your mouth.
Do not breathe in through your nose. Figure G • Do not block the air vent with your fingers. See Figure G.
Figure H • Remove the inhaler from your mouth and hold your breath for about 3 to 4 seconds (or as long as comfortable for you). See Figure H. Figure I Step 4.
Breathe out slowly and gently. See Figure I. • You may not taste or feel the medicine, even when you are using the inhaler correctly. • Do not take another dose from the inhaler even if you do not feel or taste the medicine. Figure J Step 5.
Close the inhaler. See Figure J. • You can clean the mouthpiece if needed, using a dry tissue, before you close the cover. Routine cleaning is not required. • Slide the cover up and over the mouthpiece as far as it will go.
Figure K Step 6. Rinse your mouth. See Figure K. • Rinse your mouth with water after you have used the inhaler and spit the water out.
Do not swallow the water. Important Note: When should you get a refill? Figure L • When you have fewer than 10 doses remaining in your inhaler, the left half of the counter shows red a… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0173-0888-10 ARNUITY ELLIPTA \ (fluticasone furoate inhalation powder) 50 mcg Rx Only FOR ORAL INHALATION ONLY Each blister contains 50 mcg of fluticasone furoate and lactose monohydrate. 1 ELLIPTA Inhaler containing 1 Foil Strip of 30 Blisters GSK Made in Singapore ©2023 GSK group of companies or its licensor. 62000000087776 Rev. 4/23 Arnuity Ellipta 50 mcg 30 count carton
PRINCIPAL DISPLAY PANEL NDC 0173-0874-10 ARNUITY ELLIPTA (fluticasone furoate inhalation powder) 100 mcg Rx Only FOR ORAL INHALATION ONLY Each blister contains 100 mcg of fluticasone furoate and lactose monohydrate. 1 ELLIPTA Inhaler containing 1 Foil Strip of 30 Blisters GSK Made in Singapore ©2023 the GSK group of companies or its licensor. 62000000087842 Rev. 4/23 Arnuity Ellipta 100 mcg 30 count carton
PRINCIPAL DISPLAY PANEL NDC 0173-0876-10 ARNUITYELLIPTA (fluticasone furoate inhalation powder) 200 mcg Rx Only FOR ORAL INHALATION ONLY Each blister contains 200 mcg of fluticasone furoate and lactose monohydrate. 1 ELLIPTA Inhaler containing 1 Foil Strip of 30 Blisters GSK Made in Singapore ©2023 the GSK group of companies 62000000087779 Rev. 4/23 Arnuity Ellipta 200 mcg 30 count carton