
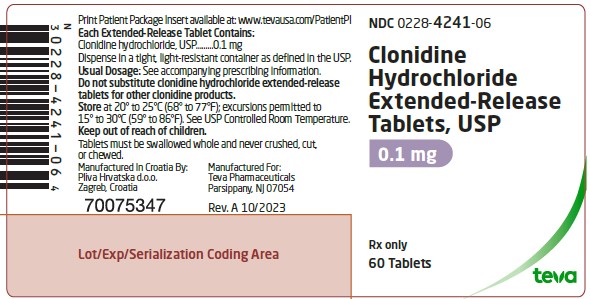
Clonidine Hydrochloride .1 mg Tablet, Extended Release, 60-count — NDC 0228-4241-06 (Billing 00228-4241-06)
This is a package of 60 tablets of Clonidine Hydrochloride .1 mg Tablet, Extended Release from Actavis Pharma, Inc., marketed since Jun 2015 and currently FDA-listed; retail pharmacies pay about $0.2117 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 066895
- GCN: 29319
- GPI-14 (Medi-Span): 61353020107420
- HICL (First Databank): 000113
- AHFS class code: 12:12.04.00
- RxCUI (RxNorm): 1013930
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Clonidine is used alone or in combination with other medications to treat high blood pressure. Clonidine is also used alone or in combination with other medications as part of a treatment program to control symptoms of attention deficit hyperactivity disorder (ADHD; more difficulty focusing, controlling actions, and remaining still or quiet than other people who are the same age) in children 6 years of age and older. Clonidine is in a class of medications called centrally acting alpha-agonist hypotensive agents. Clonidine treats high blood pressure by decreasing your heart rate and relaxing th...
Read the full MedlinePlus article ↗- It depends on the product. Tablets, oral solutions, Nexiclon XR and patches lower high blood pressure. Certain extended-release products treat ADHD. The epidural injection is used...
- No. Stopping suddenly can cause rebound high blood pressure, with headache, a racing heart, nervousness and anxiety. Your doctor will lower the dose gradually.
- Sleepiness is common. Don't drive or use heavy equipment until you know how it affects you. Avoid alcohol, and ask me before combining it with other sedating medicines.
- No. Extended-release clonidine tablets should be swallowed whole, not crushed, chewed or broken. They can be taken with or without food.
Patient education
Supplement & herbal interactions
Clonidine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.212 | $12.70 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4542 | $27.25 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.4712 | $28.27 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00228-4241-06 You're viewing this Main listing | 60 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2015-06-17 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clonidine Hydrochloride .1 mgthis 00228-4241-06 | Actavis | 60 tablets | $0.212 | AB1 | Availability likely | — |
| Clonidine hydrochloride .1 mg 27241-0108-06 | Ajanta | 60 tablets | $0.212 | AB1 | Availability likely | — |
| Clonidine Hydrochloride .1 mg 43547-0435-06 | Solco | 60 tablets | $0.212 | AB1 | Availability likely | — |
| Clonidine hydrochloride .1 mg 60687-0462-21 | American | 1 tablet | $0.212 | AB1 | Availability likely | — |
| Clonidine hydrochloride .1 mg 68001-0568-06 | BluePoint | 60 tablets | $0.212 | AB1 | Availability likely | — |
| Clonidine Hydrochloride .1 mg 70069-0044-01 | Somerset | 60 tablets | $0.212 | AB1 | Availability likely | — |
| Clonidine .1 mg 50742-0247-05 | Ingenus | 500 tablets | — | AB1 | FDA listed | — |
| Clonidine Hydrochloride .1 mg 63629-1208-01 | Bryant | 60 tablets | — | AB1 | Discontinued | — |
| Clonidine Hydrochloride .1 mg 68180-0606-06 | Lupin | 30 tablets | — | AB1 | FDA listed | — |
| Clonidine Hydrochloride .1 mg 71034-0001-60 | Xiamen | 60 tablets | — | AB1 | FDA listed | — |
| Clonidine Hydrochloride .1 mg 72162-1367-06 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII R33S7TK2EP
Hydroxyethyl cellulose is a thickening agent made from processed plant cellulose. It's used in medicines to increase viscosity, improve texture, and help distribute active ingredients evenly throughout liquid or semi-solid formulations.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Clonidine hydrochloride extended-release tablets are indicated for the treatment of attention deficit hyperactivity disorder (ADHD) as monotherapy and as adjunctive therapy to stimulant medications [see Clinical Studies (14) ] . Clonidine hydrochloride extended-release tablets are a centrally acting alpha 2 -adrenergic agonist indicated for the treatment of attention deficit hyperactivity disorder (ADHD) as monotherapy or as adjunctive therapy to stimulant medications. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Start with one 0.1 mg tablet at bedtime for one week. Increase daily dosage in increments of 0.1 mg/day at weekly intervals until the desired response is achieved. Take twice a day, with either an equal or higher split dosage being given at bedtime, as depicted below ( 2.2 ) Total Daily Dose Morning Dose Bedtime Dose 0.1 mg/day 0.1 mg 0.2 mg/day 0.1 mg 0.1 mg 0.3 mg/day 0.1 mg 0.2 mg 0.4 mg/day 0.2 mg 0.2 mg Do not crush, chew or break tablet before swallowing.
( 2.1 ) Do not substitute for other clonidine products on a mg-per-mg basis, because of differing pharmacokinetic profiles. ( 2.1 ) When discontinuing, taper the dose in decrements of no more than 0.1 mg every 3 to 7 days to avoid rebound hypertension. ( 2.3 )
2.1General Dosing Information Clonidine hydrochloride is an extended-release tablet to be taken orally with or without food. Swallow tablets whole. Do not crush, chew, or break tablets because this will increase the rate of clonidine release.
Due to the lack of controlled clinical trial data and differing pharmacokinetic profiles, substitution of clonidine hydrochloride extended-release tablets for other clonidine products on a mg-per-mg basis is not recommended [see Clinical Pharmacology (12.3) ] .
2.2Dose Selection The dose of clonidine hydrochloride extended-release tablets administered either as monotherapy or as adjunctive therapy to a psychostimulant, should be individualized according to the therapeutic needs and response of the patient. Dosing should be initiated with one 0.1 mg tablet at bedtime, and the daily dosage should be adjusted in increments of 0.1 mg/day at weekly intervals until the desired response is achieved. Doses should be taken twice a day, with either an equal or higher split dosage being given at bedtime (see Table 1).
Table 1 Clonidine Hydrochloride Extended-Release Tablets Dosing Guidance Total Daily Dose Morning Dose Bedtime Dose 0.1 mg/day 0.1 mg 0.2 mg/day 0.1 mg 0.1 mg 0.3 mg/day 0.1 mg 0.2 mg 0.4 mg/day 0.2 mg 0.2 mg Doses of clonidine hydrochloride extended-release tablets higher than 0.4 mg/day (0.2 mg twice daily) were not evaluated in clinical trials for ADHD and are not recommended. When a clonidine hydrochloride extended-release tablet is being added-on to a psychostimulant, the dose of the psychostimulant can be adjusted depending on the patient's response to clonidine hydrochloride extended-release tablets.
2.3Discontinuation When discontinuing clonidine hydrochloride extended-release tablets, the total daily dose should be tapered in decrements of no more than 0.1 mg every 3 to 7 days to avoid rebound hypertension [see Warnings and Precautions (5.3) ] .
2.4Missed Doses If patients miss a dose of clonidine hydrochloride extended-release tablets, they should skip that dose and take the next dose as scheduled. Do not take more than the prescribed total daily amount of clonidine hydrochloride extended-release tablets in any 24-hour period.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Clonidine hydrochloride, USP is available as 0.1 mg strength extended-release tablets. The 0.1 mg tablets are pink, unscored, round and debossed with on one side and 241 on the other side. Clonidine hydrochloride extended-release tablets must be swallowed whole and never crushed, cut or chewed. Extended-release tablets: 0.1 mg, not scored. ( 3 ) bceb3bbb-figure-02
⛔ Contraindications ▾
4 CONTRAINDICATIONS Clonidine hydrochloride extended-release tablets are contraindicated in patients with a history of a hypersensitivity reaction to clonidine. Reactions have included generalized rash, urticaria, and angioedema [see Adverse Reactions (6) ] . History of a hypersensitivity reaction to clonidine. Reactions have included generalized rash, urticaria, angioedema. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension/bradycardia/syncope: Titrate slowly and monitor vital signs frequently in patients at risk for hypotension, heart block, bradycardia, syncope, cardiovascular disease, vascular disease, cerebrovascular disease or chronic renal failure. Measure heart rate and blood pressure prior to initiation of therapy, following dose increases, and periodically while on therapy. Avoid concomitant use of drugs with additive effects unless clinically indicated.
Advise patients to avoid becoming dehydrated or overheated. ( 5.1 ) Somnolence/Sedation: Has been observed with clonidine hydrochloride extended-release tablets. Consider the potential for additive sedative effects with CNS depressant drugs.
Caution patients against operating heavy equipment or driving until they know how they respond to clonidine hydrochloride extended-release tablets. ( 5.2 ) Cardiac Conduction Abnormalities: May worsen sinus node dysfunction and atrioventricular (AV) block, especially in patients taking other sympatholytic drugs. Titrate slowly and monitor vital signs frequently.
( 5.5 )
5.1Hypotension/Bradycardia Treatment with clonidine hydrochloride extended-release tablets can cause dose-related decreases in blood pressure and heart rate [see Adverse Reactions (6.1) ] . Measure heart rate and blood pressure prior to initiation of therapy, following dose increases, and periodically while on therapy. Titrate clonidine hydrochloride extended-release tablets slowly in patients with a history of hypotension, and those with underlying conditions that may be worsened by hypotension and bradycardia; e.g., heart block, bradycardia, cardiovascular disease, vascular disease, cerebrovascular disease, or chronic renal failure.
In patients who have a history of syncope or may have a condition that predisposes them to syncope, such as hypotension, orthostatic hypotension, bradycardia, or dehydration, advise patients to avoid becoming dehydrated or overheated. Monitor blood pressure and heart rate, and adjust dosages accordingly in patients treated concomitantly with antihypertensives or other drugs that can reduce blood pressure or heart rate or increase the risk of syncope.
5.2Sedation and Somnolence Somnolence and sedation were commonly reported adverse reactions in clinical studies. In patients that completed 5 weeks of therapy in a controlled, fixed dose pediatric monotherapy study, 31% of patients treated with 0.4 mg/day and 38% treated with 0.2 mg/day versus 4% of placebo treated patients reported somnolence as an adverse event. In patients that completed 5 weeks of therapy in a controlled flexible dose pediatric adjunctive to stimulants study, 19% of patients treated with clonidine hydrochloride extended-release tablets+stimulant versus 7% treated with placebo+stimulant reported somnolence.
Before using clonidine hydrochloride extended-release tablets with other centrally active depressants (such as phenothiazines, barbiturates, or benzodiazepines), consider the potential for additive sedative effects. Caution patients against operating heavy equipment or driving until they know how they respond to treatment with clonidine hydrochloride extended-release tablets. Advise patients to avoid use with alcohol.
5.3Rebound Hypertension Abrupt discontinuation of clonidine hydrochloride extended-release tablets can cause rebound hypertension. In adults with hypertension, sudden cessation of clonidine hydrochloride extended-release formulation treatment in the 0.2 to 0.6 mg/day range resulted in reports of headache, tachycardia, nausea, flushing, warm feeling, brief lightheadedness, tightness in chest, and anxiety. In adults with hypertension, sudden cessation of treatment with immediate-release clonidine has, in some cases, resulted in symptoms such as nervousness, agitation, headache, and tremor accompanied or followed by a rapid rise in blood pressure and elevated catecholamine concentrations in the plasma.
No studies evaluating abrupt di… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described in greater detail elsewhere in labeling: Hypotension/bradycardia [see Warnings and Precautions (5.1) ] Sedation and somnolence [see Warnings and Precautions (5.2)] Rebound hypertension [see Warnings and Precautions (5.3)] Allergic reactions [see Warnings and Precautions (5.4)] Cardiac Conduction Abnormalities [see Warnings and Precautions (5.5)] Most common adverse reactions (incidence at least 5% and twice the rate of placebo) as monotherapy in ADHD: somnolence, fatigue, irritability, nightmare, insomnia, constipation, dry mouth.
( 6.1 ) Most common adverse reactions (incidence at least 5% and twice the rate of placebo) as adjunct therapy to psychostimulant in ADHD: somnolence, fatigue, decreased appetite, dizziness. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Two clonidine hydrochloride extended-release tablet ADHD clinical studies (Study 1, CLON-301 and Study 2, CLON-302) evaluated 256 patients in two 8-week placebo-controlled studies. A third clonidine hydrochloride extended-release tablet ADHD clinical study (Study 3, SHN-KAP-401) evaluated 135 children and adolescents in a 40- week placebo-controlled randomized-withdrawal study.
Study 1: Fixed-dose Clonidine Hydrochloride Extended-Release Tablets Monotherapy Study 1 (CLON-301) was a short-term, multi-center, randomized, double-blind, placebo-controlled study of two fixed doses (0.2 mg/day or 0.4 mg/day) of clonidine hydrochloride extended-release tablets in children and adolescents (6 to 17 years of age) who met DSM-IV criteria for ADHD hyperactive or combined inattentive/hyperactive subtypes. Most Common Adverse Reactions (incidence of greater than or equal to 5% and at least twice the rate of placebo): somnolence, fatigue, irritability, insomnia, nightmare, constipation, dry mouth.
Adverse Events Leading to Discontinuation of Clonidine Hydrochloride Extended-Release Tablets – Five patients (7%) in the low dose group (0.2 mg), 15 patients (20%) in the high dose group (0.4 mg), and 1 patient in the placebo group (1%) reported adverse reactions that led to discontinuation. The most common adverse reactions that led to discontinuation were somnolence and fatigue. Commonly observed adverse reactions (incidence of greater than or equal to 2% in either active treatment group and greater than the rate on placebo) during the treatment period are listed in Table 2.
Commonly observed adverse reactions (incidence of greater than or equal to 2% in either active treatment group and greater than the rate on placebo) during the taper period are listed in Table 3. Table 2 Common Adverse Reactions in the Fixed-Dose Monotherapy Trial - Treatment Period (Study 1) Percentage of Patients Reporting Event Clonidine Hydrochloride Extended-Release Tablets Clonidine Hydrochloride Extended-Release Tablets 0.2 mg/day 0.4 mg/day Placebo Preferred Term N=76 N=78 (N=76) PSYCHIATRIC DISORDERS Somnolence* 38% 31% 4% Nightmare 4% 9% 0% Emotional Disorder 4% 4% 1% Aggression 3% 1% 0% Tearfulness 1% 3% 0% Enuresis 0% 4% 0% Sleep Terror 3% 0% 0% Poor Quality Sleep 0% 3% 1% NERVOUS SYSTEM DISORDERS Headache 20% 13% 16% Insomnia 5% 6% 1% Tremor 1% 4% 0% Abnormal Sleep-Related Event 3% 1% 0% GASTROINTESTINAL DISORDERS Upper Abdominal Pain 15% 10% 12% Nausea 4% 5% 3% Constipation 1% 6% 0% Dry Mouth 0% 5% 1% GENERAL DISORDERS Fatigue† 16% 13% 1% Irritability 9% 5% 4% CARDIAC DISORDERS Dizziness 7% 3% 5% Bradycardia 0% 4% 0% INVESTIGATIONS Increased Heart Rate 0% 3% 0% METABOLISM AND NUTRITION DISORDERS Decreased Appetite 3% 4% 4% * Somnolence includes the terms "somn… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The following have been reported with other oral immediate release formulations of clonidine: Table 6 Clinically Important Drug Interactions Concomitant Drug Name or Drug Class Clinical Rationale Clinical Recommendation Tricyclic antidepressants Increase blood pressure and may counteract clonidine’s hypotensive effects Monitor blood pressure and adjust as needed Antihypertensive drugs Potentiate clonidine’s hypotensive effects Monitor blood pressure and adjust as needed CNS depressants Potentiate sedating effects Avoid use Drugs that affect sinus node function or AV node conduction (e.g., digitalis, calcium channel blockers, beta blockers) Potentiate bradycardia and risk of AV block Avoid use Sedating Drugs: Clonidine may potentiate the CNS-depressive effects of alcohol, barbiturates or other sedating drugs.
( 7 ) Tricyclic Antidepressants: May reduce the hypotensive effect of clonidine. ( 7 ) Drugs Known to Affect Sinus Node Function or AV Nodal Conduction: Caution is warranted in patients receiving clonidine concomitantly with agents known to affect sinus node function or AV nodal conduction (e.g., digitalis, calcium channel blockers and beta-blockers) due to a potential for additive effects such as bradycardia and AV block. ( 7 ) Antihypertensive drugs: Use caution when coadministered with clonidine hydrochloride extended-release tablets.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal Impairment: The dosage of clonidine hydrochloride extended-release tablets must be adjusted according to the degree of impairment, and patients should be carefully monitored. ( 8.6 , 12.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ADHD medications, including clonidine hydrochloride extended-release tablets, during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for ADHD Medications at 1-866-961-2388 or visiting https://womensmentalhealth.org/research/pregnancyregistry/adhd-medications/ . Risk Summary Prolonged experience with clonidine in pregnant women over several decades, based on published literature, including controlled trials, a retrospective cohort study and case reports, have not identified a drug associated risk of major birth defects, miscarriage, and adverse maternal or fetal outcomes.
In animal embryofetal studies, increased resorptions were seen in rats and mice administered oral clonidine hydrochloride from implantation through organogenesis at 10 and 5 times, respectively, the maximum recommended human dose (MRHD) given to adolescents on a mg/m 2 basis. No developmental effects were seen in rabbits administered oral clonidine hydrochloride during organogenesis at doses up to 3 times the MRHD (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Oral administration of clonidine hydrochloride to pregnant rabbits during the period of embryo/fetal organogenesis at doses of up to 80 mcg/kg/day (approximately 3 times the oral maximum recommended daily dose [MRHD] of 0.4 mg/day given to adolescents on a mg/m 2 basis) produced no developmental effects.
In pregnant rats, however, doses as low as 15 mcg/kg/day (1/3 the MRHD given to adolescents on a mg/m 2 basis) were associated with increased resorptions in a study in which dams were treated continuously from 2 months prior to mating and throughout gestation. Increased resorptions were not associated with treatment at the same or at higher dose levels (up to 3 times the MRHD) when treatment of the dams was restricted to gestation days 6 to 15. Increases in resorptions were observed in both rats and mice at 500 mcg/kg/day (10 and 5 times the MRHD in rats and mice, respectively) or higher when the animals were treated on gestation days 1 to 14; 500 mcg/kg/day was the lowest dose employed in this study.
8.2Lactation Risk Summary Based on published lactation studies, clonidine hydrochloride is present in human milk at relative infant doses ranging from 4.1 to 8.4% of the maternal weight-adjusted dosage. Although in most cases, there were no reported adverse effects in breastfed infants exposed to clonidine, there is one case report of sedation, hypotonia, and apnea in an infant exposed to clonidine through breast milk. If an infant is exposed to clonidine hydrochloride through breastmilk, monitor for symptoms of hypotension and bradycardia, such as sedation, lethargy, tachypnea and poor feeding (see Clinical Considerations) .
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for clonidine hydrochloride extended-release tablets and any potential adverse effects on the breastfed child from clonidine hydrochloride extended-release tablets or from the underlying maternal condition. Exercise caution when clonidine hydrochloride extended-release tablets are administered to a nursing woman. Clinical Considerations Monitor breastfeeding infants exposed to clonidine hydrochloride ext… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
10 OVERDOSAGE Symptoms Clonidine overdose: hypertension may develop early and may be followed by hypotension, bradycardia, respiratory depression, hypothermia, drowsiness, decreased or absent reflexes, weakness, irritability and miosis. The frequency of CNS depression may be higher in children than adults. Large overdoses may result in reversible cardiac conduction defects or dysrhythmias, apnea, coma and seizures.
Signs and symptoms of overdose generally occur within 30 minutes to two hours after exposure. Treatment Consult with a Certified Poison Control Center (1-800-222-1222) for up-to-date guidance and advice.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Clonidine stimulates alpha 2 -adrenergic receptors in the brain. Clonidine is not a central nervous system stimulant. The mechanism of action of clonidine in ADHD is not known.
12.2Pharmacodynamics Clonidine is a known antihypertensive agent. By stimulating alpha 2 -adrenergic receptors in the brain stem, clonidine reduces sympathetic outflow from the central nervous system and decreases peripheral resistance, renal vascular resistance, heart rate, and blood pressure.
12.3Pharmacokinetics Single-dose Pharmacokinetics in Adults Immediate-release clonidine hydrochloride and clonidine hydrochloride extended-release have different pharmacokinetic characteristics; dose substitution on a milligram for milligram basis will result in differences in exposure. A comparison across studies suggests that the C max is 50% lower for clonidine hydrochloride extended-release compared to immediate-release clonidine hydrochloride. Following oral administration of an immediate release formulation, plasma clonidine concentration peaks in approximately 3 to 5 hours and the plasma half-life ranges from 12 to 16 hours.
The half-life increases up to 41 hours in patients with severe impairment of renal function. Following oral administration about 40% to 60% of the absorbed dose is recovered in the urine as unchanged drug in 24 hours. About 50% of the absorbed dose is metabolized in the liver.
Although studies of the effect of renal impairment and studies of clonidine excretion have not been performed with clonidine hydrochloride extended-release, results are likely to be similar to those of the immediate release formulation. The pharmacokinetic profile of clonidine hydrochloride extended-release tablet administration was evaluated in an open-label, three-period, randomized, crossover study of 15 healthy adult subjects who received three single-dose regimens of clonidine: 0.1 mg of clonidine hydrochloride extended-release tablets under fasted conditions, 0.1 mg of clonidine hydrochloride extended-release tablets following a high fat meal, and 0.1 mg of clonidine hydrochloride immediate-release under fasted conditions.
Treatments were separated by one-week washout periods. Mean concentration-time data from the 3 treatments are shown in Table 7 and Figure 1. After administration of clonidine hydrochloride extended-release tablets, maximum clonidine concentrations were approximately 50% of the clonidine hydrochloride immediate-release maximum concentrations and occurred approximately 5 hours later relative to clonidine hydrochloride immediate-release.
Similar elimination half-lives were observed and total systemic bioavailability following clonidine hydrochloride extended-release tablets was approximately 89% of that following clonidine hydrochloride immediate-release. Food had no effect on plasma concentrations, bioavailability, or elimination half-life. Table 7 Pharmacokinetic Parameters of Clonidine in Healthy Adult Volunteers Clonidine Hydrochloride Immediate-Release-Fasted Clonidine Hydrochloride Extended-Release-Fed Clonidine Hydrochloride Extended-Release -Fasted n=15 n=15 n=14 Parameter Mean SD Mean SD MEAN SD C max (pg/mL) 443 59.6 235 34.7 258
33.3AUC inf 7313 1812 6505 1728 6729 1650 (hr*pg/mL) hT max (hr) 2.07 0.5 6.80 3.61 6.50
1.23T 1/2 (hr) 12.57 3.11 12.67 3.76 12.65
3.56Figure 1: Mean Clonidine Concentration-Time Profiles after Single Dose Administration Multiple-dose Pharmacokinetics in Children and Adolescents Plasma clonidine concentrations in children and adolescents (0.1 mg bid and 0.2 mg bid) with ADHD are greater than those of adults with hypertension with children and adolescents receiving higher doses on a mg/kg basis. Body weight normalized clearance (CL/F) in children and adolescents was higher than CL/F observed in adults with hypertension. Clonidine concentrations in plasma increased with increases in dose over the dose range of 0.2 to 0.4 mg/day.
Clonidine CL/F was indep… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Clonidine Hydrochloride Extended-Release Tablets, USP are supplied as follows: 0.1 mg — Each pink, round, unscored tablet debossed with on one side and 241 on the other side contains 0.1 mg of clonidine hydrochloride, USP. Tablets are supplied in bottles of 60 (NDC 0228-4241-06). Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F).
See USP Controlled Room Temperature. Brands listed are the trademarks of their respective owners. Dispense in a tight, light-resistant container as defined in the USP. bceb3bbb-figure-05
📋 Description ▾
11 DESCRIPTION Clonidine hydrochloride extended-release is a centrally acting alpha 2 -adrenergic agonist available as 0.1 mg extended-release tablets for oral administration. Each 0.1 mg tablet is equivalent to 0.087 mg of the free base. The inactive ingredients are colloidal silicon dioxide, hydroxyethyl cellulose, hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, red iron oxide, sodium lauryl sulfate and titanium dioxide.
The formulation is designed to delay the absorption of active drug in order to decrease peak to trough plasma concentration differences. Clonidine hydrochloride, USP is an imidazoline derivative and exists as a mesomeric compound. The chemical name is 2-(2,6-dichlorophenylamino)-2-imidazoline hydrochloride.
The following is the structural formula: Clonidine hydrochloride, USP is an odorless, bitter, white, crystalline substance soluble in water and alcohol. Product meets Dissolution Test 4. bceb3bbb-figure-03
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved Patient Labeling ( Patient Information ) Dosage and Administration Advise patients that clonidine hydrochloride extended-release tablets must be swallowed whole, never crushed, cut, or chewed, and may be taken with or without food. When initiating treatment, provide dosage escalation instructions [see Dosage and Administration (2.1) ] . Missed Dose If patients miss a dose of clonidine hydrochloride extended-release tablets, advise them to skip the dose and take the next dose as scheduled and not to take more than the prescribed total daily amount of clonidine hydrochloride extended-release tablets in any 24-hour period [see Dosage and Administration (2.4) ] .
Hypotension/Bradycardia Advise patients who have a history of syncope or may have a condition that predisposes them to syncope, such as hypotension, orthostatic hypotension, bradycardia, or dehydration, to avoid becoming dehydrated or overheated [see Warnings and Precautions (5.1) ] . Sedation and Somnolence Instruct patients to use caution when driving a car or operating hazardous machinery until they know how they will respond to treatment with clonidine hydrochloride extended-release tablets. Also advise patients to avoid the use of clonidine hydrochloride extended-release tablets with other centrally active depressants and with alcohol [see Warnings and Precautions (5.2) ] .
Rebound Hypertension Advise patients not to discontinue clonidine hydrochloride extended-release tablets abruptly [see Warnings and Precautions (5.3) ] . Allergic Reactions Advise patients to discontinue clonidine hydrochloride extended-release tablets and seek immediate medical attention if any signs or symptoms of a hypersensitivity reaction occur, such as generalized rash, urticaria, or angioedema [see Warnings and Precautions (5.4) ] . Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in patients exposed to clonidine hydrochloride extended-release tablets during pregnancy [see Use in Specific Populations ( 8.1 )] .
Lactation Advise breastfeeding women using clonidine hydrochloride extended-release tablets to monitor infants for excess sedation, decreased muscle tone, and respiratory depression and to seek medical care if they notice these signs [see Use in Specific Populations ( 8.2 )] . Fertility Advise females and males of reproductive potential that clonidine hydrochloride extended-release tablets may impair fertility [see Use in Specific Populations ( 8.3 ) and Nonclinical Toxicology ( 13.1 )] . Dispense with Patient Package Insert available at: www.tevausa.com/PatientPI Manufactured In Croatia By: Pliva Hrvatska d.o.o.
Zagreb, Croatia Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev. A 10/2023
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Efficacy of clonidine hydrochloride extended-release tablets in the treatment of ADHD was established in children and adolescents (6 to 17 years) in: One short-term, placebo-controlled monotherapy trial (Study 1) One short-term adjunctive therapy to psychostimulants trial (Study 2) One randomized withdrawal trial as monotherapy (Study 3) Short-term Monotherapy and Adjunctive Therapy to Psychostimulant Studies for ADHD The efficacy of clonidine hydrochloride extended-release tablets in the treatment of ADHD was established in 2 (one monotherapy and one adjunctive therapy) placebo-controlled trials in pediatric patients aged 6 to 17, who met DSM-IV criteria of ADHD hyperactive or combined hyperactive/inattentive subtypes.
Signs and symptoms of ADHD were evaluated using the investigator administered and scored ADHD Rating Scale-IV-Parent Version (ADHDRS-IV) total score including hyperactive/impulsivity and inattentive subscales. Study 1 (CLON-301), was an 8-week randomized, double-blind, placebo-controlled, fixed dose study of children and adolescents aged 6 to 17 (N=236) with a 5-week primary efficacy endpoint. Patients were randomly assigned to one of the following three treatment groups: clonidine hydrochloride extended-release tablets (CLON) 0.2 mg/day (N=78), clonidine hydrochloride extended-release tablets 0.4 mg/day (N=80), or placebo (N=78).
Dosing for the clonidine hydrochloride extended-release tablets groups started at 0.1 mg/day and was titrated in increments of 0.1 mg/week to their respective dose (as divided doses). Patients were maintained at their dose for a minimum of 2 weeks before being gradually tapered down to 0.1 mg/day at the last week of treatment. At both doses, improvements in ADHD symptoms were statistically significantly superior in clonidine hydrochloride extended-release tablets-treated patients compared with placebo-treated patients at the end of 5 weeks as measured by the ADHDRS-IV total score (Table 8).
Study 2 (CLON-302) was an 8-week randomized, double-blind, placebo-controlled, flexible dose study in children and adolescents aged 6 to 17 (N=198) with a 5-week primary efficacy end point. Patients had been treated with a psychostimulant (methylphenidate or amphetamine) for four weeks with inadequate response. Patients were randomly assigned to one of two treatment groups: clonidine hydrochloride extended-release tablets adjunct to a psychostimulant (N=102) or psychostimulant alone (N=96).
The clonidine hydrochloride extended-release tablet dose was initiated at 0.1 mg/day and doses were titrated in increments of 0.1 mg/week up to 0.4 mg/day, as divided doses, over a 3-week period based on tolerability and clinical response. The dose was maintained for a minimum of 2 weeks before being gradually tapered to 0.1 mg/day at the last week of treatment. ADHD symptoms were statistically significantly improved in clonidine hydrochloride extended-release tablets plus stimulant group compared with the stimulant alone group at the end of 5 weeks as measured by the ADHDRS-IV total score (Table 8).
Table 8 Short-Term Trials Study Number Treatment Group Primary Efficacy Measure: ADHDRS-IV Total Score Mean Baseline Score LS Mean Change from Placebo-subtracted (SD) Baseline (SE) Difference a (95% CI) Study 1 Clonidine Hydrochloride Extended-Release Tablets (0.2 mg/day) 43.8 (7.47) -15.0 (1.38) -8.5 (-12.2, -4.8) Clonidine Hydrochloride Extended-Release Tablets (0.4 mg/day) 44.6 (7.73) -15.6 (1.33) -9.1 (-12.8, -5.5) Placebo 45.0 (8.53) -6.5 (1.35) -- Study 2 Clonidine Hydrochloride Extended-Release Tablets (0.4 mg/day) + Psychostimulant 38.9 (6.95) -15.8 (1.18) -4.5 (-7.8, -1.1) Psychostimulant alone 39.0 (7.68) -11.3 (1.24) -- SD: standard deviation; SE: standard error; LS Mean: least-squares mean; CI: unadjusted confidence interval. a Difference (drug minus placebo) in least-squares mean change from baseline.
Maintenance Monotherapy for ADHD Study 3 (SHN-KAP-401), was a double-blind, place… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Clonidine hydrochloride extended-release tablets are not a controlled substance and have no known potential for abuse or dependence.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis and Impairment of Fertility Carcinogenesis Clonidine hydrochloride was not carcinogenic when administered in the diet of rats (for up to 132 weeks) or mice (for up to 78 weeks) at doses of up to 1620 (male rats), 2040 (female rats), or 2500 (mice) mcg/kg/day. These doses are approximately 20, 25, and 15 times, respectively, the maximum recommended human dose (MRHD) of 0.4 mg/day on a mg/m 2 basis. Mutagenesis There was no evidence of genotoxicity in the Ames test for mutagenicity or mouse micronucleus test for clastogenicity.
Impairment of Fertility In a reproduction study fertility of female rats appeared to be adversely affected at dose levels of 500 and 2000 mcg/kg/day (10 and 40 times the MRHD on a mg/ m 2 basis). Lower doses have not been adequately evaluated and a no adverse effect level could not be established.
📄 Patient Package Insert ▾
PATIENT NFORMATION Dispense with Patient Package Insert available at: www.tevausa.com/PatientPI Clonidine Hydrochloride (klon' i deen hye'' droe klor' ide ) Extended-Release Tablets Rx only Read the Patient Information that comes with clonidine hydrochloride extended-release tablets before you start taking it and each time you get a refill. There may be new information. This Patient Information leaflet does not take the place of talking to your doctor about your medical condition or treatment.
What are clonidine hydrochloride extended-release tablets ? Clonidine hydrochloride extended-release tablets are a prescription medicine used for the treatment of Attention-Deficit Hyperactivity Disorder (ADHD). Your doctor may prescribe clonidine hydrochloride extended-release tablets alone or together with certain other ADHD medicines.
Clonidine hydrochloride extended-release tablets are not a central nervous system (CNS) stimulant. Clonidine hydrochloride extended-release tablets should be used as part of a total treatment program for ADHD that may include counseling or other therapies. Who should not take clonidine hydrochloride extended-release tablets ?
Do not take clonidine hydrochloride extended-release tablets if you are allergic to clonidine in clonidine hydrochloride extended-release tablets. See the end of this leaflet for a complete list of ingredients in clonidine hydrochloride extended-release tablets. What should I tell my doctor before taking clonidine hydrochloride extended-release tablets ?
Before you take clonidine hydrochloride extended-release tablets, tell your doctor if you: have kidney problems have low or high blood pressure have a history of passing out (syncope) have heart problems, including history of heart attack have had a stroke or have stroke symptoms had a skin reaction (such as a rash) after taking clonidine in a transdermal form (skin patch) have any other medical conditions are pregnant or plan to become pregnant. It is not known if clonidine hydrochloride extended-release tablets will harm your unborn baby.
Talk to your doctor if you are pregnant or plan to become pregnant. There is a pregnancy registry for females who are exposed to ADHD medications, including clonidine hydrochloride extended-release tablets, during pregnancy. The purpose of the registry is to collect information about the health of females exposed to clonidine hydrochloride extended-release tablets and their baby.
If you or your child becomes pregnant during treatment with clonidine hydrochloride extended-release tablets, talk to your healthcare provider about registering with the National Pregnancy Registry of ADHD Medications at 1-866-961-2388 or visit online at https://womensmentalhealth.org/research/pregnancyregistry/adhd-medications/ . are breastfeeding or plan to breastfeed. Clonidine hydrochloride passes into your breast milk. Talk to your doctor about the best way to feed your baby if you take clonidine hydrochloride extended-release tablets.
Tell your doctor about all of the medicines that you take, including prescription and non-prescription medicines, vitamins, and herbal supplements. Clonidine hydrochloride extended-release tablets and certain other medicines may affect each other causing serious side effects. Sometimes the doses of other medicines may need to be changed while taking clonidine hydrochloride extended-release tablets.
Especially tell your doctor if you take: anti-depression medicines heart or blood pressure medicine other medicines that contain clonidine a medicine that makes you sleepy (sedation) Ask your doctor or pharmacist for a list of these medicines, if you are not sure if your medicine is listed above. Know the medicines that you take. Keep a list of your medicines with you to show your doctor and pharmacist when you get a new medicine.
How should I take clonidine hydrochloride extended-release tablets ? Take clonidine hydrochloride extended-release tablets exactly as your doctor tells you to tak… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 0228-4241-06 Clonidine Hydrochloride Extended-Release Tablets, USP 0.1 mg Rx only 60 Tablets Container 0.1 mg, 60 Tablets