
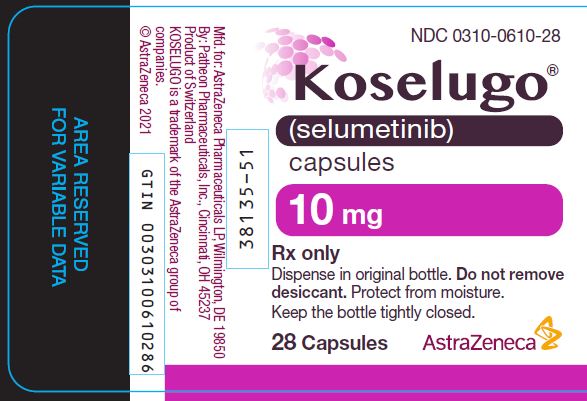
KOSELUGO SELUMETINIB 10 mg Capsule, 28-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Selumetinib is used to treat certain types of neurofibromatosis type 1 (NF1; a nervous system disorder that causes tumors to grow on nerves). Selumetinib is in a class of medications called kinase inhibitors. It works by helping stop tumor growth.
Read the full MedlinePlus article ↗- Koselugo targets plexiform neurofibromas — the large, deep nerve tumors that can grow in people with neurofibromatosis type 1 (NF1) when they can't be removed with surgery and are...
- What exactly is this medication treating — and will it cure my (or my child's) NF1 tumors?
- Most people experience some side effects — diarrhea, nausea, vomiting, and skin rashes (sometimes acne-like) are the most common. These are often manageable: for diarrhea, start an...
- What side effects should I realistically expect, and which ones should I call the doctor about right away?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Selumetinib Sulfate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII 5C69YCD2YJ
Carrageenan is a natural thickener and stabilizer extracted from red seaweed. It's used in medicines to create gel-like textures, improve consistency, and help keep ingredients from separating during storage.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII ND2M416302
Isopropyl alcohol is a clear liquid solvent derived from petroleum. In medicines, it dissolves active ingredients and other components, helps the product flow smoothly, and aids in sterilization during manufacturing.
-
UNII 660YQ98I10
Potassium chloride is a mineral salt used in medicines as a buffer and to help maintain the proper pH balance and stability of the formulation during storage and use.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII O03S90U1F2
A synthetic compound combining vitamin E with polyethylene glycol and succinic acid. It acts as a solubilizer and antioxidant in medicines, helping dissolve poorly water-soluble drugs and prevent degradation of active ingredients.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $96.37 | $2,698.33 / 28 capsules |
| Medicare drug plans payPart D · Q2 2026 | $99.90 | $2,797.27 / 28 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Koselugo 10 mgthis 00310-0610-28 | AstraZeneca | 28 capsules | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12364684 ↗ | Method of use | U-4357 | Mar 26, 2029 |
| US 12364684 ↗ | Method of use | U-4357 | Mar 26, 2029 |
| US 9562017 ↗ | Drug substance | U-4357 | Dec 12, 2026 |
| US 9562017 ↗ | Drug substance | U-4357 | Dec 12, 2026 |
| US 9156795 ↗ | Drug substance | — | Dec 12, 2026 |
| US 11813246 ↗ | Drug product | — | Mar 26, 2029 |
| US 11813246 ↗ | Drug product | — | Mar 26, 2029 |
| US 8178693 ↗ | Drug substance | — | Mar 13, 2026 |
| US 12318367 ↗ | Drug product | — | Mar 26, 2029 |
| US 12220403 ↗ | Drug product | — | Mar 26, 2029 |
| US 7425637 ↗ | Drug substance | — | Mar 13, 2028 |
| US 9156795 ↗ | Drug substance | — | Dec 12, 2026 |
| US 12220403 ↗ | Drug product | — | Mar 26, 2029 |
| US 8178693 ↗ | Drug substance | — | Mar 13, 2026 |
| US 7425637 ↗ | Drug substance | — | Mar 13, 2028 |
| US 12318367 ↗ | Drug product | — | Mar 26, 2029 |
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | Nov 19, 2028 |
| NPP | New Patient Population | Sep 10, 2028 |
| ODE-288 | Orphan Drug Exclusivity (7-year) | Apr 10, 2027 |
| ODE-545 | Orphan Drug Exclusivity (7-year) | Nov 19, 2032 |
| NPP | New Patient Population | Sep 10, 2028 |
| NPP | New Patient Population | Nov 19, 2028 |
| ODE-288 | Orphan Drug Exclusivity (7-year) | Apr 10, 2027 |
| ODE-545 | Orphan Drug Exclusivity (7-year) | Nov 19, 2032 |
Is there a generic version of KOSELUGO 10 MG CAPSULE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00310-0610-28 You're viewing this | 28 CAPSULE in 1 BOTTLE (0310-0610-28) | 2021-06-11 | Active |
| 00310-0610-60 | 60 CAPSULE in 1 BOTTLE (0310-0610-60) | 2020-04-16 | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack accounts for about 3.3% of this product's recent Medicaid fills; most go to the 60 capsules pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 00310-0610-28?
What is the difference between NDC 00310-0610-28 and NDC 00310-0610-60?
What NDC number is used to bill for this package of KOSELUGO SELUMETINIB 10 mg Capsule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE KOSELUGO is indicated for the treatment of adult and pediatric patients 1 year of age and older with neurofibromatosis type 1 (NF1) who have symptomatic, inoperable plexiform neurofibromas (PN) [see Dosage and Administration (2) ]. KOSELUGO is a kinase inhibitor indicated for the treatment of adult and pediatric patients 1 year of age and older with neurofibromatosis type 1 (NF1) who have symptomatic, inoperable plexiform neurofibromas (PN). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • KOSELUGO capsules: The recommended dosage is 25 mg/m 2 , swallowed whole, taken orally twice daily with or without food (see Table 1) . (2.1 , 2.2 ) • KOSELUGO oral granules: The recommended dosage is equivalent to 25 mg/m 2 , sprinkled onto or mixed with soft food and taken orally twice daily (see Table 2). ( 2.1 , 2.2 ) • Moderate hepatic impairment (Child-Pugh B): The recommended dosage is 20 mg/m 2 orally twice daily (see Tables 6 and 7) .
( 2.2 , 2.4 ) • Severe hepatic impairment (Child-Pugh C): The recommended dosage has not been established. ( 2.4 , 8.6 ) • Strong or Moderate CYP3A4 Inhibitors or Fluconazole: If coadministration with strong or moderate CYP3A4 inhibitors or fluconazole cannot be avoided, reduce the dose of KOSELUGO (see Tables 8 and 9) . ( 2.5 )
2.1Recommended Dosage The recommended dosage of KOSELUGO capsules ( see Table 1 ) and KOSELUGO oral granules ( see Table 2 ) for adult and pediatric patients 1 year of age and older, based on body surface area, is 25 mg/m 2 orally twice daily, until disease progression or unacceptable toxicity [see Dosage and Administration (2.2)]. Table 1 Recommended Dosage: KOSELUGO Capsules Body Surface Area The recommended dosage of KOSELUGO capsules for patients with a BSA less than 0.55 m 2 has not been established. KOSELUGO Capsules 0.55 – 0.69 m 2 20 mg in the morning and 10 mg in the evening 0.70 – 0.89 m 2 20 mg twice daily 0.90 – 1.09 m 2 25 mg twice daily 1.10 – 1.29 m 2 30 mg twice daily 1.30 – 1.49 m 2 35 mg twice daily 1.50 – 1.69 m 2 40 mg twice daily 1.70 – 1.89 m 2 45 mg twice daily ≥ 1.90 m 2 50 mg twice daily Table 2 Recommended Dosage: KOSELUGO Oral Granules Body Surface Area The recommended dosage of KOSELUGO oral granules for patients with a BSA less than 0.40 m 2 has not been established.
KOSELUGO Oral Granules 0.40 – 0.59 m 2 12.5 mg twice daily 0.60 – 0.69 m 2 15 mg twice daily 0.70 – 0.89 m 2 20 mg twice daily 0.90 – 1.09 m 2 25 mg twice daily 1.10 – 1.29 m 2 30 mg twice daily 1.30 – 1.49 m 2 35 mg twice daily 1.50 – 1.69 m 2 40 mg twice daily 1.70 – 1.89 m 2 45 mg twice daily ≥ 1.90 m 2 50 mg twice daily
2.2Administration KOSELUGO is available in two dosage forms: KOSELUGO capsules and KOSELUGO oral granules. Prescribe KOSELUGO oral granules for patients who have difficulty swallowing whole capsules. KOSELUGO Capsules • Administer KOSELUGO capsules to patients who can swallow a whole capsule. • Swallow KOSELUGO capsules whole.
Do not open, chew or crush KOSELUGO capsules. • KOSELUGO capsules may be administered with or without food. KOSELUGO Oral Granules Administer KOSELUGO oral granules to patients who have difficulty swallowing a whole capsule. Sprinkle KOSELUGO oral granules on or mix with a small amount (about 1 to 3 teaspoons) of smooth yogurt, or fruit puree containing the following fruits: apple, banana, pear, or strawberry and consume within 30 minutes of preparation.
If not consumed within 30 minutes of preparation, discard and prepare a new dose. If a dose has been partially consumed within 30 minutes of preparation, discard the remainder of the dose and do not prepare a new dose, aim to complete dosing within 30 minutes next time. The KOSELUGO oral granules should be free-flowing.
Do NOT use if the oral granules are clumped or stuck inside the capsule shell. Instruct the patient or caregiver to contact their pharmacy if this happens. Discard the empty capsule shells after use.
Do NOT swallow, chew, or dissolve the capsule shells of KOSELUGO oral granules. Do NOT chew or crush the KOSELUGO oral granules. Do NOT add oral granules to liquids.
Do NOT mix KOSELUGO oral granules in grapefruit or any juice, fruit puree or jam containing Seville orange. Missed Dose If a dose of KOSELUGO capsules or KOSELUGO oral granules is missed, make up that dose unless the next dose is due within 6 hours. Vomiting If vomiting occurs after taking a dose of KOSELUGO capsules or KOSELUGO oral granules, do not take an additional dose…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: • 10 mg selumetinib: white to off-white, opaque, hard capsule sealed with a clear band and marked with “SEL 10” in black ink. • 25 mg selumetinib: blue, opaque, hard capsule sealed with a clear band and marked with “SEL 25” in black ink. Oral Granules: • 5 mg selumetinib: off-white to light-yellow free-flowing oral granules contained within capsules. The capsules have a yellow cap and white body.
The cap is printed with “sel 5” in black ink, and body is printed with a sprinkle capsule image indicating opening. • 7.5 mg selumetinib: off-white to light-yellow free-flowing oral granules contained within capsules. The capsules have a pink cap and white body. The cap is printed with “sel 7.5” in black ink, and body is printed with a sprinkle capsule image indicating opening. • Capsules: 10 mg and 25 mg of selumetinib.
( 3 ) • Oral Granules: 5 mg and 7.5 mg of selumetinib. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Left Ventricular Dysfunction : Assess ejection fraction prior to initiating treatment, every 3 months during the first year, then every 6 months thereafter and as clinically indicated. Withhold, reduce the dose, or permanently discontinue KOSELUGO based on severity of adverse reaction. ( 2.3 , 5.1 ) • Ocular Toxicity : Conduct ophthalmic assessments prior to initiating KOSELUGO, at regular intervals during treatment and for new or worsening visual changes.
Permanently discontinue KOSELUGO for retinal vein occlusion (RVO). Withhold KOSELUGO for retinal pigment epithelial detachment (RPED), monitor with optical coherence tomography assessments until resolution, and resume at reduced dose. ( 2.3 , 5.2 ) • Gastrointestinal Toxicity : Advise patients to start an anti-diarrheal agent immediately after the first episode of loose stool and to increase fluid intake.
Withhold, reduce the dose, or permanently discontinue KOSELUGO based on severity of adverse reaction. ( 2.3 , 5.3 ) • Skin Toxicity : Monitor for severe skin rashes. Withhold, reduce the dose, or permanently discontinue KOSELUGO based on severity of adverse reaction.
( 2.3 , 5.4 ) • Increased Creatine Phosphokinase (CPK) : Increased CPK and rhabdomyolysis can occur. Obtain serum CPK prior to initiating KOSELUGO, periodically during treatment, and as clinically indicated. If increased CPK occurs, evaluate for rhabdomyolysis or other causes.
Withhold, reduce the dose, or permanently discontinue KOSELUGO based on severity of adverse reaction. ( 2.3 , 5.5 ) • Increased Vitamin E Levels and Increased Risk of Bleeding (KOSELUGO Capsules) : KOSELUGO capsules contain vitamin E and daily intake of vitamin E that exceeds the recommended or safe limits may increase the risk of bleeding. An increased risk of bleeding may occur in patients co-administered vitamin-K antagonists or anti-platelet agents.
KOSELUGO oral granules do not contain vitamin E. ( 5.6 ) • Embryo-Fetal Toxicity: Can cause fetal harm. Advise patients of reproductive potential of the potential risk to a fetus and to use effective contraception ( 5.7 , 8.1 , 8.3 ).
5.1Left Ventricular Dysfunction KOSELUGO can cause cardiomyopathy, defined as a decrease in left ventricular ejection fraction (LVEF) ≥ 10% below baseline. KOSELUGO has not been studied in patients with a history of clinically significant cardiac disease or LVEF less than 55% prior to treatment. Pediatric Patients In the NF1 PN pediatric safety pool (N = 134) [see Adverse Reactions (6.1) ], Grade 2 LVEF decrease [Grade 2 LVEF decrease (40% to 50%; 10 to 19% drop from baseline)], based on reported adverse reactions, occurred in 17% of evaluable patients.
Decreased LVEF of ≥ 20% occurred in 0.7% of patients and resulted in dose interruption and dose reduction. Decreased LVEF resolved in 75% of these patients. The median time to first onset of maximum CTCAE grade LVEF decrease was approximately 12 months (median duration approximately 3 months).
Adult Patients In the KOMET adult NF1 PN study (N = 71) [see Adverse Reactions (6.1) ], Grade 2 LVEF decrease [Grade 2 LVEF decrease (40% to 50%; 10 to 19% drop from baseline)], based on echocardiogram results, occurred in 14% of evaluable patients. Decreased LVEF resulted in dose interruption in 1.4% of patients. The median time to first onset of maximum CTCAE grade LVEF decrease was approximately 4 months (median duration approximately 4 months).
Assess ejection fraction by echocardiogram prior to initiating treatment, every 3 months during the first year of treatment, every 6 months thereafter, and as clinically indicated. Withhold, reduce dose, or permanently discontinue KOSELUGO based on severity of adverse reaction [see Dosage and Administration (2.3)]. In patients who interrupt KOSELUGO for decreased LVEF, obtain an echocardiogram or a cardiac MRI every 3 to 6 weeks until resolution.
Upon resolution of decreased LVEF to greater than or equal to the institutional LLN, obtain an echocar…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Left Ventricular Dysfunction [see Warnings and Precautions (5.1) ] • Ocular Toxicity [see Warnings and Precautions (5.2) ] • Gastrointestinal Toxicity [see Warnings and Precautions (5.3) ] • Skin Toxicity [see Warnings and Precautions (5.4) ] • Increased Creatine Phosphokinase [see Warnings and Precautions (5.5) ] Most common adverse reactions in pediatric patients (≥ 40%) are: vomiting, diarrhea, increased creatine phosphokinase, dry skin, paronychia, nausea, dermatitis acneiform, and pyrexia.
( 6.1 ) Most common adverse reactions in adult patients (≥ 40%) are rash (all), dermatitis acneiform, and diarrhea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca 1-800-236-9933 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The NF1 PN pediatric safety pool described in the WARNINGS AND PRECAUTIONS reflects exposure to KOSELUGO at the recommended dosage in 134 pediatric patients in SPRINKLE (N = 36) (NCT05309668), SPRINT Phase I (N = 24) (NCT01362803), SPRINT Phase II Stratum 1 (N = 50) [see Clinical Studies (14.1) ] , and Phase I Food Effect Study (N = 24) (NCT05101148).
Among pediatric patients, the duration of KOSELUGO exposure was 12 months or longer (80%), more than 2 years (44%), or more than 3 years (37%). The most common adverse reactions in pediatric patients (≥ 40%) are vomiting, diarrhea, increased creatine phosphokinase, dry skin, paronychia, nausea, dermatitis acneiform, and pyrexia. In the KOMET adult NF1 PN study, 71 adult patients received KOSELUGO at the recommended dosage [see Clinical Studies (14.1) ] .
Among adult patients, the duration of KOSELUGO exposure in the randomized period was 6 months or longer (92%), and 11 months or longer (66%). The most common adverse reactions in adult patients (≥ 40%) are rash (all), dermatitis acneiform, and diarrhea. Neurofibromatosis Type 1 (NF1) with Inoperable Plexiform Neurofibromas (PN) Pediatrics 2-18 years of Age (SPRINT Phase II Stratum 1) The safety of KOSELUGO was evaluated in SPRINT Phase II Stratum 1 [see Clinical Studies (14.1) ] .
Eligible patients were 2-18 years of age with neurofibromatosis type 1 (NF1) who had inoperable plexiform neurofibromas (PN) that was causing significant morbidity. Patients were excluded for abnormal LVEF, uncontrolled hypertension (blood pressure ≥ the 95th percentile for age, height, and sex), any current or past history of RVO or RPED, intraocular pressure > 21 mmHg (or upper limit of normal adjusted by age), uncontrolled glaucoma, and inability to swallow whole capsules. Patients received KOSELUGO 25 mg/m 2 orally twice daily (N = 50).
Among these patients, 88% were exposed for 12 months or longer and 66% were exposed for greater than 2 years. Serious adverse reactions occurred in 24% of patients who received KOSELUGO. Serious adverse reactions that occurred in 2 or more patients were anemia, hypoxia and diarrhea.
Permanent discontinuation due to an adverse reaction occurred in 12% of patients who received KOSELUGO. Adverse reactions resulting in permanent discontinuation of KOSELUGO included increased blood creatinine, increased weight, diarrhea, paronychia, malignant peripheral nerve sheath tumor, acute kidney injury, and skin ulcer. Dosage interruptions and dose reductions due to adverse reactions occurred in 80% and 24% of patients who received KOSELUGO, respectively.
Adverse reactions requiring a dosage interruption or reduction in ≥ 5% of patients were vomiting, paronychia, diarrhea, nausea, abdominal pain, rash, skin infection, influenza-like illness, pyrexia and weight gain. The most common adverse rea…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong or Moderate CYP3A4 Inhibitors or Fluconazole : Avoid coadministration of strong or moderate CYP3A4 inhibitors or fluconazole with KOSELUGO. If coadministration cannot be avoided, reduce the dose of KOSELUGO. ( 2.5 , 7.1 ) • Strong or Moderate CYP3A4 Inducers : Avoid concomitant use of strong and moderate CYP3A4 inducers. ( 7.1 )
7.1Effect of Other Drugs on KOSELUGO Strong or Moderate CYP3A4 Inhibitors or Fluconazole Management • Avoid concomitant use of strong or moderate CYP3A4 inhibitors or fluconazole with KOSELUGO. If coadministration with strong or moderate CYP3A4 inhibitors or fluconazole cannot be avoided, reduce KOSELUGO dosage [see Dosage Modifications for Drug Interactions (2.5) ]. Clinical Impact • Concomitant use of KOSELUGO with a strong or moderate CYP3A4 inhibitor or fluconazole increased selumetinib plasma concentrations [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions.
Strong or Moderate CYP3A4 Inducers Management • Avoid concomitant use of strong or moderate CYP3A4 inducers with KOSELUGO. Clinical Impact • Concomitant use of KOSELUGO with a strong or moderate CYP3A4 inducer decreased selumetinib plasma concentrations [see Clinical Pharmacology (12.3) ] , which may reduce KOSELUGO efficacy. Vitamin E Management • Supplemental vitamin E is not recommended if daily vitamin E intake (including the amount of vitamin E in KOSELUGO capsules and supplement) will exceed the recommended or safe limits. • Monitor for bleeding in patients administered a vitamin‑K antagonist or an anti‑platelet agent with KOSELUGO capsules.
Increase INR monitoring, as appropriate, in patients taking a vitamin‑K antagonist [see Warnings and Precautions (5.3) ] . Clinical Impact • KOSELUGO capsules contain vitamin E and daily vitamin E intake that exceeds the recommended or safe limits may increase the risk of bleeding. An increased risk of bleeding may occur in patients taking a vitamin‑K antagonist or an anti‑platelet agent with KOSELUGO capsules.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Advise not to breastfeed. (8.2)
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1) ] , KOSELUGO can cause fetal harm when administered to a pregnant woman. There are no available data on the use of KOSELUGO in pregnant women to evaluate drug-associated risk. In animal reproduction studies, administration of selumetinib to mice during organogenesis caused reduced fetal weight, adverse structural defects, and effects on embryofetal survival at exposures approximately > 5 times the human exposure at the clinical dose of 25 mg/m 2 twice daily ( see Data ).
Advise pregnant women of the potential risk to the fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data In KOMET, a first trimester spontaneous abortion was reported in a patient receiving KOSELUGO.
Animal Data In embryo-fetal development studies in mice at doses > 2.5 mg/kg twice daily (~5-times the human exposure based on area under the curve [AUC] at the clinical dose of 25 mg/m 2 twice daily), selumetinib caused increases in post-implantation loss, a reduction in mean fetal and litter weights, and an increased occurrence of open eye and cleft palate, but did not induce significant maternal toxicity. Administration of selumetinib to pregnant mice from gestation Day 6 through lactation Day 20 resulted in reduced pup body weights and fewer pups met the pupil constriction criterion on day 21 post-partum.
The incidence of malformations (e.g., prematurely open eye(s) and cleft palate) was increased even at the lowest dose of 0.5 mg/kg twice daily (maternal maximal concentration [C max ] of ~0.6 times the human C max at the clinical dose of 25 mg/m 2 twice daily).
8.2Lactation Risk Summary There are no data on the presence of selumetinib or its active metabolite in human milk or their effects on the breastfed child or milk production. Selumetinib and its active metabolite were present in the milk of lactating mice ( see Data ). Due to the potential for adverse reactions in a breastfed child, advise women not to breastfeed during treatment with KOSELUGO and for 1 week after the last dose.
Data Animal Data Selumetinib and its active metabolite were present in milk from mice dosed with selumetinib throughout gestation and lactation, with a mean plasma/milk ratio of 1.5 in lactating dams dosed at 5 mg/kg twice daily. Administration of selumetinib to dams during gestation and early lactation was associated with adverse events in pups, including reduced growth rates and incidence of malformations [see Use in Specific Populations (8.1) ].
8.3Females and Males of Reproductive Potential KOSELUGO can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating KOSELUGO [see Use in Specific Populations (8.1) ] . Contraception Females Advise females of reproductive potential to use effective contraception during treatment and for 1 week after the last dose.
Males Advise male patients with female partners of reproductive potential to use effective contraception during treatment with KOSELUGO and for 1 week after the last dose.
8.4Pediatric Use The safety and effectiveness have been established in pediatric patients 1 year of age and older with NF1 who have inoperable PN and the information on this use is discussed throughout the labeling. The safety and effectiveness of KOSELUGO have not been established in pediatric patients younger than 1 year of age. Animal Toxicity Data In 3-month general toxicology studies, male rats receiving selumetinib at doses ≥ 10 mg/kg daily (~60-times the human exposure based on AUC at the clinical dose of 25 mg/m 2 twice daily) showed growth plate dysplasia.
8.…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1) ] , KOSELUGO can cause fetal harm when administered to a pregnant woman. There are no available data on the use of KOSELUGO in pregnant women to evaluate drug-associated risk. In animal reproduction studies, administration of selumetinib to mice during organogenesis caused reduced fetal weight, adverse structural defects, and effects on embryofetal survival at exposures approximately > 5 times the human exposure at the clinical dose of 25 mg/m 2 twice daily ( see Data ).
Advise pregnant women of the potential risk to the fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data In KOMET, a first trimester spontaneous abortion was reported in a patient receiving KOSELUGO.
Animal Data In embryo-fetal development studies in mice at doses > 2.5 mg/kg twice daily (~5-times the human exposure based on area under the curve [AUC] at the clinical dose of 25 mg/m 2 twice daily), selumetinib caused increases in post-implantation loss, a reduction in mean fetal and litter weights, and an increased occurrence of open eye and cleft palate, but did not induce significant maternal toxicity. Administration of selumetinib to pregnant mice from gestation Day 6 through lactation Day 20 resulted in reduced pup body weights and fewer pups met the pupil constriction criterion on day 21 post-partum.
The incidence of malformations (e.g., prematurely open eye(s) and cleft palate) was increased even at the lowest dose of 0.5 mg/kg twice daily (maternal maximal concentration [C max ] of ~0.6 times the human C max at the clinical dose of 25 mg/m 2 twice daily).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness have been established in pediatric patients 1 year of age and older with NF1 who have inoperable PN and the information on this use is discussed throughout the labeling. The safety and effectiveness of KOSELUGO have not been established in pediatric patients younger than 1 year of age. Animal Toxicity Data In 3-month general toxicology studies, male rats receiving selumetinib at doses ≥ 10 mg/kg daily (~60-times the human exposure based on AUC at the clinical dose of 25 mg/m 2 twice daily) showed growth plate dysplasia.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of KOSELUGO did not include a sufficient number of patients aged 65 and over to determine whether they respond differently from younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Dialysis is not effective as KOSELUGO is highly protein bound and is extensively metabolized.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Selumetinib is an inhibitor of mitogen-activated protein kinase kinases 1 and 2 (MEK1/2). MEK1/2 proteins are upstream regulators of the extracellular signal-related kinase (ERK) pathway. Both MEK and ERK are critical components of the RAS-regulated RAF-MEK-ERK pathway, which is often activated in different types of cancers.
In genetically modified mouse models of NF1 that generate neurofibromas that recapitulate the genotype and phenotype of human NF1, oral dosing of selumetinib inhibited ERK phosphorylation, and reduced neurofibroma numbers, volume, and proliferation.
12.2Pharmacodynamics The exposure-response relationship and time course of pharmacodynamic response for the safety and effectiveness of KOSELUGO have not been fully characterized. Cardiac Electrophysiology At a dose 1.5-times the maximum recommended dose, clinically significant QTc interval prolongation was not observed.
12.3Pharmacokinetics Selumetinib pharmacokinetics were observed at steady state in adult and pediatric patients with NF1 and are presented as mean (CV%) unless otherwise indicated. The maximum plasma concentration (C max ) is 792 (49) ng/mL and systemic exposure (AUC) is 2141 (55) ng•h/mL following KOSELUGO 25 mg/m 2 twice daily. Selumetinib AUC and C max increases in a dose proportional manner over a dose range from 20 mg/m 2 to 30 mg/m 2 (0.8 to 1.2 times the recommended dose).
Selumetinib accumulation range is 1.2-1.5 fold following administration of KOSELUGO at 25 mg/m 2 . At the recommended dosage of 25 mg/m 2 of KOSELUGO oral granules (sprinkled on smooth yogurt, smooth fruit sauce, smooth fruit puree, or smooth fruit jam) twice daily in pediatric patients (> 1 year old to < 7 years old), the AUC 0-24h following the first dose of KOSELUGO oral granules was within the range of that in patients administered KOSELUGO capsules. No clinically relevant differences in the pharmacokinetics of selumetinib were observed following administration of a single-dose of either the granule or capsule dosage forms of KOSELUGO at equivalent dosages, under fasted and fed conditions, in healthy adults.
Absorption Selumetinib absolute oral bioavailability is 62%. Selumetinib median (min, max) time to maximum plasma concentrations (Tmax) is 1.5 (0.22, 6.0) hours. Effect of Food No clinically significant differences in selumetinib pharmacokinetics were observed following administration of low fat (400-500 calories) or high-fat (800-1000 calories) meal.
Distribution Selumetinib apparent volume of distribution across a dose range of 20 mg/m 2 to 30 mg/m 2 (0.8 to 1.2 times the recommended dosage) ranges from 40 L-3710 L (66). The plasma protein binding is 98.4% (primarily albumin). Elimination Selumetinib elimination half-life is 9 (28) hours with an apparent (oral) clearance of 16 (44) L/hr/m 2 .
Metabolism Selumetinib is primarily metabolized by CYP3A4 and to a lesser extent by CYP2C19, CYP1A2, CYP2C9, CYP2E1, and CYP3A5. Selumetinib also undergoes glucuronidation by UGT1A1 and UGT1A3. It is estimated that 56% of the observed intrinsic clearance of selumetinib can be attributed to CYP metabolism and about 29% to direct glucuronidation by UGT enzymes.
The active metabolite, N desmethyl selumetinib, is generated by CYP2C19 and CYP1A2 with additional contribution by CYP2C9 and CYP2A6, and it is metabolized through the same routes as selumetinib. N-desmethyl selumetinib represents < 10% of selumetinib levels in human plasma, but is approximately 3- to 5- times more potent than the parent compound, contributing to about 21% to 35% of the overall pharmacologic activity. Excretion After a single oral dose of radiolabeled selumetinib 75 mg (1.5-times the recommended dose) to healthy adults, 59% of the dose was recovered in feces (19% as unchanged) and 33% in urine (< 1% as parent).
Specific Populations No clinically significant differences in the pharmacokinetics of selumetinib or N-desmethyl selumetinib were observed…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Selumetinib is an inhibitor of mitogen-activated protein kinase kinases 1 and 2 (MEK1/2). MEK1/2 proteins are upstream regulators of the extracellular signal-related kinase (ERK) pathway. Both MEK and ERK are critical components of the RAS-regulated RAF-MEK-ERK pathway, which is often activated in different types of cancers.
In genetically modified mouse models of NF1 that generate neurofibromas that recapitulate the genotype and phenotype of human NF1, oral dosing of selumetinib inhibited ERK phosphorylation, and reduced neurofibroma numbers, volume, and proliferation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Selumetinib Capsules Strength Description Capsules per Bottle NDC Number 10 mg White to off-white, opaque, hard capsule sealed with a clear band and marked with “SEL 10” in black ink. 60 0310-0610-60 28 0310-0610-28 25 mg Blue, opaque, hard capsule sealed with a clear band and marked with “SEL 25” in black ink. 60 0310-0625-60 28 0310-0625-28 Selumetinib Oral Granules Strength Description Capsules per Bottle NDC Number 5 mg Off‑white to light‑yellow free‑flowing oral granules contained within capsules.
The capsules have a yellow cap and white body. The cap is printed with “sel 5” in black ink, and body is printed with a sprinkle capsule image indicating opening. 60 0310‑0635‑60 7.5 mg Off‑white to light‑yellow free‑flowing oral granules contained within capsules.
The capsules have a pink cap and white body where the cap is printed with “sel 7.5” in black ink, and body is printed with a sprinkle capsule image indicating opening. 60 0310‑0640‑60 Storage KOSELUGO Capsules Store KOSELUGO capsules at 20°C to 25°C (68°F to 77°F) with excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Dispense and store in the original bottle to protect from light and moisture.
Do not remove desiccant. Keep the bottle tightly closed after first opening. KOSELUGO Oral Granules Store and transport KOSELUGO oral granules refrigerated at 2°C to 8°C (36°F to 46°F).
After receipt, patients may store at room temperature 20°C to 25°C (68°F to 77°F). Do NOT exceed 30°C (86°F). KOSELUGO oral granules may clump together or stick to the capsule shell if exposed to high temperatures, which may lead to underdose.
Dispense and store in the original bottle to protect from light and moisture. Do not remove desiccant. Keep the bottle tightly closed after first opening.
📋 Description ▾
11 DESCRIPTION KOSELUGO contains selumetinib sulfate, a kinase inhibitor. The chemical name is 5-[(4-bromo-2-chlorophenyl)amino]-4-fluoro-6-[(2-hydroxyethoxy)carbamoyl]-1-methyl-1 H -benzimidazol-3-ium hydrogen sulfate. The molecular formula for selumetinib sulfate is C 17 H 17 BrClFN 4 O 7 S and the relative molecular mass is 555.76 g/mol.
Selumetinib sulfate has the following structural formula: Selumetinib sulfate is a white to yellow monomorphic crystalline powder that exhibits a pH dependent solubility. Selumetinib sulfate is freely soluble at pH < 1.5, sparingly soluble in the pH range at 1.5 to 3 and slightly soluble at pH > 3. Selumetinib sulfate has two ionizable functions with pKa values of 2.8 and 8.4.
KOSELUGO (selumetinib) 10 mg capsules for oral use, contain 10 mg selumetinib (equivalent to 12.1 mg selumetinib sulfate) and the excipient, vitamin E polyethylene glycol succinate. The capsule shell contains carnauba wax, carrageenan, hypromellose, potassium chloride, purified water, and titanium dioxide. The capsule is imprinted with black ink that contains ammonium hydroxide, iron oxide black, propylene glycol, and shellac.
KOSELUGO (selumetinib) 25 mg capsules for oral use, contain 25 mg selumetinib (equivalent to 30.25 mg selumetinib sulfate) and the excipient, vitamin E polyethylene glycol succinate. The capsule shell contains carnauba wax and/or cornstarch, carrageenan, FD&C blue 2, ferric oxide yellow, hypromellose, potassium chloride, purified water, and titanium dioxide. The capsule is imprinted with black ink that contains carnauba wax, FD&C Blue 2 aluminum lake, ferric oxide red, ferric oxide yellow, glyceryl monooleate, and shellac.
KOSELUGO (selumetinib) 5 mg oral granules contain 5 mg selumetinib (equivalent to 6.05 mg selumetinib sulfate). The uncoated cores contain selumetinib sulfate, glyceryl dibehenate, and stearoyl polyoxylglycerides. The granule coating contains acetone, hypromellose acetate succinate, and stearic acid.
The capsule shell contains ferric oxide yellow, hypromellose, and titanium dioxide. The capsule shell is imprinted with black ink that contains butyl alcohol, dehydrated alcohol, ferric oxide black, isopropyl alcohol, potassium hydroxide, propylene glycol, purified water, shellac, and strong ammonia solution. KOSELUGO (selumetinib) 7.5 mg oral granules contain 7.5 mg selumetinib (equivalent to 9.08 mg selumetinib sulfate).
The uncoated cores contain selumetinib sulfate, glyceryl dibehenate, and stearoyl polyoxylglycerides. The granule coating contains acetone, hypromellose acetate succinate, and stearic acid. The capsule shell contains ferric oxide red, hypromellose, and titanium dioxide.
The capsule shell is imprinted with black ink that contains butyl alcohol, dehydrated alcohol, ferric oxide black, isopropyl alcohol, potassium hydroxide, propylene glycol, purified water, shellac, and strong ammonia solution. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Left Ventricular Dysfunction Advise patients and caregivers that KOSELUGO can cause a reduction in LVEF and to immediately report any signs or symptoms of cardiomyopathy to their healthcare provider [see Warnings and Precautions (5.1) ] . Ocular Toxicity Advise patients and caregivers that KOSELUGO can cause ocular toxicity that can lead to blindness and to contact their healthcare provider if the patient experiences any changes in their vision [see Warnings and Precautions (5.2) ] .
Gastrointestinal Toxicity Advise patients and caregivers that KOSELUGO can cause diarrhea, nausea, vomiting, and stomatitis and to contact their healthcare provider at the first sign of gastrointestinal toxicity [see Warnings and Precautions (5.3) ] . Skin Toxicity Advise patients and caregivers that KOSELUGO can cause serious skin toxicities and to contact their healthcare provider for severe skin changes [see Warnings and Precautions (5.4) ] . Increased Creatine Phosphokinase Advise patients and caregivers that KOSELUGO can cause increased CPK and rhabsomyolysis to report any signs and symptoms of muscle pain or weakness to their healthcare provider [see Warnings and Precautions (5.5) ] .
Increased Vitamin E Levels and Increased Risk of Bleeding (KOSELUGO Capsules) Advise patients and caregivers to notify their healthcare provider if they are taking a supplement containing vitamin E, a vitamin-K antagonist or an anti-platelet agent [see Warnings and Precautions (5.6) ] . Embryo-Fetal Toxicity • Advise pregnant women and females of reproductive potential of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.7) , Use in Specific Populations (8.1) ]. • Advise females of reproductive potential to use effective contraception during treatment with KOSELUGO and for 1 week after the last dose [see Use in Specific Populations (8.3) ] . • Advise males with female partners of reproductive potential to use effective contraception during treatment with KOSELUGO and for 1 week after the last dose [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] .
Lactation Advise women not to breastfeed during treatment with KOSELUGO and for 1 week after the last dose [see Use in Specific Populations (8.2) ] . Drug Interactions Advise patients and caregivers to inform their healthcare provider of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products. Inform patients to avoid St.
John’s wort, grapefruit or grapefruit juice, and Seville orange while taking KOSELUGO [see Drug Interactions (7) ] . Dosing and Administration Inform patients and caregivers on how to take KOSELUGO and what to do for missed or vomited doses [see Dosage and Administration (2.1) ] . Distributed by: AstraZeneca Pharmaceuticals LP Wilmington, DE 19850 © AstraZeneca 20XX