
Ipratropium Bromide .5 mg/2.5mL Solution — NDC 0378-7970-93 (Billing 00378-7970-93)
This is a package of Ipratropium Bromide .5 mg/2.5mL Solution from Mylan Pharmaceuticals Inc., marketed since Nov 2010 and currently FDA-listed; retail pharmacies pay about $0.1122 per mL (NADAC).
NDC database record
One package, one record: these facts belong to NDC 0378-7970-93 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0378 labeler · 7970 product · 93 package
- Package marketed since
- Nov 9, 2010
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0378797093 2
- Medicaid fills, this package
- 11,062 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 021700
- GCN: 42235
- GPI-14 (Medi-Span): 44100030102020
- HICL (First Databank): 000057
- AHFS class code: 12:08.08.00
- RxCUI (RxNorm): 836358
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Anticholinergic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Ipratropium oral inhalation is used to prevent wheezing, shortness of breath, coughing, and chest tightness in people with chronic obstructive pulmonary disease (COPD; a group of diseases that affect the lungs and airways) such as chronic bronchitis (swelling of the air passages that lead to the lungs) and emphysema (damage to the air sacs in the lungs). Ipratropium is in a class of medications called bronchodilators. It works by relaxing and opening the air passages to the lungs to make breathing easier.
Read the full MedlinePlus article ↗- No, the ipratropium inhaler (like Atrovent HFA) is a maintenance medicine — it's meant to be used regularly every day to keep your airways open, not as a rescue inhaler during a su...
- My doctor gave me an ipratropium inhaler — can I use it when I have a sudden asthma attack?
- It depends on why you're using it. For a common cold, safety and effectiveness have only been established for up to 4 days. For seasonal allergies (hay fever), it's been studied fo...
- The nasal spray helps my runny nose, but can I keep using it past a week?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.112 | $8.42 / 75 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.1528 | $11.46 / 75 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.1185 | $8.89 / 75 ml |
| Medicare Part B allowsASP · J7644 | $0.444 / J7644 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00378-7970-52 0378-7970-52 Main listing | 1 POUCH in 1 CARTON / 25 AMPULE in 1 POUCH / 2.5 mL in 1 AMPULE | $0.1040 / mL | $6.50 | 2010-11-09 | — | Active |
| 00378-7970-55 0378-7970-55 | 30 POUCH in 1 CARTON / 1 AMPULE in 1 POUCH / 2.5 mL in 1 AMPULE | $0.1122 / mL | $8.42 | 2010-11-09 | — | Active |
| 00378-7970-91 0378-7970-91 | 2 POUCH in 1 CARTON / 30 AMPULE in 1 POUCH / 2.5 mL in 1 AMPULE | $0.1099 / mL | $16.49 | 2010-11-09 | — | Active |
| 00378-7970-93 You're viewing this | 1 POUCH in 1 CARTON / 30 AMPULE in 1 POUCH / 2.5 mL in 1 AMPULE | $0.1122 / mL | $8.42 | 2010-11-09 | — | Active |
Per mL, this pack runs about 8% above the cheapest pack (NDC 00378-7970-52, $0.1040 vs $0.1122 NADAC).
This pack accounts for about 15% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Ipratropium Bromide .5 mg/2.5mL Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ipratropium Bromide .5 mg/2.5mL 47335-0706-49 | Sun | 5 pouches | $0.095 | — | FDA listed | save 15% |
| Ipratropium Bromide .5 mg/2.5mL 64980-0640-02 | Rising | 1 pouch | $0.104 | AN | Availability likely | save 7% |
| Ipratropium Bromide .5 mg/2.5mLthis 00378-7970-93 | Mylan | 1 pouch | $0.112 | AN | Availability likely | — |
| Ipratropium Bromide .5 mg/2.5mL 00487-9801-01 | Nephron | 30 pouches | $0.112 | AN | Availability likely | — |
| Ipratropium Bromide .5 mg/2.5mL 60687-0394-83 | American | 30 pouches | $0.112 | AN | Availability likely | — |
| Ipratropium Bromide .5 mg/2.5mL 76204-0100-01 | Ritedose | 30 pouches | $0.112 | AN | Availability likely | — |
| Ipratropium Bromide .5 mg/2.5mL 62135-0830-84 | Chartwell | 6 pouches | $0.114 | AN | Availability likely | +1% |
| Ipratropium Bromide .5 mg/2.5mL 50090-0668-00 | A-S | 1 pouch | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 50090-6373-00 | A-S | 25 pouches | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 55154-2134-05 | Cardinal | 5 pouches | — | AN | FDA listed | — |
| Ipratropium bromide .5 mg/2.5mL 65862-0905-03 | Aurobindo | 30 pouches | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 67296-2246-01 | Redpharm | 1 pouch | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 68071-3769-02 | NuCare | 25 ampules | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 55154-4411-05 | Cardinal | 5 pouches | — | AN | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Ipratropium inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Mylan Pharmaceuticals Inc. labeler code 00378
- Ethynodiol Diacetate and Ethinyl Estradiol Kit NDC 0378-7306-53
- Ethynodiol Diacetate and Ethinyl Estradiol Kit NDC 0378-7307-53
- Levonorgestrel and Ethinyl Estradiol Kit NDC 0378-7316-85
- BREYNA Budesonide and Formoterol Fumarate 80 ug; 4.5 ug Aerosol, Metered NDC 0378-7502-32
- BREYNA Budesonide and Formoterol Fumarate 160 ug; 4.5 ug Aerosol, Metered NDC 0378-7503-32
- Difluprednate .5 mg/mL Emulsion NDC 0378-7518-35
- Lansoprazole 15 mg Capsule, Delayed Release Pellets NDC 0378-8015-93
- Fluvastatin Sodium 20 mg Capsule NDC 0378-8020-77
- Fluvastatin Sodium 40 mg Capsule NDC 0378-8021-77
- Lansoprazole 30 mg Capsule, Delayed Release Pellets NDC 0378-8030-05
- Halcinonide 1 mg/g Cream NDC 0378-8056-49
- Glucagon Kit NDC 0378-8067-90
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Ipratropium Bromide Inhalation Solution administered either alone or with other bronchodilators, especially beta adrenergics, is indicated as a bronchodilator for maintenance treatment of bronchospasm associated with chronic obstructive pulmonary disease, including chronic bronchitis and emphysema.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The usual dosage of ipratropium bromide inhalation solution is 500 mcg (1 Unit-Dose Vial) administered three to four times a day by oral nebulization, with doses 6 to 8 hours apart. Ipratropium bromide inhalation solution unit-dose vials contain 500 mcg ipratropium bromide, USP anhydrous in 2.5 mL normal saline. Ipratropium bromide inhalation solution can be mixed in the nebulizer with albuterol or metaproterenol if used within one hour.
Drug stability and safety of Ipratropium Bromide Inhalation Solution when mixed with other drugs in a nebulizer have not been established.
⛔ Contraindications ▾
CONTRAINDICATIONS Ipratropium bromide is contraindicated in known or suspected cases of hypersensitivity to ipratropium bromide, or to atropine and its derivatives.
⚠️ Warnings ▾
WARNINGS The use of ipratropium bromide inhalation solution as a single agent for the relief of bronchospasm in acute COPD exacerbation has not been adequately studied. Drugs with faster onset of action may be preferable as initial therapy in this situation. Combination of ipratropium bromide and beta agonists has not been shown to be more effective than either drug alone in reversing the bronchospasm associated with acute COPD exacerbation.
Immediate hypersensitivity reactions may occur after administration of ipratropium bromide, as demonstrated by rare cases of urticaria, angioedema, rash, bronchospasm and oropharyngeal edema.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reaction information concerning ipratropium bromide inhalation solution is derived from 12-week active-controlled clinical trials. Additional information is derived from foreign post-marketing experience and the published literature. All adverse events, regardless of drug relationship, reported by three percent or more patients in the 12-week controlled clinical trials appear in the table below.
Additional adverse reactions reported in less than three percent of the patients treated with ipratropium bromide include tachycardia, palpitations, eye pain, urinary retention, urinary tract infection and urticaria. Cases of precipitation or worsening of narrow-angle glaucoma, mydriasis, and acute eye pain have been reported. Lower respiratory adverse reactions (bronchitis, dyspnea and bronchospasm) were the most common events leading to discontinuation of ipratropium bromide therapy in the 12-week trials.
Headache, mouth dryness and aggravation of COPD symptoms are more common when the total daily dose of ipratropium bromide equals or exceeds 2,000 mcg. Allergic-type reactions such as skin-rash, angioedema of tongue, lips and face, urticaria, laryngospasm and anaphylactic reaction have been reported. Many of the patients had a history of allergies to other drugs and/or foods.
All Adverse Events, from a Double-blind, Parallel, 12-week Study of patients with COPD All adverse events, regardless of drug relationship, reported by three percent or more patients in the 12-week controlled clinical trials. PERCENT OF PATIENTS Ipratropium Metaproterenol Ipratropium/Metaproterenol Albuterol Ipratropium/Albuterol (500 mcg t.i.d.) (15 mg t.i.d.) (500 mcg t.i.d./15 mg t.i.d.) (2.5 mg t.i.d.) (500 mcg t.i.d./2.5 mg t.i.d.) n = 219 n = 212 n = 108 n = 205 n = 100 Body as a Whole-General Disorders Headache 6.4 5.2 6.5 6.3
9.0Pain 4.1 3.3 0.9 2.9
5.0Influenza-like symptoms 3.7 4.7 6.5 0.5
1.0Back Pain 3.2 1.9 1.9 2.4
0.0Chest Pain 3.2 4.2 5.6 2.0
1.0Cardiovascular Disorders Hypertension/Hypertension Aggravated 0.9 1.9 0.9 1.5
4.0Central & Peripheral Nervous System Dizziness 2.3 3.3 1.9 3.9
4.0Insomnia 0.9 0.5 4.6 1.0
1.0Tremor 0.9 7.1 8.3 1.0
0.0Nervousness 0.5 4.7 6.5 1.0
1.0Gastrointestinal System Disorders Mouth Dryness 3.2 0.0 1.9 2.0
3.0Nausea 4.1 3.8 1.9 2.9
2.0Constipation 0.9 0.0 3.7 1.0
1.0Musculo-skeletal System Disorders Arthritis 0.9 1.4 0.9 0.5
3.0Respiratory System Disorders (Lower) Coughing 4.6 8.0 6.5 5.4
6.0Dyspnea 9.6 13.2 16.7 12.7
9.0Bronchitis 14.6 24.5 15.7 16.6
20.0Bronchospasm 2.3 2.8 4.6 5.4
5.0Sputum Increased 1.4 1.4 4.6 3.4
0.0Respiratory Disorder 0.0 6.1 6.5 2.0
4.0Respiratory System Disorders (Upper) Upper Respiratory Tract Infection 13.2 11.3 9.3 12.2
16.0Pharyngitis 3.7 4.2 5.6 2.9
4.0Rhinitis 2.3 4.2 1.9 2.4
0.0Sinusitus 2.3 2.8 0.9 5.4 4.0
🔄 Drug Interactions ▾
Drug Interactions Ipratropium bromide has been shown to be a safe and effective bronchodilator when used in conjunction with beta adrenergic bronchodilators. Ipratropium bromide has also been used with other pulmonary medications, including methylxanthines and corticosteroids, without adverse drug interactions.
🤰 Pregnancy ▾
Pregnancy TERATOGENIC EFFECTS Pregnancy Category B Oral reproduction studies performed in mice, rats and rabbits at doses of 10, 100, and 125 mg/kg respectively, and inhalation reproduction studies in rats and rabbits at doses of 1.5 and 1.8 mg/kg (or approximately 38 and 45 times the recommended human daily dose) respectively, have demonstrated no evidence of teratogenic effects as a result of ipratropium bromide. However, no adequate or well-controlled studies have been conducted in pregnant women. Because animal reproduction studies are not always predictive of human response, ipratropium bromide should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in the pediatric population below the age of 12 have not been established.
🆘 Overdosage ▾
OVERDOSAGE Acute systemic overdosage by inhalation solution is unlikely since ipratropium bromide is not well absorbed after inhalation at up to four-fold the recommended dose, or after oral administration at up to forty-fold the recommended dose. The oral LD 50 of ipratropium bromide ranged between 1001 and 2010 mg/kg in mice; between 1667 and 4000 mg/kg in rats; and between 400 and 1300 mg/kg in dogs.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Ipratropium bromide is an anticholinergic (parasympatholytic) agent that, based on animal studies, appears to inhibit vagally mediated reflexes by antagonizing the action of acetylcholine, the transmitter agent released from the vagus nerve. Anticholinergics prevent the increases in intracellular concentration of cyclic guanosine monophosphate (cyclic GMP) that are caused by interaction of acetylcholine with the muscarinic receptor on bronchial smooth muscle. The bronchodilation following inhalation of ipratropium bromide is primarily a local, site-specific effect, not a systemic one.
Much of an administered dose is swallowed but not absorbed, as shown by fecal excretion studies. Following nebulization of a 2 mg dose, a mean 7% of the dose was absorbed into the systemic circulation either from the surface of the lung or from the gastrointestinal tract. The half-life of elimination is about 1.6 hours after intravenous administration.
Ipratropium bromide is minimally (0 to 9% in vitro ) bound to plasma albumin and a 1 -acid glycoproteins. It is partially metabolized. Autoradiographic studies in rats have shown that ipratropium bromide does not penetrate the blood-brain barrier.
Ipratropium bromide has not been studied in patients with hepatic or renal insufficiency. It should be used with caution in those patient populations. In controlled 12-week studies in patients with bronchospasm associated with chronic obstructive pulmonary disease (chronic bronchitis and emphysema) significant improvements in pulmonary function (FEV 1 increases of 15% or more) occurred within 15 to 30 minutes, reached a peak in 1 to 2 hours, and persisted for periods of 4 to 5 hours in the majority of patients, with about 25% to 38% of the patients demonstrating increases of 15% or more for at least 7 to 8 hours.
Continued effectiveness of ipratropium bromide inhalation solution was demonstrated throughout the 12-week period. In addition, significant increases in forced vital capacity (FVC) have been demonstrated. However, ipratropium bromide did not consistently produce significant improvement in subjective symptom scores nor in quality of life scores over the 12-week duration of study.
Additional controlled 12-week studies were conducted to evaluate the safety and effectiveness of ipratropium bromide inhalation solution administered concomitantly with the beta adrenergic bronchodilator solutions metaproterenol and albuterol compared with the administration of each of the beta agonists alone. Combined therapy produced significant additional improvement in FEV 1 and FVC. On combined therapy, the median duration of 15% improvement in FEV 1 was 5 to 7 hours, compared with 3 to 4 hours in patients receiving a beta agonist alone.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Ipratropium Bromide Inhalation Solution Unit Dose Vial is supplied as a 0.02% clear, colorless solution containing 2.5 mL. NDC 0378-7970-52 25 vials per carton/25 vials per foil pouch NDC 0378-7970-93 30 vials per carton/30 vials per foil pouch NDC 0378-7970-91 60 vials per carton/30 vials per foil pouch NDC 0378-7970-55 30 vials per carton / 1 vial per foil pouch Each vial is made from a low density polyethylene (LDPE) resin. Vials are supplied in a foil pouch.
Store between 59°F (15°C) and 86°F (30°C). Protect from light. Store unused vials in the foil pouch.
ATTENTION PHARMACIST: Detach "Patient's Instructions for Use" from Package Insert and dispense with solution.
📦 Storage and Handling ▾
Store between 59°F (15°C) and 86°F (30°C). Protect from light. Store unused vials in the foil pouch. ATTENTION PHARMACIST: Detach "Patient's Instructions for Use" from Package Insert and dispense with solution.
📋 Description ▾
DESCRIPTION The active ingredient, ipratropium bromide monohydrate, USP, is an anticholinergic bronchodilator chemically described as 8-azoniabicyclo [3.2.1]- octane, 3-(3-hydroxy-1-oxo-2-phenylpropoxy)-8-methyl-8-(1-methylethyl)-, bromide, monohydrate (endo, syn)-, (±)-; a synthetic quaternary ammonium compound, chemically related to atropine. Ipratropium Bromide Monohydrate C 20 H 30 BrNO 3 •H 2 O Mol.Wt. 430.4 Ipratropium bromide is a white crystalline substance, freely soluble in water and lower alcohols.
It is a quaternary ammonium compound and thus exists in an ionized state in aqueous solutions. It is relatively insoluble in non-polar media. Ipratropium Bromide Inhalation Solution is administered by oral inhalation with the aid of a nebulizer.
It contains ipratropium bromide, USP 0.02% (anhydrous basis) in a sterile, preservative-free, isotonic saline solution, pH-adjusted to 3.4 (3 to 4) with hydrochloric acid. Chemical Structure
💬 Information for Patients ▾
Information for Patients Patients should be advised that temporary blurring of vision, precipitation or worsening of narrow-angle glaucoma or eye pain may result if the solution comes into direct contact with the eyes. Use of a nebulizer with mouthpiece rather than face mask may be preferable, to reduce the likelihood of the nebulizer solution reaching the eyes. Patients should be advised that ipratropium bromide inhalation solution can be mixed in the nebulizer with albuterol or metaproterenol if used within one hour.
Drug stability and safety of Ipratropium Bromide Inhalation Solution when mixed with other drugs in a nebulizer have not been established. Patients should be reminded that ipratropium bromide inhalation solution should be used consistently as prescribed throughout the course of therapy.
⚠️ Precautions ▾
PRECAUTIONS General Ipratropium bromide should be used with caution in patients with narrow-angle glaucoma, prostatic hypertrophy or bladder-neck obstruction. Information for Patients Patients should be advised that temporary blurring of vision, precipitation or worsening of narrow-angle glaucoma or eye pain may result if the solution comes into direct contact with the eyes. Use of a nebulizer with mouthpiece rather than face mask may be preferable, to reduce the likelihood of the nebulizer solution reaching the eyes.
Patients should be advised that ipratropium bromide inhalation solution can be mixed in the nebulizer with albuterol or metaproterenol if used within one hour. Drug stability and safety of Ipratropium Bromide Inhalation Solution when mixed with other drugs in a nebulizer have not been established. Patients should be reminded that ipratropium bromide inhalation solution should be used consistently as prescribed throughout the course of therapy.
Drug Interactions Ipratropium bromide has been shown to be a safe and effective bronchodilator when used in conjunction with beta adrenergic bronchodilators. Ipratropium bromide has also been used with other pulmonary medications, including methylxanthines and corticosteroids, without adverse drug interactions. Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year oral carcinogenicity studies in rats and mice have revealed no carcinogenic potential at dietary doses up to 6 mg/kg/day of ipratropium bromide.
Results of various mutagenicity studies (Ames test, mouse dominant lethal test, mouse micronucleus test and chromosome aberration of bone marrow in Chinese hamsters) were negative. Fertility of male or female rats at oral doses up to 50 mg/kg/day was unaffected by ipratropium bromide administration. At doses above 90 mg/kg increased resorption and decreased conception rates were observed.
Pregnancy TERATOGENIC EFFECTS Pregnancy Category B Oral reproduction studies performed in mice, rats and rabbits at doses of 10, 100, and 125 mg/kg respectively, and inhalation reproduction studies in rats and rabbits at doses of 1.5 and 1.8 mg/kg (or approximately 38 and 45 times the recommended human daily dose) respectively, have demonstrated no evidence of teratogenic effects as a result of ipratropium bromide. However, no adequate or well-controlled studies have been conducted in pregnant women. Because animal reproduction studies are not always predictive of human response, ipratropium bromide should be used during pregnancy only if clearly needed.
Nursing Mothers It is not known whether ipratropium bromide is excreted in human milk. Although lipid-insoluble quaternary bases pass into breast milk, it is unlikely that ipratropium bromide would reach the infant to a significant extent, especially when taken by inhalation since ipratropium bromide is not well absorbed systemically after inhalation or oral administration. However, because many drugs are excreted in human milk, caution should be exercised when ipratropium bromide is administered to a nursing woman.
Pediatric Use Safety and effectiveness in the pediatric population below the age of 12 have not been established.
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether ipratropium bromide is excreted in human milk. Although lipid-insoluble quaternary bases pass into breast milk, it is unlikely that ipratropium bromide would reach the infant to a significant extent, especially when taken by inhalation since ipratropium bromide is not well absorbed systemically after inhalation or oral administration. However, because many drugs are excreted in human milk, caution should be exercised when ipratropium bromide is administered to a nursing woman.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Two-year oral carcinogenicity studies in rats and mice have revealed no carcinogenic potential at dietary doses up to 6 mg/kg/day of ipratropium bromide. Results of various mutagenicity studies (Ames test, mouse dominant lethal test, mouse micronucleus test and chromosome aberration of bone marrow in Chinese hamsters) were negative. Fertility of male or female rats at oral doses up to 50 mg/kg/day was unaffected by ipratropium bromide administration.
At doses above 90 mg/kg increased resorption and decreased conception rates were observed.
📖 Instructions for Use ▾
Patient's Instructions for Use Ipratropium Bromide Inhalation Solution, 0.02% Read complete instructions carefully before using. • Twist open the top of one unit dose vial and squeeze the contents into the nebulizer reservoir. (Figure 1). • Connect the nebulizer reservoir to the mouthpiece or face mask (Figure 2). • Connect the nebulizer to the compressor. • Sit in a comfortable, upright position; place the mouthpiece in your mouth (Figure 3) or put on the face mask and turn on the compressor. If a face mask is used, care should be taken to avoid leakage around the mask as temporary blurring of vision, pupil enlargement, precipitation or worsening of narrow-angle glaucoma, or eye pain may occur if the solution comes into direct contact with the eyes. • Breathe as calmly, deeply, and evenly as possible until no more mist is formed in the nebulizer chamber (about 5 to 15 minutes).
At this point, the treatment is finished. • Clean the nebulizer (see manufacturer's instructions). Note: Use only as directed by your physician. More frequent administration or higher doses are not recommended.
Ipratropium Bromide Inhalation Solution can be mixed in the nebulizer with albuterol or metaproterenol if used within one hour but not with other drugs. Drug stability and safety of Ipratropium Bromide Inhalation Solution when mixed with other drugs in the nebulizer have not been established. Store between 59°F (15°C) and 86°F (30°).
Protect from light. Store unused vials in the foil pouch. ADDITIONAL INSTRUCTIONS: _______________________________________ _______________________________________ _______________________________________ _______________________________________ _______________________________________ _______________________________________ _______________________________________ Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 Manufactured by: The Ritedose Corporation Columbia, SC 29203 TRC:PIL:IPBRIS:R3 MAY 2013 Figure 1 Figure 2 Figure 3
📄 Package Label / Principal Display Panel ▾
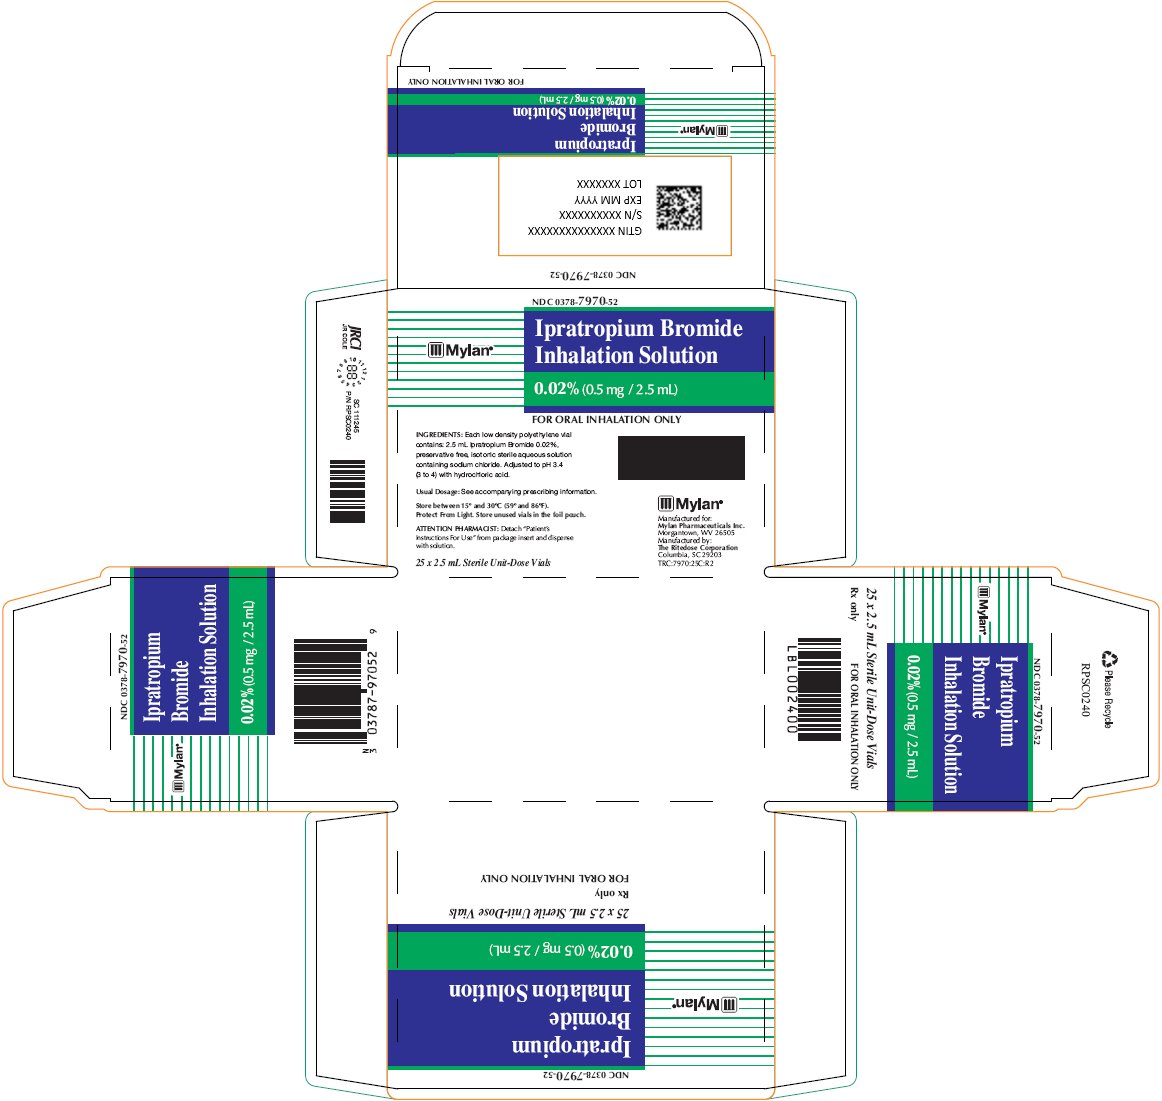
PRINCIPAL DISPLAY PANEL - 2.5 mL Pouch Carton Mylan ® NDC 0378-7970-52 Ipratropium Bromide Inhalation Solution 0.02% (0.5 mg / 2.5 mL) 25 x 2.5 mL Sterile Unit-Dose Vials Rx only FOR ORAL INHALATION ONLY Ipratropium Bromide Inhalation Solution 0.02% Carton Label