
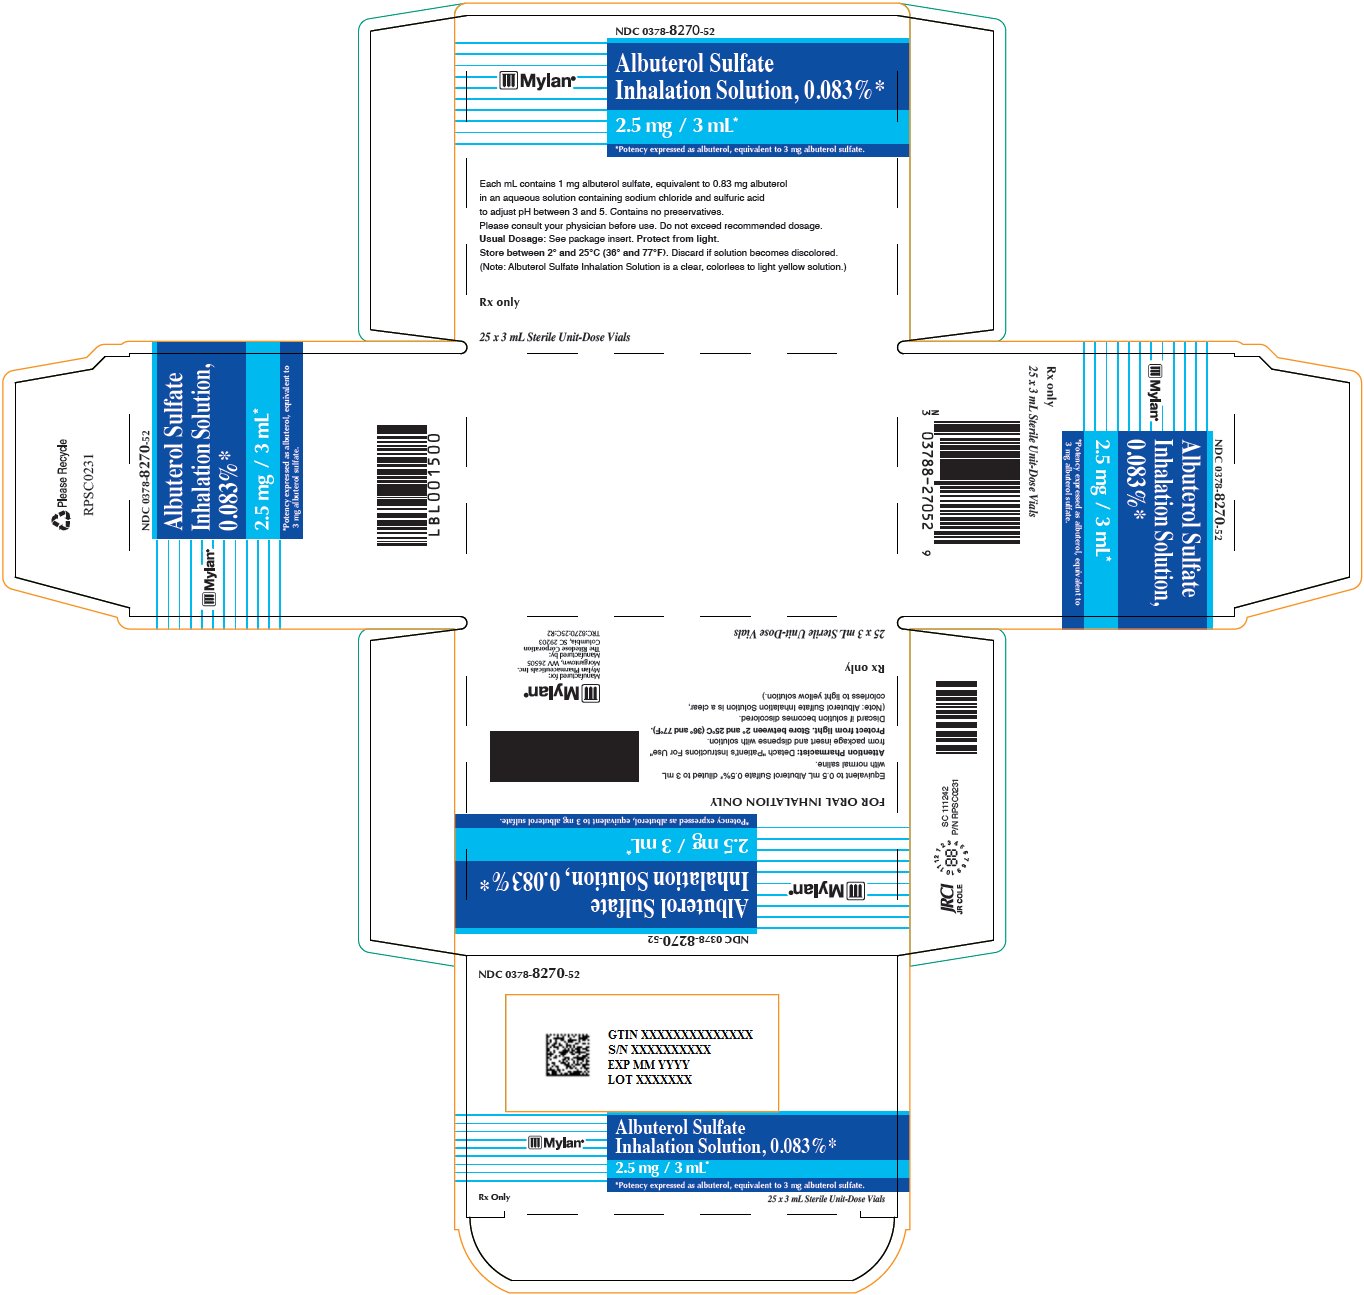
Albuterol Sulfate 2.5 mg/3mL Solution
Other active recalls for Albuterol Sulfate (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta2-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Albuterol quickly relaxes the muscles around your airways, opening them up so you can breathe more easily. Think of it as a fast-acting rescue medicine — you use it when you feel y...
- What exactly does albuterol do, and when should I use it?
- That depends on which inhaler you have. If you have a standard HFA inhaler (like Ventolin HFA or Albuterol Sulfate HFA), shake it well before every puff and prime it with a few tes...
- The most common side effects are pretty mild — a scratchy throat, cough, or upper respiratory irritation, and sometimes a slightly faster heartbeat, shakiness, or headache. Those u...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Albuterol Sulfate — tap one for details:
Albuterol Sulfate may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII O40UQP6WCF
A strong acid used in small amounts to adjust and maintain the pH balance of a medicine, helping ensure stability and proper dissolution of the active ingredients.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.059 | $4.46 / 75 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.1056 | $7.92 / 75 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.1002 | $7.52 / 75 ml |
| Medicare Part B allowsASP · J7613 | $0.063 / J7613 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Albuterol Sulfate 2.5 mg/3mLthis 00378-8270-52 | Mylan | 1 pouch | $0.059 | AN | Availability likely | — |
| Albuterol Sulfate .83 mg/mL 47335-0703-49 | Sun | 5 pouches | $0.059 | AN | Availability likely | — |
| Albuterol Sulfate 2.5 mg/3mL 00487-9501-01 | Nephron | 30 pouches | $0.061 | AN | Availability likely | +2% |
| Albuterol Sulfate 2.5 mg/3mL 60687-0395-83 | American | 30 pouches | $0.061 | AN | Availability likely | +2% |
| Albuterol Sulfate 2.5 mg/3mL 62135-0828-84 | Chartwell | 6 pouches | $0.061 | AN | Availability likely | +2% |
| Albuterol Sulfate 2.5 mg/3mL 76204-0200-01 | Ritedose | 30 pouches | $0.061 | AN | Availability likely | +2% |
| Albuterol Sulfate 2.5 mg/3mL 50090-0516-00 | A-S | 1 pouch | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 50090-6560-00 | A-S | 25 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 51662-1499-01 | HF | 5 vials | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 55154-2132-05 | Cardinal | 5 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 55154-4410-05 | Cardinal | 5 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 63187-0204-25 | Proficient | 1 pouch | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 64980-0641-02 | Rising | 1 pouch | — | AN | FDA listed | — |
| Albuterol Sulfate .83 mg/mL 65862-0858-03 | Aurobindo | 30 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 68071-3780-02 | NuCare | 1 pouch | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 68071-4543-06 | NuCare | 3 ml | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 68071-4754-02 | NuCare | 3 ml | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 68788-8399-02 | Preferred | 25 ampules | — | AN | FDA listed | — |
| Albuterol Sulfate .83 mg/mL 68788-8492-02 | Preferred | 5 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate .83 mg/mL 70518-3560-00 | REMEDYREPACK | 12 pouches | — | AN | Discontinued | — |
| Albuterol Sulfate .83 mg/mL 70518-4490-00 | REMEDYREPACK | 5 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate .83 mg/mL 71205-0641-25 | Proficient | 5 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 71872-7054-01 | Medical | 1 ampule | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 76420-0087-03 | Asclemed | 1 vial | — | AN | FDA listed | — |
| Albuterol Sulfate .83 mg/mL 81894-0104-02 | Luoxin | 30 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 85766-0127-01 | Sportpharm | 30 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 2.5 mg/3mL 87063-0031-01 | ASCLEMED | 30 pouches | — | AN | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00378-8270-52 You're viewing this | 1 POUCH in 1 CARTON (0378-8270-52) / 25 AMPULE in 1 POUCH (0378-8270-62) / 3 mL in 1 AMPULE | $0.0594 / mL | $4.46 | 2012-12-18 | Active |
| 00378-8270-55 | 30 POUCH in 1 CARTON (0378-8270-55) / 1 AMPULE in 1 POUCH (0378-8270-31) / 3 mL in 1 AMPULE | $0.0605 / mL | $5.45 | 2014-03-06 | Active |
| 00378-8270-91 | 2 POUCH in 1 CARTON (0378-8270-91) / 30 AMPULE in 1 POUCH (0378-8270-64) / 3 mL in 1 AMPULE | $0.0658 / mL | $11.84 | 2013-04-11 | Active |
| 00378-8270-93 | 1 POUCH in 1 CARTON (0378-8270-93) / 30 AMPULE in 1 POUCH / 3 mL in 1 AMPULE | $0.0605 / mL | $5.45 | 2013-01-22 | Active |
This pack has the lowest per-mL cost of the 4 priced pack sizes ($0.0594 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 81% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00378-8270-52?
What NDC number is used to bill for this package of Albuterol Sulfate 2.5 mg/3mL Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Albuterol inhalation solution is indicated for the relief of bronchospasm in patients 2 years of age and older with reversible obstructive airway disease and acute attacks of bronchospasm.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Adults and Children 2 to 12 Years of Age The usual dosage for adults and for children weighing at least 15 kg is 2.5 mg of albuterol (one vial) administered three to four times daily by nebulization. Children weighing <15 kg who require <2.5 mg/dose (i.e., less than a full vial) should use albuterol inhalation solution, 0.5% instead of albuterol inhalation solution, 0.083%. More frequent administration or higher doses are not recommended.
To administer 2.5 mg of albuterol, administer the entire contents of one sterile unit dose vial (3 mL of 0.083% inhalation solution) by nebulization. The flow rate is regulated to suit the particular nebulizer so that albuterol inhalation solution will be delivered over approximately 5 to 15 minutes. The use of albuterol inhalation solution can be continued as medically indicated to control recurring bouts of bronchospasm.
During this time most patients gain optimum benefit from regular use of the inhalation solution. If a previously effective dosage regimen fails to provide the usual relief, medical advice should be sought immediately, as this is often a sign of seriously worsening asthma which would require reassessment of therapy.
⛔ Contraindications ▾
CONTRAINDICATIONS Albuterol inhalation solution is contraindicated in patients with a history of hypersensitivity to any of its components.
⚠️ Warnings ▾
WARNINGS As with other inhaled beta-adrenergic agonists, albuterol inhalation solution can produce paradoxical bronchospasm, which can be life threatening. If it occurs, the preparation should be discontinued immediately and alternative therapy instituted. Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs and with the home use of nebulizers.
It is, therefore, essential that the physician instruct the patient in the need for further evaluation, if his/her asthma becomes worse. In individual patients, any beta 2 -adrenergic agonist, including albuterol solution for inhalation, may have a clinically significant cardiac effect. Immediate hypersensitivity reactions may occur after administration of albuterol as demonstrated by rare cases of urticaria, angioedema, rash, bronchospasm, and oropharyngeal edema.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Clinical Trial Experience The results of clinical trials with albuterol inhalation solution in 135 patients showed the following side effects which were considered probably or possibly drug related: Central Nervous System: tremors (20%), dizziness (7%), nervousness (4%), headache (3%), insomnia (1%). Gastrointestinal: nausea (4%), dyspepsia (1%). Ear Nose and Throat: pharyngitis (<1%), nasal congestion (1%).
Cardiovascular: tachycardia (1%), hypertension (1%). Respiratory: bronchospasm (8%), cough (4%), bronchitis (4%), wheezing (1%). No clinically relevant laboratory abnormalities related to albuterol inhalation solution administration were determined in these studies.
In comparing the adverse reactions reported for patients treated with albuterol inhalation solution with those of patients treated with isoproterenol during clinical trials of three months, the following moderate to severe reactions, as judged by the investigators, were reported. This table does not include mild reactions. Percent Incidence of Moderate to Severe Adverse Reactions Reaction Albuterol N=65 Isoproterenol N=65 Central Nervous System Tremors 10.7% 13.8% Headache 3.1% 1.5% Insomnia 3.1% 1.5% Cardiovascular Hypertension 3.1% 3.1% Arrhythmias 0% 3% The finding of no arrhythmias and no palpitations after albuterol administration in this clinical study should not be interpreted as indicating that these adverse effects cannot occur after the administration of inhaled albuterol.
Palpitation 0% 22% Respiratory In most cases of bronchospasm, this term was generally used to describe exacerbations in the underlying pulmonary disease. Bronchospasm 15.4% 18% Cough 3.1% 5% Bronchitis 1.5% 5% Wheeze 1.5% 1.5% Sputum Increase 1.5% 1.5% Dyspnea 1.5% 1.5% Gastrointestinal Nausea 3.1% 0% Dyspepsia 1.5% 0% Systemic Malaise 1.5% 0% Post-Marketing Experience Cases of urticaria, angioedema, rash, bronchospasm, hoarseness, oropharyngeal edema, arrhythmias (including atrial fibrillations, supraventricular tachycardia, extrasystoles) and metabolic acidosis have been reported after the use of albuterol inhalation solution.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
🔄 Drug Interactions ▾
Drug Interactions Other sympathomimetic aerosol bronchodilators or epinephrine should not be used concomitantly with albuterol. Albuterol should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants, since the action of albuterol on the vascular system may be potentiated. Beta-receptor blocking agents and albuterol inhibit the effect of each other.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Pregnancy Category C Albuterol has been shown to be teratogenic in mice when given subcutaneously in doses corresponding to 1.25 times the human nebulization dose (based on a 50 kg human). There are no adequate and well-controlled studies in pregnant women. Albuterol should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
A reproduction study in CD-1 mice with albuterol (0.025, 0.25, and 2.5 mg/kg subcutaneously, corresponding to 0.125, 1.25 and 12.5 times the maximum human nebulization dose, respectively) showed cleft palate formation in 5 of 111 (4.5%) fetuses at 0.25 mg/kg and in 10 of 108 (9.3%) fetuses at 2.5 mg/kg. None were observed at 0.025 mg/kg. Cleft palate also occurred in 22 of 72 (30.5%) fetuses treated with 2.5 mg/kg isoproterenol (positive control).
A reproduction study in Stride Dutch rabbits revealed cranioschisis in 7 of 19 (37%) fetuses at 50 mg/kg, corresponding to 250 times the maximum nebulization dose for a 50 kg human. During worldwide marketing experience, various congenital anomalies, including cleft palate and limb defects, have been rarely reported in the offspring of patients being treated with albuterol. Some of the mothers were taking multiple medications during their pregnancies.
No consistent pattern of defects can be discerned, and a relationship between albuterol use and congenital anomalies has not been established.
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of albuterol inhalation solution have been established in children 2 years of age or older. Use of albuterol inhalation solution in these age groups is supported by evidence from adequate and well-controlled studies of albuterol inhalation solution in adults; the likelihood that the disease course, pathophysiology, and the drug’s effect in pediatric and adult patients are substantially similar; and published reports of trials in pediatric patients 3 years of age or older. The recommended dose for the pediatric population is based upon three published dose comparison studies of efficacy and safety in children aged 5 to 17 years, and on the safety profile in both adults and pediatric patients at doses equal to or higher than the recommended doses.
The safety and effectiveness of albuterol inhalation solution in children below 2 years of age have not been established.
🆘 Overdosage ▾
OVERDOSAGE Manifestations of overdosage may include seizures, anginal pain, hypertension, hypokalemia, tachycardia with rates up to 200 beats/min, and exaggeration of the pharmacological effects listed in ADVERSE REACTIONS . In isolated cases in children 2 to 12 years of age, tachycardia with rates >200 beats/min has been observed. The oral LD 50 in rats and mice was greater than 2,000 mg/kg.
The inhalational LD 50 could not be determined. There is insufficient evidence to determine if dialysis is beneficial for overdosage of albuterol inhalation solution.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The prime action of beta-adrenergic drugs is to stimulate adenyl cyclase, the enzyme which catalyzes the formation of cyclic-3',5'-adenosine monophosphate (cyclic AMP) from adenosine triphosphate (ATP). The cyclic AMP thus formed mediates the cellular responses. In vitro studies and in vivo pharmacologic studies have demonstrated that albuterol has a preferential effect on beta 2 -adrenergic receptors compared with isoproterenol.
While it is recognized that beta 2 -adrenergic receptors are the predominant receptors in bronchial smooth muscle, 10% to 50% of the beta-receptors in the human heart may be beta 2 -receptors. The precise function of these receptors, however, is not yet established. Albuterol has been shown in most controlled clinical trials to have more effect on the respiratory tract in the form of bronchial smooth muscle relaxation than isoproterenol at comparable doses while producing fewer cardiovascular effects.
Controlled clinical studies and other clinical experience have shown that inhaled albuterol, like other beta-adrenergic agonist drugs, can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms, and/or electrocardiographic changes. Albuterol is longer acting than isoproterenol in most patients by any route of administration because it is not a substrate for the cellular uptake processes for catecholamines nor for catechol-O-methyl transferase. Studies in asthmatic patients have shown that less than 20% of a single albuterol dose was absorbed following IPPB (intermittent positive-pressure breathing) or nebulizer administration; the remaining amount was recovered from the nebulizer and apparatus and expired air.
Most of the absorbed dose was recovered in the urine 24 hours after drug administration. Following a 3 mg dose of nebulized albuterol, the maximum albuterol plasma level at 0.5 hour was 2.1 ng/mL (range 1.4 to 3.2 ng/mL). There was a significant dose-related response in FEV 1 (forced expiratory volume in one second) and peak flow rate.
It has been demonstrated that following oral administration of 4 mg albuterol, the elimination half-life was five to six hours. Animal studies show that albuterol does not pass the blood-brain barrier. Recent studies in laboratory animals (minipigs, rodents, and dogs) recorded the occurrence of cardiac arrhythmias and sudden death (with histologic evidence of myocardial necrosis) when beta-agonists and methylxanthines were administered concurrently.
The significance of these findings when applied to humans is currently unknown. In controlled clinical trials, most patients exhibited an onset of improvement in pulmonary function within 5 minutes as determined by FEV 1 . FEV 1 measurements also showed that the maximum average improvement in pulmonary function usually occurred at approximately 1 hour following inhalation of 2.5 mg of albuterol by compressor-nebulizer, and remained close to peak for 2 hours.
Clinically significant improvement in pulmonary function (defined as maintenance of a 15% or more increase in FEV 1 over baseline values) continued for 3 to 4 hours in most patients and in some patients continued up to 6 hours. In repetitive dose studies, continued effectiveness was demonstrated throughout the three-month period of treatment in some patients. Published reports of trials in asthmatic children aged 3 years or older have demonstrated significant improvement in either FEV 1 or PEFR within 2 to 20 minutes following single dose of albuterol inhalation solution.
An increase of 15% or more in baseline FEV 1 has been observed in children aged 5 to 11 years up to 6 hours after treatment with doses of 0.10 mg/kg or higher of albuterol inhalation solution. Single doses of 3, 4 or 10 mg resulted in improvement in baseline PEFR that was comparable to extent and duration to a 2 mg dose, but doses above 3 mg were associated with heart rate increases of more than 10%.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Unit-dose plastic vial containing Albuterol Inhalation Solution, USP 0.083%, 2.5 mg/3 mL. Equivalent to 0.5 mL albuterol (as the sulfate) 0.5% (2.5 mg albuterol) diluted to 3 mL. Supplied in cartons as listed below.
NDC 0378-8270-52 25 vials per carton / 25 vials per foil pouch NDC 0378-8270-93 30 vials per carton / 30 vials per foil pouch NDC 0378-8270-91 60 vials per carton / 30 vials per foil pouch NDC 0378-8270-55 30 vials per carton / 1 vial per foil pouch Storage PROTECT FROM LIGHT. Store in pouch until time of use. Store between 2° and 25°C (36° and 77°F).
📦 Storage and Handling ▾
Storage PROTECT FROM LIGHT. Store in pouch until time of use. Store between 2° and 25°C (36° and 77°F).
📋 Description ▾
DESCRIPTION Albuterol inhalation solution is a relatively selective beta 2 -adrenergic bronchodilator (see CLINICAL PHARMACOLOGY section below). Albuterol sulfate, the racemic form of albuterol, has the chemical name α 1 -[( tert - Butylamino)methyl]-4-hydroxy- m -xylene-α,α'-diol sulfate (2:1) (salt), and the following structural formula: Albuterol sulfate has a molecular weight of 576.70 and the molecular formula (C 13 H 21 NO 3 ) 2 •H 2 SO 4 . Albuterol sulfate is a white or practically white powder, freely soluble in water and slightly soluble in alcohol.
The World Health Organization recommended name for albuterol base is salbutamol. Albuterol inhalation solution 0.083% requires no dilution before administration. Each milliliter of Albuterol Inhalation Solution, USP 0.083% contains 0.83 mg of albuterol (as 1 mg of albuterol sulfate) in an isotonic, sterile, aqueous solution containing sodium chloride; sulfuric acid is used to adjust the pH to between 3 and 5.
Albuterol Inhalation Solution, USP 0.083% contains no sulfiting agents or preservatives. Albuterol inhalation solution is a clear, colorless to light yellow solution. Albuterol Sulfate Structural Formula
💬 Information for Patients ▾
Information for Patients The action of albuterol inhalation solution may last up to six hours, and therefore it should not be used more frequently than recommended. Do not increase the dose or frequency of medication without medical consultation. If symptoms get worse, medical consultation should be sought promptly.
While taking albuterol inhalation solution, other anti-asthma medicines should not be used unless prescribed. Drug compatibility (physical and chemical), efficacy, and safety of albuterol inhalation solution when mixed with other drugs in a nebulizer have not been established. See illustrated “ Patient’s Instructions for Use .”