
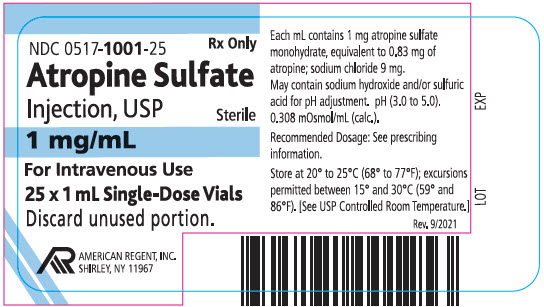
Atropine Sulfate 1 mg/mL Injection, Solution, 25 vials
Other active recalls for Atropine Sulfate (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anticholinergic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Atropine works by blocking a nerve signal that, when overactive, can cause a dangerously slow heart rate, flooding secretions, or — in poisoning — life-threatening over-stimulation...
- Why am I being given atropine — what does it actually do?
- It's very common to notice a dry mouth, blurred vision, light sensitivity, a faster heartbeat, flushing, or difficulty urinating — those are expected effects of how atropine works...
- What side effects should I expect, and which ones mean I need to call for help?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Atropine Sulfate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $53.78 | $1,344.52 / 25 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0462 | $0.127 / J0462 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Atropine Sulfate 1 mg/mL 00404-9989-01 | Henry | 1 vial | — | — | FDA listed | — |
| Atropine Sulfate 1 mg/mLthis 00517-1001-25 | American | 25 vials | — | AP | FDA listed | — |
| Atropine Sulfate 1 mg/mL 00641-6275-25 | Hikma | 25 vials | — | AP | FDA listed | — |
| Atropine Sulfate 1 mg/mL 51662-1626-03 | HF | 25 pouches | — | AP | FDA listed | — |
| Atropine Sulfate 1 mg/mL 70069-0641-25 | Somerset | 25 vials | — | AP | FDA listed | — |
| Atropine Sulfate 1 mg/mL 71872-7340-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Atropine Sulfate 1 mg/mL 84549-0001-25 | ProPharma | 1 ml | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00517-1001-25 You're viewing this | 25 VIAL, GLASS in 1 TRAY (0517-1001-25) / 1 mL in 1 VIAL, GLASS (0517-1001-01) | 2022-08-02 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Atropine Sulfate Injection, USP, is indicated for temporary blockade of severe or life threatening muscarinic effects, e.g., as an antisialagogue, an antivagal agent, an antidote for organophosphorus or muscarinic mushroom poisoning, and to treat bradyasystolic cardiac arrest. Atropine is a muscarinic antagonist indicated for temporary blockade of severe or life threatening muscarinic effects. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For intravenous administration. ( 2.1 ). Titrate according to heart rate, PR interval, blood pressure and symptoms.
( 2.1 ) Adult dosage Antisialagogue or for antivagal effects: Initial single dose of 0.5 to 1 mg. ( 2.2 ) Antidote for organophosphorus or muscarinic mushroom poisoning: Initial single dose of 2 to 3 mg, repeated every 20 to 30 minutes. ( 2.2 ) Bradyasystolic cardiac arrest: 1 mg dose, repeated every 3 to 5 minutes if asystole persists.
( 2.2 ) Patients with Coronary Artery Disease: Limit the total dose to 0.03 mg/kg to 0.04 mg/kg. ( 2.4 )
2.1General Administration Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. Do not administer unless solution is clear and seal is intact. Each vial is intended for single dose only. Discard unused portion. For Intravenous administration. Titrate based on heart rate, PR interval, blood pressure and symptoms.
2.2Adult Dosage Table 1: Recommended Dosage Use Dose (adults) Repeat Antisialagogue or other antivagal 0.5 to 1 mg 1 to 2 hours Organophosphorus or muscarinic mushroom poisoning 2 to 3 mg 20 to 30 minutes Bradyasystolic cardiac arrest 1 mg 3 to 5 minutes; 3 mg maximum total dose
2.3Pediatric Dosage Dosing in pediatric populations has not been well studied. Usual initial dose is 0.01 to 0.03 mg/kg.
2.4Dosing in Patients with Coronary Artery Disease Limit the total dose of atropine sulfate to 0.03 to 0.04 mg/kg [see Warnings and Precautions (5.1) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: supplied as a clear, colorless solution in a 1 mL glass vial in the following concentrations: 0.4 mg/mL: containing 0.4 mg of atropine sulfate monohydrate equivalent to 0.332 mg of atropine. 1 mg/mL: containing 1 mg atropine sulfate monohydrate equivalent to 0.83 mg of atropine. Injection: 0.4 or 1 mg/mL as a clear, colorless solution in a single-dose vial.
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Tachycardia ( 5.1 ) Glaucoma ( 5.2 ) Pyloric obstruction ( 5.3 ) Worsening urinary retention ( 5.4 ) Viscid bronchial plugs ( 5.5 )
5.1Tachycardia When the recurrent use of atropine is essential in patients with coronary artery disease, the total dose should be restricted to 2 to 3 mg (maximum 0.03 to 0.04 mg/kg) to avoid the detrimental effects of atropine-induced tachycardia on myocardial oxygen demand.
5.2Acute Glaucoma Atropine may precipitate acute glaucoma.
5.3Pyloric Obstruction Atropine may convert partial organic pyloric stenosis into complete obstruction.
5.4Complete Urinary Retention Atropine may lead to complete urinary retention in patients with prostatic hypertrophy.
5.5Viscid Plugs Atropine may cause inspissation of bronchial secretions and formation of viscid plugs in patients with chronic lung disease.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions have been identified during post-approval use of atropine sulfate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Most of the side effects of atropine are directly related to its antimuscarinic action.
Dryness of the mouth, blurred vision, photophobia and tachycardia commonly occur. Anhidrosis can produce heat intolerance. Constipation and difficulty in micturition may occur in elderly patients.
Occasional hypersensitivity reactions have been observed, especially skin rashes which in some instances progressed to exfoliation. Most adverse reactions are directly related to atropine's antimuscarinic action. Dryness of the mouth, blurred vision, photophobia and tachycardia commonly occur with chronic administration of therapeutic doses.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact American Regent, Inc. at 1-800-734-9236, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Mexiletine: Decreases rate of mexiletine absorption. ( 7.1 )
7.1Mexiletine Atropine Sulfate Injection decreased the rate of mexiletine absorption without altering the relative oral bioavailability; this delay in mexiletine absorption was reversed by the combination of atropine and intravenous metoclopramide during pretreatment for anesthesia.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Risk Summary There are risks to the mother and fetus associated with untreated severe or life-threatening muscarinic events (see Clinical Considerations). Available data from published observational studies on atropine use in pregnant women are insufficient to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data) . Animal reproduction studies have not been conducted with atropine.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Severe or life-threatening muscarinic events such as acute organophosphate poisoning and symptomatic bradycardia are medical emergencies in pregnancy which can be fatal if left untreated. Life-sustaining therapy for the pregnant woman should not be withheld because of concerns regarding the effects of atropine on the fetus. Data Human Data Atropine crosses the placenta [see Clinical Pharmacology (12.3)].
No adequate and well-controlled studies are available regarding use of atropine in pregnant women. In a cohort study of 401 pregnancies in the first trimester and 797 pregnancies in the second or third trimester, atropine use was not associated with an increased risk of congenital malformation. In a surveillance study, 381 newborns were exposed to atropine during the first trimester; 18 major birth defects were observed when 16 were expected.
No specific pattern of major birth defects was identified. In another surveillance study of 50 pregnancies in the first trimester, atropine use was not associated with an increased risk of malformations. Methodological limitations of these observational studies including the inability to control for the dosage and timing of atropine exposure, underlying maternal disease, or concomitant maternal drug use, cannot definitively establish or exclude any drug associated risk during pregnancy.
8.2Lactation Risk Summary Trace amounts of atropine have been reported in human milk after oral intake. There are no available data on atropine levels in human milk after intravenous injection, the effects on the breastfed infant, or the effects on milk production. Clinical Considerations Minimizing exposure The elimination half-life of atropine is more than doubled in children less than 2 years of age [ see Clinical Pharmacology (12.3 )] .
To minimize potential infant exposure to Atropine Sulfate Injection, a woman may pump and discard her milk for 24 hours after use before resuming to breastfeed her infant.
8.4Pediatric Use Recommendations for use in pediatric patients are not based on clinical trials.
8.5Geriatric Use An evaluation of current literature revealed no clinical experience identifying differences in response between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Risk Summary There are risks to the mother and fetus associated with untreated severe or life-threatening muscarinic events (see Clinical Considerations). Available data from published observational studies on atropine use in pregnant women are insufficient to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data) . Animal reproduction studies have not been conducted with atropine.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Severe or life-threatening muscarinic events such as acute organophosphate poisoning and symptomatic bradycardia are medical emergencies in pregnancy which can be fatal if left untreated. Life-sustaining therapy for the pregnant woman should not be withheld because of concerns regarding the effects of atropine on the fetus. Data Human Data Atropine crosses the placenta [see Clinical Pharmacology (12.3)].
No adequate and well-controlled studies are available regarding use of atropine in pregnant women. In a cohort study of 401 pregnancies in the first trimester and 797 pregnancies in the second or third trimester, atropine use was not associated with an increased risk of congenital malformation. In a surveillance study, 381 newborns were exposed to atropine during the first trimester; 18 major birth defects were observed when 16 were expected.
No specific pattern of major birth defects was identified. In another surveillance study of 50 pregnancies in the first trimester, atropine use was not associated with an increased risk of malformations. Methodological limitations of these observational studies including the inability to control for the dosage and timing of atropine exposure, underlying maternal disease, or concomitant maternal drug use, cannot definitively establish or exclude any drug associated risk during pregnancy.
🧒 Pediatric Use ▾
8.4Pediatric Use Recommendations for use in pediatric patients are not based on clinical trials.
🧓 Geriatric Use ▾
8.5Geriatric Use An evaluation of current literature revealed no clinical experience identifying differences in response between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Excessive dosing may cause palpitation, dilated pupils, difficulty in swallowing, hot dry skin, thirst, dizziness, restlessness, tremor, fatigue and ataxia. Toxic doses lead to restlessness and excitement, hallucinations, delirium and coma. Depression and circulatory collapse occur only with severe intoxication.
In such cases, blood pressure declines and death due to respiratory failure may ensue following paralysis and coma. The fatal adult dose of atropine is not known. In pediatric populations, 10 mg or less may be fatal.
In the event of toxic overdosage, a short acting barbiturate or diazepam may be given as needed to control marked excitement and convulsions. Large doses for sedation should be avoided because central depressant action may coincide with the depression occurring late in atropine poisoning. Central stimulants are not recommended.
Physostigmine, given as an atropine antidote by slow intravenous injection of 1 to 4 mg (0.5 to 1 mg in pediatric populations), rapidly abolishes delirium and coma caused by large doses of atropine. Since physostigmine is rapidly destroyed, the patient may again lapse into coma after one to two hours, and repeated doses may be required. Artificial respiration with oxygen may be necessary.
Ice bags and alcohol sponges help to reduce fever, especially in pediatric populations. Atropine is not removed by dialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Atropine is an antimuscarinic agent since it antagonizes the muscarine-like actions of acetylcholine and other choline esters. Atropine inhibits the muscarinic actions of acetylcholine on structures innervated by postganglionic cholinergic nerves, and on smooth muscles which respond to endogenous acetylcholine but are not so innervated. As with other antimuscarinic agents, the major action of atropine is a competitive or surmountable antagonism which can be overcome by increasing the concentration of acetylcholine at receptor sites of the effector organ (e.g., by using anticholinesterase agents which inhibit the enzymatic destruction of acetylcholine).
The receptors antagonized by atropine are the peripheral structures that are stimulated or inhibited by muscarine (i.e., exocrine glands and smooth and cardiac muscle). Responses to postganglionic cholinergic nerve stimulation also may be inhibited by atropine, but this occurs less readily than with responses to injected (exogenous) choline esters.
12.2Pharmacodynamics Atropine-induced parasympathetic inhibition may be preceded by a transient phase of stimulation, especially on the heart where small doses first slow the rate before characteristic tachycardia develops due to paralysis of vagal control. Atropine exerts a more potent and prolonged effect on heart, intestine and bronchial muscle than scopolamine, but its action on the iris, ciliary body and certain secretory glands is weaker than that of scopolamine. Unlike the latter, atropine in clinical doses does not depress the central nervous system but may stimulate the medulla and higher cerebral centers.
Although mild vagal excitation occurs, the increased respiratory rate and (sometimes) increased depth of respiration produced by atropine are more probably the result of bronchiolar dilatation. Accordingly, atropine is an unreliable respiratory stimulant and large or repeated doses may depress respiration. Adequate doses of atropine abolish various types of reflex vagal cardiac slowing or asystole.
The drug also prevents or abolishes bradycardia or asystole produced by injection of choline esters, anticholinesterase agents or other parasympathomimetic drugs, and cardiac arrest produced by stimulation of the vagus. Atropine also may lessen the degree of partial heart block when vagal activity is an etiologic factor. In some patients with complete heart block, the idioventricular rate may be accelerated by atropine; in others, the rate is stabilized.
Occasionally a large dose may cause atrioventricular (A-V) block and nodal rhythm. Atropine Sulfate Injection, USP in clinical doses counteracts the peripheral dilatation and abrupt decrease in blood pressure produced by choline esters. However, when given by itself, atropine does not exert a striking or uniform effect on blood vessels or blood pressure.
Systemic doses slightly raise systolic and lower diastolic pressures and can produce significant postural hypotension. Such doses also slightly increase cardiac output and decrease central venous pressure. Occasionally, therapeutic doses dilate cutaneous blood vessels, particularly in the "blush" area (atropine flush), and may cause atropine "fever" due to suppression of sweat gland activity in infants and small children.
The effects of intravenous atropine on heart rate (maximum heart rate) and saliva flow (minimum flow) after intravenous administration (rapid, constant infusion over 3 min.) are delayed by 7 to 8 minutes after drug administration and both effects are non-linearly related to the amount of drug in the peripheral compartment. Changes in plasma atropine levels following intramuscular administration (0.5 to 4 mg doses) and heart rate are closely overlapped but the time course of the changes in atropine levels and behavioral impairment indicates that pharmacokinetics is not the primary rate-limiting mechanism for the central nervous system effect of atropine.
12.3 Pha…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Atropine is an antimuscarinic agent since it antagonizes the muscarine-like actions of acetylcholine and other choline esters. Atropine inhibits the muscarinic actions of acetylcholine on structures innervated by postganglionic cholinergic nerves, and on smooth muscles which respond to endogenous acetylcholine but are not so innervated. As with other antimuscarinic agents, the major action of atropine is a competitive or surmountable antagonism which can be overcome by increasing the concentration of acetylcholine at receptor sites of the effector organ (e.g., by using anticholinesterase agents which inhibit the enzymatic destruction of acetylcholine).
The receptors antagonized by atropine are the peripheral structures that are stimulated or inhibited by muscarine (i.e., exocrine glands and smooth and cardiac muscle). Responses to postganglionic cholinergic nerve stimulation also may be inhibited by atropine, but this occurs less readily than with responses to injected (exogenous) choline esters.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Atropine Sulfate Injection, USP 0.4 and 1 mg/mL are supplied in 1 mL, single-dose glass vials as follows: Table 2: How Supplied Concentration (mg/mL) Package Size NDC # 0.4 mg/mL 25 Vials 0517-1004-25 1 mg/mL 25 Vials 0517-1001-25 Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C and 30°C (59°F and 86°F). [ See USP Controlled Room Temperature .] IN1004 Rev. 9/2021 AR Logo
📋 Description ▾
11 DESCRIPTION Atropine Sulfate Injection, USP is a sterile, nonpyrogenic isotonic solution of atropine sulfate monohydrate in water for injection with sodium chloride sufficient to render the solution isotonic. It is administered parenterally by intravenous injection. Each milliliter (mL) contains 0.4 mg or 1 mg of atropine sulfate monohydrate equivalent to 0.332 mg or 0.83 mg of atropine, and sodium chloride, 9 mg.
May contain sodium hydroxide and/or sulfuric acid for pH adjustment. 0.308 mOsmol/mL (calc.). pH (3.0 to 5.0). The solution contains no bacteriostat, antimicrobial agent or added buffer (except for pH adjustment) and is intended for use only as a single-dose injection.
When smaller doses are required the unused portion should be discarded. Atropine Sulfate, USP is chemically designated 1α H, 5α H-Tropan-3-α-ol (±)-tropate (ester), sulfate (2:1) (salt) monohydrate, (C 17 H 23 NO 3 ) 2 ∙ H 2 SO 4 ∙ H 2 O, colorless crystals or white crystalline powder very soluble in water. It has the following structural formula: Atropine, a naturally occurring belladonna alkaloid, is a racemic mixture of equal parts of d- and 1-hyocyamine, whose activity is due almost entirely to the levo isomer of the drug. structural formula atropine sulfate