
Spiriva Respimat tiotropium bromide inhalation spray 1.562 ug Spray, Metered — NDC 0597-0160-28 (Billing 00597-0160-28)
This is a package of Spiriva Respimat tiotropium bromide inhalation spray 1.562 ug Spray, Metered from Boehringer Ingelheim Pharmaceuticals, Inc., marketed since Sep 2015 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 0597-0160-28 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0597 labeler · 0160 product · 28 package
- Package marketed since
- Sep 15, 2015
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0597016028 1
- FDA record last changed
- Sep 3, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 074813
- GCN: 39587
- HICL (First Databank): 024024
- AHFS class code: 12:08.08.00
- RxCUI (RxNorm): 1552002
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Anticholinergic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Tiotropium is used to prevent wheezing, shortness of breath, coughing, and chest tightness in patients with chronic obstructive pulmonary disease (COPD, a group of diseases that affect the lungs and airways) such as chronic bronchitis (swelling of the air passages that lead to the lungs) and emphysema (damage to air sacs in the lungs). Tiotropium is in a class of medications called bronchodilators. It works by relaxing and opening the air passages to the lungs to make breathing easier.
Read the full MedlinePlus article ↗- Spiriva Respimat is a daily controller for COPD, including chronic bronchitis and emphysema, and it helps reduce flare-ups. It is also used for asthma in people 6 and older. It kee...
- No. It is not a rescue inhaler and will not relieve sudden symptoms. Keep your fast-acting inhaler as your doctor directed and get help if breathing gets worse.
- Can I use it when I suddenly can't breathe well?
- Take two inhalations by mouth once a day, and never more than one dose in 24 hours. The inhaler must be primed before first use. Food does not matter. In asthma, full benefit can t...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $126.60 | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00597-0160-28 You're viewing this | 1 CARTRIDGE in 1 CARTON / 28 SPRAY, METERED in 1 CARTRIDGE | — | — | 2015-09-15 | — | Active |
| 00597-0160-61 0597-0160-61 Main listing | 1 CARTRIDGE in 1 CARTON / 60 SPRAY, METERED in 1 CARTRIDGE | $126.08 / g | — | 2015-09-15 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Spiriva Respimat tiotropium bromide inhalation spray 1.562 ug Spray, Metered?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Spiriva Respimat 1.562 ugthis 00597-0160-28 | Boehringer | 1 cartridge | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Tiotropium Oral Inhalation inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Boehringer Ingelheim Pharmaceuticals, Inc. labeler code 00597
- Jentadueto linagliptin and metformin hydrochloride 2.5 mg; 850 mg Tablet, Film Coated NDC 0597-0147-18
- Jentadueto linagliptin and metformin hydrochloride 2.5 mg; 1000 mg Tablet, Film Coated NDC 0597-0148-18
- Jardiance Empagliflozin 10 mg Tablet, Film Coated NDC 0597-0152-07
- Jardiance Empagliflozin 25 mg Tablet, Film Coated NDC 0597-0153-07
- Stiolto Respimat tiotropium bromide and olodaterol 3.124 ug; 2.736 ug Spray, Metered NDC 0597-0155-28
- Synjardy empagliflozin and metformin hydrochloride 5 mg; 500 mg Tablet NDC 0597-0159-18
- Glyxambi empagliflozin and linagliptin 25 mg; 5 mg Tablet, Film Coated NDC 0597-0164-07
- Synjardy empagliflozin and metformin hydrochloride 12.5 mg; 1000 mg Tablet NDC 0597-0168-18
- Synjardy empagliflozin and metformin hydrochloride 5 mg; 1000 mg Tablet NDC 0597-0175-18
- Synjardy empagliflozin and metformin hydrochloride 12.5 mg; 500 mg Tablet NDC 0597-0180-18
- Glyxambi empagliflozin and linagliptin 10 mg; 5 mg Tablet, Film Coated NDC 0597-0182-07
- Striverdi Respimat olodaterol respimat inhalation spray 2.5 ug Spray, Metered NDC 0597-0192-61
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SPIRIVA RESPIMAT is an anticholinergic indicated for: The long-term, once-daily, maintenance treatment of bronchospasm associated with chronic obstructive pulmonary disease (COPD), and for reducing COPD exacerbations ( 1.1 ) The long-term, once-daily, maintenance treatment of asthma in patients 6 years of age and older ( 1.2 ) Limitation of Use: Not indicated for relief of acute bronchospasm ( 1.1 , 1.2 , 5.1 )
1.1Maintenance Treatment of Chronic Obstructive Pulmonary Disease SPIRIVA RESPIMAT (tiotropium bromide) is indicated for the long-term, once-daily, maintenance treatment of bronchospasm associated with chronic obstructive pulmonary disease (COPD), including chronic bronchitis and emphysema. SPIRIVA RESPIMAT is indicated to reduce exacerbations in COPD patients. Important Limitation of Use: SPIRIVA RESPIMAT is NOT indicated for the relief of acute bronchospasm.
1.2Maintenance Treatment of Asthma SPIRIVA RESPIMAT is a bronchodilator indicated for the long-term, once-daily, maintenance treatment of asthma in patients 6 years of age and older . Important Limitation of Use: SPIRIVA RESPIMAT is NOT indicated for the relief of acute bronchospasm.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION To receive the full dosage of medication, SPIRIVA RESPIMAT must be administered as two inhalations once-daily. Do not take more than one dose (2 inhalations) in 24 hours. Prior to first use, the SPIRIVA RESPIMAT cartridge is inserted into the SPIRIVA RESPIMAT inhaler and the unit is primed.
When using the unit for the first time, patients are to actuate the inhaler toward the ground until an aerosol cloud is visible and then repeat the process three more times. The unit is then considered primed and ready for use. If not used for more than 3 days, patients are to actuate the inhaler once to prepare the inhaler for use.
If not used for more than 21 days, patients are to actuate the inhaler until an aerosol cloud is visible and then repeat the process three more times to prepare the inhaler for use [see Patient Counseling Information (17) ]. For oral inhalation only. To receive the full dose of medication, SPIRIVA RESPIMAT must be administered as two inhalations once-daily.
Treatment of COPD: 2 inhalations of SPIRIVA RESPIMAT 2.5 mcg once-daily. ( 2 ) Treatment of asthma patients 6 years and older: 2 inhalations of SPIRIVA RESPIMAT 1.25 mcg once-daily. ( 2 )
2.1Chronic Obstructive Pulmonary Disease The recommended dosage for patients with COPD is 2 inhalations of SPIRIVA RESPIMAT 2.5 mcg per actuation once-daily; total dose equals 5 mcg of SPIRIVA RESPIMAT.
2.2Asthma The recommended dosage for patients with asthma is 2 inhalations of SPIRIVA RESPIMAT 1.25 mcg per actuation once-daily; total dose equals 2.5 mcg of SPIRIVA RESPIMAT. In the treatment of asthma, the maximum benefits in lung function may take up to 4 to 8 weeks of dosing [see Patient Counseling Information (17) ].
2.3Special Populations No dosage adjustment is required for geriatric, hepatically-impaired, or renally-impaired patients. However, patients with moderate to severe renal impairment given SPIRIVA RESPIMAT should be monitored closely for anticholinergic effects [see Warnings and Precautions (5.6) , Use in Specific Populations (8.5 , 8.6 , 8.7) , and Clinical Pharmacology (12.3) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SPIRIVA RESPIMAT consists of a SPIRIVA RESPIMAT inhaler and an aluminum cylinder (SPIRIVA RESPIMAT cartridge) containing tiotropium bromide (as the monohydrate). The SPIRIVA RESPIMAT cartridge is only intended for use with the SPIRIVA RESPIMAT inhaler. SPIRIVA RESPIMAT is available in two dosage strengths.
Each actuation from the SPIRIVA RESPIMAT inhaler delivers 1.25 mcg or 2.5 mcg of tiotropium (equivalent to 1.562 mcg or 3.124 mcg, respectively, of tiotropium bromide monohydrate) from the mouthpiece. Two actuations equal one dose (2.5 mcg or 5 mcg). Inhalation spray: 1.25 mcg or 2.5 mcg tiotropium (equivalent to 1.562 mcg or 3.124 mcg, respectively, of tiotropium bromide monohydrate) per actuation with the SPIRIVA RESPIMAT inhaler.
Two actuations equal one dose (2.5 mcg or 5 mcg). ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS SPIRIVA RESPIMAT is contraindicated in patients with a hypersensitivity to tiotropium, ipratropium, or any component of this product [see Warnings and Precautions (5.2) ] . In clinical trials with SPIRIVA RESPIMAT, immediate hypersensitivity reactions, including angioedema (including swelling of the lips, tongue, or throat), itching, or rash have been reported [see Warnings and Precautions (5.2) ] . Hypersensitivity to tiotropium, ipratropium, or any component of this product.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Not for acute use, i.e., not a rescue medication. ( 5.1 ) Immediate hypersensitivity reactions: Discontinue SPIRIVA RESPIMAT at once and consider alternatives if immediate hypersensitivity reactions, including angioedema, urticaria, rash, bronchospasm, or anaphylaxis, occur. ( 5.2 ) Paradoxical bronchospasm: Discontinue SPIRIVA RESPIMAT and consider other treatments if paradoxical bronchospasm occurs.
( 5.3 ) Worsening of narrow-angle glaucoma may occur. Use with caution in patients with narrow-angle glaucoma and instruct patients to consult a physician immediately if this occurs. ( 5.4 ) Worsening of urinary retention may occur.
Use with caution in patients with prostatic hyperplasia or bladder-neck obstruction and instruct patient to consult a physician immediately if this occurs. ( 5.5 )
5.1Not for Acute Use SPIRIVA RESPIMAT is intended as a once-daily maintenance treatment for COPD and asthma and should not be used for the relief of acute symptoms, i.e., as rescue therapy for the treatment of acute episodes of bronchospasm. In the event of an acute attack, a rapid-acting beta 2 -agonist should be used.
5.2Immediate Hypersensitivity Reactions Immediate hypersensitivity reactions, including urticaria, angioedema (including swelling of the lips, tongue or throat), rash, bronchospasm, anaphylaxis, or itching may occur after administration of SPIRIVA RESPIMAT. If such a reaction occurs, therapy with SPIRIVA RESPIMAT should be stopped at once and alternative treatments should be considered. Given the similar structural formula of atropine to tiotropium, patients with a history of hypersensitivity reactions to atropine or its derivatives should be closely monitored for similar hypersensitivity reactions to SPIRIVA RESPIMAT.
5.3Paradoxical Bronchospasm Inhaled medicines, including SPIRIVA RESPIMAT, may cause paradoxical bronchospasm. If this occurs, it should be treated immediately with an inhaled short-acting beta 2 -agonist such as albuterol. Treatment with SPIRIVA RESPIMAT should be stopped and other treatments considered.
5.4Worsening of Narrow-Angle Glaucoma SPIRIVA RESPIMAT should be used with caution in patients with narrow-angle glaucoma. Prescribers and patients should be alert for signs and symptoms of acute narrow-angle glaucoma (e.g., eye pain or discomfort, blurred vision, visual halos or colored images in association with red eyes from conjunctival congestion and corneal edema). Instruct patients to consult a physician immediately should any of these signs or symptoms develop.
5.5Worsening of Urinary Retention SPIRIVA RESPIMAT should be used with caution in patients with urinary retention. Prescribers and patients should be alert for signs and symptoms of urinary retention (e.g., difficulty passing urine, painful urination), especially in patients with prostatic hyperplasia or bladder-neck obstruction. Instruct patients to consult a physician immediately should any of these signs or symptoms develop.
5.6Renal Impairment As a predominantly renally excreted drug, patients with moderate to severe renal impairment (creatinine clearance of <60 mL/min) treated with SPIRIVA RESPIMAT should be monitored closely for anticholinergic side effects [see Clinical Pharmacology (12.3) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described, or described in greater detail, in other sections: Immediate hypersensitivity reactions [see Warnings and Precautions (5.2) ] Paradoxical bronchospasm [see Warnings and Precautions (5.3) ] Worsening of narrow-angle glaucoma [see Warnings and Precautions (5.4) ] Worsening of urinary retention [see Warnings and Precautions (5.5) ] Because clinical trials are conducted under widely varying conditions, the incidence of adverse reactions observed in the clinical trials of a drug cannot be directly compared to the incidences in the clinical trials of another drug and may not reflect the incidences observed in practice.
Since the same active ingredient (tiotropium bromide) is administered to COPD and asthma patients, prescribers and patients should take into account that the observed adverse reactions could be relevant for both patient populations independent of dosage strength. The most common adverse reactions in: COPD: (>3% incidence in the placebo-controlled trials with treatment durations of between 4 and 48 weeks) were pharyngitis, cough, dry mouth, and sinusitis. ( 6.1 ).
Asthma: (>2% incidence in the placebo-controlled trials with treatment durations of between 12 and 52 weeks) were pharyngitis, headache, bronchitis, and sinusitis in adults. ( 6.2 ). To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience in Chronic Obstructive Pulmonary Disease The SPIRIVA RESPIMAT clinical development program included ten placebo controlled clinical trials in COPD. Two trials were four-week cross-over trials and eight were parallel group trials. The parallel group trials included a three-week dose-ranging trial, two 12-week trials, three 48-week trials, and two trials of 4-week and 24-week duration conducted for a different program that contained tiotropium bromide 5 mcg treatment arms.
The primary safety database consists of pooled data from the 7 randomized, parallel-group, double-blind, placebo-controlled studies of 4-48 weeks in treatment duration. These trials included 6,565 adult COPD patients (75% males and 25% females) 40 years of age and older. Of these patients, 3,282 patients were treated with SPIRIVA RESPIMAT 5 mcg and 3,283 received placebo.
The SPIRIVA RESPIMAT 5 mcg group was composed mostly of Caucasians (78%) with a mean age of 65 years and a mean baseline percent predicted post-bronchodilator FEV 1 of 46%. In these 7 clinical trials, 68.3% of patients exposed to SPIRIVA RESPIMAT 5 mcg reported an adverse event compared to 68.7% of patients in the placebo group. There were 68 deaths in the SPIRIVA RESPIMAT 5 mcg treatment group (2.1%) and 52 deaths (1.6%) in patients who received placebo [see Clinical Studies (14) Long-term Active-Controlled Mortality Trial: Survival ] .
The percentage of SPIRIVA RESPIMAT patients who discontinued due to an adverse event were 7.3% compared to 10% with placebo patients. The percentage of SPIRIVA RESPIMAT 5 mcg patients who experienced a serious adverse event were 15.0% compared to 15.1% with placebo patients. In both groups, the adverse event most commonly leading to discontinuation was COPD exacerbation (SPIRIVA RESPIMAT 2.0%, placebo 4.0%) which was also the most frequent serious adverse event.
The most commonly reported adverse reactions were pharyngitis, cough, dry mouth, and sinusitis (Table 1). Other adverse reactions reported in individual patients and consistent with possible anticholinergic effects included constipation, dysuria, and urinary retention. Table 1 shows all adverse reactions that occurred with an incidence of >3% in the SPIRIVA RESPIMAT 5 mcg treatment group, and a higher incidence rate on SPIRIVA RESPIMAT 5 mcg than on placebo.
Table 1 Number (Percentage) of COPD Patients Exposed to SPIRIVA RESPIMAT 5 mcg with Adverse Reactions >3% (and Higher than Placebo): Pooled Data f… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Anticholinergics: May interact additively with concomitantly used anticholinergic medications. Avoid administration of SPIRIVA RESPIMAT with other anticholinergic-containing drugs. ( 7.2 )
7.1Concomitant Respiratory Medications SPIRIVA RESPIMAT has been used concomitantly with short-acting and long-acting sympathomimetic (beta-agonists) bronchodilators, methylxanthines, oral and inhaled steroids, antihistamines, mucolytics, leukotriene modifiers, cromones, and anti-IgE treatment without increases in adverse reactions.
7.2Anticholinergics There is potential for an additive interaction with concomitantly used anticholinergic medications. Therefore, avoid coadministration of SPIRIVA RESPIMAT with other anticholinergic-containing drugs as this may lead to an increase in anticholinergic adverse effects [see Warnings and Precautions (5.4 , 5.5) and Adverse Reactions (6) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Patients with moderate to severe renal impairment should be monitored closely for potential anticholinergic side effects. ( 2 , 8.6 )
8.1Pregnancy Risk Summary The limited human data with SPIRIVA RESPIMAT use during pregnancy are insufficient to inform a drug-associated risk of adverse pregnancy-related outcomes. There are risks to the mother and the fetus associated with poorly controlled asthma in pregnancy (see Clinical Considerations ) . Based on animal reproduction studies, no structural abnormalities were observed when tiotropium was administered by inhalation to pregnant rats and rabbits during the period of organogenesis at doses 790 and 8 times, respectively, the maximum recommended human daily inhalation dose (MRHDID).
Increased post-implantation loss was observed in rats and rabbits administered tiotropium at maternally toxic doses 430 times and 40 times the MRHDID, respectively (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Poorly or moderately controlled asthma in pregnancy increases the maternal risk of preeclampsia and infant prematurity, low birth weight, and small for gestational age. The level of asthma control should be closely monitored in pregnant women and treatment adjusted as necessary to maintain optimal control.
Data Animal Data In 2 separate embryo-fetal development studies, pregnant rats and rabbits received tiotropium during the period of organogenesis at doses up to approximately 790 and 8 times the maximum recommended human daily inhalation dose (MRHDID), respectively (on a mcg/m 2 basis at inhalation doses of 1,471 and 7 mcg/kg/day in rats and rabbits, respectively). No evidence of structural abnormalities was observed in rats or rabbits. However, in rats, tiotropium caused fetal resorption, litter loss, decreases in the number of live pups at birth and the mean pup weights, and a delay in pup sexual maturation at tiotropium doses of approximately 40 times the MRHDID (on a mcg/m 2 basis at a maternal inhalation dose of 78 mcg/kg/day).
In rabbits, tiotropium caused an increase in post-implantation loss at a tiotropium dose of approximately 430 times the MRHDID (on a mcg/m 2 basis at a maternal inhalation dose of 400 mcg/kg/day). Such effects were not observed at approximately 5 and 95 times the MRHDID, respectively (on a mcg/m 2 basis at inhalation doses of 9 and 88 mcg/kg/day in rats and rabbits, respectively).
8.2Lactation Risk Summary There are no data on the presence of tiotropium in human milk, the effects on the breastfed infant, or the effects on milk production. Tiotropium is present in milk of lactating rats; however, due to species-specific differences in lactation physiology, the clinical relevance of these data are not clear (see Data ) . The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for SPIRIVA RESPIMAT and any potential adverse effects on the breastfed child from SPIRIVA RESPIMAT or from the underlying maternal condition.
Data The distribution of tiotropium bromide into milk was investigated after a single intravenous administration of 10 mg/kg to lactating rats. Tiotropium and/or its metabolites are present in the milk of lactating rats at concentrations above those in plasma.
8.4Pediatric Use The safety and efficacy of SPIRIVA RESPIMAT 2.5 mcg have been established in pediatric patients aged 6 to 17 years with asthma in 6 clinical trials up to 1 year in duration. In three clinical trials, 327 patients aged 12 to 17 years with asthma were treated with SPIRIVA RESPIMAT… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited human data with SPIRIVA RESPIMAT use during pregnancy are insufficient to inform a drug-associated risk of adverse pregnancy-related outcomes. There are risks to the mother and the fetus associated with poorly controlled asthma in pregnancy (see Clinical Considerations ) . Based on animal reproduction studies, no structural abnormalities were observed when tiotropium was administered by inhalation to pregnant rats and rabbits during the period of organogenesis at doses 790 and 8 times, respectively, the maximum recommended human daily inhalation dose (MRHDID).
Increased post-implantation loss was observed in rats and rabbits administered tiotropium at maternally toxic doses 430 times and 40 times the MRHDID, respectively (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Poorly or moderately controlled asthma in pregnancy increases the maternal risk of preeclampsia and infant prematurity, low birth weight, and small for gestational age. The level of asthma control should be closely monitored in pregnant women and treatment adjusted as necessary to maintain optimal control.
Data Animal Data In 2 separate embryo-fetal development studies, pregnant rats and rabbits received tiotropium during the period of organogenesis at doses up to approximately 790 and 8 times the maximum recommended human daily inhalation dose (MRHDID), respectively (on a mcg/m 2 basis at inhalation doses of 1,471 and 7 mcg/kg/day in rats and rabbits, respectively). No evidence of structural abnormalities was observed in rats or rabbits. However, in rats, tiotropium caused fetal resorption, litter loss, decreases in the number of live pups at birth and the mean pup weights, and a delay in pup sexual maturation at tiotropium doses of approximately 40 times the MRHDID (on a mcg/m 2 basis at a maternal inhalation dose of 78 mcg/kg/day).
In rabbits, tiotropium caused an increase in post-implantation loss at a tiotropium dose of approximately 430 times the MRHDID (on a mcg/m 2 basis at a maternal inhalation dose of 400 mcg/kg/day). Such effects were not observed at approximately 5 and 95 times the MRHDID, respectively (on a mcg/m 2 basis at inhalation doses of 9 and 88 mcg/kg/day in rats and rabbits, respectively).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of SPIRIVA RESPIMAT 2.5 mcg have been established in pediatric patients aged 6 to 17 years with asthma in 6 clinical trials up to 1 year in duration. In three clinical trials, 327 patients aged 12 to 17 years with asthma were treated with SPIRIVA RESPIMAT 2.5 mcg; in three additional clinical trials, 345 patients aged 6 to 11 years with asthma were treated with SPIRIVA RESPIMAT 2.5 mcg. Patients in these age groups demonstrated efficacy results similar to those observed in patients aged 18 years and older with asthma [see Clinical Studies (14.2) ] .
The safety and efficacy of SPIRIVA RESPIMAT have not been established in pediatric patients less than 6 years of age. The safety of SPIRIVA RESPIMAT 2.5 mcg has been studied in pediatric patients with asthma aged 1 to 5 years who were on background treatment of at least ICS in one placebo-controlled clinical trial of 12 weeks duration (36 treated with SPIRIVA RESPIMAT 2.5 mcg and 34 with placebo RESPIMAT). In this study, SPIRIVA RESPIMAT or placebo RESPIMAT was delivered with the AeroChamber Plus Flow-Vu ® valved holding chamber with facemask once daily.
The majority of the patients in the trial were male (60.4%) and Caucasian (76.2%) with a mean age of 3.1 years. The adverse reaction profile was similar to that observed in adults and older pediatric patients [see Adverse Reactions (6.2) ] . In Vitro Characterization Studies with Valved Holding Chamber Dose delivery and fine particle fraction of SPIRIVA RESPIMAT when administered via a valved holding chamber (AeroChamber Plus Flow-Vu ® with or without face mask) was assessed by in vitro studies.
Inspiratory flow rates of 4.9, 8.0, and
12.0L/min in combination with holding times of 0, 2, 5, and 10 seconds were tested. The flow rates were selected to be representative of inspiratory flow rates of children aged 6 to 12 months, 2 to 5 years, and over 5 years, respectively. Table 3 summarizes the results for delivered dose under the respective test conditions and configurations.
Table 3 In Vitro Medication Delivery through AeroChamber Plus Flow-Vu ® Valved Holding Chamber with Face Mask at Different Flow Rates and Holding Times Using the Dose 2.5 mcg (as two actuations) Flow Rate (L/min) and corresponding age Mask Holding Time (seconds) Mean Medication Delivery through AeroChamber Plus Flow-Vu ® per Dose (mcg) Body Weight 50 th Percentile (kg) a Medication Delivered per Dose (ng/kg) b a Centers for Disease Control and Prevention growth charts, developed by the National Center for Health Statistics in collaboration with the National Center for Chronic Disease Prevention and Health Promotion (2009).
Body weight values correspond to the average of the 50 percentile weight for boys and girls at the ages indicated. b Inhalation of SPIRIVA RESPIMAT 2.5 mcg dose (as two actuations) in a 70-kg adult without use of a valved holding chamber and mask delivers approximately 2.5 mcg, or 36 ng/kg. 4.9 (6 to 12 Months) small 0 2 5 10 0.85 0.86 0.55 0.62 7.5-9.9 86-113 87-115 56-73 63-83 8.0 (2 to 5 Years) medium 0 2 5 10 0.74 0.93 0.72 0.57 12.3-18.0 41-60 52-76 40-59 32-46 12.0 (> 5 Years) medium 0 2 5 10 1.16 0.96 0.78 0.61 18.0 64 53 43 34 The in vitro study data show a reduction of the absolute delivered dose through the valved holding chamber.
However, in terms of dose per kilogram of body weight the data suggest that under all tested conditions the dose of SPIRIVA RESPIMAT delivered by the AeroChamber Plus Flow-Vu ® valved holding chamber with mask will at least lead to a dosing comparable to that of adults without use of a holding chamber and mask (Table 3). The fine particle fraction (<5 µm) across the flow rates used in these studies was 69-89% of the delivered dose through the valved holding chamber, consistent with the removal of the coarser fraction by the holding chamber.
In contrast, the fine particle fraction for SPIRIVA RESPIMAT delivered without a holding chamber typically represents approxim… [Excerpted — this section continues on DailyMed.]
🧓 Geriatric Use ▾
8.5Geriatric Use Based on available data, no adjustment of SPIRIVA RESPIMAT dosage in geriatric patients is warranted [see Clinical Pharmacology (12.3) ]. Thirty nine percent of SPIRIVA RESPIMAT clinical trial patients with COPD were between 65 and 75 years of age and 14% were greater than or equal to 75 years of age. Approximately seven percent of SPIRIVA RESPIMAT clinical trial patients with asthma were greater than or equal to 65 years of age.
The adverse drug reaction profiles were similar in the older population compared to the patient population overall.
🆘 Overdosage ▾
10 OVERDOSAGE High doses of tiotropium may lead to anticholinergic signs and symptoms. However, there were no systemic anticholinergic adverse effects following a single inhaled dose of up to 282 mcg tiotropium dry powder in 6 healthy volunteers. Dry mouth/throat and dry nasal mucosa occurred in a dose-dependent [10-40 mcg daily] manner, following 14-day dosing of up to 40 mcg tiotropium bromide inhalation solution in healthy subjects.
Treatment of overdosage consists of discontinuation of SPIRIVA RESPIMAT together with institution of appropriate symptomatic and/or supportive therapy.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tiotropium is a long-acting, antimuscarinic agent, which is often referred to as an anticholinergic. It has similar affinity to the subtypes of muscarinic receptors, M 1 to M 5 . In the airways, it exhibits pharmacological effects through inhibition of M 3 -receptors at the smooth muscle leading to bronchodilation.
The competitive and reversible nature of antagonism was shown with human and animal origin receptors and isolated organ preparations. In preclinical in vitro as well as in vivo studies, prevention of methacholine-induced bronchoconstriction effects was dose-dependent and lasted longer than 24 hours. The bronchodilation following inhalation of tiotropium is predominantly a site-specific effect.
12.2Pharmacodynamics Cardiac Electrophysiology In a multicenter, randomized, double-blind trial using tiotropium dry powder for inhalation that enrolled 198 patients with COPD, the number of subjects with changes from baseline-corrected QT interval of 30 to 60 msec was higher in the SPIRIVA group as compared with placebo. This difference was apparent using both the Bazett (QTcB) [20 (20%) patients vs. 12 (12%) patients] and Fredericia (QTcF) [16 (16%) patients vs.
1 (1%) patient] corrections of QT for heart rate. No patients in either group had either QTcB or QTcF of >500 msec. Other clinical trials with SPIRIVA did not detect an effect of the drug on QTc intervals.
The effect of tiotropium dry powder for inhalation on QT interval was also evaluated in a randomized, placebo- and positive-controlled crossover study in 53 healthy volunteers. Subjects received tiotropium inhalation powder 18 mcg, 54 mcg (3 times the recommended dose), or placebo for 12 days. ECG assessments were performed at baseline and throughout the dosing interval following the first and last dose of study medication.
Relative to placebo, the maximum mean change from baseline in study-specific QTc interval was 3.2 msec and 0.8 msec for tiotropium inhalation powder 18 mcg and 54 mcg, respectively. No subject showed a new onset of QTc >500 msec or QTc changes from baseline of ≥60 msec.
12.3Pharmacokinetics Tiotropium is administered as an inhalation spray. Some of the pharmacokinetic data described below were obtained with higher doses than recommended for therapy. A dedicated pharmacokinetic study in patients with COPD evaluating once-daily tiotropium delivered from the RESPIMAT inhaler (5 mcg) and as inhalation powder (18 mcg) from the HandiHaler resulted in a similar systemic exposure between the two products.
Absorption Following inhalation of the solution by young healthy volunteers, urinary excretion data suggests that approximately 33% of the inhaled dose reaches the systemic circulation. Oral solutions of tiotropium have an absolute bioavailability of 2% to 3%. Food is not expected to influence the absorption of tiotropium for the same reason.
Following 4-week SPIRIVA RESPIMAT once daily dosing, maximum tiotropium plasma concentrations were observed 5-7 minutes after inhalation in COPD and asthma patients. Distribution The drug has a plasma protein binding of 72% and shows a volume of distribution of 32 L/kg after an intravenous dose to young healthy volunteers. Local concentrations in the lung are not known, but the mode of administration suggests substantially higher concentrations in the lung.
Studies in rats have shown that tiotropium does not penetrate the blood-brain barrier. Elimination Metabolism The extent of metabolism is small. This is evident from a urinary excretion of 74% of unchanged substance after an intravenous dose to young healthy volunteers.
Tiotropium, an ester, is nonenzymatically cleaved to the alcohol N-methylscopine and dithienylglycolic acid, neither of which binds to muscarinic receptors. In vitro experiments with human liver microsomes and human hepatocytes suggest that a fraction of the administered dose (74% of an intravenous dose is excreted unchanged in the urine, leavi… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tiotropium is a long-acting, antimuscarinic agent, which is often referred to as an anticholinergic. It has similar affinity to the subtypes of muscarinic receptors, M 1 to M 5 . In the airways, it exhibits pharmacological effects through inhibition of M 3 -receptors at the smooth muscle leading to bronchodilation.
The competitive and reversible nature of antagonism was shown with human and animal origin receptors and isolated organ preparations. In preclinical in vitro as well as in vivo studies, prevention of methacholine-induced bronchoconstriction effects was dose-dependent and lasted longer than 24 hours. The bronchodilation following inhalation of tiotropium is predominantly a site-specific effect.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SPIRIVA RESPIMAT Inhalation Spray is supplied in a carton containing one SPIRIVA RESPIMAT cartridge and one SPIRIVA RESPIMAT inhaler. The SPIRIVA RESPIMAT cartridge is provided as an aluminum cylinder with a tamper protection seal on the cap. The SPIRIVA RESPIMAT cartridge is only intended for use with the SPIRIVA RESPIMAT inhaler and should not be interchanged with any other RESPIMAT device delivered product.
The SPIRIVA RESPIMAT inhaler is a cylindrical shaped plastic inhalation device with a gray colored body and a clear base. The clear base is removed to insert the cartridge. The inhaler contains a dose indicator.
The written information on the label of the gray inhaler body indicates that it is labeled for use with the SPIRIVA RESPIMAT cartridge. SPIRIVA RESPIMAT Inhalation Spray is available in two dosage strengths, identified by dose delivered per actuation and by the color of the cap and associated container label: aqua represents 2.5 mcg per actuation; blue represents 1.25 mcg per actuation. To deliver the recommended dosage for COPD: SPIRIVA RESPIMAT Inhalation Spray 2.5 mcg/actuation 60 metered actuations (NDC 0597-0100-61) SPIRIVA RESPIMAT Inhalation Spray 2.5 mcg/actuation 10 metered actuations (NDC 0597-0100-51) (institutional pack) To deliver the recommended dosage for asthma: SPIRIVA RESPIMAT Inhalation Spray 1.25 mcg/actuation 60 metered actuations (NDC 0597-0160-61) The SPIRIVA RESPIMAT cartridge for each strength has a net fill weight of 4 grams and when used with the SPIRIVA RESPIMAT inhaler, is designed to deliver the labeled number of metered actuations after preparation for use.
Each actuation from the SPIRIVA RESPIMAT inhaler delivers 1.25 mcg or 2.5 mcg of tiotropium (equivalent to 1.562 mcg or 3.124 mcg, respectively, of tiotropium bromide monohydrate) from the mouthpiece. When the labeled number of actuations has been dispensed from the inhaler, the RESPIMAT locking mechanism will be engaged and no more actuations can be dispensed. After assembly, the SPIRIVA RESPIMAT inhaler should be discarded at the latest 3 months after first use or when the locking mechanism is engaged, whichever comes first.
Keep out of reach of children. Do not spray into eyes. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Avoid freezing.
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Avoid freezing.
📋 Description ▾
11 DESCRIPTION The active component of SPIRIVA RESPIMAT is tiotropium. The drug substance, tiotropium bromide monohydrate, is an anticholinergic with specificity for muscarinic receptors. It is chemically described as (1α, 2β, 4β, 5α, 7β)-7-[(Hydroxydi-2-thienylacetyl)oxy]-9,9-dimethyl-3-oxa-9-azoniatricyclo[3.3.1.0 2,4 ] nonane bromide monohydrate.
It is a synthetic, non-chiral, quaternary ammonium compound. Tiotropium bromide is a white or yellowish white powder. It is sparingly soluble in water and soluble in methanol.
The structural formula is: Tiotropium bromide (monohydrate) has a molecular mass of 490.4 and a molecular formula of C 19 H 22 NO 4 S 2 Br ∙ H 2 O. The drug product, SPIRIVA RESPIMAT, is composed of a sterile, aqueous solution of tiotropium bromide filled into a 4.5 mL plastic container crimped into an aluminum cylinder (SPIRIVA RESPIMAT cartridge) for use with the SPIRIVA RESPIMAT inhaler. Excipients include benzalkonium chloride, edetate disodium, hydrochloric acid, and water for injection.
The SPIRIVA RESPIMAT cartridge is only intended for use with the SPIRIVA RESPIMAT inhaler. The RESPIMAT inhaler is a hand held, pocket sized oral inhalation device that uses mechanical energy to generate a slow-moving aerosol cloud of medication from a metered volume of the drug solution. When used with the SPIRIVA RESPIMAT inhaler, each cartridge containing 4 grams of sterile aqueous solution delivers the labeled number of metered actuations after preparation for use.
Each dose (one dose equals two actuations) from the SPIRIVA RESPIMAT inhaler delivers 2.5 mcg or 5 mcg of tiotropium (equivalent to 3.124 mcg or 6.247 mcg, respectively, of tiotropium bromide monohydrate) in 22.1 mcL from the mouthpiece. As with all inhaled drugs, the actual amount of drug delivered to the lung may depend on patient factors, such as the coordination between the actuation of the inhaler and inspiration through the delivery system. The duration of inspiration should be at least as long as the spray duration (1.5 seconds).
Prior to first use, the SPIRIVA RESPIMAT cartridge is inserted into the SPIRIVA RESPIMAT inhaler and the unit is primed. When using the unit for the first time, patients are to actuate the inhaler toward the ground until an aerosol cloud is visible and then repeat the process three more times. The unit is then considered primed and ready for use.
If not used for more than 3 days, patients are to actuate the inhaler once to prepare the inhaler for use. If not used for more than 21 days, patients are to actuate the inhaler until an aerosol cloud is visible and then repeat the process three more times to prepare the inhaler for use [see Patient Counseling Information (17) ]. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Instructions for Use). Not for Acute Use Instruct patients that SPIRIVA RESPIMAT is a once-daily maintenance bronchodilator and should not be used for immediate relief of breathing problems, (i.e., as a rescue medication). Immediate Hypersensitivity Reactions Inform patients that anaphylaxis, angioedema (including swelling of the lips, tongue, or throat), urticaria, rash, bronchospasm, or itching, may occur after administration of SPIRIVA RESPIMAT.
Advise patient to immediately discontinue treatment and consult a physician should any of these signs or symptoms develop. Paradoxical Bronchospasm Inform patients that SPIRIVA RESPIMAT can produce paradoxical bronchospasm. Advise patients that if paradoxical bronchospasm occurs, patients should discontinue SPIRIVA RESPIMAT.
Worsening of Narrow-Angle Glaucoma Instruct patients to be alert for signs and symptoms of narrow-angle glaucoma (e.g., eye pain or discomfort, blurred vision, visual halos or colored images in association with red eyes from conjunctival congestion and corneal edema). Instruct patients to consult a physician immediately should any of these signs and symptoms develop. Inform patients that care must be taken not to allow the aerosol cloud to enter into the eyes as this may cause blurring of vision and pupil dilation.
Since dizziness and blurred vision may occur with the use of SPIRIVA RESPIMAT, caution patients about engaging in activities such as driving a vehicle or operating appliances or machinery. Worsening of Urinary Retention Instruct patients to be alert for signs and symptoms of urinary retention (e.g., difficulty passing urine, painful urination). Instruct patients to consult a physician immediately should any of these signs or symptoms develop.
Treatment of Asthma Instruct asthma patients that the maximum benefits may only be apparent after 4 to 8 weeks of SPIRIVA RESPIMAT treatment. Instructions for Administering SPIRIVA RESPIMAT It is important for patients to understand how to correctly administer SPIRIVA inhalation spray using the SPIRIVA RESPIMAT inhaler. Instruct patients that SPIRIVA inhalation spray should only be administered via the SPIRIVA RESPIMAT inhaler and the SPIRIVA RESPIMAT inhaler should not be used for administering other medications.
Instruct patients that priming SPIRIVA RESPIMAT is essential to ensure appropriate content of the medication in each actuation. When using the unit for the first time, the SPIRIVA RESPIMAT cartridge is inserted into the SPIRIVA RESPIMAT inhaler and the unit is primed. SPIRIVA RESPIMAT patients are to actuate the inhaler toward the ground until an aerosol cloud is visible and then to repeat the process three more times.
The unit is then considered primed and ready for use. If not used for more than 3 days, patients are to actuate the inhaler once to prepare the inhaler for use. If not used for more than 21 days, patients are to actuate the inhaler until an aerosol cloud is visible and then repeat the process three more times to prepare the inhaler for use.
Instruct caregivers of children that SPIRIVA RESPIMAT should be used with an adult's assistance.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Tiotropium is administered as an inhalation spray. Some of the pharmacokinetic data described below were obtained with higher doses than recommended for therapy. A dedicated pharmacokinetic study in patients with COPD evaluating once-daily tiotropium delivered from the RESPIMAT inhaler (5 mcg) and as inhalation powder (18 mcg) from the HandiHaler resulted in a similar systemic exposure between the two products.
Absorption Following inhalation of the solution by young healthy volunteers, urinary excretion data suggests that approximately 33% of the inhaled dose reaches the systemic circulation. Oral solutions of tiotropium have an absolute bioavailability of 2% to 3%. Food is not expected to influence the absorption of tiotropium for the same reason.
Following 4-week SPIRIVA RESPIMAT once daily dosing, maximum tiotropium plasma concentrations were observed 5-7 minutes after inhalation in COPD and asthma patients. Distribution The drug has a plasma protein binding of 72% and shows a volume of distribution of 32 L/kg after an intravenous dose to young healthy volunteers. Local concentrations in the lung are not known, but the mode of administration suggests substantially higher concentrations in the lung.
Studies in rats have shown that tiotropium does not penetrate the blood-brain barrier. Elimination Metabolism The extent of metabolism is small. This is evident from a urinary excretion of 74% of unchanged substance after an intravenous dose to young healthy volunteers.
Tiotropium, an ester, is nonenzymatically cleaved to the alcohol N-methylscopine and dithienylglycolic acid, neither of which binds to muscarinic receptors. In vitro experiments with human liver microsomes and human hepatocytes suggest that a fraction of the administered dose (74% of an intravenous dose is excreted unchanged in the urine, leaving 25% for metabolism) is metabolized by cytochrome P450-dependent oxidation and subsequent glutathione conjugation to a variety of Phase II metabolites. This enzymatic pathway can be inhibited by CYP450 2D6 and 3A4 inhibitors, such as quinidine, ketoconazole, and gestodene.
Thus, CYP450 2D6 and 3A4 are involved in the metabolic pathway that is responsible for the elimination of a small part of the administered dose. In vitro studies using human liver microsomes showed that tiotropium in supra-therapeutic concentrations does not inhibit CYP450 1A1, 1A2, 2B6, 2C9, 2C19, 2D6, 2E1, or 3A4. Excretion The terminal half-life of tiotropium in COPD and asthma patients following once daily inhalation is 25 and 44 hours, respectively.
Total clearance was 880 mL/min after an intravenous dose in young healthy volunteers. Intravenously administered tiotropium bromide is mainly excreted unchanged in urine (74%). Following 21-day once daily inhalation of 5 mcg of the solution by patients with COPD, 24-hour urinary excretion is 18.6% (0.93 mcg) of the dose.
The renal clearance of tiotropium exceeds the creatinine clearance, indicating secretion into the urine. In comparison, 12.8% (0.32 mcg) of the dose was excreted unchanged in the urine over 24 hours at steady state after inhalation of 2.5 mcg in patients with asthma. After chronic once-daily inhalation by COPD and asthma patients, pharmacokinetic steady-state was reached by day 7 with no accumulation thereafter.
Specific Populations Geriatric Patients As expected for all predominantly renally excreted drugs, advancing age was associated with a decrease of tiotropium renal clearance (347 mL/min in COPD patients <65 years to 275 mL/min in COPD patients ≥65 years). This did not result in a corresponding increase in AUC 0-6,ss and C max,ss values following inhalation of the solution. Exposure to tiotropium was not found to differ with age in patients with asthma.
Pediatric Patients The peak and total exposure to tiotropium was not found to differ between pediatric patients (aged 6 to 17 years) and adults with asthma. Renal Impairment Following 4-week SPIRIVA RESPIMAT 5… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology In a multicenter, randomized, double-blind trial using tiotropium dry powder for inhalation that enrolled 198 patients with COPD, the number of subjects with changes from baseline-corrected QT interval of 30 to 60 msec was higher in the SPIRIVA group as compared with placebo. This difference was apparent using both the Bazett (QTcB) [20 (20%) patients vs. 12 (12%) patients] and Fredericia (QTcF) [16 (16%) patients vs.
1 (1%) patient] corrections of QT for heart rate. No patients in either group had either QTcB or QTcF of >500 msec. Other clinical trials with SPIRIVA did not detect an effect of the drug on QTc intervals.
The effect of tiotropium dry powder for inhalation on QT interval was also evaluated in a randomized, placebo- and positive-controlled crossover study in 53 healthy volunteers. Subjects received tiotropium inhalation powder 18 mcg, 54 mcg (3 times the recommended dose), or placebo for 12 days. ECG assessments were performed at baseline and throughout the dosing interval following the first and last dose of study medication.
Relative to placebo, the maximum mean change from baseline in study-specific QTc interval was 3.2 msec and 0.8 msec for tiotropium inhalation powder 18 mcg and 54 mcg, respectively. No subject showed a new onset of QTc >500 msec or QTc changes from baseline of ≥60 msec.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Chronic Obstructive Pulmonary Disease The efficacy of SPIRIVA RESPIMAT compared to placebo was evaluated in 6 clinical trials: one dose-ranging trial and 5 confirmatory trials (Trials 1-5). In addition, SPIRIVA RESPIMAT was compared to SPIRIVA HandiHaler in a long-term active-controlled trial in COPD (Trial 6). Dose-Ranging Trial Dose selection for the Phase III clinical program was supported by a 3-week randomized, double-blind, placebo and active-controlled, parallel group trial in 202 COPD patients.
A total of five doses of tiotropium RESPIMAT (1.25 to 20 mcg) were evaluated compared to placebo. Results demonstrated numerical improvements in FEV 1 at all doses compared to placebo. The difference in trough FEV 1 from placebo for the 1.25, 2.5, 5, 10 and 20 mcg once daily doses were
0.08L (95% CI -0.03, 0.20),
0.03L (-0.08, 0.15),
0.13L (0.02, 0.25),
0.11L (-0.004, 0.224), and
0.13L (0.01, 0.24), respectively. Based on these results, the 5 and 10 mcg doses were further evaluated in the confirmatory COPD trials. Confirmatory Trials A total of 6,614 COPD patients (2,801 receiving SPIRIVA RESPIMAT 5 mcg and 2,798 receiving placebo) were studied in the five confirmatory trials of SPIRIVA RESPIMAT.
Trials 1 and 2 were 12-week, randomized, double-blind, placebo- and active- (ipratropium) controlled trials that evaluated bronchodilation. Trials 3-5 were 48-week, randomized, double-blind, placebo-controlled, trials that evaluated bronchodilation and effects on COPD exacerbations. Trials 1-4 included both the tiotropium RESPIMAT 5 mcg and 10 mcg doses, whereas Trial 5 included only the 5 mcg dose.
These trials enrolled patients who had a clinical diagnosis of COPD, were 40 years of age or older, had a history of smoking greater than 10 pack-years, had an FEV 1 less than or equal to 60% of predicted and a ratio of FEV 1 /FVC of less than or equal to 0.7. All treatments were administered once-daily in the morning. Change from baseline in trough FEV 1 was a primary endpoint in all trials.
Trials 3-5 included COPD exacerbations as primary endpoints. Baseline patient characteristics were similar across the five individual confirmatory trials, except for race in Trial 5 in which there were more Asian patients (30%) compared to other trials (<1%). The mean age ranged from 62 to 66 years.
Most patients were male (64-78%), ex-smokers (57-65%) and Caucasian (69-99%). Mean pre-bronchodilator FEV 1 was between 1.03 and
1.26L with a mean FEV 1 /FVC ratio of 42-50%. Except for LABAs and other inhaled anticholinergic agents, other pulmonary medications were allowed as concomitant therapy in Trials 1-4. LABA use was permitted in Trial 5.
Effect on Lung Function SPIRIVA RESPIMAT 5 mcg demonstrated significant improvement in trough FEV 1 compared to placebo in all 5 confirmatory trials (Table 4). The change from baseline in trough FEV 1 over time from Trial 4 is depicted in Figure 1 and is representative of the other two 48-week trials. In Trials 3 and 4 patients treated with SPIRIVA RESPIMAT 5 mcg also used less rescue medication compared to patients on placebo.
Table 4 Mean Change from Baseline in Trough FEV 1 (L) at End of Treatment Trial SPIRIVA RESPIMAT 5 mcg N Placebo N Trough FEV 1 (L) at End of Treatment Difference from placebo (95% CI) † at week 12 ‡ at week 48 Trial 1† 85 87 0.11 (0.04, 0.18) Trial 2† 90 84 0.13 (0.07, 0.18) Trial 3‡ 326 296 0.14 (0.10, 0.18) Trial 4‡ 324 307 0.11 (0.08, 0.15) Trial 5‡ 1,889 1,870 0.10 (0.09, 0.12) Figure 1 Trough FEV 1 Change from Baseline over 48 weeks (Trial 4), SPIRIVA RESPIMAT 5 mcg Figure 1 Exacerbations Trials 3, 4, and 5 also evaluated the effect of SPIRIVA RESPIMAT 5 mcg on COPD exacerbations.
For Trials 3 and 4, a pooled analysis of exacerbation rate per patient year was pre-specified as a primary endpoint, while the primary endpoint for Trial 5 was time to first exacerbation. Trial 5 also included exacerbation rate per patient year as a secondary endpoint. Exacerbatio… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of tumorigenicity was observed in a 104-week inhalation study in rats at tiotropium doses up to 59 mcg/kg/day, in an 83-week inhalation study in female mice at doses up to 145 mcg/kg/day, and in a 101-week inhalation study in male mice at doses up to 2 mcg/kg/day. These doses correspond to approximately 30, 40, and 0.5, times the maximum recommended human daily inhalation dose (MRHDID) on a mcg/m 2 basis, respectively. Tiotropium bromide demonstrated no evidence of mutagenicity or clastogenicity in the following assays: the bacterial gene mutation assay, the V79 Chinese hamster cell mutagenesis assay, the chromosomal aberration assays in human lymphocytes in vitro and mouse micronucleus formation in vivo , and the unscheduled DNA synthesis in primary rat hepatocytes in vitro assay.
In rats, decreases in the number of corpora lutea and the percentage of implants were noted at inhalation tiotropium doses of 78 mcg/kg/day or greater (approximately 40 times the MRHDID on a mcg/m 2 basis). No such effects were observed at 9 mcg/kg/day (approximately 5 times the MRHDID on a mcg/m 2 basis). The fertility index, however, was not affected at inhalation doses up to 1,689 mcg/kg/day (approximately 910 times the MRHDID on a mcg/m 2 basis).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of tumorigenicity was observed in a 104-week inhalation study in rats at tiotropium doses up to 59 mcg/kg/day, in an 83-week inhalation study in female mice at doses up to 145 mcg/kg/day, and in a 101-week inhalation study in male mice at doses up to 2 mcg/kg/day. These doses correspond to approximately 30, 40, and 0.5, times the maximum recommended human daily inhalation dose (MRHDID) on a mcg/m 2 basis, respectively. Tiotropium bromide demonstrated no evidence of mutagenicity or clastogenicity in the following assays: the bacterial gene mutation assay, the V79 Chinese hamster cell mutagenesis assay, the chromosomal aberration assays in human lymphocytes in vitro and mouse micronucleus formation in vivo , and the unscheduled DNA synthesis in primary rat hepatocytes in vitro assay.
In rats, decreases in the number of corpora lutea and the percentage of implants were noted at inhalation tiotropium doses of 78 mcg/kg/day or greater (approximately 40 times the MRHDID on a mcg/m 2 basis). No such effects were observed at 9 mcg/kg/day (approximately 5 times the MRHDID on a mcg/m 2 basis). The fertility index, however, was not affected at inhalation doses up to 1,689 mcg/kg/day (approximately 910 times the MRHDID on a mcg/m 2 basis).
📄 Patient Package Insert ▾
Instructions for Use SPIRIVA ® RESPIMAT ® (speh REE vah - RES peh mat) (tiotropium bromide inhalation spray), for oral inhalation use For oral inhalation only Do not spray SPIRIVA RESPIMAT into your eyes. Read this Instructions for Use before you start using SPIRIVA RESPIMAT and each time you get a refill. There may be new information.
This leaflet does not take the place of talking to your doctor about your medical condition or your treatment. You will need to use this inhaler 1 time each day, at the same time each day. Each time you use it take 2 puffs.
Use SPIRIVA RESPIMAT exactly as prescribed by your doctor. Do not change your dose or how often you use SPIRIVA RESPIMAT without talking with your doctor. Children should use SPIRIVA RESPIMAT with the help of an adult, as instructed by their doctor.
Tell your doctor about all of the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. SPIRIVA RESPIMAT may affect the way some medicines work and some other medicines may affect the way SPIRIVA RESPIMAT works. Do not use other inhaled medicines with SPIRIVA RESPIMAT without talking to your doctor.
The SPIRIVA RESPIMAT inhaler has a slow-moving mist that helps you inhale the medicine. Do not turn the clear base before inserting the cartridge. Your SPIRIVA RESPIMAT may have either an aqua or a blue cap, depending on the strength prescribed by your doctor.
The steps shown below should be followed. How to store your SPIRIVA RESPIMAT inhaler Store SPIRIVA RESPIMAT at room temperature between 68°F to 77°F (20°C to 25°C). Do not freeze your SPIRIVA RESPIMAT cartridge and inhaler.
If SPIRIVA RESPIMAT has not been used for more than 3 days, release 1 puff towards the ground. If SPIRIVA RESPIMAT has not been used for more than 21 days, repeat steps 4 to 6 under the "Prepare for first use" until a mist is visible. Then repeat steps 4 to 6 three more times.
Keep your SPIRIVA RESPIMAT cartridge, inhaler, and all medicines out of the reach of children. How to care for your SPIRIVA RESPIMAT inhaler Clean the mouthpiece, including the metal part inside the mouthpiece, with a damp cloth or tissue only, at least 1 time each week. Any minor discoloration in the mouthpiece does not affect your SPIRIVA RESPIMAT inhaler.
When to get a new SPIRIVA RESPIMAT inhaler The scale on your inhaler shows the number of puffs in the inhaler. You should use 2 puffs 1 time each day. The dose indicator shows approximately how many puffs are left in the inhaler.
When the dose indicator enters the red area of the scale you need to refill your prescription as soon as possible. When the dose indicator reaches the end of the red scale, your SPIRIVA RESPIMAT is empty and automatically locks. At this point, the clear base cannot be turned any further.
Three months after insertion of cartridge, throw away the SPIRIVA RESPIMAT even if it has not been used, or when the inhaler is locked, or when it expires, whichever comes first. Prepare for first use 1. Remove clear base Keep the cap closed.
Press the safety catch while firmly pulling off the clear base with your other hand. Be careful not to touch the piercing element. Write the discard by date on the label (3 months from the date the cartridge is inserted).
2. Insert cartridge Insert the narrow end of the cartridge into the inhaler. Place the inhaler on a firm surface and push down firmly until it clicks into place.
3. Replace clear base Put the clear base back into place until it clicks. Do not remove the clear base or the cartridge after it has been put together.
4. Turn Keep the cap closed. Turn the clear base in the direction of the arrows on the label until it clicks (half a turn).
5. Open Open the cap until it snaps fully open. 6.
Press Point the inhaler toward the ground. Press the dose-release button. Close the cap.
If you do not see a mist, repeat steps 4 to 6 until a mist is seen. After a mist is seen, repeat steps 4 to 6 three more times. After complete pre… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
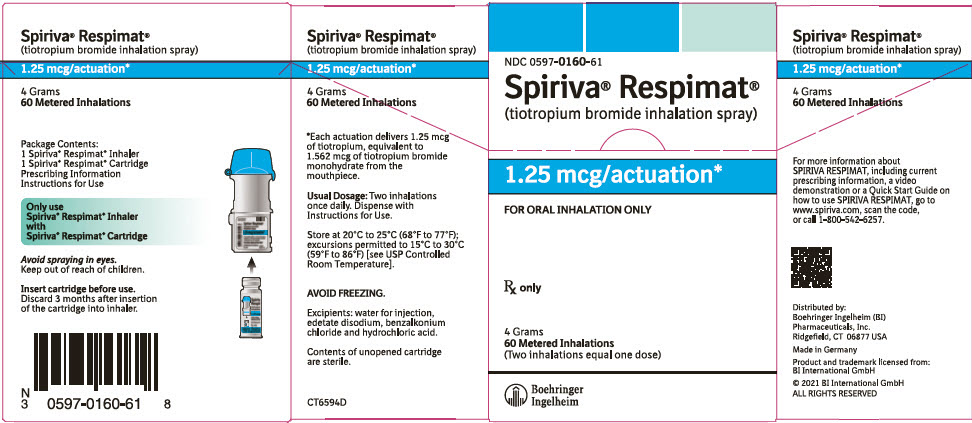
PRINCIPAL DISPLAY PANEL - 1.25 mcg Cartridge Carton NDC 0597-0160-61 Spiriva ® Respimat ® (tiotropium bromide inhalation spray) 1.25 mcg/actuation* FOR ORAL INHALATION ONLY ATTENTION PHARMACIST: Dispense with Instructions for Use Rx only 4 Grams 60 Metered Inhalations (Two inhalations equal one dose) Boehringer Ingelheim PRINCIPAL DISPLAY PANEL - 1.25 mcg Cartridge Carton
PRINCIPAL DISPLAY PANEL - 2.5 mcg Cartridge Carton NDC 0597-0100-61 Spiriva ® Respimat ® (tiotropium bromide inhalation spray) 2.5 mcg/actuation* FOR ORAL INHALATION ONLY ATTENTION PHARMACIST: Dispense with Instructions for Use Rx only 4 Grams 60 Metered Inhalations (Two inhalations equal one dose) Boehringer Ingelheim PRINCIPAL DISPLAY PANEL - 2.5 mcg Cartridge Carton
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |