
Metformin Hydrochloride 500 mg Tablet, Film Coated, 30-count — NDC 0615-8015-39 (Billing 00615-8015-39)
This is a package of 30 tablets of Metformin Hydrochloride 500 mg Tablet, Film Coated from NCS HealthCare of KY, LLC dba Vangard Labs, marketed since Jan 2005 and currently FDA-listed, this package's marketing is listed to end Jan 2027.
Other active recalls for Metformin Hydrochloride (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 861004
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Biguanide class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Metformin is used alone or with other medications, including insulin, to treat type 2 diabetes (condition in which the body does not use insulin normally and, therefore, cannot control the amount of sugar in the blood). Metformin is in a class of drugs called biguanides. Metformin helps to control the amount of glucose (sugar) in your blood. It decreases the amount of glucose you absorb from your food and the amount of glucose made by your liver. Metformin also increases your body's response to insulin, a natural substance that controls the amount of glucose in the blood. Metformin is not used...
Read the full MedlinePlus article ↗- Metformin works in three ways: it lowers the amount of sugar your liver dumps into your bloodstream, slows how much sugar your gut absorbs from food, and helps your body respond to...
- What exactly is metformin doing for my diabetes?
- Yes, this is very common — diarrhea, nausea, and stomach discomfort are the most frequently reported side effects, and they're often worst when you first start or when your dose go...
- My stomach has been a mess since I started metformin. Is that normal? Will it get better?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Metformin Hydrochloride — tap one for details:
Metformin Hydrochloride may be associated with lower levels of 4 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.0671 | $2.01 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00615-8015-05 0615-8015-05 Main listing | 15 TABLET, FILM COATED in 1 BLISTER PACK | 2005-01-14 | Jan 31, 2027 | Active |
| 00615-8015-30 0615-8015-30 | 6 BLISTER PACK in 1 BOX, UNIT-DOSE / 5 TABLET, FILM COATED in 1 BLISTER PACK | 2019-04-24 | Jan 31, 2027 | Active |
| 00615-8015-39 You're viewing this | 30 TABLET, FILM COATED in 1 BLISTER PACK | 2005-01-14 | Jan 31, 2027 | Active |
| 00615-8015-28 0615-8015-28 | 28 TABLET, FILM COATED in 1 BLISTER PACK | 2024-04-23 | Jan 31, 2027 | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00615-8015-05?
What NDC number is used to bill for this package of Metformin Hydrochloride 500 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Metformin Hydrochloride 500 mg 71093-0132-04 | ACI | 100 tablets | $0.014 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 00378-7185-05 | Mylan | 500 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 00904-7162-61 | Major | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 23155-0841-01 | Heritage | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 42385-0947-01 | Laurus | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin HCl 500 mg 49483-0622-01 | TIME | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 59651-0854-01 | Aurobindo | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 60687-0155-01 | American | 1 tablet | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 62135-0680-05 | Chartwell | 500 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 65862-0008-01 | Aurobindo | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin HCl 500 mg 67877-0561-01 | Ascend | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 67877-0930-01 | Ascend | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 68094-0688-60 | Precision | 500 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 68382-0758-01 | Zydus | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin hydrochloride 500 mg 68645-0582-59 | Legacy | 60 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 69367-0180-01 | Westminster | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 69367-0381-01 | Westminster | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 70010-0063-01 | Granules | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 82009-0046-10 | Quallent | 1000 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 82009-0174-10 | Quallent | 1000 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 83301-0008-01 | Mullan | 100 tablets | $0.015 | AB | Availability likely | — |
| Metformin Hydrochloride 500 mg 24658-0790-01 | PuraCap | 100 tablets | $0.017 | AB | FDA listed | — |
| Metformin Hydrochloride 500 mgthis 00615-8015-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 00615-8629-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 25000-0134-03 | MARKSANS | 30 tablets | — | AB | FDA listed | — |
| Metformin hydrochloride 500 mg 33342-0141-10 | Macleods | 90 tablets | — | — | FDA listed | — |
| Metformin HCl 500 mg 42708-0009-60 | QPharma, | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 42806-0313-01 | Epic | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 43063-0527-14 | PD-Rx | 14 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride 500 mg 43353-0982-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-2081-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 50090-3064-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 50090-4891-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-6485-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-6858-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-6859-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7010-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7011-00 | A-S | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7013-00 | A-S | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7278-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7280-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7595-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7597-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50228-0105-00 | ScieGen | 9000 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 51655-0556-25 | Northwind | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 53746-0218-01 | Amneal | 100 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride 500 mg 55154-4172-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 60429-0111-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 62207-0440-43 | Granules | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 63187-0238-90 | Proficient | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 63629-8501-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 63629-8502-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 67046-0298-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 67046-1594-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 67877-0217-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68071-3518-08 | NuCare | 180 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 68071-3541-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68071-3739-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68071-3900-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68788-4076-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68788-8498-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68788-8564-01 | Preferred | 100 tablets | — | AB | Discontinued | — |
| Metformin Hydrochloride 500 mg 68788-8652-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 70518-1149-01 | REMEDYREPACK | 1 tablet | — | AB | Discontinued | — |
| Metformin Hydrochloride 500 mg 70518-1951-01 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Metformin Hydrochloride 500 mg 70518-2833-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 70882-0124-56 | Cambridge | 56 tablets | — | AB | Discontinued | — |
| Metformin HCl 500 mg 71205-0562-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71205-0622-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71205-0784-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71205-0882-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 71335-1072-00 | Bryant | 25 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-1834-00 | Bryant | 25 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-2224-00 | Bryant | 25 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-2466-00 | Bryant | 25 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-3132-00 | Bryant | 25 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0917-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0920-53 | Aphena | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0929-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 71709-0110-06 | Metcure | 500 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 72162-1522-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 72189-0219-30 | direct | 30 tablets | — | AB | FDA listed | — |
| Metformin HCL 500 mg 72189-0617-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Metformin HCL 500 mg 72189-0658-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 72789-0192-20 | PD-Rx | 20 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 72789-0531-42 | PD-Rx | 42 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 72789-0561-20 | PD-Rx | 20 tablets | — | AB | FDA listed | — |
| Metformin HCl 500 mg 82868-0049-90 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 65841-0809-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 70518-4698-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68071-5306-08 | NuCare | 180 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 82804-0309-78 | Proficient | 180 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 42708-0203-60 | QPharma,Inc. | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-8041-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-8043-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Metformin Hydrochloride 500 mg 68071-5323-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LACTIC ACIDOSIS Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio; and metformin plasma levels generally >5 mcg/mL (see PRECAUTIONS ).
Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g. carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., acute congestive heart failure), excessive alcohol intake, and hepatic impairment. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided (see DOSAGE AND ADMINISTRATION , CONTRAINDICATONS , and PRECAUTIONS ).
If metformin-associated lactic acidosis is suspected, immediately discontinue metformin hydrochloride tablets and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended (see PRECAUTIONS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Metformin hydrochloride tablets are indicated as an adjunct to diet and exercise to improve glycemic control in adults and children with type 2 diabetes mellitus.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION There is no fixed dosage regimen for the management of hyperglycemia in patients with type 2 diabetes with metformin or any other pharmacologic agent. Dosage of metformin must be individualized on the basis of both effectiveness and tolerance, while not exceeding the maximum recommended daily doses. The maximum recommended daily dose of metformin hydrochloride tablets is 2550 mg in adults and 2000 mg in pediatric patients (10 to 16 years of age).
Metformin hydrochloride tablets should be given in divided doses with meals and should be started at a low dose, with gradual dose escalation, to reduce gastrointestinal side effects and to permit identification of the minimum dose required for adequate glycemic control of the patient. During treatment initiation and dose titration (see Recommended Dosing Schedule ), fasting plasma glucose should be used to determine the therapeutic response to metformin and identify the minimum effective dose for the patient. Thereafter, glycosylated hemoglobin should be measured at intervals of approximately 3 months.
The therapeutic goal should be to decrease both fasting plasma glucose and glycosylated hemoglobin levels to normal or near normal by using the lowest effective dose of metformin, either when used as monotherapy or in combination with sulfonylurea or insulin. Monitoring of blood glucose and glycosylated hemoglobin will also permit detection of primary failure, i.e., inadequate lowering of blood glucose at the maximum recommended dose of medication, and secondary failure, i.e., loss of an adequate blood glucose lowering response after an initial period of effectiveness.
Short-term administration of metformin may be sufficient during periods of transient loss of control in patients usually well-controlled on diet alone. Recommended Dosing Schedule Adults The usual starting dose of metformin hydrochloride tablets is 500 mg twice a day or 850 mg once a day, given with meals. In general, clinically significant responses are not seen at doses below 1500 mg per day.
Dosage increases should be made in increments of 500 mg weekly or 850 mg every 2 weeks, up to a total of 2000 mg per day, given in divided doses. The dosage of metformin hydrochloride tablets must be individualized on the basis of both effectiveness and tolerability. Patients can also be titrated from 500 mg twice a day to 850 mg twice a day after 2 weeks.
For those patients requiring additional glycemic control, metformin hydrochloride tablets may be given to a maximum daily dose of 2550 mg per day. Doses above 2000 mg may be better tolerated given 3 times a day with meals. Pediatrics The usual starting dose of metformin hydrochloride tablets is 500 mg twice a day, given with meals.
Dosage increases should be made in increments of 500 mg weekly up to a maximum of 2000 mg per day, given in divided doses. The dosage of metformin hydrochloride tablets must be individualized on the basis of both effectiveness and tolerability. Recommendations for Use in Renal Impairment Assess renal function prior to initiation of metformin hydrochloride tablets and periodically thereafter.
Metformin hydrochloride tablet is contraindicated in patients with an estimated glomerular filtration rate (eGFR) below 30 mL/minute/1.73 m 2 . Initiation of metformin hydrochloride tablets in patients with an eGFR between 30 to 45 mL/minute/1.73 m 2 is not recommended. In patients taking metformin hydrochloride tablets whose eGFR later falls below 45 mL/min/1.73 m 2 , assess the benefit risk of continuing therapy.
Discontinue metformin hydrochloride tablets if the patient's eGFR later falls below 30 mL/minute/1.73 m 2 (See WARNINGS and PRECAUTIONS ). Discontinuation for Iodinated Contrast Imaging Procedures Discontinue metformin hydrochloride tablets at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR between 30 and 60 mL/min/1.73 m 2 ; in patients with a history of liver disease, alcoholism or h… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Metformin hydrochloride tablets are contraindicated in patients with: Severe renal impairment (eGFR below 30 mL/min/1.73 m 2 ) (see WARNINGS and PRECAUTIONS ). Known hypersensitivity to metformin hydrochloride. Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma. Diabetic ketoacidosis should be treated with insulin.
⚠️ Warnings ▾
WARNINGS WARNING: LACTIC ACIDOSIS Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio; and metformin plasma levels generally >5 mcg/mL (see PRECAUTIONS ).
Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g. carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., acute congestive heart failure), excessive alcohol intake, and hepatic impairment. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided (see DOSAGE AND ADMINISTRATION , CONTRAINDICATONS , and PRECAUTIONS ).
If metformin-associated lactic acidosis is suspected, immediately discontinue metformin hydrochloride tablets and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended (see PRECAUTIONS ).
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In a U.S. double-blind clinical study of metformin hydrochloride tablets in patients with type 2 diabetes, a total of 141 patients received metformin hydrochloride tablets therapy (up to 2550 mg per day) and 145 patients received placebo. Adverse reactions reported in greater than 5% of the metformin hydrochloride tablets patients, and that were more common in metformin hydrochloride tablets- than placebo-treated patients, are listed in Table 11 . Table 11: Most Common Adverse Reactions (>5 Percent) in a Placebo-Controlled Clinical Study of Metformin Hydrochloride Tablets Monotherapy* Adverse Reaction Metformin Hydrochloride Tablets Monotherapy (n = 141) Placebo (n = 145) % of Patients * Reactions that were more common in metformin hydrochloride tablets- than placebo-treated patients.
Diarrhea 53.2
11.7Nausea/Vomiting 25.5
8.3Flatulence 12.1
5.5Asthenia 9.2
5.5Indigestion 7.1
4.1Abdominal Discomfort 6.4
4.8Headache 5.7
4.8Diarrhea led to discontinuation of study medication in 6% of patients treated with metformin hydrochloride tablets. Additionally, the following adverse reactions were reported in ≥ 1% to ≤ 5% of metformin hydrochloride tablets patients and were more commonly reported with metformin hydrochloride tablets than placebo: abnormal stools, hypoglycemia, myalgia, lightheaded, dyspnea, nail disorder, rash, sweating increased, taste disorder, chest discomfort, chills, flu syndrome, flushing, palpitation. Cholestatic, hepatocellular, and mixed hepatocellular liver injury have been reported with postmarketing use of metformin.
Pediatric Patients In clinical trials with metformin hydrochloride tablets in pediatric patients with type 2 diabetes, the profile of adverse reactions was similar to that observed in adults.
🔄 Drug Interactions ▾
Drug Interactions (Clinical Evaluation of Drug Interactions Conducted with Metformin Hydrochloride Tablets) Glyburide— In a single-dose interaction study in type 2 diabetes patients, coadministration of metformin and glyburide did not result in any changes in either metformin pharmacokinetics or pharmacodynamics. Decreases in glyburide AUC and C max were observed, but were highly variable. The single-dose nature of this study and the lack of correlation between glyburide blood levels and pharmacodynamic effects, makes the clinical significance of this interaction uncertain (see DOSAGE AND ADMINISTRATION: Concomitant Metformin and Oral Sulfonylurea Therapy in Adult Patients ).
Furosemide— A single-dose, metformin-furosemide drug interaction study in healthy subjects demonstrated that pharmacokinetic parameters of both compounds were affected by coadministration. Furosemide increased the metformin plasma and blood C max by 22% and blood AUC by 15%, without any significant change in metformin renal clearance. When administered with metformin, the C max and AUC of furosemide were 31% and 12% smaller, respectively, than when administered alone, and the terminal half-life was decreased by 32%, without any significant change in furosemide renal clearance.
No information is available about the interaction of metformin and furosemide when coadministered chronically. Nifedipine— A single-dose, metformin-nifedipine drug interaction study in normal healthy volunteers demonstrated that coadministration of nifedipine increased plasma metformin C max and AUC by 20% and 9%, respectively, and increased the amount excreted in the urine. T max and half-life were unaffected.
Nifedipine appears to enhance the absorption of metformin. Metformin had minimal effects on nifedipine. Drugs that reduce metformin clearance— Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2] / multidrug and toxin extrusion [MATE] inhibitors such as ranolazine, vandetanib, dolutegravir, and cimetidine) could increase systemic exposure to metformin and may increase the risk for lactic acidosis.
Consider the benefits and risks of concomitant use. Such interaction between metformin and oral cimetidine has been observed in normal healthy volunteers in both single- and multiple-dose, metformin-cimetidine drug interaction studies, with a 60% increase in peak metformin plasma and whole blood concentrations and a 40% increase in plasma and whole blood metformin AUC. There was no change in elimination half-life in the single-dose study.
Metformin had no effect on cimetidine pharmacokinetics. In healthy volunteers, the pharmacokinetics of metformin and propranolol, and metformin and ibuprofen were not affected when coadministered in single-dose interaction studies. Metformin is negligibly bound to plasma proteins and is, therefore, less likely to interact with highly protein-bound drugs such as salicylates, sulfonamides, chloramphenicol, and probenecid, as compared to the sulfonylureas, which are extensively bound to serum proteins.
Other— Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control. These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, and isoniazid. When such drugs are administered to a patient receiving metformin hydrochloride tablets, the patient should be closely observed for loss of blood glucose control.
When such drugs are withdrawn from a patient receiving metformin hydrochloride tablets, the patient should be observed closely for hypoglycemia. Carbonic anhydrase inhibitors — Topiramate or other carbonic anhydrase inhibitors (e.g., zonisamide, acetazolamide or dichlorphenamide) frequently cause a decrease in serum bicarbonate and induce non-anion gap, hy… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects: Pregnancy Category B Recent information strongly suggests that abnormal blood glucose levels during pregnancy are associated with a higher incidence of congenital abnormalities. Most experts recommend that insulin be used during pregnancy to maintain blood glucose levels as close to normal as possible. Because animal reproduction studies are not always predictive of human response, metformin should not be used during pregnancy unless clearly needed.
There are no adequate and well-controlled studies in pregnant women with metformin. Metformin was not teratogenic in rats and rabbits at doses up to 600 mg/kg/day. This represents an exposure of about 2 and 6 times the maximum recommended human daily dose of 2000 mg based on body surface area comparisons for rats and rabbits, respectively.
Determination of fetal concentrations demonstrated a partial placental barrier to metformin.
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of metformin hydrochloride tablets for the treatment of type 2 diabetes have been established in pediatric patients ages 10 to 16 years (studies have not been conducted in pediatric patients below the age of 10 years). Use of metformin hydrochloride tablets in this age group is supported by evidence from adequate and well-controlled studies of metformin hydrochloride tablets in adults with additional data from a controlled clinical study in pediatric patients ages 10 to 16 years with type 2 diabetes, which demonstrated a similar response in glycemic control to that seen in adults.
(See CLINICAL PHARMACOLOGY: Pediatric Clinical Studies .) In this study, adverse effects were similar to those described in adults. (See ADVERSE REACTIONS: Pediatric Patients . ) A maximum daily dose of 2000 mg is recommended. (see DOSAGE AND ADMINISTRATION: Recommended Dosing Schedule: Pediatrics . )
🧓 Geriatric Use ▾
Geriatric Use Controlled clinical studies of metformin did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients, although other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of lactic acidosis.
Assess renal function more frequently in elderly patients (see WARNINGS , PRECAUTIONS , and DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE Overdose of metformin hydrochloride has occurred, including ingestion of amounts greater than 50 grams. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin hydrochloride has been established. Lactic acidosis has been reported in approximately 32% of metformin overdose cases (see WARNINGS ).
Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Metformin is an antihyperglycemic agent which improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose. Its pharmacologic mechanisms of action are different from other classes of oral antihyperglycemic agents. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
Unlike sulfonylureas, metformin does not produce hypoglycemia in either patients with type 2 diabetes or normal subjects (except in special circumstances, see PRECAUTIONS ) and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease. Pharmacokinetics Absorption and Bioavailability The absolute bioavailability of a metformin hydrochloride 500 mg tablet given under fasting conditions is approximately 50% to 60%.
Studies using single oral doses of metformin hydrochloride tablets 500 to 1500 mg, and 850 to 2550 mg, indicate that there is a lack of dose proportionality with increasing doses, which is due to decreased absorption rather than an alteration in elimination. Food decreases the extent of and slightly delays the absorption of metformin, as shown by approximately a 40% lower mean peak plasma concentration (C max ), a 25% lower area under the plasma concentration versus time curve (AUC), and a 35-minute prolongation of time to peak plasma concentration (T max ) following administration of a single 850 mg tablet of metformin with food, compared to the same tablet strength administered fasting.
The clinical relevance of these decreases is unknown. Distribution The apparent volume of distribution (V/F) of metformin following single oral doses of metformin hydrochloride tablets 850 mg averaged 654 ± 358 L. Metformin is negligibly bound to plasma proteins, in contrast to sulfonylureas, which are more than 90% protein bound.
Metformin partitions into erythrocytes, most likely as a function of time. At usual clinical doses and dosing schedules of metformin hydrochloride tablets, steady state plasma concentrations of metformin are reached within 24 to 48 hours and are generally <1 mcg/mL. During controlled clinical trials of metformin hydrochloride tablets, maximum metformin plasma levels did not exceed 5 mcg/mL, even at maximum doses.
Metabolism and Elimination Intravenous single-dose studies in normal subjects demonstrate that metformin is excreted unchanged in the urine and does not undergo hepatic metabolism (no metabolites have been identified in humans) nor biliary excretion. Renal clearance (see Table 1 ) is approximately 3.5 times greater than creatinine clearance, which indicates that tubular secretion is the major route of metformin elimination. Following oral administration, approximately 90% of the absorbed drug is eliminated via the renal route within the first 24 hours, with a plasma elimination half-life of approximately 6.2 hours.
In blood, the elimination half-life is approximately 17.6 hours, suggesting that the erythrocyte mass may be a compartment of distribution. Specific Populations Patients with Type 2 Diabetes In the presence of normal renal function, there are no differences between single- or multiple-dose pharmacokinetics of metformin between patients with type 2 diabetes and normal subjects (see Table 1 ), nor is there any accumulation of metformin in either group at usual clinical doses. Renal Impairment In patients with decreased renal function, the plasma and blood half-life of metformin is prolonged and the renal clearance is decreased (see Table 1 ; also see CONTRAINDICATIONS , WARNINGS , PRECAUTIONS , and DOSAGE AND ADMINISTRATION ).
Hepatic Impairment No pharmacokinetic studies of metformin have been conducted in patients with hepatic insufficiency (see PRECAUTIONS ). Geriatrics Limited data fro… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action Metformin is an antihyperglycemic agent which improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose. Its pharmacologic mechanisms of action are different from other classes of oral antihyperglycemic agents. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
Unlike sulfonylureas, metformin does not produce hypoglycemia in either patients with type 2 diabetes or normal subjects (except in special circumstances, see PRECAUTIONS ) and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Metformin hydrochloride tablets, USP are supplied as: Metformin Hydrochloride Tablets, USP 500 mg: White, biconvex, circular shaped film coated tablets with ‘A’ debossed on one side and ‘12’ debossed on the other side. Blistercards of 30 NDC 0615-8015-39 Blistercards of 28 NDC 0615-8015-28 Blistercards of 15 NDC 0615-8015-05 Unit dose boxes of 30 NDC 0615-8015-30 Metformin Hydrochloride Tablets, USP 850 mg : White, biconvex, circular shaped film coated tablets with ‘A’ debossed on one side and ‘13’ debossed on the other side.
Blistercards of 30 NDC 0615-8105-39 Metformin Hydrochloride Tablets, USP 1000 mg : White, biconvex, oval shaped film coated tablets with a score line in between ‘1’ and ‘4’ on one side and ‘A’ debossed on the other side. Blistercards of 30 NDC 0615-7982-39 Blistercards of 15 NDC 0615-7982-05 Unit dose boxes of 30 NDC 0615-7982-30 Storage Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Dispense in light-resistant containers.
📋 Description ▾
DESCRIPTION Metformin hydrochloride tablets, USP are oral antihyperglycemic drugs used in the management of type 2 diabetes. Metformin hydrochloride ( N,N- dimethylimidodicarbonimidic diamide hydrochloride) is not chemically or pharmacologically related to any other classes of oral antihyperglycemic agents. The structural formula is as shown: Metformin hydrochloride, USP is a white to off-white crystalline compound with a molecular formula of C 4 H 11 N 5 • HCl and a molecular weight of 165.63.
Metformin hydrochloride, USP is freely soluble in water and is practically insoluble in acetone, ether, and chloroform. The pK a of metformin is 12.4. The pH of a 1% aqueous solution of metformin hydrochloride is 6.68.
Metformin hydrochloride tablets, USP for oral administration, contains 500 mg, 850 mg, or 1000 mg of metformin hydrochloride, USP. Each tablet contains the inactive ingredients povidone and magnesium stearate. In addition, the coating for the 500 mg, 850 mg, and 1000 mg contains hypromellose and polyethylene glycol.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Patients should be informed of the potential risks and benefits of metformin and of alternative modes of therapy. They should also be informed about the importance of adherence to dietary instructions, of a regular exercise program, and of regular testing of blood glucose, glycosylated hemoglobin, renal function, and hematologic parameters. The risks of lactic acidosis, its symptoms, and conditions that predispose to its development, as noted in the WARNINGS and PRECAUTIONS sections, should be explained to patients.
Patients should be advised to discontinue metformin immediately and to promptly notify their health practitioner if unexplained hyperventilation, myalgia, malaise, unusual somnolence, or other nonspecific symptoms occur. Once a patient is stabilized on any dose level of metformin, gastrointestinal symptoms, which are common during initiation of metformin therapy, are unlikely to be drug related. Later occurrence of gastrointestinal symptoms could be due to lactic acidosis or other serious disease.
Patients should be counseled against excessive alcohol intake, either acute or chronic, while receiving metformin. Metformin hydrochloride tablets alone does not usually cause hypoglycemia, although it may occur when metformin is used in conjunction with oral sulfonylureas and insulin. When initiating combination therapy, the risks of hypoglycemia, its symptoms and treatment, and conditions that predispose to its development should be explained to patients and responsible family members.
(See Patient Information printed below.)
⚠️ Precautions ▾
PRECAUTIONS General Lactic acidosis - There have been postmarketing cases of metformin-associated lactic acidosis, including fatal cases. These cases had a subtle onset and were accompanied by nonspecific symptoms such as malaise, myalgias, abdominal pain, respiratory distress, or increased somnolence; however, hypotension and resistant bradyarrhythmias have occurred with severe acidosis. Metformin-associated lactic acidosis was characterized by elevated blood lactate concentrations (>5 mmol/L), anion gap acidosis (without evidence of ketonuria or ketonemia), and an increased lactate: pyruvate ratio; metformin plasma levels were generally >5 mcg/mL.
Metformin decreases liver uptake of lactate increasing lactate blood levels which may increase the risk of lactic acidosis, especially in patients at risk. If metformin-associated lactic acidosis is suspected, general supportive measures should be instituted promptly in a hospital setting, along with immediate discontinuation of metformin hydrochloride tablets. In metformin hydrochloride tablets treated patients with a diagnosis or strong suspicion of lactic acidosis, prompt hemodialysis is recommended to correct the acidosis and remove accumulated metformin (metformin hydrochloride is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions).
Hemodialysis has often resulted in reversal of symptoms and recovery. Educate patients and their families about the symptoms of lactic acidosis and, if these symptoms occur, instruct them to discontinue metformin hydrochloride tablets and report these symptoms to their healthcare provider. For each of the known and possible risk factors for metformin-associated lactic acidosis, recommendations to reduce the risk of and manage metformin-associated lactic acidosis are provided below: Renal impairment— The postmarketing metformin-associated lactic acidosis cases primarily occurred in patients with significant renal impairment.
The risk of metformin accumulation and metformin-associated lactic acidosis increases with the severity of renal impairment because metformin is substantially excreted by the kidney. Clinical recommendations based upon the patient's renal function include (see DOSAGE AND ADMINISTRATION , CLINICAL PHARMACOLOGY ): Before initiating metformin hydrochloride tablets, obtain an estimated glomerular filtration rate (eGFR) Metformin hydrochloride tablet is contraindicated in patients with an eGFR less than 30 mL/min/1.73 m 2 (see CONTRAINDCATIONS ).
Initiation of metformin hydrochloride tablets are not recommended in patients with eGFR between 30 to 45 mL/min/1.73 m 2 . Obtain an eGFR at least annually in all patients taking metformin hydrochloride tablets. In patients at risk for the development of renal impairment (e.g., the elderly), renal function should be assessed more frequently.
In patients taking metformin hydrochloride tablets whose eGFR falls below 45 mL/min/1.73 m 2 , assess the benefit and risk of continuing therapy. Drug interactions - The concomitant use of metformin hydrochloride tablets with specific drugs may increase the risk of metformin-associated lactic acidosis: those that impair renal function, result in significant hemodynamic change, interfere with acid-base balance, or increase metformin accumulation. Consider more frequent monitoring of patients.
Age 65 or greater —The risk of metformin-associated lactic acidosis increases with the patient's age because elderly patients have a greater likelihood of having hepatic, renal, or cardiac impairment than younger patients. Assess renal function more frequently in elderly patients. Radiologic studies contrast —Administration of intravascular iodinated contrast agents in metformin-treated patients has led to an acute decrease in renal function and the occurrence of lactic acidosis.
Stop metformin hydrochloride tablets at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR between 30 and 60 mL/min/1.7… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Studies in lactating rats show that metformin is excreted into milk and reaches levels comparable to those in plasma. Similar studies have not been conducted in nursing mothers. Because the potential for hypoglycemia in nursing infants may exist, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
If metformin is discontinued, and if diet alone is inadequate for controlling blood glucose, insulin therapy should be considered.
🧬 Pharmacokinetics ▾
Pharmacokinetics Absorption and Bioavailability The absolute bioavailability of a metformin hydrochloride 500 mg tablet given under fasting conditions is approximately 50% to 60%. Studies using single oral doses of metformin hydrochloride tablets 500 to 1500 mg, and 850 to 2550 mg, indicate that there is a lack of dose proportionality with increasing doses, which is due to decreased absorption rather than an alteration in elimination. Food decreases the extent of and slightly delays the absorption of metformin, as shown by approximately a 40% lower mean peak plasma concentration (C max ), a 25% lower area under the plasma concentration versus time curve (AUC), and a 35-minute prolongation of time to peak plasma concentration (T max ) following administration of a single 850 mg tablet of metformin with food, compared to the same tablet strength administered fasting.
The clinical relevance of these decreases is unknown. Distribution The apparent volume of distribution (V/F) of metformin following single oral doses of metformin hydrochloride tablets 850 mg averaged 654 ± 358 L. Metformin is negligibly bound to plasma proteins, in contrast to sulfonylureas, which are more than 90% protein bound.
Metformin partitions into erythrocytes, most likely as a function of time. At usual clinical doses and dosing schedules of metformin hydrochloride tablets, steady state plasma concentrations of metformin are reached within 24 to 48 hours and are generally <1 mcg/mL. During controlled clinical trials of metformin hydrochloride tablets, maximum metformin plasma levels did not exceed 5 mcg/mL, even at maximum doses.
Metabolism and Elimination Intravenous single-dose studies in normal subjects demonstrate that metformin is excreted unchanged in the urine and does not undergo hepatic metabolism (no metabolites have been identified in humans) nor biliary excretion. Renal clearance (see Table 1 ) is approximately 3.5 times greater than creatinine clearance, which indicates that tubular secretion is the major route of metformin elimination. Following oral administration, approximately 90% of the absorbed drug is eliminated via the renal route within the first 24 hours, with a plasma elimination half-life of approximately 6.2 hours.
In blood, the elimination half-life is approximately 17.6 hours, suggesting that the erythrocyte mass may be a compartment of distribution.
🔬 Clinical Studies ▾
Clinical Studies In a double-blind, placebo-controlled, multicenter U.S. clinical trial involving obese patients with type 2 diabetes whose hyperglycemia was not adequately controlled with dietary management alone (baseline fasting plasma glucose [FPG] of approximately 240 mg/dL), treatment with metformin hydrochloride tablets (up to 2550 mg/day) for 29 weeks resulted in significant mean net reductions in fasting and postprandial plasma glucose (PPG) and hemoglobin A 1c (HbA 1c ) of 59 mg/dL, 83 mg/dL, and 1.8%, respectively, compared to the placebo group (see Table 2 ).
Table 2: Metformin Hydrochloride Tablets vs Placebo Summary of Mean Changes from Baseline* in Fasting Plasma Glucose, HbA1c, and Body Weight, at Final Visit (29-week study) Metformin Hydrochloride Tablets (n = 141) Placebo (n = 145) p–Value FPG (mg/dL) Baseline Change at FINAL VISIT 241.5 -53 237.7
6.3NS** 0.001 Hemoglobin A 1c (%) Baseline Change at FINAL VISIT 8.4 -1.4 8.2
0.4NS** 0.001 Body Weight (lbs) Baseline Change at FINAL VISIT 201 -1.4 206 -2.4 NS ** NS ** *All patients on diet therapy at Baseline **Not statistically significant A 29-week, double-blind, placebo-controlled study of metformin hydrochloride tablets and glyburide, alone and in combination, was conducted in obese patients with type 2 diabetes who had failed to achieve adequate glycemic control while on maximum doses of glyburide (baseline FPG of approximately 250 mg/dL) (see Table 3 ). Patients randomized to the combination arm started therapy with metformin hydrochloride tablets 500 mg and glyburide 20 mg.
At the end of each week of the first 4 weeks of the trial, these patients had their dosages of metformin hydrochloride tablets increased by 500 mg if they had failed to reach target fasting plasma glucose. After week 4, such dosage adjustments were made monthly, although no patient was allowed to exceed metformin hydrochloride tablets 2500 mg. Patients in the metformin hydrochloride tablets only arm (metformin plus placebo) followed the same titration schedule.
At the end of the trial, approximately 70% of the patients in the combination group were taking metformin hydrochloride tablets 2000 mg/glyburide 20 mg or metformin hydrochloride tablets 2500 mg/glyburide 20 mg. Patients randomized to continue on glyburide experienced worsening of glycemic control, with mean increases in FPG, PPG, and HbA 1c of 14 mg/dL, 3 mg/dL, and 0.2% respectively. In contrast, those randomized to metformin hydrochloride tablets (up to 2500 mg/day) experienced a slight improvement, with mean reductions in FPG, PPG, and HbA 1c of 1 mg/dL, 6 mg/dL, and 0.4%, respectively.
The combination of metformin hydrochloride tablets and glyburide was effective in reducing FPG, PPG, and HbA 1c levels by 63 mg/dL, 65 mg/dL, and 1.7%, respectively. Compared to results of glyburide treatment alone, the net differences with combination treatment were -77 mg/dL, -68 mg/dL, and -1.9%, respectively (see Table 3 ). Table 3: Combined Metformin Hydrochloride Tablets/Glyburide (Comb) vs Glyburide (Glyb) or Metformin Hydrochloride Tablets (MET) Monotherapy: Summary of Mean Changes from Baseline* in Fasting Plasma Glucose, HbA1c, and Body Weight, at Final Visit (29-week study) p-values Comb (n = 213) Glyb (n = 209) MET (n =210) Glyb vs Comb MET vs Comb MET vs Glyb Fasting Plasma Glucose (mg/dL) Baseline Change at FINAL VISIT 250.5 -63.5 247.5 13.7 253.9 -0.9 NS** 0.001 NS** 0.001 NS** 0.025 Hemoglobin A 1c (%) Baseline Change at FINAL VISIT 8.8 -1.7 8.5 0.2 8.9 -0.4 NS** 0.001 NS** 0.001 0.007 0.001 Body Weight (lbs) Baseline Change at FINAL VISIT 202.2 0.9 203 -0.7 204 -8.4 NS** 0.011 NS** 0.001 NS** 0.001 * All patients on glyburide, 20 mg/day, at Baseline ** Not statistically significant The magnitude of the decline in fasting blood glucose concentration following the institution of metformin hydrochloride tablets therapy was proportional to the level of fasting hyperglycemia.
Patients with type 2 diabetes with higher fasting glu… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term carcinogenicity studies have been performed in rats (dosing duration of 104 weeks) and mice (dosing duration of 91 weeks) at doses up to and including 900 mg/kg/day and 1500 mg/kg/day, respectively. These doses are both approximately 4 times the maximum recommended human daily dose of 2000 mg based on body surface area comparisons. No evidence of carcinogenicity with metformin was found in either male or female mice.
Similarly, there was no tumorigenic potential observed with metformin in male rats. There was, however, an increased incidence of benign stromal uterine polyps in female rats treated with 900 mg/kg/day. There was no evidence of a mutagenic potential of metformin in the following in vitro tests: Ames test ( S. typhimurium ), gene mutation test (mouse lymphoma cells), or chromosomal aberrations test (human lymphocytes).
Results in the in vivo mouse micronucleus test were also negative. Fertility of male or female rats was unaffected by metformin when administered at doses as high as 600 mg/kg/day, which is approximately 3 times the maximum recommended human daily dose based on body surface area comparisons.
📄 Patient Package Insert ▾
Patient Information Metformin Hydrochloride Tablets, USP (met for' min hye' droe klor' ide) Rx only Read this information carefully before you start taking this medicine and each time you refill your prescription. There may be new information. This information does not take the place of your doctor’s advice.
Ask your doctor or pharmacist if you do not understand some of this information or if you want to know more about this medicine. What is metformin? Metformin is used to treat type 2 diabetes.
This is also known as non-insulin-dependent diabetes mellitus. People with type 2 diabetes are not able to make enough insulin or respond normally to the insulin their bodies make. When this happens, sugar (glucose) builds up in the blood.
This can lead to serious medical problems including kidney damage, amputations, and blindness. Diabetes is also closely linked to heart disease. The main goal of treating diabetes is to lower your blood sugar to a normal level.
High blood sugar can be lowered by diet and exercise, by a number of medicines taken by mouth, and by insulin shots. Before you take metformin, try to control your diabetes by exercise and weight loss. While you take your diabetes medicine, continue to exercise and follow the diet advised for your diabetes.
No matter what your recommended diabetes management plan is, studies have shown that maintaining good blood sugar control can prevent or delay complications of diabetes, such as blindness. Metformin help control your blood sugar in a number of ways. These include helping your body respond better to the insulin it makes naturally, decreasing the amount of sugar your liver makes, and decreasing the amount of sugar your intestines absorb.
Metformin do not cause your body to make more insulin. Because of this, when taken alone, they rarely cause hypoglycemia (low blood sugar), and usually do not cause weight gain. However, when they are taken with a sulfonylurea or with insulin, hypoglycemia is more likely to occur, as is weight gain.
Tell your doctor if you are pregnant or plan to become pregnant. Metformin may not be right for you. Talk with your doctor about your choices.
You should also discuss your choices with your doctor if you are nursing a child. Can metformin hydrochloride tablets be used in children? Metformin hydrochloride tablets have been shown to effectively lower glucose levels in children (ages 10 to 16 years) with type 2 diabetes.
Metformin hydrochloride tablets have not been studied in children younger than 10 years old. Metformin hydrochloride tablets have not been studied in combination with other oral glucose-control medicines or insulin in children. If you have any questions about the use of metformin hydrochloride tablets in children, talk with your doctor or other healthcare provider.
How should I take metformin hydrochloride tablets? Your doctor will tell you how much medicine to take and when to take it. You will probably start out with a low dose of the medicine.
Your doctor may slowly increase your dose until your blood sugar is better controlled. You should take metformin with meals. Your doctor may have you take other medicines along with metformin to control your blood sugar.
These medicines may include insulin shots. Taking metformin hydrochloride tablets with insulin may help you better control your blood sugar while reducing the insulin dose. Continue your exercise and diet program and test your blood sugar regularly while taking metformin.
Your doctor will monitor your diabetes and may perform blood tests on you from time to time to make sure your kidneys and your liver are functioning normally. There is no evidence that metformin causes harm to the liver or kidneys. Tell your doctor if you: have an illness that causes severe vomiting, diarrhea or fever, or if you drink a much lower amount of liquid than normal.
These conditions can lead to severe dehydration (loss of water in your body). You may need to stop taking metformin for a short tim… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
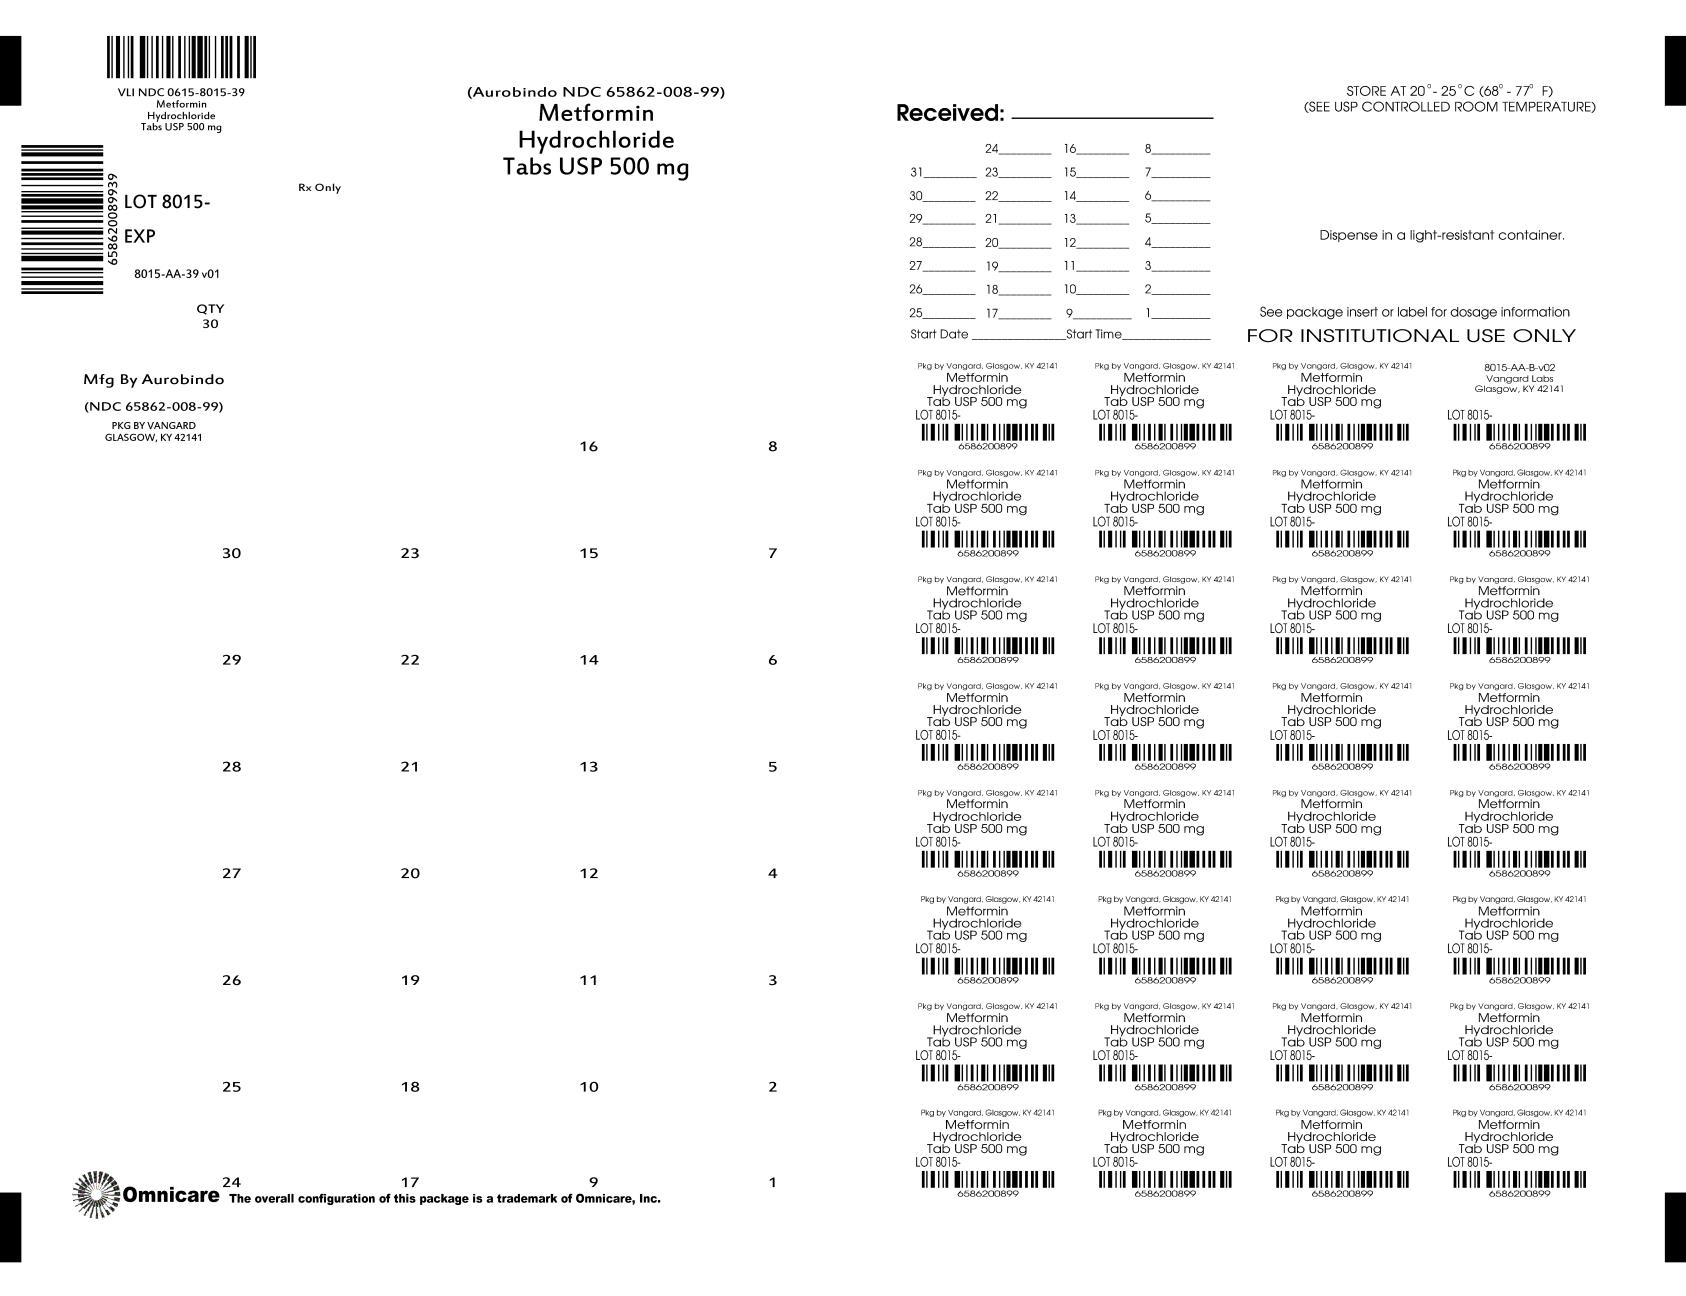
PRINCIPAL DISPLAY PANEL - 500 MG BINGO CARD PRINCIPAL DISPLAY PANEL
PRINCIPAL DISPLAY PANEL - 500 MG UNIT DOSE PRINCIPAL DISPLAY PANEL
PRINCIPAL DISPLAY PANEL - 850 MG PRINCIPAL DISPLAY PANEL
PRINCIPAL DISPLAY PANEL - 1000 MG BINGO CARD PRINCIPAL DISPLAY PANEL
PRINCIPAL DISPLAY PANEL - 1000 MG UNIT DOSE PRINCIPAL DISPLAY PANEL
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |