
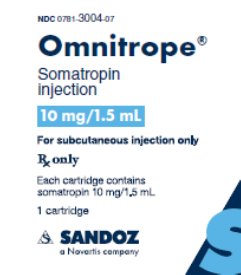
Omnitrope Somatropin 10 mg/1.5mL Injection, Solution, 1 cartridge
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Recombinant Human Growth Hormone class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Somatropin injection is used to treat growth failure caused by growth hormone deficiency and certain other conditions to increase body weight and endurance in certain people with human immunodeficiency virus (HIV) infection to treat short bowel syndrome in adults who need special nutrition therapy Somatropin is a human growth hormone (hGH) analog. It works by replacing growth hormones that are normally produced in the body, which may result in increased growth, body weight, and improved absorption of nutrients and fluids from the intestines.
Read the full MedlinePlus article ↗- Somatropin is a lab-made version of the growth hormone your body naturally produces. Your doctor has likely prescribed it because your body — or your child's body — isn't making en...
- What exactly is somatropin and why has my doctor prescribed it?
- You'll inject it just under the skin — not into a vein or deep muscle. Common spots are the belly, thigh, upper arm, or buttock. The most important habit to get into is rotating yo...
- How do I give the injection, and does it hurt?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
27.75 mg / 1.5 mL
UNII TE7660XO1C
Glycine is an amino acid used in medicines as a buffer to help stabilize pH and improve taste. It may also serve as a filler or binder to give the product proper form and consistency.
-
4.5 mg / 1.5 mL
UNII 339NCG44TV
Phenol is a chemical compound derived from coal tar or petroleum. It serves as a preservative and antimicrobial agent in medicines, helping prevent bacterial and fungal growth to keep the product stable and safe during storage.
-
3 mg / 1.5 mL
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
0.71 mg / 1.5 mL
UNII 22ADO53M6F
A mineral salt derived from phosphoric acid, used as a buffer to maintain the pH balance of the medication and help stabilize the active ingredients.
-
1.2 mg / 1.5 mL
UNII 3980JIH2SW
A salt form of phosphoric acid that acts as a buffer and pH adjuster in medicines. It helps keep the product at the correct acidity level for stability and effectiveness.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $855.322 | $1,282.98 / 1.5 ml |
| Medicaid paysCMS SDUD · 12 mo | $760.06 | $1,140.09 / 1.5 ml |
| Medicare drug plans payPart D · Q2 2026 | $855.20 | $1,282.80 / 1.5 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Omnitrope 10 mg/1.5mLthis 00781-3004-07 | Sandoz | 1 cartridge | $855.322 | — | FDA listed | — |
| Norditropin 10 mg/1.5mL 00169-7705-21 | Novo | 1 syringe | $1,137.180 | — | Availability likely | +33% |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00781-3004-07 You're viewing this | 1 CARTRIDGE in 1 CARTON (0781-3004-07) / 1.5 mL in 1 CARTRIDGE | $855.32 / mL | $1,282.98 | 2006-05-30 | Active |
| 00781-3004-26 | 5 CARTRIDGE in 1 CARTON (0781-3004-26) / 1.5 mL in 1 CARTRIDGE | — | — | 2006-05-30 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 00781-3004-07?
What is the difference between NDC 00781-3004-07 and NDC 00781-3004-26?
What NDC number is used to bill for this package of Omnitrope Somatropin 10 mg/1.5mL Injection, Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE OMNITROPE is a recombinant human growth hormone indicated for: • Pediatric: Treatment of children with growth failure due to growth hormone deficiency (GHD), Prader-Willi Syndrome, Small for Gestational Age, Turner Syndrome, and Idiopathic Short Stature ( 1.1 ) • Adult: Treatment of adults with either adult onset or childhood onset GHD ( 1.2 )
1.1Pediatric Patients OMNITROPE is indicated for the treatment of children with growth failure due to inadequate secretion of endogenous growth hormone (GH). OMNITROPE is indicated for the treatment of pediatric patients who have growth failure due to Prader-Willi Syndrome (PWS). The diagnosis of PWS should be confirmed by appropriate genetic testing [see Contraindications ( 4 ) and Warnings and Precautions ( 5.2 )] .
OMNITROPE is indicated for the treatment of growth failure in children born small for gestational age (SGA) who fail to manifest catch-up growth by age 2 years. OMNITROPE is indicated for the treatment of growth failure associated with Turner Syndrome. OMNITROPE is indicated for the treatment of idiopathic short stature (ISS), also called non-growth hormone-deficient short stature, defined by height standard deviation score (SDS) ≤ -2.25, and associated with growth rates unlikely to permit attainment of adult height in the normal range, in pediatric patients whose epiphyses are not closed and for whom diagnostic evaluation excludes other causes associated with short stature that should be observed or treated by other means.
1.2Adult Patients OMNITROPE is indicated for the replacement of endogenous GH in adults with growth hormone deficiency (GHD) who meet either of the following two criteria: • Adult Onset (AO): Patients who have GHD, either alone or associated with multiple hormone deficiencies (hypopituitarism), as a result of pituitary disease, hypothalamic disease, surgery, radiation therapy, or trauma; or • Childhood Onset (CO): Patients who were GH deficient during childhood as a result of congenital, genetic, acquired, or idiopathic causes.
Patients who were treated with somatropin for growth hormone deficiency in childhood and whose epiphyses are closed should be reevaluated before continuation of somatropin therapy at the reduced dose level recommended for growth hormone deficient adults. Confirmation of the diagnosis of adult growth hormone deficiency in both groups involves an appropriate growth hormone provocative test with two exceptions: (1) patients with multiple other pituitary hormone deficiencies due to organic disease; and (2) patients with congenital/genetic growth hormone deficiency.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The weekly dose should be divided over 6 or 7 days of subcutaneous injections. Therapy with OMNITROPE should be supervised by a physician who is experienced in the diagnosis and management of pediatric patients with short stature associated with GHD, Prader-Willi Syndrome (PWS), Turner Syndrome (TS), those who were born small for gestational age (SGA), Idiopathic Short Stature (ISS) and adult patients with either childhood onset or adult onset GHD. OMNITROPE should be administered subcutaneously ( 2 ). • Pediatric GHD: 0.16 to 0.24 mg/kg/week, divided into 6 to 7 daily injections ( 2.1 ) • Prader-Willi Syndrome: 0.24 mg/kg/week, divided into 6 to 7 daily injections ( 2.1 ) • Small for Gestational Age: Up to 0.48 mg/kg/week, divided into 6 to 7 daily injections ( 2.1 ) • Turner Syndrome: 0.33 mg/kg/week, divided into 6 to 7 daily injections ( 2.1 ) • Idiopathic Short Stature: Up to 0.47 mg/kg/week, divided into 6 to 7 daily injections ( 2.1 ) • Adult GHD: not more than 0.04 mg/kg/week (divided into daily injections) to be increased as tolerated to not more than 0.08 mg/kg/week; to be increased gradually every 1 to 2 months ( 2.2 ) • OMNITROPE Cartridges 5 mg/1.5 mL and 10 mg/1.5 mL must be used with the corresponding OMNITROPE Pen 5 and Pen 10 delivery system, respectively ( 2.3 ) • Injection sites should always be rotated to avoid lipoatrophy ( 2.3 )
2.1Dosing of Pediatric Patients General Pediatric Dosing Information The OMNITROPE dosage and administration schedule should be individualized based on the growth response of each patient. Response to somatropin therapy in pediatric patients tends to decrease with time. However, in pediatric patients, the failure to increase growth rate, particularly during the first year of therapy, indicates the need for close assessment of compliance and evaluation for other causes of growth failure, such as hypothyroidism, undernutrition, advanced bone age and antibodies to recombinant human GH (rhGH).
Treatment with OMNITROPE for short stature should be discontinued when the epiphyses are fused. Pediatric Growth Hormone Deficiency (GHD) Generally, a dosage of 0.16 to 0.24 mg/kg body weight/week is recommended. The weekly dose should be divided over 6 or 7 days of subcutaneous injections.
Prader-Willi Syndrome (PWS) Generally, a dosage of 0.24 mg/kg body weight/week is recommended. The weekly dose should be divided over 6 or 7 days of subcutaneous injections. Small for Gestational Age (SGA) Generally, a dosage of up to 0.48 mg/kg body weight/week is recommended.
The weekly dose should be divided over 6 or 7 days of subcutaneous injections. Turner Syndrome (TS) Generally, a dose of 0.33 mg/kg body weight/week is recommended. The weekly dose should be divided over 6 or 7 days of subcutaneous injections.
Idiopathic Short Stature (ISS) Generally, a dose up to 0.47 mg/kg of body weight/week is recommended. The weekly dose should be divided over 6 or 7 days of subcutaneous injections.
2.2Dosing of Adult Patients Adult Growth Hormone Deficiency (GHD) Weight-Based Dosing Based on the weight-based dosing utilized in clinical studies with another somatropin product, the recommended dosage at the start of therapy is not more than 0.04 mg/kg/week given as a daily subcutaneous injection. The dose may be increased at 4- to 8-week intervals according to individual patient requirements to not more than 0.08 mg/kg/week. Clinical response, side effects, and determination of age- and gender-adjusted serum IGF-1 levels may be used as guidance in dose titration.
Non-Weight Dosing Alternatively, taking into account recent literature, a starting dose of approximately 0.2 mg/day (range, 0.15-0.30 mg/day) may be used without consideration of body weight. This dose can be increased gradually every 1-2 months by increments of approximately 0.1 to 0.2 mg/day, according to individual patient requirements based on the clinical response and serum IGF-1 concentrations. During therapy, the dose s…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 5 mg/1.5 mL or 10 mg/1.5 mL clear, colorless solution in a single-patient-use prefilled cartridge. For Injection: 5.8 mg white to off-white lyophilized powder in a single-patient-use vial. • Injection: 5 mg/1.5 mL or 10 mg/1.5 mL solution in a single-patient-use prefilled cartridge ( 3 ) • For injection: 5.8 mg lyophilized powder in a single-patient-use vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS OMNITROPE is contraindicated in patients with: • Acute Critical Illness Treatment with pharmacologic amounts of somatropin is contraindicated in patients with acute critical illness due to complications following open heart surgery, abdominal surgery or multiple accidental trauma, or those with acute respiratory failure [see Warnings and Precautions ( 5.1 )] . • Prader-Willi Syndrome in Children Somatropin is contraindicated in patients with Prader-Willi Syndrome who are severely obese, have a history of upper airway obstruction or sleep apnea, or have severe respiratory impairment.
There have been reports of sudden death when somatropin was used in such patients [see Warnings and Precautions ( 5.2 )] . • Active Malignancy In general, somatropin is contraindicated in the presence of active malignancy. Any preexisting malignancy should be inactive and its treatment complete prior to instituting therapy with somatropin. Somatropin should be discontinued if there is evidence of recurrent activity.
Since GHD may be an early sign of the presence of a pituitary tumor (or, rarely, other brain tumors), the presence of such tumors should be ruled out prior to initiation of treatment. Somatropin should not be used in patients with any evidence of progression or recurrence of an underlying intracranial tumor [see Warnings and Precautions ( 5.3 )] . • Hypersensitivity OMNITROPE is contraindicated in patients with a known hypersensitivity to somatropin or any of its excipients. Systemic hypersensitivity reactions have been reported with postmarketing use of somatropins [see Warnings and Precautions ( 5.6 )]. • Diabetic Retinopathy Somatropin is contraindicated in patients with active proliferative or severe non-proliferative diabetic retinopathy. • Closed Epiphyses Somatropin should not be used for growth promotion in pediatric patients with closed epiphyses. • Acute Critical Illness ( 4 ) • Children with Prader-Willi Syndrome who are severely obese or have severe respiratory impairment - reports of sudden death ( 4 ) • Active Malignancy ( 4 ) • Hypersensitivity to somatropin or its excipients ( 4 ) • Active Proliferative or Severe Non-Proliferative Diabetic Retinopathy ( 4 ) • Children with closed epiphyses ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Acute Critical Illness: Potential benefit of treatment continuation should be weighed against the potential risk ( 5.1 ) • Prader-Willi Syndrome in children: Evaluate for signs of upper airway obstruction and sleep apnea before initiation of treatment. Discontinue treatment if these signs occur ( 5.2 ) • Neoplasm: Monitor patients with preexisting tumors for progression or recurrence. Increased risk of a second neoplasm in childhood cancer survivors treated with somatropin - in particular meningiomas in patients treated with radiation to the head for their first neoplasm ( 5.3 ) • Impaired Glucose Tolerance and Diabetes Mellitus: May be unmasked.
Periodically monitor glucose levels in all patients. Doses of concurrent antihyperglycemic drugs in diabetics may require adjustment ( 5.4 ) • Intracranial Hypertension: Exclude preexisting papilledema. May develop and is usually reversible after discontinuation or dose reduction ( 5.5 ) • Hypersensitivity: Serious hypersensitivity reactions may occur.
In the event of an allergic reaction, seek prompt medical attention ( 5.6 ) • Fluid Retention (i.e., edema, arthralgia, carpal tunnel syndrome - especially in adults): May occur frequently. Reduce dose as necessary ( 5.7 ) • Hypoadrenalism: Monitor patients for reduced serum cortisol levels and/or need for glucocorticoid dose increases in those with known hypoadrenalism ( 5.8 ) • Hypothyroidism: May first become evident or worsen ( 5.9 ) • Slipped Capital Femoral Epiphysis: May develop. Evaluate children with the onset of a limp or hip/knee pain ( 5.10 ) • Progression of Preexisting Scoliosis: May develop ( 5.11 ) • Pancreatitis: Consider pancreatitis in patients with persistent severe abdominal pain (5.15)
5.1Acute Critical Illness Increased mortality in patients with acute critical illness due to complications following open heart surgery, abdominal surgery or multiple accidental trauma, or those with acute respiratory failure has been reported after treatment with pharmacologic amounts of somatropin [see Contraindications ( 4 )] . Two placebo-controlled clinical trials in non-growth hormone deficient adult patients (n=522) with these conditions in intensive care units revealed a significant increase in mortality (42% vs.
19%) among somatropin-treated patients (doses 5.3-8 mg/day) compared to those receiving placebo. The safety of continuing somatropin treatment in patients receiving replacement doses for approved indications who concurrently develop these illnesses has not been established. Therefore, the potential benefit of treatment continuation with somatropin in patients experiencing acute critical illnesses should be weighed against the potential risk.
5.2Prader-Willi Syndrome in Children There have been reports of fatalities after initiating therapy with somatropin in pediatric patients with Prader-Willi Syndrome who had one or more of the following risk factors: severe obesity, history of upper airway obstruction or sleep apnea, or unidentified respiratory infection. Male patients with one or more of these factors may be at greater risk than females. Patients with Prader-Willi Syndrome should be evaluated for signs of upper airway obstruction (including onset of or increased snoring) and sleep apnea before initiation of treatment with somatropin.
If, during treatment with somatropin, patients show signs of upper airway obstruction (including onset of or increased snoring) and/or new onset sleep apnea, treatment should be interrupted. All patients with Prader-Willi Syndrome treated with somatropin should also have effective weight control and be monitored for signs of respiratory infection, which should be diagnosed as early as possible and treated aggressively [see Contraindications ( 4 )] .
5.3Neoplasms In childhood cancer survivors who were treated with radiation to the brain/head for their first neoplasm and who developed subsequent GHD and were treated with somatropin, an increased risk of…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Other common somatropin-related adverse reactions include injection site reactions/rashes and lipoatrophy ( 6.1 ) and headaches ( 6.2 ). To report SUSPECTED ADVERSE REACTIONS, contact Sandoz Inc. at 1-800-525-8747 or FDA at 1-800-FDA-1088 or http://www.fda.gov/medwatch The following important adverse reactions are also described elsewhere in labeling: • Increased mortality in patients with acute critical illness [see Warnings and Precautions ( 5.1 )] • Fatalities in children with Prader-Willi Syndrome [see Warnings and Precautions ( 5.2 )] • Neoplasms [see Warnings and Precautions ( 5.3 )] • Glucose intolerance and diabetes mellitus [see Warnings and Precautions ( 5.4 )] • Intracranial hypertension [see Warnings and Precautions ( 5.5 )] • Severe hypersensitivity [see Warnings and Precautions ( 5.6 )] • Fluid retention [see Warnings and Precautions ( 5.7 )] • Hypoadrenalism [see Warnings and Precautions ( 5.8 )] • Hypothyroidism [see Warnings and Precautions ( 5.9 )] • Slipped capital femoral epiphysis in pediatric patients [see Warnings and Precautions ( 5.10 )] • Progression of preexisting scoliosis in pediatric patients [see Warnings and Precautions ( 5.11 )] • Otitis media and cardiovascular disorders in patients with Turner Syndrome [see Warnings and Precautions ( 5.12 )] • Lipoatrophy [see Warnings and Precautions ( 5.13 )] • Pancreatitis [see Warnings and Precautions ( 5.15 )] • Benzyl Alcohol [see Warnings and Precautions ( 5.16 )]
6.1Clinical Trials Experience Because clinical trials are conducted under varying conditions, adverse reaction rates observed during the clinical trials performed with one somatropin formulation cannot always be directly compared to the rates observed during the clinical trials performed with a second somatropin formulation, and may not reflect the adverse reaction rates observed in practice. Clinical Trials in Pediatric GHD Patients The following events were observed during clinical studies with OMNITROPE Cartridge conducted in children with GHD: Table 1.
Incidence of Adverse Reactions Reported in ≥ 5% Pediatric Patients with GHD During Treatment with OMNITROPE Cartridge (N=86) Adverse Event n (%) N=number of patients receiving treatment n=number of patients who reported the event during study period %=percentage of patients who reported the event during study period Elevated HbA1c 12 (14%) Eosinophilia 10 (12%) Hematoma 8 (9%) The following events were observed during clinical studies with OMNITROPE for injection conducted in children with GHD: Table 2. Incidence of Adverse Reactions Reported in ≥ 5% Pediatric Patients with GHD During Treatment with OMNITROPE for Injection (N=44) Adverse Event n (%) N=number of patients receiving treatment n=number of patients who reported the event during study period %= percentage of patients who reported the event during study period Hypothyroidism 7 (16%) Eosinophilia 5 (11%) Elevated HbA1c 4 (9%) Hematoma 4 (9%) Headache 3 (7%) Hypertriglyceridemia 2 (5%) Leg Pain 2 (5%) Clinical Trials in PWS In two clinical studies in pediatric patients with Prader-Willi Syndrome carried out with another somatropin product, the following drug-related events were reported: edema, aggressiveness, arthralgia, benign intracranial hypertension, hair loss, headache, and myalgia.
Clinical Trials in Children with SGA In clinical studies of 273 pediatric patients born small for gestational age treated with another somatropin product, the following clinically significant events were reported: mild transient hyperglycemia, one patient with benign intracranial hypertension, two patients with central precocious puberty, two patients with jaw prominence, and several patients with aggravation of preexisting scoliosis, injection site reactions, and self-limited progression of pigmented nevi. Clinical Trials in Children with Idiopathic Short Stature In two open-label clinical studies conducted with another somatropin product in pediatric patients with ISS, the mo…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • 11β-Hydroxysteroid Dehydrogenase Type 1: May require the initiation of glucocorticoid replacement therapy. Patients treated with glucocorticoid replacement for previously diagnosed hypoadrenalism may require an increase in their maintenance doses ( 7.1 , 7.2 ) • Pharmacologic Glucocorticoid Therapy and Supraphysiologic Glucocorticoid Treatment: Should be carefully adjusted ( 7.2 ) • Cytochrome P450-Metabolized Drugs: Monitor carefully if used with somatropin ( 7.3 ) • Oral Estrogen: Larger doses of somatropin may be required in women ( 7.4 ) • Insulin and/or Oral Hypoglycemic Agents: May require adjustment ( 7.5 ) 7.1 11β-Hydroxysteroid Dehydrogenase Type 1 (11βHSD-1) The microsomal enzyme 11β-hydroxysteroid dehydrogenase type 1 (11βHSD-1) is required for conversion of cortisone to its active metabolite, cortisol, in hepatic and adipose tissue.
GH and somatropin inhibit 11βHSD-1. Consequently, individuals with untreated GH deficiency have relative increases in 11βHSD-1 and serum cortisol. Introduction of somatropin treatment may result in inhibition of 11βHSD-1 and reduced serum cortisol concentrations.
As a consequence, previously undiagnosed central (secondary) hypoadrenalism may be unmasked and glucocorticoid replacement may be required in patients treated with somatropin. In addition, patients treated with glucocorticoid replacement for previously diagnosed hypoadrenalism may require an increase in their maintenance or stress doses following initiation of somatropin treatment; this may be especially true for patients treated with cortisone acetate and prednisone since conversion of these drugs to their biologically active metabolites is dependent on the activity of 11βHSD-1 [see Warnings and Precautions ( 5.8 )].
7.2Pharmacologic Glucocorticoid Therapy and Supraphysiologic Glucocorticoid Treatment Pharmacologic glucocorticoid therapy and supraphysiologic glucocorticoid treatment may attenuate the growth promoting effects of somatropin in children. Therefore, glucocorticoid replacement dosing should be carefully adjusted in children receiving concomitant somatropin and glucocorticoid treatments to avoid both hypoadrenalism and an inhibitory effect on growth.
7.3Cytochrome P450-Metabolized Drugs Limited published data indicate that somatropin treatment increases cytochrome P450 (CYP450)-mediated antipyrine clearance in man. These data suggest that somatropin administration may alter the clearance of compounds known to be metabolized by CYP450 liver enzymes (e.g., corticosteroids, sex steroids, anticonvulsants, cyclosporine). Careful monitoring is advisable when somatropin is administered in combination with other drugs known to be metabolized by CYP450 liver enzymes.
However, formal drug interaction studies have not been conducted.
7.4Oral Estrogen In adult women on oral estrogen replacement, a larger dose of somatropin may be required to achieve the defined treatment goal [see Dosage and Administration ( 2.2 )] .
7.5Insulin and/or Oral Hypoglycemic Agents In patients with diabetes mellitus requiring drug therapy, the dose of insulin and/or oral agent may require adjustment when somatropin therapy is initiated [see Warnings and Precautions ( 5.4 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary OMNITROPE contains the preservative benzyl alcohol. Because benzyl alcohol is rapidly metabolized by a pregnant woman, benzyl alcohol exposure in the fetus is unlikely. However, adverse reactions have occurred in premature neonates and low birth weight infants who received intravenously administered benzyl alcohol-containing drugs [see Warnings and Precautions (5.16)] .
Limited available data with somatropin use in pregnant women are insufficient to determine a drug-associated risk of adverse developmental outcomes. In animal studies (rats and rabbits), there was no evidence of embryo‑fetal or neonatal harm following somatropin administration during organogenesis at doses approximately 24 times and 19 times the recommended human therapeutic levels, respectively, based on body surface area ( see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Animal reproduction studies with somatropin during the period of organogenesis at doses of 0.3, 1, and 3.3 mg/kg/day administered subcutaneously in pregnant rats and 0.08, 0.3, and 1.3 mg/kg/day administered intramuscularly in pregnant rabbits were not teratogenic (highest doses approximately 24 times and 19 times the recommended human therapeutic levels, respectively, based on body surface area).
In perinatal and postnatal studies in rats, doses of 0.3, 1, and 3.3 mg/kg/day somatropin produced growth-promoting effects in the dams but not in the fetuses. Young rats at the highest dose showed increased weight gain during suckling but the effect was not apparent by 10 weeks of age. No adverse effects were observed on gestation, morphogenesis, parturition, lactation, postnatal development, or reproductive capacity of the offspring due to somatropin.
8.2Lactation Risk Summary There is no information regarding the presence of somatropin in human milk. Limited published data indicate that exogenous somatropin does not increase normal breastmilk concentrations of growth hormone. No adverse effects related to somatropin in the breastfed infant have been reported.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for OMNITROPE and any potential adverse effects on the breastfed infant from OMNITROPE or from the underlying maternal condition.
8.5Geriatric Use The safety and effectiveness of OMNITROPE in patients aged 65 and over have not been evaluated in clinical studies. Elderly patients may be more sensitive to the action of somatropin, and therefore may be more prone to develop adverse reactions. A lower starting dose and smaller dose increments should be considered for older patients [see Dosage and Administration ( 2.2 )] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary OMNITROPE contains the preservative benzyl alcohol. Because benzyl alcohol is rapidly metabolized by a pregnant woman, benzyl alcohol exposure in the fetus is unlikely. However, adverse reactions have occurred in premature neonates and low birth weight infants who received intravenously administered benzyl alcohol-containing drugs [see Warnings and Precautions (5.16)] .
Limited available data with somatropin use in pregnant women are insufficient to determine a drug-associated risk of adverse developmental outcomes. In animal studies (rats and rabbits), there was no evidence of embryo‑fetal or neonatal harm following somatropin administration during organogenesis at doses approximately 24 times and 19 times the recommended human therapeutic levels, respectively, based on body surface area ( see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Animal reproduction studies with somatropin during the period of organogenesis at doses of 0.3, 1, and 3.3 mg/kg/day administered subcutaneously in pregnant rats and 0.08, 0.3, and 1.3 mg/kg/day administered intramuscularly in pregnant rabbits were not teratogenic (highest doses approximately 24 times and 19 times the recommended human therapeutic levels, respectively, based on body surface area).
In perinatal and postnatal studies in rats, doses of 0.3, 1, and 3.3 mg/kg/day somatropin produced growth-promoting effects in the dams but not in the fetuses. Young rats at the highest dose showed increased weight gain during suckling but the effect was not apparent by 10 weeks of age. No adverse effects were observed on gestation, morphogenesis, parturition, lactation, postnatal development, or reproductive capacity of the offspring due to somatropin.
🧓 Geriatric Use ▾
8.5Geriatric Use The safety and effectiveness of OMNITROPE in patients aged 65 and over have not been evaluated in clinical studies. Elderly patients may be more sensitive to the action of somatropin, and therefore may be more prone to develop adverse reactions. A lower starting dose and smaller dose increments should be considered for older patients [see Dosage and Administration ( 2.2 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Short-Term Short-term overdosage could lead initially to hypoglycemia and subsequently to hyperglycemia. Furthermore, overdose with somatropin is likely to cause fluid retention. Long-Term Long-term overdosage could result in signs and symptoms of gigantism and/or acromegaly consistent with the known effects of excess growth hormone [see Dosage and Administration ( 2 )] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Somatropin (as well as endogenous GH) binds to a dimeric GH receptor in the cell membrane of target cells resulting in intracellular signal transduction and a host of pharmacodynamic effects. Some of these pharmacodynamic effects are primarily mediated by IGF-1 produced in the liver and also locally (e.g., skeletal growth, protein synthesis), while others are primarily a consequence of the direct effects of somatropin (e.g., lipolysis) [see Pharmacodynamics ( 12.2 )] .
12.2Pharmacodynamics Tissue Growth The primary and most intensively studied action of somatropin is the stimulation of linear growth. This effect is demonstrated in children with GHD and children who have PWS, were born SGA, have TS or have ISS. Skeletal Growth The measurable increase in bone length after administration of somatropin results from its effect on the cartilaginous growth areas of long bones.
Studies in vitro have shown that the incorporation of sulfate into proteoglycans is not due to a direct effect of somatropin, but rather is mediated by the somatomedins or insulin-like growth factors (IGFs). The somatomedins, among them IGF-1, are polypeptide hormones which are synthesized in the liver, kidney, and various other tissues. IGF-1 levels are low in the serum of hypopituitary dwarfs and hypophysectomized humans or animals and increase after treatment with somatropin.
Cell Growth It has been shown that the total number of skeletal muscle cells is markedly decreased in children with short stature lacking endogenous GH compared with normal children, and that treatment with somatropin results in an increase in both the number and size of muscle cells. Organ Growth Somatropin influences the size of internal organs, and it also increases red cell mass. Protein Metabolism Linear growth is facilitated in part by increased cellular protein synthesis.
This synthesis and growth are reflected by nitrogen retention which can be quantitated by observing the decline in urinary nitrogen excretion and blood urea nitrogen following the initiation of somatropin therapy. Carbohydrate Metabolism Hypopituitary children sometimes experience fasting hypoglycemia that may be improved by treatment with somatropin. In healthy subjects, large doses of somatropin may impair glucose tolerance.
Although the precise mechanism of the diabetogenic effect of somatropin is not known, it is attributed to blocking the action of insulin rather than blocking insulin secretion. Insulin levels in serum actually increase as somatropin levels increase. Administration of human growth hormone to normal adults and patients with growth hormone deficiency results in increases in mean serum fasting and postprandial insulin levels, although mean values remain in the normal range.
In addition, mean fasting and postprandial glucose and hemoglobin A 1C levels remain in the normal range. Lipid Metabolism Somatropin stimulates intracellular lipolysis, and administration of somatropin leads to an increase in plasma free fatty acids and triglycerides. Untreated GHD is associated with increased body fat stores, including increased abdominal visceral and subcutaneous adipose tissue.
Treatment of growth hormone deficient patients with somatropin results in a general reduction of fat stores, and decreased serum levels of low density lipoprotein (LDL) cholesterol. Mineral Metabolism Administration of somatropin results in an increase in total body potassium and phosphorus and to a lesser extent sodium. This retention is thought to be the result of cell growth.
Serum levels of phosphate increase in children with GHD after somatropin therapy due to metabolic activity associated with bone growth. Serum calcium levels are not altered. Although calcium excretion in the urine is increased, there is a simultaneous increase in calcium absorption from the intestine.
Negative calcium balance, however, may occasionally occur during somatropin treatment. Connective Tissue…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Somatropin (as well as endogenous GH) binds to a dimeric GH receptor in the cell membrane of target cells resulting in intracellular signal transduction and a host of pharmacodynamic effects. Some of these pharmacodynamic effects are primarily mediated by IGF-1 produced in the liver and also locally (e.g., skeletal growth, protein synthesis), while others are primarily a consequence of the direct effects of somatropin (e.g., lipolysis) [see Pharmacodynamics ( 12.2 )] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied OMNITROPE (somatropin) injection is a clear, colorless, sterile solution for subcutaneous injection supplied in a cartridge for use with OMNITROPE Pen delivery system. OMNITROPE (somatropin) for injection is a white to off-white lyophilized powder supplied in a vial for subcutaneous injection after reconstitution with co-packaged diluent. Carton Contents Strength NDC 1 single-patient-use cartridge 5 mg/1.5 mL a NDC 0781-3001-07 5 single-patient-use cartridges 5 mg/1.5 mL a NDC 0781-3001-26 1 single-patient-use cartridge 10 mg/1.5 mL b NDC 0781-3004-07 5 single-patient-use cartridges 10 mg/1.5 mL b NDC 0781-3004-26 8 single-patient-use vials 8 single-dose vials of diluent (Bacteriostatic Water for Injection containing 1.5% benzyl alcohol as a preservative) 5.8 mg per vial NDC 0781-4004-36 a For use only with the OMNITROPE Pen 5 delivery system, which is sold separately. b For use only with the OMNITROPE Pen 10 delivery system, which is sold separately.
16.2Storage and Handling Before use, store OMNITROPE vials and cartridges refrigerated at 2° to 8°C (36° to 46°F) in the original carton to protect from light. Do not freeze. After first use, the OMNITROPE cartridge should remain in the pen and kept the original carton in a refrigerator at 2° to 8°C (36° to 46°F) for a maximum of 28 days (see Table 11 ).
Discard unused portions in the cartridge after 28 days. After reconstitution of the lyophilized powder, the contents of the OMNITROPE vial must be used within 21 days. After the first injection, store the vial in the original carton in a refrigerator at 2° to 8°C (36° to 46°F) (see Table 11 ).
Discard unused portions after 21 days. Table 11. Storage Options OMNITROPE Product Formulation Storage Requirement Before Use In-use (after 1st injection) 5 mg/1.5 mL cartridge Refrigerate at 2° to 8°C (36° to 46°F) Until exp date Refrigerate at 2° to 8°C (36° to 46°F) up to 28 days 10 mg/1.5 mL cartridge Refrigerate at 2° to 8°C (36° to 46°F) up to 28 days 5.8 mg per vial Refrigerate at 2° to 8°C (36° to 46°F) Until exp date Refrigerate at 2° to 8°C (36° to 46°F) up to 21 days
📋 Description ▾
11 DESCRIPTION Somatropin is a human growth hormone (GH) produced by recombinant DNA technology using Escherichia coli. The protein is comprised of 191 amino acid residues and a molecular weight of approximately 22,125 daltons. The amino acid sequence is identical to that of human GH of pituitary origin.
OMNITROPE (somatropin) injection is a clear, colorless, sterile solution for subcutaneous injection supplied in a cartridge for use with OMNITROPE Pen delivery system. Sodium hydroxide and/or phosphoric acid may be added during manufacture to adjust pH. OMNITROPE (somatropin) for injection is a white to off-white lyophilized powder supplied in a vial for subcutaneous injection after reconstitution.
Sodium hydroxide and/or hydrochloric acid may be added during manufacture to adjust pH. Vials are co-packaged with accompanying 1.14 mL vials of a diluent containing Bacteriostatic Water for Injection with 1.5% benzyl alcohol as a preservative. After reconstitution, the concentration is 5 mg/mL.
Each OMNITROPE cartridge or vial contains the following (see Table 4 ): Table 4. Contents of OMNITROPE Cartridges and Vial Product Cartridge 5 mg/ 1.5 mL Cartridge 10 mg/ 1.5 mL For Injection 5.8 mg/ vial Component Somatropin 5 mg 10 mg 5.8 mg Dibasic sodium phosphate 0.609 mg 0.71 mg 0.996 mg Monobasic sodium phosphate 1.28 mg 1.2 mg 0.52 mg Poloxamer 3 mg 3 mg - Mannitol 52.5 mg - - Glycine - 27.75 mg 27.6 mg Benzyl alcohol 13.5 mg - - Phenol - 4.5 mg - Water for Injection to make 1.5 mL to make 1.5 mL - Diluent (vials only) Bacteriostatic Water for Injection Water for injection to make 1.14 mL Benzyl alcohol 17 mg
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Instructions For Use: OMNITROPE Pen 5 Instructions For Use, OMNITROPE Pen 10 Instructions For Use, Instructions For OMNITROPE 5.8 mg/Vial). Patients being treated with OMNITROPE (and/or their parents) should be informed about the potential risks and benefits associated with somatropin treatment. This information is intended to better educate patients (and caregivers); it is not a disclosure of all possible adverse or intended effects.
Patients and caregivers who will administer OMNITROPE should receive appropriate training and instruction on the proper use of OMNITROPE from the physician or other suitably qualified health care professional. A puncture-resistant container for the disposal of used syringes and needles should be strongly recommended. Patients and/or parents should be thoroughly instructed in the importance of proper disposal, and cautioned against any reuse of needles and syringes.
Counsel patients and parents that they should never share an OMNITROPE Pen with another person, even if the needle is changed. Sharing of the pen between patients may pose a risk of transmission of infection. If patients are prescribed OMNITROPE Cartridge 5 mg/1.5 mL or 10 mg/1.5 mL (to be inserted into OMNITROPE Pen 5 or Pen 10 delivery systems), physicians should instruct patients to read the corresponding Instructions For Use provided with the OMNITROPE Pens delivery systems and the OMNITROPE Cartridges.
If patients are prescribed OMNITROPE for injection, physicians should instruct patients to read the Instructions For Use leaflets provided with the OMNITROPE for injection 5.8 mg/vial. Manufactured by: Sandoz Inc., Princeton, NJ 08540 US License No. 2003