
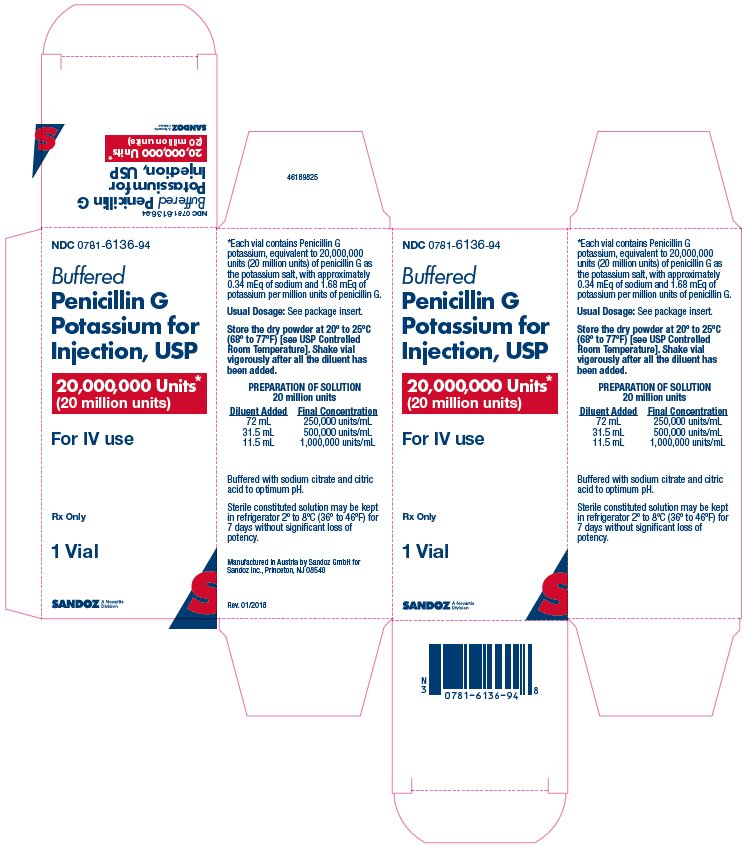
Penicillin G Potassium 20000000 [iU]/1 Injection, Powder, For Solution, 1 vial
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Penicillin-class Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Penicillin G injection is used to treat and prevent certain infections caused by bacteria. Penicillin G injection is in a class of medications called penicillins. It works by killing bacteria that cause infections. Antibiotics such as penicillin G injection will not work for colds, flu, or other viral infections. Taking antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Penicillin G injection is reserved for serious, potentially life-threatening infections where we need high levels of antibiotic in your blood fast. An IV or intramuscular injection...
- Why am I getting this antibiotic through an IV instead of just taking a pill?
- Prior exposure without a reaction is reassuring, but it doesn't completely rule out a future allergic reaction. Allergies can develop over time or after repeated exposures. The mor...
- I've taken penicillin before without a problem. Do I still need to worry about an allergic reaction?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Penicillin G Potassium — tap one for details:
Penicillin G Potassium may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 1Q73Q2JULR
Sodium citrate is a salt derived from citric acid. It works as a buffer to maintain the medicine's pH level and may also help improve taste or act as a preservative in the formulation.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $10.02 | — |
| Medicare drug plans payPart D · Q2 2026 | $38.82 | — |
| Medicare Part B allowsASP · J2540 | $0.637 / J2540 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Pfizerpen 5000000 [iU] 00049-0420-10 | Roerig | 10 vials | — | AP | FDA listed | — |
| Pfizerpen 20000000 [iU] 00049-0430-20 | Roerig | 1 vial | — | AP | FDA listed | — |
| Pfizerpen 5000000 [iU] 00049-0520-22 | Roerig | 10 vials | — | AP | FDA listed | — |
| Pfizerpen 20000000 [iU] 00049-0530-22 | Roerig | 1 vial | — | AP | FDA listed | — |
| Penicillin G Potassium 5000000 [iU] 00781-6135-95 | Sandoz | 10 vials | — | — | FDA listed | — |
| Penicillin G Potassium 20000000 [iU]this 00781-6136-94 | Sandoz | 1 vial | — | — | FDA listed | — |
| Penicillin G Potassium 5000000 [iU] 25021-0153-20 | Sagent | 10 vials | — | AP | FDA listed | — |
| Penicillin G Potassium 20000000 [iU] 25021-0154-51 | Sagent | 1 vial | — | AP | FDA listed | — |
| Penicillin G Potassium 1000000 [iU] 44567-0310-10 | WG | 10 vials | — | — | FDA listed | — |
| Penicillin G Potassium 5000000 [iU] 44567-0311-10 | WG | 10 vials | — | AP | FDA listed | — |
| Penicillin G Potassium 20000000 [iU] 44567-0312-10 | WG | 10 vials | — | AP | FDA listed | — |
| Buffered Penicillin G Potassium 5000000 [iU] 51662-1436-01 | HF | 1 injection | — | — | Discontinued | — |
| Penicillin G Potassium 5000000 [iU] 51662-1689-01 | HF | 1 injection | — | AP | FDA listed | — |
| Penicillin G Potassium 20000000 [iU] 70860-0127-51 | Athenex | 1 vial | — | AP | FDA listed | — |
| Penicillin G Potassium 5000000 [iU] 72603-0210-01 | NorthStar | 1 vial | — | AP | FDA listed | — |
| Penicillin G Potassium 20000000 [iU] 72603-0345-01 | NorthStar | 1 vial | — | AP | FDA listed | — |
| Penicillin G Potassium 5000000 [iU] 83634-0102-20 | Avenacy | 10 vials | — | AP | FDA listed | — |
| Penicillin G Potassium 20000000 [iU] 83634-0103-51 | Avenacy | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00781-6136-94 You're viewing this | 1 VIAL in 1 CARTON (0781-6136-94) / 1 INJECTION, POWDER, FOR SOLUTION in 1 VIAL | 2001-08-30 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Therapy Buffered penicillin G potassium for injection is indicated in the treatment of serious infections caused by susceptible strains of the designated microorganisms in the conditions listed below. Appropriate culture and susceptibility tests should be done before treatment in order to isolate and identify organisms causing infection and to determine their susceptibility to penicillin G. Therapy with Buffered penicillin G potassium for injection may be initiated before results of such tests are known when there is reason to believe the infection may involve any of the organisms listed below, however, once these results become available, appropriate therapy should be continued.
CLINICAL INDICATION INFECTING ORGANISM Septicemia, empyema, pneumonia, pericarditis, endocarditis, meningitis Streptococcus pyogenes (group A beta-hemolytic streptococcus ), other beta-hemolytic streptococci including groups C, H, G, L and M, Streptococcus pneumoniae and Staphylococcus species (non-penicillinase producing strains) Anthrax Bacillus anthracis Actinomycosis (cervicofacial disease and thoracic and abdominal disease) Actinomyces Israelil Botulism (adjunctive therapy to antitoxin), gas gangrene, and tetanus (adjunctive therapy to human tetanus immune globulin) Clostridium species Diphtheria (adjunctive therapy to antitoxin and prevention of the carrier state) Corynebacterium diphtheriae Erysipelothrix endocarditis Erysipelothrix rhusiopthiae Fusospirochetosis (severe infections of the oropharynx [Vincent’s], lower respiratory tract and genital area) Fusobacterium species and spirochetes Listeria infections including meningitis and endocarditis Listeria monocytogenes Pasteurella infections including bacteremia and meningitis Pasteurella multocida Haverhill fever Streptobacillus moniliformis Rat-bite fever Spirillum minus or Streptobacillus moniliformis Disseminated gonococcal infections Neisseria gonorrhoeae (penicillin-susceptible) Syphilis (congenital and neurosyphilis) Treponema pallidum Meningococcal meningitis and/or septicemia Neisseria meningitidis Gram-negative bacillary infections (bacteremias) Escherichia coli, Enterobacter aerogenes, Alcaligenes faecalis, salmonella, shigella and Proteus mirabilis, Penicillin G is not the drug of choice in the treatment of gram-negative bacillary infections.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of penicillin G potassium and other antibacterial drugs, penicillin G potassium should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Buffered penicillin G potassium for injection may be given intravenously or intramuscularly. The usual dose recommendations are as follows: CLINICAL INDICATION DOSAGE Serious infections due to susceptible strains of streptococci (including S. pneumoniae) and staphylococci-septicemia , empyema, pneumonia, pericarditis, endocarditis and meningitis 5 to 24 million units/day depending on the infection and its severity administered in equally divided doses every 4 to 6 hours Anthrax Minimum of 8 million units/day in divided doses every 6 hours.
Higher doses may be required depending on susceptibility of organism. Actinomycosis Cervicofacial disease 1 to 6 million units/day Thoracic and abdominal disease 10 to 20 million units/day Clostridial infections Botulism (adjunctive therapy to antitoxin) 20 million units/day Gas gangrene (debridement and/or surgery as indicated) Tetanus (adjunctive therapy to human tetanus immune globulin) Diphtheria (adjunctive therapy to antitoxin and for the prevention of the carrier state) 2 to 3 million units/day in divided doses for 10 to 12 days Erysipelothrix endocarditis 12 to 20 million units/day for 4 to 6 weeks Fusospirochetosis (severe infections of the oropharnyx [Vincent’s], lower respiratory tract and genital area) 5 to 10 million units/day Listeria infections Meningitis 15 to 20 million units/day for 2 weeks Endocarditis 15 to 20 million units/day for 4 weeks Pasteurella infections including bacteremia and meningitis 4 to 6 million units/day for 2 weeks Haverhill fever, Rat-bite fever 12 to 20 million units/day for 3 to 4 weeks Disseminated gonococcal infections, such as meningitis endocarditis, arthritis, etc., caused by penicillin-susceptible organisms 10 million units/day; duration depends on the type of infection Syphilis (neurosyphilis) 12 to 24 million units/day, as 2 to 4 MU every 4 hours for 10 to 14 days; many experts recommend additional therapy with Benzathine PCN G
2.4MU intramuscular weekly for 3 doses after completion of intravenous therapy Meningococcal meningitis and/or septicemia 24 million units/day as 2 million units every 2 hours * Because of its short half-life, penicillin G is administered in divided doses, usually every 4 to 6 hours with the exception of meningococcal meningitis/septicemia, i.e., every 2 hours. Pediatric patients This product should not be administered to patients requiring less than one million units per dose (see PRECAUTIONS – Pediatric Use ). CLINICAL INDICATION DOSAGE Serious infections, such as pneumonia and endocarditis, due to susceptible strains of streptococci (including S. pneumoniae) and meningococcus 150,000 units/kg/day divided in equal doses every 4 to 6 hours; duration depends on infecting organism and type of infection.
Meningitis caused by susceptible strains of pneumococcus and meningococcus 250,000 units/kg/day divided in equal doses every 4 hours for 7 to 14 days depending on the infecting organism (maximum dose of 12 to 20 million units/day) Disseminated Gonococcal infections (penicillin-susceptible strains) weight less than 45 kg: Arthritis 100,000 units/kg/day in 4 equally divided doses for 7 to 10 days Meningitis 250,000 units/kg/day in equal doses every 4 hours for 10 to 14 days Endocarditis 250,000 units/kg/day in equal doses every 4 hours for 4 weeks Arthritis, meningitis, endocarditis weight 45 kg or greater: 10 million units/day in 4 equally divided doses with the duration of therapy depending on the type of infection Syphilis (congenital and neurosyphilis) after the newborn period 200,000 to 300,000 units/kg/day (administered as 50,000 units/kg every 4 to 6 hours) for 10 to 14 days Diphtheria (adjunctive therapy to antitoxin and for prevention of the carrier state) 150,000 to 250,000 units/kg/day in equal doses every 6 hours for 7 to 10 days Rat-bite fever; Haverhill fever (with endocarditis caused by S. moniliformis) 150,000 to 250,000 units/kg/day in equal doses every 4 hours for 4 weeks Renal…
⛔ Contraindications ▾
CONTRAINDICATIONS A history of hypersensitivity (anaphylactic) reaction to any penicillin is a contraindication.
⚠️ Warnings ▾
WARNINGS SERIOUS AND OCCASIONALLY FATAL HYPERSENSITIVITY (ANAPHYLACTIC) REACTIONS HAVE BEEN REPORTED IN PATIENTS ON PENICILLIN THERAPY. THESE REACTIONS ARE MORE LIKELY TO OCCUR IN INDIVIDUALS WITH A HISTORY OF PENICILLIN HYPERSENSITIVITY AND/OR A HISTORY OF SENSITIVITY TO MULTIPLE ALLERGENS. THERE HAVE BEEN REPORTS OF INDIVIDUALS WITH A HISTORY OF PENICILLIN HYPERSENSITIVITY WHO HAVE EXPERIENCED SEVERE REACTIONS WHEN TREATED WITH CEPHALOSPORINS.
BEFORE INITIATING THERAPY WITH PENICILLIN G, CAREFUL INQUIRY SHOULD BE MADE CONCERNING PREVIOUS HYPERSENSITIVITY REACTIONS TO PENICILLINS, CEPHALOSPORINS, OR OTHER ALLERGENS. IF AN ALLERGIC REACTION OCCURS, PENICILLIN G SHOULD BE DISCONTINUED AND APPROPRIATE THERAPY INSTITUTED. SERIOUS ANAPHYLACTIC REACTIONS REQUIRE IMMEDIATE EMERGENCY TREATMENT WITH EPINEPHRINE.
OXYGEN, INTRAVENOUS STEROIDS, AND AIRWAY MANAGEMENT, INCLUDING INTUBATION, SHOULD ALSO BE ADMINISTERED AS INDICATED. Pseudomembranous colitis has been reported with nearly all antibacterial agents, including penicillin G, and may range in severity from mild to life-threatening. Therefore, it is important to consider this diagnosis in patients who present with diarrhea subsequent to the administration of antibacterial agents.
Treatment with antibacterial agents alters the normal flora of the colon and may permit overgrowth of clostridia. Studies indicate that a toxin produced by Clostridium difficile is one primary cause of “antibiotic-associated colitis”. After the diagnosis of pseudomembranous colitis has been established, therapeutic measures should be initiated.
Mild cases of pseudomembranous colitis usually respond to drug discontinuation alone. In moderate to severe cases, consideration should be given to management with fluids and electrolytes, protein supplementation and treatment with an antibacterial drug effective against C. difficile.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Body as a whole The Jarisch-Herxheimer reaction is a systemic reaction, that may occur after the initiation of penicillin therapy in patients with syphilis or other spirochetal infections (i.e., Lyme disease and Relapsing fever). The reaction begins one to two hours after initiation of therapy and disappears within 12 to 24 hours. It is characterized by fever, chills, myalgias, headache, exacerbation of cutaneous lesions, tachycardia, hyperventiliation, vasodilation with flushing and mild hypotension.
The pathogenesis of the Herxheimer reaction may be due to the release from the spirochaete of host stable pyrogen. Hypersensitivity reactions The reported incidence of allergic reactions to all penicillins ranges from 0.7 to 10 percent in different studies (see WARNINGS ). Sensitization is usually the result of previous treatment with a penicillin, but some individuals have had immediate reactions when first treated.
In such cases, it is postulated that prior exposure to penicillin may have occurred via trace amounts present in milk or vaccines. Two types of allergic reactions to penicillin are noted clinically – Immediate and delayed. Immediate reactions usually occur within 20 minutes of administration and range in severity from urticaria and pruritus to angloneurotic edema, laryngospasm, bronchospasm, hypotension, vascular collapse and death (see WARNINGS ).
Such immediate anaphylactic reactions are very rare and usually occur after parenteral therapy, but a few cases of anaphylaxis have been reported following oral therapy. Another type of immediate reaction, an accelerated reaction, may occur between 20 minutes and 48 hours after administration and may include urticaria, pruritus, fever and, occasionally, laryngeal edema. Delayed reactions to penicillin therapy usually occur within 1 to 2 weeks after initiation of therapy.
Manifestations include serum sickness-like symptoms, i.e., fever, malaise, urticaria, myalgia, arthralgia, abdominal pain and various skin rashes, ranging from maculopapular eruptions to exfoliative dermatitis. Contact dermatitis has been observed in individuals who prepare penicillin solutions. Gastrointestinal system Pseudomembranous colitis has been reported with the onset occurring during or after penicillin G treatment.
Nausea, vomiting, stomatitis, black or hairy tongue, and other symptoms of gastrointestinal irritation may occur, especially during oral therapy. Hematologic system Reactions include neutropenia, which resolves after penicillin therapy is discontinued; Coombspositive hemolytic anemia, an uncommon reaction, occurs in patients treated with intravenous penicillin G in doses greater than 10 million units/day and who have previously received large doses of the drug; and with large doses of penicillin, a bleeding diathesis, can occur secondary to platelet dysfunction.
Metabolic Buffered penicillin G potassium for injection (1 million units contains 0.3 mEq of sodium and 1.68 mEq of potassium) may cause serious and even fatal electrolyte disturbances, i.e., hyperkalemia, when given intravenously in large doses. Nervous system Neurotoxic reactions including hyperreflexia, myoclonic twitches, seizures and coma have been reported following the administration of massive intravenous doses, and are more likely in patients with impaired renal function. Urogenital system Renal tubular damage and interstitial nephritis have been associated with large intravenous doses of penicillin G.
Manifestations of this reaction may include fever, rash, eosinophilia, proteinuria, eosinophiluria, hematuria and a rise in serum urea nitrogen. Discontinuation of penicillin G results in resolution in the majority of patients. Local reactions Phlebitis and thrombophlebitis may occur with intravenous administration.
🔄 Drug Interactions ▾
Drug Interactions Bacteriostatic antibacterials (i.e., chloramphenicol, erythromycins, sulfonamides or tetracyclines) may antagonize the bactericidal effect of penicillin, and concurrent use of these drugs should be avoided. This has been documented in vitro, however, the clinical significance of this interaction is not well-documented. Penicillin blood levels may be prolonged by concurrent administration of probenecid which blocks the renal tubular secretion of penicillins.
Other drugs may compete with penicillin G for renal tubular secretion and thus prolong the serum half-life of penicillin. These drugs include: aspirin, phenylbutazone, sulfonamides, indomethacin, thiazide diuretics, furosemide and ethacrynic acid.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions After treatment with penicillin G, a false-positive reaction for glucose in the urine may occur with Benedict’s solution, Fehling’s solution or Clinitest ® tablet, but not with the enzyme-based tests, such as Clinistix ® . Penicillin G has been associated with pseudoproteinuria by certain test methods.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Reproduction studies performed in the mouse, rat, and rabbit have revealed no evidence of impaired fertility or harm to the fetus due to penicillin G. Human experience with the penicillins during pregnancy has not shown any positive evidence of adverse effects on the fetus. There are, however, no adequate and well controlled studies in pregnant women showing conclusively that harmful effects of these drugs on the fetus can be excluded.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Incompletely developed renal function in newborns may delay elimination of penicillin; therefore, appropriate reductions in the dosage and frequency of administration should be made in these patients. All newborns treated with penicillins should be monitored closely for clinical and laboratory evidence of toxic or adverse effects (see PRECAUTIONS ). Pediatric doses are generally determined on a weight basis and should be calculated for each patient individually.
Recommended guidelines for pediatric dosages are presented in DOSAGE AND ADMINISTRATION . The potential for toxic effects in children from chemicals that may leach from the single dose premixed intravenous preparation in plastic containers has not been evaluated. Patients should be counseled that antibacterial drugs including penicillin G potassium should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When penicillin G potassium is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may: (1) decrease the effectiveness of the immediate treatment, and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by penicillin G potassium or other antibacterial drugs in the future.
🆘 Overdosage ▾
OVERDOSAGE Dose related toxicity may arise with the use of massive doses of intravenous penicillins (40 to 100 million units per day), particularly in patients with severe renal impairment (see PRECAUTIONS ). The manifestations may include agitation, confusion, asterixis, hallucinations, stupor, coma, multifocal myoclonus, seizures and encephalopathy. Hyperkalemia is also possible (see ADVERSE REACTIONS – Metabolic ).
In case of overdosage, discontinue penicillin, treat symptomatically and institute supportive measures as required. If necessary, hemodialysis may be used to reduce blood levels of penicillin G, although the degree of effectiveness of this procedure is questionable.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY After an intravenous infusion of penicillin G, peak serum concentrations are attained immediately after completion of the infusion. In a study of ten patients administered a single 5 million unit dose of penicillin G intravenously over 3 to 5 minutes, the mean serum concentrations were 400 mcg/mL, 273 mcg/mL and 3 mcg/mL at 5 to 6 minutes, 10 minutes and 4 hours after completion of the injection, respectively. In a separate study, five healthy adults were administered one million units of penicillin G intravenously, either as a bolus over 4 minutes or as an infusion over 60 minutes.
The mean serum concentration eight minutes after completion of the bolus was 45 mcg/mL and eight minutes after completion of the infusion was 14.4 mcg/mL. The mean beta-phase serum half-life of penicillin G administered by the intravenous route in ten patients with normal renal function was 42 minutes, with a range of 31 to 50 minutes. The clearance of penicillin G in normal individuals is predominantly via the kidney.
The renal clearance, which is extremely rapid, is the result of glomerular filtration and active tubular transport, with the latter route predominating. Urinary recovery is reported to be 58 to 85% of the administered dose. Renal clearance of penicillin is delayed in premature infants, neonates and in the elderly due to decreased renal function.
The serum half-life of penicillin G correlates inversely with age and clearance of creatinine and ranges from 3.2 hours in infants 0 to 6 days of age to 1.4 hours in infants 14 days of age or older. Nonrenal clearance includes hepatic metabolism and, to a lesser extent, biliary excretion. The latter routes become more important with renal impairment.
Probenecid blocks the renal tubular secretion of penicillin. Therefore, the concurrent administration of probenecid prolongs the elimination of penicillin G and, consequently, increases the serum concentrations. Penicillin G is distributed to most areas of the body including lung, liver, kidney, muscle, bone and placenta.
In the presence of inflammation, levels of penicillin in abscesses, middle ear, pleural, peritoneal and synovial fluids are sufficient to inhibit most susceptible bacteria. Penetration into the eye, brain, cerebrospinal fluid (CSF) or prostate is poor in the absence of inflammation. With inflamed meninges, the penetration of penicillin G into the CSF improves, such that the CSF/serum ratio is 2 to 6%.
Inflammation also enhances its penetration into the pericardial fluid. Penicillin G is actively secreted into the bile resulting in levels at least 10 times those achieved simultaneously in serum. Penicillin G penetrates poorly into human polymorphonuclear leukocytes.
In the presence of impaired renal function, the beta-phase serum half-life of penicillin G is prolonged. beta-phase serum half-lives of one to two hours were observed in azotemic patients with serum creatinine concentrations <3 mg/100 mL and ranged as high as 20 hours in anuric patients. A linear relationship, including the lowest range of renal function, is found between the serum elimination rate constant and renal function as measured by creatinine clearance. In patients with altered renal function, the presence of hepatic insufficiency further alters the elimination of penicillin G.
In one study, the serum half-lives in two anuric patients (excreting <400 mL urine/day) were 7.2 and 10.1 hours. A totally anuric patient with terminal hepatic cirrhosis had a penicillin half-life of 30.5 hours, while another patient with anuria and liver disease had a serum half-life of 16.4 hours. The dosage of penicillin G should be reduced in patients with severe renal impairment, with additional modifications when hepatic disease accompanies the renal impairment.
Hemodialysis has been shown to reduce penicillin G serum levels. Microbiology Penicillin G is bactericidal against penicillin-susceptible microorganisms during the stage of active multiplication. It…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Buffered penicillin G potassium for injection, USP, is supplied in dry powder form in vials containing: 1,000,000 units (1 million units) × 10’s (NDC 0781-6134-95) 5,000,000 units (5 million units) × 10’s (NDC 0781-6135-95) 20,000,000 units (20 million units) × 1’s (NDC 0781-6136-94) of crystalline penicillin G as the potassium salt; buffered with sodium citrate and citric acid to an optimum pH. Storage Store the dry powder at 20° to 25°C (68° to 77°F) [see USP controlled room temperature]. Sterile constituted solution may be kept in refrigerator 2° to 8°C (36° to 46°F) for 7 days without significant loss of potency.
📋 Description ▾
DESCRIPTION Buffered penicillin G potassium for injection, USP is sterile penicillin G potassium powder for reconstitution. It is an antibacterial agent intended for intravenous or intramuscularly use. Chemically, penicillin G potassium is monopotassium (2S,5R,6R)-3,3-dimethyl-7-oxo-6-(2-phenylacetamido)-4-thia-1-azabicyclo (3.2.0) heptane-2-carboxylate, and has the following chemical structure: Molecular Formula: C 16 H 17 KN 2 O 4 S Molecular Weight: 372.48 Penicillin G potassium, a water soluble benzylpenicillin, is a white to almost white crystalline powder which is almost odorless and/or after reconstitution a colorless solution.
The pH of freshly constituted solutions usually ranges from 6 to 8.5. Sodium citrate and citric acid have been added as a buffer. Buffered penicillin G potassium for injection, USP is supplied in vials equivalent to 1,000,000 units (1 million units), 5,000,000 units (5 million units), or 20,000,000 units (20 million units) of penicillin G as the potassium salt.
Each million unit contains approximately 7.9 milligrams of sodium (0.34 mEq) and 65.6 milligrams of potassium (1.68 mEq). chemical-structure