
carisoprodol 350 mg Tablet, 500-count — NDC 16571-781-50 (Billing 16571-0781-50)
This is a package of 500 tablets of carisoprodol 350 mg Tablet from Rising Pharma Holdings, Inc., marketed since Aug 2009 and currently FDA-listed; retail pharmacies pay about $0.0706 per tablet (NADAC). It is the main listing for this product, which comes in 3 package sizes.
NDC database record
One package, one record: these facts belong to NDC 16571-781-50 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 16571 labeler · 781 product · 50 package
- Package marketed since
- Aug 6, 2009
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 500 EA per package
- Barcode (UPC-A, from the NDC)
- 3 1657178150 8
- Medicaid fills, this package
- 784 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 004663
- GCN: 17912
- GPI-14 (Medi-Span): 75100020000305
- HICL (First Databank): 001944
- AHFS class code: 12:20.04.00
- RxCUI (RxNorm): 197446
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Muscle Relaxant class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Carisoprodol is used with rest, physical therapy, and other measures to relax muscles and relieve pain and discomfort caused by strains, sprains, and other muscle injuries. Carisoprodol is in a class of medications called skeletal muscle relaxants. It works by acting in the brain and nervous system to allow the muscles to relax.
Read the full MedlinePlus article ↗- It relieves discomfort from sudden, painful muscle and bone problems, like a strain, in adults. It is meant for short use, up to two or three weeks.
- Take it by mouth, usually three times a day and at bedtime, with or without food. Follow your prescriber's directions and don't use it longer than prescribed.
- It can. Drowsiness, dizziness, and headache are the most common side effects. Don't drive or do hazardous tasks until you know how it affects you.
- No, it's best to avoid alcohol. It adds to the sedation. The same goes for benzodiazepines, opioids, and tricyclic antidepressants, so tell me about everything you take.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Carisoprodol — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.071 | $35.30 / 500 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.1468 | $73.40 / 500 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1410 | $70.50 / 500 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 16571-0781-01 16571-781-01 | 100 TABLET in 1 BOTTLE | $0.0706 / ea | $7.06 | 2009-08-06 | — | Active |
| 16571-0781-10 16571-781-10 | 1000 TABLET in 1 BOTTLE | $0.0706 / ea | $70.59 | 2009-08-06 | — | Active |
| 16571-0781-50 You're viewing this Main listing | 500 TABLET in 1 BOTTLE | $0.0706 / ea | $35.30 | 2009-08-06 | — | Active |
You're viewing one of 3 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 3 priced pack sizes ($0.0706 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 92% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 16571-0781-01?
What NDC number is used to bill for this package of carisoprodol 350 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Carisoprodol 350 mg 42543-0700-01 | Vensun | 100 tablets | $0.051 | AA | FDA listed | save 27% |
| carisoprodol 350 mgthis 16571-0781-50 | Rising | 500 tablets | $0.071 | AA | Availability likely | — |
| Carisoprodol 350 mg 50228-0109-01 | ScieGen | 100 tablets | $0.071 | AA | Availability likely | — |
| Carisoprodol 350 mg 50742-0656-01 | Ingenus | 100 tablets | $0.071 | AA | Availability likely | — |
| Carisoprodol 350 mg 62135-0241-12 | Chartwell | 120 tablets | $0.071 | AA | Availability likely | — |
| Carisoprodol Tablets, USP, 350 mg 63561-0127-01 | Granulation | 100 tablets | $0.071 | AA | Availability likely | — |
| Carisoprodol 350 mg 69367-0420-01 | Westminster | 100 tablets | $0.071 | AA | Availability likely | — |
| Carisoprodol 350 mg 69584-0111-10 | Oxford | 100 tablets | $0.071 | AA | Availability likely | — |
| carisoprodol 350 mg 65862-0158-01 | Aurobindo | 100 tablets | $0.071 | — | FDA listed | +1% |
| Soma 350 mg 00037-2001-01 | Viatris | 100 tablets | $11.298 | AA | Availability likely | +15904% |
| Carisoprodol 350 mg 45865-0233-30 | Medsource | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 50090-5953-05 | A-S | 90 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 50090-5955-00 | A-S | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 52536-0688-10 | Wilshire | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 60760-0397-90 | St. | 90 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 61919-0878-60 | Direct_Rx | 60 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-2416-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-8477-01 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-8478-01 | Bryant | 500 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-8479-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 68071-3421-06 | NuCare | 60 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 68071-5075-03 | NuCare | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 70518-2800-00 | REMEDYREPACK | 60 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 70518-3792-00 | REMEDYREPACK | 90 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71205-0241-20 | Proficient | 20 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71205-0339-30 | Proficient | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71205-0704-30 | Proficient | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71335-1203-00 | Bryant | 56 tablets | — | AA | FDA listed | — |
| Carisoprodol Tablets, USP, 350 mg 71335-3018-01 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 71335-9613-00 | Bryant | 56 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71335-9621-00 | Bryant | 56 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71610-0617-30 | Aphena | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71610-0761-30 | Aphena | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72162-1524-00 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72162-1928-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol Tablets, USP, 350 mg 72162-2525-00 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72189-0310-30 | Directrx | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72189-0386-30 | Direct_Rx | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72789-0182-01 | PD-Rx | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72789-0190-14 | PD-Rx | 14 tablets | — | AA | FDA listed | — |
| Carisoprodol Tablets, USP, 350 mg 72789-0477-01 | PD-Rx | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 76420-0646-01 | Asclemed | 100 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 76420-0853-00 | Asclemed | 1000 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 80425-0291-01 | Advanced | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 82868-0062-30 | Northwind | 30 tablets | — | AA | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Carisoprodol inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Rising Pharma Holdings, Inc. labeler code 16571
- Glimepiride 1 mg Tablet NDC 16571-773-01
- Glimepiride 2 mg Tablet NDC 16571-774-01
- Glimepiride 4 mg Tablet NDC 16571-775-01
- Donepezil Hydrochloride 5 mg Tablet, Film Coated NDC 16571-778-03
- Donepezil Hydrochloride 10 mg Tablet, Film Coated NDC 16571-779-03
- carisoprodol 250 mg Tablet NDC 16571-780-01
- Cyclobenzaprine Hydrochloride 5 mg Tablet, Film Coated NDC 16571-782-01
- Cyclobenzaprine Hydrochloride 10 mg Tablet, Film Coated NDC 16571-783-01
- Gemfibrozil 600 mg Tablet, Film Coated NDC 16571-784-06
- Lamotrigine 5 mg Tablet, Chewable NDC 16571-785-01
- Lamotrigine 25 mg Tablet, Chewable NDC 16571-786-01
- Zolmitriptan 2.5 mg Tablet, Film Coated NDC 16571-803-16
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Carisoprodol tablets are indicated for the relief of discomfort associated with acute, painful musculoskeletal conditions in adults. Limitation of Use Carisoprodol tablets should only be used for short periods (up to two or three weeks) because adequate evidence of effectiveness for more prolonged use has not been established and because acute, painful musculoskeletal conditions are generally of short duration [see Dosage and Administration (2) ]. Carisoprodol is a muscle relaxant indicated for the relief of discomfort associated with acute, painful musculoskeletal conditions in adults.
(1) Limitation of Use Should only be used for acute treatment periods up to two or three weeks (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of carisoprodol tablets is 250 mg to 350 mg three times a day and at bedtime. The recommended maximum duration of carisoprodol tablets use is up to two or three weeks. Recommended dose is 250 mg to 350 mg three times a day and at bedtime. (2)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Carisoprodol tablets USP, 250 mg are white colored, round shaped, biconvex, uncoated tablets, identified with ‘H 94’ debossed on one side and other side plain. Carisoprodol tablets USP, 350 mg are white colored, round shaped, biconvex, uncoated tablets, identified with ‘D’ debossed on one side and ‘31’ on the other side. Tablets: 250 mg, 350 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Carisoprodol tablets are contraindicated in patients with a history of acute intermittent porphyria or a hypersensitivity reaction to a carbamate such as meprobamate. Acute intermittent porphyria (4) Hypersensitivity reactions to a carbamate such as meprobamate (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Due to sedative properties, may impair ability to perform hazardous tasks such as driving or operating machinery (5.1) Additive sedative effects when used with other CNS depressants including alcohol (5.1) Cases of abuse, dependence and withdrawal (5.2, 9.2 , 9.3 ) Seizures (5.3)
5.1Sedation Carisoprodol has sedative properties (in the low back pain trials, 13% to 17% of patients who received carisoprodol experienced sedation compared to 6% of patients who received placebo) [see ADVERSE REACTIONS (6.1) ] and may impair the mental and/or physical abilities required for the performance of potentially hazardous tasks such as driving a motor vehicle or operating machinery. There have been post-marketing reports of motor vehicle accidents associated with the use of carisoprodol. Since the sedative effects of carisoprodol and other CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) may be additive, appropriate caution should be exercised with patients who take more than one of these CNS depressants simultaneously.
5.2Abuse, Dependence and Withdrawal Carisoprodol, the active ingredient in carisoprodol, has been subject to abuse, dependence, and withdrawal, misuse and criminal diversion [see Drug Abuse and Dependence ( 9.1 , 9.2 , 9.3) ]. Abuse of carisoprodol poses a risk of overdosage which may lead to death, CNS and respiratory depression, hypotension, seizures and other disorders [see Overdosage (10) ]. Post-marketing experience cases of carisoprodol abuse and dependence have been reported in patients with prolonged use and a history of drug abuse.
Although most of these patients took other drugs of abuse, some patients solely abused carisoprodol. Withdrawal symptoms have been reported following abrupt cessation of carisoprodol after prolonged use. Reported withdrawal symptoms included insomnia, vomiting, abdominal cramps, headache, tremors, muscle twitching, ataxia, hallucinations, and psychosis.
One of carisoprodol’s metabolites, meprobamate (a controlled substance), may also cause dependence [see Clinical Pharmacology (12.3) ]. To reduce the risk of carisoprodol abuse assess the risk of abuse prior to prescribing. After prescribing, limit the length of treatment to three weeks for the relief of acute musculoskeletal discomfort, keep careful prescription records, monitor for signs of abuse and overdose, and educate patients and their families about abuse and on proper storage and disposal.
5.3Seizures There have been post-marketing reports of seizures in patients who received carisoprodol. Most of these cases have occurred in the setting of multiple drug overdoses (including drugs of abuse, illegal drugs, and alcohol) [see Overdosage (10) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence > 2%) are drowsiness, dizziness, and headache (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Rising Pharma Holdings, Inc. at 1(844) 874-7464 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect rates observed in practice. The data described below are based on 1387 patients pooled from two double blind, randomized, multicenter, placebo controlled, one-week trials in adult patients with acute, mechanical, lower back pain [see Clinical Studies (14) ] .
In these studies, patients were treated with 250 mg of carisoprodol, 350 mg of carisoprodol, or placebo three times a day and at bedtime for seven days. The mean age was about 41 years old with 54% females and 46% males and 74% Caucasian, 16% Black, 9% Asian, and 2% other. There were no deaths and there were no serious adverse reactions in these two trials.
In these two studies, 2.7%, 2%, and 5.4%, of patients treated with placebo, 250 mg of carisoprodol, and 350 mg of carisoprodol, respectively, discontinued due to adverse events; and 0.5%, 0.5%, and 1.8% of patients treated with placebo, 250 mg of carisoprodol, and 350 mg of carisoprodol, respectively, discontinued due to central nervous system adverse reactions. Table 1 displays adverse reactions reported with frequencies greater than 2% and more frequently than placebo in patients treated with carisoprodol in the two trials described above.
Table 1. Patients with Adverse Reactions in Controlled Studies Adverse Reaction Placebo (n=560) n (%) Carisoprodol 250 mg (n=548) n (%) Carisoprodol 350 mg (n=279) n (%) Drowsiness 31 (6) 73 (13) 47 (17) Dizziness 11 (2) 43 (8) 19 (7) Headache 11 (2) 26 (5) 9 (3)
6.2Post-marketing Experience The following events have been reported during postapproval use of carisoprodol. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cardiovascular: Tachycardia, postural hypotension, and facial flushing [see Overdosage (10) ].
Central Nervous System: Drowsiness, dizziness, vertigo, ataxia, tremor, agitation, irritability, headache, depressive reactions, syncope, insomnia, and seizures [see Overdosage (10) ] . Gastrointestinal: Nausea, vomiting, and epigastric discomfort. Hematologic: Leukopenia, pancytopenia.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) - additive sedative effects (5.1 , 7.1)
7.1CNS Depressants The sedative effects of carisoprodol and other CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) may be additive. Therefore, caution should be exercised with patients who take more than one of these CNS depressants simultaneously. Concomitant use of carisoprodol and meprobamate, a metabolite of carisoprodol, is not recommended [see Warnings and Precautions (5.1) ] .
7.2CYP2C19 Inhibitors and Inducers Carisoprodol is metabolized in the liver by CYP2C19 to form meprobamate [see Clinical Pharmacology (12.3) ] . Co-administration of CYP2C19 inhibitors, such as omeprazole or fluvoxamine, with carisoprodol could result in increased exposure of carisoprodol and decreased exposure of meprobamate. Co-administration of CYP2C19 inducers, such as rifampin or St.
John’s Wort, with carisoprodol could result in decreased exposure of carisoprodol and increased exposure of meprobamate. Low dose aspirin also showed an induction effect on CYP2C19. The full pharmacological impact of these potential alterations of exposures in terms of either efficacy or safety of carisoprodol is unknown.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Data over many decades of carisoprodol use in pregnancy have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Data on meprobamate, the primary metabolite of carisoprodol, also do not show a consistent association between maternal use of meprobamate and an increased risk of major birth defects (see Data). In a published animal reproduction study, pregnant mice administered carisoprodol orally at 2.6-and 4.1-times the maximum recommended human dose ([MRHD] of 1400 mg per day [350 mg QID] based on body surface area [BSA] comparison) from gestation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Retrospective case-control and cohort studies of meprobamate use during the first trimester of pregnancy have not consistently identified an increased risk or pattern of major birth defects. For children exposed to meprobamate in-utero , one study found no adverse effect on mental or motor development or IQ scores. Animal Data Embryofetal development studies in animals have not been completed.
In a published pre-and post-natal development animal study, pregnant mice administered carisoprodol orally at 300, 750, or 1200 mg/kg/day (approximately 1-, 2.6-, and 4.1-times the MRHD based on BSA comparison) from 7-days prior to gestation through birth and from lactation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival at 2.6-and 4.1-times the MRHD.
8.2Lactation Risk Summary Data from published literature report that carisoprodol and its metabolite, meprobamate, are present in breastmilk. There are no data on the effect of carisoprodol on milk production. There is one report of sedation in an infant who was breastfed by a mother taking carisoprodol (see Clinical Considerations).
Because there have been no consistent reports of adverse events in breastfed infants over decades of use, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for carisoprodol and any potential adverse effects on the breastfed infant from carisoprodol or from the underlying maternal condition. Clinical Considerations Infants exposed to carisoprodol through breast milk should be monitored for sedation.
8.4Pediatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in pediatric patients less than 16 years of age have not been established.
8.5Geriatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in patients over 65 years old have not been established.
8.6Renal Impairment The safety and pharmacokinetics of carisoprodol in patients with renal impairment have not been evaluated. Since carisoprodol is excreted by the kidney, caution should be exercised if carisoprodol is administered to patients with impaired renal function. Carisoprodol is dialyzable by hemodialysis and peritoneal dialysis.
8.7Hepatic Impairment The safety and pharmacokinetics of carisoprodol in patients with hepatic impairment have not been evaluated. Since carisoprodol is metabolized in the liver, caution should be exercised if carisoprodol is administered to patients with impaired hepatic function.
8.8Patients with Reduced CYP2C19 Activity Patients with reduced CYP2C19 activity have higher exposure to carisoprodol. Therefore, caution should be exercised in administration of carisoprodol to these patients [see Clinical Pharmacology (12.3) ] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Data over many decades of carisoprodol use in pregnancy have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Data on meprobamate, the primary metabolite of carisoprodol, also do not show a consistent association between maternal use of meprobamate and an increased risk of major birth defects (see Data). In a published animal reproduction study, pregnant mice administered carisoprodol orally at 2.6-and 4.1-times the maximum recommended human dose ([MRHD] of 1400 mg per day [350 mg QID] based on body surface area [BSA] comparison) from gestation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Retrospective case-control and cohort studies of meprobamate use during the first trimester of pregnancy have not consistently identified an increased risk or pattern of major birth defects. For children exposed to meprobamate in-utero , one study found no adverse effect on mental or motor development or IQ scores. Animal Data Embryofetal development studies in animals have not been completed.
In a published pre-and post-natal development animal study, pregnant mice administered carisoprodol orally at 300, 750, or 1200 mg/kg/day (approximately 1-, 2.6-, and 4.1-times the MRHD based on BSA comparison) from 7-days prior to gestation through birth and from lactation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival at 2.6-and 4.1-times the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in pediatric patients less than 16 years of age have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in patients over 65 years old have not been established.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Overdosage of carisoprodol commonly produces CNS depression. Death, coma, respiratory depression, hypotension, seizures, delirium, hallucinations, dystonic reactions, nystagmus, blurred vision, mydriasis, euphoria, muscular incoordination, rigidity, and/or headache have been reported with carisoprodol overdosage. Serotonin syndrome has been reported with carisoprodol intoxication.
Many of the carisoprodol overdoses have occurred in the setting of multiple drug overdoses (including drugs of abuse, illegal drugs, and alcohol). The effects of an overdose of carisoprodol and other CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) can be additive even when one of the drugs has been taken in the recommended dosage. Fatal accidental and non-accidental overdoses of carisoprodol have been reported alone or in combination with CNS depressants.
Treatment of Overdosage Basic life support measures should be instituted as dictated by the clinical presentation of the carisoprodol overdose. Vomiting should not be induced because of the risk of CNS and respiratory depression, and subsequent aspiration. Circulatory support should be administered with volume infusion and vasopressor agents if needed.
Seizures should be treated with intravenous benzodiazepines and the reoccurrence of seizures may be treated with phenobarbital. In cases of severe CNS depression, airway protective reflexes may be compromised and tracheal intubation should be considered for airway protection and respiratory support. For decontamination in cases of severe toxicity, activated charcoal should be considered in a hospital setting in patients with large overdoses who present early and are not demonstrating CNS depression and can protect their airway.
For more information on the management of an overdose of carisoprodol, contact a Poison Control Center.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of carisoprodol in relieving discomfort associated with acute painful musculoskeletal conditions has not been clearly identified. In animal studies, muscle relaxation induced by carisoprodol is associated with altered interneuronal activity in the spinal cord and in the descending reticular formation of the brain.
12.2Pharmacodynamics Carisoprodol is a centrally acting skeletal muscle relaxant that does not directly relax skeletal muscles. A metabolite of carisoprodol, meprobamate, has anxiolytic and sedative properties. The degree to which these properties of meprobamate contribute to the safety and efficacy of carisoprodol is unknown.
12.3Pharmacokinetics Absorption The pharmacokinetics of carisoprodol and its metabolite meprobamate were studied in a crossover study of 24 healthy subjects (12 male and 12 female) who received single doses of 250 mg and 350 mg carisoprodol (see Table 2). The exposure of carisoprodol and meprobamate was dose proportional between the 250 mg and 350 mg doses. The C max of meprobamate was 2.5 ± 0.5 mcg/mL (mean ± SD) after administration of a single 350 mg dose of carisoprodol, which is approximately 30% of the C max of meprobamate (approximately 8 mcg/mL) after administration of a single 400 mg dose of meprobamate.
Table 2. Pharmacokinetic Parameters of Carisoprodol and Meprobamate (Mean ± SD, n=24) 250 mg Carisoprodol 350 mg Carisoprodol Carisoprodol C max (mcg/mL) 1.2 ± 0.5 1.8 ± 1 AUC inf (mcg * hr/mL) 4.5 ± 3.1 7 ± 5 T max (hr) 1.5 ± 0.8 1.7 ±
0.8T 1/2 (hr) 1.7 ± 0.5 2 ±
0.5Meprobamate C max (mcg/mL) 1.8 ± 0.3 2.5 ±
0.5AUC inf (mcg * hr/mL) 32 ± 6.2 46 ± 9 T max (hr) 3.6 ± 1.7 4.5 ±
1.9T 1/2 (hr) 9.7 ± 1.7 9.6 ±
1.5Absolute bioavailability of carisoprodol has not been determined. The mean time to peak plasma concentrations (T max ) of carisoprodol was approximately 1.5 to 2 hours. Food Effect: Co-administration of a high-fat meal with carisoprodol (350 mg tablet) had no effect on the pharmacokinetics of carisoprodol.
Therefore, carisoprodol may be administered with or without food. Elimination Metabolism: The major pathway of carisoprodol metabolism is via the liver by cytochrome enzyme CYP2C19 to form meprobamate. This enzyme exhibits genetic polymorphism (see Patients with Reduced CYP2C19 Activity below).
Excretion: Carisoprodol is eliminated by both renal and non-renal routes with a terminal elimination half-life of approximately 2 hours. The half-life of meprobamate is approximately 10 hours. Specific Populations Sex: Exposure of carisoprodol is higher in female than in male subjects (approximately 30 to 50% on a weight adjusted basis).
Overall exposure of meprobamate is comparable between female and male subjects. Patients with Reduced CYP2C19 Activity: Carisoprodol should be used with caution in patients with reduced CYP2C19 activity. Published studies indicate that patients who are poor CYP2C19 metabolizers have a 4-fold increase in exposure to carisoprodol, and concomitant 50% reduced exposure to meprobamate compared to normal CYP2C19 metabolizers.
The prevalence of poor metabolizers in Caucasians and African Americans is approximately 3 to 5% and in Asians is approximately 15 to 20%.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of carisoprodol in relieving discomfort associated with acute painful musculoskeletal conditions has not been clearly identified. In animal studies, muscle relaxation induced by carisoprodol is associated with altered interneuronal activity in the spinal cord and in the descending reticular formation of the brain.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Carisoprodol Tablets USP, 250 mg are white colored, round shaped, biconvex, uncoated tablets, identified with ‘H 94’ debossed on one side and other side plain. Bottles of 100 NDC 16571-780-01 Carisoprodol Tablets USP, 350 mg are white colored, round shaped, biconvex, uncoated tablets, identified with ‘D’ debossed on one side and ‘31’ on the other side. Bottles of 100 NDC 16571-781-01 Bottles of 500 NDC 16571-781-50 Bottles of 1,000 NDC 16571-781-10 Storage Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Dispense in tight container.
📋 Description ▾
11 DESCRIPTION Carisoprodol tablets, USP are available as 250 mg and 350 mg round, white tablets. Carisoprodol USP is a white, crystalline powder, having a mild, characteristic odor and a bitter taste. It is slightly soluble in water; freely soluble in alcohol, in chloroform, and in acetone; and its solubility is practically independent of pH.
Carisoprodol is present as a racemic mixture. Chemically, carisoprodol is (±)-2-Methyl-2-propyl-1,3-propanediol carbamate isopropylcarbamate and the molecular formula is C 12 H 24 N 2 O 4 , with a molecular weight of 260.33. The structural formula is: Other ingredients in the carisoprodol tablets, USP include pregelatinized starch (maize), crospovidone, povidone, microcrystalline cellulose, colloidal silicon dioxide, and magnesium stearate. str1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Patients should be advised to contact their physician if they experience any adverse reactions to carisoprodol. Sedation Advise patients that carisoprodol may cause drowsiness and/or dizziness, and has been associated with motor vehicle accidents. Patients should be advised to avoid taking carisoprodol before engaging in potentially hazardous activities such as driving a motor vehicle or operating machinery [see Warnings and Precautions (5.1) ].
Avoidance of Alcohol and Other CNS Depressants Advise patients to avoid alcoholic beverages while taking carisoprodol and to check with their doctor before taking other CNS depressants such as benzodiazepines, opioids, tricyclic antidepressants, sedating antihistamines, or other sedatives [see Warnings and Precautions (5.1)] . Carisoprodol Should Only Be Used for Short-Term Treatment Advise patients that treatment with carisoprodol should be limited to acute use (up to two or three weeks) for the relief of acute, musculoskeletal discomfort.
In the post-marketing experience with carisoprodol, cases of dependence, withdrawal, and abuse have been reported with prolonged use. If the musculoskeletal symptoms still persist, patients should contact their healthcare provider for further evaluation. Lactation Advise nursing mothers using carisoprodol to monitor neonates for signs of sedation [see Use in Specific Populations (8.2) ].
Distributed by: Rising Pharma Holdings, Inc. East Brunswick, NJ 08816 Made in India Code: TS/DRUGS/19/1993 Issued: 06/2021
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The pharmacokinetics of carisoprodol and its metabolite meprobamate were studied in a crossover study of 24 healthy subjects (12 male and 12 female) who received single doses of 250 mg and 350 mg carisoprodol (see Table 2). The exposure of carisoprodol and meprobamate was dose proportional between the 250 mg and 350 mg doses. The C max of meprobamate was 2.5 ± 0.5 mcg/mL (mean ± SD) after administration of a single 350 mg dose of carisoprodol, which is approximately 30% of the C max of meprobamate (approximately 8 mcg/mL) after administration of a single 400 mg dose of meprobamate.
Table 2. Pharmacokinetic Parameters of Carisoprodol and Meprobamate (Mean ± SD, n=24) 250 mg Carisoprodol 350 mg Carisoprodol Carisoprodol C max (mcg/mL) 1.2 ± 0.5 1.8 ± 1 AUC inf (mcg * hr/mL) 4.5 ± 3.1 7 ± 5 T max (hr) 1.5 ± 0.8 1.7 ±
0.8T 1/2 (hr) 1.7 ± 0.5 2 ±
0.5Meprobamate C max (mcg/mL) 1.8 ± 0.3 2.5 ±
0.5AUC inf (mcg * hr/mL) 32 ± 6.2 46 ± 9 T max (hr) 3.6 ± 1.7 4.5 ±
1.9T 1/2 (hr) 9.7 ± 1.7 9.6 ±
1.5Absolute bioavailability of carisoprodol has not been determined. The mean time to peak plasma concentrations (T max ) of carisoprodol was approximately 1.5 to 2 hours. Food Effect: Co-administration of a high-fat meal with carisoprodol (350 mg tablet) had no effect on the pharmacokinetics of carisoprodol.
Therefore, carisoprodol may be administered with or without food. Elimination Metabolism: The major pathway of carisoprodol metabolism is via the liver by cytochrome enzyme CYP2C19 to form meprobamate. This enzyme exhibits genetic polymorphism (see Patients with Reduced CYP2C19 Activity below).
Excretion: Carisoprodol is eliminated by both renal and non-renal routes with a terminal elimination half-life of approximately 2 hours. The half-life of meprobamate is approximately 10 hours. Specific Populations Sex: Exposure of carisoprodol is higher in female than in male subjects (approximately 30 to 50% on a weight adjusted basis).
Overall exposure of meprobamate is comparable between female and male subjects. Patients with Reduced CYP2C19 Activity: Carisoprodol should be used with caution in patients with reduced CYP2C19 activity. Published studies indicate that patients who are poor CYP2C19 metabolizers have a 4-fold increase in exposure to carisoprodol, and concomitant 50% reduced exposure to meprobamate compared to normal CYP2C19 metabolizers.
The prevalence of poor metabolizers in Caucasians and African Americans is approximately 3 to 5% and in Asians is approximately 15 to 20%.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Carisoprodol is a centrally acting skeletal muscle relaxant that does not directly relax skeletal muscles. A metabolite of carisoprodol, meprobamate, has anxiolytic and sedative properties. The degree to which these properties of meprobamate contribute to the safety and efficacy of carisoprodol is unknown.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The safety and efficacy of carisoprodol for the relief of acute, idiopathic mechanical low back pain was evaluated in two, 7-day, double blind, randomized, multicenter, placebo controlled, U.S. trials (Studies 1 and 2). Patients had to be 18 to 65 years old and had to have acute back pain (≤ 3 days of duration) to be included in the trials. Patients with chronic back pain; at increased risk for vertebral fracture (e.g., history of osteoporosis); with a history of spinal pathology (e.g., herniated nucleus pulposus, spondylolisthesis or spinal stenosis); with inflammatory back pain, or with evidence of a neurologic deficit were excluded from participation.
Concomitant use of analgesics (e.g., acetaminophen, NSAIDs, tramadol, opioid agonists), other muscle relaxants, botulinum toxin, sedatives (e.g., barbiturates, benzodiazepines, promethazine hydrochloride), and anti-epileptic drugs was prohibited. In Study 1, patients were randomized to one of three treatment groups (i.e., carisoprodol 250 mg, carisoprodol 350 mg, or placebo) and in Study 2 patients were randomized to two treatment groups (i.e., carisoprodol 250 mg or placebo). In both studies, patients received study medication three times a day and at bedtime for seven days.
The primary endpoints were the relief from starting backache and the global impression of change, as reported by patients, on Study Day 3. Both endpoints were scored on a 5-point rating scale from 0 (worst outcome) to 4 (best outcome) in both studies. The primary statistical comparison was between the carisoprodol 250 mg and placebo groups in both studies.
The proportion of patients who used concomitant acetaminophen, NSAIDs, tramadol, opioid agonists, other muscle relaxants, and benzodiazepines was similar in the treatment groups. The results for the primary efficacy evaluations in the acute, low back pain studies are presented in Table 3. a The primary efficacy endpoints (Relief from Starting Backache and Global Impression of Change) were assessed by the patients on Study Day 3. These endpoints were scored on a 5-point rating scale from 0 (worst outcome) to 4 (best outcome). b Mean is the least squared mean and SE is the standard error of the mean.
The ANOVA model was used for the primary statistical comparison between the carisoprodol 250 mg and placebo groups. Table 3. Results of the Primary Efficacy Endpoints a in Studies 1 and 2 Study Parameter Placebo Carisoprodol 250 mg Carisoprodol 350 mg 1 Number of Patients n=269 n=264 n=273 Relief from Starting Backache, Mean (SE) b 1.4 (0.1) 1.8 (0.1) 1.8 (0.1) Difference between Carisoprodol and Placebo, Mean (SE) b (95% CI) 0.4 (0.2, 0.5) 0.4 (0.2, 0.6) Global Impression of Change, Mean (SE) b 1.9 (0.1) 2.2 (0.1) 2.2 (0.1) Difference between Carisoprodol and Placebo, Mean (SE) b (95% CI) 0.2 (0.1, 0.4) 0.3 (0.1, 0.4) 2 Number of Patients n=278 n=269 Relief from Starting Backache, Mean (SE) b 1.1 (0.1) 1.8 (0.1) Difference between Carisoprodol and Placebo, Mean (SE) b (95% CI) 0.7 (0.5, 0.9) Global Impression of Change, Mean (SE) b 1.7 (0.1) 2.2 (0.1) Difference between Carisoprodol and Placebo, Mean (SE) b (95% CI) 0.5 (0.4, 0.7) Patients treated with carisoprodol experienced improvement in function as measured by the Roland-Morris Disability Questionnaire (RMDQ) score on Days 3 and 7.
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Carisoprodol, a Schedule IV controlled substance. Carisoprodol has been subject to abuse, misuse, and criminal diversion for nontherapeutic use [see Warnings and Precautions (5.2) ] .
9.2Abuse Abuse of carisoprodol poses a risk of overdosage which may lead to death, CNS and respiratory depression, hypotension, seizures and other disorders [see Warnings and Precautions (5.2) and Overdosage (10) ] . Patients at high risk of carisoprodol abuse may include those with prolonged use of carisoprodol, with a history of drug abuse, or those who use carisoprodol in combination with other abused drugs. Prescription drug abuse is the intentional non-therapeutic use of a drug, even once, for its rewarding psychological effects.
Drug addiction, which develops after repeated drug abuse, is characterized by a strong desire to take a drug despite harmful consequences, difficulty in controlling its use, giving a higher priority to drug use than to obligations, increased tolerance, and sometimes physical withdrawal. Drug abuse and drug addiction are separate and distinct from physical dependence and tolerance (for example, abuse or addiction may not be accompanied by tolerance or physical dependence) [see Drug Abuse and Dependence (9.3) ].
9.3Dependence Tolerance is when a patient’s reaction to a specific dosage and concentration is progressively reduced in the absence of disease progression, requiring an increase in the dosage to maintain the same. Physical dependence is characterized by withdrawal symptoms after abrupt discontinuation or a significant dose reduction of a drug. Both tolerance and physical dependence have been reported with the prolonged use of carisoprodol.
Reported withdrawal symptoms with carisoprodol include insomnia, vomiting, abdominal cramps, headache, tremors, muscle twitching, anxiety, ataxia, hallucinations, and psychosis. Instruct patients taking large doses of carisoprodol or those taking the drug for a prolonged time to not abruptly stop carisoprodol [see Warnings and Precautions (5.2) ].
🔒 Controlled Substance ▾
9.1Controlled Substance Carisoprodol, a Schedule IV controlled substance. Carisoprodol has been subject to abuse, misuse, and criminal diversion for nontherapeutic use [see Warnings and Precautions (5.2) ] .
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long term studies in animals have not been performed to evaluate the carcinogenic potential of carisoprodol. M utagenesis Carisoprodol was not formally evaluated for genotoxicity. In published studies, carisoprodol was mutagenic in the in vitro mouse lymphoma cell assay in the absence of metabolizing enzymes, but was not mutagenic in the presence of metabolizing enzymes.
Carisoprodol was clastogenic in the in vitro chromosomal aberration assay using Chinese hamster ovary cells with or without the presence of metabolizing enzymes. Other types of genotoxic tests resulted in negative findings. Carisoprodol was not mutagenic in the Ames reverse mutation assay using S. typhimurium strains with or without metabolizing enzymes, and was not clastogenic in an in vivo mouse micronucleus assay of circulating blood cells.
I mpairment of Fertility Carisoprodol was not formally evaluated for effects on fertility. A published reproductive study in which female mice received carisoprodol orally at doses of 300, 750, or 1200 mg/kg/day (approximately 1, 2.6, and 4.1 times the MRHD of 1400 mg per day [350 mg QID] based on body surface area [BSA] comparison) from 1-week prior to mating, to 27-weeks post-mating found no alteration in fertility although an alteration in reproductive cycles characterized by a greater time spent in estrus was observed at a carisoprodol dose of 1200 mg/kg/day.
In a 13-week toxicology study that did not determine fertility, mouse testes weight and sperm motility were reduced at a dose of 1200 mg/kg/day (maternal doses equivalent to 4.2-times the MRHD based on BSA comparison). In both studies, the no effect level was 750 mg/kg/day, corresponding to approximately 2.6-times the MRHD based on a BSA comparison. The significance of these findings for human fertility is not known.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long term studies in animals have not been performed to evaluate the carcinogenic potential of carisoprodol. M utagenesis Carisoprodol was not formally evaluated for genotoxicity. In published studies, carisoprodol was mutagenic in the in vitro mouse lymphoma cell assay in the absence of metabolizing enzymes, but was not mutagenic in the presence of metabolizing enzymes.
Carisoprodol was clastogenic in the in vitro chromosomal aberration assay using Chinese hamster ovary cells with or without the presence of metabolizing enzymes. Other types of genotoxic tests resulted in negative findings. Carisoprodol was not mutagenic in the Ames reverse mutation assay using S. typhimurium strains with or without metabolizing enzymes, and was not clastogenic in an in vivo mouse micronucleus assay of circulating blood cells.
I mpairment of Fertility Carisoprodol was not formally evaluated for effects on fertility. A published reproductive study in which female mice received carisoprodol orally at doses of 300, 750, or 1200 mg/kg/day (approximately 1, 2.6, and 4.1 times the MRHD of 1400 mg per day [350 mg QID] based on body surface area [BSA] comparison) from 1-week prior to mating, to 27-weeks post-mating found no alteration in fertility although an alteration in reproductive cycles characterized by a greater time spent in estrus was observed at a carisoprodol dose of 1200 mg/kg/day.
In a 13-week toxicology study that did not determine fertility, mouse testes weight and sperm motility were reduced at a dose of 1200 mg/kg/day (maternal doses equivalent to 4.2-times the MRHD based on BSA comparison). In both studies, the no effect level was 750 mg/kg/day, corresponding to approximately 2.6-times the MRHD based on a BSA comparison. The significance of these findings for human fertility is not known.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (100 Tablet Bottle) Rising ® PHARMACEUTICALS NDC 16571-780-01 Carisoprodol Tablets, USP CIV 250 mg 100 Tablets Rx only PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 250 mg (100 Tablet Bottle)
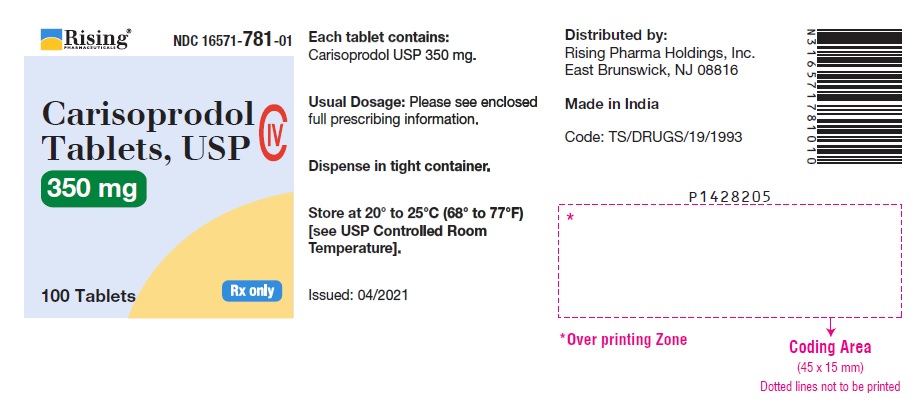
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 350 mg (100 Tablet Bottle) Rising ® PHARMACEUTICALS NDC 16571-781-01 Carisoprodol Tablets, USP CIV 350 mg 100 Tablets Rx only PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 350 mg (100 Tablet Bottle)