
Cefpodoxime Proxetil 50 mg/5mL Granule, For Suspension — NDC 16714-402-02 (Billing 16714-0402-02)
This is a package of Cefpodoxime Proxetil 50 mg/5mL Granule, For Suspension from NorthStar Rx LLC, marketed since Jun 2007 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 16714-402-02 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 16714 labeler · 402 product · 02 package
- Package marketed since
- Jun 8, 2007
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0316714402017, 0316714403014
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 016929
- GCN: 49301
- GPI-14 (Medi-Span): 02300065101920
- HICL (First Databank): 006495
- AHFS class code: 08:12.06.12
- RxCUI (RxNorm): 309077
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Cephalosporin Antibacterial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Cefpodoxime treats a wide range of common bacterial infections. These include ear infections, strep throat and tonsillitis, sinus infections, pneumonia, bronchitis flare-ups, skin...
- What kinds of infections does cefpodoxime treat?
- It depends on which form you have. If you're taking the tablet, take it with food — your body absorbs it better that way, so you'll get more of the medication working for you. If y...
- Should I take cefpodoxime with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cefpodoxime Proxetil — tap one for details:
Cefpodoxime Proxetil may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.6034 | $60.34 / 100 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 16714-0402-01 16714-402-01 Main listing | 1 BOTTLE in 1 CARTON / 50 mL in 1 BOTTLE | 2007-06-08 | — | Active |
| 16714-0402-02 You're viewing this | 1 BOTTLE in 1 CARTON / 100 mL in 1 BOTTLE | 2007-06-08 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Cefpodoxime Proxetil 50 mg/5mL Granule, For Suspension?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cefpodoxime Proxetil 50 mg/5mLthis 16714-0402-02 | NorthStar | 1 bottle | — | — | FDA listed | — |
| Cefpodoxime Proxetil 50 mg/5mL 64980-0402-10 | Rising | 1 bottle | — | — | FDA listed | — |
| Cefpodoxime Proxetil 50 mg/5mL 65862-0140-01 | Aurobindo | 1 bottle | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Cefpodoxime inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from NorthStar Rx LLC labeler code 16714
- Cefprozil 125 mg/5mL Powder, For Suspension NDC 16714-396-01
- Cefprozil 250 mg/5mL Powder, For Suspension NDC 16714-397-01
- Cefprozil 250 mg Tablet, Film Coated NDC 16714-398-01
- Cefprozil 500 mg Tablet, Film Coated NDC 16714-399-01
- Cefuroxime Axetil 250 mg Tablet NDC 16714-400-01
- Cefuroxime Axetil 500 mg Tablet NDC 16714-401-01
- Cefpodoxime Proxetil 100 mg/5mL Granule, For Suspension NDC 16714-403-01
- PIMTREA desogestrel/ethinyl estradiol and ethinyl Kit NDC 16714-404-01
- Larin Fe 1.5/30 Norethindrone Acetate/Ethinyl Estradiol and Ferrous Fumarate Kit NDC 16714-405-01
- Larin Fe 1/20 Norethindrone Acetate/Ethinyl Estradiol and Ferrous Fumarate Kit NDC 16714-406-01
- Larin 1.5/30 Norethindrone Acetate/Ethinyl Estradiol Kit NDC 16714-407-01
- Larin 1/20 Norethindrone Acetate/Ethinyl Estradiol Kit NDC 16714-408-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Cefpodoxime proxetil is indicated for the treatment of patients with mild to moderate infections caused by susceptible strains of the designated microorganisms in the conditions listed below. Recommended dosages, durations of therapy, and applicable patient populations vary among these infections. Please see DOSAGE AND ADMINISTRATION for specific recommendations.
Acute otitis media caused by Streptococcus pneumoniae (excluding penicillin-resistant strains), Streptococcus pyogenes , Haemophilus influenzae (including beta-lactamase-producing strains), or Moraxella (Branhamella) catarrhalis (including beta-lactamase producing strains). Pharyngitis and/or tonsillitis caused by Streptococcus pyogenes . NOTE: Only penicillin by the intramuscular route of administration has been shown to be effective in the prophylaxis of rheumatic fever.
Cefpodoxime proxetil is generally effective in the eradication of streptococci from the oropharynx. However, data establishing the efficacy of cefpodoxime proxetil for the prophylaxis of subsequent rheumatic fever are not available. Community-acquired pneumonia caused by S. pneumoniae or H.
Influenzae (including beta-lactamase-producing strains). Acute bacterial exacerbation of chronic bronchitis caused by S. pneumoniae , H. influenzae (non-beta-lactamase-producing strains only), or M. catarrhalis . Data are insufficient at this time to establish efficacy in patients with acute bacterial exacerbations of chronic bronchitis caused by beta-lactamase-producing strains of H. influenzae .
Acute, uncomplicated urethral and cervical gonorrhea caused by Neisseria gonorrhoeae (including penicillinase-producing strains). Acute, uncomplicated ano-rectal infections in women due to Neisseria gonorrhoeae (including penicillinase-producing strains). NOTE: The efficacy of cefpodoxime in treating male patients with rectal infections caused by N. gonorrhoeae has not been established.
Data do not support the use of cefpodoxime proxetil in the treatment of pharyngeal infections due to N. gonorrhoeae in men or women. Uncomplicated skin and skin structure infections caused by Staphylococcus aureus (including penicillinase-producing strains) or Streptococcus pyogenes . Abscesses should be surgically drained as clinically indicated.
NOTE: In clinical trials, successful treatment of uncomplicated skin and skin structure infections was dose-related. The effective therapeutic dose for skin infections was higher than those used in other recommended indications. (See DOSAGE AND ADMINISTRATION .) Acute maxillary sinusitis caused by Haemophilus influenzae (including beta-lactamase-producing strains), Streptococcus pneumoniae , and Moraxella catarrhalis .
Uncomplicated urinary tract infections (cystitis) caused by Escherichia coli, Klebsiella pneumoniae, Proteus mirabilis , or Staphylococcus saprophyticus . NOTE: In considering the use of cefpodoxime proxetil in the treatment of cystitis, cefpodoxime proxetil’s lower bacterial eradication rates should be weighed against the increased eradication rates and different safety profiles of some other classes of approved agents. (See CLINICAL STUDIES section.) Appropriate specimens for bacteriological examination should be obtained in order to isolate and identify causative organisms and to determine their susceptibility to cefpodoxime.
Therapy may be instituted while awaiting the results of these studies. Once these results become available, antimicrobial therapy should be adjusted accordingly. To reduce the development of drug-resistant bacteria and maintain the effectiveness of cefpodoxime proxetil and other antibacterial drugs, cefpodoxime proxetil should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria.
When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and suscep… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION (See INDICATIONS AND USAGE for indicated pathogens.) Cefpodoxime proxetil for oral suspension may be given without regard to food. The recommended dosages, durations of treatment, and applicable patient populations are as described in the following chart: Adults and Adolescents (age 12 years and older): Type of Infection Total Daily Dose Dose Frequency Duration Pharyngitis and/or tonsillitis 200 mg 100 mg Q 12 hours 5 to 10 days Acute community-acquired pneumonia 400 mg 200 mg Q 12 hours 14 days Uncomplicated gonorrhea (men and women) and rectal gonococcal infections (women) 200 mg single dose Skin and skin structure 800 mg 400 mg Q 12 hours 7 to 14 days Acute maxillary sinusitis 400 mg 200 mg Q 12 hours 10 days Uncomplicated urinary tract infection 200 mg 100 mg Q 12 hours 7 days Infants and Pediatric Patients (age 2 months through 12 years): Type of Infection Total Daily Dose Dose Frequency Duration Acute otitis media 10 mg/kg/day (Max 400 mg/day) 5 mg/kg Q 12 h (Max 200 mg/dose) 5 days Pharyngitis and/or tonsillitis 10 mg/kg/day (Max 200 mg/day) 5 mg/kg/dose Q 12 h (Max 100 mg/dose) 5 to 10 days Acute maxillary sinusitis 10 mg/kg/day (Max 400 mg/day) 5 mg/kg Q 12 hours (Max 200 mg/dose) 10 days Patients with Renal Dysfunction: For patients with severe renal impairment (<30 mL/min creatinine clearance), the dosing intervals should be increased to Q 24 hours.
In patients maintained on hemodialysis, the dose frequency should be 3 times/week after hemodialysis. When only the serum creatinine level is available, the following formula (based on sex, weight, and age of the patient) may be used to estimate creatinine clearance (mL/min). For this estimate to be valid, the serum creatinine level should represent a steady state of renal function.
Males: Weight (kg) x (140 - age) (mL/min) 72 x serum creatinine (mg/100 mL) Females: 0.85 x above value (mL/min) Patients with Cirrhosis: Cefpodoxime pharmacokinetics in cirrhotic patients (with or without ascites) are similar to those in healthy subjects. Dose adjustment is not necessary in this population. Directions for use: Before reconstitution, remove the desiccant capsule by pulling out two small rings, then discard.
Preparation of Suspension: Constitution Directions For Oral Suspension Constituted Volume Final Concentration Directions 50 mL 50 mg per 5 mL Suspend in a total of 31 mL of distilled water. Method: First, shake the bottle to loosen granules. Then add the water in two approximately equal portions, shaking vigorously after each aliquot of water.
100 mL 50 mg per 5 mL Suspend in a total of 57 mL of distilled water. Method: First, shake the bottle to loosen granules. Then add the water in two approximately equal portions, shaking vigorously after each aliquot of water.
50 mL 100 mg per 5 mL Suspend in a total of 30 mL of distilled water. Method: First, shake the bottle to loosen granules. Then add the water in two approximately equal portions, shaking vigorously after each aliquot of water.
100 mL 100 mg per 5 mL Suspend in a total of 57 mL of distilled water. Method: First, shake the bottle to loosen granules. Then add the water in two approximately equal portions, shaking vigorously after each aliquot of water.
After mixing, the suspension should be stored in a refrigerator, 2° to 8°C (36° to 46°F). Shake well before using. Keep container tightly closed.
The mixture may be used for 14 days. Discard unused portion after 14 days.
⛔ Contraindications ▾
CONTRAINDICATIONS Cefpodoxime proxetil is contraindicated in patients with a known allergy to cefpodoxime or to the cephalosporin group of antibiotics.
⚠️ Warnings ▾
WARNINGS BEFORE THERAPY WITH CEFPODOXIME PROXETIL IS INSTITUTED, CAREFUL INQUIRY SHOULD BE MADE TO DETERMINE WHETHER THE PATIENT HAS HAD PREVIOUS HYPERSENSITIVITY REACTIONS TO CEFPODOXIME, OTHER CEPHALOSPORINS, PENICILLINS, OR OTHER DRUGS. IF CEFPODOXIME IS TO BE ADMINISTERED TO PENICILLIN SENSITIVE PATIENTS, CAUTION SHOULD BE EXERCISED BECAUSE CROSS HYPERSENSITIVITY AMONG BETA-LACTAM ANTIBIOTICS HAS BEEN CLEARLY DOCUMENTED AND MAY OCCUR IN UP TO 10% OF PATIENTS WITH A HISTORY OF PENICILLIN ALLERGY. IF AN ALLERGIC REACTION TO CEFPODOXIME PROXETIL OCCURS, DISCONTINUE THE DRUG.
SERIOUS ACUTE HYPERSENSITIVITY REACTIONS MAY REQUIRE TREATMENT WITH EPINEPHRINE AND OTHER EMERGENCY MEASURES, INCLUDING OXYGEN, INTRAVENOUS FLUIDS, INTRAVENOUS ANTIHISTAMINE, AND AIRWAY MANAGEMENT, AS CLINICALLY INDICATED. Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including cefpodoxime proxetil, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile.
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
A concerted effort to monitor for C. difficile in cefpodoxime-treated patients with diarrhea was undertaken because of an increased incidence of diarrhea associated with C. difficile in early trials in normal subjects. C. difficile organisms or toxin was reported in 10% of the cefpodoxime-treated adult patients with diarrhea; however, no specific diagnosis of pseudomembranous colitis was made in these patients. In post-marketing experience outside the United States, reports of pseudomembranous colitis associated with the use of cefpodoxime proxetil have been received.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Clinical Trials: In clinical trials using multiple doses of cefpodoxime proxetil granules for oral suspension, 2128 pediatric patients (93% of whom were less than 12 years of age) were treated with the recommended dosages of cefpodoxime (10 mg/kg/day Q 24 hours or divided Q 12 hours to a maximum equivalent adult dose). There were no deaths or permanent disabilities in any of the patients in these studies. Twenty-four patients (1.1%) discontinued medication due to adverse events thought possibly or probably related to study drug.
Primarily, these discontinuations were for gastrointestinal disturbances, usually diarrhea, vomiting, or rashes. Adverse events thought possibly or probably related, or of unknown relationship to cefpodoxime proxetil for oral suspension in multiple dose clinical trials (N=2128 patients treated with cefpodoxime) were: Incidence Greater Than 1%: Diarrhea 6% The incidence of diarrhea in infants and toddlers (age 1 month to 2 years) was 12.8%. Diaper rash/Fungal skin rash 2% (includes moniliasis) The incidence of diaper rash in infants and toddlers was 8.5%.
Other skin rashes 1.8% Vomiting 2.3% Incidence Less Than 1%: Body: Localized abdominal pain, abdominal cramp, headache, monilia, generalized abdominal pain, asthenia, fever, fungal infection. Digestive: Nausea, monilia, anorexia, dry mouth, stomatitis, pseudomembranous colitis. Hemic & Lymphatic: Thrombocythemia, positive direct Coombs’ test, eosinophilia, leukocytosis, leukopenia, prolonged partial thromboplastin time, thrombocytopenic purpura.
Metabolic & Nutritional: Increased SGPT. Musculo-Skeletal: Myalgia. Nervous: Hallucination, hyperkinesia, nervousness, somnolence.
Respiratory: Epistaxis, rhinitis. Skin: Skin moniliasis, urticaria, fungal dermatitis, acne, exfoliative dermatitis, maculopapular rash. Special Senses: Taste perversion.
Laboratory Changes Significant laboratory changes that have been reported in adult and pediatric patients in clinical trials of cefpodoxime proxetil, without regard to drug relationship, were: Hepatic: Transient increases in AST (SGOT), ALT (SGPT), GGT, alkaline phosphatase, bilirubin, and LDH. Hematologic: Eosinophilia, leukocytosis, lymphocytosis, granulocytosis, basophilia, monocytosis, thrombocytosis, decreased hemoglobin, decreased hematocrit, leukopenia, neutropenia, lymphocytopenia, thrombocytopenia, thrombocythemia, positive Coombs’ test, and prolonged PT, and PTT.
Serum Chemistry: Hyperglycemia, hypoglycemia, hypoalbuminemia, hypoproteinemia, hyperkalemia, and hyponatremia. Renal: Increases in BUN and creatinine. Most of these abnormalities were transient and not clinically significant.
Post-marketing Experience: The following serious adverse experiences have been reported: allergic reactions including Stevens-Johnson syndrome, toxic epidermal necrolysis, erythema multiforme and serum sickness-like reactions, pseudomembranous colitis, bloody diarrhea with abdominal pain, ulcerative colitis, rectorrhagia with hypotension, anaphylactic shock, acute liver injury, in utero exposure with miscarriage, purpuric nephritis, pulmonary infiltrate with eosinophilia, and eyelid dermatitis. One death was attributed to pseudomembranous colitis and disseminated intravascular coagulation.
Cephalosporin Class Labeling: In addition to the adverse reactions listed above which have been observed in patients treated with cefpodoxime proxetil, the following adverse reactions and altered laboratory tests have been reported for cephalosporin class antibiotics: Adverse Reactions and Abnormal Laboratory Tests: Renal dysfunction, toxic nephropathy, hepatic dysfunction including cholestasis, aplastic anemia, hemolytic anemia, serum sickness-like reaction, hemorrhage, agranulocytosis, and pancytopenia. Several cephalosporins have been implicated in triggering seizures, particularly in patients with renal impairment when the dosage was not reduced.
(See DOSAGE AND ADMINISTRATION and OVERDOSAGE .) If seizures associated… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions: Antacids : Concomitant administration of high doses of antacids (sodium bicarbonate and aluminum hydroxide) or H 2 blockers reduces peak plasma levels by 24% to 42% and the extent of absorption by 27% to 32%, respectively. The rate of absorption is not altered by these concomitant medications. Oral anti-cholinergics (e.g., propantheline) delay peak plasma levels (47% increase in T max ), but do not affect the extent of absorption (AUC).
Probenecid : As with other beta-lactam antibiotics, renal excretion of cefpodoxime was inhibited by probenecid and resulted in an approximately 31% increase in AUC and 20% increase in peak cefpodoxime plasma levels. Nephrotoxic drugs : Although nephrotoxicity has not been noted when cefpodoxime proxetil was given alone, close monitoring of renal function is advised when cefpodoxime proxetil is administered concomitantly with compounds of known nephrotoxic potential.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions: Cephalosporins, including cefpodoxime proxetil, are known to occasionally induce a positive direct Coombs’ test.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects: Pregnancy Category B Cefpodoxime proxetil was neither teratogenic nor embryocidal when administered to rats during organogenesis at doses up to 100 mg/kg/day (2 times the human dose based on mg/m 2 ) or to rabbits at doses up to 30 mg/kg/day (1 to 2 times the human dose based on mg/m 2 ). There are, however, no adequate and well-controlled studies of cefpodoxime proxetil use in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use: Safety and efficacy in infants less than 2 months of age have not been established.
🧓 Geriatric Use ▾
Geriatric Use: Of the 3338 patients in multiple-dose clinical studies of cefpodoxime proxetil film-coated tablets, 521 (16%) were 65 and over, while 214 (6%) were 75 and over. No overall differences in effectiveness or safety were observed between the elderly and younger patients. In healthy geriatric subjects with normal renal function, cefpodoxime half-life in plasma averaged 4.2 hours and urinary recovery averaged 21% after a 400 mg dose was given every 12 hours for 15 days.
Other pharmacokinetic parameters were unchanged relative to those observed in healthy younger subjects. Dose adjustment in elderly patients with normal renal function is not necessary.
🆘 Overdosage ▾
OVERDOSAGE In acute rodent toxicity studies, a single 5 g/kg oral dose produced no adverse effects. In the event of serious toxic reaction from overdosage, hemodialysis or peritoneal dialysis may aid in the removal of cefpodoxime from the body, particularly if renal function is compromised. The toxic symptoms following an overdose of beta-lactam antibiotics may include nausea, vomiting, epigastric distress, and diarrhea.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Absorption and Excretion: Cefpodoxime proxetil is a prodrug that is absorbed from the gastrointestinal tract and de-esterified to its active metabolite, cefpodoxime. Following oral administration of 100 mg of cefpodoxime proxetil to fasting subjects, approximately 50% of the administered cefpodoxime dose was absorbed systemically. Over the recommended dosing range (100 to 400 mg), approximately 29 to 33% of the administered cefpodoxime dose was excreted unchanged in the urine in 12 hours.
There is minimal metabolism of cefpodoxime in vivo . Effects of Food: When a 200 mg dose of the suspension was taken with food, the extent of absorption (mean AUC) and mean peak plasma concentration in fed subjects were not significantly different from fasted subjects, but the rate of absorption was slower with food (48% increase in T max ). Pharmacokinetics of Cefpodoxime Proxetil Suspension: In adult subjects, a 100 mg dose of oral suspension produced an average peak cefpodoxime concentration of approximately 1.5 mcg/mL (range: 1.1 to 2.1 mcg/mL), which is equivalent to that reported following administration of the 100 mg tablet.
Time to peak plasma concentration and area under the plasma concentration-time curve (AUC) for the oral suspension were also equivalent to those produced with film-coated tablets in adults following a 100 mg oral dose. The pharmacokinetics of cefpodoxime were investigated in 29 patients aged 1 to 17 years. Each patient received a single, oral, 5 mg/kg dose of cefpodoxime oral suspension.
Plasma and urine samples were collected for 12 hours after dosing. The plasma levels reported from this study are as follows: CEFPODOXIME PLASMA LEVELS (mcg/mL) IN FASTED PATIENTS (1 to 17 YEARS OF AGE) AFTER SUSPENSION ADMINISTRATION Dose (cefpodoxime equivalents) Time after oral ingestion 1hr 2hr 3hr 4hr 6hr 8hr 12hr 1 Dose did not exceed 200 mg. 5 mg/kg 1 1.4 2.1 2.1 1.7 0.9 0.4
0.09Distribution: Protein binding of cefpodoxime ranges from 22 to 33% in serum and from 21 to 29% in plasma. Skin Blister: Following multiple-dose administration every 12 hours for 5 days of 200 mg or 400 mg cefpodoxime proxetil, the mean maximum cefpodoxime concentration in skin blister fluid averaged 1.6 and 2.8 mcg/mL, respectively. Skin blister fluid cefpodoxime levels at 12 hours after dosing averaged 0.2 and 0.4 mcg/mL for the 200 mg and 400 mg multiple-dose regimens, respectively.
Tonsil Tissue: Following a single, oral 100 mg cefpodoxime proxetil film-coated tablet, the mean maximum cefpodoxime concentration in tonsil tissue averaged 0.24 mcg/g at 4 hours post-dosing and 0.09 mcg/g at 7 hours post-dosing. Equilibrium was achieved between plasma and tonsil tissue within 4 hours of dosing. No detection of cefpodoxime in tonsillar tissue was reported 12 hours after dosing.
These results demonstrated that concentrations of cefpodoxime exceeded the MIC 90 of S. pyogenes for at least 7 hours after dosing of 100 mg of cefpodoxime proxetil. Lung Tissue: Following a single, oral 200 mg cefpodoxime proxetil film-coated tablet, the mean maximum cefpodoxime concentration in lung tissue averaged 0.63 mcg/g at 3 hours post-dosing, 0.52 mcg/g at 6 hours post-dosing, and 0.19 mcg/g at 12 hours post-dosing. The results of this study indicated that cefpodoxime penetrated into lung tissue and produced sustained drug concentrations for at least 12 hours after dosing at levels that exceeded the MIC 90 for S. pneumoniae and H. influenzae .
CSF: Adequate data on CSF levels of cefpodoxime are not available. Effects of Decreased Renal Function: Elimination of cefpodoxime is reduced in patients with moderate to severe renal impairment (<50 mL/min creatinine clearance). (See PRECAUTIONS and DOSAGE AND ADMINISTRATION .) In subjects with mild impairment of renal function (50 to 80 mL/min creatinine clearance), the average plasma half-life of cefpodoxime was 3.5 hours.
In subjects with moderate (30 to 49 mL/min creatinine clearance) or severe renal imp… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Cefpodoxime Proxetil for Oral Suspension, USP provides the equivalent of 50 mg or 100 mg cefpodoxime per 5 mL suspension (when constituted as directed) and is available as off-white colored granular powder in the following sizes: 50 mg/5 mL 50-mL suspension NDC 16714-402-01 100-mL suspension NDC 16714-402-02 100 mg/5 mL 50-mL suspension NDC 16714-403-01 100-mL suspension NDC 16714-403-02 Store unsuspended granules at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
Directions for mixing are included on the label. After mixing, suspension should be stored in a refrigerator, 2° to 8°C (36° to 46°F). Shake well before using.
Keep container tightly closed. The mixture may be used for 14 days. Discard unused portion after 14 days.
📋 Description ▾
DESCRIPTION Cefpodoxime proxetil is an orally administered, extended spectrum, semi-synthetic antibiotic of the cephalosporin class. The chemical name is (RS)-1(isopropoxycarbonyloxy) ethyl (+)-(6R,7R)-7-[2-(2-amino-4-thiazolyl)-2-{(Z)methoxyimino}acetamido]-3-methoxymethyl-8-oxo-5-thia-1-azabicyclo [4.2.0]oct-2-ene- 2-carboxylate. Its molecular formula is C 21 H 27 N 5 O 9 S 2 and its structural formula is represented below: The molecular weight of cefpodoxime proxetil is 557.6.
Cefpodoxime proxetil is a prodrug; its active metabolite is cefpodoxime. All doses of cefpodoxime proxetil in this insert are expressed in terms of the active cefpodoxime moiety. The drug is supplied as flavoured granules for oral suspension.
Each 5 mL of cefpodoxime proxetil for oral suspension USP contains cefpodoxime proxetil USP equivalent to 50 mg or 100 mg of cefpodoxime activity after constitution and the following inactive ingredients: lactose monohydrate, corn starch, croscarmellose sodium, ferric oxide yellow, hydroxypropyl cellulose, microcrystalline cellulose and carboxymethyl cellulose sodium, colloidal silicon dioxide, citric acid anhydrous, sodium citrate, sodium benzoate, sucrose, and citron & vanille flavorings. Chemical Structure
💬 Information for Patients ▾
Information for Patients: Patients should be counseled that antibacterial drugs including cefpodoxime proxetil should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When cefpodoxime proxetil is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by cefpodoxime proxetil or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic.
If this occurs, patients should contact their physician as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General: In patients with transient or persistent reduction in urinary output due to renal insufficiency, the total daily dose of cefpodoxime proxetil should be reduced because high and prolonged serum antibiotic concentrations can occur in such individuals following usual doses. Cefpodoxime, like other cephalosporins, should be administered with caution to patients receiving concurrent treatment with potent diuretics. (See DOSAGE AND ADMINISTRATION .) As with other antibiotics, prolonged use of cefpodoxime proxetil may result in overgrowth of non-susceptible organisms.
Repeated evaluation of the patient’s condition is essential. If superinfection occurs during therapy, appropriate measures should be taken. Prescribing cefpodoxime proxetil in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria.
Information for Patients: Patients should be counseled that antibacterial drugs including cefpodoxime proxetil should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When cefpodoxime proxetil is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by cefpodoxime proxetil or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic.
If this occurs, patients should contact their physician as soon as possible. Drug Interactions: Antacids : Concomitant administration of high doses of antacids (sodium bicarbonate and aluminum hydroxide) or H 2 blockers reduces peak plasma levels by 24% to 42% and the extent of absorption by 27% to 32%, respectively. The rate of absorption is not altered by these concomitant medications.
Oral anti-cholinergics (e.g., propantheline) delay peak plasma levels (47% increase in T max ), but do not affect the extent of absorption (AUC). Probenecid : As with other beta-lactam antibiotics, renal excretion of cefpodoxime was inhibited by probenecid and resulted in an approximately 31% increase in AUC and 20% increase in peak cefpodoxime plasma levels. Nephrotoxic drugs : Although nephrotoxicity has not been noted when cefpodoxime proxetil was given alone, close monitoring of renal function is advised when cefpodoxime proxetil is administered concomitantly with compounds of known nephrotoxic potential.
Drug/Laboratory Test Interactions: Cephalosporins, including cefpodoxime proxetil, are known to occasionally induce a positive direct Coombs’ test. Carcinogenesis, Mutagenesis, Impairment of Fertility: Long-term animal carcinogenesis studies of cefpodoxime proxetil have not been performed. Mutagenesis studies of cefpodoxime, including the Ames test both with and without metabolic activation, the chromosome aberration test, the unscheduled DNA synthesis assay, mitotic recombination and gene conversion, the forward gene mutation assay and the in vivo micronucleus test, were all negative.
No untoward effects on fertility or reproduction were noted when 100 mg/kg/day or less (2 times the human dose based on mg/m 2 ) was administered orally to rats. Pregnancy Teratogenic Effects: Pregnancy Category B Cefpodoxime proxetil was neither teratogenic nor embryocidal when administered to rats during organogenesis at doses up to 100 mg/kg/day (2 tim… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers: Cefpodoxime is excreted in human milk. In a study of 3 lactating women, levels of cefpodoxime in human milk were 0%, 2% and 6% of concomitant serum levels at 4 hours following a 200 mg oral dose of cefpodoxime proxetil. At 6 hours post-dosing, levels were 0%, 9% and 16% of concomitant serum levels.
Because of the potential for serious reactions in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
🔬 Clinical Studies ▾
CLINICAL TRIALS Cystitis In two double-blind, 2:1 randomized, comparative trials performed in adults in the United States, cefpodoxime proxetil was compared to other beta-lactam antibiotics. In these studies, the following bacterial eradication rates were obtained at 5 to 9 days after therapy: Pathogen Cefpodoxime Comparator E. coli 200/243 (82%) 99/123 (80%) Other pathogens 34/42 (81%) 23/28 (82%) K. pneumoniae P. mirabilis S. saprophyticus TOTAL 234/285 (82%) 122/151 (81%) In these studies, clinical cure rates and bacterial eradication rates for cefpodoxime proxetil were comparable to the comparator agents; however, the clinical cure rates and bacteriologic eradication rates were lower than those observed with some other classes of approved agents for cystitis.
Acute Otitis Media Studies In controlled studies of acute otitis media performed in the United States, where significant rates of beta-lactamase-producing organisms were found, cefpodoxime proxetil was compared to cefixime. In these studies, using very strict evaluability criteria and microbiologic and clinical response criteria at the 4 to 21 day post-therapy follow-up, the following presumptive bacterial eradication/clinical success outcomes (cured and improved) were obtained. Cefpodoxime Proxetil Cefixime Pathogen 5 mg/kg Q 12 h x 5 d S. pneumoniae 88/122 (72%) 72/124 (58%) H. influenzae 50/76 (66%) 61/81 (75%) M. catarrhalis 22/39 (56%) 23/41 (56%) S. pyogenes 20/25 (80%) 13/23 (57%) Clinical success rate 171/254 (67%) 165/258 (64%) Manufactured for: Northstar Rx LLC Memphis, TN 38141.
Manufactured by: Aurobindo Pharma Limited Chitkul (V) - 502 307, India. M.L.No.: 78/MD/AP/96/F/B/R Revised: 10/2018
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility: Long-term animal carcinogenesis studies of cefpodoxime proxetil have not been performed. Mutagenesis studies of cefpodoxime, including the Ames test both with and without metabolic activation, the chromosome aberration test, the unscheduled DNA synthesis assay, mitotic recombination and gene conversion, the forward gene mutation assay and the in vivo micronucleus test, were all negative. No untoward effects on fertility or reproduction were noted when 100 mg/kg/day or less (2 times the human dose based on mg/m 2 ) was administered orally to rats.
📄 Package Label / Principal Display Panel ▾
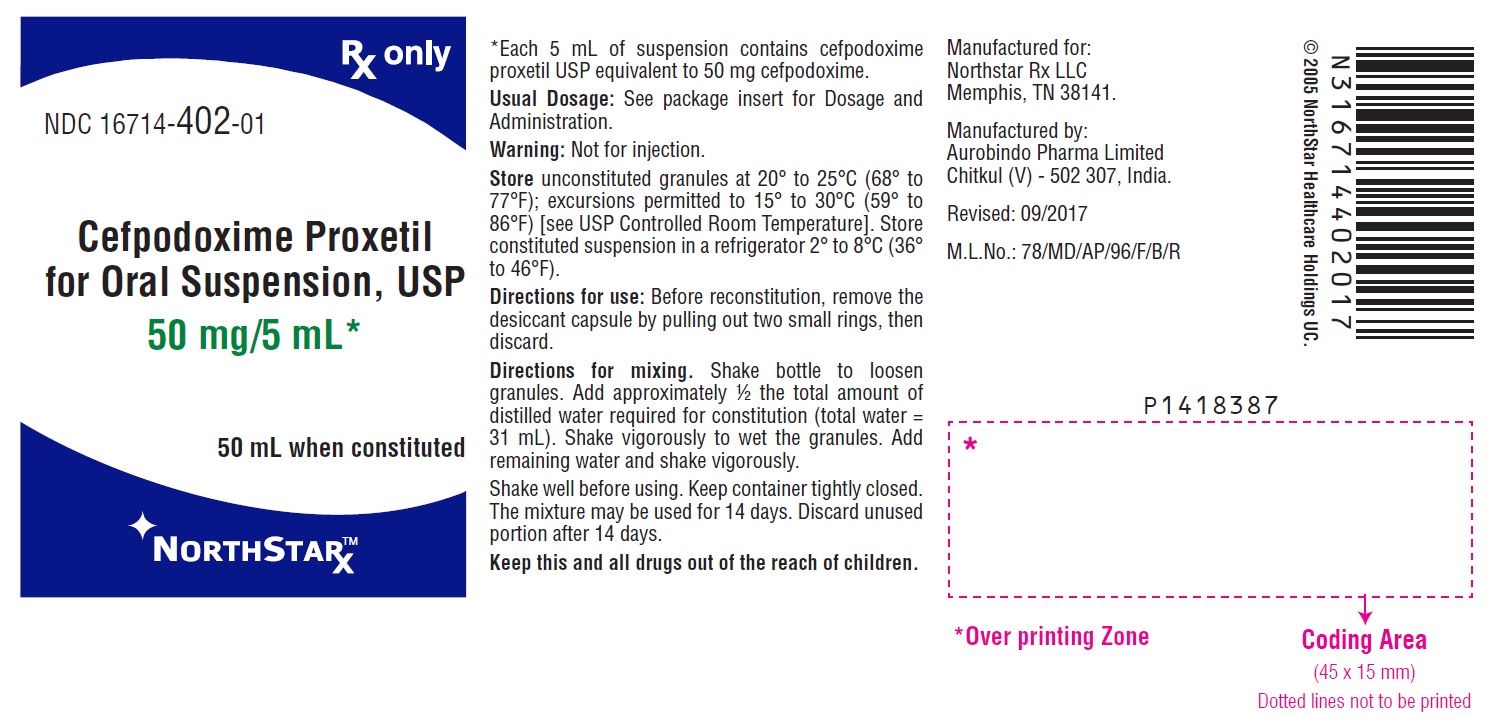
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg/5 mL (50 mL Bottle) R x only NDC 16714-402-01 Cefpodoxime Proxetil for Oral Suspension, USP 50 mg/5 mL* 50 mL when constituted Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg/5 mL (50 mL Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg/5 mL Carton Label R x only NDC 16714-402-01 Cefpodoxime Proxetil for Oral Suspension, USP 50 mg/5 mL* 50 mL when constituted Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 50 mg/5 mL Carton Label
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 100 mg/5 mL (50 mL Bottle) R x only NDC 16714-403-01 Cefpodoxime Proxetil for Oral Suspension, USP 100 mg/5 mL* 50 mL when constituted Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 100 mg/5 mL (50 mL Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 100 mg/5 mL Carton Label R x only NDC 16714-403-01 Cefpodoxime Proxetil for Oral Suspension, USP 100 mg/5 mL* 50 mL when constituted Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 100 mg/5 mL Carton Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |