
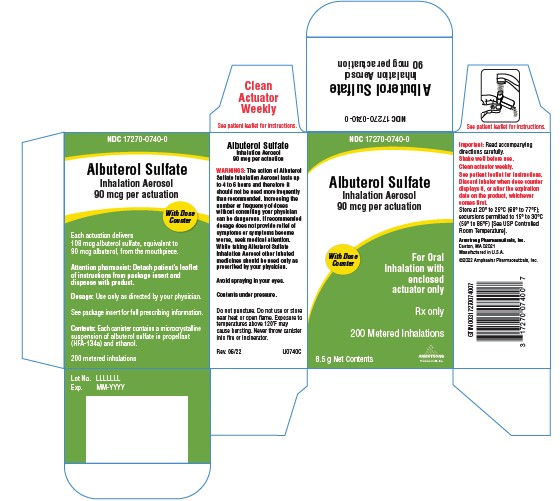
Albuterol Sulfate 90 ug Inhalant
Other active recalls for Albuterol Sulfate (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta2-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Albuterol is used to prevent and treat difficulty breathing, wheezing, shortness of breath, coughing, and chest tightness caused by lung diseases such as asthma and chronic obstructive pulmonary disease (COPD; a group of diseases that affect the lungs and airways). Albuterol inhalation aerosol and powder for oral inhalation is also used to prevent breathing difficulties during exercise. Albuterol inhalation aerosol (Proair HFA, Proventil HFA, Ventolin HFA) is used in adults and children 4 years of age and older. Albuterol powder for oral inhalation (Proair Respiclick) is used in children 12 ye...
Read the full MedlinePlus article ↗- Albuterol quickly relaxes the muscles around your airways, opening them up so you can breathe more easily. Think of it as a fast-acting rescue medicine — you use it when you feel y...
- What exactly does albuterol do, and when should I use it?
- That depends on which inhaler you have. If you have a standard HFA inhaler (like Ventolin HFA or Albuterol Sulfate HFA), shake it well before every puff and prime it with a few tes...
- The most common side effects are pretty mild — a scratchy throat, cough, or upper respiratory irritation, and sometimes a slightly faster heartbeat, shakiness, or headache. Those u...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Albuterol Sulfate — tap one for details:
Albuterol Sulfate may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII DH9E53K1Y8
A synthetic fluorinated hydrocarbon used primarily as a propellant or aerosol dispersant in pressurized inhaler formulations to help deliver medication to the lungs.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.541 | — |
| Medicaid paysCMS SDUD · 12 mo | $3.04 | — |
| Medicare drug plans payPart D · Q2 2026 | $2.82 | — |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Albuterol Sulfate HFA 90 ug 00093-3174-31 | Teva | 1 inhaler | $1.540 | AB2 | Availability likely | — |
| Albuterol Sulfate 90 ugthis 17270-0740-00 | Armstrong | 1 inhaler | $1.540 | AB2 | Availability likely | — |
| albuterol sulfate 90 ug 45802-0088-01 | Padagis | 1 inhaler | $1.540 | AB2 | Availability likely | — |
| Albuterol sulfate 90 ug 68180-0963-01 | Lupin | 1 canister | $1.540 | AB2 | Availability likely | — |
| Albuterol Sulfate Inhalation 90 ug 69238-1291-01 | Amneal | 1 canister | $1.540 | AB2 | Availability likely | — |
| Albuterol Sulfate HFA 90 ug 66993-0019-68 | Prasco | 1 inhaler | $1.825 | AB3 | Availability likely | +18% |
| Albuterol 90 ug 69097-0021-60 | Cipla | 1 inhaler | $1.825 | AB3 | Availability likely | +18% |
| Albuterol Sulfate 90 ug 76282-0679-42 | Exelan | 1 canister | $2.120 | AB1 | Availability likely | +38% |
| Albuterol Sulfate 90 ug 00054-0742-87 | Hikma | 1 canister | $2.120 | AB1 | Availability likely | +38% |
| Albuterol Sulfate 90 ug 60687-0662-91 | American | 1 canister | $2.120 | AB1 | Availability likely | +38% |
| Albuterol Sulfate 90 ug 69097-0142-60 | Cipla | 1 canister | $2.120 | AB1 | Availability likely | +38% |
| Ventolin Hfa 90 ug 00173-0682-20 | GlaxoSmithKline | 1 inhaler | $3.035 | AB3 | Availability likely | +97% |
| ProAir Digihaler 90 ug 59310-0117-20 | Teva | 1 inhaler | $86.326 | — | FDA listed | +5504% |
| Albuterol sulfate 90 ug 50090-5231-00 | A-S | 1 canister | — | AB2 | FDA listed | — |
| Albuterol Sulfate 90 ug 51662-1513-01 | HF | 1 inhaler | — | AB2 | FDA listed | — |
| Albuterol sulfate 90 ug 68071-2300-02 | NuCare | 1 canister | — | AB2 | FDA listed | — |
| Albuterol Sulfate 90 ug 68071-3902-02 | NuCare | 1 inhaler | — | AB2 | FDA listed | — |
| Albuterol Sulfate HFA 90 ug 68071-4940-02 | NuCare | 200 aerosols | — | AB2 | FDA listed | — |
| Albuterol Sulfate 90 ug 68788-4041-02 | Preferred | 1 inhaler | — | AB2 | FDA listed | — |
| Albuterol sulfate 90 ug 68788-8878-02 | Preferred | 1 canister | — | AB2 | FDA listed | — |
| Albuterol sulfate 90 ug 70518-3541-00 | REMEDYREPACK | 1 canister | — | AB2 | FDA listed | — |
| Albuterol Sulfate 90 ug 70518-4496-00 | REMEDYREPACK | 1 inhaler | — | AB2 | FDA listed | — |
| Albuterol Sulfate HFA 90 ug 71205-0211-85 | Proficient | 1 inhaler | — | AB2 | FDA listed | — |
| albuterol sulfate 90 ug 71205-0441-85 | Proficient | 1 inhaler | — | AB2 | FDA listed | — |
| Albuterol sulfate 90 ug 71205-0732-85 | Proficient | 1 canister | — | AB2 | FDA listed | — |
| Albuterol Sulfate HFA 90 ug 76420-0088-01 | Asclemed | 1 inhaler | — | AB2 | FDA listed | — |
| Albuterol sulfate 90 ug 76420-0350-90 | Asclemed | 1 canister | — | AB2 | FDA listed | — |
| Albuterol Sulfate 90 ug 80425-0266-01 | Advanced | 1 canister | — | AB2 | FDA listed | — |
| albuterol sulfate 90 ug 85766-0055-90 | Sportpharm | 1 inhaler | — | AB2 | FDA listed | — |
| Albuterol sulfate 90 ug 85766-0062-90 | Sportpharm | 1 canister | — | AB2 | FDA listed | — |
| albuterol sulfate HFA 90 ug 50090-4137-00 | A-S | 1 inhaler | — | AB3 | FDA listed | — |
| Ventolin Hfa 90 ug 63187-0026-08 | Proficient | 60 aerosols | — | AB3 | FDA listed | — |
| Albuterol Sulfate 90 ug 76420-0531-01 | Asclemed | 200 aerosols | — | AB1 | FDA listed | — |
| Albuterol Sulfate 90 ug 68788-8874-02 | Preferred | 1 canister | — | AB1 | FDA listed | — |
| Ventolin Hfa 90 ug 50090-1158-00 | A-S | 1 inhaler | — | AB3 | FDA listed | — |
| Albuterol Sulfate 90 ug 51662-1267-01 | HF | 1 inhaler | — | AB3 | FDA listed | — |
| Ventolin Hfa 90 ug 68071-1890-06 | NuCare | 60 aerosols | — | AB3 | FDA listed | — |
| Ventolin Hfa 90 ug 70518-1081-00 | REMEDYREPACK | 200 aerosols | — | AB3 | FDA listed | — |
| Ventolin Hfa 90 ug 70518-1237-00 | REMEDYREPACK | 1 inhaler | — | AB3 | FDA listed | — |
| Albuterol Sulfate 90 ug 50090-5735-01 | A-S | 96 canisters | — | AB1 | FDA listed | — |
| Albuterol Sulfate HFA 90 ug 80425-0359-01 | Advanced | 1 inhaler | — | AB3 | FDA listed | — |
| Albuterol Sulfate 90 ug 50090-5179-00 | A-S | 1 canister | — | AB1 | FDA listed | — |
| Ventolin Hfa 90 ug 50090-1159-00 | A-S | 1 inhaler | — | AB3 | FDA listed | — |
| Albuterol Sulfate 90 ug 68788-8787-02 | Preferred | 1 canister | — | AB1 | FDA listed | — |
| Albuterol Sulfate 90 ug 82804-0189-67 | Proficient | 1 canister | — | AB1 | FDA listed | — |
| Ventolin Hfa 90 ug 68071-1670-02 | NuCare | 200 aerosols | — | AB3 | FDA listed | — |
| Albuterol Sulate HFA 90 ug 70518-2072-00 | REMEDYREPACK | 1 inhaler | — | AB3 | FDA listed | — |
| Albuterol Sulfate 90 ug 85766-0020-90 | Sportpharm | 1 canister | — | AB1 | FDA listed | — |
| Albuterol Sulate HFA 90 ug 68071-4777-02 | NuCare | 200 aerosols | — | AB3 | FDA listed | — |
| Albuterol Sulfate 90 ug 85534-0039-00 | HAWAII | 1 canister | — | AB1 | FDA listed | — |
| Albuterol Sulfate 90 ug 68071-5312-06 | NuCare | 1 canister | — | AB1 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 17270-0740-00 You're viewing this | 1 INHALER in 1 CARTON (17270-0740-0) / 200 INHALANT in 1 INHALER | 2024-08-06 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Albuterol Sulfate Inhalation Aerosol is a beta 2 -adrenergic agonist indicated for: Treatment or prevention of bronchospasm in patients 4 years of age and older with reversible obstructive airway disease. ( 1.1 ) Prevention of exercise-induced bronchospasm in patients 4 years of age and older. ( 1.2 )
1.1Bronchospasm Albuterol Sulfate Inhalation Aerosol is indicated for the treatment or prevention of bronchospasm in patients 4 years of age and older with reversible obstructive airway disease.
1.2Exercise-Induced Bronchospasm Albuterol Sulfate Inhalation Aerosol is indicated for the prevention of exercise-induced bronchospasm in patients 4 years of age and older.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For oral inhalation only Treatment or prevention of bronchospasm in adults and children 4 years of age and older: 2 inhalations every 4 to 6 hours. In some patients, one inhalation every 4 hours may be sufficient. ( 2.1 ) Prevention of exercise-induced bronchospasm in adults and children 4 years of age and older: 2 inhalations 15 to 30 minutes before exercise.
( 2.2 ) Priming information: Prime Albuterol Sulfate Inhalation Aerosol before using for the first time, or when the inhaler has not been used for more than 2 weeks. To prime Albuterol Sulfate Inhalation Aerosol, release 3 sprays into the air away from the face. Shake well before each spray.
( 2.3 ) Cleaning information: At least once a week, wash the actuator with warm water, shake off excess, and air dry thoroughly. ( 2.3 ) Albuterol Sulfate Inhalation Aerosol inhaler should be discarded when the dose counter displays 0 or after the expiration date on the product, whichever comes first. ( 2.3 )
2.1Bronchospasm For treatment of acute episodes of bronchospasm or prevention of symptoms associated with bronchospasm, the usual dosage for adults and children 4 years and older is two inhalations repeated every 4 to 6 hours. More frequent administration or a larger number of inhalations is not recommended. In some patients, one inhalation every 4 hours may be sufficient.
2.2Exercise-Induced Bronchospasm The usual dosage for adults and children 4 years of age or older is two inhalations 15 to 30 minutes before exercise.
2.3Administration Information Administer Albuterol Sulfate Inhalation Aerosol by oral inhalation only. Shake well before each spray. To maintain proper use of this product and to prevent medication build-up and blockage, it is important to follow the cleaning directions carefully.
Priming: Prime the inhaler before using for the first time and in cases where the inhaler has not been used for more than 2 weeks by releasing three sprays into the air, away from the face. Cleaning: As with all HFA-containing albuterol inhalers, to maintain proper use of this product and to prevent medication build-up and blockage, it is important to clean the plastic mouthpiece regularly. The inhaler may cease to deliver medication if the plastic actuator mouthpiece is not properly cleaned and dried.
To clean: Wash the plastic mouthpiece with warm running water for 30 seconds, shake off excess water, and air dry thoroughly at least once a week. If the patient has more than one Albuterol Sulfate Inhalation Aerosol inhaler, the patient should wash each one separately to prevent attaching the wrong canister to the wrong plastic actuator. In this way, the patient can be sure to always know the correct number of remaining doses.
Never attach a canister of medication from any other inhaler to the Albuterol Sulfate Inhalation Aerosol actuator and never attach the Albuterol Sulfate Inhalation Aerosol canister to an actuator from any other inhaler. If the mouthpiece becomes blocked, washing the mouthpiece will remove the blockage. If it is necessary to use the inhaler before it is completely dry, shake off excess water, replace canister, spray twice into the air away from face, and take the prescribed dose.
After such use, the mouthpiece should be rewashed and allowed to air dry thoroughly. [see FDA-Approved Patient Labeling ( 17.9 ) ] . Dose Counter: Albuterol Sulfate Inhalation Aerosol has a dose counter attached to the actuator. When the patient receives the inhaler, the number 200 will appear slightly to the right of the viewing window until it has been primed 3 times, at which point the number 200 will be displayed.
The dose counter will count down each time a spray is released. When the dose counter reaches 20, the color of the background will change to red to remind the patient to contact their pharmacist for a refill of medication or consult their physician for a prescription refill. This color will remain when the dose counter reaches 0.
Albuterol Sulfa…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Albuterol Sulfate is an inhalation aerosol. Albuterol Sulfate Inhalation Aerosol is supplied as an 8.5 g/200 actuations pressurized aluminum canister with a green plastic actuator with a dose counter and yellow dust cap each in boxes of one. Each actuation delivers 120 mcg of albuterol sulfate from the canister valve and 108 mcg of albuterol sulfate from the actuator mouthpiece (equivalent to 90 mcg of albuterol base).
Inhalation Aerosol: Each actuation delivers 108 mcg of albuterol sulfate from the actuator mouthpiece (equivalent to 90 mcg of albuterol base). Supplied in 8.5-g canister containing 200 actuations.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Albuterol Sulfate Inhalation Aerosol is contraindicated in patients with a history of hypersensitivity to albuterol and any other Albuterol Sulfate Inhalation Aerosol components. Rare cases of hypersensitivity reactions, including urticaria, angioedema, and rash have been reported after the use of albuterol sulfate [see Warnings and Precautions ( 5.6 ) ] . Hypersensitivity to albuterol and any other Albuterol Sulfate Inhalation Aerosol Components.
⚠️ Warnings and Cautions ▾
5 WARNINGS & PRECAUTIONS Life-threatening paradoxical bronchospasm may occur. Discontinue Albuterol Sulfate Inhalation Aerosol immediately and treat with alternative therapy. ( 5.1 ) Need for more doses of Albuterol Sulfate Inhalation Aerosol than usual may be a sign of deterioration of asthma and requires reevaluation of treatment.
( 5.2 ) Albuterol Sulfate Inhalation Aerosol is not a substitute for corticosteroids. ( 5.3 ) Cardiovascular effects may occur. Use with caution in patients sensitive to sympathomimetic drugs and patients with cardiovascular or convulsive disorders.
( 5.4 , 5.7 ) Excessive use may be fatal. Do not exceed recommended dose. ( 5.5 ) Immediate hypersensitivity reactions may occur.
Discontinue Albuterol Sulfate Inhalation Aerosol immediately. ( 5.6 ) Hypokalemia and changes in blood glucose may occur. ( 5.7 , 5.8 )
5.1Paradoxical Bronchospasm Albuterol Sulfate Inhalation Aerosol can produce paradoxical bronchospasm that may be life threatening. If paradoxical bronchospasm occurs, Albuterol Sulfate Inhalation Aerosol should be discontinued immediately and alternative therapy instituted. It should be recognized that paradoxical bronchospasm, when associated with inhaled formulations, frequently occurs with the first use of a new canister.
5.2Deterioration of Asthma Asthma may deteriorate acutely over a period of hours or chronically over several days or longer. If the patient needs more doses of Albuterol Sulfate Inhalation Aerosol than usual, this may be a marker of destabilization of asthma and requires re-evaluation of the patient and treatment regimen, giving special consideration to the possible need for anti-inflammatory treatment, e.g., corticosteroids.
5.3Use of Anti-inflammatory Agents The use of beta-adrenergic-agonist bronchodilators alone may not be adequate to control asthma in many patients. Early consideration should be given to adding anti-inflammatory agents, e.g., corticosteroids, to the therapeutic regimen.
5.4Cardiovascular Effects Albuterol Sulfate Inhalation Aerosol, like other beta-adrenergic agonists, can produce clinically significant cardiovascular effects in some patients as measured by pulse rate, blood pressure, and/or symptoms. Although such effects are uncommon after administration of Albuterol Sulfate Inhalation Aerosol at recommended doses, if they occur, the drug may need to be discontinued. In addition, beta-agonists have been reported to produce ECG changes, such as flattening of the T wave, prolongation of the QTc interval, and ST segment depression.
The clinical significance of these findings is unknown. Therefore, Albuterol Sulfate Inhalation Aerosol, like all sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias, and hypertension.
5.5Do Not Exceed Recommended Dose Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs in patients with asthma. The exact cause of death is unknown, but cardiac arrest following an unexpected development of a severe acute asthmatic crisis and subsequent hypoxia is suspected.
5.6Immediate Hypersensitivity Reactions Immediate hypersensitivity reactions may occur after administration of albuterol sulfate, as demonstrated by rare cases of urticaria, angioedema, rash, bronchospasm, anaphylaxis, and oropharyngeal edema. The potential for hypersensitivity must be considered in the clinical evaluation of patients who experience immediate hypersensitivity reactions while receiving Albuterol Sulfate Inhalation Aerosol.
5.7Coexisting Conditions Albuterol Sulfate Inhalation Aerosol, like all sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias, and hypertension; in patients with convulsive disorders, hyperthyroidism, or diabetes mellitus; and in patients who are unusually responsive to sympathomimetic amines. Cl…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Use of Albuterol Sulfate may be associated with the following: Paradoxical bronchospasm [see Warnings and Precautions ( 5.1 ) ] Cardiovascular Effects [see Warnings and Precautions ( 5.4 ) ] Immediate hypersensitivity reactions [see Warnings and Precautions ( 5.6 ) ] Hypokalemia [see Warnings and Precautions ( 5.8 ) ] Most common adverse reactions (≥3.0% and >placebo) are headache, tachycardia, pain, dizziness, pharyngitis, and rhinitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Armstrong Pharmaceuticals, Inc. at 1-800-423-4136 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience A total of 1090 subjects were treated with Albuterol Sulfate Inhalation Aerosol, or with the same formulation of albuterol as in Albuterol Sulfate Inhalation Aerosol, during the worldwide clinical development program. Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adult and Adolescents 12 Years of Age and Older: The adverse reaction information presented in the table below concerning Albuterol Sulfate Inhalation Aerosol is derived from a 6-week, blinded study which compared Albuterol Sulfate Inhalation Aerosol (180 mcg four times daily) with a double-blinded matched placebo Inhalation Aerosol and an evaluator-blinded marketed active comparator HFA-134a albuterol inhaler in 172 asthmatic patients 12 to 76 years of age.
The table lists the incidence of all adverse events (whether considered by the investigator drug related or unrelated to drug) from this study which occurred at a rate of 3% or greater in the Albuterol Sulfate Inhalation Aerosol treatment group and more frequently in the Albuterol Sulfate Inhalation Aerosol treatment group than in the matched placebo group. Overall, the incidence and nature of the adverse events reported for Albuterol Sulfate Inhalation Aerosol and the marketed active comparator HFA-134a albuterol inhaler were comparable.
Adverse Experience Incidences (% of Patients) in a Six-Week Clinical Trial This table includes all adverse events (whether considered by the investigator drug related or unrelated to drug) which occurred at an incidence rate of at least 3.0% in the Albuterol Sulfate HFA Inhalation Aerosol group and more frequently in the Albuterol Sulfate HFA Inhalation Aerosol group than in the placebo HFA Inhalation Aerosol group. Body System/ Adverse Event (as Preferred Term) Albuterol Sulfate HFA Inhalation Aerosol (N = 58) Marketed active comparator HFA-134a albuterol inhaler (N = 56) Matched Placebo HFA-134a Inhalation Aerosol (N = 58) Body as a whole Headache 7 5 2 Cardiovascular Tachycardia 3 2 0 Musculoskeletal Pain 3 0 0 Nervous System Dizziness 3 0 0 Respiratory System Pharyngitis Rhinitis 14 5 7 4 9 2 Adverse events reported by less than 3% of the patients receiving Albuterol Sulfate Inhalation Aerosol but by a greater proportion of Albuterol Sulfate Inhalation Aerosol patients than the matched placebo patients, which have the potential to be related to Albuterol Sulfate Inhalation Aerosol, included chest pain, infection, diarrhea, glossitis, accidental injury (nervous system), anxiety, dyspnea, ear disorder, ear pain, and urinary tract infection.
In small cumulative dose studies, tremor, nervousness, and headache were the most frequently occurring adverse events. Pediatric Patients 4 to 11 Years of Age: Adverse events reported in a 3-week pediatric clinical trial comparing the same formulation of albuterol as in Albuterol Sulfate Inhalation Aerosol (180 mcg albuterol four times daily) to a matching placebo HFA inhalation aerosol occurred at a low incidence rate (no greater than 2% in the active treatment group) and were similar to those seen in adult and adolescent trials.
6.2 Postmarketing Experience The following adverse reactions…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Other short-acting sympathomimetic aerosol bronchodilators should not be used concomitantly with Albuterol Sulfate Inhalation Aerosol. If additional adrenergic drugs are to be administered by any route, they should be used with caution to avoid deleterious cardiovascular effects. Other short-acting sympathomimetic aerosol bronchodilators and adrenergic drugs: May potentiate effect.
( 7 ) Beta-blockers: May decrease effectiveness of Albuterol Sulfate and produce severe bronchospasm. Patients with asthma should not normally be treated with beta-blockers. ( 7.1 ) Diuretics, or non-potassium sparing diuretics: May potentiate hypokalemia or ECG changes.
Consider monitoring potassium levels. ( 7.2 ) Digoxin: May decrease serum digoxin levels. Consider monitoring digoxin levels.
( 7.3 ) Monoamine oxidase (MAO) inhibitors and tricyclic antidepressants: May potentiate effect of albuterol on the cardiovascular system. Consider alternative therapy in patients taking MAOs or tricyclic antidepressants. ( 7.4 )
7.1Beta-Blockers Beta-adrenergic-receptor blocking agents not only block the pulmonary effect of beta-agonists, such as Albuterol Sulfate Inhalation Aerosol, but may produce severe bronchospasm in asthmatic patients. Therefore, patients with asthma should not normally be treated with beta-blockers. However, under certain circumstances, e.g., as prophylaxis after myocardial infarction, there may be no acceptable alternatives to the use of beta-adrenergic-blocking agents in patients with asthma.
In this setting, consider cardioselective beta-blockers, although they should be administered with caution.
7.2Diuretics The ECG changes and/or hypokalemia which may result from the administration of non-potassium sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the recommended dose of the beta-agonist is exceeded. Although the clinical significance of these effects is not known, caution is advised in the coadministration of beta-agonists with non-potassium sparing diuretics. Consider monitoring potassium levels.
7.3Digoxin Mean decreases of 16% and 22% in serum digoxin levels were demonstrated after single dose intravenous and oral administration of albuterol, respectively, to normal volunteers who had received digoxin for 10 days. The clinical significance of these findings for patients with obstructive airway disease who are receiving albuterol and digoxin on a chronic basis is unclear. Nevertheless, it would be prudent to carefully evaluate the serum digoxin levels in patients who are currently receiving digoxin and Albuterol Sulfate Inhalation Aerosol.
7.4Monoamine Oxidase Inhibitors or Tricyclic Antidepressants Albuterol Sulfate Inhalation Aerosol should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants, or within 2 weeks of discontinuation of such agents, because the action of albuterol on the cardiovascular system may be potentiated. Consider alternative therapy in patients taking MAO inhibitors or tricyclic antidepressants.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to asthma medications during pregnancy. For more information, contact the Mothers To Baby Pregnancy Studies conducted by the Organization of Teratology Information Specialists at 1-877-311-8972 or visit http://mothertobaby.org/pregnancy-studies/. Risk Summary There are no randomized clinical studies of use of albuterol during pregnancy.
Available data from published epidemiological studies and postmarketing case reports of pregnancy outcomes following inhaled albuterol use do not consistently demonstrate a risk of major birth defects or miscarriage. There are clinical considerations with use of albuterol in pregnant women [see Clinical Considerations ] . In animal reproduction studies, when albuterol sulfate was administered subcutaneously to pregnant mice there was evidence of cleft palate at less than and up to 9 times the maximum recommended human daily inhalation dose (MRHDID) [see Data ].
The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with poorly or moderately controlled asthma, there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored and medication adjusted as necessary to maintain optimal control. Labor or Delivery Because of the potential for beta-agonist interference with uterine contractility, use of Albuterol Sulfate Inhalation Aerosol for relief of bronchospasm during labor should be restricted to those patients in whom the benefits clearly outweigh the risk. Albuterol Sulfate Inhalation Aerosol has not been approved for the management of pre-term labor.
Serious adverse reactions, including pulmonary edema, have been reported during or following treatment of premature labor with beta 2 -agonists, including albuterol. Data Animal Data In a mouse reproduction study, subcutaneously administered albuterol sulfate produced cleft palate formation in 5 of 111 (4.5%) fetuses at an exposure nine-tenths of the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 0.25 mg/kg) and in 10 of 108 (9.3%) fetuses at approximately 9 times the MRHDID (on a mg/m 2 basis at a maternal dose of 2.5 mg/kg).
Similar effects were not observed at approximately one-eleventh the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 0.025 mg/kg). Cleft palate also occurred in 22 of 72 (30.5%) fetuses from females treated subcutaneously with isoproterenol (positive control). In a rabbit reproduction study, orally administered albuterol sulfate induced cranioschisis in 7 of 19 fetuses (37%) at approximately 750 times the MRHDID (on a mg/m 2 basis at a maternal dose of 50 mg/kg).
In a rat reproduction study, an albuterol sulfate/HFA-134a formulation administered by inhalation did not produce any teratogenic effects at exposures approximately 80 times the MRHDID (on a mg/m 2 basis at a maternal dose of 10.5 mg/kg). A study in which pregnant rats were dosed with radiolabeled albuterol sulfate demonstrated that drug-related material is transferred from the maternal circulation to the fetus.
8.2Lactation Risk Summary There are no available data on the presence of albuterol in human milk, the effects on the breastfed child, or the effects on milk production. However, plasma levels of albuterol after inhaled therapeutic doses are low in humans, and if present in breast milk, albuterol has a low oral bioavailability [see Clinical Pharmacology ( 12.2 ) ] . The developmental and health benefits of breastfeeding should be considered along with the mothe…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to asthma medications during pregnancy. For more information, contact the Mothers To Baby Pregnancy Studies conducted by the Organization of Teratology Information Specialists at 1-877-311-8972 or visit http://mothertobaby.org/pregnancy-studies/. Risk Summary There are no randomized clinical studies of use of albuterol during pregnancy.
Available data from published epidemiological studies and postmarketing case reports of pregnancy outcomes following inhaled albuterol use do not consistently demonstrate a risk of major birth defects or miscarriage. There are clinical considerations with use of albuterol in pregnant women [see Clinical Considerations ] . In animal reproduction studies, when albuterol sulfate was administered subcutaneously to pregnant mice there was evidence of cleft palate at less than and up to 9 times the maximum recommended human daily inhalation dose (MRHDID) [see Data ].
The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk In women with poorly or moderately controlled asthma, there is an increased risk of preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate.
Pregnant women should be closely monitored and medication adjusted as necessary to maintain optimal control. Labor or Delivery Because of the potential for beta-agonist interference with uterine contractility, use of Albuterol Sulfate Inhalation Aerosol for relief of bronchospasm during labor should be restricted to those patients in whom the benefits clearly outweigh the risk. Albuterol Sulfate Inhalation Aerosol has not been approved for the management of pre-term labor.
Serious adverse reactions, including pulmonary edema, have been reported during or following treatment of premature labor with beta 2 -agonists, including albuterol. Data Animal Data In a mouse reproduction study, subcutaneously administered albuterol sulfate produced cleft palate formation in 5 of 111 (4.5%) fetuses at an exposure nine-tenths of the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 0.25 mg/kg) and in 10 of 108 (9.3%) fetuses at approximately 9 times the MRHDID (on a mg/m 2 basis at a maternal dose of 2.5 mg/kg).
Similar effects were not observed at approximately one-eleventh the MRHDID for adults (on a mg/m 2 basis at a maternal dose of 0.025 mg/kg). Cleft palate also occurred in 22 of 72 (30.5%) fetuses from females treated subcutaneously with isoproterenol (positive control). In a rabbit reproduction study, orally administered albuterol sulfate induced cranioschisis in 7 of 19 fetuses (37%) at approximately 750 times the MRHDID (on a mg/m 2 basis at a maternal dose of 50 mg/kg).
In a rat reproduction study, an albuterol sulfate/HFA-134a formulation administered by inhalation did not produce any teratogenic effects at exposures approximately 80 times the MRHDID (on a mg/m 2 basis at a maternal dose of 10.5 mg/kg). A study in which pregnant rats were dosed with radiolabeled albuterol sulfate demonstrated that drug-related material is transferred from the maternal circulation to the fetus.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Albuterol Sulfate Inhalation Aerosol for the treatment or prevention of bronchospasm in children 12 years of age and older with reversible obstructive airway disease is based on one 6-week clinical trial in 116 patients 12 years of age and older with asthma comparing doses of 180 mcg four times daily with placebo, and one single-dose crossover study comparing doses of 90, 180, and 270 mcg with placebo in 58 patients [see Clinical Studies ( 14.1 ) ]. The safety and effectiveness of Albuterol Sulfate Inhalation Aerosol for treatment of exercise-induced bronchospasm in children 12 years of age and older is based on one single-dose crossover study in 24 adults and adolescents with exercise-induced bronchospasm comparing doses of 180 mcg with placebo [see Clinical Studies ( 14.2 ) ].
The safety of Albuterol Sulfate Inhalation Aerosol in children 4 to 11 years of age is based on one 3-week clinical trial in 50 patients 4 to 11 years of age with asthma using the same formulation of albuterol as in Albuterol Sulfate Inhalation Aerosol comparing doses of 180 mcg four times daily with placebo. The effectiveness of Albuterol Sulfate Inhalation Aerosol in children 4 to 11 years of age is extrapolated from clinical trials in patients 12 years of age and older with asthma and exercise-induced bronchospasm, based on data from a single-dose study comparing the bronchodilatory effect of Albuterol Sulfate 90 mcg and 180 mcg with placebo in 55 patients with asthma and a 3-week clinical trial using the same formulation of albuterol as in Albuterol Sulfate Inhalation Aerosol in 95 asthmatic children 4 to 11 years of age comparing a dose of 180 mcg albuterol four times daily with placebo [see Clinical Studies ( 14.1 ) ].
The safety and effectiveness of Albuterol Sulfate Inhalation Aerosol in pediatric patients below the age of 4 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Albuterol Sulfate Inhalation Aerosol did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. Other reported clinical experience has not identified differences in responses between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Warnings and Precautions ( 5.4 , 5.7 ) ].
All beta 2 -adrenergic agonists, including albuterol, are known to be substantially excreted by the kidney, and the risk of toxic reactions may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE The expected symptoms with overdosage are those of excessive beta-adrenergic stimulation and/or occurrence or exaggeration of any of the symptoms listed under ADVERSE REACTIONS, e.g., seizures, angina, hypertension or hypotension, tachycardia with rates up to 200 beats per minute, arrhythmias, nervousness, headache, tremor, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, and insomnia. Hypokalemia may also occur. As with all sympathomimetic medications, cardiac arrest and even death may be associated with abuse of Albuterol Sulfate Inhalation Aerosol.
Treatment consists of discontinuation of Albuterol Sulfate Inhalation Aerosol together with appropriate symptomatic therapy. The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medication can produce bronchospasm. There is insufficient evidence to determine if dialysis is beneficial for overdosage of Albuterol Sulfate Inhalation Aerosol.
The oral median lethal dose of albuterol sulfate in mice is greater than 2,000 mg/kg (approximately 6,800 times the maximum recommended daily inhalation dose for adults on a mg/m 2 basis and approximately 3,200 times the maximum recommended daily inhalation dose for children on a mg/m 2 basis). In mature rats, the subcutaneous median lethal dose of albuterol sulfate is approximately 450 mg/kg (approximately 3,000 times the maximum recommended daily inhalation dose for adults on a mg/m 2 basis and approximately 1,400 times the maximum recommended daily inhalation dose for children on a mg/m 2 basis).
In young rats, the subcutaneous median lethal dose is approximately 2,000 mg/kg (approximately 14,000 times the maximum recommended daily inhalation dose for adults on a mg/m 2 basis and approximately 6,400 times the maximum recommended daily inhalation dose for children on a mg/m 2 basis). The inhalation median lethal dose has not been determined in animals.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Albuterol sulfate is a beta 2 -adrenergic agonist. The pharmacologic effects of albuterol sulfate are attributable to activation of beta 2 -adrenergic receptors on airway smooth muscle. Activation of beta 2 -adrenergic receptors leads to the activation of adenylcyclase and to an increase in the intracellular concentration of cyclic-3’, 5’-adenosine monophosphate (cyclic AMP).
This increase of cyclic AMP is associated with the activation of protein kinase A, which in turn inhibits the phosphorylation of myosin and lowers intracellular ionic calcium concentrations, resulting in muscle relaxation. Albuterol relaxes the smooth muscle of all airways, from the trachea to the terminal bronchioles. Albuterol acts as a functional antagonist to relax the airway irrespective of the spasmogen involved, thus protecting against all bronchoconstrictor challenges.
Increased cyclic AMP concentrations are also associated with the inhibition of release of mediators from mast cells in the airway. While it is recognized that beta 2 -adrenergic receptors are the predominant receptors on bronchial smooth muscle, data indicate that there are beta-receptors in the human heart, 10% to 50% of which are cardiac beta 2 -adrenergic receptors. The precise function of these receptors has not been established [see Warnings and Precautions ( 5.4 ) ].
Albuterol has been shown in most controlled clinical trials to have more effect on the respiratory tract, in the form of bronchial smooth muscle relaxation, than isoproterenol at comparable doses while producing fewer cardiovascular effects. However, inhaled albuterol, like other beta-adrenergic agonist drugs, can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms, and/or electrocardiographic changes [see Warnings and Precautions ( 5.4 ) ] .
12.2Pharmacokinetics The systemic levels of albuterol are low after inhalation of recommended doses. In a crossover study conducted in healthy male and female volunteers, high cumulative doses of Albuterol Sulfate Inhalation Aerosol (1,080 mcg of albuterol base administered over one hour) yielded mean peak plasma concentrations (C max ) and systemic exposure (AUC inf ) of approximately 4,100 pg/mL and 28,426 pg/mL*hr, respectively compared to approximately 3,900 pg/mL and 28,395 pg/mL*hr, respectively following the same dose of an active HFA-134a albuterol inhaler comparator.
The terminal plasma half-life of albuterol delivered by Albuterol Sulfate Inhalation Aerosol was approximately 6 hours. Comparison of the pharmacokinetic parameters demonstrated no differences between the products. The pharmacokinetic profile of Albuterol Sulfate Inhalation Aerosol was evaluated in a two-way cross-over study in 11 healthy pediatric volunteers, 4 to 11 years of age.
A single dose administration of Albuterol Sulfate Inhalation Aerosol (180 mcg albuterol base) yielded a least square mean (SE) C max and AUC 0-∞ of 1,100 (1.18) pg/mL and 5,120 (1.15) pg/mL*hr, respectively. The least square mean (SE) terminal plasma half-life of albuterol delivered by Albuterol Sulfate Inhalation Aerosol was 166 (7.8) minutes. Metabolism and Elimination: Information available in the published literature suggests that the primary enzyme responsible for the metabolism of albuterol in humans is SULTIA3 (sulfotransferase).
When racemic albuterol was administered either intravenously or via inhalation after oral charcoal administration, there was a 3- to 4-fold difference in the area under the concentration-time curves between the (R)- and (S)-albuterol enantiomers, with (S)-albuterol concentrations being consistently higher. However, without charcoal pretreatment, after either oral or inhalation administration the differences were 8- to 24-fold, suggesting that the (R)-albuterol is preferentially metabolized in the gastrointestinal tract, presumably by SULTIA3.
The primary route of elimination of albut…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Albuterol sulfate is a beta 2 -adrenergic agonist. The pharmacologic effects of albuterol sulfate are attributable to activation of beta 2 -adrenergic receptors on airway smooth muscle. Activation of beta 2 -adrenergic receptors leads to the activation of adenylcyclase and to an increase in the intracellular concentration of cyclic-3’, 5’-adenosine monophosphate (cyclic AMP).
This increase of cyclic AMP is associated with the activation of protein kinase A, which in turn inhibits the phosphorylation of myosin and lowers intracellular ionic calcium concentrations, resulting in muscle relaxation. Albuterol relaxes the smooth muscle of all airways, from the trachea to the terminal bronchioles. Albuterol acts as a functional antagonist to relax the airway irrespective of the spasmogen involved, thus protecting against all bronchoconstrictor challenges.
Increased cyclic AMP concentrations are also associated with the inhibition of release of mediators from mast cells in the airway. While it is recognized that beta 2 -adrenergic receptors are the predominant receptors on bronchial smooth muscle, data indicate that there are beta-receptors in the human heart, 10% to 50% of which are cardiac beta 2 -adrenergic receptors. The precise function of these receptors has not been established [see Warnings and Precautions ( 5.4 ) ].
Albuterol has been shown in most controlled clinical trials to have more effect on the respiratory tract, in the form of bronchial smooth muscle relaxation, than isoproterenol at comparable doses while producing fewer cardiovascular effects. However, inhaled albuterol, like other beta-adrenergic agonist drugs, can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms, and/or electrocardiographic changes [see Warnings and Precautions ( 5.4 ) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE & HANDLING Albuterol Sulfate Inhalation Aerosol (albuterol sulfate) is supplied as a pressurized aluminum canister with a green plastic actuator with a dose counter and yellow dust cap each in boxes of one. Each canister contains 8.5 g of the formulation and provides 200 actuations (NDC 17270- 0740-0). Each actuation delivers 120 mcg of albuterol sulfate from the canister valve and 108 mcg of albuterol sulfate from the actuator mouthpiece (equivalent to 90 mcg of albuterol base).
SHAKE WELL BEFORE USE. Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F)[See USP Controlled Room Temperature]. Contents under pressure.
Do not puncture or incinerate. Protect from freezing temperatures and prolonged exposure to direct sunlight. Exposure to temperatures above 120°F may cause bursting.
For best results, canister should be at room temperature before use. Avoid spraying in eyes. Keep out of reach of children.
See FDA-Approved Patient Labeling ( 17.9 ) for priming and cleaning instructions. The green actuator supplied with Albuterol Sulfate Inhalation Aerosol should not be used with the canister from any other inhalation aerosol products. The Albuterol Sulfate Inhalation Aerosol canister should not be used with the actuator from any other inhalation aerosol products.
Albuterol Sulfate inhaler has a dose counter attached to the actuator. Patients should never try to alter the numbers for the dose counter or tamper with the pin mechanism inside the actuator. Discard the Albuterol Sulfate inhaler when the counter displays 0 or after the expiration date on the product, whichever comes first.
The labeled amount of medication in each actuation cannot be assured after the counter displays 0, even though the canister is not completely empty and will continue to operate. Never immerse the canister into water to determine how full the canister is (“float test”). Albuterol Sulfate Inhalation Aerosol does not contain chlorofluorocarbons (CFCs) as the propellant.
📋 Description ▾
11 DESCRIPTION The active ingredient of Albuterol Sulfate Inhalation Aerosol is albuterol sulfate, a racemic salt, of albuterol. Albuterol sulfate has the chemical name α 1 -[( tert -butylamino) methyl]-4-hydroxy- m -xylene-α,α’-diol sulfate (2:1)(salt), and has the following chemical structure: The molecular weight of albuterol sulfate is 576.7, and the empirical formula is (C 13 H 21 NO 3 ) 2 •H 2 SO 4 . Albuterol sulfate is a white to off-white crystalline powder.
It is soluble in water and slightly soluble in ethanol. Albuterol sulfate is the official generic name in the United States, and salbutamol sulfate is the World Health Organization recommended generic name. Albuterol Sulfate Inhalation Aerosol is a pressurized metered-dose aerosol unit with a dose counter.
Albuterol Sulfate is for oral inhalation only. It contains a microcrystalline suspension of albuterol sulfate in propellant HFA-134a (1, 1, 1, 2-tetrafluoroethane) and ethanol. Prime the inhaler before using for the first time and in cases where the inhaler has not been used for more than 2 weeks by releasing three sprays into the air, away from the face.
After priming, each actuation delivers 108 mcg albuterol sulfate, from the actuator mouthpiece (equivalent to 90 mcg of albuterol base). Each canister provides 200 actuations (inhalations). This product does not contain chlorofluorocarbons (CFCs) as the propellant. structure