
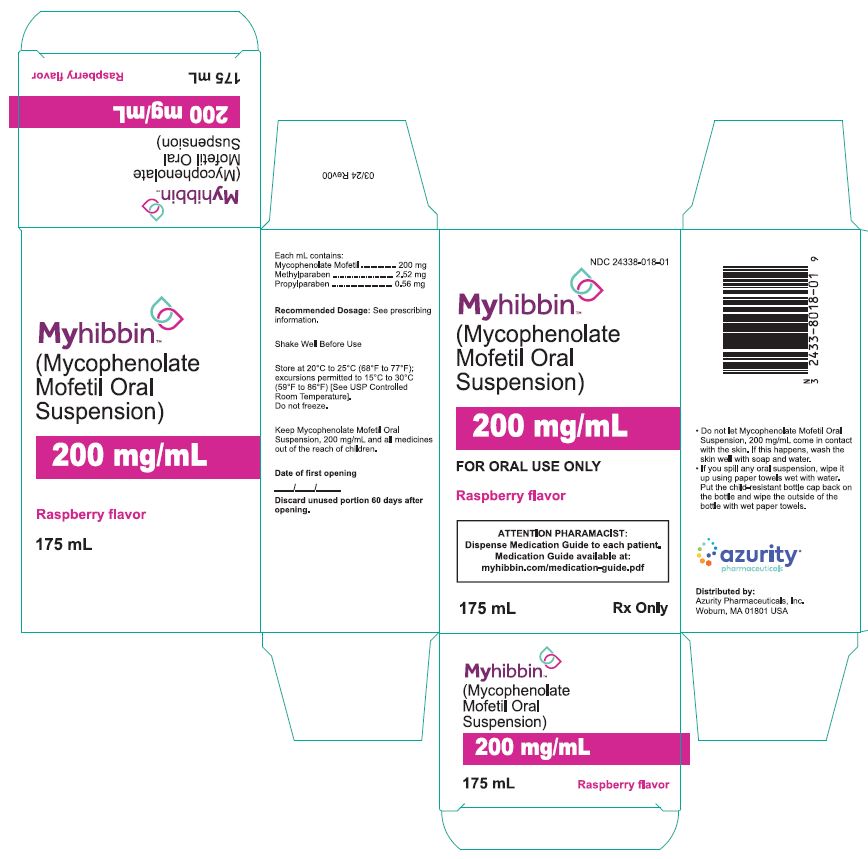
MYHIBBIN MYCOPHENOLATE MOFETIL 200 mg/mL Suspension — NDC 24338-018-01 (Billing 24338-0018-01)
This is a package of MYHIBBIN MYCOPHENOLATE MOFETIL 200 mg/mL Suspension from Azurity Pharmaceuticals, Inc., marketed since Jun 2024 and currently FDA-listed. It is this product's only package size.
Other active recalls for Mycophenolate Mofetil (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 086051
- GCN: 55684
- HICL (First Databank): 010012
- AHFS class code: 90:28.08.92
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Mycophenolate is used to prevent transplant organ rejection (attack of the new organ by the immune system) in people who have received kidney, heart, or liver transplants. Mycophenolate is in a class of medications called immunosuppressive agents. It works by weakening the body's immune system so it will not attack and reject the transplanted organ.
Read the full MedlinePlus article ↗- It helps keep your body from rejecting a transplanted kidney, heart or liver. You take it together with other immunosuppressant medicines. It works by calming the immune cells that...
- It's usually taken twice a day, by mouth as a capsule, tablet or liquid, or through an IV in the hospital. Follow your prescriber's directions and your label. Don't switch it with...
- Diarrhea, nausea, vomiting and stomach pain are common. Call your doctor if you have a fever, chills or other signs of infection, unusual bruising or bleeding, black stools, severe...
- What side effects are normal, and when should I call?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mycophenolate Mofetil — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $4.35 | $762.04 / 175 ml |
| Medicare drug plans payPart D · Q2 2026 | $4.35 | $761.97 / 175 ml |
| Medicare Part B allowsASP · J7514 | $2.296 / J7514 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 24338-0018-01 You're viewing this Main listing | 1 BOTTLE, PLASTIC in 1 CARTON / 175 mL in 1 BOTTLE, PLASTIC | 2024-06-10 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mycophenolate Mofetil 200 mg/mL 00527-5160-82 | Lannett | 1 bottle | $0.982 | AB | Availability likely | — |
| Mycophenolate Mofetil 200 mg/mL 23155-0848-51 | Heritage | 1 bottle | $0.982 | AB | Availability likely | — |
| Mycophenolate Mofetil 200 mg/mL 59651-0646-26 | Aurobindo | 1 bottle | $0.982 | AB | Availability likely | — |
| Mycophenolate Mofetil 200 mg/mL 66689-0307-08 | VistaPharm, | 1 bottle | $0.982 | AB | Availability likely | — |
| Mycophenolate mofetil 200 mg/mL 67877-0230-22 | Ascend | 1 bottle | $0.982 | AB | Availability likely | — |
| Mycophenolate Mofetil 200 mg/mL 69238-1595-02 | Amneal | 1 bottle | $0.982 | AB | Availability likely | — |
| Mycophenolate Mofetil 200 mg/mL 72603-0751-01 | NorthStar | 1 bottle | $0.982 | AB | Availability likely | — |
| CellCept 200 mg/mL 00004-0261-29 | Genentech, | 1 bottle | $8.314 | AB | Availability likely | — |
| Myhibbin 200 mg/mLthis 24338-0018-01 | Azurity | 1 bottle | — | — | FDA listed | — |
| Mycophenolate Mofetil 200 mg/mL 60219-1595-02 | Amneal | 1 bottle | — | AB | FDA listed | — |
| Mycophenolate Mofetil 200 mg/mL 70752-0294-60 | QUAGEN | 1 bottle | — | AB | FDA listed | — |
| Mycophenolate Mofetil 200 mg/mL 64380-0899-00 | Strides | 1 bottle | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12194143 ↗ | Method of use | U-1752 | Aug 16, 2039 |
| US 12097285 ↗ | Method of use | U-1752 | Aug 16, 2039 |
| US 12226526 ↗ | Method of use | U-1752 | Aug 16, 2039 |
| US 11931455 ↗ | Method of use | U-1752 | Aug 16, 2039 |
| US 12097284 ↗ | Drug product | — | Aug 16, 2039 |
Is there a generic version of MYHIBBIN 200 MG/ML SUSPENSION?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII GR686LBA74
Sodium phosphate, dibasic is a salt derived from phosphoric acid. It acts as a buffer to help maintain the medicine's pH balance and may serve as a binder or filler in tablets and capsules.
-
UNII 3980JIH2SW
A salt form of phosphoric acid that acts as a buffer and pH adjuster in medicines. It helps keep the product at the correct acidity level for stability and effectiveness.
-
UNII 8KW3E207O2
A liquid sweetener made from sorbitol, a sugar alcohol derived from glucose. It sweetens the medicine and also acts as a humectant to help retain moisture and improve texture in liquid formulations.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYOFETAL TOXICITY, MALIGNANCIES, and SERIOUS INFECTIONS Use during pregnancy is associated with increased risks of first trimester pregnancy loss and congenital malformations. Avoid if safer treatment options are available. Females of reproductive potential must be counseled regarding pregnancy prevention and planning [see Warnings and Precautions ( 5.1 ), Use in Special Populations ( 8.1 , 8.3 )] .
Increased risk of development of lymphoma and other malignancies, particularly of the skin [see Warnings and Precautions ( 5.2 )] . Increased susceptibility to bacterial, viral, fungal and protozoal infections, including opportunistic infections and viral reactivation of hepatitis B and C, which may lead to hospitalizations and fatal outcomes [see Warnings and Precautions ( 5.3 )] . WARNING: EMBRYOFETAL TOXICITY, MALIGNANCIES and SERIOUS INFECTIONS See full prescribing information for complete boxed warning Use during pregnancy is associated with increased risks of first trimester pregnancy loss and congenital malformations.
Avoid if safer treatment options are available. Females of reproductive potential must be counseled regarding pregnancy prevention and planning [see Warnings and Precautions (5.1) ]. Increased risk of development of lymphoma and other malignancies, particularly of the skin [see Warnings and Precautions (5.2) ] .
Increased susceptibility to infections, including opportunistic infections and severe infections with fatal outcomes [see Warnings and Precautions (5.3) ].
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE MYHIBBIN is indicated for the prophylaxis of organ rejection, in adult and pediatric recipients 3 months of age and older of allogeneic kidney [see Clinical Studies ( 14.1 )], heart [see Clinical Studies ( 14.2 )] or liver transplants [see Clinical Studies ( 14.3 )] , in combination with other immunosuppressants. MYHIBBIN is an antimetabolite immunosuppressant indicated for the prophylaxis of organ rejection in adult and pediatric recipients 3 months of age and older of allogeneic kidney, heart or liver transplants, in combination with other immunosuppressants.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION ADULTS DOSAGE Kidney Transplant 1 g orally twice daily ( 2.2 ) Heart Transplant 1.5 g orally twice daily ( 2.3 ) Liver Transplant 1.5 g orally twice daily ( 2.4 ) PEDIATRICS Kidney Transplant 600 mg/m 2 orally twice daily, up to maximum of 2 g daily ( 2.2 ) Heart Transplant 600 mg/m 2 orally twice daily (starting dose) up to a maximum of 900 mg/m 2 twice daily (maximum daily dose of 3 g or 15 mL of oral suspension) ( 2.3 ) Liver Transplant 600 mg/m 2 orally twice daily (starting dose) up to a maximum of 900 mg/m 2 twice daily (maximum daily dose of 3 g or 15 mL of oral suspension) ( 2.4 ) Reduce or interrupt dosing in the event of neutropenia.
( 2.5 ) See full prescribing information (FPI) for: dosage modifications for renal impairment and neutropenia ( 2.5 )
2.1Important Administration Instructions MYHIBBIN should not be used without the supervision of a physician with experience in immunosuppressive therapy. MYHIBBIN should not be used interchangeably with mycophenolic acid delayed-release tablets without supervision of a physician with experience in immunosuppressive therapy because the rates of absorption following the administration of MYHIBBIN and mycophenolic acid delayed-release tablets are not equivalent. Patients should avoid contact of the skin or mucous membranes with MYHIBBIN.
If such contact occurs, they must wash the area of contact thoroughly with soap and water. In case of ocular contact, rinse eyes with plain water. The initial oral dose of MYHIBBIN should be given as soon as possible following kidney, heart or liver transplant.
It is recommended that MYHIBBIN be administered on an empty stomach. In stable transplant patients, however, MYHIBBIN may be administered with food if necessary [see Clinical Pharmacology ( 12.3 )]. MYHIBBIN must not be mixed with any liquids prior to dose administration.
If needed, MYHIBBIN can be administered via a nasogastric tube with a minimum size of 8 French (minimum 1.7 mm interior diameter). Patients should be instructed to take a missed dose as soon as they remember, except if it is closer than 2 hours to the next scheduled dose; in this case, they should continue to take MYHIBBIN at the usual times.
2.2Recommended Dosage for Kidney Transplant Patients Adults The recommended dosage for adult kidney transplant patients is 1 g orally, administered twice daily (total daily dose of 2 g). Pediatrics Patients 3 months and older Pediatric dosing is based on body surface area (BSA). The recommended dosage for pediatric kidney transplant patients 3 months and older is 600 mg/m2, administered twice daily (maximum daily dose of 2 g or 10 mL of the oral suspension).
2.3Recommended Dosage for Heart Transplant Patients Adults The recommended dosage for adult heart transplant patients is 1.5 g orally administered twice daily (total daily dose of 3 g). Pediatric Patients 3 months and older The recommended starting dosage for pediatric heart transplant patients 3 months and older is 600 mg/m 2 , administered twice daily. If well tolerated, the dose can be increased to a maintenance dosage of 900 mg/m 2 administered twice daily (maximum total daily dose of 3 g or 15 mL of the oral suspension).
The dose may be individualized based on clinical assessment.
2.4Recommended Dosage for Liver Transplant Patients Adults The recommended dosage for adult liver transplant patients is 1.5 g administered orally twice daily (total daily dose of 3 g). Pediatrics Patients 3 months and older The recommended starting dosage for pediatric liver transplant patients 3 months and older is 600 mg/m 2 , administered twice daily. If well tolerated, the dose can be increased to a maintenance dosage of 900 mg/m 2 administered twice daily (maximum total daily dose of 3 g or 15 mL of the oral suspension).
The dose may be individualized based on clinical assessment.
2.5Dosage Modifications: Patients with Renal Impairment, Neutropenia Renal Impairment No dosage modifications are needed in ki… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oral suspension: mycophenolate mofetil 200 mg/mL in a white to off-white suspension. Oral Suspension: 200 mg/mL mycophenolate mofetil.
⛔ Contraindications ▾
4 CONTRAINDICATIONS MYHIBBIN is contraindicated in patients with a history of hypersensitivity, including anaphylaxis, to mycophenolate mofetil (MMF), mycophenolic acid (MPA), polysorbate 80 (TWEEN) or any other component of the drug product [see Warnings and Precautions ( 5.8 )] . History of hypersensitivity, including anaphylaxis, to mycophenolate mofetil, mycophenolic acid, polysorbate 80 or any component of the drug product ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Blood Dyscrasias (Neutropenia, Red Blood Cell Aplasia): Monitor with blood tests; consider treatment interruption or dose reduction. ( 5.4 ) Gastrointestinal Complications: Monitor for complications such as bleeding, ulceration and perforations, particularly in patients with underlying gastrointestinal disorders. ( 5.5 ) Hypoxanthine-Guanine Phosphoribosyl-Transferase Deficiency: Avoid use of MYHIBBIN.
( 5.6 ) Acute Inflammatory Syndrome Associated with Mycophenolate Products: Monitor for this paradoxical inflammatory reaction. ( 5.7 ) Hypersensitivity Reactions: Discontinue MYHIBBIN; treat and monitor until signs and symptoms resolve. ( 5.8 ) Immunizations: Avoid live attenuated vaccines.
( 5.9 ) Blood Donation: Avoid during therapy and for 6 weeks thereafter. ( 5.10 ) Semen Donation: Avoid during therapy and for 90 days thereafter. ( 5.11 ) Potential Impairment on Driving and Use of Machinery: MYHIBBIN may affect ability to drive or operate machinery.
( 5.13 )
5.1Embryofetal Toxicity Use of MMF during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of congenital malformations, especially external ear and other facial abnormalities including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney and nervous system. Females of reproductive potential must be made aware of these risks and must be counseled regarding pregnancy prevention and planning. Avoid use of MYHIBBIN during pregnancy if safer treatment options are available [see Use in Specific Populations ( 8.1 , 8.3 )].
5.2Lymphoma and Other Malignancies Patients receiving immunosuppressants, including MYHIBBIN, are at increased risk of developing lymphomas and other malignancies, particularly of the skin [see Adverse Reactions ( 6.1 )]. The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent. For patients with increased risk for skin cancer, exposure to sunlight and UV light should be limited by wearing protective clothing and using a broad-spectrum sunscreen with a high protection factor.
Post-transplant lymphoproliferative disorder (PTLD) developed in 0.4% to 1% of patients receiving mycophenolate mofetil (2 g or 3 g) with other immunosuppressive agents in controlled clinical trials of kidney, heart and liver transplant patients [see Adverse Reactions ( 6.1 )]. The majority of PTLD cases appear to be related to Epstein Barr Virus (EBV) infection. The risk of PTLD appears greatest in those individuals who are EBV seronegative, a population which includes many young children.
In pediatric patients, no other malignancies besides PTLD were observed in clinical trials [see Adverse Reactions ( 6.1 )].
5.3Serious Infections Patients receiving immunosuppressants, including MYHIBBIN, are at increased risk of developing bacterial, fungal, protozoal and new or reactivated viral infections, including opportunistic infections. The risk increases with the total immunosuppressive load. These infections may lead to serious outcomes, including hospitalizations and death [see Adverse Reactions (6.1 , 6.2) ].
Serious viral infections reported include: Polyomavirus-associated nephropathy (PVAN), especially due to BK virus infection JC virus-associated progressive multifocal leukoencephalopathy (PML), and Cytomegalovirus (CMV) infections: CMV seronegative transplant patients who receive an organ from a CMV seropositive donor are at highest risk of CMV viremia and CMV disease. Viral reactivation in patients infected with Hepatitis B and C COVID-19 Consider dose reduction or discontinuation of MYHIBBIN in patients who develop new infections or reactivate viral infections, weighing the risk that reduced immunosuppression represents to the functioning allograft.
PVAN, especially due to BK virus infection, is associated with serious outcomes, including deteriorating renal function and renal graft loss [see Adverse… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: • Embryofetal Toxicity [see Warnings and Precautions (5.1) ] • Lymphomas and Other Malignancies [see Warnings and Precautions (5.2) ] • Serious Infections [see Warnings and Precautions (5.3) ] • Blood Dyscrasias: Neutropenia, Pure Red Cell Aplasia [see Warnings and Precautions (5.4) ] • Gastrointestinal Complications [see Warnings and Precautions (5.5) ] • Acute Inflammatory Syndrome Associated with Mycophenolate Products [see Warnings and Precautions (5.7) ] • Hypersensitivity Reactions [see Warnings and Precautions (5.8) ] The most common adverse reactions in clinical trials (20 % or greater) include diarrhea, leukopenia, infection, vomiting, and there is evidence of a higher frequency of certain types of infections e.g., opportunistic infection.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Azurity Pharmaceuticals, Inc. at 1-800-461-7449 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. An estimated total of 1557 adult patients received mycophenolate mofetil during pivotal clinical trials in the prevention of acute organ rejection. Of these, 991 were included in the three renal studies, 277 were included in one hepatic study, and 289 were included in one cardiac study.
Patients in all study arms also received cyclosporine and corticosteroids. The data described below primarily derive from five randomized, active-controlled double-blind 12-month trials of mycophenolate mofetil in de novo kidney (3) heart (1) and liver (1) transplant patients [see Clinical Studies ( 14.1 , 14.2 , and 14.3 )] . Oral Mycophenolate Mofetil The incidence of adverse reactions for mycophenolate mofetil was determined in five randomized, comparative, double- blind trials in the prevention of rejection in kidney, heart and liver transplant patients (two active- and one placebo- controlled trials, one active-controlled trial, and one active-controlled trial, respectively) [see Clinical Studies ( 14.1 , 14.2 and 14.3 )] .
The three de novo kidney studies with 12-month duration compared two dose levels of oral mycophenolate mofetil (1 g twice daily and 1.5 g twice daily) with azathioprine (2 studies) or placebo (1 study) when administered in combination with cyclosporine (Sandimmune ® ) and corticosteroids to prevent acute rejection episodes. One study also included anti-thymocyte globulin (ATGAM ® ) induction therapy. In the de novo heart transplantation study with 12-month duration, patients received mycophenolate mofetil 1.5 g twice daily (n=289) or azathioprine 1.5 to 3 mg/kg/day (n=289), in combination with cyclosporine (Sandimmune ® or Neoral ® ) and corticosteroids as maintenance immunosuppressive therapy.
In the de novo liver transplantation study with 12-month duration, patients received mycophenolate mofetil 1.5 g twice daily orally or azathioprine 1 to 2 mg/kg/day orally, in combination with cyclosporine (Neoral ® ) and corticosteroids as maintenance immunosuppressive therapy. The total number of patients enrolled was 565. Approximately 53% of the kidney transplant patients, 65% of the heart transplant patients, and 48% of the liver transplant patients were treated for more than 1 year.
Adverse reactions reported in ≥ 20% of patients in the mycophenolate mofetil treatment groups are presented below. The safety data of three kidney transplantation studies are pooled together. Table 1 Adverse Reactions in Controlled Studies of De Novo Kidney, Heart or Liver Transplantation Reported in ≥20% of Patients in the Mycophenolate Mofetil (MMF) Group System Organ Class Kidney Studies Heart Study Liver Study MMF 2 g/day (n=501) or 3 g/day (n=… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See FPI for drugs that may interfere with systemic exposure and reduce MYHIBBIN efficacy: antacids with magnesium or aluminum hydroxide, proton pump inhibitors, drugs that interfere with enterohepatic recirculation, telmisartan, calcium-free phosphate binders. ( 7.1 ) MYHIBBIN may reduce effectiveness of oral contraceptives. Use of additional barrier contraceptive methods is recommended.
( 7.2 ) See FPI for other important drug interactions. ( 7 )
7.1Effect of Other Drugs on MYHIBBIN Table 3 Drug Interactions with MYHIBBIN that Affect Mycophenolic Acid (MPA) Exposure Antacids with Magnesium or Aluminum Hydroxide Clinical Impact Concomitant use with an antacid containing magnesium or aluminum hydroxide decreases MPA systemic exposure [see Clinical Pharmacology ( 12.3 )] , which may reduce MYHIBBIN efficacy. Prevention or Management Administer magnesium or aluminum hydroxide containing antacids at least 2h after MYHIBBIN. Proton Pump Inhibitors (PPIs) Clinical Impact Concomitant use with PPIs decreases MPA systemic exposure [see Clinical Pharmacology ( 12.3 )] , which may reduce MYHIBBIN efficacy.
Prevention or Management Monitor patients for alterations in efficacy when PPIs are co- administered with MYHIBBIN. Examples Lansoprazole, pantoprazole Drugs that Interfere with Enterohepatic Recirculation Clinical Impact Concomitant use with drugs that directly interfere with enterohepatic recirculation, or indirectly interfere with enterohepatic recirculation by altering the gastrointestinal flora, can decrease MPA systemic exposure [see Clinical Pharmacology ( 12.3 )] , which may reduce MYHIBBIN efficacy. Prevention or Management Monitor patients for alterations in efficacy or MYHIBBIN-related adverse reactions when these drugs are co-administered with MYHIBBIN.
Examples Cyclosporine A, trimethoprim/sulfamethoxazole, bile acid sequestrants (cholestyramine), rifampin as well as aminoglycoside, cephalosporin, fluoroquinolone and penicillin classes of antimicrobials Drugs Modulating Glucuronidation Clinical Impact Concomitant use with drugs inducing glucuronidation decreases MPA systemic exposure, potentially reducing MYHIBBIN efficacy, while use with drugs inhibiting glucuronidation increases MPA systemic exposure [see Clinical Pharmacology (12.3)] , which may increase the risk of MYHIBBIN-related adverse reactions.
Prevention or Management Monitor patients for alterations in efficacy or MYHIBBIN-related adverse reactions when these drugs are co-administered with MYHIBBIN. Examples Telmisartan (induces glucuronidation); isavuconazole (inhibits glucuronidation). Calcium Free Phosphate Binders Clinical Impact Concomitant use with calcium free phosphate binders decrease MPA systemic exposure [see Clinical Pharmacology ( 12.3 )] , which may reduce MYHIBBIN efficacy.
Prevention or Management Administer calcium free phosphate binders at least 2 hours after MYHIBBIN. Examples Sevelamer
7.2Effect of MYHIBBIN on Other Drugs Table 4 Drug Interactions with MYHIBBIN that Affect Other Drugs Drugs that Undergo Renal Tubular Secretion Clinical Impact When concomitantly used with MYHIBBIN, its metabolite MPAG, may compete with drugs eliminated by renal tubular secretion which may increase plasma concentrations and/or adverse reactions associated with these drugs. Prevention or Management Monitor for drug-related adverse reactions in patients with renal impairment. Examples Acyclovir, ganciclovir, probenecid, valacyclovir, valganciclovir Combination Oral Contraceptives Clinical Impact Concomitant use with mycophenolate mofetil decreased the systemic exposure to levonorgestrel, but did not affect the systemic exposure to ethinylestradiol [see Clinical Pharmacology ( 12.3 )] , which may result in reduced combination oral contraceptive effectiveness.
Prevention or Management Use additional barrier contraceptive methods.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Male Patients: Sexually active male patients and/or their female partners are recommended to use effective contraception during treatment of the male patient and for at least 90 days after cessation of treatment ( 8.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to mycophenolate during pregnancy and those becoming pregnant within 6 weeks of discontinuing MYHIBBIN treatment. To report a pregnancy or obtain information about the registry, visit the Mycophenolate Pregnancy Registry at www.mycophenolateREMS.com or call 1-800-617-8191. Risk Summary Use of mycophenolate mofetil (MMF) during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of multiple congenital malformations in multiple organ systems (see Human Data).
Oral administration of mycophenolate to rats and rabbits during the period of organogenesis produced congenital malformations and pregnancy loss at doses less than the recommended clinical dose (0.01 to 0.05 times the recommended clinical doses in kidney and heart transplant patients) (see Animal Data). Consider alternative immunosuppressants with less potential for embryofetal toxicity. Risks and benefits of MYHIBBIN should be discussed with the pregnant woman.
The background risk of pregnancy loss and congenital malformations in organ transplant populations is not clear. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data A spectrum of congenital malformations (including multiple malformations in individual newborns) has been reported in 23 to 27% of live births in MMF exposed pregnancies, based on published data from pregnancy registries.
Malformations that have been documented include external ear, eye, and other facial abnormalities including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney, and nervous system. Based on published data from pregnancy registries, the risk of first trimester pregnancy loss has been reported at 45 to 49% following MMF exposure. Animal Data In animal reproductive toxicology studies, there were increased rates of fetal resorptions and malformations in the absence of maternal toxicity.
Oral administration of MMF to pregnant rats from Gestational Day 7 to Day 16 produced increased embryofetal lethality and fetal malformations including anophthalmia, agnathia, and hydrocephaly at doses equivalent to 0.015 and 0.01 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA. Oral administration of MMF to pregnant rabbits from Gestational Day 7 to Day 19 produced increased embryofetal lethality and fetal malformations included ectopia cordis, ectopic kidneys, diaphragmatic hernia, and umbilical hernia at dose equivalents as low as 0.05 and 0.03 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA.
8.2Lactation Risk Summary There are no data on the presence of mycophenolate in human milk, or the effects on milk production. There are limited data in the National Transplantation Pregnancy Registry on the effects of mycophenolate on a breastfed child (see Data). Studies in rats treated with MMF have shown mycophenolic acid (MPA) to be present in milk.
Because available data are limited, it is not possible to exclude potential risks to a breastfeeding infant. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for MYHIBBIN and any potential adverse effects on the breastfed infant from MYHIBBIN or from the underlying maternal condition. Data Limited information is available from the National Transplantation Pregnancy Registry.
Of seven infants reported by the National Transplantati… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to mycophenolate during pregnancy and those becoming pregnant within 6 weeks of discontinuing MYHIBBIN treatment. To report a pregnancy or obtain information about the registry, visit the Mycophenolate Pregnancy Registry at www.mycophenolateREMS.com or call 1-800-617-8191. Risk Summary Use of mycophenolate mofetil (MMF) during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of multiple congenital malformations in multiple organ systems (see Human Data).
Oral administration of mycophenolate to rats and rabbits during the period of organogenesis produced congenital malformations and pregnancy loss at doses less than the recommended clinical dose (0.01 to 0.05 times the recommended clinical doses in kidney and heart transplant patients) (see Animal Data). Consider alternative immunosuppressants with less potential for embryofetal toxicity. Risks and benefits of MYHIBBIN should be discussed with the pregnant woman.
The background risk of pregnancy loss and congenital malformations in organ transplant populations is not clear. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data A spectrum of congenital malformations (including multiple malformations in individual newborns) has been reported in 23 to 27% of live births in MMF exposed pregnancies, based on published data from pregnancy registries.
Malformations that have been documented include external ear, eye, and other facial abnormalities including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney, and nervous system. Based on published data from pregnancy registries, the risk of first trimester pregnancy loss has been reported at 45 to 49% following MMF exposure. Animal Data In animal reproductive toxicology studies, there were increased rates of fetal resorptions and malformations in the absence of maternal toxicity.
Oral administration of MMF to pregnant rats from Gestational Day 7 to Day 16 produced increased embryofetal lethality and fetal malformations including anophthalmia, agnathia, and hydrocephaly at doses equivalent to 0.015 and 0.01 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA. Oral administration of MMF to pregnant rabbits from Gestational Day 7 to Day 19 produced increased embryofetal lethality and fetal malformations included ectopia cordis, ectopic kidneys, diaphragmatic hernia, and umbilical hernia at dose equivalents as low as 0.05 and 0.03 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have been established in pediatric patients 3 months and older for the prophylaxis of organ rejection of allogenic kidney, heart or liver transplants. Kidney Transplant Use of MYHIBBIN in this population is supported by evidence from adequate and well-controlled studies of mycophenolate mofetil in adults with additional data from one open-label, pharmacokinetic and safety study of mycophenolate mofetil in pediatric patients after receiving allogeneic kidney transplant (100 patients, 3 months to 18 years of age) [see Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), Clinical Studies ( 14.1 )].
Heart Transplant and Liver Transplant Use of MYHIBBIN in pediatric heart transplant and liver transplant patients is supported by adequate and well-controlled studies and pharmacokinetic data in adult heart transplant and liver transplant patients. Additional supportive data include pharmacokinetic data in pediatric kidney transplant and pediatric liver transplant patients (8 liver transplant patients, 9 months to 5 years of age, in an open-label, pharmacokinetic and safety study) and published evidence of clinical efficacy and safety in pediatric heart transplant and pediatric liver transplant patients [see Dosage and Administration ( 2.3 , 2.4 ), Adverse Reactions ( 6.1 ), Clinical Pharmacology ( 12.3 ), Clinical Studies ( 14.1 )].
The combination of inactive ingredients (e.g., simethicone, sodium phosphate monobasic dihydrate, sodium phosphate dibasic dihydrate, glycerin) in MYHIBBIN have the potential to impact gastrointestinal tolerability. Monitor pediatric patients receiving MYHIBBIN for signs and symptoms of gastrointestinal intolerance.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of mycophenolate mofetil did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between geriatric and younger patients. In general, dose selection for a geriatric patient should take into consideration the presence of decreased hepatic, renal or cardiac function and of concomitant drug therapies. [see Adverse Reactions ( 6.1 ), Drug Interactions ( 7 )].
🆘 Overdosage ▾
10 OVERDOSAGE Possible signs and symptoms of acute overdose include hematological abnormalities such as leukopenia and neutropenia, and gastrointestinal symptoms such as abdominal pain, diarrhea, nausea, vomiting, and dyspepsia. The experience with overdose of mycophenolate mofetil in humans is limited. The reported effects associated with overdose fall within the known safety profile of the drug.
The highest dose administered to kidney transplant patients in clinical trials has been 4 g/day. In limited experience with heart and liver transplant patients in clinical trials, the highest doses used were 4 g/day or 5 g/day. At doses of 4 g/day or 5 g/day, there appears to be a higher rate, compared to the use of 3 g/day or less, of gastrointestinal intolerance (nausea, vomiting, and/or diarrhea), and occasional hematologic abnormalities, particularly neutropenia [see Warnings and Precautions ( 5.4 )] .
Treatment and Management MPA and the phenolic glucuronide metabolite of MPA (MPAG) are usually not removed by hemodialysis. However, at high MPAG plasma concentrations (>100 µg/mL), small amounts of MPAG are removed. By increasing excretion of the drug, MPA can be removed by bile acid sequestrants, such as cholestyramine [see Clinical Pharmacology ( 12.3 )].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Mycophenolate mofetil (MMF) is absorbed following oral administration and hydrolyzed to mycophenolic acid (MPA), the active metabolite. MPA is a selective uncompetitive inhibitor of the two isoforms (type I and type II) of inosine monophosphate dehydrogenase (IMPDH) leading to inhibition of the de novo pathway of guanosine nucleotide synthesis and blocks DNA synthesis. The mechanism of action of MPA is multifaceted and includes effects on cellular checkpoints responsible for metabolic programming of lymphocytes.
MPA shifts transcriptional activities in lymphocytes from a proliferative state to catabolic processes. In vitro studies suggest that MPA modulates transcriptional activities in human CD4+ T-lymphocytes by suppressing the Akt/mTOR and STAT5 pathways that are relevant to metabolism and survival, leading to an anergic state of T-cells whereby the cells become less responsive to antigenic stimulation. Additionally, MPA enhanced the expression of negative co-stimulators such as CD70, PD-1, CTLA-4, and transcription factor FoxP3 as well as decreased the expression of positive co-stimulators CD27 and CD28.
MPA decreases proliferative responses of T- and B-lymphocytes to both mitogenic and allo-antigenic stimulation, antibody responses, as well as the production of cytokines from lymphocytes and monocytes such as GM-CSF, IFN-Ɣ, IL-17, and TNF-α. Additionally, MPA prevents the glycosylation of lymphocyte and monocyte glycoproteins that are involved in intercellular adhesion to endothelial cells and may inhibit recruitment of leukocytes into sites of inflammation and graft rejection. Overall, the effect of MPA is cytostatic and reversible.
12.2Pharmacodynamics There is a lack of information regarding the pharmacodynamic effects of MMF.
12.3Pharmacokinetics Absorption Following oral administration, MMF undergoes complete conversion to MPA, the active metabolite. In 12 healthy volunteers, the mean absolute bioavailability of oral MMF relative to intravenous MMF was 94%. The mean (±SD) pharmacokinetic parameters estimates for MPA following the administration of MMF given as single doses to healthy volunteers, and multiple doses to kidney, heart, and liver transplant patients, are shown in Table 6 .
The area under the plasma-concentration time curve (AUC) for MPA appears to increase in a dose-proportional fashion in kidney transplant patients receiving multiple oral doses of MMF up to a daily dose of 3 g (1.5 g twice daily) (see Table 6 ). Table 6 Pharmacokinetic Parameters for MPA [mean (±SD)] Following Administration of MMF to Healthy Volunteers (Single Dose), and Kidney, Heart, and Liver Transplant Patients (Multiple Doses) Healthy Volunteers Dose/Route Tmax (h) Cmax (mcg/mL) Total AUC (mcg∙h/mL) Single dose 1 g/oral 0.80 (±0.36) (n=129) 24.5 (±9.5) (n=129) 63.9 (±16.2) (n=117) Kidney Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route Tmax (h) Cmax (mcg/mL) Interdosing Interval AUC(0-12h) (mcg∙h/mL) 5 days 1 g 1.58 (±0.46) (n=31) 12.0 (±3.82) (n=31) 40.8 (±11.4) (n=31) 6 days 1 g/oral 1.33 (±1.05) (n=31) 10.7 (±4.83) (n=31) 32.9 (±15.0) (n=31) Early (Less than 40 days) 1 g/oral 1.31 (±0.76) (n=25) 8.16 (±4.50) (n=25) 27.3 (±10.9) (n=25) Early (Less than 40 days) 1.5 g/oral 1.21 (±0.81) (n=27) 13.5 (±8.18) (n=27) 38.4 (±15.4) (n=27) Late (Greater than 3 months) 1.5 g/oral 0.90 (±0.24) (n=23) 24.1 (±12.1) (n=23) 65.3 (±35.4) (n=23) Heart Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route Tmax (h) Cmax (mcg/mL) Interdosing Interval AUC(0-12h) (mcg∙h/mL) Early (Day before discharge) 1.5 g/oral 1.8 (±1.3) (n=11) 11.5 (±6.8) (n=11) 43.3 (±20.8) (n=9) Late (Greater than 6 months) 1.5 g/oral 1.1 (±0.7) (n=52) 20.0 (±9.4) (n=52) 54.1 a (±20.4) (n=49) Liver Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route Tmax (h) Cmax (mcg/mL) Interdosing Interval AUC(0-12h) (mcg∙h/mL) 4 to 9 days 1 g 1.50 (±0.517) (n=… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Mycophenolate mofetil (MMF) is absorbed following oral administration and hydrolyzed to mycophenolic acid (MPA), the active metabolite. MPA is a selective uncompetitive inhibitor of the two isoforms (type I and type II) of inosine monophosphate dehydrogenase (IMPDH) leading to inhibition of the de novo pathway of guanosine nucleotide synthesis and blocks DNA synthesis. The mechanism of action of MPA is multifaceted and includes effects on cellular checkpoints responsible for metabolic programming of lymphocytes.
MPA shifts transcriptional activities in lymphocytes from a proliferative state to catabolic processes. In vitro studies suggest that MPA modulates transcriptional activities in human CD4+ T-lymphocytes by suppressing the Akt/mTOR and STAT5 pathways that are relevant to metabolism and survival, leading to an anergic state of T-cells whereby the cells become less responsive to antigenic stimulation. Additionally, MPA enhanced the expression of negative co-stimulators such as CD70, PD-1, CTLA-4, and transcription factor FoxP3 as well as decreased the expression of positive co-stimulators CD27 and CD28.
MPA decreases proliferative responses of T- and B-lymphocytes to both mitogenic and allo-antigenic stimulation, antibody responses, as well as the production of cytokines from lymphocytes and monocytes such as GM-CSF, IFN-Ɣ, IL-17, and TNF-α. Additionally, MPA prevents the glycosylation of lymphocyte and monocyte glycoproteins that are involved in intercellular adhesion to endothelial cells and may inhibit recruitment of leukocytes into sites of inflammation and graft rejection. Overall, the effect of MPA is cytostatic and reversible.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Handling and Disposal Mycophenolate mofetil has demonstrated teratogenic effects in humans [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.1 )] . Wearing disposable gloves is recommended when wiping the outer surface of the bottle and or bottle cap. Avoid direct contact of MYHIBBIN with skin or mucous membranes [see Dosage and Administration ( 2.1 )].
Follow applicable special handling and disposal procedures 1 . Do not use after 60 days of first opening the bottle. MYHIBBIN is supplied as a white to off-white oral suspension of mycophenolate mofetil 200 mg/mL and it is supplied with a child resistant cap: 175 mL of suspension in 225 mL bottle..............................................
NDC 24338-018-01 Storage and Stability Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature]. Do not freeze.
📋 Description ▾
11 DESCRIPTION MYHIBBIN (mycophenolate mofetil) is an antimetabolite immunosuppressant. It is the 2-morpholinoethyl ester of mycophenolic acid (MPA), an immunosuppressive agent; inosine monophosphate dehydrogenase (IMPDH) inhibitor. The chemical name for mycophenolate mofetil (MMF) is 4-Hexenoic acid, 6-(1,3-dihydro-4-hydroxy-6-methoxy-7-methyl-3-oxo-5-isobenzofuranyl)-4-methyl-,2-(4-morpholinyl) ethyl ester, (E)-.
It has an empirical formula of C23H31NO7, a molecular weight of 433.49, and the following structural formula: MMF is a white or almost white, crystalline powder. It is slightly soluble in water (43 µg/mL at pH 7.4); the solubility increases in acidic medium (4.27 mg/mL at pH 3.6). The drug product is an oral suspension that contains 200 mg of mycophenolate mofetil/mL.
The pH of suspension is between 6 and 8. Inactive ingredients in MYHIBBIN include dibasic sodium phosphate, glycerin, methylparaben, monobasic sodium phosphate, polysorbate 80, propylparaben, purified water, raspberry flavor, simethicone emulsion, sorbitol solution, and xanthan gum. Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ).
17.1Embryofetal Toxicity Pregnancy loss and malformation Inform females of reproductive potential and pregnant women that use of MYHIBBIN during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of congenital malformations. Advise that they must use an acceptable form of contraception [see Warnings and Precautions ( 5.1 ), Use in Specific Populations ( 8.1 , 8.3 )] . Encourage pregnant women to enroll in the Pregnancy Exposure Registry.
This registry monitors pregnancy outcomes in women exposed to mycophenolate [see Use in Specific Populations ( 8.1 )] . Contraception Discuss pregnancy testing, pregnancy prevention and planning with females of reproductive potential [see Use in Specific Populations ( 8.3 )] . Females of reproductive potential must use an acceptable form of birth control during the entire MYHIBBIN therapy and for 6 weeks after stopping MYHIBBIN, unless the patient chooses abstinence.
MYHIBBIN may reduce effectiveness of oral contraceptives. Use of additional barrier contraceptive methods is recommended [see Use in Specific Populations ( 8.3 )] . For patients who are considering pregnancy, discuss appropriate alternative immunosuppressants with less potential for embryofetal toxicity.
Risks and benefits of MYHIBBIN should be discussed with the patient. Advise sexually active male patients and/or their partners to use effective contraception during the treatment of the male patient and for at least 90 days after cessation of treatment. This recommendation is based on findings of animal studies [see Use in Specific Populations ( 8.3 ), Nonclinical Toxicology ( 13.1 )] .
17.2Development of Lymphoma and Other Malignancies Inform patients that they are at increased risk of developing lymphomas and other malignancies, particularly of the skin, due to immunosuppression [see Warnings and Precautions ( 5.2 )] . Advise patients to limit exposure to sunlight and ultraviolet (UV) light by wearing protective clothing and use of broad-spectrum sunscreen with high protection factor.
17.3Increased Risk of Serious Infections Inform patients that they are at increased risk of developing a variety of infections due to immunosuppression. Instruct them to contact their physician if they develop any of the signs and symptoms of infection explained in the Medication Guide [see Warnings and Precautions ( 5.3) ] .
17.4Blood Dyscrasias Inform patients that they are at increased risk for developing blood adverse effects such as anemia or low white blood cells. Advise patients to immediately contact their healthcare provider if they experience any evidence of infection, unexpected bruising, or bleeding, or any other manifestation of bone marrow suppression [see Warnings and Precautions ( 5.4 )].
17.5Gastrointestinal Tract Complications Inform patients that MYHIBBIN can cause gastrointestinal tract complications including bleeding, intestinal perforations, and gastric or duodenal ulcers. Advise the patient to contact their healthcare provider if they have symptoms of gastrointestinal bleeding, or sudden onset or persistent abdominal pain [see Warnings and Precautions ( 5.5 )] .
17.6Acute Inflammatory Syndrome Inform patients that acute inflammatory reactions have been reported in some patients who received mycophenolate mofetil. Some reactions were severe, requiring hospitalization. Advise patients to contact their physician if they develop fever, joint stiffness, joint pain or muscle pains [see Warnings and Precautions ( 5.7 )] .
17.7Hypersensitivity Reactions Inform patients of the potential risk of hypersensitivity reactions. Advise patients to stop taking MYHIBBIN and seek immediate medical attention if signs or symptoms of a hypersensitivity reaction occur (such as swelling of face, lips, tongue, or throat; difficulty breathing or swallowing) [see Warnings and P… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE MYHIBBIN ® (my hib in) (mycophenolate mofetil oral suspension) Read the Medication Guide that comes with MYHIBBIN before you start taking it and each time you refill your prescription. There may be new information. This Medication Guide does not take the place of talking with your doctor about your medical condition or treatment.
What is the most important information I should know about MYHIBBIN? MYHIBBIN can cause serious side effects, including: Increased risk of loss of a pregnancy (miscarriage) and higher risk of birth defects. Females who take MYHIBBIN during pregnancy have a higher risk of miscarriage during the first 3 months (first trimester), and a higher risk that their baby will be born with birth defects.
If you are a female who can become pregnant , your healthcare provider must talk with you about acceptable birth control methods (contraceptive counseling) to use while taking MYHIBBIN. You should have 1 pregnancy test immediately before starting MYHIBBIN and another pregnancy test 8 to 10 days later. Pregnancy tests should be repeated during routine follow-up visits with your healthcare provider.
Talk to your healthcare provider about the results of all of your pregnancy tests. You must use acceptable birth control during your entire MYHIBBIN treatment and for 6 weeks after stopping MYHIBBIN, unless at any time you choose to avoid sexual intercourse (abstinence) with a man completely. MYHIBBIN decreases blood levels of the hormones in birth control pills that you take by mouth.
Birth control pills may not work as well while you take MYHIBBIN, and you could become pregnant. If you take birth control pills while using MYHIBBIN you must also use another form of birth control. Talk to your healthcare provider about other birth control methods that you can use while taking MYHIBBIN.
If you are a sexually active male whose female partner can become pregnant while you are taking MYHIBBIN , use effective contraception during treatment and for at least 90 days after stopping MYHIBBIN. If you plan to become pregnant , talk with your healthcare provider. Your healthcare provider will decide if other medicines to prevent rejection may be right for you.
If you become pregnant while taking MYHIBBIN , do not stop taking MYHIBBIN. Call your healthcare provider right away. You and your healthcare provider may decide that other medicines to prevent rejection may be right for you.
You and your healthcare provider should report your pregnancy to the Mycophenolate Pregnancy Registry either: o By phone at 1-800-617-8191 or o By visiting the REMS website at: www.mycophenolateREMS.com The purpose of this registry is to gather information about the health of you and your baby. Increased risk of getting certain cancers. People who take MYHIBBIN have a higher risk of getting lymphoma, and other cancers, especially skin cancer.
Tell your healthcare provider if you have: unexplained fever, prolonged tiredness, weight loss or lymph node swelling a change in the size and color of a mole a brown or black skin lesion with uneven borders, or one part of the lesion does not look like the other a new skin lesion or bump any other changes to your health Increased risk of getting serious infections. MYHIBBIN weakens the body’s immune system and affects your ability to fight infections. Serious infections can happen with MYHIBBIN and can lead to hospitalizations and death.
These serious infections can include: Viral infections. Certain viruses can live in your body and cause active infections when your immune system is weak. Viral infections that can happen with MYHIBBIN include: o Shingles, other herpes infections, and cytomegalovirus (CMV).
CMV can cause serious tissue and blood infections. o BK virus. BK virus can affect how your kidney works and cause your transplanted kidney to fail. o Hepatitis B and C viruses. Hepatitis viruses can affect how your liver works.
Talk to your healthcare provider about how hepatitis viruses may af… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following oral administration, MMF undergoes complete conversion to MPA, the active metabolite. In 12 healthy volunteers, the mean absolute bioavailability of oral MMF relative to intravenous MMF was 94%. The mean (±SD) pharmacokinetic parameters estimates for MPA following the administration of MMF given as single doses to healthy volunteers, and multiple doses to kidney, heart, and liver transplant patients, are shown in Table 6 .
The area under the plasma-concentration time curve (AUC) for MPA appears to increase in a dose-proportional fashion in kidney transplant patients receiving multiple oral doses of MMF up to a daily dose of 3 g (1.5 g twice daily) (see Table 6 ). Table 6 Pharmacokinetic Parameters for MPA [mean (±SD)] Following Administration of MMF to Healthy Volunteers (Single Dose), and Kidney, Heart, and Liver Transplant Patients (Multiple Doses) Healthy Volunteers Dose/Route Tmax (h) Cmax (mcg/mL) Total AUC (mcg∙h/mL) Single dose 1 g/oral 0.80 (±0.36) (n=129) 24.5 (±9.5) (n=129) 63.9 (±16.2) (n=117) Kidney Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route Tmax (h) Cmax (mcg/mL) Interdosing Interval AUC(0-12h) (mcg∙h/mL) 5 days 1 g 1.58 (±0.46) (n=31) 12.0 (±3.82) (n=31) 40.8 (±11.4) (n=31) 6 days 1 g/oral 1.33 (±1.05) (n=31) 10.7 (±4.83) (n=31) 32.9 (±15.0) (n=31) Early (Less than 40 days) 1 g/oral 1.31 (±0.76) (n=25) 8.16 (±4.50) (n=25) 27.3 (±10.9) (n=25) Early (Less than 40 days) 1.5 g/oral 1.21 (±0.81) (n=27) 13.5 (±8.18) (n=27) 38.4 (±15.4) (n=27) Late (Greater than 3 months) 1.5 g/oral 0.90 (±0.24) (n=23) 24.1 (±12.1) (n=23) 65.3 (±35.4) (n=23) Heart Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route Tmax (h) Cmax (mcg/mL) Interdosing Interval AUC(0-12h) (mcg∙h/mL) Early (Day before discharge) 1.5 g/oral 1.8 (±1.3) (n=11) 11.5 (±6.8) (n=11) 43.3 (±20.8) (n=9) Late (Greater than 6 months) 1.5 g/oral 1.1 (±0.7) (n=52) 20.0 (±9.4) (n=52) 54.1 a (±20.4) (n=49) Liver Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route Tmax (h) Cmax (mcg/mL) Interdosing Interval AUC(0-12h) (mcg∙h/mL) 4 to 9 days 1 g 1.50 (±0.517) (n=22) 17.0 (±12.7) (n=22) 34.0 (±17.4) (n=22) Early (5 to 8 days) 1.5 g/oral 1.15 (±0.432) (n=20) 13.1 (±6.76) (n=20) 29.2 (±11.9) (n=20) Late (Greater than 6 months) 1.5 g/oral 1.54 (±0.51) (n=6) 19.3 (±11.7) (n=6) 49.3 (±14.8) (n=6) aAUC(0-12h) values quoted are extrapolated from data from samples collected over 4 hours.
In the early post-transplant period (less than 40 days post-transplant), kidney, heart, and liver transplant patients had mean MPA AUCs approximately 20% to 41% lower and mean Cmax approximately 32% to 44% lower compared to the late transplant period (i.e., 3 to 6 months post-transplant) (non-stationarity in MPA pharmacokinetics). In liver transplant patients, administration of 1.5 g twice daily oral MMF resulted in mean MPA AUC estimates similar to those found in kidney transplant patients administered 1 g MMF twice daily.
Effect of Food Food (27 g fat, 650 calories) had no effect on the extent of absorption (MPA AUC) of MMF when administered at doses of 1.5 g twice daily to kidney transplant patients. However, MPA Cmax was decreased by 40% in the presence of food [see Dosage and Administration ( 2.1 )]. Distribution The mean (±SD) apparent volume of distribution of MPA in 12 healthy volunteers was approximately 3.6 (±1.5) L/kg.
At clinically relevant concentrations, MPA is 97% bound to plasma albumin. The phenolic glucuronide metabolite of MPA (MPAG) is 82% bound to plasma albumin at MPAG concentration ranges that are normally seen in stable kidney transplant patients; however, at higher MPAG concentrations (observed in patients with kidney impairment or delayed kidney graft function), the binding of MPA may be reduced as a result of competition between MPAG and MPA for protein binding. Mean blood to plasma ratio of radioactivity concentrations was approximately 0.6… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics There is a lack of information regarding the pharmacodynamic effects of MMF.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Kidney Transplantation Adults The three de novo kidney transplantation studies compared two dose levels of oral mycophenolate mofetil (1 g twice daily and 1.5 g twice daily) with azathioprine (2 studies) or placebo (1 study) to prevent acute rejection episodes. One of the two studies with azathioprine (AZA) control arm also included anti-thymocyte globulin (ATGAM®) induction therapy. The geographic location of the investigational sites of these studies are included in Table 9 .
In all three de novo kidney transplantation studies, the primary efficacy endpoint was the proportion of patients in each treatment group who experienced treatment failure within the first 6 months after transplantation. Treatment failure was defined as biopsy-proven acute rejection on treatment or the occurrence of death, graft loss or early termination from the study for any reason without prior biopsy-proven rejection. Mycophenolate mofetil, in combination with corticosteroids and cyclosporine, reduced (statistically significant at 0.05 level) the incidence of treatment failure within the first 6 months following transplantation ( Table 9).
Patients who prematurely discontinued treatment were followed for the occurrence of death or graft loss, and the cumulative incidence of graft loss and patient death combined are summarized in Table 10 . Patients who prematurely discontinued treatment were not followed for the occurrence of acute rejection after termination. Table 9 Treatment Failure in De Novo Kidney Transplantation Studies USA Study MYCOPHENOLATE MOFETIL 2 g/day MYCOPHENOLATE MOFETIL 3 g/day AZA 1 to 2 mg/kg/day (N=499 patients) (n=167 patients) (n=166 patients) (n=166 patients) All 3 groups received anti-thymocyte globulin induction, cyclosporine and corticosteroids All treatment failures 31.1% 31.3% 47.6% Early termination without prior acute rejection 9.6% 12.7% 6.0% Biopsy-proven rejection episode on treatment 19.8% 17.5% 38.0% Europe/Canada/Australia Study (N=503 patients) MYCOPHENOLATE MOFETIL 2 g/day (n=173 patients) MYCOPHENOLATE MOFETIL 3 g/day (n=164 patients) AZA 100 to 150 mg/day (n=166 patients) No induction treatment administered; all 3 groups received cyclosporine and corticosteroids.
All treatment failures 38.2% 34.8% 50.0% Early termination without prior acute rejection 13.9% 15.2% 10.2% Biopsy-proven rejection episode on treatment 19.7% 15.9% 35.5% Europe Study MYCOPHENOLATE MOFETIL 2 g/day MYCOPHENOLATE MOFETIL 3 g/day Placebo (N=491 patients) (n=165 patients) (n=160 patients) (n=166 patients) No induction treatment administered; all 3 groups received cyclosporine and corticosteroids. All treatment failures 30.3% 38.8% 56.0% Early termination without prior acute rejection 11.5% 22.5% 7.2% Biopsy-proven rejection episode on treatment 17.0% 13.8% 46.4% *Does not include death and graft loss as reason for early termination.
No advantage of mycophenolate mofetil at 12 months with respect to graft loss or patient death (combined) was established ( Table 10 ). Numerically, patients receiving mycophenolate mofetil 2 g/day and 3 g/day experienced a better outcome than controls in all three studies; patients receiving mycophenolate mofetil 2 g/day experienced a better outcome than mycophenolate mofetil 3 g/day in two of the three studies. Patients in all treatment groups who terminated treatment early were found to have a poor outcome with respect to graft loss or patient death at 1 year.
Table 10 De Novo Kidney Transplantation Studies Cumulative Incidence of Combined Graft Loss or Patient Death at 12 Months Study MYCOPHENOLATE MOFETIL 2 g/day MYCOPHENOLATE MOFETIL 3 g/day Control (AZA or Placebo) USA 8.5% 11.5% 12.2% Europe/Canada/Australia 11.7% 11.0% 13.6% Europe 8.5% 10.0% 11.5% Pediatrics- De Novo Kidney transplantation PK Study with Long Term Follow-Up One open-label, safety and pharmacokinetic study of mycophenolate mofetil oral suspension 600 mg/m2 twice daily (up to 1 g twice daily) in combination with… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 104-week oral carcinogenicity study in mice, MMF in daily doses up to 180 mg/kg was not tumorigenic. The highest dose tested was 0.2 times the recommended clinical dose (2 g/day) in renal transplant patients and 0.15 times the recommended clinical dose (3 g/day) in cardiac transplant patients when corrected for differences in body surface area (BSA). In a 104-week oral carcinogenicity study in rats, MMF in daily doses up to 15 mg/kg was not tumorigenic.
The highest dose was 0.035 times the recommended clinical dose in kidney transplant patients and 0.025 times the recommended clinical dose in heart transplant patients when corrected for BSA. While these animal doses were lower than those given to patients, they were maximal in those species and were considered adequate to evaluate the potential for human risk [see Warnings and Precautions ( 5.2 )]. The genotoxic potential of MMF was determined in five assays.
MMF was genotoxic in the mouse lymphoma/thymidine kinase assay and the in vivo mouse micronucleus assay. MMF was not genotoxic in the bacterial mutation assay, the yeast mitotic gene conversion assay or the Chinese hamster ovary cell chromosomal aberration assay. MMF had no effect on fertility of male rats at oral doses up to 20 mg/kg/day.
This dose represents 0.05 times the recommended clinical dose in renal transplant patients and 0.03 times the recommended clinical dose in cardiac transplant patients when corrected for BSA. In a female fertility and reproduction study conducted in rats, oral doses of 4.5 mg/kg/day caused malformations (principally of the head and eyes) in the first generation offspring in the absence of maternal toxicity. This dose was 0.01 times the recommended clinical dose in renal transplant patients and 0.005 times the recommended clinical dose in cardiac transplant patients when corrected for BSA.
No effects on fertility or reproductive parameters were evident in the dams or in the subsequent generation.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 104-week oral carcinogenicity study in mice, MMF in daily doses up to 180 mg/kg was not tumorigenic. The highest dose tested was 0.2 times the recommended clinical dose (2 g/day) in renal transplant patients and 0.15 times the recommended clinical dose (3 g/day) in cardiac transplant patients when corrected for differences in body surface area (BSA). In a 104-week oral carcinogenicity study in rats, MMF in daily doses up to 15 mg/kg was not tumorigenic.
The highest dose was 0.035 times the recommended clinical dose in kidney transplant patients and 0.025 times the recommended clinical dose in heart transplant patients when corrected for BSA. While these animal doses were lower than those given to patients, they were maximal in those species and were considered adequate to evaluate the potential for human risk [see Warnings and Precautions ( 5.2 )]. The genotoxic potential of MMF was determined in five assays.
MMF was genotoxic in the mouse lymphoma/thymidine kinase assay and the in vivo mouse micronucleus assay. MMF was not genotoxic in the bacterial mutation assay, the yeast mitotic gene conversion assay or the Chinese hamster ovary cell chromosomal aberration assay. MMF had no effect on fertility of male rats at oral doses up to 20 mg/kg/day.
This dose represents 0.05 times the recommended clinical dose in renal transplant patients and 0.03 times the recommended clinical dose in cardiac transplant patients when corrected for BSA. In a female fertility and reproduction study conducted in rats, oral doses of 4.5 mg/kg/day caused malformations (principally of the head and eyes) in the first generation offspring in the absence of maternal toxicity. This dose was 0.01 times the recommended clinical dose in renal transplant patients and 0.005 times the recommended clinical dose in cardiac transplant patients when corrected for BSA.
No effects on fertility or reproductive parameters were evident in the dams or in the subsequent generation.
📚 References ▾
15 REFERENCES 1. “OSHA Hazardous Drugs.” OSHA. http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Recent Major Changes ▾
Warnings and Precautions, Hypersensitivity Reactions ( 5.8 ) 4/2025
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL MYHIBBIN Oral Suspension, 200 mg/mL - NDC 24338-018-01 - 175 mL Carton label MYHIBBIN Oral Suspension, 200 mg/mL - NDC 24338-018-01 - 175 mL Bottle label carton-label bottle-label
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |