
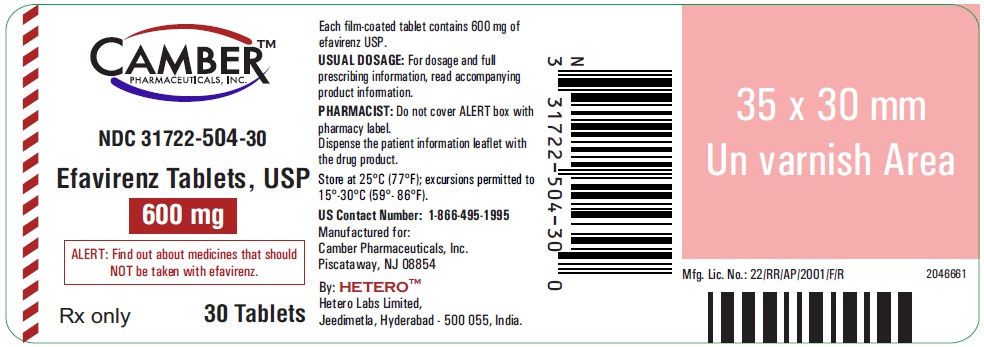
Efavirenz 600 mg Tablet, Film Coated, 250-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus 1 Non-Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Efavirenz is used to treat human immunodeficiency virus (HIV) infection. Efavirenz is in a class of medications called non-nucleoside reverse transcriptase inhibitors (NNRTIs). It works by decreasing the amount of HIV in the blood. Although efavirenz does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications along and making other life-style changes may decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗- Efavirenz is an antiretroviral medicine — it treats HIV-1 infection. It works by blocking an enzyme the virus needs to make copies of itself. It won't cure HIV, but used consistent...
- What exactly is efavirenz and what is it treating in my body?
- That's actually one of the most common things people notice with efavirenz, and it can feel unsettling. Dizziness, vivid or strange dreams, trouble sleeping, and foggy thinking are...
- Why do I feel so dizzy and have such weird dreams since starting this medication?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Efavirenz — tap one for details:
Efavirenz may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $6.10 | $1,524.10 / 250 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Efavirenz 600 mg 69097-0301-02 | Cipla | 30 tablets | $1.349 | AB | Availability likely | — |
| Efavirenz 600 mgthis 31722-0504-25 | Camber | 250 tablets | — | AB | FDA listed | — |
| Efavirenz 600 mg 33342-0013-07 | Macleods | 30 tablets | — | AB | FDA listed | — |
| Efavirenz 600 mg 65862-0049-10 | Aurobindo | 10 tablets | — | — | FDA listed | — |
| Efavirenz 600 mg 72865-0172-25 | XLCare | 250 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 31722-0504-25 You're viewing this | 250 TABLET, FILM COATED in 1 BOTTLE (31722-504-25) | — | — | 2018-04-27 | Active |
| 31722-0504-30 | 30 TABLET, FILM COATED in 1 BOTTLE (31722-504-30) | $1.35 / ea | $40.47 | 2018-04-27 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 31722-0504-25?
What is the difference between NDC 31722-0504-25 and NDC 31722-0504-30?
What NDC number is used to bill for this package of Efavirenz 600 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Efavirenz tablets in combination with other antiretroviral agents is indicated for the treatment of human immunodeficiency virus type 1 (HIV-1) infection in adults and in pediatric patients at least 3 months old and weighing at least 3.5 kg. Efavirenz is a non-nucleoside reverse transcriptase inhibitor indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus type 1 infection in adults and in pediatric patients at least 3 months old and weighing at least 3.5 kg.
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION • Efavirenz tablets should be taken orally once daily on an empty stomach, preferably at bedtime. (2) • Recommended adult dose: 600 mg. (2.2) • Pediatric dosing is based on weight. (2.3)
2.1Hepatic Function Monitor hepatic function prior to and during treatment with efavirenz tablets [see Warnings and Precautions ( 5.9)]. Efavirenz tablets are not recommended in patients with moderate or severe hepatic impairment (Child Pugh B or C) [see Warnings and Precautions (5.9) and Use in Specific Populationns ( 8.6)].
2.2Adults The recommended dosage of efavirenz tablets are 600 mg orally, once daily, in combination with a protease inhibitor and/or nucleoside analogue reverse transcriptase inhibitors (NRTIs). It is recommended that efavirenz tablets be taken on an empty stomach, preferably at bedtime. The increased efavirenz concentrations observed following administration of efavirenz tablets with food may lead to an increase in frequency of adverse reactions [see Clinical Pharmacology (12.3)].
Dosing at bedtime may improve the tolerability of nervous system symptoms [see Warnings and Precautions (5.6), Adverse Reactions (6.1), and Patient Counseling Information ( 17)]. Efavirenz tablets should be swallowed intact with liquid. Concomitant Antiretroviral Therapy Efavirenz tablets must be given in combination with other antiretroviral medications [see Indications and Usage (1), Warnings and Precautions (5.3), Drug Interactions (7.1), and Clinical Pharmacology (12.3)].
2.3Pediatric Patients It is recommended that efavirenz tablets be taken on an empty stomach, preferably at bedtime. Table 1 describes the recommended dose of efavirenz tablets for pediatric patients 3 months of age or older and weighing between 3.5 kg and 40 kg [see Clinical Pharmacology (12.3)]. The recommended dosage of efavirenz tablets for pediatric patients weighing 40 kg or greater is 600 mg once daily.
Table 1: Efavirenz Tablets Dosing in Pediatric Patients Patient Body Weight Efavirenz Tablets Daily Dose Number of Tablets b and Strength to Administer at least 40 kg 600 mg one 600 mg tablet b Tablets must not be crushed.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS • Tablets 600 mg tablets are yellow, capsular-shaped, film-coated tablets, with ‘H’ on one side and ‘4’ on the other side. • Tablets: 600 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Efavirenz tablets are contraindicated in patients with previously demonstrated clinically significant hypersensitivity (eg, Stevens-Johnson syndrome, erythema multiforme, or toxic skin eruptions) to any of the components of this product. • Coadministration of efavirenz with elbasvir and grazoprevir is contraindicated [see Warnings and Precautions (5.1) and Drug Interactions ( 7.1)]. • Patients with previously demonstrated hypersensitivity (eg, Stevens-Johnson syndrome, erythema multiforme, or toxic skin eruptions) to any of the components of this product.
(4) • Coadministration of efavirenz with elbasvir/grazoprevir.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • QTc prolongation: Consider alternatives to efavirenz in patients taking other medications with a known risk of Torsade de Pointes or in patients at higher risk of Torsade de Pointes. (5.2) • Do not use as a single agent or add on as a sole agent to a failing regimen. Consider potential for cross-resistance when choosing other agents.
(5.3) • Not recommended with ATRIPLA, which contains efavirenz, emtricitabine, and tenofovir disoproxil fumarate, unless needed for dose adjustment when coadministered with rifampin. (5.4) • Serious psychiatric symptoms: Immediate medical evaluation is recommended for serious psychiatric symptoms such as severe depression or suicidal ideation. (5.5, 17) • Nervous system symptoms (NSS): NSS are frequent and usually begin 1 to 2 days after initiating therapy and resolve in 2 to 4 weeks.
Dosing at bedtime may improve tolerability. NSS are not predictive of onset of psychiatric symptoms. (5.6 , 6.1 , 17) • Embryo-Fetal Toxicity: Avoid administration in the first trimester of pregnancy as fetal harm may occur.
(5.7 , 8.1) • Hepatotoxicity: Monitor liver function tests before and during treatment in patients with underlying hepatic disease, including hepatitis B or C coinfection, marked transaminase elevations, or who are taking medications associated with liver toxicity. Among reported cases of hepatic failure, a few occurred in patients with no pre-existing hepatic disease. (5.9 , 6.1 , 8.6) • Rash: Rash usually begins within 1 to 2 weeks after initiating therapy and resolves within 4 weeks.
Discontinue if severe rash develops. (5.8 , 6.1 , 17) • Convulsions: Use caution in patients with a history of seizures . (5.10) • Lipids: Total cholesterol and triglyceride elevations.
Monitor before therapy and periodically thereafter. (5.11) • Immune reconstitution syndrome: May necessitate further evaluation and treatment. (5.12) • Redistribution/accumulation of body fat: Observed in patients receiving antiretroviral therapy.
(5.13 , 17)
5.1Drug Interactions Efavirenz plasma concentrations may be altered by substrates, inhibitors, or inducers of CYP3A. Likewise, efavirenz may alter plasma concentrations of drugs metabolized by CYP3A or CYP2B6. The most prominent effect of efavirenz at steady-state is induction of CYP3A and CYP2B6 [See Dosage and Administration (2.2) and Drug Interactions ( 7.1)].
5.2QTc Prolongation QTc prolongation has been observed with the use of efavirenz [see Drug Interactions (7.3 , 7.4) and Clinical Pharmacology ( 12.2)]. Consider alternatives to efavirenz tablets when coadministered with a drug with a known risk of Torsade de Pointes or when administered to patients at higher risk of Torsade de Pointes.
5.3Resistance Efavirenz tablets must not be used as a single agent to treat HIV-1 infection or added on as a sole agent to a failing regimen. Resistant virus emerges rapidly when efavirenz is administered as monotherapy. The choice of new antiretroviral agents to be used in combination with efavirenz should take into consideration the potential for viral cross-resistance.
5.4Coadministration with Related Products Coadministration of efavirenz tablets with ATRIPLA (efavirenz 600 mg/emtricitabine 200 mg/tenofovir disoproxil fumarate 300 mg) is not recommended unless needed for dose adjustment (eg, with rifampin), since efavirenz is one of its active ingredients.
5.5Psychiatric Symptoms Serious psychiatric adverse experiences have been reported in patients treated with efavirenz tablets. In controlled trials of 1,008 patients treated with regimens containing efavirenz tablets for a mean of 2.1 years and 635 patients treated with control regimens for a mean of 1.5 years, the frequency (regardless of causality) of specific serious psychiatric events among patients who received efavirenz tablets or control regimens, respectively, were severe depression (2.4%, 0.9%), suicidal ideation (0.7%, 0.3%), nonfatal suicide attempts (0.5%, 0), aggressive behavior (0.4%…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most significant adverse reactions observed in patients treated with efavirenz tablets are: • psychiatric symptoms [see Warnings and Precautions ( 5.5)], • nervous system symptoms [see Warnings and Precautions (5.6)], • rash [see Warnings and Precautions (5.8)]. • hepatotoxicity [see Warnings and Precautions ( 5.9)] Most common adverse reactions (>5%, moderate-severe) are impaired concentration, abnormal dreams, rash, dizziness, nausea, headache, fatigue, insomnia, and vomiting. (6) To report SUSPECTED ADVERSE REACTIONS, contact Hetero Labs Limited at 866-495-1995 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, the adverse reaction rates reported cannot be directly compared to rates in other clinical studies and may not reflect the rates observed in clinical practice. Adverse Reactions in Adults The most common (>5% in either efavirenz treatment group) adverse reactions of at least moderate severity among patients in Study 006 treated with efavirenz tablets in combination with zidovudine/lamivudine or indinavir were rash, dizziness, nausea, headache, fatigue, insomnia, and vomiting.
Selected clinical adverse reactions of moderate or severe intensity observed in ≥2% of efavirenz tablets-treated patients in two controlled clinical trials are presented in Table 2. Table 2: Selected Treatment-Emergent a Adverse Reactions of Moderate or Severe Intensity Reported in ≥2% of Efavirenz-Treated Patients in Studies 006 and ACTG 364 Adverse Reactions Study 006 LAM-, NNRTI-, and Protease Inhibitor-Naive Patients Study ACTG 364 NRTI-experienced, NNRTI-, and Protease Inhibitor-Naive Patients Efavirenz tablets b + ZDV/LAM (n=412) 180 weeks c Efavirenz tablets b + Indinavir (n=415) 102 weeks c Indinavir + ZDV/LAM (n=401) 76 weeks c Efavirenz tablets b + Nelfinavir + NRTIs (n=64) 71.1 weeks c Efavirenz tablets b + NRTIs (n=65) 70.9 weeks c Nelfinavir + NRTIs (n=66) 62.7 weeks c Body as a Whole Fatigue 8% 5% 9% 0 2% 3% Pain 1% 2% 8% 13% 6% 17% Central and Peripheral Nervous System Dizziness 9% 9% 2% 2% 6% 6% Headache 8% 5% 3% 5% 2% 3% Insomnia 7% 7% 2% 0 0 2% Concentration impaired 5% 3% <1% 0 0 0 Abnormal dreams 3% 1% 0 — — — Somnolence 2% 2% <1% 0 0 0 Anorexia 1% <1% <1% 0 2% 2% Gastrointestinal Nausea 10% 6% 24% 3% 2% 2% Vomiting 6% 3% 14% — — — Diarrhea 3% 5% 6% 14% 3% 9% Dyspepsia 4% 4% 6% 0 0 2% Abdominal pain 2% 2% 5% 3% 3% 3% Psychiatric Anxiety 2% 4% <1% — — — Depression 5% 4% <1% 3% 0 5% Nervousness 2% 2% 0 2% 0 2% Skin & Appendages Rash d 11% 16% 5% 9% 5% 9% Pruritus <1% 1% 1% 9% 5% 9% a Includes adverse events at least possibly related to study drug or of unknown relationship for Study 006.
Includes all adverse events regardless of relationship to study drug for Study ACTG 364. b Efavirenz tablets provided as 600 mg once daily. c Median duration of treatment. d Includes erythema multiforme, rash, rash erythematous, rash follicular, rash maculopapular, rash petechial, rash pustular, and urticaria for Study 006 and macules, papules, rash, erythema, redness, inflammation, allergic rash, urticaria, welts, hives, itchy, and pruritus for ACTG 364. — = Not Specified. ZDV = zidovudine, LAM=lamivudine. Pancreatitis has been reported, although a causal relationship with efavirenz has not been established.
Asymptomatic increases in serum amylase levels were observed in a significantly higher number of patients treated with efavirenz 600 mg than in control patients (see Laboratory Abnormalities ). Nervous System Symptoms For 1,008 patients treated with regimens containing efavirenz tablets and 635 patients treated with a control regimen in controlled trials, Table 3 lists the frequency of symptoms of different degrees of severity and gives the discontinuation rates for one or more of the following nervous system symptoms: dizziness, insomnia, impaired concentration, somnolence, abnormal dreaming, euphoria, confusion,…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Coadministration of efavirenz can alter the concentrations of other drugs and other drugs may alter the concentrations of efavirenz. The potential for drug-drug interactions should be considered before and during therapy. (7)
7.1Potential for Efavirenz to Affect other Drugs Efavirenz has been shown in vivo to induce CYP3A and CYP2B6. Other compounds that are substrates of CYP3A or CYP2B6 may have decreased plasma concentrations when coadministered with efavirenz tablets.
7.2Potential for Other Drugs to Affect Efavirenz Drugs that induce CYP3A activity (eg, phenobarbital, rifampin, rifabutin) would be expected to increase the clearance of efavirenz resulting in lowered plasma concentrations [see Dosage and Administration (2.2)].
7.3QT Prolonging Drugs There is limited information available on the potential for a pharmacodynamic interaction between efavirenz and drugs that prolong the QTc interval. QTc prolongation has been observed with the use of efavirenz [see Clinical Pharmacology ( 12.2)]. Consider alternatives to efavirenz when coadministered with a drug with a known risk of Torsade de Pointes.
7.4Established and Other Potentially Significant Drug Interactions Drug interactions with efavirenz tablets are summarized in Tables 5. For pharmacokinetics data, [see Clinical Pharmacology (12.3)] Tables 7 and 8. This table includes potentially significant interactions, but is not all inclusive.
Table 5: Established and Other Potentially Significant Drug Interactions: Alteration in Dose or Regimen May Be Recommended Based on Drug Interaction Studies or Predicted Interaction Concomitant Drug Class: Drug Name Effect Clinical Comment HIV antiviral agents Protease inhibitor: Fosamprenavir calcium ↓amprenavir Fosamprenavir (unboosted): Appropriate doses of the combinations with respect to safety and efficacy have not been established. Fosamprenavir/ritonavir: An additional 100 mg/day (300 mg total) of ritonavir is recommended when efavirenz tablets are administered with fosamprenavir/ritonavir once daily.
No change in the ritonavir dose is required when efavirenz tablets are administered with fosamprenavir plus ritonavir twice daily. Protease inhibitor: Atazanavir ↓atazanavir * Treatment-naive patients: When coadministered with efavirenz tablets, the recommended dose of atazanavir is 400 mg with ritonavir 100 mg (together once daily with food) and efavirenz tablets 600 mg (once daily on an empty stomach, preferably at bedtime). Treatment-experienced patients: Coadministration of efavirenz tablets and atazanavir is not recommended.
Protease inhibitor: Indinavir ↓indinavir * The optimal dose of indinavir, when given in combination with efavirenz tablets, is not known. Increasing the indinavir dose to 1,000 mg every 8 hours does not compensate for the increased indinavir metabolism due to efavirenz tablets. Protease inhibitor: Lopinavir/ritonavir ↓lopinavir * Lopinavir/ritonavir once daily dosing is not recommended when coadministered with efavirenz tablets.
The dose of lopinavir/ritonavir must be increased when coadministered with efavirenz tablets. See the lopinavir/ritonavir prescribing information for dose adjustments of lopinavir/ritonavir when coadministered with efavirenz in adult and pediatric patients. Protease inhibitor: Ritonavir ↑ritonavir * ↑efavirenz * Monitor for elevation of liver enzymes and for adverse clinical experiences (e.g., dizziness, nausea, paresthesia) when efavirenz tablet is coadministered with ritonavir.
Protease inhibitor: Saquinavir ↓saquinavir * Appropriate doses of the combination of efavirenz tablets and saquinavir/ritonavir with respect to safety and efficacy have not been established. NNRTI: Other NNRTIs ↑ or ↓efavirenz and/or NNRTI Combining two NNRTIs has not been shown to be beneficial. ↑Efavirenz tablets should not be coadministered with other NNRTIs. CCR5 co-receptor antagonist: Maraviroc ↓maraviroc * Refer to the full prescribing information for maraviroc for guidance…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Breastfeeding not recommended. (8.2) • Females and Males of Reproductive Potential: Pregnancy testing and contraception are recommended. (8.3) • Hepatic impairment: Efavirenz tablets are not recommended for patients with moderate or severe hepatic impairment. Use caution in patients with mild hepatic impairment. (8.6) • Pediatric patients: The incidence of rash was higher than in adults. ( 5.8 , 6.2 , 8.4)
8.1Pregnancy Tetratogenic Effects Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to efavirenz tablets during pregnancy. Physicians are encouraged to register patients by calling the Antiretroviral Pregnancy Registry at 1-800-258-4263. Risk Summary There are retrospective case reports of neural tube defects in infants whose mothers were exposed to efavirenz-containing regimens in the first trimester of pregnancy.
Prospective pregnancy data from the Antiretroviral Pregnancy Registry are not sufficient to adequately assess this risk. Available data from the Antiretroviral Pregnancy Registry show no difference in the risk of overall major birth defects compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). Although a causal relationship has not been established between exposure to efavirenz in the first trimester and neural tube defects, similar malformations have been observed in studies conducted in monkeys at doses similar to the human dose.
In addition, fetal and embryonic toxicities occurred in rats, at a dose ten times less than the human exposure at recommended clinical dose. Because of the potential risk of neural tube defects, efavirenz should not be used in the first trimester of pregnancy. Advise pregnant women of the potential risk to a fetus.
Data Human Data There are retrospective postmarketing reports of findings consistent with neural tube defects, including meningomyelocele, all in infants of mothers exposed to efavirenz-containing regimens in the first trimester. Based on prospective reports from the Antiretroviral Pregnancy Registry (APR) of approximately 1,000 live births following exposure to efavirenz-containing regimens (including over 800 live births exposed in the first-trimester), there was no difference between efavirenz and overall birth defects compared with the background birth defect rate of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program.
As of the interim APR report issued December 2014, the prevalence of birth defects following first-trimester exposure was 2.3% (95% CI: 1.4% to 3.6%). One of these prospectively reported defects with first-trimester exposure was a neural tube defect. A single case of anophthalmia with first-trimester exposure to efavirenz has also been prospectively reported.
This case also included severe oblique facial clefts and amniotic banding, which have a known association with anophthalmia. Animal Data Effects of efavirenz on embryo-fetal development have been studied in three nonclinical species (cynomolgus monkeys, rats, and rabbits). In monkeys, efavirenz 60 mg/kg/day was administered to pregnant females throughout pregnancy (gestation days 20 through 150).
The maternal systemic drug exposures (AUC) were 1.3 times the exposure in humans at the recommended clinical dose (600 mg/day), with fetal umbilical venous drug concentrations approximately 0.7 times the maternal values. Three of 20 fetuses/infants had one or more malformations; there were no malformed fetuses or infants from placebo-treated mothers. The malformations that occurred in these three monkey fetuses included anencephaly and unilateral anophthalmia in one fetus, microphthalmia in a second, and cleft palate in the third.
There was no NOAEL (no observable adverse effect level) established for this study because only one dosage was evaluated. In ra…
🤰 Pregnancy ▾
8.1Pregnancy Tetratogenic Effects Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to efavirenz tablets during pregnancy. Physicians are encouraged to register patients by calling the Antiretroviral Pregnancy Registry at 1-800-258-4263. Risk Summary There are retrospective case reports of neural tube defects in infants whose mothers were exposed to efavirenz-containing regimens in the first trimester of pregnancy.
Prospective pregnancy data from the Antiretroviral Pregnancy Registry are not sufficient to adequately assess this risk. Available data from the Antiretroviral Pregnancy Registry show no difference in the risk of overall major birth defects compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). Although a causal relationship has not been established between exposure to efavirenz in the first trimester and neural tube defects, similar malformations have been observed in studies conducted in monkeys at doses similar to the human dose.
In addition, fetal and embryonic toxicities occurred in rats, at a dose ten times less than the human exposure at recommended clinical dose. Because of the potential risk of neural tube defects, efavirenz should not be used in the first trimester of pregnancy. Advise pregnant women of the potential risk to a fetus.
Data Human Data There are retrospective postmarketing reports of findings consistent with neural tube defects, including meningomyelocele, all in infants of mothers exposed to efavirenz-containing regimens in the first trimester. Based on prospective reports from the Antiretroviral Pregnancy Registry (APR) of approximately 1,000 live births following exposure to efavirenz-containing regimens (including over 800 live births exposed in the first-trimester), there was no difference between efavirenz and overall birth defects compared with the background birth defect rate of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program.
As of the interim APR report issued December 2014, the prevalence of birth defects following first-trimester exposure was 2.3% (95% CI: 1.4% to 3.6%). One of these prospectively reported defects with first-trimester exposure was a neural tube defect. A single case of anophthalmia with first-trimester exposure to efavirenz has also been prospectively reported.
This case also included severe oblique facial clefts and amniotic banding, which have a known association with anophthalmia. Animal Data Effects of efavirenz on embryo-fetal development have been studied in three nonclinical species (cynomolgus monkeys, rats, and rabbits). In monkeys, efavirenz 60 mg/kg/day was administered to pregnant females throughout pregnancy (gestation days 20 through 150).
The maternal systemic drug exposures (AUC) were 1.3 times the exposure in humans at the recommended clinical dose (600 mg/day), with fetal umbilical venous drug concentrations approximately 0.7 times the maternal values. Three of 20 fetuses/infants had one or more malformations; there were no malformed fetuses or infants from placebo-treated mothers. The malformations that occurred in these three monkey fetuses included anencephaly and unilateral anophthalmia in one fetus, microphthalmia in a second, and cleft palate in the third.
There was no NOAEL (no observable adverse effect level) established for this study because only one dosage was evaluated. In rats, efavirenz was administered either during organogenesis (gestation days 7 to 18) or from gestation day 7 through lactation day 21 at 50, 100, or 200 mg/kg/day. Administration of 200 mg/kg/day in rats was associated with increase in the incidence of early resorptions; and doses 100 mg/kg/day and greater were associated with early neonatal mortality.
The AUC at the NOAEL (50 mg/kg/day) in this rat study was 0.1 times that in humans at the recommend…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety, pharmacokinetic profile, and virologic and immunologic responses of efavirenz tablets were evaluated in antiretroviral-naive and -experienced HIV-1 infected pediatric patients 3 months to 21 years of age in three open-label clinical trials [see Adverse Reactions ( 6.2), Clinical Pharmacology ( 12.3), and Clinical Studies ( 14.2)]. The type and frequency of adverse reactions in these trials were generally similar to those of adult patients with the exception of a higher frequency of rash, including a higher frequency of Grade 3 or 4 rash, in pediatric patients compared to adults [see Warnings and Precautions (5.8) and Adverse Reactions (6.2)].
Use of efavirenz tablets in patients younger than 3 months of age OR less than 3.5 kg body weight is not recommended because the safety, pharmacokinetics, and antiviral activity of efavirenz tablets have not been evaluated in this age group and there is a risk of developing HIV resistance if efavirenz tablets are underdosed. [See Dosage and Administration (2.2)] for dosing recommendations for pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of efavirenz tablets did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Some patients accidentally taking 600 mg twice daily have reported increased nervous system symptoms. One patient experienced involuntary muscle contractions. Treatment of overdose with efavirenz tablets should consist of general supportive measures, including monitoring of vital signs and observation of the patient’s clinical status.
Administration of activated charcoal may be used to aid removal of unabsorbed drug. There is no specific antidote for overdose with efavirenz tablets. Since efavirenz is highly protein bound, dialysis is unlikely to significantly remove the drug from blood.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Efavirenz is an antiviral drug [see Microbiology ( 12.4)].
12.2Pharmacodynamics Cardiac Electrophysiology The effect of efavirenz on the QTc interval was evaluated in an open-label, positive and placebo controlled, fixed single sequence 3-period, 3-treatment crossover QT study in 58 healthy subjects enriched for CYP2B6 polymorphisms. The mean C max of efavirenz in subjects with CYP2B6 *6/*6 genotype following the administration of 600 mg daily dose for 14 days was 2.25-fold the mean C max observed in subjects with CYP2B6 *1/*1 genotype. A positive relationship between efavirenz concentration and QTc prolongation was observed.
Based on the concentration-QTc relationship, the mean QTc prolongation and its upper bound 90% confidence interval are 8.7 ms and 11.3 ms in subjects with CYP2B6*6/*6 genotype following the administration of 600 mg daily dose for 14 days [see Warnings and Precautions (5.2)].
12.3Pharmacokinetics Absorption Peak efavirenz plasma concentrations of 1.6 to 9.1 μM were attained by 5 hours following single oral doses of 100 mg to 1,600 mg administered to uninfected volunteers. Dose-related increases in C max and AUC were seen for doses up to 1,600 mg; the increases were less than proportional suggesting diminished absorption at higher doses. In HIV-1-infected patients at steady state, mean C max , mean C min , and mean AUC were dose proportional following 200 mg, 400 mg, and 600 mg daily doses.
Time-to-peak plasma concentrations were approximately 3 to 5 hours and steady-state plasma concentrations were reached in 6 to 10 days. In 35 patients receiving efavirenz tablets 600 mg once daily, steady-state C max was 12.9 ± 3.7 μM (mean ± SD), steady-state C min was 5.6 ± 3.2 μM, and AUC was 184 ± 73 μM•h. Effect of Food on Oral Absorption: Tablets: Administration of a single 600 mg efavirenz tablet with a high-fat/high-caloric meal (approximately 1,000 kcal, 500 to 600 kcal from fat) was associated with a 28% increase in mean AUC ∞ of efavirenz and a 79% increase in mean C max of efavirenz relative to the exposures achieved under fasted conditions. [ See Dosage and Administration (2) and Patient Counseling Information (17 .] Distribution Efavirenz is highly bound (approximately 99.5 to 99.75%) to human plasma proteins, predominantly albumin.
In HIV-1 infected patients (n=9) who received efavirenz tablets 200 to 600 mg once daily for at least one month, cerebrospinal fluid concentrations ranged from 0.26 to 1.19% (mean 0.69%) of the corresponding plasma concentration. This proportion is approximately 3-fold higher than the non-protein-bound (free) fraction of efavirenz in plasma. Metabolism Studies in humans and in vitro studies using human liver microsomes have demonstrated that efavirenz is principally metabolized by the cytochrome P450 system to hydroxylated metabolites with subsequent glucuronidation of these hydroxylated metabolites.
These metabolites are essentially inactive against HIV-1. The in vitro studies suggest that CYP3A and CYP2B6 are the major isozymes responsible for efavirenz metabolism. Efavirenz has been shown to induce CYP enzymes, resulting in the induction of its own metabolism.
Multiple doses of 200 to 400 mg per day for 10 days resulted in a lower than predicted extent of accumulation (22 to 42% lower) and a shorter terminal half-life of 40 to 55 hours (single dose half-life 52 to 76 hours). Elimination Efavirenz has a terminal half-life of 52 to 76 hours after single doses and 40 to 55 hours after multiple doses. A one-month mass balance/excretion study was conducted using 400 mg per day with a 14 C-labeled dose administered on Day 8.
Approximately 14 to 34% of the radiolabel was recovered in the urine and 16 to 61% was recovered in the feces. Nearly all of the urinary excretion of the radiolabeled drug was in the form of metabolites. Efavirenz accounted for the majority of the total radioactivity measured in feces.
Special Populations Pedi…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Efavirenz is an antiviral drug [see Microbiology ( 12.4)].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.2Tablets Efavirenz tablets, USP are available as follows: Tablets 600 mg are yellow, capsular-shaped, film-coated tablets debossed with ‘H’ on one side and ‘4’ on the other side. Bottles of 30 NDC 31722-504-30 Bottles of 250 NDC 31722-504-25
16.3Storage Efavirenz tablets, USP should be stored at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Efavirenz is an HIV-1 specific, non-nucleoside, reverse transcriptase inhibitor (NNRTI). Efavirenz USP is chemically described as (S)-6-chloro-4-(cyclopropylethynyl)-1,4-dihydro-4-(trifluoromethyl)-2H-3,1-benzoxazin-2-one. Its empirical formula is C 14 H 9 ClF 3 NO 2 and its structural formula is: Efavirenz USP is a white to slightly pink crystalline powder with a molecular mass of 315.68.
It is practically insoluble in water (<10 microgram/mL). Tablets: Efavirenz are available as film-coated tablets for oral administration containing 600 mg of efavirenz USP and the following inactive ingredients: microcrystalline cellulose, sodium lauryl sulfate, croscarmellose sodium, hydroxypropyl cellulose, lactose monohydrate, magnesium stearate. The film coating contains Opadry® Yellow (hypromellose, titanium dioxide, iron oxide yellow and polyethylene glycol).
Efavirenzstructure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Drug Interactions A statement to patients and healthcare providers is included on the product’s bottle labels: ALERT: Find out about medicines that should NOT be taken with efavirenz tablets. Efavirenz may interact with some drugs; therefore, patients should be advised to report to their doctor the use of any other prescription or nonprescription medication.
General Information for Patients Patients should be informed that efavirenz tablets are not a cure for HIV-1 infection and patients may continue to experience illnesses associated with HIV-1 infection, including opportunistic infections. Patients should remain under the care of a physician while taking efavirenz tablets. Patients should be advised to avoid doing things that can spread HIV-1 infection to others. • Do not share or reuse needles or other injection equipment. • Do not share personal items that can have blood or body fluids on them, like toothbrushes and razor blades. • Do not have any kind of sex without protection.
Always practice safer sex by using a latex or polyurethane condom to lower the chance of sexual contact with semen, vaginal secretions, or blood. • Do not breastfeed. Mothers with HIV-1 should not breastfeed because HIV-1 can be passed to the baby in breast milk. Dosing Instructions Patients should be advised to take efavirenz tablets every day as prescribed.
If a patient forgets to take efavirenz tablets, tell the patient to take the missed dose right away, unless it is almost time for the next dose. Advise the patient not to take 2 doses at one time and to take the next dose at the regularly scheduled time. Advise the patient to ask a healthcare provider if he/she needs help in planning the best times to take his/her medicine.
Efavirenz tablets must always be used in combination with other antiretroviral drugs. Patients should be advised to take efavirenz tablets on an empty stomach, preferably at bedtime. Taking efavirenz tablets with food increases efavirenz concentrations and may increase the frequency of adverse reactions.
Dosing at bedtime may improve the tolerability of nervous system symptoms [see Dosage and Administration (2) and Adverse Reactions (6.1)]. Healthcare providers should assist parents or caregivers in determining the best efavirenz tablets dosing schedule for infants and young children. Patients should call their healthcare provider or pharmacist if they have any questions.
Nervous System Symptoms Patients should be informed that central nervous system symptoms (NSS) including dizziness, insomnia, impaired concentration, drowsiness, and abnormal dreams are commonly reported during the first weeks of therapy with efavirenz tablets [see Warnings and Precautions (5.6)]. Dosing at bedtime may improve the tolerability of these symptoms, which are likely to improve with continued therapy. Patients should be alerted to the potential for additive effects when efavirenz tablets are used concomitantly with alcohol or psychoactive drugs.
Patients should be instructed that if they experience NSS they should avoid potentially hazardous tasks such as driving or operating machinery. Psychiatric Symptoms Patients should be informed that serious psychiatric symptoms including severe depression, suicide attempts, aggressive behavior, delusions, paranoia, psychosis-like symptoms and catatonia have been reported in patients receiving efavirenz tablets [see Warnings and Precautions (5.5)]. If they experience severe psychiatric adverse experiences they should seek immediate medical evaluation.
Patients should be advised to inform their physician of any history of mental illness or substance abuse. Rash Patients should be informed that a common side effect is rash [see Warnings and Precautions ( 5.8)]. Rashes usually go away without any change in treatment.
However, since rash may be serious, patients should…