
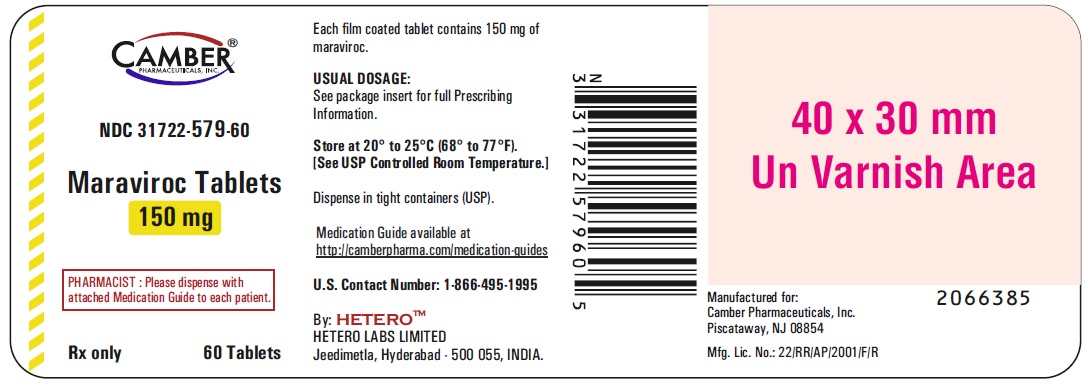
Maraviroc 150 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the CCR5 Co-receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Maraviroc is used to treat a certain type of human immunodeficiency virus (HIV) infection. Maraviroc is in a class of medications called HIV entry and fusion inhibitors. It works by decreasing the amount of HIV in the blood. Although maraviroc does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗- Maraviroc is not a cure. It's an antiretroviral drug that helps control HIV by blocking the virus from entering your immune cells. When taken consistently with your other HIV medic...
- What exactly is maraviroc treating — is it a cure for HIV?
- Maraviroc only works against a specific strain of HIV called CCR5-tropic HIV. The test — called a tropism assay — checks whether your virus uses the CCR5 doorway to enter cells. If...
- Why did my doctor order a special test before prescribing this?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Maraviroc — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 1DI56QDM62
A natural fatty substance from soybeans that helps mix oil and water-based ingredients together. It acts as an emulsifier and lubricant in medicines to improve texture and help the product break down properly in your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.150 | $548.98 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $16.08 | $964.57 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $17.26 | $1,035.74 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Maraviroc 150 mgthis 31722-0579-60 | Camber | 60 tablets | $9.150 | AB | Availability likely | — |
| Maraviroc 150 mg 70710-1930-06 | Zydus | 60 tablets | $9.150 | AB | Availability likely | — |
| Maraviroc 150 mg 72319-0024-02 | i3 | 60 tablets | $9.150 | AB | Availability likely | — |
| Selzentry 150 mg 49702-0223-18 | ViiV | 60 tablets | $28.016 | AB | Availability likely | +206% |
| Selzentry 150 mg 50090-6238-00 | A-S | 60 tablets | — | AB | FDA listed | — |
| Maraviroc 150 mg 68475-0008-01 | Navinta | 60 tablets | — | AB | FDA listed | — |
| Maraviroc 150 mg 68554-3079-00 | Hetero | 60 tablets | — | AB | Discontinued | — |
| Maraviroc 150 mg 72865-0231-60 | XLCare | 60 tablets | — | AB | FDA listed | — |
| Maraviroc 150 mg 73141-0024-02 | A2A | 60 tablets | — | AB | FDA listed | — |
| Maraviroc 150 mg 50090-8010-00 | A-S | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 31722-0579-60 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE (31722-579-60) | 2022-02-06 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING WARNING: HEPATOTOXICITY Hepatotoxicity has been reported with use of maraviroc tablets. Severe rash or evidence of a systemic allergic reaction (e.g., fever, eosinophilia, or elevated IgE) prior to the development of hepatotoxicity may occur. Patients with signs or symptoms of hepatitis or allergic reaction following use of maraviroc tablets should be evaluated immediately [see Warnings and Precautions ( 5.1 )].
WARNING: HEPATOTOXICITY See full prescribing information for complete boxed warning. • Hepatotoxicity has been reported which may be preceded by severe rash or other features of a systemic allergic reaction (e.g., fever, eosinophilia, or elevated IgE). ( 5.1 ) • Immediately evaluate patients with signs or symptoms of hepatitis or allergic reaction. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Maraviroc tablets are indicated in combination with other antiretroviral agents for the treatment of only CCR5-tropic human immunodeficiency virus type 1 (HIV-1) infection in adult and pediatric patients 2 years of age and older weighing at least 10 kg. Limitations of Use: • Maraviroc tablets are not recommended in patients with dual/mixed- or CXCR4-tropic HIV-1 [ see Microbiology ( 12.4 ) ]. Maraviroc tablet is a CCR5 co-receptor antagonist indicated in combination with other antiretroviral agents for the treatment of only CCR5-tropic HIV-1 infection in adults and pediatric patients 2 years of age and older weighing at least 10 kg.
( 1 ) Limitations of Use: • Not recommended in patients with dual/mixed- or CXCR4-tropic HIV-1. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Prior to initiation of maraviroc tablets for treatment of HIV-1 infection, test all patients for CCR5 tropism using a highly sensitive tropism assay. ( 2.1 ) • Maraviroc tablets are taken twice daily by mouth and may be taken with or without food. Maraviroc tablets must be given in combination with other antiretroviral medications.
( 2.2 ) Recommended Dosage in Adult Patients: ( 2.3 ) Concomitant Medications Dosage of Maraviroc tablets When given with potent cytochrome P450 (CYP)3A inhibitors (with or without potent CYP3A inducers) including PIs (except tipranavir/ritonavir) ( 2.3 , 7.1 ) 150 mg twice daily With NRTIs, tipranavir/ritonavir, nevirapine, raltegravir, and other drugs that are not potent CYP3A inhibitors or CYP3A inducers ( 2.3 , 7.1 ) 300 mg twice daily With potent and moderate CYP3A inducers including efavirenz (without a potent CYP3A inhibitor) ( 2.3 , 7.1 ) 600 mg twice daily A more complete list of coadministered drugs is listed in Dosage and Administration.
( 2 ) Recommended Dosage in Pediatric Patients 2 years and older and weighing at Least 10 kg: Administer twice daily. Dosage should be based on body weight (kg) and concomitant medications and should not exceed the recommended adult dose. ( 2.4 ) Recommended Dosage in Patients with Renal Impairment: Dose adjustment may be necessary in adult patients with renal impairment.
( 2.5 )
2.1Testing prior to Initiation of Maraviroc Tablets Prior to initiation of maraviroc tablets for treatment of HIV-1 infection, test all patients for CCR5 tropism using a highly sensitive tropism assay. Maraviroc tablets are recommended for patients with only CCR5-tropic HIV-1 infection. Outgrowth of pre-existing low-level CXCR4- or dual/mixed-tropic HIV-1 not detected by tropism testing at screening has been associated with virologic failure on maraviroc tablets [ see Microbiology ( 12.4 ), Clinical Studies ( 14.1 ) ].
Monitor patients for ALT, AST, and bilirubin prior to initiation of maraviroc tablets and at other time points during treatment as clinically indicated [see Warnings and Precautions ( 5.1 )] .
2.2General Dosing Recommendations • Maraviroc tablets are taken twice daily by mouth and may be taken with or without food. • Maraviroc tablets must be given in combination with other antiretroviral medications. • The recommended dosage of maraviroc tablets differs based on concomitant medications due to drug interactions.
2.3Recommended Dosage in Adult Patients with Normal Renal Function Table 1 displays oral dosage of maraviroc tablets based on different concomitant medications [ see Drug Interactions ( 7.1 ) ]. Table 1. Recommended Dosage in Adults Concomitant Medications Dosage of Maraviroc Tablets Potent cytochrome P450 (CYP)3A inhibitors (with or without a potent CYP3A inducer) a 150 mg twice daily Noninteracting concomitant medications b 300 mg twice daily Potent and moderate CYP3A inducers (without a potent CYP3A inhibitor) c 600 mg twice daily a Potent CYP3A inhibitors (with or without a potent CYP3A inducer) including: clarithromycin, cobicistat, elvitegravir/ritonavir, itraconazole, ketoconazole, nefazodone, protease inhibitors (except tipranavir/ritonavir), telithromycin. b Noninteracting concomitant medications include all medications that are not potent CYP3A inhibitors or inducers such as: dolutegravir, enfuvirtide, nevirapine, all nucleoside reverse transcriptase inhibitors (NRTIs), raltegravir, and tipranavir/ritonavir. c Potent and moderate CYP3A inducers (without a potent CYP3A inhibitor) including: carbamazepine, efavirenz, etravirine, phenobarbital, phenytoin, and rifampin.
2.4Recommended Dosage in Pediatric Patients with Normal Renal Function The recommended dosage of maraviroc tablets should be based on body weight (kg) and should not exceed the recommended adult dose. The recommended dosage also differs based on concomitant medications due to drug interactions (Table 2 and Table 3) [ see Drug Interactions ( 7.1 ), Use…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • 150 mg white to off-white colored, oval, biconvex, film coated tablets debossed with ‘J’ on one side and ‘62’ on the other side. • 300 mg white to off-white colored, oval, biconvex, film coated tablets debossed with ‘J’ on one side and ‘63’ on the other side. Tablets: 150 mg and 300 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Maraviroc tablets are contraindicated in patients with severe renal impairment or ESRD (CrCl less than 30 mL per minute) who are concomitantly taking potent CYP3A inhibitors or inducers [ see Warnings and Precautions ( 5.3 ) ]. • Maraviroc tablets are contraindicated in patients with severe renal impairment or end-stage renal disease (ESRD) (CrCl less than 30 mL per minute) who are concomitantly taking potent CYP3A inhibitors or inducers. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hepatotoxicity accompanied by severe rash or systemic allergic reaction, including potentially life-threatening events, has been reported. Hepatic laboratory parameters including ALT, AST, and bilirubin should be obtained prior to starting maraviroc tablets and at other time points during treatment as clinically indicated. If rash or symptoms or signs of hepatitis or allergic reaction develop, hepatic laboratory parameters should be monitored and discontinuation of treatment should be considered.
When administering maraviroc tablets to patients with pre-existing liver dysfunction or who are co-infected with hepatitis B and/or C virus, additional monitoring may be warranted. ( 5.1 ) • Severe and potentially life-threatening skin and hypersensitivity reactions have been reported in patients taking maraviroc. This includes cases of Stevens-Johnson syndrome, hypersensitivity reaction, and toxic epidermal necrolysis.
Immediately discontinue maraviroc and other suspected agents if signs or symptoms of severe skin or hypersensitivity reactions develop and monitor clinical status, including liver aminotransferases, closely. ( 5.2 ) • More cardiovascular events, including myocardial ischemia and/or infarction, were observed in treatment-experienced subjects who received maraviroc. Additional monitoring may be warranted.
( 5.3 ) • If patients with severe renal impairment or ESRD receiving maraviroc (without concomitant CYP3A inducers or inhibitors) experience postural hypotension, the dose of maraviroc should be reduced from 300 mg twice daily to 150 mg twice daily. ( 5.3 )
5.1Hepatotoxicity Hepatotoxicity with allergic features including life-threatening events has been reported in clinical trials and postmarketing. Severe rash or evidence of systemic allergic reaction including drug-related rash with fever, eosinophilia, elevated IgE, or other systemic symptoms have been reported in conjunction with hepatotoxicity [ see Warnings and Precautions ( 5.2 ) ]. These events occurred approximately 1 month after starting treatment.
Among reported cases of hepatitis, some were observed in the absence of allergic features or with no pre-existing hepatic disease. Appropriate laboratory testing including ALT, AST, and bilirubin should be conducted prior to initiating therapy with maraviroc and at other time points during treatment as clinically indicated. Hepatic laboratory parameters should be obtained in any patient who develops rash, or signs or symptoms of hepatitis, or allergic reaction.
Discontinuation of maraviroc should be considered in any patient with signs or symptoms of hepatitis, or with increased liver transaminases combined with rash or other systemic symptoms. When administering maraviroc to patients with pre-existing liver dysfunction or who are co-infected with hepatitis B and/or C virus, additional monitoring may be warranted. The safety and efficacy of maraviroc have not been specifically studied in patients with significant underlying liver disorders.
5.2Severe Skin and Hypersensitivity Reactions Severe, potentially life-threatening skin and hypersensitivity reactions have been reported in patients taking maraviroc, in most cases concomitantly with other drugs associated with these reactions. These include cases of Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug rash with eosinophilia and systemic symptoms (DRESS) [ see Adverse Reactions (6.3) ]. The cases were characterized by features including rash, constitutional findings, and sometimes organ dysfunction, including hepatic failure.
Discontinue maraviroc and other suspected agents immediately if signs or symptoms of severe skin or hypersensitivity reactions develop (including, but not limited to, severe rash or rash accompanied by fever, malaise, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, lip swelling, eosinophilia). Delay in stopping treatment with maraviroc or other suspect drugs…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: • Hepatotoxicity [ see Boxed Warning, Warnings and Precautions ( 5.1 ) ] • Severe Skin and Hypersensitivity Reactions [ see Warnings and Precautions ( 5.2 ) ] • Cardiovascular Events [ see Warnings and Precautions ( 5.3 ) ] • The most common adverse events in treatment-experienced adult subjects (greater than 8% incidence) which occurred at a higher frequency compared with placebo are upper respiratory tract infections, cough, pyrexia, rash, and dizziness.
( 6.1 ) • The most common adverse events in treatment-naive adult subjects (greater than 8% incidence) which occurred at a higher frequency than the comparator arm are upper respiratory tract infections, bronchitis, flatulence, bloating and distention, upper respiratory tract signs and symptoms, and gastrointestinal atonic and hypomotility disorders. ( 6.1 ) • The most common adverse reactions in treatment-experienced pediatric subjects (greater than or equal to 3% incidence) are vomiting, abdominal pain, diarrhea, nausea, and dizziness.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Hetero Labs Limited at 1-866-495-1995 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clinical Trials Experience in Adult Subjects Treatment-Experienced Subjects: The safety profile of maraviroc is primarily based on 840 HIV-1-infected subjects who received at least 1 dose of maraviroc during two Phase 3 trials.
A total of 426 of these subjects received the indicated twice-daily dosing regimen. Assessment of treatment-emergent adverse events is based on the pooled data from 2 trials in subjects with CCR5-tropic HIV-1 (A4001027 and A4001028). The median duration of therapy with maraviroc for subjects in these trials was 48 weeks, with the total exposure on maraviroc twice daily at 309 patient-years versus 111 patient-years on placebo each administered with optimized background therapy (OBT).
The population was 89% male and 84% white, with mean age of 46 years (range: 17 to 75 years). Subjects received dose equivalents of 300 mg maraviroc once or twice daily. The most common adverse events reported with twice-daily therapy with maraviroc with frequency rates higher than placebo, regardless of causality, were upper respiratory tract infections, cough, pyrexia, rash, and dizziness.
In these 2 trials, the rate of discontinuation due to adverse events was 5% for subjects who received maraviroc twice daily + OBT as well as those who received placebo + OBT. Most of the adverse events reported were judged to be mild to moderate in severity. The data described below occurred with twice-daily dosing of maraviroc.
The total numbers of subjects reporting infections were 233 (55%) and 84 (40%) in the group receiving maraviroc twice daily and the placebo group, respectively. Correcting for the longer duration of exposure on maraviroc compared with placebo, the exposure-adjusted frequency (rate per 100 subject-years) of these events was 133 for both maraviroc twice daily and placebo. Dizziness or postural dizziness occurred in 8% of subjects on either maraviroc or placebo, with 2 subjects (0.5%) on maraviroc permanently discontinuing therapy (1 due to syncope, 1 due to orthostatic hypotension) versus 1 subject on placebo (0.5%) permanently discontinuing therapy due to dizziness.
Treatment-emergent adverse events, regardless of causality, from Trials A4001027 and A4001028 are summarized in Table 5. Selected events occurring at greater than or equal to 2% of subjects and at a numerically higher rate in subjects treated with maraviroc are included; events that occurred at the same or higher rate on placebo are not…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Coadministration with CYP3A inhibitors, including protease inhibitors (except tipranavir/ritonavir), will increase the concentration of maraviroc. ( 7.1 ) • Coadministration with CYP3A inducers, including efavirenz, may decrease the concentration of maraviroc. ( 7.1 ) • Coadministration with St. John’s wort is not recommended. ( 7.1 ).
7.1Effect of Concomitant Drugs on the Pharmacokinetics of Maraviroc Maraviroc is metabolized by CYP3A and is also a substrate for P-glycoprotein (P-gp), organic anion-transporting polypeptide (OATP)1B1, and multidrug resistance-associated protein (MRP)2. The pharmacokinetics of maraviroc are likely to be modulated by inhibitors and inducers of CYP3A and P-gp and may be modulated by inhibitors of OATP1B1 and MRP2. Therefore, a dosage adjustment may be required when maraviroc is coadministered with those drugs [ see Dosage and Administration ( 2.3 , 2.4 ) ].
Concomitant use of maraviroc and St. John's wort ( Hypericum perforatum ) or products containing St. John's wort is not recommended.
Coadministration of maraviroc with St. John's wort is expected to substantially decrease maraviroc concentrations and may result in suboptimal levels of maraviroc and lead to loss of virologic response and possible resistance to maraviroc. Additional drug interaction information is available [ see Clinical Pharmacology ( 12.3 ) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Women infected with HIV should be instructed not to breastfeed due to the potential for HIV transmission. ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to maraviroc during pregnancy. Physicians are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Limited data on the use of maraviroc during pregnancy from the APR and case reports are not sufficient to inform a drug-associated risk of birth defects and miscarriage.
In animal reproduction studies, no evidence of adverse developmental outcomes was observed with maraviroc. During organogenesis in the rat and rabbit, systemic exposures (AUC) to maraviroc were approximately 20 times (rats) and 5 times (rabbits) the exposure in humans at the recommended 300-mg twice-daily dose. In the rat pre- and post-natal development study, maternal systemic exposure (AUC) to maraviroc was approximately 14 times the exposure in humans at the recommended 300-mg twice-daily dose ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data: Maraviroc was administered orally to pregnant rats (up to 1,000 mg per kg per day) and rabbits (up to 75 mg per kg per day) on gestation Days 6 to 17 and 7 to 19, respectively. No adverse effects on embryo-fetal development were observed at these dose levels, resulting in exposures (AUC) approximately 20 times (rats) and 5 times (rabbits) higher than human exposures at the recommended daily dose. In the rat pre- and post-natal development study, maraviroc was administered orally at up to 1,000 mg per kg per day on gestation Day 6 to lactation/post-partum Day 20, with development of the offspring (including fertility and reproductive performance) unaffected by maternal administration of maraviroc at an exposure (AUC) approximately 14 times higher than human exposure at the recommended daily dose.
8.2Lactation Risk Summary The Centers for Disease Control and Prevention recommend that HIV-1–infected mothers in the United States not breastfeed their infants to avoid risking postnatal transmission of HIV-1 infection. There are no data on the presence of maraviroc in human milk, the effects on the breastfed infant, or the effects on milk production. When administered to lactating rats, maraviroc was present in milk ( see Data ).
Because of the potential for (1) HIV transmission (in HIV-negative infants), (2) developing viral resistance (in HIV-positive infants), and (3) serious adverse reactions in a breastfed infant similar to those seen in adults, instruct mothers not to breastfeed if they are receiving maraviroc. Data Maraviroc (and related metabolites) was excreted into the milk of lactating rats following a single oral dose of maraviroc (100 mg per kg) on lactation Day 12, with a maximal milk concentration achieved one hour post-administration at a milk concentration approximately 2.5 times that of maternal plasma concentrations.
8.4Pediatric Use The safety and efficacy of maraviroc have been established in pediatric patients aged from aged 2 to less than 18 years. The use of maraviroc in pediatric patients was supported by pharmacokinetic and safety data described below and by previous demonstration of efficacy in adult patients [ see Indications and Usage (1)], Dosage and Administration ( 2.4 ) ]. HIV-1–Infected Pediatric Patients Aged 2 to Less Than 18 Years : The safety, pharmacokinetic profile, and antiviral activity of maraviroc were evaluated in treatment-experienced, CCR5- tropic, HIV-1–infected pediatric subjec…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to maraviroc during pregnancy. Physicians are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Limited data on the use of maraviroc during pregnancy from the APR and case reports are not sufficient to inform a drug-associated risk of birth defects and miscarriage.
In animal reproduction studies, no evidence of adverse developmental outcomes was observed with maraviroc. During organogenesis in the rat and rabbit, systemic exposures (AUC) to maraviroc were approximately 20 times (rats) and 5 times (rabbits) the exposure in humans at the recommended 300-mg twice-daily dose. In the rat pre- and post-natal development study, maternal systemic exposure (AUC) to maraviroc was approximately 14 times the exposure in humans at the recommended 300-mg twice-daily dose ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data: Maraviroc was administered orally to pregnant rats (up to 1,000 mg per kg per day) and rabbits (up to 75 mg per kg per day) on gestation Days 6 to 17 and 7 to 19, respectively. No adverse effects on embryo-fetal development were observed at these dose levels, resulting in exposures (AUC) approximately 20 times (rats) and 5 times (rabbits) higher than human exposures at the recommended daily dose. In the rat pre- and post-natal development study, maraviroc was administered orally at up to 1,000 mg per kg per day on gestation Day 6 to lactation/post-partum Day 20, with development of the offspring (including fertility and reproductive performance) unaffected by maternal administration of maraviroc at an exposure (AUC) approximately 14 times higher than human exposure at the recommended daily dose.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of maraviroc have been established in pediatric patients aged from aged 2 to less than 18 years. The use of maraviroc in pediatric patients was supported by pharmacokinetic and safety data described below and by previous demonstration of efficacy in adult patients [ see Indications and Usage (1)], Dosage and Administration ( 2.4 ) ]. HIV-1–Infected Pediatric Patients Aged 2 to Less Than 18 Years : The safety, pharmacokinetic profile, and antiviral activity of maraviroc were evaluated in treatment-experienced, CCR5- tropic, HIV-1–infected pediatric subjects aged 2 to less than 18 years weighing at least 10 kg in an open-label, multicenter clinical trial, A4001031 [ see Adverse Reactions ( 6.1 ), Clinical Studies ( 14.2 ) ].
Pharmacokinetics were evaluated in a total of 98 pediatric subjects: 85 subjects received maraviroc and concomitant medications that included potent CYP3A inhibitors with or without potent CYP3A inducers, 10 subjects received maraviroc and noninteracting medications (not containing potent CYP3A inhibitors or potent CYP3A inducers), and three subjects received maraviroc and medications that included potent CYP3A inducers without potent CYP3A inhibitors [ see Clinical Pharmacology ( 12.3 ) ]. There are insufficient data to make dosing recommendations for use of maraviroc in pediatric patients concomitantly receiving potent CYP3A inhibitors and weighing less than 10 kg, or in any pediatric patients concomitantly receiving potent CYP3A inducers without a potent CYP3A inhibitor [ see Dosage and Administration ( 2.4 , 2.5 ) ].
Maraviroc is not recommended in pediatric patients weighing less than 10 kg.
🧓 Geriatric Use ▾
8.5Geriatric Use There were insufficient numbers of subjects aged 65 and over in the clinical trials to determine whether they respond differently from younger subjects. In general, caution should be exercised when administering maraviroc in elderly patients, also reflecting the greater frequency of decreased hepatic and renal function, of concomitant disease and other drug therapies.
🆘 Overdosage ▾
10 OVERDOSAGE The highest single dose administered in clinical trials was 1,200 mg. The dose-limiting adverse event was postural hypotension, which was observed at 600 mg. While the recommended dose for maraviroc in patients receiving a CYP3A inducer without a CYP3A inhibitor is 600 mg twice daily, this dose is appropriate due to enhanced metabolism.
Prolongation of the QT interval was seen in dogs and monkeys at plasma concentrations 6 and 12 times, respectively, those expected in humans at the intended exposure of 300-mg equivalents twice daily. However, no significant QT prolongation was seen in the trials in treatment-experienced subjects with HIV using the recommended doses of maraviroc, or in a specific pharmacokinetic trial to evaluate the potential of maraviroc to prolong the QT interval [ see Clinical Pharmacology ( 12.2 ) ]. There is no specific antidote for overdose with maraviroc.
Treatment of overdose should consist of general supportive measures including keeping the patient in a supine position, careful assessment of patient vital signs, blood pressure, and ECG. Administration of activated charcoal may also be used to aid in removal of unabsorbed drug. Hemodialysis had a minimal effect on maraviroc clearance and exposure in a trial in subjects with ESRD [ see Clinical Pharmacology ( 12.3 ) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Maraviroc is an HIV-1 antiviral drug [ see Microbiology ( 12.4 ) ].
12.2Pharmacodynamics Exposure-Response Relationship in Treatment-Experienced Adult Subjects The relationship between maraviroc, modeled plasma trough concentration (C min ) (1 to 9 samples per subject taken on up to 7 visits), and virologic response was evaluated in 973 treatment-experienced HIV-1-infected subjects with varied optimized background antiretroviral regimens in Trials A4001027 and A4001028. The C min , baseline viral load, baseline CD4+ cell count, and overall sensitivity score (OSS) were found to be important predictors of virologic success (defined as viral load less than 400 copies per mL at 24 weeks).
Table 9 illustrates the proportions of subjects with virologic success (%) within each C min quartile for 150-mg twice-daily and 300-mg twice-daily groups. Table 9. Treatment-Experienced Subjects with Virologic Success by Cmin Quartile (Q1 to Q4) 150 mg Twice Daily (with CYP3A Inhibitors) 300 mg Twice Daily (without CYP3A Inhibitors) n Median C min % Subjects with Virologic Success n Median C min % Subjects with Virologic Success Placebo 160 - 30.6 35 -
28.6Q1 78 33 52.6 22 13
50.0Q2 77 87 63.6 22 29
68.2Q3 78 166 78.2 22 46
63.6Q4 78 279 74.4 22 97
68.2Exposure-Response Relationship in Treatment-Naive Adult Subjects The relationship between maraviroc, modeled plasma trough concentration (C min ) (1 to 12 samples per subject taken on up to 8 visits), and virologic response was evaluated in 294 treatment-naive HIV-1-infected subjects receiving maraviroc 300 mg twice daily in combination with lamivudine/zidovudine in Trial A4001026. Table 10 illustrates the proportion (%) of subjects with virologic success less than 50 copies per mL at 48 weeks within each C min quartile for the 300-mg twice-daily dose.
Table 10. Treatment-Naive Subjects with Virologic Success by C min Quartile (Q1 to Q4) 300 mg Twice Daily n Median C min % Subjects with Virologic Success Q1 75 23
57.3 Q2 72 39
72.2 Q3 73 56
74.0 Q4 74 81
83.8Eighteen of 75 (24%) subjects in Q1 had no measurable maraviroc concentration on at least one occasion versus 1 of 73 and 1 of 74 in Q3 and Q4, respectively. Effects on Electrocardiogram A placebo-controlled, randomized, crossover trial to evaluate the effect on the QT interval of healthy male and female volunteers was conducted with 3 single oral doses of maraviroc and moxifloxacin. The placebo-adjusted mean maximum (upper 1-sided 95% CI) increases in QTc from baseline after 100, 300, and 900 mg of maraviroc were -2 (0), -1 (1), and 1 (3) msec, respectively, and 13 (15) msec for moxifloxacin 400 mg.
No subject in any group had an increase in QTc of greater than or equal to 60 msec from baseline. No subject experienced an interval exceeding the potentially clinically relevant threshold of 500 msec.
12.3Pharmacokinetics Table 11. Mean Maraviroc Pharmacokinetic Parameters in Adults Patient Population Maraviroc Dose n AUC 12 (ng.h/mL) C max (ng/mL) C min (ng/mL) Healthy volunteers (Phase 1) 300 mg twice daily 64 2,908 888
43.1 Asymptomatic HIV subjects (Phase 2a) 300 mg twice daily 8 2,550 618
33.6Treatment-experienced HIV subjects (Phase 3) a 300 mg twice daily 94 1,513 266 37.2 150 mg twice daily (+ CYP3A inhibitor) 375 2,463 332 101 Treatment-naiveHIV subjects (Phase 2b/3) a 300 mg twice daily 344 1,865 287 60 a The estimated exposure is lower compared with other trials possibly due to sparse sampling, food effect, compliance, and concomitant medications. Absorption Peak maraviroc plasma concentrations are attained 0.5 to 4 hours following single oral doses of 1 to1,200 mg administered to uninfected volunteers.
The pharmacokinetics of oral maraviroc are not dose proportional over the dose range. The absolute bioavailability of a 100-mg dose is 23% and is predicted to be 33% at 300 mg. Maraviroc is a substrate for the efflux transporter P-gp.
Effect of Food on Oral Absorption: Coadminis…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Maraviroc is an HIV-1 antiviral drug [ see Microbiology ( 12.4 ) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Maraviroc film-coated tablets are available as follows: 150 mg white to off-white colored, oval, biconvex, film coated tablets debossed with ‘J’ on one side and ‘62’ on the other side. Bottle of 60 tablets (NDC 31722-579-60) 300 mg white to off-white colored, oval, biconvex, film coated tablets debossed with ‘J’ on one side and ‘63’ on the other side. Bottle of 60 tablets (NDC 31722-580-60) Maraviroc film-coated tablets should be stored at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.]
📋 Description ▾
11 DESCRIPTION Maraviroc is a selective, slowly reversible, small molecule antagonist of the interaction between human CCR5 and HIV-1 gp120. Blocking this interaction prevents CCR5-tropic HIV-1 entry into cells. Maraviroc is available as film-coated tablets for oral administration containing either 150 or 300 mg of maraviroc and the following inactive ingredients: colloidal silicon dioxide, lactose monohydrate, magnesium stearate, microcrystalline cellulose, sodium starch glycolate.
The tablets are coated with, Opadry II White contains lecithin, polyethylene glycol, polyvinyl alcohol, talc and titanium dioxide. Maraviroc is chemically described as 4,4-Difluoro-N-[(1S)-3-[(3-exo)-3-[3-methyl-5- (1-methylethyl)-4H-1,2,4-triazol-4-yl]-8-azabicyclo[3.2.1]oct-8-yl]-1-phenylpropyl]-cyclohexane carboxamide. The molecular formula is C 29 H 41 F 2 N 5 O and the structural formula is: Maraviroc is a white to pale colored powder with a molecular weight of 513.67.
It is freely soluble in methanol and hygroscopic. maraviroctabletstructure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Hepatotoxicity Inform patients that hepatotoxicity, including life-threatening cases, has been reported with maraviroc tablets; therefore, it is important to inform the healthcare professional if patients have underlying hepatitis B or C or elevations in liver-associated tests prior to treatment. Inform patients to stop maraviroc tablets and seek medical evaluation immediately if they develop signs or symptoms of hepatitis or allergic reaction following use of maraviroc tablets.
Advise patients that laboratory tests for liver enzymes and bilirubin will be ordered prior to starting maraviroc tablets, at other times during treatment, and if they develop severe rash or signs and symptoms of hepatitis or an allergic reaction on treatment [ see Dosage and Administration ( 2.1 ), Warnings and Precautions ( 5.1 , 5.2 ) ]. Cardiovascular Events When administering maraviroc tablets in patients with cardiovascular comorbidities, a history of postural hypotension or receiving concomitant medication known to lower blood pressure, advise patients that they may be at increased risk for cardiovascular events.
Advise patients to avoid driving or operating machinery if they experience dizziness while taking maraviroc tablets [ see Warnings and Precautions ( 5.3 ) ]. Drug Interactions Advise patients to inform their healthcare provider of concomitant HIV medications as dosage of maraviroc tablets may be modified depending on other HIV medications taken with maraviroc tablets. Advise patients that coadministration of maraviroc tablets with St.
John’s wort is not recommended as it can lead to loss of virologic response and possible resistance to maraviroc tablets [ see Dosage and Administration ( 2.2 ), Drug Interactions ( 7.1 ) ]. Missed Dosage Inform patients that it is important to take maraviroc tablets in combination with other antiretroviral medications on a regular dosing schedule with or without food. Advise patients to avoid missing doses as it can result in development of resistance.
Instruct patients that if they miss a dose, to take it as soon as they remember. Advise patients not to double their next dose or take more than the prescribed dose [ see Dosage and Administration ( 2.2 ) ]. Pregnancy Inform patients that there is insufficient data on the safety of maraviroc tablets in pregnancy.
Inform patients that there is an antiretroviral pregnancy registry that monitors pregnancy outcomes in women exposed to maraviroc tablets during pregnancy [ see Use in Specific Populations ( 8.1 ) ]. Lactation Instruct women with HIV-1 infection not to breastfeed because HIV-1 can be passed to the baby in breast milk [ see Use in Specific Populations ( 8.2 ) ]. The brands listed are trademarks of their respective owners and are not trademarks of the Hetero Labs Limited.
Manufactured for: Camber Pharmaceuticals, Inc., Piscataway, NJ 08854 Manufactured by: HETERO TM Hetero Labs Limited Jeedimetla, Hyderabad - 500 055, India Issued: 01/2022 maraviroctabletcamberlogo1