
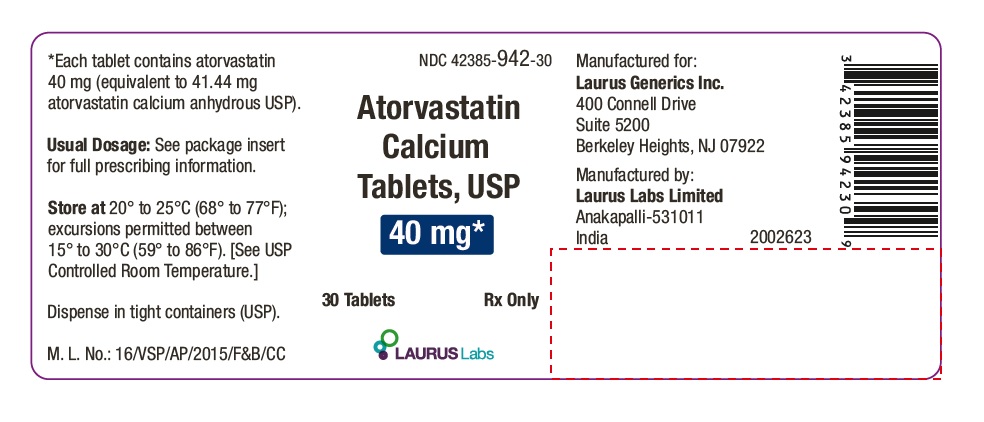
Atorvastatin Calcium 40 mg Tablet, Film Coated, 500-count
Other active recalls for Atorvastatin Calcium (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the HMG-CoA Reductase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It mainly lowers your LDL — the "bad" cholesterol — and triglycerides, while nudging your HDL ("good" cholesterol) a little higher. Over time, keeping those numbers in a healthier...
- What exactly is atorvastatin supposed to do for me?
- Honestly, no — the cholesterol-lowering effect is the same whether you take it in the morning or at night, and whether you eat beforehand or not. The most important thing is that y...
- Does it matter what time of day I take it, or whether I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Atorvastatin Calcium — tap one for details:
Atorvastatin Calcium may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H0G9379FGK
Calcium carbonate is a white mineral powder used as a filler and buffering agent in medicines. It helps give tablets their bulk and size while neutralizing stomach acid in some formulations.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII UKE75GEA7F
Hydroxypropyl cellulose is a plant-based polymer used as a binder and thickener. It helps hold tablet ingredients together, controls how fast the medicine dissolves, and improves the texture of liquid formulations.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.037 | $18.50 / 500 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.5055 | $252.75 / 500 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.0927 | $46.35 / 500 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Atorvastatin Calcium 40 mg 00093-5058-10 | Teva | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 00378-3952-05 | Mylan | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 00480-3587-10 | Teva | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 00904-6292-06 | Major | 1 tablet | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 16571-0138-09 | Rising | 90 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 16714-0175-01 | NORTHSTAR | 90 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 31722-0426-05 | Camber | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin calcium 40 mg 33342-0317-10 | Macleods | 90 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mgthis 42385-0942-05 | Laurus | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 42571-0174-10 | Micro | 1000 tablets | $0.037 | AB | Discontinued | — |
| Atorvastatin Calcium 40 mg 43598-0101-05 | Dr. | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 43598-0832-05 | Dr. | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 50228-0453-10 | ScieGen | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 50268-0095-15 | AvPAK | 1 tablet | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 51079-0210-20 | Mylan | 1 tablet | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 55111-0123-05 | Dr. | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 67877-0513-05 | Ascend | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 68084-0099-01 | American | 1 tablet | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 70377-0079-11 | Biocon | 90 tablets | $0.037 | AB | Availability likely | — |
| atorvastatin calcium 40 mg 70710-1772-00 | Zydus | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin calcium 40 mg 70756-0249-12 | Lifestar | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin calcium 40 mg 72205-0024-05 | Novadoz | 500 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 72603-0284-01 | NorthStar | 90 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin calcium 40 mg 72603-0405-02 | NorthStar | 100 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin calcium 40 mg 75834-0257-01 | NIVAGEN | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 82009-0003-10 | Quallent | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 82009-0178-10 | Quallent | 1000 tablets | $0.037 | AB | Availability likely | — |
| Atorvastatin Calcium 40 mg 63304-0829-05 | Sun | 500 tablets | $0.040 | — | FDA listed | +9% |
| Atorvastatin Calcium 40 mg 16729-0046-15 | Accord | 90 tablets | $0.068 | AB | FDA listed | +85% |
| Atorvastatin Calcium 40 mg 69097-0946-05 | Cipla | 90 tablets | $0.068 | AB | FDA listed | +85% |
| Atorvastatin Calcium 40 mg 68180-0637-02 | Lupin | 500 tablets | $0.068 | — | Discontinued | +85% |
| Lipitor 40 mg 58151-0157-77 | Viatris | 90 tablets | $19.114 | AB | Availability likely | +51503% |
| Atorvastatin Calcium 40 mg 00615-8008-05 | NCS | 15 tablets | — | AB | Discontinued | — |
| Atorvastatin Calcium 40 mg 42708-0005-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 42708-0108-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 42708-0144-30 | QPharma, | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 43063-0453-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 48433-0009-20 | Safecor | 1 tablet | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-5207-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-5208-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-5632-00 | A-S | 30 tablets | — | — | FDA listed | — |
| Atorvastatin calcium 40 mg 50090-5915-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-6440-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-6441-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-7384-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-7385-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| atorvastatin calcium 40 mg 50090-7726-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| atorvastatin calcium 40 mg 50090-7727-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-7806-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 50090-7807-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 51655-0465-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 55154-4166-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 55154-6646-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 55154-7628-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 59651-0608-62 | Aurobindo | 30000 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 60290-0041-01 | Umedica | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 60505-2580-00 | Apotex | 10 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 60760-0726-30 | St. | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 60760-0734-30 | St. | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 60760-0882-30 | St. | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 63187-0109-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 67046-1529-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 68071-2302-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-2991-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| atorvastatin calcium 40 mg 68071-2994-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-3267-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-3595-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-3628-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-3667-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-3882-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 68071-3948-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-4837-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-5091-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68071-5194-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 68788-8094-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68788-8574-09 | Preferred | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 68788-8887-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 69097-0899-05 | Cipla | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 70518-1322-01 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 70518-3273-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Atorvastatin calcium 40 mg 70518-4321-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 70518-4474-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 70518-4592-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| atorvastatin calcium 40 mg 70771-1877-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 71205-0264-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Atorvastatin Calcium 40 mg 71205-0731-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 71205-0765-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 71209-0092-04 | Cadila | 90 tablets | — | — | FDA listed | — |
| Atorvastatin Calcium 40 mg 71335-1011-01 | Bryant | 30 tablets | — | — | Discontinued | — |
| Atorvastatin Calcium 40 mg 71335-1126-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 71335-2493-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 71335-2591-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 71335-2697-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 71335-9711-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 71335-9723-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 71610-0163-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 71610-0745-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 72162-2238-09 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 72189-0557-30 | Direct_rx | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 72789-0089-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 76420-0946-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 77771-0453-10 | Radha | 1000 tablets | — | AB | FDA listed | — |
| atorvastatin calcium 40 mg 82137-0018-01 | Lepu | 90 tablets | — | — | FDA listed | — |
| Atorvastatin Calcium 40 mg 82804-0026-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 82804-0056-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 82868-0029-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin calcium 40 mg 82868-0048-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 87441-0013-01 | Unit | 30 tablets | — | AB | FDA listed | — |
| Atorvastatin Calcium 40 mg 72189-0239-90 | DIRECT | 90 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 42385-0942-01 | 100 TABLET, FILM COATED in 1 BOTTLE (42385-942-01) | $0.0370 / ea | $3.70 | 2024-01-23 | Active |
| 42385-0942-05 You're viewing this | 500 TABLET, FILM COATED in 1 BOTTLE (42385-942-05) | $0.0370 / ea | $18.52 | 2024-01-23 | Active |
| 42385-0942-11 | 1000 TABLET, FILM COATED in 1 BOTTLE (42385-942-11) | $0.0370 / ea | $37.04 | 2024-01-23 | Active |
| 42385-0942-30 | 30 TABLET, FILM COATED in 1 BOTTLE (42385-942-30) | — | — | 2024-01-23 | Active |
| 42385-0942-68 | 10 BLISTER PACK in 1 CARTON (42385-942-68) / 10 TABLET, FILM COATED in 1 BLISTER PACK (42385-942-10) | — | — | 2024-01-23 | Active |
| 42385-0942-90 | 90 TABLET, FILM COATED in 1 BOTTLE (42385-942-90) | $0.0370 / ea | $3.33 | 2024-01-23 | Active |
This pack effectively ties for the lowest per-ea cost of the 4 priced pack sizes ($0.0370 NADAC).
Pack size FAQ
What quantity is in NDC 42385-0942-05?
What is the difference between NDC 42385-0942-05 and NDC 42385-0942-30?
What NDC number is used to bill for this package of Atorvastatin Calcium 40 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Atorvastatin calcium tablets are indicated: • To reduce the risk of: o Myocardial infarction (MI), stroke, revascularization procedures, and angina in adults with multiple risk factors for coronary heart disease (CHD) but without clinically evident CHD o MI and stroke in adults with type 2 diabetes mellitus with multiple risk factors for CHD but without clinically evident CHD o Non-fatal MI, fatal and non-fatal stroke, revascularization procedures, hospitalization for congestive heart failure, and angina in adults with clinically evident CHD • As an adjunct to diet to reduce low-density lipoprotein cholesterol (LDL-C) in: o Adults with primary hyperlipidemia. o Adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH). • As an adjunct to other LDL-C-lowering therapies, or alone if such treatments are unavailable, to reduce LDL-C in adults and pediatric patients aged 10 years and older with homozygous familial hypercholesterolemia (HoFH). • As an adjunct to diet for the treatment of adults with: o Primary dysbetalipoproteinemia o Hypertriglyceridemia Atorvastatin calcium tablets are an HMG-CoA reductase inhibitor (statin) indicated (1) : • To reduce the risk of: o Myocardial infarction (MI), stroke, revascularization procedures, and angina in adults with multiple risk factors for coronary heart disease (CHD) but without clinically evident CHD. o MI and stroke in adults with type 2 diabetes mellitus with multiple risk factors for CHD but without clinically evident CHD. o Non-fatal MI, fatal and non-fatal stroke, revascularization procedures, hospitalization for congestive heart failure, and angina in adults with clinically evident CHD. • As an adjunct to diet to reduce low-density lipoprotein (LDL-C) in: o Adults with primary hyperlipidemia. o Adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH). • As an adjunct to other LDL-C-lowering therapies to reduce LDL-C in adults and pediatric patients aged 10 years and older with homozygous familial hypercholesterolemia. • As an adjunct to diet for the treatment of adults with: o Primary dysbetalipoproteinemia. o Hypertriglyceridemia.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Take orally once daily with or without food (2.1) . • Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating atorvastatin calcium tablets, and adjust dosage if necessary (2.1) . • Adults (2.2) : o Recommended starting dosage is 10 or 20 mg once daily; dosage range is 10 mg to 80 mg once daily. o Patients requiring LDL-C reduction >45% may start at 40 mg once daily. • Pediatric Patients Aged 10 Years of Age and Older with HeFH: Recommended starting dosage is 10 mg once daily; dosage range is 10 to 20 mg once daily (2.3) . • Pediatric Patients Aged 10 Years of Age and Older with HoFH: Recommended starting dosage is 10 to 20 mg once daily; dosage range is 10 to 80 mg once daily (2.4) . • See full prescribing information for atorvastatin calcium tablets dosage modifications due to drug interactions (2.5) .
2.1Important Dosage Information • Take atorvastatin calcium tablets orally once daily at any time of the day, with or without food. • Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating atorvastatin calcium tablets, and adjust the dosage if necessary. • If a dose is missed, advise patients not to take the missed dose and resume with the next scheduled dose.
2.2Recommended Dosage in Adult Patients The recommended starting dosage of atorvastatin calcium tablets is 10 mg to 20 mg once daily. The dosage range is 10 mg to 80 mg once daily. Patients who require reduction in LDL-C greater than 45% may be started at 40 mg once daily.
2.3Recommended Dosage in Pediatric Patients 10 Years of Age and Older with HeFH The recommended starting dosage of atorvastatin calcium tablets is 10 mg once daily. The dosage range is 10 mg to 20 mg once daily.
2.4Recommended Dosage in Pediatric Patients 10 Years of Age and Older with HoFH The recommended starting dosage of atorvastatin calcium tablets is 10 mg to 20 mg once daily. The dosage range is 10 mg to 80 mg once daily.
2.5Dosage Modifications Due to Drug Interactions Concomitant use of atorvastatin calcium tablets with the following drugs requires dosage modification of atorvastatin calcium tablets [see Warnings and Precautions (5.1) and Drug Interactions (7.1) ]. Anti-Viral Medications • In patients taking saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, fosamprenavir plus ritonavir, elbasvir plus grazoprevir or letermovir, do not exceed atorvastatin calcium tablets 20 mg once daily. • In patients taking nelfinavir, do not exceed atorvastatin calcium tablets 40 mg once daily.
Select Azole Antifungals or Macrolide Antibiotics • In patients taking clarithromycin or itraconazole, do not exceed atorvastatin calcium tablets 20 mg once daily. For additional recommendations regarding concomitant use of atorvastatin calcium tablets with other anti-viral medications, azole antifungals or macrolide antibiotics, see Drug Interactions (7.1) .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Atorvastatin calcium tablets, USP: 10 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with “LA37” on one side and plain on the other side. 20 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with “LA38” on one side and plain on the other side. 40 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with “LA39” on one side and plain on the other side.
80 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with “LA8” on one side and plain on the other side. Tablets: 10 mg; 20 mg; 40 mg; 80 mg of atorvastatin (3) .
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Acute liver failure or decompensated cirrhosis [see Warnings and Precautions (5.3) ] • Hypersensitivity to atorvastatin or any excipients in atorvastatin calcium tablets. Hypersensitivity reactions, including anaphylaxis, angioneurotic edema, erythema multiforme, Stevens-Johnson syndrome, and toxic epidermal necrolysis, have been reported [see Adverse Reactions (6.2) ] . • Acute liver failure or decompensated cirrhosis (4) . • Hypersensitivity to atorvastatin or any excipient in atorvastatin calcium tablets (4) .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Myopathy and Rhabdomyolysis: Risk factors include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs, and higher atorvastatin dosage. Discontinue atorvastatin if markedly elevated CK levels occur or myopathy is diagnosed or suspected. Temporarily discontinue atorvastatin in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis.
Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing atorvastatin dosage. Instruct patients to promptly report unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever (2.5, 5.1, 7.1, 8.5, 8.6) . • Immune-Mediated Necrotizing Myopathy (IMNM): Rare reports of IMNM, an autoimmune myopathy, have been reported with statin use. Discontinue atorvastatin if IMNM is suspected (5.2) . • Hepatic Dysfunction: Increases in serum transaminases have occurred, some persistent.
Rare reports of fatal and non-fatal hepatic failure have occurred. Consider testing liver enzymes before initiating therapy and as clinically indicated thereafter. If serious hepatic injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs, promptly discontinue atorvastatin (5.3) .
5.1Myopathy and Rhabdomyolysis Atorvastatin may cause myopathy (muscle pain, tenderness, or weakness associated with elevated creatine kinase [CK]) and rhabdomyolysis. Acute kidney injury secondary to myoglobinuria and rare fatalities have occurred as a result of rhabdomyolysis in patients treated with statins, including atorvastatin. Risk Factors for Myopathy Risk factors for myopathy include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs (including other lipid-lowering therapies), and higher atorvastatin dosage [see Drug Interactions (7.1) and Use in Specific Populations (8.5, 8.6) ] .
Steps to Prevent or Reduce the Risk of Myopathy and Rhabdomyolysis Atorvastatin exposure may be increased by drug interactions due to inhibition of cytochrome P450 enzyme 3A4 (CYP3A4) and/or transporters (e.g., breast cancer resistant protein [BCRP], organic anion-transporting polypeptide [OATP1B1/OATP1B3] and P-glycoprotein [P-gp]), resulting in an increased risk of myopathy and rhabdomyolysis. Concomitant use of cyclosporine, gemfibrozil, tipranavir plus ritonavir, or glecaprevir plus pibrentasvir with atorvastatin is not recommended.
Atorvastatin dosage modifications are recommended for patients taking certain anti-viral, azole antifungals, or macrolide antibiotic medications [see Dosage and Administration (2.5) ] . Cases of myopathy/rhabdomyolysis have been reported with atorvastatin co-administered with lipid modifying doses (>1 gram/day) of niacin, fibrates, colchicine, and ledipasvir plus sofosbuvir [see Adverse Reactions (6.1) ] . Consider if the benefit of use of these products outweighs the increased risk of myopathy and rhabdomyolysis [see Drug Interactions (7.1) ] .
Concomitant intake of large quantities, more than 1.2 liters daily, of grapefruit juice is not recommended in patients taking atorvastatin [see Drug Interactions (7.1) ] . Discontinue atorvastatin if markedly elevated CK levels occur or if myopathy is either diagnosed or suspected. Muscle symptoms and CK elevations may resolve if atorvastatin is discontinued.
Temporarily discontinue atorvastatin in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis (e.g., sepsis; shock; severe hypovolemia; major surgery; trauma; severe metabolic, endocrine, or electrolyte disorders; or uncontrolled epilepsy). Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing the atorvastatin dosage. Instruct patients to promptly report any unexplained muscle pain, tenderness or weakness, particularly if accompanied by malaise o…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described below and elsewhere in the labeling: • Myopathy and Rhabdomyolysis [see Warnings and Precautions (5.1) ] • Immune-Mediated Necrotizing Myopathy [see Warnings and Precautions (5.2) ] • Hepatic Dysfunction [see Warnings and Precautions (5.3) ] • Increases in HbA1c and Fasting Serum Glucose Levels [see Warnings and Precautions (5.4) ] Most common adverse reactions (incidence ≥5%) are nasopharyngitis, arthralgia, diarrhea, pain in extremity, and urinary tract infection (6.1) .
To report SUSPECTED ADVERSE REACTIONS, contact Laurus Generics Inc. at 1-833-3-LAURUS (1-833-352-8787) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, the adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In the atorvastatin placebo-controlled clinical trial database of 16,066 patients (8,755 atorvastatin vs. 7,311 placebo; age range 10 to 93 years, 39% female, 91% White, 3% Black or African American, 2% Asian, 4% other) with a median treatment duration of 53 weeks, the most common adverse reactions in patients treated with atorvastatin that led to treatment discontinuation and occurred at a rate greater than placebo were: myalgia (0.7%), diarrhea (0.5%), nausea (0.4%), alanine aminotransferase increase (0.4%), and hepatic enzyme increase (0.4%).
Table 1 summarizes adverse reactions reported in ≥ 2% and at a rate greater than placebo in patients treated with atorvastatin (n=8,755), from seventeen placebo-controlled trials. Table 1: Adverse Reactions Occurring in ≥ 2% in Patients Atorvastatin-Treated with any Dose and Greater than Placebo Adverse Reaction % Placebo N=7,311 % 10 mg N=3,908 % 20 mg N=188 % 40 mg N=604 % 80 mg N=4,055 % Any dose N=8,755 Nasopharyngitis 8.2 12.9 5.3 7.0 4.2
8.3Arthralgia 6.5 8.9 11.7 10.6 4.3
6.9Diarrhea 6.3 7.3 6.4 14.1 5.2
6.8Pain in extremity 5.9 8.5 3.7 9.3 3.1
6.0Urinary tract infection 5.6 6.9 6.4 8.0 4.1
5.7Dyspepsia 4.3 5.9 3.2 6.0 3.3
4.7Nausea 3.5 3.7 3.7 7.1 3.8
4.0Musculoskeletal pain 3.6 5.2 3.2 5.1 2.3
3.8Muscle spasms 3.0 4.6 4.8 5.1 2.4
3.6Myalgia 3.1 3.6 5.9 8.4 2.7
3.5Insomnia 2.9 2.8 1.1 5.3 2.8
3.0Pharyngolaryngeal pain 2.1 3.9 1.6 2.8 0.7
2.3Other adverse reactions reported in placebo-controlled trials include: Body as a Whole: malaise, pyrexia Digestive System: abdominal discomfort, eructation, flatulence, hepatitis, cholestasis Musculoskeletal System: musculoskeletal pain, muscle fatigue, neck pain, joint swelling Metabolic and Nutritional System: transaminases increase, liver function test abnormal, blood alkaline phosphatase increase, creatine phosphokinase increase, hyperglycemia Nervous System: nightmare Respiratory System: epistaxis Skin and Appendages: urticaria Special Senses: vision blurred, tinnitus Urogenital System: white blood cells urine positive Elevations in Liver Enzyme Tests Persistent elevations in serum transaminases, defined as more than 3 times the ULN and occurring on 2 or more occasions, occurred in 0.7% of patients who received atorvastatin in clinical trials.
The incidence of these abnormalities was 0.2%, 0.2%, 0.6%, and 2.3% for 10, 20, 40, and 80 mg, respectively. One patient in clinical trials developed jaundice. Increases in liver enzyme tests in other patients were not associated with jaundice or other clinical signs or symptoms.
Upon dose reduction, drug interruption, or discontinuation, transaminase levels returned to or near pretreatment levels without sequelae. Eighteen of 30 patients with persistent liver enzyme elevations continued treatment with a reduced dose of atorvastatin. Treating to New Targets Study (TNT) In TNT, [see Clinical Studies (14.1)] 10,001 patients (age range 29 to 78 years, 19% female; 94% White, 3% Black or African American…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • See full prescribing information for details regarding concomitant use of atorvastatin with other drugs or grapefruit juice that increase the risk of myopathy and rhabdomyolysis (2.5, 7.1) . • Rifampin: May reduce atorvastatin plasma concentrations. Administer simultaneously with atorvastatin (7.2) . • Oral Contraceptives: May increase plasma levels of norethindrone and ethinyl estradiol; consider this effect when selecting an oral contraceptive (7.3) . • Digoxin: May increase digoxin plasma levels; monitor patients appropriately (7.3) .
7.1Drug Interactions that may Increase the Risk of Myopathy and Rhabdomyolysis with Atorvastatin Atorvastatin is a substrate of CYP3A4 and transporters (e.g., OATP1B1/1B3, P-gp, or BCRP). Atorvastatin plasma levels can be significantly increased with concomitant administration of inhibitors of CYP3A4 and transporters. Table 2 includes a list of drugs that may increase exposure to atorvastatin and may increase the risk of myopathy and rhabdomyolysis when used concomitantly and instructions for preventing or managing them [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ].
Table 2: Drug Interactions that may Increase the Risk of Myopathy and Rhabdomyolysis with Atorvastatin Cyclosporine or Gemfibrozil Clinical Impact: Atorvastatin plasma levels were significantly increased with concomitant administration of atorvastatin and cyclosporine, an inhibitor of CYP3A4 and OATP1B1 [see Clinical Pharmacology (12.3) ]. Gemfibrozil may cause myopathy when given alone. The risk of myopathy and rhabdomyolysis is increased with concomitant use of cyclosporine or gemfibrozil with atorvastatin.
Intervention: Concomitant use of cyclosporine or gemfibrozil with atorvastatin is not recommended. Anti-Viral Medications Clinical Impact: Atorvastatin plasma levels were significantly increased with concomitant administration of atorvastatin with many anti-viral medications, which are inhibitors of CYP3A4 and/or transporters (e.g., BCRP, OATP1B1/1B3, P-gp, MRP2, and/or OAT2) [see Clinical Pharmacology (12.3) ]. Cases of myopathy and rhabdomyolysis have been reported with concomitant use of ledipasvir plus sofosbuvir with atorvastatin.
Intervention: Concomitant use of tipranavir plus ritonavir or glecaprevir plus pibrentasvir with atorvastatinis not recommended. In patients taking lopinavir plus ritonavir, or simeprevir, consider the risk/benefit of concomitant use with atorvastatin. In patients taking saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, fosamprenavir plus ritonavir, elbasvir plus grazoprevir or letermovir, do not exceed atorvastatin 20 mg.
In patients taking nelfinavir, do not exceed atorvastatin 40 mg [see Dosage and Administration (2.5) ]. Consider the risk/benefit of concomitant use of ledipasvir plus sofosbuvir with atorvastatin. Monitor all patients for signs and symptoms of myopathy particularly during initiation of therapy and during upward dose titration of either drug.
Examples: Tipranavir plus ritonavir, glecaprevir plus pibrentasvir, lopinavir plus ritonavir, simeprevir, saquinavir plus ritonavir, darunavir plus ritonavir, fosamprenavir, fosamprenavir plus ritonavir, elbasvir plus grazoprevir, letermovir, nelfinavir, and ledipasvir plus sofosbuvir. Select Azole Antifungals or Macrolide Antibiotics Clinical Impact: Atorvastatin plasma levels were significantly increased with concomitant administration of atorvastatin with select azole antifungals or macrolide antibiotics, due to inhibition of CYP3A4 and/or transporters [see Clinical Pharmacology (12.3) ].
Intervention: In patients taking clarithromycin or itraconazole, do not exceed atorvastatin 20 mg [see Dosage and Administration (2.5) ]. Consider the risk/benefit of concomitant use of other azole antifungals or macrolide antibiotics with atorvastatin. Monitor all patients for signs and symptoms of myopathy particularly during initiation of therapy and during upward dose titration of e…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: May cause fetal harm. (8.1) . • Lactation: Breastfeeding not recommended during treatment with atorvastatin (8.2) .
8.1Pregnancy Risk Summary Discontinue atorvastatin when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. Atorvastatin decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, atorvastatin may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with atorvastatin use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data) . In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered atorvastatin at doses that resulted in up to 30 and 20 times, respectively, the human exposure at the maximum recommended human dose (MRHD) of 80 mg, based on body surface area (mg/m 2 ).
In rats administered atorvastatin during gestation and lactation, decreased postnatal growth and development delay were observed at doses ≥ 6 times the MRHD (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data A Medicaid cohort linkage study of 1,152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders – including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods. The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounders, particularly pre-existing diabetes mellitus.
There were also no statistically significant increases in any of the organ-specific malformations assessed after accounting for confounders. In the majority of pregnancies, statin treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified. Study limitations include reliance on physician coding to define the presence of a malformation, lack of control for certain confounders such as body mass index, use of prescription dispensing as verification for the use of a statin, and lack of information on non-live births.
Animal Data Atorvastatin was administered to pregnant rats and rabbits during organogenesis at oral doses up to 300 mg/kg/day and 100 mg/kg/day, respectively. Atorvastatin was not teratogenic in rats at doses up to 300 mg/kg/day or in rabbits at doses up to 100 mg/kg/day. These doses resulted in multiples of about 30 times (rat) or 20 times (rabbit) the human exposure at the MRHD based on surface area (mg/m 2 ).
In rats, the maternally toxic dose of 300 mg/kg resulted in increased post-implantation loss and decreased fetal body weight. At the maternally toxic doses of 50 and 100 mg/kg/day in rabbits, there was increased post-im…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Discontinue atorvastatin when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. Atorvastatin decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, atorvastatin may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with atorvastatin use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data) . In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered atorvastatin at doses that resulted in up to 30 and 20 times, respectively, the human exposure at the maximum recommended human dose (MRHD) of 80 mg, based on body surface area (mg/m 2 ).
In rats administered atorvastatin during gestation and lactation, decreased postnatal growth and development delay were observed at doses ≥ 6 times the MRHD (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data A Medicaid cohort linkage study of 1,152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders – including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods. The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounders, particularly pre-existing diabetes mellitus.
There were also no statistically significant increases in any of the organ-specific malformations assessed after accounting for confounders. In the majority of pregnancies, statin treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified. Study limitations include reliance on physician coding to define the presence of a malformation, lack of control for certain confounders such as body mass index, use of prescription dispensing as verification for the use of a statin, and lack of information on non-live births.
Animal Data Atorvastatin was administered to pregnant rats and rabbits during organogenesis at oral doses up to 300 mg/kg/day and 100 mg/kg/day, respectively. Atorvastatin was not teratogenic in rats at doses up to 300 mg/kg/day or in rabbits at doses up to 100 mg/kg/day. These doses resulted in multiples of about 30 times (rat) or 20 times (rabbit) the human exposure at the MRHD based on surface area (mg/m 2 ).
In rats, the maternally toxic dose of 300 mg/kg resulted in increased post-implantation loss and decreased fetal body weight. At the maternally toxic doses of 50 and 100 mg/kg/day in rabbits, there was increased post-implantation loss, and at 100 mg/kg/day fetal body weights were decreased. In a study in pregnant rats administered 20, 100, or 225 mg/kg/day from gestation day…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of atorvastatin as an adjunct to diet to reduce LDL-C have been established pediatric patients 10 years of age and older with HeFH. Use of atorvastatin for this indication is based on a double-blind, placebo-controlled clinical trial in 187 pediatric patients 10 years of age and older with HeFH. In this limited controlled trial, there was no significant effect on growth or sexual maturation in the males or females or on menstrual cycle length in females.
The safety and effectiveness of atorvastatin as an adjunct to other LDL-C-lowering therapies to reduce LDL-C have been established pediatric patients 10 years of age and older with HoFH. Use of atorvastatin for this indication is based on a trial without a concurrent control group in 8 pediatric patients 10 years of age and older with HoFH [see Clinical Studies (14) ] . The safety and effectiveness of atorvastatin have not been established in pediatric patients younger than 10 years of age with HeFH or HoFH, or in pediatric patients with other types of hyperlipidemia (other than HeFH or HoFH).
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of atorvastatin-treated patients in clinical trials, 15,813 (40%) were ≥65 years old and 2,800 (7%) were ≥75 years old. No overall differences in safety or effectiveness were observed between these patients and younger patients. Advanced age (≥65 years) is a risk factor for atorvastatin-associated myopathy and rhabdomyolysis.
Dose selection for an elderly patient should be cautious, recognizing the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of myopathy. Monitor geriatric patients receiving atorvastatin for the increased risk of myopathy [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE No specific antidotes for atorvastatin are known. Contact Poison Control (1-800-222-1222) for latest recommendations. Due to extensive drug binding to plasma proteins, hemodialysis is not expected to significantly enhance atorvastatin clearance.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Atorvastatin is a selective, competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl-coenzyme A to mevalonate, a precursor of sterols, including cholesterol. In animal models, atorvastatin lowers plasma cholesterol and lipoprotein levels by inhibiting HMG-CoA reductase and cholesterol synthesis in the liver and by increasing the number of hepatic LDL receptors on the cell surface to enhance uptake and catabolism of LDL; atorvastatin also reduces LDL production and the number of LDL particles.
12.2Pharmacodynamics Atorvastatin, as well as some of its metabolites, are pharmacologically active in humans. The liver is the primary site of action and the principal site of cholesterol synthesis and LDL clearance. Drug dosage, rather than systemic drug concentration, correlates better with LDL-C reduction. Individualization of drug dosage should be based on therapeutic response [see Dosage and Administration (2) ] .
12.3Pharmacokinetics Absorption Atorvastatin is rapidly absorbed after oral administration; maximum plasma concentrations occur within 1 to 2 hours. Extent of absorption increases in proportion to atorvastatin dose. The absolute bioavailability of atorvastatin (parent drug) is approximately 14% and the systemic availability of HMG-CoA reductase inhibitory activity is approximately 30%.
The low systemic availability is attributed to presystemic clearance in gastrointestinal mucosa and/or hepatic first-pass metabolism. Although food decreases the rate and extent of drug absorption by approximately 25% and 9%, respectively, as assessed by Cmax and AUC, LDL-C reduction is similar whether atorvastatin is given with or without food. Plasma atorvastatin concentrations are lower (approximately 30% for Cmax and AUC) following evening drug administration compared with morning.
However, LDL-C reduction is the same regardless of the time of day of drug administration. Distribution Mean volume of distribution of atorvastatin is approximately 381 liters. Atorvastatin is ≥98% bound to plasma proteins.
A blood/plasma ratio of approximately 0.25 indicates poor drug penetration into red blood cells. Elimination Metabolism Atorvastatin is extensively metabolized to ortho- and parahydroxylated derivatives and various beta-oxidation products. In vitro inhibition of HMG-CoA reductase by ortho- and parahydroxylated metabolites is equivalent to that of atorvastatin.
Approximately 70% of circulating inhibitory activity for HMG-CoA reductase is attributed to active metabolites. In vitro studies suggest the importance of atorvastatin metabolism by cytochrome P450 3A4, consistent with increased plasma concentrations of atorvastatin in humans following co-administration with erythromycin, a known inhibitor of this isozyme [see Drug Interactions (7.1) ] . In animals, the ortho-hydroxy metabolite undergoes further glucuronidation.
Excretion Atorvastatin and its metabolites are eliminated primarily in bile following hepatic and/or extra-hepatic metabolism; however, the drug does not appear to undergo enterohepatic recirculation. Mean plasma elimination half-life of atorvastatin in humans is approximately 14 hours, but the half-life of inhibitory activity for HMG-CoA reductase is 20 to 30 hours due to the contribution of active metabolites. Less than 2% of a dose of atorvastatin is recovered in urine following oral administration.
Specific Populations Geriatric Plasma concentrations of atorvastatin are higher (approximately 40% for Cmax and 30% for AUC) in healthy elderly subjects (age ≥65 years) than in young adults. Pediatric Apparent oral clearance of atorvastatin in pediatric subjects appeared similar to that of adults when scaled allometrically by body weight as the body weight was the only significant covariate in atorvastatin population PK model with data including pediatric HeFH patients (ages 10 years to 17 years of age, n=29) in an open-lab…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Atorvastatin is a selective, competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl-coenzyme A to mevalonate, a precursor of sterols, including cholesterol. In animal models, atorvastatin lowers plasma cholesterol and lipoprotein levels by inhibiting HMG-CoA reductase and cholesterol synthesis in the liver and by increasing the number of hepatic LDL receptors on the cell surface to enhance uptake and catabolism of LDL; atorvastatin also reduces LDL production and the number of LDL particles.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Atorvastatin calcium tablets, USP are supplied as follows: 10 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with "LA37" on one side and plain on the other side. Bottles of 30 NDC 42385-940-30 Bottles of 90 NDC 42385-940-90 Bottles of 100 NDC 42385-940-01 Bottles of 500 NDC 42385-940-05 Bottles of 1,000 NDC 42385-940-11 Carton with 100 (10 x 10) Unit-Dose Tablets NDC 42385-940-68 20 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with "LA38" on one side and plain on the other side.
Bottles of 30 NDC 42385-941-30 Bottles of 90 NDC 42385-941-90 Bottles of 100 NDC 42385-941-01 Bottles of 500 NDC 42385-941-05 Bottles of 1,000 NDC 42385-941-11 Carton with 100 (10 x 10) Unit-Dose Tablets NDC 42385-941-68 40 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with "LA39" on one side and plain on the other side. Bottles of 30 NDC 42385-942-30 Bottles of 90 NDC 42385-942-90 Bottles of 100 NDC 42385-942-01 Bottles of 500 NDC 42385-942-05 Bottles of 1,000 NDC 42385-942-11 Carton with 100 (10 x 10) Unit-Dose Tablets NDC 42385-942-68 80 mg of atorvastatin: white to off-white, oval shaped, biconvex, film coated tablets debossed with "LA8" on one side and plain on the other side.
Bottles of 30 NDC 42385-943-30 Bottles of 90 NDC 42385-943-90 Bottles of 100 NDC 42385-943-01 Bottles of 500 NDC 42385-943-05 Bottles of 1,000 NDC 42385-943-11 Carton with 64 (8 x 8) Unit-Dose Tablets NDC 42385-943-64 Carton with 100 (10 x 10) Unit-Dose Tablets NDC 42385-943-68 Storage Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature.]
📋 Description ▾
11 DESCRIPTION Atorvastatin is an inhibitor of 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase. Atorvastatin calcium is calcium( βR,δR )-2-( p -fluorophenyl)- β,δ -dihydroxy-5-isopropyl-3-phenyl-4-(phenylcarbamoyl)pyrrole-1-heptanoate (1:2). The molecular formula of atorvastatin calcium is C 66 H 68 CaF 2 N 4 O 10 •3H 2 O and its molecular weight is 1,209.41.
Its structural formula is: Atorvastatin calcium USP is a white to off white powder that is insoluble in aqueous solutions of pH 4 and below. Atorvastatin calcium USP is insoluble to very slightly soluble in distilled water, in pH 7.4 phosphate buffer, and in acetonitrile; very slightly soluble to soluble in alcohol (99.9%); and soluble to freely soluble in methanol. Atorvastatin calcium tablets, USP for oral use contain atorvastatin 10 mg, 20 mg, 40 mg, or 80 mg (equivalent to 10.36 mg, 20.72 mg, 41.44 mg, or 82.88 mg atorvastatin calcium anhydrous) and the following inactive ingredients: calcium carbonate, croscarmellose sodium, hydroxypropyl cellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, Opadry White YS-1-7040 (hypromellose, polyethylene glycol, talc, titanium dioxide) and polysorbate 80.
Meets USP Dissolution Test 3. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Myopathy and Rhabdomyolysis Advise patients that atorvastatin may cause myopathy and rhabdomyolysis. Inform patients that the risk is also increased when taking certain types of medication or consuming large quantities of grapefruit juice and they should discuss all medication, both prescription and over the counter, with their healthcare provider.
Instruct patients to promptly report any unexplained muscle pain, tenderness or weakness particularly if accompanied by malaise or fever [see Warnings and Precautions (5.1) , Drug Interactions (7.1) ]. Hepatic Dysfunction Inform patients that atorvastatin may cause liver enzyme elevations and possibly liver failure. Advise patients to promptly report fatigue, anorexia, right upper abdominal discomfort, dark urine or jaundice [see Warnings and Precautions (5.3) ].
Increases in HbA1c and Fasting Serum Glucose Levels Inform patients that increases in HbA1c and fasting serum glucose levels may occur with atorvastatin. Encourage patients to optimize lifestyle measures, including regular exercise, maintaining a healthy body weight, and making healthy food choices [see Warnings and Precautions (5.4) ]. Pregnancy Advise pregnant patients and patients who can become pregnant of the potential risk to a fetus.
Advise patients to inform their healthcare provider of a known or suspected pregnancy to discuss if atorvastatin should be discontinued [see Use in Specific Populations (8.1) ]. Lactation Advise patients that breastfeeding is not recommended during treatment with atorvastatin [see Use in Specific Populations (8.2) ]. Missed Doses If a dose is missed, advise patients not to take the missed dose and resume with the next scheduled dose.
The brands listed are trademarks of their respective owners and are not trademarks of Laurus Labs Limited. Dispense with Patient Information available at : https://www.laurusgenerics.us/patient-info/ator-tabs.pdf Manufactured for: Laurus Generics Inc. 400 Connell Drive, Suite 5200 Berkeley Heights, NJ 07922 Manufactured by: Laurus Labs Limited Anakapalli-531011 India