
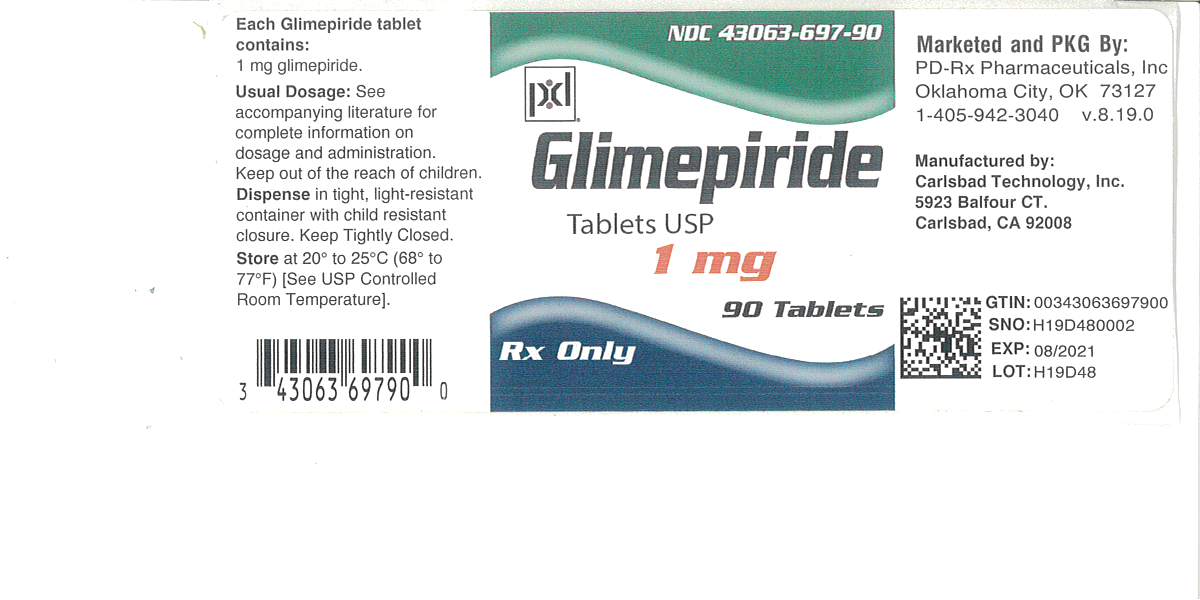
Glimepiride 1 mg Tablet, 180-count
Other active recalls for Glimepiride (different manufacturers) — 4 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Sulfonylurea class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Glimepiride is used along with diet and exercise, and sometimes with other medications, to treat type 2 diabetes (condition in which the body does not use insulin normally and, therefore, cannot control the amount of sugar in the blood). Glimepiride lowers blood sugar by causing the pancreas to produce insulin (a natural substance that is needed to break down sugar in the body) and helping the body use insulin efficiently. This medication will only help lower blood sugar in people whose bodies produce insulin naturally. Glimepiride is not used to treat type 1 diabetes (condition in which the b...
Read the full MedlinePlus article ↗- Glimepiride helps lower your blood sugar if you have type 2 diabetes. It works by prompting your pancreas to release more insulin, which helps move sugar out of your bloodstream an...
- What exactly is glimepiride supposed to do for me?
- Yes, timing with food really matters here. You should take glimepiride with your breakfast or your first main meal of the day — every day. Taking it with a meal helps reduce the ri...
- When should I take it, and does it matter if I take it with food?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Glimepiride — tap one for details:
Glimepiride may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1093 | $19.67 / 180 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Glimepiride 1 mg 16571-0773-01 | Rising | 100 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 42571-0100-01 | Micro | 100 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 43547-0394-10 | Solco | 100 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 50268-0358-15 | AvPAK | 50 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 55111-0320-01 | Dr. | 100 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 61442-0115-01 | Carlsbad | 100 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 68001-0584-00 | BluePoint | 100 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 68084-0788-25 | American | 30 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 71921-0214-01 | Florida | 100 tablets | $0.024 | AB | Availability likely | — |
| Glimepiride 1 mg 16729-0001-01 | Accord | 100 tablets | $0.025 | AB | FDA listed | — |
| Glimepiride 1 mg 00615-8332-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 43063-0121-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mgthis 43063-0697-93 | PD-Rx | 180 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 50090-6394-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 50090-7187-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 60429-0918-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 63187-0698-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 65862-0579-01 | Aurobindo | 100 tablets | — | — | FDA listed | — |
| Glimepiride 1 mg 71205-0779-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 71335-1885-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 71335-2561-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 71335-9655-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Glimepiride 1 mg 82804-0140-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 43063-0697-90 | 90 TABLET in 1 BOTTLE, PLASTIC (43063-697-90) | 2016-08-01 | Active |
| 43063-0697-93 You're viewing this | 180 TABLET in 1 BOTTLE, PLASTIC (43063-697-93) | 2016-08-01 | Active |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 43063-0697-93?
What is the difference between NDC 43063-0697-93 and NDC 43063-0697-90?
What NDC number is used to bill for this package of Glimepiride 1 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Glimepiride Tablet are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus [see Clinical Studies ( 14.1 ) ]. Limitations of Use Glimepiride should not be used for the treatment of type 1 diabetes mellitus or diabetic ketoacidosis, as it would not be effective in these settings. Glimepiride Tablets are a sulfonylurea indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus ( 1 ).
Important Limitations of Use: Not for treating type 1 diabetes mellitus or diabetic ketoacidosis ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended starting dose is 1 or 2 mg once daily. Increase in 1 or 2 mg increments no more frequently than every 1-2 weeks based on glycemic response. Maximum recommended dose is 8 mg once daily ( 2.1 ). Administer with breakfast or first meal of the day ( 2.1 ). Use 1 mg starting dose and titrate slowly in patients at increased risk for hypoglycemia (e.g., elderly, patients with renal impairment) ( 2.1 ).
2.1Recommended Dosing Glimepiride should be administered with breakfast or the first main meal of the day. The recommended starting dose of glimepiride is 1 mg or 2 mg once daily. Patients at increased risk for hypoglycemia (e.g., the elderly or patients with renal impairment) should be started on 1 mg once daily [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.5 , 8.6 ) ].
After reaching a daily dose of 2 mg, further dose increases can be made in increments of 1 mg or 2 mg based upon the patient's glycemic response. Uptitration should not occur more frequently than every 1-2 weeks. A conservative titration scheme is recommended for patients at increased risk for hypoglycemia [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.5 , 8.6 ) ].
The maximum recommended dose is 8 mg once daily. Patients being transferred to glimepiride from longer half-life sulfonylureas (e.g., chlorpropamide) may have overlapping drug effect for 1-2 weeks and should be appropriately monitored for hypoglycemia. When colesevelam is coadministered with glimepiride, maximum plasma concentration and total exposure to glimepiride is reduced.
Therefore, glimepiride should be administered at least 4 hours prior to colesevelam.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Glimepiride Tablets USP are formulated as tablets of: 1 mg (Scored white to off-white, round imprinted with on one side) Tablets (scored): 1 mg ( 3 ) Figure
⛔ Contraindications ▾
4 CONTRAINDICATIONS Glimepiride Tablets USP are contraindicated in patients with a history of a hypersensitivity reaction to: Glimepiride or any of the product's ingredients [ see Warnings and Precautions ( 5.2 ) ]. Sulfonamide derivatives: Patients who have developed an allergic reaction to sulfonamide derivatives may develop an allergic reaction to glimepiride. Do not use glimepiride in patients who have a history of an allergic reaction to sulfonamide derivatives.
Hypersensitivity to glimepiride or any of the product's ingredients ( 4 ) Hypersensitivity to sulfonamide derivatives ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypoglycemia: May be severe. Ensure proper patient selection, dosing, and instructions, particularly in at-risk populations (e.g., elderly, renally impaired) and when used with other anti-diabetic medications ( 5.1 ). Hypersensitivity Reactions: Postmarketing reports include anaphylaxis, angioedema and Stevens-Johnson Syndrome.
Promptly discontinue glimepiride, assess for other causes, institute appropriate monitoring and treatment, and initiate alternative treatment for diabetes ( 5.2 ). Hemolytic Anemia: Can occur if glucose 6-phosphate dehydrogenase (G6PD) deficient. Consider a non-sulfonylurea alternative.
( 5.3 ). Potential Increased Risk of Cardiovascular Mortality with Sulfonylureas: Inform patient of risks, benefits and treatment alternatives ( 5.4 ). Macrovascular Outcomes: No clinical studies establishing conclusive evidence of macrovascular risk reduction with glimepiride or any other anti-diabetic drug ( 5.5 ).
5.1Hypoglycemia All sulfonylureas, including glimepiride, can cause severe hypoglycemia [see Adverse Reactions ( 6.1 ) ]. The patient's ability to concentrate and react may be impaired as a result of hypoglycemia. These impairments may present a risk in situations where these abilities are especially important, such as driving or operating other machinery.
Severe hypoglycemia can lead to unconsciousness or convulsions and may result in temporary or permanent impairment of brain function or death. Patients must be educated to recognize and manage hypoglycemia. Use caution when initiating and increasing glimepiride doses in patients who may be predisposed to hypoglycemia (e.g., the elderly, patients with renal impairment, patients on other anti- diabetic medications).
Debilitated or malnourished patients, and those with adrenal, pituitary, or hepatic impairment are particularly susceptible to the hypoglycemic action of glucose-lowering medications. Hypoglycemia is also more likely to occur when caloric intake is deficient, after severe or prolonged exercise, or when alcohol is ingested. Early warning symptoms of hypoglycemia may be different or less pronounced in patients with autonomic neuropathy, the elderly, and in patients who are taking beta-adrenergic blocking medications or other sympatholytic agents.
These situations may result in severe hypoglycemia before the patient is aware of the hypoglycemia.
5.2Hypersensitivity Reactions There have been postmarketing reports of hypersensitivity reactions in patients treated with glimepiride, including serious reactions such as anaphylaxis, angioedema, and Stevens-Johnson Syndrome. If a hypersensitivity reaction is suspected, promptly discontinue glimepiride, assess for other potential causes for the reaction, and institute alternative treatment for diabetes.
5.3Hemolytic Anemia Sulfonylureas can cause hemolytic anemia in patients with glucose 6-phosphate dehydrogenase (G6PD) deficiency. Because glimepiride is a sulfonylurea, use caution in patients with G6PD deficiency and consider the use of a non-sulfonylurea alternative. There are also postmarketing reports of hemolytic anemia in patients receiving glimepiride who did not have known G6PD deficiency [see Adverse Reactions ( 6.2 ) ].
5.4Increased Risk of Cardiovascular Mortality with Sulfonylureas The administration of oral hypoglycemic drugs has been reported to be associated with increased cardiovascular mortality as compared to treatment with diet alone or diet plus insulin. This warning is based on the study conducted by the University Group Diabetes Program (UGDP), a long-term, prospective clinical trial designed to evaluate the effectiveness of glucose-lowering drugs in preventing or delaying vascular complications in patients with non-insulin-dependent diabetes.
The study involved 823 patients who were randomly assigned to one of four treatment groups. UGDP reported that patients treated for 5 to 8 years with diet plus a fixed dose of tolbutamide (1.5 grams per day) had a r…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in more detail below and elsewhere in the labeling: Hypoglycemia [see Warnings and Precautions ( 5.1 ) ] Hemolytic anemia [see Warnings and Precautions ( 5.3 ) ] Common adverse reactions in clinical trials (≥5% and more common than with placebo) include hypoglycemia, headache, nausea, and dizziness ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Carlsbad Technology, Inc. at 1-855-397-9777 or contact FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Approximately 2,800 patients with type 2 diabetes have been treated with glimepiride in the controlled clinical trials. In these trials, approximately 1,700 patients were treated with glimepiride for at least 1 year.
Table 1 summarizes adverse events, other than hypoglycemia, that were reported in 11 pooled placebo-controlled trials, whether or not considered to be possibly or probably related to study medication. Treatment duration ranged from 13 weeks to 12 months. Terms that are reported represent those that occurred at an incidence of ≥5% among glimepiride -treated patients and more commonly than in patients who received placebo.
Table 1. Eleven Pooled Placebo-Controlled Trials ranging from 13 weeks to 12 months: Adverse Events (Excluding Hypoglycemia) Occurring in ≥5% of glimepiride -treated Patients and at a Greater Incidence than with Placebo* *Glimepiride doses ranged from 1-16 mg administered daily †Insufficient information to determine whether any of the accidental injury events were associated with hypoglycemia Glimepiride N=745 % Placebo N=294 % Headache 8.2
7.8Accidental Injury † 5.8
3.4Flu Syndrome 5.4
4.4Nausea 5.0
3.4Dizziness 5.0
2.4Hypoglycemia: In a randomized, double-blind, placebo-controlled monotherapy trial of 14 weeks duration, patients already on sulfonylurea therapy underwent a 3-week washout period then were randomized to glimepiride 1 mg, 4 mg, 8 mg or placebo. Patients randomized to glimepiride 4 mg or 8 mg underwent forced-titration from an initial dose of 1 mg to these final doses, as tolerated [see Clinical Studies ( 14.1 )]. The overall incidence of possible hypoglycemia (defined by the presence of at least one symptom that the investigator believed might be related to hypoglycemia; a concurrent glucose measurement was not required) was 4% for glimepiride 1 mg, 17% for glimepiride 4 mg, 16% for glimepiride 8 mg and 0% for placebo.
All of these events were self-treated. In a randomized, double-blind, placebo-controlled monotherapy trial of 22 weeks duration, patients received a starting dose of either 1 mg glimepiride or placebo daily. The dose of glimepiride was titrated to a target fasting plasma glucose of 90-150 mg/dL.
Final daily doses of glimepiride were 1, 2, 3, 4, 6 or 8 mg [see Clinical Studies ( 14.1 )] . The overall incidence of possible hypoglycemia (as defined above for the 14-week trial) for glimepiride vs. placebo was 19.7% vs. 3.2%.
All of these events were self-treated. Weight gain: Glimepiride, like all sulfonylureas, can cause weight gain [see Clinical Studies ( 14.1 ) ]. Allergic Reactions: In clinical trials, allergic reactions, such as pruritus, erythema, urticaria, and morbilliform or maculopapular eruptions, occurred in less than 1% of glimepiride -treated patients.
These may resolve despite continued treatment with glimepiride. There are postmarketing reports of more serious allergic reactions (e.g., dyspnea, hypotension, shock) [see Warnings and Precautions ( 5.2 ) ]. Laboratory Tests: Elevated Serum Alanine Aminotransferase (ALT): In 11 pooled placebo-controlled trials of glimepiride, 1.9% of glimepiride -treated patients and 0.8% of placebo-treated pat…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Certain medications may affect glucose metabolism, requiring glimepiride dose adjustment and close monitoring of blood glucose ( 7.1 ). Miconazole: Severe hypoglycemia can occur when glimepiride and oral miconazole are used concomitantly. ( 7.2 ).
Cytochrome P450 2C9 interactions: Inhibitors and inducers of cytochrome P450 2C9 may affect glycemic control by altering glimepiride plasma concentrations ( 7.3 ). Colesevelam: Coadministration may reduce glimepiride absorption. Glimepiride should be administered at least 4 hours prior to colesevelam ( 2.1 , 7.4 ).
7.1Drugs Affecting Glucose Metabolism A number of medications affect glucose metabolism and may require glimepiride dose adjustment and particularly close monitoring for hypoglycemia or worsening glycemic control. The following are examples of medications that may increase the glucose-lowering effect of sulfonylureas including glimepiride, increasing the susceptibility to and/or intensity of hypoglycemia: oral anti-diabetic medications, pramlintide acetate, insulin, angiotensin converting enzyme (ACE) inhibitors, H2 receptor antagonists, fibrates, propoxyphene, pentoxifylline, somatostatin analogs, anabolic steroids and androgens, cyclophosphamide, phenyramidol, guanethidine, fluconazole, sulfinpyrazone, tetracyclines, clarithromycin, disopyramide, quinolones, and those drugs that are highly protein-bound, such as fluoxetine, nonsteroidal anti-inflammatory drugs, salicylates, sulfonamides, chloramphenicol, coumarins, probenecid and monoamine oxidase inhibitors.
When these medications are administered to a patient receiving glimepiride, monitor the patient closely for hypoglycemia. When these medications are withdrawn from a patient receiving glimepiride, monitor the patient closely for worsening glycemic control. The following are examples of medications that may reduce the glucose-lowering effect of sulfonylureas including glimepiride, leading to worsening glycemic control: danazol, glucagon, somatropin, protease inhibitors, atypical antipsychotic medications (e.g., olanzapine and clozapine), barbiturates, diazoxide, laxatives, rifampin, thiazides and other diuretics, corticosteroids, phenothiazines, thyroid hormones, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics (e.g., epinephrine, albuterol, terbutaline), and isoniazid.
When these medications are administered to a patient receiving glimepiride, monitor the patient closely for worsening glycemic control. When these medications are withdrawn from a patient receiving glimepiride, monitor the patient closely for hypoglycemia. Beta-blockers, clonidine, and reserpine may lead to either potentiation or weakening of glimepiride's glucose-lowering effect.
Both acute and chronic alcohol intake may potentiate or weaken the glucose-lowering action of glimepiride in an unpredictable fashion. The signs of hypoglycemia may be reduced or absent in patients taking sympatholytic drugs such as beta-blockers, clonidine, guanethidine, and reserpine.
7.2Miconazole A potential interaction between oral miconazole and sulfonylureas leading to severe hypoglycemia has been reported. Whether this interaction also occurs with other dosage forms of miconazole is not known.
7.3Cytochrome P450 2C9 Interactions There may be an interaction between glimepiride and inhibitors (e.g., fluconazole) and inducers (e.g., rifampin) of cytochrome P450 2C9. Fluconazole may inhibit the metabolism of glimepiride, causing increased plasma concentrations of glimepiride which may lead to hypoglycemia. Rifampin may induce the metabolism of glimepiride, causing decreased plasma concentrations of glimepiride which may lead to worsening glycemic control.
7.4Concomitant Administration of Colesevelam Colesevelam can reduce the maximum plasma concentration and total exposure of glimepiride when the two are coadministered. However, absorption is not reduced when glimepiride is administered 4 hours prior to colesevelam. Ther…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric Patients: Not recommended because of adverse effects on body weight and hypoglycemia ( 8.4 ). Geriatric or Renally Impaired Patients: At risk for hypoglycemia with glimepiride. Use caution in dose selection and titration, and monitor closely ( 8.5 , 8.6 ).
8.1Pregnancy Risk Summary Available data from a small number of published studies and postmarketing experience with Glimepiride use in pregnancy over decades have not identified any drug associated risks for major birth defects, miscarriage, or adverse maternal outcomes. However, sulfonylureas (including Glimepiride) cross the placenta and have been associated with neonatal adverse reactions such as hypoglycemia. Therefore, Glimepiride should be discontinued at least two weeks before expected delivery (see Clinical Considerations).
Poorly controlled diabetes in pregnancy is also associated with risks to the mother and fetus (see Clinical Considerations). In animal studies (see Data), there were no effects on embryo-fetal development following administration of Glimepiride to pregnant rats and rabbits at oral doses approximately 4000 times and 60 times the maximum human dose based on body surface area, respectively. However, fetotoxicity was observed in rats and rabbits at doses 50 times and 0.1 times the maximum human dose, respectively.
The estimated background risk of major birth defects is 6% to 10% in women with pregestational diabetes with a HbA1c >7% and has been reported to be as high as 20% to 25% in women with a HbA1c >10%. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo-fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, still birth, and macrosomia related morbidity. Fetal/neonatal adverse reactions Neonates of women with gestational diabetes who are treated with sulfonylureas during pregnancy may be at increased risk for neonatal intensive care admission and may develop respiratory distress, hypoglycemia, birth injury, and be large for gestational age.
Prolonged severe hypoglycemia, lasting 4–10 days, has been reported in neonates born to mothers receiving a sulfonylurea at the time of delivery and has been reported with the use of agents with a prolonged half-life. Observe newborns for symptoms of hypoglycemia and respiratory distress and manage accordingly. Dose adjustments during pregnancy and the postpartum period Due to reports of prolonged severe hypoglycemia in neonates born to mothers receiving a sulfonylurea at the time of delivery, Glimepiride should be discontinued at least two weeks before expected delivery (see Fetal/Neonatal Adverse Reactions).
Data Animal data In animal studies, there was no increase in congenital anomalies, but an increase in fetal deaths occurred in rats and rabbits at Glimepiride doses 50 times (rats) and 0.1 times (rabbits) the maximum recommended human dose (based on body surface area). This fetotoxicity was observed only at doses inducing maternal hypoglycemia and is believed to be directly related to the pharmacologic (hypoglycemic) action of Glimepiride, as has been similarly noted with other sulfonylureas.
8.2Lactation Risk Summary Breastfed infants of lactating women using Glimepiride should be monitored for symptoms of hypoglycemia (see Clinical Considerations). It is not known whether Glimepiride is excreted in human milk and there are no data on the effects of Glimepiride on milk production. Glimepiride is present in rat milk [see Data]. The developmental and health benefits of breastfeedin…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from a small number of published studies and postmarketing experience with Glimepiride use in pregnancy over decades have not identified any drug associated risks for major birth defects, miscarriage, or adverse maternal outcomes. However, sulfonylureas (including Glimepiride) cross the placenta and have been associated with neonatal adverse reactions such as hypoglycemia. Therefore, Glimepiride should be discontinued at least two weeks before expected delivery (see Clinical Considerations).
Poorly controlled diabetes in pregnancy is also associated with risks to the mother and fetus (see Clinical Considerations). In animal studies (see Data), there were no effects on embryo-fetal development following administration of Glimepiride to pregnant rats and rabbits at oral doses approximately 4000 times and 60 times the maximum human dose based on body surface area, respectively. However, fetotoxicity was observed in rats and rabbits at doses 50 times and 0.1 times the maximum human dose, respectively.
The estimated background risk of major birth defects is 6% to 10% in women with pregestational diabetes with a HbA1c >7% and has been reported to be as high as 20% to 25% in women with a HbA1c >10%. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo-fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, still birth, and macrosomia related morbidity. Fetal/neonatal adverse reactions Neonates of women with gestational diabetes who are treated with sulfonylureas during pregnancy may be at increased risk for neonatal intensive care admission and may develop respiratory distress, hypoglycemia, birth injury, and be large for gestational age.
Prolonged severe hypoglycemia, lasting 4–10 days, has been reported in neonates born to mothers receiving a sulfonylurea at the time of delivery and has been reported with the use of agents with a prolonged half-life. Observe newborns for symptoms of hypoglycemia and respiratory distress and manage accordingly. Dose adjustments during pregnancy and the postpartum period Due to reports of prolonged severe hypoglycemia in neonates born to mothers receiving a sulfonylurea at the time of delivery, Glimepiride should be discontinued at least two weeks before expected delivery (see Fetal/Neonatal Adverse Reactions).
Data Animal data In animal studies, there was no increase in congenital anomalies, but an increase in fetal deaths occurred in rats and rabbits at Glimepiride doses 50 times (rats) and 0.1 times (rabbits) the maximum recommended human dose (based on body surface area). This fetotoxicity was observed only at doses inducing maternal hypoglycemia and is believed to be directly related to the pharmacologic (hypoglycemic) action of Glimepiride, as has been similarly noted with other sulfonylureas.
🧒 Pediatric Use ▾
8.4Pediatric Use The pharmacokinetics, efficacy and safety of glimepiride have been evaluated in pediatric patients with type 2 diabetes as described below. Glimepiride is not recommended in pediatric patients because of its adverse effects on body weight and hypoglycemia. The pharmacokinetics of a 1 mg single dose of glimepiride was evaluated in 30 patients with type 2 diabetes (male = 7; female = 23) between ages 10 and 17 years.
The mean (± SD) AUC (0-last) (339±203 ng•hr/mL), Cmax (102±48 ng/mL) and t1/2 (3.1±1.7 hours) for glimepiride were comparable to historical data from adults (AUC ( 0-last ) 315±96 ng•hr/mL, Cmax 103±34 ng/mL and t1/2 5.3±4.1 hours). The safety and efficacy of glimepiride in pediatric patients was evaluated in a single-blind, 24-week trial that randomized 272 patients (8-17 years of age) with type 2 diabetes to glimepiride (n=135) or metformin (n=137). Both treatment-naïve patients (those treated with only diet and exercise for at least 2 weeks prior to randomization) and previously treated patients (those previously treated or currently treated with other oral antidiabetic medications for at least 3 months) were eligible to participate.
Patients who were receiving oral antidiabetic agents at the time of study entry discontinued these medications before randomization without a washout period. Glimepiride was initiated at 1 mg, and then titrated up to 2, 4 or 8 mg (mean last dose 4 mg) through Week 12, targeting a self-monitored fasting fingerstick blood glucose < 126 mg/dL. Metformin was initiated at 500 mg twice daily and titrated at Week 12 up to 1000 mg twice daily (mean last dose 1365 mg).
After 24 weeks, the overall mean treatment difference in HbA 1c between glimepiride and metformin was 0.2%, favoring metformin (95% confidence interval -0.3% to +0.6%). Based on these results, the trial did not meet its primary objective of showing a similar reduction in HbA 1c with glimepiride compared to metformin. Table 2.
Change from Baseline in HbA 1C and Body Weight in Pediatric Patients Taking Glimepiride or Metformin * Intent-to-treat population using last-observation-carried-forward for missing data (Glimepiride, n=127; metformin, n=126) + adjusted for baseline HbA 1C and Tanner Stage ** Difference is Glimepiride – metformin with positive differences favoring metformin Metformin Glimepiride Treatment-Naïve Patients* N=69 N=72 HbA 1C (%) Baseline (mean) 8.2
8.3Change from baseline (adjusted LS mean) + -1.2 -1.0 Adjusted Treatment Difference** (95%CI) 0.2 (-0.3; 0.6) Previously Treated Patients* N=57 N=55 HbA 1C (%) Baseline (mean) 9.0
8.7Change from baseline (adjusted LS mean) + -0.2
0.2Adjusted Treatment Difference** (95%CI) 0.4 (-0.4; 1.2) Body Weight (kg)* N=126 N=129 Baseline (mean) 67.3
66.5Change from baseline (adjusted LS mean)+ 0.7
2.0Adjusted Treatment Difference** (95% CI) 1.3 (0.3; 2.3) The profile of adverse reactions in pediatric patients treated with glimepiride was similar to that observed in adults [see Adverse Reactions ( 6 )]. Hypoglycemic events documented by blood glucose values <36 mg/dL were observed in 4% of pediatric patients treated with glimepiride and in 1% of pediatric patients treated with metformin. One patient in each treatment group experienced a severe hypoglycemic episode (severity was determined by the investigator based on observed signs and symptoms).
🧓 Geriatric Use ▾
8.5Geriatric Use In clinical trials of glimepiride, 1053 of 3491 patients (30%) were >65 years of age. No overall differences in safety or effectiveness were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out. There were no significant differences in glimepiride pharmacokinetics between patients with type 2 diabetes ≤65 years (n=49) and those >65 years (n=42) [see Clinical Pharmacology ( 12.3 ) ].
Glimepiride is substantially excreted by the kidney. Elderly patients are more likely to have renal impairment. In addition, hypoglycemia may be difficult to recognize in the elderly [see Dosage and Administration ( 2.1 ) and Warnings and Precautions ( 5.1 ) ].
Use caution when initiating glimepiride and increasing the dose of glimepiride in this patient population.
🆘 Overdosage ▾
10 OVERDOSAGE An overdosage of glimepiride, as with other sulfonylureas, can produce severe hypoglycemia. Mild episodes of hypoglycemia can be treated with oral glucose. Severe hypoglycemic reactions constitute medical emergencies requiring immediate treatment.
Severe hypoglycemia with coma, seizure, or neurological impairment can be treated with glucagon or intravenous glucose. Continued observation and additional carbohydrate intake may be necessary because hypoglycemia may recur after apparent clinical recovery [see Warnings and Precautions ( 5.1 ) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Glimepiride primarily lowers blood glucose by stimulating the release of insulin from pancreatic beta cells. Sulfonylureas bind to the sulfonylurea receptor in the pancreatic beta-cell plasma membrane, leading to closure of the ATP-sensitive potassium channel, thereby stimulating the release of insulin.
12.2Pharmacodynamics In healthy subjects, the time to reach maximal effect (minimum blood glucose concentrations) was approximately 2-3 hours after single oral doses of glimepiride. The effects of glimepiride on HbA 1c , fasting plasma glucose, and post-prandial glucose have been assessed in clinical trials [ see Clinical Studies ( 14 ) ].
12.3Pharmacokinetics Absorption: Studies with single oral doses of glimepiride in healthy subjects and with multiple oral doses in patients with type 2 diabetes showed peak drug concentrations (C max ) 2 to 3 hours post-dose. When glimepiride was given with meals, the mean C max and AUC (area under the curve) were decreased by 8% and 9%, respectively. Glimepiride does not accumulate in serum following multiple dosing.
The pharmacokinetics of glimepiride does not differ between healthy subjects and patients with type 2 diabetes. Clearance of glimepiride after oral administration does not change over the 1 mg to 8 mg dose range, indicating linear pharmacokinetics. In healthy subjects, the intra- and inter-individual variabilities of glimepiride pharmacokinetic parameters were 15-23% and 24-29%, respectively.
Distribution: After intravenous dosing in healthy subjects, the volume of distribution (Vd) was
8.8L (113 mL/kg), and the total body clearance (CL) was 47.8 mL/min. Protein binding was greater than 99.5%. Metabolism: Glimepiride is completely metabolized by oxidative biotransformation after either an intravenous or oral dose.
The major metabolites are the cyclohexyl hydroxy methyl derivative (M1) and the carboxyl derivative (M2). Cytochrome P450 2C9 is involved in the biotransformation of glimepiride to M1. M1 is further metabolized to M2 by one or several cytosolic enzymes.
M2 is inactive. In animals, M1 possesses about one-third of the pharmacological activity of glimepiride, but it is unclear whether M1 results in clinically meaningful effects on blood glucose in humans. Excretion: When 14 C-glimepiride was given orally to 3 healthy male subjects, approximately 60% of the total radioactivity was recovered in the urine in 7 days.
M1 and M2 accounted for 80-90% of the radioactivity recovered in the urine. The ratio of M1 to M2 in the urine was approximately 3:2 in two subjects and 4:1 in one subject. Approximately 40% of the total radioactivity was recovered in feces.
M1 and M2 accounted for approximately 70% (ratio of M1 to M2 was 1:3) of the radioactivity recovered in feces. No parent drug was recovered from urine or feces. After intravenous dosing in patients, no significant biliary excretion of glimepiride or its M1 metabolite was observed.
Specific Populations Geriatric Patients : A comparison of glimepiride pharmacokinetics in patients with type 2 diabetes ≤65 years and those >65 years was evaluated in a multiple-dose study using glimepiride 6 mg daily. There were no significant differences in glimepiride pharmacokinetics between the two age groups. The mean AUC at steady state for the older patients was approximately 13% lower than that for the younger patients; the mean weight-adjusted clearance for the older patients was approximately 11% higher than that for the younger patients.
Gender : There were no differences between males and females in the pharmacokinetics of glimepiride when adjustment was made for differences in body weight. Race : No studies have been conducted to assess the effects of race on glimepiride pharmacokinetics but in placebo-controlled trials of glimepiride in patients with type 2 diabetes, the reduction in HbA 1C was comparable in Caucasians (n = 536), blacks (n = 63), and Hispanics (n = 63). Renal Impair…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Glimepiride primarily lowers blood glucose by stimulating the release of insulin from pancreatic beta cells. Sulfonylureas bind to the sulfonylurea receptor in the pancreatic beta-cell plasma membrane, leading to closure of the ATP-sensitive potassium channel, thereby stimulating the release of insulin.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Glimepiride Tablets are available in the following strengths and package sizes: 1 mg (Scored white to off-white, round imprinted with "CTI 115" on one side) are supplied in: Bottles of 90 . . . . . . . . .(NDC 43063-697-90) Store at 25ºC (77ºF); excursions permitted to 20ºC to 25ºC (68º to 77ºF) (See USP Controlled Room Temperature). Dispense in well-closed containers with safety closures.
📋 Description ▾
11 DESCRIPTION Glimepiride Tablets are an oral sulfonylurea that contains the active ingredient glimepiride. Chemically, glimepiride is identified as 1-[[p-[2-(3-ethyl-4-methyl-2-oxo-3-pyrroline-1-carboxamido) ethyl]phenyl]sulfonyl]-3-(trans-4-methylcyclohexyl)urea (C 24 H 34 N 4 O 5 S) with a molecular weight of 490.62. Glimepiride is a white to yellowish-white, crystalline, odorless to practically odorless powder and is practically insoluble in water.
The structural formula is: Glimepiride Tablets contain the active ingredient glimepiride and the following inactive ingredients: lactose monohydrate, magnesium stearate, microcrystalline cellulose, poloxamer, povidone, and sodium starch glycolate. Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypoglycemia Explain the symptoms and treatment of hypoglycemia as well as conditions that predispose to hypoglycemia. Inform patients that their ability to concentrate and react may be impaired as a result of hypoglycemia and that this may present a risk in situations where these abilities are especially important, such as driving or operating other machinery [see Warnings and Precautions ( 5.1 )]. Hypersensitivity Reactions Inform patients that hypersensitivity reactions may occur with Glimepiride and that if a reaction occurs to seek medical treatment and discontinue Glimepiride [see Warnings and Precautions ( 5.2 )].
Pregnancy Advise females of reproductive potential to inform their prescriber of a known or suspected pregnancy [see Use in Specific Populations ( 8.1 )]. Lactation Advise breastfeeding women taking Glimepiride to monitor breastfed infants for signs of hypoglycemia (e.g., jitters, cyanosis, apnea, hypothermia, excessive sleepiness, poor feeding, seizures) [see Use in Specific Populations ( 8.2 )]. Manufactured and Distributed by: Carlsbad Technology, Inc.
5923 Balfour Court Carlsbad, CA 92008 Revised: 03/2024 CTI-16 Rev. H