
Naproxen 375 mg Tablet, 60-count — NDC 43353-218-53 (Billing 43353-0218-53)
This is a package of 60 tablets of Naproxen 375 mg Tablet from Aphena Pharma Solutions - Tennessee, LLC, marketed since Jun 2016 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Naproxen (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 008361
- GCN: 35792
- GPI-14 (Medi-Span): 66100060000310
- HICL (First Databank): 003727
- AHFS class code: 28:08.04.04
- RxCUI (RxNorm): 198012
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Prescription naproxen is used to relieve pain, tenderness, swelling, and stiffness caused by osteoarthritis (arthritis caused by a breakdown of the lining of the joints), rheumatoid arthritis (arthritis caused by swelling of the lining of the joints), juvenile arthritis (a form of joint disease in children), and ankylosing spondylitis (arthritis that mainly affects the spine). Prescription naproxen tablets, extended-release tablets, and suspension are also used to relieve shoulder pain caused by bursitis (inflammation of a fluid-filled sac in the shoulder joint), tendinitis (inflammation of th...
Read the full MedlinePlus article ↗- It relieves pain, inflammation and fever. Prescription versions treat arthritis, tendonitis, bursitis, acute gout and painful periods. Over-the-counter versions handle minor aches...
- Take it by mouth with a full glass of water. Over-the-counter products are taken every 8 to 12 hours while symptoms last, and you should use the smallest dose that works. For presc...
- Headache, indigestion, heartburn, nausea and swelling are common. Call your doctor if you have black stools, vomit blood, a rash, yellow skin or eyes, or chest pain.
- Usually not. Combining naproxen with other NSAIDs or aspirin raises bleeding risk with little added benefit. Naproxen can also interfere with low-dose aspirin taken for your heart,...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Naproxen — tap one for details:
Naproxen may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1110 | $6.66 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 43353-0218-53 You're viewing this Main listing | 60 TABLET in 1 BOTTLE | 2016-08-18 | — | Active |
| 43353-0218-80 43353-218-80 | 180 TABLET in 1 BOTTLE | 2016-08-18 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 43353-0218-80?
What NDC number is used to bill for this package of Naproxen 375 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Naproxen 375 mg 49483-0617-01 | TIME | 100 tablets | $0.059 | AB | Availability likely | — |
| Naproxen 375 mg 50228-0435-01 | ScieGen | 100 tablets | $0.059 | AB | Availability likely | — |
| Naproxen 375 mg 50268-0595-15 | AvPAK | 50 tablets | $0.059 | AB | Availability likely | — |
| Naproxen 375 mg 65162-0189-10 | Amneal | 100 tablets | $0.059 | AB | Availability likely | — |
| Naproxen 375 mg 68462-0189-01 | Glenmark | 100 tablets | $0.059 | AB | Availability likely | — |
| Naproxen 375 mg 70010-0138-01 | Granules | 100 tablets | $0.059 | AB | Availability likely | — |
| Naproxen 375 mg 76282-0341-01 | Exelan | 100 tablets | $0.059 | — | Availability likely | — |
| Naproxen 375 mg 42494-0453-10 | Cameron | 100 tablets | $2.234 | AB | Availability likely | — |
| Naproxen 375 mg 25000-0139-03 | MARKSANS | 30 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 43063-0650-06 | PD-Rx | 6 tablets | — | AB | FDA listed | — |
| Naproxen 375 mgthis 43353-0218-53 | Aphena | 60 tablets | — | — | FDA listed | — |
| Naproxen 375 mg 45865-0238-60 | Medsource | 60 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 50090-1583-02 | A-S | 30 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 50090-1584-01 | A-S | 60 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 50090-1585-00 | A-S | 20 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 50090-4636-00 | A-S | 20 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 50090-4637-01 | A-S | 60 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 50090-4638-00 | A-S | 10 tablets | — | AB | Discontinued | — |
| Naproxen 375 mg 51655-0657-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 53746-0189-01 | Amneal | 100 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 55700-0987-30 | Quality | 30 tablets | — | AB | Discontinued | — |
| Naproxen 375 mg 60760-0644-20 | ST. | 20 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 62207-0746-43 | Granules | 100 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 63187-0535-15 | Proficient | 15 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 63629-8512-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 63629-8513-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 65862-0521-01 | Aurobindo | 100 tablets | — | — | FDA listed | — |
| Naproxen 375 mg 67046-0500-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 68788-7946-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 68788-8844-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| naproxen 375 mg 69097-0854-07 | Cipla | 100 tablets | — | — | FDA listed | — |
| Naproxen 375 mg 70518-3486-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 71335-0095-01 | Bryant | 20 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 71335-0255-01 | Bryant | 20 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 71335-1850-01 | Bryant | 20 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 71610-0591-53 | Aphena | 60 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 72189-0425-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 76420-0788-01 | Asclemed | 1 tablet | — | AB | FDA listed | — |
| Naproxen 375 mg 77771-0435-01 | Radha | 100 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 80425-0010-01 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 80425-0048-01 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 80425-0175-02 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 82868-0030-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 85766-0106-00 | Sportpharm | 1000 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 72162-2275-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Naproxen 375 mg 85534-0023-00 | HAWAII | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISK OF SERIOUS CARDIOVASCULAR AND GASTROINTESTINAL EVENTS Cardiovascular Thrombotic Events Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use (see WARNINGS ). Naproxen tablets are contraindicated in the setting of coronary artery bypass graft (CABG) surgery (see CONTRAINDICATIONS , WARNINGS ).
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs cause an increased risk of serious gastrointestinal (GI) adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. These events can occur at any time during use and without warning symptoms. Elderly patients and patients with a prior history of peptic ulcer disease and/or GI bleeding are at greater risk for serious GI events (see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carefully consider the potential benefits and risks of naproxen tablets and other treatment options before deciding to use naproxen tablets. Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals (see WARNINGS: Gastrointestinal Bleeding, Ulceration, and Perforation) . Naproxen tablets are indicated: For the relief of the signs and symptoms of rheumatoid arthritis For the relief of the signs and symptoms of osteoarthritis For the relief of the signs and symptoms of ankylosing spondylitis For the relief of the signs and symptoms of juvenile arthritis Naproxen tablets are also indicated: For relief of the signs and symptoms of tendonitis For relief of the signs and symptoms of bursitis For relief of the signs and symptoms of acute gout For the management of pain For the management of primary dysmenorrhea
⏱️ Dosage and Administration ▾
OVERDOSAGE Symptoms following acute NSAID overdosages have been typically limited to lethargy, drowsiness, nausea, vomiting, and epigastric pain, which have been generally reversible with supportive care. Gastrointestinal bleeding has occurred. Hypertension, acute renal failure, respiratory depression, and coma have occurred, but were rare.
Because naproxen sodium may be rapidly absorbed, high and early blood levels should be anticipated. A few patients have experienced convulsions, but it is not clear whether or not these were drug-related. It is not known what dose of the drug would be life threatening.
(see WARNINGS; Cardiovascular Thrombotic Events, Gastrointestinal Bleeding, Ulceration, and Perforation, Hypertension , Renal Toxicity and Hyperkalemia ). Manage patients with symptomatic and supportive care following an NSAID overdosage. There are no specific antidotes.
Hemodialysis does not decrease the plasma concentration of naproxen because of the high degree of its protein binding. Consider emesis and/or activated charcoal (60 to 100 g in adults, 1 to 2 g/kg of body weight in pediatric patients) and/or osmotic cathartic in symptomatic patients seen within four hours of ingestion or in patients with a large overdosage (5 to 10 times the recommended dosage). Forced diuresis, alkalinization of urine, hemodialysis, or hemoperfusion may not be useful due to high protein binding.
For additional information about overdosage treatment contact a poison control center (1-800-222-1222). DOSAGE AND ADMINISTRATION Carefully consider the potential benefits and risks of naproxen tablets and other treatment options before deciding to use naproxen tablets. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS; Gastrointestinal Bleeding, Ulceration, and Perforation ).
After observing the response to initial therapy with naproxen tablets, the dose and frequency should be adjusted to suit an individual patient’s needs. Different dose strengths and formulations (i.e., tablets, suspension) of the drug are not necessarily bioequivalent. This difference should be taken into consideration when changing formulation.
Although naproxen tablets, naproxen suspension, naproxen delayed-released tablets, and naproxen sodium tablets all circulate in the plasma as naproxen, they have pharmacokinetic differences that may affect onset of action. Onset of pain relief can begin within 1 hour in patients taking naproxen. The recommended strategy for initiating therapy is to choose a formulation and a starting dose likely to be effective for the patient and then adjust the dosage based on observation of benefit and/or adverse events.
A lower dose should be considered in patients with renal or hepatic impairment or in elderly patients (see WARNINGS; Hepatotoxicity , and Renal Toxicity and Hyperkalemia , and PRECAUTIONS ; Geriatric Use ). Geriatric Patients Studies indicate that although total plasma concentration of naproxen is unchanged, the unbound plasma fraction of naproxen is increased in the elderly. Caution is advised when high doses are required and some adjustment of dosage may be required in elderly patients.
As with other drugs used in the elderly, it is prudent to use the lowest effective dose. Patients With Moderate to Severe Renal Impairment Naproxen-containing products are not recommended for use in patients with moderate to severe and severe renal impairment (creatinine clearance <30 mL/min) (see WARNINGS: Renal Effects ). Rheumatoid Arthritis, Osteoarthritis and Ankylosing Spondylitis Naproxen Tablets 250 mg or 375 mg or 500 mg twice daily twice daily twice daily During long-term administration, the dose of naproxen may be adjusted up or down depending on the clinical response of the patient.
A lower daily dose may suffice for long-term administration. The morning and evening doses do not have to be equal in size and the administration of the drug more frequently than twice dail… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Naproxen tablets are contraindicated in the following patents: Known hypersensitivity (e.g., anaphylactic reactions and serious skin reactions) to naproxen or any components of the drug product (see WARNINGS ; Anaphylactic Reactions, Serious Skin Reactions) . History of asthma, urticaria, or other allergic-type reactions after taking aspirin or other NSAIDs. Severe, sometimes fatal, anaphylactic reactions to NSAIDs have been reported in such patients (see WARNINGS ; Anaphylactic Reactions, Exacerbation of Asthma Related to Aspirin Sensitivity) .
In the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS; Cardiovascular Thrombotic Events) .
⚠️ Warnings ▾
WARNINGS Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as naproxen, increases the risk of serious gastrointestinal (GI) events (see WARNINGS; Gastrointestinal Bleeding, Ulceration, and Perforation) . Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled, clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contraindicated in the setting of CABG (see CONTRAINDICATIONS ). Post-MI Patients Observational studies conducted in the Danish National Registry have demonstrated that patients treated with NSAIDs in the post-MI period were at increased risk of reinfarction, CV-related death, and all-cause mortality beginning in the first week of treatment. In this same cohort, the incidence of death in the first year post-MI was 20 per 100 person years in NSAID-treated patients compared to 12 per 100 person years in non-NSAID exposed patients.
Although the absolute rate of death declined somewhat after the first year post-MI, the increased relative risk of death in NSAID users persisted over at least the next four years of follow-up. Avoid the use of naproxen tablets in patients with a recent MI unless the benefits are expected to outweigh the risk of recurrent CV thrombotic events. If naproxen tablets are used in patients with a recent MI, monitor patients for signs of cardiac ischemia.
Gastrointestinal Bleeding, Ulceration, and Perforation NSAIDs, including naproxen cause serious gastrointestinal (GI) adverse events including inflammation, bleeding, ulceration, and perforation of the esophagus, stomach, small intestine, or large intestine, which can be fatal. These serious adverse events can occur at any time, with or without warning symptoms, in patients treated with NSAIDs. Only one in five patients who develop a serious upper GI adverse event on NSAID therapy, is symptomatic.
Upper GI ulcers, gross bleeding, or perforation caused by NSAIDs occured in approximately 1% of patients treated for 3 to 6 months, and in about 2% to 4% of patients treated for one year. However, even short-term NSAID therapy is not without risk. Risk Factors for GI Bleeding, Ulceration, and Perforation Patients with a prior history of peptic ulcer disease and/or GI bleeding who used NSAIDs had a greater than 10-fold increased risk for developing a GI bleed compared to patients without these r… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
Data Human Data There is some evidence to suggest that when inhibitors of prostaglandin synthesis are used to delay preterm labor there is an increased risk of neonatal complications such as necrotizing enterocolitis, patent ductus arteriosus and intracranial hemorrhage. Naproxen treatment given in late pregnancy to delay parturition has been associated with persistent pulmonary hypertension, renal dysfunction and abnormal prostaglandin E levels in preterm infants. Because of the known effects of nonsteroidal anti-inflammatory drugs on the fetal cardiovascular system (closure of ductus arteriosus), use during pregnancy (particularly starting at 30-weeks of gestation, or third trimester) should be avoided.
Animal Data Reproduction studies have been performed in rats at 20 mg/kg/day (0.13 times the maximum recommended human daily dose of 1500 mg/day based on body surface area comparison), rabbits at 20 mg/kg/day (0.26 times the maximum recommended human daily dose, based on body surface area comparison), and mice at 170 mg/kg/day (0.6 times the maximum recommended human daily dose based on body surface area comparison) with no evidence of impaired fertility or harm to the fetus due to the drug. Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization.
In animal studies, administration of prostaglandin synthesis inhibitors such as naproxen resulted in increased pre- and post-implantation loss. Labor and Delivery There are no studies on the effects of naproxen tablets during labor or delivery. In animal studies, NSAIDS, including naproxen, inhibit prostaglandin synthesis, cause delayed parturition, and increase the incidence of stillbirth.
Nursing Mothers The naproxen anion has been found in the milk of lactating women at a concentration equivalent to approximately 1% of maximum naproxen concentration in plasma. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for naproxen tablets and any potential adverse effects on the breastfed infant from the naproxen tablets or from the underlying maternal condition Females and Males of Reproductive Potential Based on the mechanism of action, the use of prostaglandin-mediated NSAIDs, including naproxen, may delay or prevent rupture of ovarian follicles, which has been associated with reversible infertility in some women.
Published animal studies have shown that administration of prostaglandin synthesis inhibitors has the potential to disrupt prostaglandin- mediated follicular rupture required for ovulation. Small studies in women treated with NSAIDs have also shown a reversible delay in ovulation Consider withdrawal of NSAIDs, including naproxen tablets, in women who have difficulties conceiving or who are undergoing investigation of infertility. Pediatric Use Safety and effectiveness in pediatric patients below the age of 2 years have not been established.
Pediatric dosing recommendations for juvenile arthritis are based on well-controlled studies (see DOSAGE AND ADMINISTRATION ). There are no adequate effectiveness or dose-response data for other pediatric conditions, but the experience in juvenile arthritis and other use experience have established that single doses of 2.5 to 5 mg/kg (as naproxen suspension, see DOSAGE AND ADMINISTRATION ), with total daily dose not exceeding 15 mg/kg/day, are well tolerated in pediatric patients over 2 years of age. Safety and effectiveness in pediatric patients below the age of 2 years have not been established.
Geriatric Use Elderly patients, compared to younger patients, are at greater risk for NSAID-associated serious cardiovascular, gastrointestinal, and/or renal adverse reactions. If the anticipated benefit for the elderly patient outweighs these potential risks, start dosing at the low end of the dosing range, and monitor patients for adverse effects (see WARNINGS; Cardiovascular T… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Cardiovascular Thrombotic Events (see WARNINGS ) GI Bleeding, Ulceration and Perforation (see WARNINGS ) Hepatotoxicity (see WARNINGS ) Hypertension (see WARNINGS ) Heart Failure and Edema (see WARNINGS ) Renal Toxicity and Hyperkalemia (see WARNINGS ) Anaphylactic Reactions (see WARNINGS ) Serious Skin Reactions (see WARNINGS ) Hematologic Toxicity (see WARNINGS ) Adverse reactions reported in controlled clinical trials in 960 patients treated for rheumatoid arthritis or osteoarthritis are listed below.
In general, reactions in patients treated chronically were reported 2 to 10 times more frequently than they were in short-term studies in the 962 patients treated for mild to moderate pain or for dysmenorrhea. The most frequent complaints reported related to the gastrointestinal tract. A clinical study found gastrointestinal reactions to be more frequent and more severe in rheumatoid arthritis patients taking daily doses of 1500 mg naproxen compared to those taking 750 mg naproxen (see CLINICAL PHARMACOLOGY ).
In controlled clinical trials with about 80 pediatric patients and in well-monitored, open-label studies with about 400 pediatric patients with juvenile arthritis treated with naproxen, the incidence of rash and prolonged bleeding times were increased, the incidence of gastrointestinal and central nervous system reactions were about the same, and the incidence of other reactions were lower in pediatric patients than in adults. In patients taking naproxen in clinical trials, the most frequently reported adverse experiences in approximately 1% to 10% of patients are: Gastrointestinal (GI) Experiences, including: heartburn*, abdominal pain*, nausea*, constipation*, diarrhea, dyspepsia, stomatitis Central Nervous System: headache*, dizziness*, drowsiness*, lightheadedness, vertigo Dermatologic: pruritus (itching)*, skin eruptions*, ecchymoses*, sweating, purpura Special Senses: tinnitus*, visual disturbances, hearing disturbances Cardiovascular: edema*, palpitations General: dyspnea*, thirst *Incidence of reported reaction between 3% and 9%.
Those reactions occurring in less than 3% of the patients are unmarked. In patients taking NSAIDs, the following adverse experiences have also been reported in approximately 1% to 10% of patients. Gastrointestinal (GI) Experiences, including: flatulence, gross bleeding/ perforation, GI ulcers (gastric/duodenal), vomiting General: abnormal renal function, anemia, elevated liver enzymes, increased bleeding time, rashes The following are additional adverse experiences reported in <1% of patients taking naproxen during clinical trials and through postmarketing reports.
Those adverse reactions observed through postmarketing reports are italicized. Body as a Whole: anaphylactoid reactions, angioneurotic edema, menstrual disorders, pyrexia (chills and fever) Cardiovascular: congestive heart failure, vasculitis, hypertension, pulmonary edema Gastrointestinal: inflammation, bleeding (sometimes fatal, particularly in the elderly), ulceration, perforation and obstruction of the upper or lower gastrointestinal tract. Esophagitis, stomatitis, hematemesis, pancreatitis, vomiting, colitis, exacerbation of inflammatory bowel disease (ulcerative colitis, Crohn’s disease) Hepatobiliary: jaundice, abnormal liver function tests, hepatitis (some cases have been fatal) Hemic and Lymphatic: eosinophilia, leucopenia, melena, thrombocytopenia, agranulocytosis, granulocytopenia, hemolytic anemia, aplastic anemia Metabolic and Nutritional: hyperglycemia, hypoglycemia Nervous System: inability to concentrate, depression, dream abnormalities, insomnia, malaise, myalgia, muscle weakness, aseptic meningitis, cognitive dysfunction, convulsions Respiratory: eosinophilic pneumonitis, asthma Dermatologic: alopecia, urticaria, skin rashes, toxic epidermal necrolysis, erythema multiforme, erythema nodosum, fi… [Excerpted — this section continues on DailyMed.]
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Naproxen has analgesic, anti-inflammatory, and antipyretic properties. The sodium salt of naproxen has been developed as a more rapidly absorbed formulation of naproxen for use as an analgesic. The mechanism of action of the naproxen, like that of other NSAIDs, is not completely understood but involves inhibition of cyclooxygenase (COX-1 and COX-2).
Naproxen is a potent inhibitor of prostaglandin synthesis in vitro. Naproxen concentrations reached during therapy have produced in vivo effects. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models.
Prostaglandins are mediators of inflammation. Because naproxen is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues. Pharmacokinetics Naproxen is rapidly and completely absorbed from the gastrointestinal tract with an in vivo bioavailability of 95%.
The elimination half-life of naproxen is unchanged across products ranging from 12 to 17 hours. Steady-state levels of naproxen are reached in 4 to 5 days, and the degree of naproxen accumulation is consistent with this half-life. Absorption Naproxen Tablets, USP After administration of naproxen tablets, peak plasma levels are attained in 2 to 4 hours.
Distribution Naproxen has a volume of distribution of
0.16L/kg. At therapeutic levels naproxen is greater than 99% albumin-bound. At doses of naproxen greater than 500 mg/day there is less than proportional increase in plasma levels due to an increase in clearance caused by saturation of plasma protein binding at higher doses (average trough Css 36.5, 49.2 and 56.4 mg/L with 500, 1000 and 1500 mg daily doses of naproxen, respectively).
The naproxen anion has been found in the milk of lactating women at a concentration equivalent to approximately 1% of maximum naproxen concentration in plasma (see PRECAUTIONS: Nursing Mothers) . Elimination Metabolism Naproxen is extensively metabolized in the liver to 6-0-desmethyl naproxen, and both parent and metabolites do not induce metabolizing enzymes. Both naproxen and 6-0-desmethyl naproxen are further metabolized to their respective acylglucuronide conjugated metabolites.
Excretion The clearance of naproxen is 0.13 mL/min/kg. Approximately 95% of the naproxen from any dose is excreted in the urine, primarily as naproxen (<1%), 6-0-desmethyl naproxen (<1%) or their conjugates (66% to 92%). The plasma half-life of the naproxen anion in humans ranges from 12 to 17 hours.
The corresponding half-lives of both naproxen’s metabolites and conjugates are shorter than 12 hours, and their rates of excretion have been found to coincide closely with the rate of naproxen disappearance from the plasma. Small amounts, 3% or less of the administered dose, are excreted in the feces. In patients with renal failure metabolites may accumulate (see WARNINGS ; Renal Toxicity and Hyperkalemia) .
Special Populations Pediatric Patients In pediatric patients aged 5 to 16 years with arthritis, plasma naproxen levels following a 5 mg/kg single dose of naproxen suspension (see DOSAGE AND ADMINISTRATION ) were found to be similar to those found in normal adults following a 500 mg dose. The terminal half-life appears to be similar in pediatric and adult patients. Pharmacokinetic studies of naproxen were not performed in pediatric patients younger than 5 years of age.
Pharmacokinetic parameters appear to be similar following administration of naproxen tablets in pediatric patients. Geriatric Patients Studies indicate that although total plasma concentration of naproxen is unchanged, the unbound plasma fraction of naproxen is increased in the elderly, although the unbound fraction is < 1% of the total naproxen concentration. Unbound trough naproxen concentrations in elderly subjects have been reported to range from 0.12% to 0.19% of total naproxen concentration, compared with 0.05% to 0.075% in younger subj… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Naproxen Tablets, USP: 250 mg: Light Yellow, Round, biconvex tablets de-bossed with ‘I’ on the left side of bisect and ‘G’ on the right side of bisect on one side and ‘340’ on the other, supplied in bottles of 100’s count (NDC 76282-340-01) and 500’s count (NDC 76282-340-05). Naproxen Tablets, USP: 375 mg: Light Pink, Capsule shaped, biconvex tablets de-bossed with ‘IG’ on one side and ‘341’ on the other, supplied in bottles of 100’s count (NDC 76282-341-01) and 500’s count (NDC 76282-341-05). Naproxen Tablets, USP: 500 mg: Light Yellow, Capsules shaped, biconvex tablets de-bossed with ‘I’ on the left side of bisect and ‘G’ on the right side of bisect on one side and ‘342’ on the other, supplied in bottles of 100’s count (NDC 76282-342-01) and 500’s count (NDC 76282-342-05).
Store at 20° to 25°C (68° to 77°F); [See USP Controlled Room Temperature]. Dispense in tight, light-resistant containers. *All brand names mentioned are registered trademark of their respective owners and are not of Exelan Pharmaceuticals, Inc. Rev: 06/2016
📋 Description ▾
Naproxen Tablets, USP Rx only
DESCRIPTION Naproxen, USP is a propionic acid derivative related to the arylacetic acid group of nonsteroidal anti-inflammatory drugs. The chemical name for naproxen, USP is (S)-6-methoxy-α-methyl-2-naphthaleneacetic acid. It has the following structural formula: Naproxen, USP has a molecular weight of 230.26 and a molecular formula of C 14 H 14 O 3 .
Naproxen, USP is an odorless, white to off-white crystalline substance. It is lipid-soluble, practically insoluble in water at low pH and freely soluble in water at high pH. The octanol/water partition coefficient of naproxen at pH 7.4 is 1.6 to 1.8.
Naproxen tablets, USP are available as yellow tablets containing 250 mg of naproxen USP, pink tablets containing 375 mg of naproxen USP, and yellow tablets containing 500 mg of naproxen USP for oral administration. The inactive ingredients are croscarmellose sodium, povidone, iron oxide yellow, iron oxide red colloidal silicon dioxide and magnesium stearate. structure
💬 Medication Guide ▾
Medication Guide for Nonsteroidal Anti-Inflammatory Drugs (NSAIDs) What is the most important information I should know about medicines called Non-Steroidal Anti- Inflammatory Drugs (NSAIDs)? NSAIDs can cause serious side effects, including: Increased risk of a heart attack or stroke that can lead to death. This risk may happen early in treatment and may increase: o with increasing doses of NSAIDs o with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a “coronary artery bypass graft (CABG).” Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to.
You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. Increased risk of bleeding, ulcers, and tears (perforation) of the esophagus (tube leading from the mouth to the stomach), stomach and intestines: o anytime during use o without warning symptoms o that may cause death The risk of getting an ulcer or bleeding increases with: o past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs o taking medicines called “corticosteroids”, “anticoagulants”, “SSRIs”, or “SNRIs” o increasing doses of NSAIDs o longer use of NSAIDs o smoking o drinking alcohol o older age o poor health o advanced liver disease o bleeding problems NSAIDs should only be used: o exactly as prescribed o at the lowest dose possible for your treatment o for the shortest time needed What are NSAIDs?
NSAIDs are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as different types of arthritis, menstrual cramps, and other types of short-term pain. Who should not take NSAIDs? Do not take NSAIDs: if you have had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAIDs. right before or after heart bypass surgery.
Before taking NSAIDs, tell your healthcare provider about all of your medical conditions, including if you: have liver or kidney problems have high blood pressure have asthma are pregnant or plan to become pregnant. Talk to your healthcare provider if you are considering taking NSAIDs during pregnancy. You should not take NSAIDs after 29 weeks of pregnancy. are breastfeeding or plan to breastfeed.
Tell your healthcare provider about all of the medicines you take, including prescription or over-the-counter medicines, vitamins or herbal supplements . NSAIDs and some other medicines can interact with each other and cause serious side effects. Do not start taking any new medicine without talking to your healthcare provider first.
What are the possible side effects of NSAIDs? NSAIDs can cause serious side effects, including: See “What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? new or worse high blood pressure heart failure liver problems including liver failure kidney problems including kidney failure low red blood cells (anemia) life-threatening skin reactions life-threatening allergic reactions Other side effects of NSAIDs include: stomach pain, constipation, diarrhea, gas, heartburn, nausea, vomiting, and dizziness.
Get emergency help right away if you have any of the following symptoms: shortness of breath or trouble breathing chest pain weakness in one part or side of your body slurred speech swelling of the face or throat Stop taking your NSAID and call your healthcare provider right away if you get any of the following symptoms: nausea more tired or weaker than usual diarrhea itching your skin or eyes look yellow indigestion or stomach pain flu-like symptoms vomit blood there is blood in your bowel movement or it is black and sticky like tar unusual weight gain skin rash or blisters with fever swelling of the arms, legs, hands and feet If you take too much of your NSAID, call your healthcare provider or get medical help right away.
These are not all the possible side effects of NSAIDs. For more information, ask your health… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
Renal Toxicity and Hyperkalemia Renal Toxicity Long-term administration of NSAIDs has resulted in renal papillary necrosis and other renal injury. Renal toxicity has also been seen in patients in whom renal prostaglandins have a compensatory role in the maintenance of renal perfusion. In these patients, administration of an NSAID may cause a dose-dependent reduction in prostaglandin formation and, secondarily, in renal blood flow, which may precipitate overt renal decompensation.
Patients at greatest risk of this reaction are those with impaired renal function, dehydration, hypovolemia, heart failure, liver dysfunction, those taking diuretics and ACE inhibitors or ARBs, and the elderly. Discontinuation of NSAID therapy is usually followed by recovery to the pretreatment state No information is available from controlled clinical studies regarding the use of naproxen tablets in patients with advanced renal disease. The renal effects of naproxen tablets may hasten the progression of renal dysfunction in patients with preexisting renal disease.
Correct volume status in dehydrated or hypovolemic patients prior to initiating naproxen tablets. Monitor renal function in patients with renal or hepatic impairment, heart failure, dehydration, or hypovolemia during use of naproxen tablets ( see PRECAUTIONS ; Drug Interactions) . Avoid the use of naproxen tablets in patients with advanced renal disease unless the benefits are expected to outweigh the risk of worsening renal function.
If naproxen tablets are used in patients with advanced renal disease, monitor patients for signs of worsening renal function. Hyperkalemia Increases in serum potassium concentration, including hyperkalemia, have been reported with use of NSAIDs, even in some patients without renal impairment. In patients with normal renal function, these effects have been attributed to a hyporeninemic-hypoaldosteronism state.
Anaphylactic Reactions Naproxen has been associated with anaphylactic reactions in patients with and without known hypersensitivity to naproxen and in patients with aspirin-sensitive asthma (see CONTRAINDICATIONS , WARNINGS ; Exacerbation of Asthma Related to Aspirin Sensitivity) . Exacerbation of Asthma Related to Aspirin Sensitivity A subpopulation of patients with asthma may have aspirin-sensitive asthma which may include chronic rhinosinusitis complicated by nasal polyps; severe, potentially fatal bronchospasm; and/or intolerance to aspirin and other NSAIDs.
Because cross-reactivity between aspirin and other NSAIDs has been reported in such aspirin-sensitive patients, naproxen tablets are contraindicated in patients with this form of aspirin sensitivity ( see CONTRAINDICATIONS ). When naproxen tablets are used in patients with preexisting asthma (without known aspirin sensitivity), monitor patients for changes in the signs and symptoms of asthma. Serious Skin Reactions NSAIDs, including naproxen, can cause serious skin adverse reactions such as exfoliative dermatitis, Stevens-Johnson Syndrome (SJS), and toxic epidermal necrolysis (TEN), which can be fatal.
These serious events may occur without warning. Inform patients about the signs and symptoms of serious skin reactions and to discontinue the use of naproxen tablets at the first appearance of skin rash or any other sign of hypersensitivity. naproxen tablets are contraindicated in patients with previous serious skin reactions to NSAIDs (see CONTRAINDICATIONS ). Premature Closure of Fetal Ductus Arteriosus Naproxen may cause premature closure of the fetal ductus arteriosus.
Avoid use of NSAIDs, including naproxen tablets, in pregnant women starting at 30 weeks of gestation (third trimester) (see PRECAUTIONS; Pregnancy ). Hematologic Toxicity Anemia has occurred in NSAID-treated patients. This may be due to occult or gross blood loss, fluid retention, or an incompletely described effect on erythropoiesis.
If a patient treated with naproxen tablets has any signs or symptoms of anemia, monitor hemoglobi… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
CLINICAL STUDIES General Information Naproxen has been studied in patients with rheumatoid arthritis, osteoarthritis, juvenile arthritis, ankylosing spondylitis, tendonitis and bursitis, and acute gout. Improvement in patients treated for rheumatoid arthritis was demonstrated by a reduction in joint swelling, a reduction in duration of morning stiffness, a reduction in disease activity as assessed by both the investigator and patient, and by increased mobility as demonstrated by a reduction in walking time. Generally, response to naproxen has not been found to be dependent on age, sex, severity or duration of rheumatoid arthritis.
In patients with osteoarthritis, the therapeutic action of naproxen has been shown by a reduction in joint pain or tenderness, an increase in range of motion in knee joints, increased mobility as demonstrated by a reduction in walking time, and improvement in capacity to perform activities of daily living impaired by the disease. In a clinical trial comparing standard formulations of naproxen 375 mg twice a day (750 mg a day) vs 750 mg twice a day (1500 mg/day), 9 patients in the 750 mg group terminated prematurely because of adverse events.
Nineteen patients in the 1500 mg group terminated prematurely because of adverse events. Most of these adverse events were gastrointestinal events. In clinical studies in patients with rheumatoid arthritis, osteoarthritis, and juvenile arthritis, naproxen has been shown to be comparable to aspirin and indomethacin in controlling the aforementioned measures of disease activity, but the frequency and severity of the milder gastrointestinal adverse effects (nausea, dyspepsia, heartburn) and nervous system adverse effects (tinnitus, dizziness, lightheadedness) were less in naproxen-treated patients than in those treated with aspirin or indomethacin.
In patients with ankylosing spondylitis, naproxen has been shown to decrease night pain, morning stiffness and pain at rest. In double-blind studies the drug was shown to be as effective as aspirin, but with fewer side effects. In patients with acute gout, a favorable response to naproxen was shown by significant clearing of inflammatory changes (e.g., decrease in swelling, heat) within 24 to 48 hours, as well as by relief of pain and tenderness.
Naproxen has been studied in patients with mild to moderate pain secondary to postoperative, orthopedic, postpartum episiotomy and uterine contraction pain and dysmenorrhea. Onset of pain relief can begin within 1 hour in patients taking naproxen and within 30 minutes in patients taking naproxen sodium. Analgesic effect was shown by such measures as reduction of pain intensity scores, increase in pain relief scores, decrease in numbers of patients requiring additional analgesic medication, and delay in time to remedication.
The analgesic effect has been found to last for up to 12 hours. Naproxen may be used safely in combination with gold salts and/or corticosteroids; however, in controlled clinical trials, when added to the regimen of patients receiving corticosteroids, it did not appear to cause greater improvement over that seen with corticosteroids alone. Whether naproxen has a “steroid-sparing” effect has not been adequately studied.
When added to the regimen of patients receiving gold salts, naproxen did result in greater improvement. Its use in combination with salicylates is not recommended because there is evidence that aspirin increases the rate of excretion of naproxen and data are inadequate to demonstrate that naproxen and aspirin produce greater improvement over that achieved with aspirin alone. In addition, as with other NSAIDs, the combination may result in higher frequency of adverse events than demonstrated for either product alone.
In 51 Cr blood loss and gastroscopy studies with normal volunteers, daily administration of 1000 mg of naproxen has been demonstrated to cause statistically significantly less gastric bleeding and erosion than 3250 mg of aspirin. Ger… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
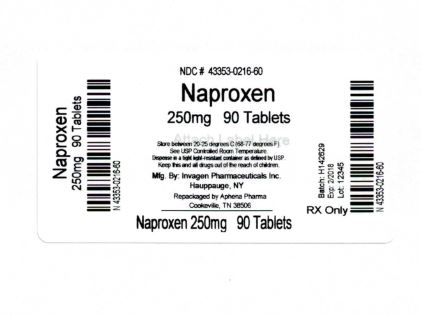
PRINCIPAL DISPLAY PANEL - 250 mg NDC 43353-216 - Naproxen 250 mg - Rx Only Bottle Label 250 mg
PRINCIPAL DISPLAY PANEL - 375 mg NDC 43353-218 - Naproxen 375 mg - Rx Only Bottle Label 375 mg
PRINCIPAL DISPLAY PANEL - 500 mg NDC 43353-211 - Naproxen 500 mg - Rx Only Bottle Label 500 mg
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |