
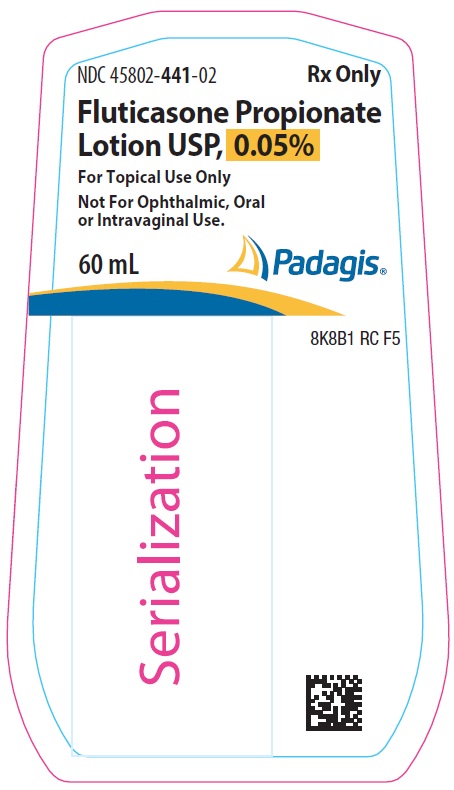
fluticasone propionate .5 mg/mL Lotion, 60 mL
Other active recalls for Fluticasone Propionate (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Fluticasone topical is used to reduce inflammation and relieve itching, redness, dryness, and scaling associated with various skin conditions, including psoriasis (a skin disease in which red, scaly patches form on some areas of the body and eczema (a skin disease that causes the skin to be dry and itchy and to sometimes develop red, scaly rashes). Fluticasone is in a class of medications called corticosteroids. It works by activating natural substances in the skin to reduce swelling, redness, and itching.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Fluticasone Propionate — tap one for details:
Fluticasone may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII I835H2IHHX
A waxy substance derived from plant oils, used as an emulsifier and solubilizer to help mix oil and water ingredients together and keep them blended throughout the product's shelf life.
-
UNII 2DMT128M1S
A waxy solid derived from plant or animal sources. It acts as an emulsifier to blend oil and water components, and also thickens the medicine to give it the right texture and consistency.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII M629807ATL
Imidazolidinyl urea is a synthetic preservative that prevents microbial growth in medicines. It's used in formulations to extend shelf life and maintain product safety during storage.
-
UNII 0RE8K4LNJS
Isopropyl myristate is an oily liquid made from coconut or palm oil. It's used in medicines as an emollient and penetration enhancer to help the medicine absorb through skin or improve spreadability in topical products.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII T5L8T28FGP
Mineral oil is a clear, odorless liquid derived from crude oil. It acts as a lubricant and emollient in medications, helping pills slide smoothly during manufacturing and aiding moisture retention in topical products.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII 1Q73Q2JULR
Sodium citrate is a salt derived from citric acid. It works as a buffer to maintain the medicine's pH level and may also help improve taste or act as a preservative in the formulation.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3.125 | $187.48 / 60 ml |
| Medicaid paysCMS SDUD · 12 mo | $4.48 | $268.57 / 60 ml |
| Medicare drug plans payPart D · Q2 2026 | $4.03 | $241.77 / 60 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| fluticasone propionate .5 mg/mLthis 45802-0441-02 | Padagis | 60 ml | $3.125 | — | Availability likely | — |
| Fluticasone Propionate .5 mg/mL 68462-0427-02 | Glenmark | 1 bottle | $3.867 | — | FDA listed | +24% |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 45802-0441-02 You're viewing this | 60 mL in 1 BOTTLE (45802-441-02) | 2013-08-08 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Fluticasone propionate lotion is a corticosteroid indicated for the relief of the inflammatory and pruritic manifestations of atopic dermatitis in patients 3 months of age or older. Fluticasone propionate lotion is a corticosteroid indicated for the relief of the inflammatory and pruritic manifestations of atopic dermatitis in patients 3 months of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Apply a thin film of fluticasone propionate lotion to the affected skin areas once daily. Rub in gently. Discontinue use when control is achieved.
If no improvement is seen within 2 weeks, reassessment of the diagnosis may be necessary. The safety and efficacy of fluticasone propionate lotion have not been established beyond 4 weeks of use. Avoid use with occlusive dressings or application to the diaper area [ see Warnings and Precautions ( 5.1 ) and ( 5.2 ) ].
Fluticasone propionate lotion is for topical use only, and not for ophthalmic, oral, or intravaginal use. • Apply a thin film to the affected skin areas once daily. Rub in gently. ( 2 ) • Discontinue use when control is achieved.
( 2 ) • Reassess diagnosis if no improvement in 2 weeks. ( 2 ) • The safety and efficacy of fluticasone propionate lotion have not been established beyond four weeks of use. ( 2 ) • Avoid use under occlusion or application to diaper area.
( 2 ) • Not for ophthalmic, oral, or intravaginal use. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lotion, 0.05%. Each gram of fluticasone propionate lotion USP contains 0.5 mg fluticasone propionate USP in a white to off-white lotion base. Fluticasone propionate lotion USP is supplied in 60 mL bottles. • Lotion, 0.05%, supplied in 60 mL bottles. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. • None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypothalamic-Pituitary-Adrenal (HPA) Axis Suppression: Reversible HPA axis suppression and resulting glucocorticoid insufficiency can occur during or after withdrawal of treatment. Risk factors include the use of high-potency topical corticosteroids, use over large surface area, prolonged use, use under occlusion, concomitant use with other corticosteroid-containing products, altered skin barrier, liver failure, and use in pediatric patients. Minimize risk by mitigating the risk factors and use product as recommended.
Modify use if HPA axis suppression is suspected. ( 5.1 , 8.4 ) • Skin Irritation and Sensitization: fluticasone propionate lotion contains the excipient imidurea which releases formaldehyde as a breakdown product. Formaldehyde may cause allergic sensitization or irritation upon contact with the skin.
Discontinue use if irritation or sensitization develops. ( 5.2 )
5.1Hypothalamic-Pituitary-Adrenal (HPA) Axis Suppression and Other Adverse Endocrine Effects Topical corticosteroids, including fluticasone propionate lotion can produce reversible HPA axis suppression with the potential for glucocorticoid insufficiency. Risk factors that predispose to HPA axis suppression include the use of high-potency topical corticosteroids, large treatment surface areas, prolonged use, use under occlusion, concomitant use of more than one corticosteroid-containing product, altered skin barrier, and liver failure.
Pediatric patients may be at greater risk of HPA axis suppression due to their higher skin surface area to body mass ratios [ see Use in Specific Populations ( 8.4 ) ]. HPA axis suppression may occur during or after withdrawal of treatment. If HPA axis suppression is suspected, gradually withdraw the drug, reduce the frequency of application, or substitute a less potent topical corticosteroid.
Evaluation of HPA axis suppression may be done by using the cosyntropin stimulation test. The effects of fluticasone propionate lotion on HPA axis function in pediatric patients were investigated in two trials. Among a total of 89 evaluable subjects from the two trials who were treated with fluticasone propionate lotion twice daily for 3 to 4 weeks, a single subject with >90% body surface area treated showed laboratory evidence of transient suppression immediately post-treatment.
The post cosyntropin stimulation test serum cortisol returned to a normal level (22.1 μg/dL) within one week of the final treatment visit [ see Use In Specific Populations ( 8.4 ) and Clinical Pharmacology ( 12.2 ) ]. Cushing’s syndrome, hyperglycemia, and unmasking of latent diabetes mellitus can also result from systemic absorption of topical corticosteroids. Use of more than one corticosteroid-containing product at the same time may increase the total systemic absorption of topical corticosteroids.
5.2Local Adverse Reactions Fluticasone propionate lotion may cause local adverse reactions, including skin atrophy [ see Adverse Reactions ( 6.1 , 6.2 ) ]. The risk is greater with use under occlusion and with higher potency products. Fluticasone propionate lotion contains the excipient imidurea which releases formaldehyde as a breakdown product.
Formaldehyde may cause allergic sensitization or irritation upon contact with the skin. Avoid using fluticasone propionate lotion in individuals with hypersensitivity to formaldehyde as it may prevent healing or worsen dermatitis. If irritation develops, discontinue fluticasone propionate lotion and institute appropriate therapy.
Allergic Contact Dermatitis Allergic contact dermatitis with corticosteroids is usually diagnosed by observing a failure to heal rather than noticing a clinical exacerbation. Such an observation can be corroborated with appropriate diagnostic patch testing. Discontinue fluticasone propionate lotion if appropriate.
5.3Concomitant Skin Infections If skin infections are present or develop at the treatment site, an appropriate antimicrobial agent should be used. If…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: • HPA Axis Suppression and Other Adverse Endocrine Effects [ see Warnings and Precautions ( 5.1 ) ] • Local Adverse Reactions [ see Warnings and Precautions ( 5.2 ) ] • Concomitant Skin Infections [ see Warnings and Precautions ( 5.3 ) ] The most common adverse reactions (2%) were burning/stinging at the application site. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Padagis ® at 1-866-634-9120 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience: Controlled Clinical Trials Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In 2 multicenter vehicle-controlled clinical trials of once-daily application of fluticasone propionate lotion by 196 adult and 242 pediatric patients, the total incidence of adverse reactions considered drug related by investigators was approximately 4%.
These were local cutaneous reactions, usually mild and self-limiting, and consisted primarily of burning/stinging (2%). All other drug-related events occurred with an incidence of less than 1%, and included were contact dermatitis, exacerbation of atopic dermatitis, folliculitis of legs, pruritus, pustules on arm, rash, and skin infection. See Table 1.
The incidence of adverse reactions between the 242 pediatric subjects (age 3 months to < 17 years) and 196 adult subjects (17 years or older) was similar (4% and 5%, respectively). Table 1: Adverse Reactions from Controlled Clinical Trials (N=438) Adverse Reactions Fluticasone propionate lotion n=221 Vehicle n=217 Burning/Stinging skin 4 (2%) 3 (1%) Contact Dermatitis 0 1 (<1%) Exacerbation of Atopic dermatitis 0 1 (<1%) Folliculitis of legs 2 (<1%) 0 Irritant Contact Dermatitis 0 1 (<1%) Pruritus 1 (<1%) 1 (<1%) Pustules on Arms 1 (<1%) 0 Rash 1 (<1%) 2 (<1%) Skin Infection 0 3 (1%) During the clinical trials, eczema herpeticum occurred in a 33-year old male patient treated with fluticasone propionate lotion.
Table 2 summarizes all adverse events by body system that occurred in at least 1% of patients in either the drug or vehicle group in the phase 3 controlled clinical trials. Table 2: Adverse Events Occurring in ≥1% of Patients from Either Arm from Controlled Clinical Trials (n=438) Body System Fluticasone propionate lotion (N=221) Vehicle Lotion (N=217) Any Adverse Event 77 (35%) 82 (38%) Skin Burning and Stinging 4 (2%) 3 (1%) Pruritus 3 (1%) 5 (2%) Rash 2 (<1%) 3 (1%) Skin Infection 0 3 (1%) Ear, Nose, Throat Common Cold 9 (4%) 5 (2%) Ear Infection 3 (1%) 3 (1%) Nasal Sinus Infection 2 (<1%) 4 (2%) Rhinitis 1 (<1%) 3 (1%) Upper Respiratory Tract Infection 6 (3%) 7 (3%) Gastrointestinal Normal Tooth Eruption 2 (<1%) 3 (1%) Diarrhea 3 (1%) 0 Vomiting 3 (1%) 2 (<1%) Lower Respiratory Cough 7 (3%) 6 (3%) Influenza 5 (2%) 0 Wheeze 0 3 (1%) Neurology Headache 4 (2%) 5 (2%) Non-Site Specific Fever 8 (4%) 8 (4%) Seasonal Allergy 2 (<1%) 3 (1%)
6.2Clinical Trials Experience: Pediatric Open Label Trials In an open label HPA axis suppression trial of 44 pediatric subjects (ages ≥3 months to ≤6 years) fluticasone propionate lotion was applied twice daily (rather than the indicated dosing regimen of once daily) to at least 35% of body surface area for 3 or 4 weeks. Subjects whose lesions cleared after 2 or 3 weeks of treatment continued to apply fluticasone propionate lotion for an additional week. The overall incidence of adverse reactions was 14%.
These were local, cutaneous reactions and included dry skin (7%), stinging at application site (5%), and excoriation (2%). Additionally, a 4-month-old patient treated with fluticasone propionate lotion had marked elevations of the hepatic enzymes AST and ALT. [ see Use in Specific Populations ( 8.4 ) ] In…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Category C There are no adequate and well-controlled studies in pregnant women. Therefore, fluticasone propionate lotion should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Systemic embryofetal development studies were conducted in mice, rats and rabbits.
Subcutaneous doses of 15, 45 and 150 μg/kg/day of fluticasone propionate were administered to pregnant female mice from gestation days 6 to 15. A teratogenic effect characteristic of corticosteroids (cleft palate) was noted after administration of 45 and 150 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) in this study. No treatment related effects on embryofetal toxicity or teratogenicity were noted at 15 μg/kg/day (less than the MRHD in adults based on body surface area comparisons).
Subcutaneous doses of 10, 30 and 100 μg/kg/day of fluticasone propionate were administered to pregnant female rats in two embryofetal development studies (one study administered fluticasone propionate from gestation days 6 to 15 and the other study from gestation days 7 to 17). In the presence of maternal toxicity, fetal effects noted at 100 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) included decreased fetal weights, omphalocele, cleft palate, and retarded skeletal ossification. No treatment related effects on embryofetal toxicity or teratogenicity were noted at 10 μg/kg/day (less than the MRHD in adults based on body surface area comparisons).
Subcutaneous doses of 0.08, 0.57 and 4 μg/kg/day of fluticasone propionate were administered to pregnant female rabbits from gestation days 6 to 18. Fetal effects noted at 4 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) included decreased fetal weights, cleft palate and retarded skeletal ossification. No treatment related effects on embryofetal toxicity or teratogenicity were noted at 0.57 μg/kg/day (less than the MRHD in adults based on body surface area comparisons).
Oral doses of 3, 30 and 300 μg/kg/day fluticasone propionate were administered to pregnant female rabbits from gestation days 8 to 20. No fetal or teratogenic effects were noted at oral doses up to 300 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) in this study. However, no fluticasone propionate was detected in the plasma in this study, consistent with the established low bioavailability following oral administration.
Fluticasone propionate crossed the placenta following administration of a subcutaneous or an oral dose of 100 μg/kg tritiated fluticasone propionate to pregnant rats.
8.3Nursing Mothers Systemically administered corticosteroids appear in human milk and can suppress growth, interfere with endogenous corticosteroid production, or cause other untoward effects. It is not known whether topical administration of corticosteroids could result in sufficient systemic absorption to produce detectable quantities in human milk. Because many drugs are excreted in human milk, caution should be exercised when fluticasone propionate lotion is administered to a nursing woman.
8.4Pediatric Use Fluticasone propionate lotion may be used in pediatric patients as young as 3 months of age. The safety and effectiveness of fluticasone propionate lotion in pediatric patients below 3 months of age have not been established. Because of a higher ratio of skin surface area to body mass, pediatric patients are at a greater risk than adults of systemic effects when treated with topical drugs.
They are, therefore, also at greater risk of HPA axis suppression and adrenal insufficiency upon the use of topical corticosteroids [ see Warnings and Precautions ( 5.1 ) ]. In an HPA axis suppression trial, none of the 40 evaluable pediatric subjects, 4 months old to < 6 years old, with moderate to severe atopic dermatitis covering ≥ 35% Body Surface Area (BSA) who were treate…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C There are no adequate and well-controlled studies in pregnant women. Therefore, fluticasone propionate lotion should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Systemic embryofetal development studies were conducted in mice, rats and rabbits.
Subcutaneous doses of 15, 45 and 150 μg/kg/day of fluticasone propionate were administered to pregnant female mice from gestation days 6 to 15. A teratogenic effect characteristic of corticosteroids (cleft palate) was noted after administration of 45 and 150 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) in this study. No treatment related effects on embryofetal toxicity or teratogenicity were noted at 15 μg/kg/day (less than the MRHD in adults based on body surface area comparisons).
Subcutaneous doses of 10, 30 and 100 μg/kg/day of fluticasone propionate were administered to pregnant female rats in two embryofetal development studies (one study administered fluticasone propionate from gestation days 6 to 15 and the other study from gestation days 7 to 17). In the presence of maternal toxicity, fetal effects noted at 100 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) included decreased fetal weights, omphalocele, cleft palate, and retarded skeletal ossification. No treatment related effects on embryofetal toxicity or teratogenicity were noted at 10 μg/kg/day (less than the MRHD in adults based on body surface area comparisons).
Subcutaneous doses of 0.08, 0.57 and 4 μg/kg/day of fluticasone propionate were administered to pregnant female rabbits from gestation days 6 to 18. Fetal effects noted at 4 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) included decreased fetal weights, cleft palate and retarded skeletal ossification. No treatment related effects on embryofetal toxicity or teratogenicity were noted at 0.57 μg/kg/day (less than the MRHD in adults based on body surface area comparisons).
Oral doses of 3, 30 and 300 μg/kg/day fluticasone propionate were administered to pregnant female rabbits from gestation days 8 to 20. No fetal or teratogenic effects were noted at oral doses up to 300 μg/kg/day (less than the MRHD in adults based on body surface area comparisons) in this study. However, no fluticasone propionate was detected in the plasma in this study, consistent with the established low bioavailability following oral administration.
Fluticasone propionate crossed the placenta following administration of a subcutaneous or an oral dose of 100 μg/kg tritiated fluticasone propionate to pregnant rats.
🧒 Pediatric Use ▾
8.4Pediatric Use Fluticasone propionate lotion may be used in pediatric patients as young as 3 months of age. The safety and effectiveness of fluticasone propionate lotion in pediatric patients below 3 months of age have not been established. Because of a higher ratio of skin surface area to body mass, pediatric patients are at a greater risk than adults of systemic effects when treated with topical drugs.
They are, therefore, also at greater risk of HPA axis suppression and adrenal insufficiency upon the use of topical corticosteroids [ see Warnings and Precautions ( 5.1 ) ]. In an HPA axis suppression trial, none of the 40 evaluable pediatric subjects, 4 months old to < 6 years old, with moderate to severe atopic dermatitis covering ≥ 35% Body Surface Area (BSA) who were treated with an exaggerated dosing regimen (twice daily) of fluticasone propionate lotion experienced adrenal suppression (defined as a 30-minute post-stimulation cortisol level ≤18 micrograms/dL) [ see Warnings and Precautions ( 5.1 ) and Clinical Pharmacology ( 12.2 ) ].
In another HPA axis suppression trial, one of 49 (2%) evaluable pediatric subjects, 3 months to 11 months old, with moderate to severe atopic dermatitis covering ≥ 35% Body Surface Area (BSA) who applied an exaggerated dosing regimen (twice daily) of fluticasone propionate lotion experienced reversible adrenal suppression (defined as a 30-minute post-stimulation cortisol level ≤18 micrograms/dL) following 4 weeks of therapy [ see Warnings and Precautions ( 5.1 ) and Clinical Pharmacology ( 12.2 ) ] . Systemic effects such as Cushing's syndrome, linear growth retardation, delayed weight gain, and intracranial hypertension have been reported in pediatric patients, especially those with prolonged exposure to large doses of high-potency topical corticosteroids, or concomitant use of more than one corticosteroid product.
Local adverse reactions including skin atrophy have also been reported with use of topical corticosteroids in pediatric patients. Parents of pediatric patients should be advised not to use this medication in the treatment of diaper dermatitis unless directed by a physician. Fluticasone propionate lotion should not be applied in the diaper areas as diapers or plastic pants may constitute occlusive dressing.
🧓 Geriatric Use ▾
8.5Geriatric Use A limited number of patients above 65 years of age have been treated with fluticasone propionate lotion in US and non-US clinical trials. Specifically only 8 patients above 65 years of age were treated with fluticasone propionate lotion in controlled clinical trials. The number of patients is too small to permit separate analyses of efficacy and safety.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Corticosteroids play a role in cellular signaling, immune function, inflammation, and protein regulation; however, the precise mechanism of action of fluticasone propionate lotion in atopic dermatitis is unknown.
12.2Pharmacodynamics Vasoconstrictor Assay Trials performed with fluticasone propionate lotion indicate that it is in the medium range of potency as demonstrated in vasoconstrictor trials in healthy subjects when compared with other topical corticosteroids. However, similar blanching scores do not necessarily imply therapeutic equivalence. Hypothalamic-Pituitary-Adrenal (HPA) Axis Suppression In an open label HPA axis suppression trial (Trial A), 42 pediatric subjects (ages 4 months to <6 years) with moderate to severe atopic dermatitis covering ≥ 35% Body Surface Area (BSA) who were treated with an exaggerated dosing regimen of fluticasone propionate lotion twice daily (rather than the indicated dosing regimen of once daily) for at least 3 to 4 weeks were assessed for HPA axis suppression.
The mean BSA treated was 65%. None of the 40 evaluable subjects were suppressed. The criterion for HPA axis suppression was a serum cortisol level of less than or equal to 18 micrograms per deciliter at 30-minutes after cosyntropin stimulation.
Another open label HPA axis suppression trial (Trial B) enrolled 56 pediatric subjects (ages 3 months to 11 months) with moderate to severe atopic dermatitis covering ≥ 35% BSA. Subjects were treated with an exaggerated dosing regimen of fluticasone propionate lotion twice daily over a period of 3 or 4 weeks. The mean BSA treated was 54%.
Out of 56 subjects, 49 were considered evaluable with respect to their adrenal axis function post-treatment. One of 49 subjects showed laboratory evidence of suppression immediately post treatment. The criterion for HPA axis suppression was a serum cortisol level of less than or equal to 18 micrograms per deciliter at 30-minutes after cosyntropin stimulation.
Repeated test one week later showed the post cosyntropin stimulation testing serum cortisol returned to normal level (22.1 μg/dL). This 4-month old subject had a baseline treatment BSA of 94% and was reported to have received 100% of the twice-daily applications of fluticasone propionate lotion, 0.05% over the 27 day treatment period.
12.3Pharmacokinetics Absorption The extent of percutaneous absorption of topical corticosteroids is determined by many factors, including the vehicle and the integrity of the epidermal barrier. Occlusive dressing enhances penetration. Topical corticosteroids can be absorbed from normal intact skin.
Inflammation and/or other disease processes in the skin increase percutaneous absorption. Plasma fluticasone levels were measured in a subset of subjects 2 to 5 years and 11 months of age in HPA axis suppression trial (Trial A) described above. A total of 13 (62%) of 21 subjects tested had measurable fluticasone at the end of 3 to 4 weeks of treatment.
The mean ± SD fluticasone plasma concentration was 0.16 ± 0.23 ng/mL. Three subjects aged 3, 4, and 4 years had fluticasone concentrations over 0.30 ng/mL, with one of them having a concentration of 0.82 ng/mL. No data were obtained for subjects < 2 years of age.
Distribution The percentage of fluticasone propionate bound to human plasma proteins averaged 91%. Fluticasone propionate is weakly and reversibly bound to erythrocytes. Fluticasone propionate is not significantly bound to human transcortin.
Metabolism No metabolites of fluticasone propionate were detected in an in vitro study of radiolabeled fluticasone propionate incubated in a human skin homogenate. Fluticasone propionate is metabolized in the liver by cytochrome P450 3A4-mediated hydrolysis of the 5-fluoromethyl carbothiolate grouping. This transformation occurs in 1 metabolic step to produce the inactive 17β-carboxylic acid metabolite, the only known metabolite detected in man.
This metabolite has approximately 200…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Corticosteroids play a role in cellular signaling, immune function, inflammation, and protein regulation; however, the precise mechanism of action of fluticasone propionate lotion in atopic dermatitis is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Fluticasone Propionate Lotion USP, 0.05% is white to off-white in color, and supplied as follows: 60 mL bottle NDC 45802- 441 -02 Store at 20-25°C (68-77°F) [see USP Controlled Room Temperature]. Do not refrigerate, and keep container tightly closed.
📋 Description ▾
11 DESCRIPTION Fluticasone propionate lotion USP, 0.05% contains fluticasone propionate [ S -Fluoromethyl 6α, 9α-difluoro-11β-hydroxy-16α-methyl-3-oxo-17α-propionyloxyandrosta-1,4-diene-17β-carbothioate], a synthetic fluorinated corticosteroid, for topical use. The topical corticosteroids constitute a class of primarily synthetic steroids used as anti-inflammatory and antipruritic agents. Chemically, fluticasone propionate, USP is C 25 H 31 F 3 O 5 S.
It has the following structural formula: Fluticasone propionate USP has a molecular weight of 500.6. It is a white to off-white powder and is practically insoluble in water, freely soluble in dimethyl sulfoxide and dimethylformamide, and slightly soluble in methanol and 95% ethanol. Each gram of fluticasone propionate lotion USP contains 0.5 mg fluticasone propionate USP in a white to off white lotion base of anhydrous citric acid, cetomacrogol 1000, cetostearyl alcohol, dimethicone 360, imidurea, isopropyl myristate, methylparaben, mineral oil, propylene glycol, propylparaben, purified water, and sodium citrate.
Image 1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Administration Instructions Advise the patient of appropriate fluticasone propionate lotion administration instructions, including those that will mitigate HPA-Axis suppression [ see Warnings and Precautions (5.1) ] and local adverse reactions [ see Warnings and Precautions ( 5.2 ) ]: • Discontinue therapy when control is achieved in less than 4 weeks; if no improvement is seen within 2 weeks, contact the healthcare provider. • Avoid contact with the eyes. • Do not bandage the treated skin area, or cover or wrap it to cause occlusion unless directed by the healthcare provider. • Do not use fluticasone propionate lotion in the treatment of diaper dermatitis unless directed by the healthcare provider, as diapers or plastic pants may constitute occlusive dressing and enhance absorption. • Do not use on the face, underarms, or groin areas unless directed by the healthcare provider.
Local Adverse Reactions Advise the patient to report any signs of local adverse reactions to their healthcare provider [ see Warnings and Precautions ( 5.2 ) ]. • Advise patients to report to their healthcare provider if they are allergic to formaldehyde. Manufactured by Padagis ® Yeruham, Israel www.padagis.com Rev 05-24 8K800 RC PH6