
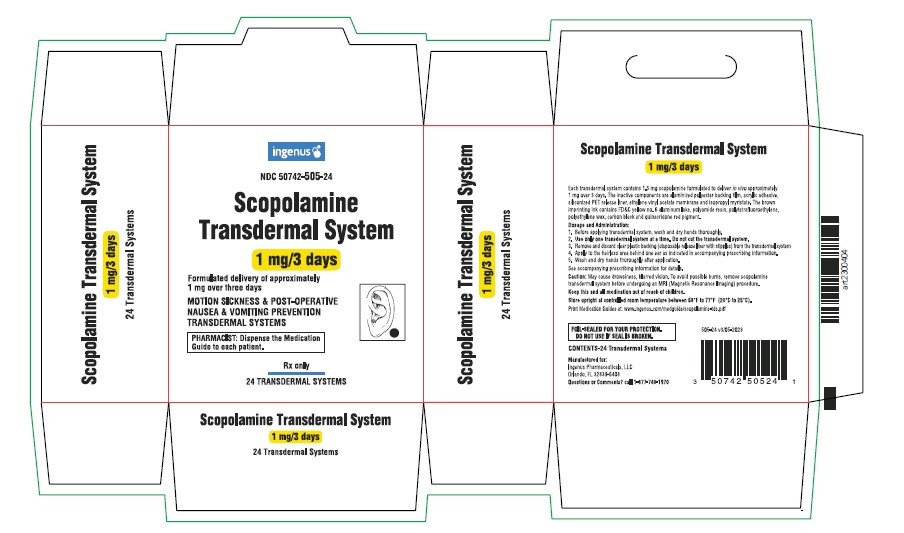
Scopolamine 1.5 mg Patch, Extended Release
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Scopolamine is used to prevent nausea and vomiting caused by motion sickness or medications used during surgery. Scopolamine is in a class of medications called antimuscarinics. It works by blocking the effects of a certain natural substance (acetylcholine) on the central nervous system.
Read the full MedlinePlus article ↗- Apply it to the hairless skin directly behind one ear — that flat area just behind the earlobe. Either side works fine. The key is that the skin is clean, dry, and hair-free so the...
- Where exactly do I put the patch, and does it matter which side?
- Put it on at least 4 hours before you need it to be working — so if you're boarding a cruise ship in the morning, apply it the night before. The patch takes several hours to build...
- How soon before a trip should I put the patch on?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Scopolamine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 11P487375P
A synthetic red colorant used to give medicines their distinctive color. It helps patients identify their medication and makes the product visually appealing.
-
UNII 4XYU5U00C4
A synthetic colorant used to give medicines a dark color. It helps identify the product and makes tablets or capsules visually distinctive.
-
UNII 76845O8NMZ
Ethyl acetate is a clear, colorless liquid solvent derived from acetic acid and ethanol. In medicines, it dissolves active ingredients, carries them into the product formulation, and helps control how quickly the drug releases and works in your body.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 0RE8K4LNJS
Isopropyl myristate is an oily liquid made from coconut or palm oil. It's used in medicines as an emollient and penetration enhancer to help the medicine absorb through skin or improve spreadability in topical products.
-
UNII E1NC1JVS3O
A synthetic plastic material that doesn't stick to other substances. It's used as a glidant and lubricant to help medicine particles flow smoothly during manufacturing and to prevent ingredients from clumping together.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $4.335 | $17.34 / 4 patch |
| Medicaid paysCMS SDUD · 12 mo | $6.43 | $25.73 / 4 patch |
| Medicare drug plans payPart D · Q2 2026 | $8.13 | $32.52 / 4 patch |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Scopolamine 1 mg/3d 00378-6470-44 | Mylan | 24 patches | $4.335 | AB | Availability likely | — |
| scopolamine 1 mg/3d 00591-2258-04 | Actavis | 4 patches | $4.335 | AB | Availability likely | — |
| Scopolamine 1 mg/3d 42858-0150-14 | Rhodes | 10 patches | $4.335 | AB | Availability likely | — |
| Scopolamine Transdermal System 1 mg 45802-0580-01 | Padagis | 1 patch | $4.335 | AB | Discontinued | — |
| Scopolamine 1.5 mgthis 50742-0505-04 | Ingenus | 1 patch | $4.335 | AB | Availability likely | — |
| Scopolamine 1 mg/3d 69238-1662-02 | Amneal | 10 patches | $4.335 | AB | Availability likely | — |
| Scopolamine 1 mg/3d 70710-1846-02 | Zydus | 10 patches | $4.335 | AB | Availability likely | — |
| Transderm Scop 1 mg/3d 10019-0008-01 | Baxter | 1 patch | — | AB | FDA listed | — |
| Scopolamine 1 mg/3d 50090-5349-00 | A-S | 4 pouches | — | AB | FDA listed | — |
| scopolamine 1 mg/3d 50090-7188-00 | A-S | 1 d | — | AB | FDA listed | — |
| Scopolamine Trandermal System 1 mg 63629-8450-01 | Bryant | 1 patch | — | AB | FDA listed | — |
| Scopolamine Trandermal System 1 mg 63629-8451-01 | Bryant | 1 patch | — | AB | FDA listed | — |
| Scopolamine Trandermal System 1 mg 63629-8452-01 | Bryant | 1 patch | — | AB | FDA listed | — |
| Scopolamine 1.5 mg 68071-3994-04 | NuCare | 1 patch | — | AB | FDA listed | — |
| Scopolamine 1 mg/3d 70771-1787-02 | Zydus | 10 patches | — | AB | FDA listed | — |
| Scopolamine Transdermal System 1 mg 71335-2718-01 | Bryant | 1 patch | — | AB | FDA listed | — |
| Scopolamine 1 mg/3d 71335-3013-01 | Bryant | 4 patches | — | AB | FDA listed | — |
| Scopolamine 1 mg/3d 71335-3014-01 | Bryant | 10 patches | — | AB | FDA listed | — |
| Scopolamine 1 mg/3d 71335-3015-01 | Bryant | 24 patches | — | AB | FDA listed | — |
| Scopolamine Trandermal System 1 mg 72162-1419-02 | Bryant | 1 patch | — | AB | FDA listed | — |
| Scopolamine 1 mg/3d 72162-2453-02 | Bryant | 4 patches | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 50742-0505-04 You're viewing this | 4 POUCH in 1 CARTON (50742-505-04) / 1 PATCH, EXTENDED RELEASE in 1 POUCH | $4.33 / ea | $17.34 | 2020-11-24 | Active |
| 50742-0505-10 | 10 POUCH in 1 CARTON (50742-505-10) / 1 PATCH, EXTENDED RELEASE in 1 POUCH | $4.33 / ea | $43.35 | 2020-11-24 | Active |
| 50742-0505-24 | 24 POUCH in 1 CARTON (50742-505-24) / 1 PATCH, EXTENDED RELEASE in 1 POUCH | $4.33 / ea | $104.04 | 2020-11-24 | Active |
This pack has the lowest per-ea cost of the 3 priced pack sizes ($4.33 NADAC).
This pack accounts for about 39% of this product's recent Medicaid fills; the largest share goes to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 50742-0505-04?
What NDC number is used to bill for this package of Scopolamine 1.5 mg Patch, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Scopolamine transdermal system is indicated in adults for the prevention of: nausea and vomiting associated with motion sickness. post-operative nausea and vomiting (PONV) associated with recovery from anesthesia and/or opiate analgesia and surgery. Scopolamine transdermal system is an anticholinergic indicated in adults for the prevention of: nausea and vomiting associated with motion sickness. ( 1 ) post-operative nausea and vomiting (PONV) associated with recovery from anesthesia and/or opiate analgesia and surgery.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Application and Removal ( 2.1 ): Each scopolamine transdermal system delivers 1 mg of scopolamine over 3 days. Only wear one transdermal system at a time. Do not cut the transdermal system.
Wash hands thoroughly with soap and water after application. Avoid touching or applying pressure to the transdermal system once applied. Upon removal, fold used transdermal system in half with sticky side together, discard to prevent accidental contact or ingestion, and wash the hands and application site with soap and water.
Recommended Dosage : Motion Sickness: Apply one transdermal system to the hairless area behind one ear at least 4 hours before antiemetic effect is required for use up to 3 days. If therapy for more than 3 days is required, remove the first transdermal system and apply a new transdermal system behind the other ear. ( 2.2 ) PONV: For surgeries other than cesarean section, apply one transdermal system behind the ear the evening before surgery and remove 24 hours following surgery.
( 2.2 )
2.1Important Application and Removal Instructions Each scopolamine transdermal system is formulated to deliver in vivo approximately 1 mg of scopolamine over 3 days. Only wear one transdermal system at any time. Do not cut the transdermal system.
Apply the transdermal system to the skin in the postauricular area (hairless area behind one ear). After the transdermal system is applied on the dry skin behind the ear, wash hands thoroughly with soap and water and dry hands [see Warnings and Precautions ( 5.7 )] . If the transdermal system becomes displaced, discard the transdermal system, and apply a new transdermal system on the hairless area behind the other ear.
Once the transdermal system has been affixed, avoid touching or applying pressure to the transdermal system while it is being worn, since pressure exerted on it may cause scopolamine to ooze out at the edge. Upon removal, fold the used transdermal system in half with the sticky side together, and discard in household trash in a manner that prevents accidental contact or ingestion by children, pets or others. Wash the hands and application site with soap and water after transdermal system removal [see Warnings and Precautions ( 5.7 )] .
2.2Recommended Adult Dosage Motion Sickness Apply one scopolamine transdermal system to the hairless area behind one ear at least 4 hours before the antiemetic effect is required – for use up to 3 days. If therapy is required for longer than 3 days, remove the first transdermal system and apply a new scopolamine transdermal system behind the other ear. PONV For surgeries other than cesarean section: Apply one scopolamine transdermal system the evening before scheduled surgery.
Remove the transdermal system 24 hours following surgery.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Transdermal system: a circular, flat, tan-colored transdermal system imprinted with “Scopolamine 1 mg/3 days” Transdermal system: 1 mg/3 days ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Scopolamine transdermal system is contraindicated in patients with: angle closure glaucoma [see Warnings and Precautions ( 5.1 )]. hypersensitivity to scopolamine or other belladonna alkaloids or to any ingredient or component in the formulation or delivery system. Reactions have included rash generalized and erythema [see Adverse Reactions ( 6.2 ), Description ( 11 )] . Angle closure glaucoma.
( 4 , 6.2 ) Hypersensitivity to scopolamine or other belladonna alkaloids or to any ingredient or component of the formulation or delivery system. ( 4 , 7 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Acute Angle Closure Glaucoma: Monitor for increased intraocular pressure in patients with open-angle glaucoma and adjust glaucoma therapy as needed. Discontinue if signs or symptoms of acute angle closure glaucoma develop. ( 5.1 ) Neuropsychiatric Adverse Reactions: May cause psychiatric and cognitive effects, seizures and impair mental and/or physical abilities.
Monitor patients for new or worsening psychiatric symptoms during treatment and during concomitant treatment with other drugs that are associated with similar psychiatric effects. ( 5.2 , 7.1 ) Eclamptic Seizures in Pregnant Women: Avoid use in patients with severe preeclampsia. ( 5.3 ) Gastrointestinal and Urinary Disorders: Consider more frequent monitoring during treatment in patients suspected of having intestinal obstruction; patients with pyloric obstruction, patients with impeded urine flow or receiving other anticholinergic drugs.
Discontinue if patient develops difficulty in urination. ( 5.4 , 7.2 ) Hyperthermia: Serious adverse reactions have been reported postmarketing in adult and pediatric patients, including fatal cases. If symptoms occur, remove the transdermal system, and contact a healthcare provider.
( 5.5 ) Drug Withdrawal/Post-Removal Symptoms: Anticholinergic symptoms may occur 24 hours or more after removal of the transdermal system. ( 5.6 ) Blurred Vision: Avoid contact with the eyes. ( 2.1 , 5.7 ) Magnetic Resonance Imaging (MRI) Skin Burns: Remove scopolamine transdermal system prior to MRI scan.
( 5.8 )
5.1Acute Angle Closure Glaucoma The mydriatic effect of scopolamine may cause an increase in intraocular pressure resulting in acute angle closure glaucoma. Monitor intraocular pressure in patients with open angle glaucoma and adjust glaucoma therapy during scopolamine transdermal system use, as needed. Advise patients to immediately remove the transdermal system and contact their healthcare provider if they experience symptoms of acute angle closure glaucoma (e.g., eye pain or discomfort, blurred vision, visual halos or colored images in association with red eyes from conjunctival congestion and corneal edema).
5.2Neuropsychiatric Adverse Reactions Psychiatric Adverse Reactions Scopolamine has been reported to exacerbate psychosis. Other psychiatric reactions have also been reported, including acute toxic psychosis, agitation, speech disorder, hallucinations, paranoia, and delusions [see Adverse Reactions ( 6.2 )] . Monitor patients for new or worsening psychiatric symptoms during treatment with scopolamine transdermal system.
Also, monitor patients for new or worsening psychiatric symptoms during concomitant treatment with other drugs that are associated with similar psychiatric effects [see Drug Interactions ( 7.1 )] . In cases of psychiatric reactions occurring scopolamine transdermal system should be removed at once. If, despite this, the symptoms persist in a severe form, instruct patients to seek medical attention.
Seizures Seizures and seizure-like activity have been reported in patients receiving scopolamine. Weigh this potential risk against the benefits before prescribing scopolamine transdermal system to patients with a history of seizures, including those receiving anti-epileptic medication or who have risk factors that can lower the seizure threshold. Cognitive Adverse Reactions Scopolamine can cause drowsiness, disorientation, and confusion.
Discontinue scopolamine transdermal system if signs or symptoms of cognitive impairment develop. If, despite this, the symptoms persist in a severe form, instruct patients to seek medical attention. Elderly and pediatric patients may be more sensitive to the neurological and psychiatric effects of scopolamine transdermal system.
Consider more frequent monitoring during treatment with scopolamine transdermal system in elderly patients [see Use in Specific Populations ( 8.5 )] . Scopolamine transdermal system is not approved for use in pediatric patients [see Use i…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions are: Motion Sickness (>15%): dry mouth, drowsiness, blurred vision and dilation of the pupils. ( 6.1 ) PONV (≥ 3%): dry mouth, dizziness, somnolence, agitation, visual impairment, confusion, mydriasis and pharyngitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ingenus Pharmaceuticals, LLC at 1-877-748-1970 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
The following serious adverse reactions are described elsewhere in labeling: Acute Angle Closure Glaucoma [see Warnings and Precautions ( 5.1 )] Neuropsychiatric Adverse Reactions [see Warnings and Precautions ( 5.2 )] Eclamptic Seizures in Pregnant Women [see Warnings and Precautions ( 5.3 )] Gastrointestinal and Urinary Disorders [see Warnings and Precautions ( 5.4 )] Hyperthermia [see Warnings and Precautions ( 5.5 )] Drug Withdrawal/Post-Removal Symptoms [see Warnings and Precautions ( 5.6 )] Blurred Vision [see Warnings and Precautions ( 5.7 )] MRI Skin Burns [see Warnings and Precautions ( 5.8 )]
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Motion Sickness The most common adverse reaction (approximately two thirds) was dry mouth. Less common adverse reactions, included drowsiness (less than one sixth), blurred vision and dilation of the pupils.
PONV Common adverse reactions, occurring in at least 3% of patients in PONV clinical trials are shown in Table 1. Table 1 Common Adverse Reactions occurring in at least 3% of patients and at a rate higher than placebo in Surgical Patients for the Prevention of PONV Scopolamine Transdermal System % (N=461) Placebo % (N=457) Dry mouth 29 16 Dizziness 12 7 Somnolence 8 4 Agitation 6 4 Visual Impairment 5 3 Confusion 4 3 Mydriasis 4 0 Pharyngitis 3 2
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of scopolamine transdermal system. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Psychiatric disorders: acute psychosis including: disorientation, hallucinations, and paranoia Nervous system disorders: amnesia, coordination abnormalities, disturbance in attention, headache, restlessness, speech disorder General disorders and administration site conditions: application site reactions (including blistering, burning, pruritus, and rash) and hyperthermia Eye disorders: amblyopia, angle closure glaucoma, dry eyes, eyelid irritation, eye pruritus Skin and subcutaneous tissue disorders: erythema, rash generalized, skin irritation Renal and urinary disorders: dysuria Ear and labyrinth disorders: vertigo
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs Causing Central Nervous System (CNS) Adverse Reactions: Monitor patients for CNS adverse reactions (drowsiness, dizziness or disorientations). ( 7.1 ) Anticholinergic Drugs: Consider more frequent monitoring during treatment in patients receiving other anticholinergic drugs. ( 7.2 ) Oral Drugs Absorbed in the Stomach: Monitor for increased or decreased therapeutic effect of the oral drug.
( 7.3 ) Interaction with Gastric Secretion Test: Discontinue use of scopolamine transdermal system 10 days prior to testing. ( 7.4 )
7.1Drugs Causing Central Nervous System (CNS) Adverse Reactions The concurrent use of scopolamine transdermal system with other drugs that cause CNS adverse reactions of drowsiness, dizziness or disorientation (e.g., sedatives, hypnotics, opiates, anxiolytics and alcohol) or have anticholinergic properties (e.g., other belladonna alkaloids, sedating antihistamines, meclizine, tricyclic antidepressants, and muscle relaxants) may potentiate the effects of scopolamine transdermal system [see Warnings and Precautions ( 5.2 )] .
Either scopolamine transdermal system or the interacting drug should be chosen, depending on the importance of the drug to the patient. If the interacting drug cannot be avoided, monitor patients for CNS adverse reactions.
7.2Anticholinergic Drugs Concomitant use of scopolamine with other drugs having anticholinergic properties may increase the risk of CNS adverse reactions [see Drug Interactions ( 7.1 )], intestinal obstruction and/or urinary retention. Consider more frequent monitoring during treatment with scopolamine transdermal system in patients receiving anticholinergic drugs [see Warnings and Precautions ( 5.2 , 5.4 )] .
7.3Oral Drugs Absorbed in the Stomach Scopolamine transdermal system, as an anticholinergic, may delay gastric and upper gastrointestinal motility and, therefore, the rate of absorption of other orally administered drugs. Monitor patients for modified therapeutic effect of concomitant orally administered drugs with a narrow therapeutic index.
7.4Interaction with Gastric Secretion Test Scopolamine will interfere with the gastric secretion test. Discontinue scopolamine transdermal system 10 days prior to testing.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Patients: Consider more frequent monitoring during treatment due to increased risk of CNS adverse reactions. ( 5.2 , 8.5 ) Renal or Hepatic Impairment: Consider more frequent monitoring during treatment due to increased risk of CNS adverse reactions. ( 5.2 , 8.6 )
8.1Pregnancy Risk Summary Eclamptic seizures have been reported in pregnant women with severe preeclampsia soon after injection of intravenous or intramuscular scopolamine. Avoid use of scopolamine transdermal system in patients with severe preeclampsia [see Warnings and Precautions ( 5.3 ) and Data] . Available data from observational studies and postmarketing reports with scopolamine use in pregnant women have not identified a drug associated risk of major birth defects, miscarriage, or adverse fetal outcomes.
In animal studies, there was no evidence of adverse developmental effects with intravenous administration of scopolamine hydrobromide revealed in rats. Embryotoxicity was observed in rabbits at intravenous doses producing plasma levels approximately 100 times the levels achieved in humans using a transdermal system. The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data In published case reports, two pregnant patients with severe preeclampsia were administered intravenous and intramuscular scopolamine, respectively, and developed eclamptic seizures soon after scopolamine administration [see Warnings and Precautions ( 5.3 )] .
Animal Data In animal reproduction studies, when pregnant rats and rabbits received scopolamine hydrobromide by daily intravenous injection, no adverse effects were observed in rats. An embryotoxic effect was observed in rabbits at doses producing plasma levels approximately 100 times the levels achieved in humans using a transdermal system. Scopolamine administered parenterally to rats and rabbits at doses higher than the dose delivered by scopolamine transdermal system did not affect uterine contractions or increase the duration of labor.
8.2Lactation Risk Summary Scopolamine is present in human milk. There are no available data on the effects of scopolamine on the breastfed infant or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for scopolamine transdermal system and any potential adverse effects on the breastfed child from scopolamine transdermal system or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of scopolamine transdermal system have not been established in pediatric patients. Pediatric patients are particularly susceptible to the anticholinergic adverse reactions of scopolamine, including neurologic and psychiatric adverse reactions and drug withdrawal syndrome. Serious adverse reactions of acute psychosis (e.g., disorientation, hallucinations), amblyopia, hyperthermia (including a fatal case), and mydriasis have also been reported in pediatric patients [see Warnings and Precautions ( 5.2 , 5.5 )] .
8.5Geriatric Use Clinical trials of scopolamine transdermal system did not include sufficient number of subjects aged 65 years and older to determine if they respond differently from younger subjects. In other clinical experience, elderly patients had an increased risk of neurologic and psychiatric adverse reactions, such as hallucinations, confusion, dizziness and drug withdrawal syndrome [see Warnings and Precautions ( 5.2 , 5.6 )] . Consider more frequent monitoring for CNS adverse reactions during treatment with scopolamine transdermal system in geriatric patients [see Warnings and Precautions ( 5.2 )] .
Serious adverse reactions of…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Eclamptic seizures have been reported in pregnant women with severe preeclampsia soon after injection of intravenous or intramuscular scopolamine. Avoid use of scopolamine transdermal system in patients with severe preeclampsia [see Warnings and Precautions ( 5.3 ) and Data] . Available data from observational studies and postmarketing reports with scopolamine use in pregnant women have not identified a drug associated risk of major birth defects, miscarriage, or adverse fetal outcomes.
In animal studies, there was no evidence of adverse developmental effects with intravenous administration of scopolamine hydrobromide revealed in rats. Embryotoxicity was observed in rabbits at intravenous doses producing plasma levels approximately 100 times the levels achieved in humans using a transdermal system. The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data In published case reports, two pregnant patients with severe preeclampsia were administered intravenous and intramuscular scopolamine, respectively, and developed eclamptic seizures soon after scopolamine administration [see Warnings and Precautions ( 5.3 )] .
Animal Data In animal reproduction studies, when pregnant rats and rabbits received scopolamine hydrobromide by daily intravenous injection, no adverse effects were observed in rats. An embryotoxic effect was observed in rabbits at doses producing plasma levels approximately 100 times the levels achieved in humans using a transdermal system. Scopolamine administered parenterally to rats and rabbits at doses higher than the dose delivered by scopolamine transdermal system did not affect uterine contractions or increase the duration of labor.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of scopolamine transdermal system have not been established in pediatric patients. Pediatric patients are particularly susceptible to the anticholinergic adverse reactions of scopolamine, including neurologic and psychiatric adverse reactions and drug withdrawal syndrome. Serious adverse reactions of acute psychosis (e.g., disorientation, hallucinations), amblyopia, hyperthermia (including a fatal case), and mydriasis have also been reported in pediatric patients [see Warnings and Precautions ( 5.2 , 5.5 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of scopolamine transdermal system did not include sufficient number of subjects aged 65 years and older to determine if they respond differently from younger subjects. In other clinical experience, elderly patients had an increased risk of neurologic and psychiatric adverse reactions, such as hallucinations, confusion, dizziness and drug withdrawal syndrome [see Warnings and Precautions ( 5.2 , 5.6 )] . Consider more frequent monitoring for CNS adverse reactions during treatment with scopolamine transdermal system in geriatric patients [see Warnings and Precautions ( 5.2 )] .
Serious adverse reactions of hyperthermia have been reported postmarketing in geriatric patients receiving transdermal scopolamine, including a fatal case. Geriatric patients may be more susceptible to the anticholinergic effects of disruption in thermoregulation. Advise patients if body temperature increases, or they are not sweating in warm environmental conditions, to remove the transdermal system and contact their healthcare provider [see Warnings and Precautions ( 5.5 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Anticholinergic toxicity includes both central and peripheral signs and symptoms: agitation, central nervous system effects (e.g., coma, confusion, hallucinations, lethargy, seizures, somnolence), decreased bowel sounds, dry flushed skin, dry mouth, hyperthermia, hypertension, supraventricular arrhythmias, tachycardia, urinary retention, visual disturbances (e.g., amblyopia, mydriasis). These symptoms can be severe and may require medical intervention. In cases of toxicity remove the scopolamine transdermal system.
Serious symptomatic cases of overdosage involving multiple transdermal system applications and/or ingestion may be managed by initially ensuring the patient has an adequate airway and supporting respiration and circulation. This should be rapidly followed by removal of all transdermal systems from the skin and the mouth. If there is evidence of transdermal system ingestion, endoscopic removal of swallowed transdermal systems, or administration of activated charcoal should be considered, as indicated by the clinical situation.
In any case where there is serious overdosage or signs of evolving acute toxicity, continuous monitoring of vital signs and ECG, establishment of intravenous access, and administration of oxygen are all recommended. The signs and symptoms of overdose/toxicity due to scopolamine should be carefully distinguished from the occasionally observed syndrome of withdrawal [see Warnings and Precautions ( 5.6 )]. Although mental confusion and dizziness may be observed with both acute toxicity and withdrawal, other characteristic findings differ: tachyarrhythmias, dry skin, and decreased bowel sounds suggest anticholinergic toxicity, while bradycardia, headache, nausea and abdominal cramps, and sweating suggest post-removal withdrawal.
If over-exposure occurs, call the Poison Help line at 1-800-222-1222 for current information on the management of poisoning or overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Scopolamine, a belladonna alkaloid, is an anticholinergic. Scopolamine acts: i) as a competitive inhibitor at postganglionic muscarinic receptor sites of the parasympathetic nervous system, and ii) on smooth muscles that respond to acetylcholine but lack cholinergic innervation. It has been suggested that scopolamine acts in the central nervous system (CNS) by blocking cholinergic transmission from the vestibular nuclei to higher centers in the CNS and from the reticular formation to the vomiting center.
Scopolamine can inhibit the secretion of saliva and sweat, decrease gastrointestinal secretions and motility, cause drowsiness, dilate the pupils, increase heart rate, and depress motor function.
12.3Pharmacokinetics The system is formulated to deliver approximately 1 mg of scopolamine to the systemic circulation over 3 days. Absorption Following application to the skin behind the ear, circulating plasma concentrations are detected within 4 hours with peak concentrations being obtained, on average, within 24 hours. The average plasma concentration produced is 87 pg/mL (0.28 nM) for free scopolamine and 354 pg/mL for total scopolamine (free + conjugates).
Following removal of the used transdermal system, there is some degree of continued systemic absorption of scopolamine bound in the skin layers. Distribution The distribution of scopolamine is not well characterized. It crosses the placenta and the blood brain barrier and may be reversibly bound to plasma proteins.
Elimination Metabolism and Excretion Scopolamine is metabolized and conjugated with less than 5% of the total dose appearing unchanged in the urine. The enzymes responsible for metabolizing scopolamine are unknown. The exact elimination pattern of scopolamine has not been determined.
Following transdermal system removal, plasma concentrations of scopolamine decline in a log linear fashion with an observed half-life of 9.5 hours. Less than 10% of the total dose is excreted in the urine as the parent drug and metabolites over 108 hours. Drug Interaction Studies An in vitro study using human hepatocytes examined the induction of CYP1A2 and CYP3A4 by scopolamine.
Scopolamine did not induce CYP1A2 and CYP3A4 isoenzymes at the concentrations up to 10 nM. In an in vitro study using human liver microsomes which evaluated the inhibition of CYP1A2, 2C8, 2C9, 2C19, 2D6 and 3A4, scopolamine did not inhibit these cytochrome P450 isoenzymes at the concentrations up to 1 micromolar. No in vivo drug-drug interaction studies have been conducted.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Scopolamine, a belladonna alkaloid, is an anticholinergic. Scopolamine acts: i) as a competitive inhibitor at postganglionic muscarinic receptor sites of the parasympathetic nervous system, and ii) on smooth muscles that respond to acetylcholine but lack cholinergic innervation. It has been suggested that scopolamine acts in the central nervous system (CNS) by blocking cholinergic transmission from the vestibular nuclei to higher centers in the CNS and from the reticular formation to the vomiting center.
Scopolamine can inhibit the secretion of saliva and sweat, decrease gastrointestinal secretions and motility, cause drowsiness, dilate the pupils, increase heart rate, and depress motor function.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Scopolamine transdermal system 1 mg/3 days is available as the following: Carton of 4 transdermal systems, packaged into individual foil pouches. NDC 50742-505-04 Carton of 10 transdermal systems, packaged into individual foil pouches. NDC 50742-505-10 Carton of 24 transdermal systems, packaged into individual foil pouches.
NDC 50742-505-24 Store at controlled room temperature between 68°F to 77°F (20°C to 25°C). Store pouch(es) in an upright position. Do not bend or roll pouch(es).
Wash hands thoroughly with soap and water immediately after handling the transdermal system. Avoid touching the system during the treatment. Upon removal, fold the used transdermal system in half with the sticky side together, and discard in household trash in a manner that prevents accidental contact or ingestion by children, pets or others.
Wash the hands and application site with soap and water after transdermal system removal [see Dosage and Administration ( 2.1 ), Warnings and Precautions ( 5.7 )] .
📋 Description ▾
11 DESCRIPTION Scopolamine transdermal system is designed for continuous release of scopolamine following application to an area of intact skin on the head, behind the ear. Each system contains 1.5 mg of scopolamine base. Scopolamine is (9-methyl-3-oxa-9-azatricyclo[3.3.1.0 2,4 ]nonan-7-yl) 3-hydroxy-2 phenylpropanoate.
The empirical formula is C 17 H 21 NO 4 and its structural formula is: Scopolamine has a molecular weight of 303.35 and a pKa of 7.55-7.81. The scopolamine transdermal system is a circular, 0.2 mm thick, 2.5 cm 2 film with four layers. Proceeding from the visible surface towards the surface attached to the skin, these layers are: (1) a backing membrane of tan-colored, aluminized, polyester film printed with brown ink; (2) a drug adhesive layer of scopolamine, acrylic adhesive and isopropyl myristate; (3) an ethylene vinyl acetate membrane that controls the rate of delivery of scopolamine from the system to the skin surface; and (4) a drug adhesive layer of scopolamine, acrylic adhesive and isopropyl myristate.
A release liner of siliconized polyester, which covers the adhesive layer, is removed before the system is used. The brown imprinting ink contains FD&C yellow no. 6 aluminum lake, polyamide resin, polytetrafluoroethylene, polyethylene wax, carbon black and quinacridone red pigment.
Cross section of the system: Structure System
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Administration Instructions Counsel patients on how to apply and remove the transdermal system [see Dosage and Administration ( 2.1 )] : Only wear one transdermal system at any time. Do not cut the transdermal system.
Apply the transdermal system to the skin in the postauricular (hairless area behind one ear) area. After the transdermal system is applied on the dry skin behind the ear, wash hands thoroughly with soap and water and dry hands. If the transdermal system becomes displaced, discard the transdermal system, and apply a new transdermal system on the hairless area behind the other ear.
Once the transdermal system has been affixed, avoid touching or applying pressure to the transdermal system, since pressure exerted on it may cause scopolamine to ooze out at the edge. Upon removal, fold the used transdermal system in half with the sticky side together, and discard in household trash in a manner that prevents accidental contact or ingestion by children, pets or others. Wash the hands and application site with soap and water after transdermal system removal.
Patients with Open-Angle Glaucoma Advise patients with open-angle glaucoma to remove the scopolamine transdermal system immediately and contact their healthcare provider if they experience symptoms of acute angle closure glaucoma, including pain and reddening of the eyes, accompanied by dilated pupils, blurred vision and/or seeing halos around lights [see Warnings and Precautions ( 5.1 )] . Neuropsychiatric Adverse Reactions Advise patients that psychiatric adverse reactions may occur, especially in patients with a past psychiatric history or in those receiving other drugs also associated with psychiatric effects, and to report to their healthcare provider any new or worsening psychiatric symptoms.
Advise patients to discontinue scopolamine transdermal system and contact a healthcare provider immediately if they experience a seizure. Advise patients, especially elderly patients, that cognitive impairment may occur during treatment with scopolamine transdermal system, especially in those receiving other drugs also associated with CNS effects, and to report to their healthcare provider if they develop signs or symptoms of cognitive impairment such as hallucinations, confusion or dizziness. Inform patients not to operate motor vehicles or other dangerous machinery or participate in underwater sports until they are reasonably certain that scopolamine transdermal system does not affect them adversely [see Warnings and Precautions ( 5.2 )] .
Decreased Gastrointestinal Motility and Urinary Retention Instruct patients to remove the transdermal system if they develop symptoms of intestinal obstruction (abdominal pain, nausea or vomiting) or any difficulties in urinating [see Warnings and Precautions ( 5.4 )] . Hyperthermia Inform patients that scopolamine transdermal system can increase body temperature and reduce sweating, which may result in hyperthermia and be exacerbated by exposure to external heat sources or high environmental temperature. Geriatric patients may be more susceptible to these effects.
Advise patients if body temperature increases, or they are not sweating in warm environmental conditions, remove the transdermal system, and contact their healthcare provider. Symptoms may persist after removal of the transdermal system [see Warnings and Precautions ( 5.5 )] . Drug Withdrawal/Post-Removal Symptoms Inform patients that if they remove the scopolamine transdermal system after several days of use, withdrawal symptoms may occur and to seek immediate medical care if they develop severe symptoms after removing scopolamine transdermal system [see Warnings and Precautions ( 5.6 )] .
Blurred Vision Inform patients that temporary dilation of the pupils and blurred vision may occur if scopolamine transdermal system comes in contac…