
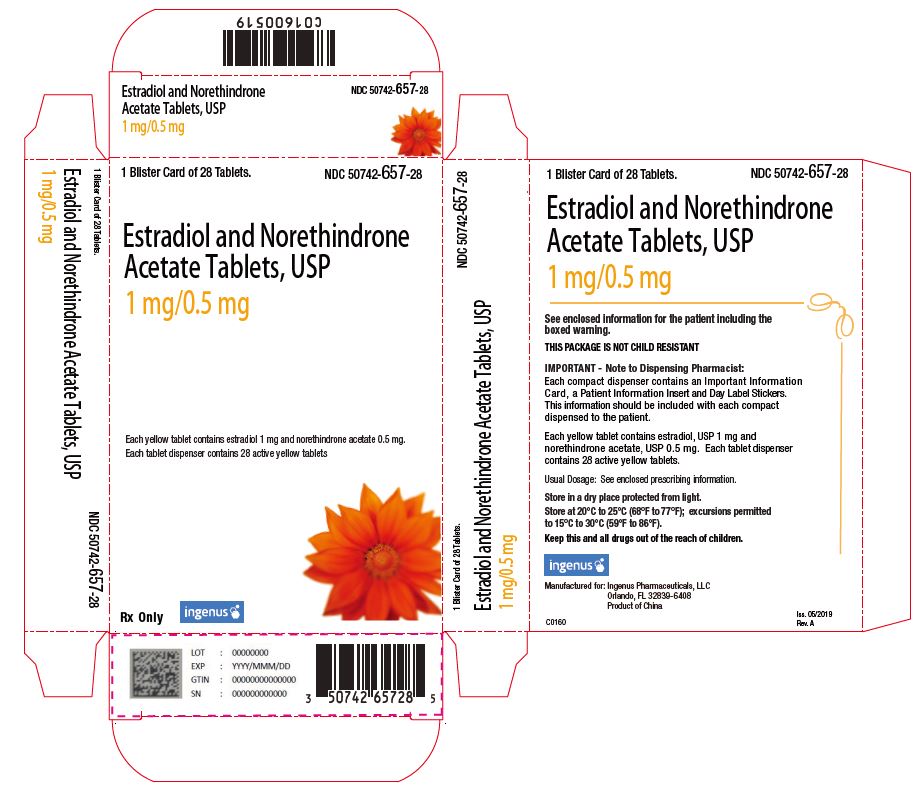
Estradiol and Norethindrone Acetate 1 mg; .5 mg Tablet, 168-count — NDC 50742-657-68 (Billing 50742-0657-68)
This is a package of 168 tablets of Estradiol and Norethindrone Acetate 1 mg; .5 mg Tablet from Ingenus Pharmaceuticals, LLC, marketed since Apr 2019 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 50742-657-68 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 50742 labeler · 657 product · 68 package
- Package marketed since
- Apr 3, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 5074265768 1
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 040888
- GCN: 95046
- GPI-14 (Medi-Span): 24993002120310
- HICL (First Databank): 007310
- AHFS class code: 68:16.04.00
- RxCUI (RxNorm): 1359123
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Radioactive Diagnostic Agent class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Great question. The estradiol (the estrogen part) is what actually relieves your hot flashes, night sweats, and vaginal dryness by replacing the estrogen your body stopped making a...
- What exactly is this medicine doing for me — why do I need both an estrogen and a progestin?
- Most women notice things like breast tenderness, some spotting or light bleeding, headaches, or nausea — especially in the first few months. Those are common and usually settle dow...
- What are the most important side effects I should actually watch out for?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.20 | $201.45 / 168 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 7, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 50742-0657-28 50742-657-28 Main listing | 1 BLISTER PACK in 1 CARTON / 28 TABLET in 1 BLISTER PACK | $0.5697 / ea | $15.95 | 2019-04-03 | — | Active |
| 50742-0657-68 You're viewing this | 6 BLISTER PACK in 1 CARTON / 28 TABLET in 1 BLISTER PACK | — | — | 2019-04-03 | — | Active |
| 50742-0657-84 50742-657-84 | 3 BLISTER PACK in 1 CARTON / 28 TABLET in 1 BLISTER PACK | $0.5697 / ea | $47.85 | 2019-04-03 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 50742-0657-28?
What NDC number is used to bill for this package of Estradiol and Norethindrone Acetate 1 mg; .5 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Estradiol / Norethindrone Acetate 1 mg/1; .5 mg 51991-0474-28 | Breckenridge | 28 tablets | $0.570 | AB | Availability likely | — |
| Abigale 1 mg/1; .5 mg 70700-0330-85 | Xiromed | 84 tablets | $0.570 | AB | Availability likely | — |
| Mimvey 1 mg/1; .5 mg 00093-5455-28 | Teva | 28 tablets | $0.570 | AB | Availability likely | — |
| Estradiol and Norethindrone Acetate 1 mg/1; .5 mgthis 50742-0657-68 | Ingenus | 168 tablets | — | AB | FDA listed | — |
| Etyqa 1 mg/1; .5 mg 59651-0424-28 | Aurobindo | 28 tablets | — | — | FDA listed | — |
| Estradiol / Norethindrone Acetate 1 mg/1; .5 mg 50090-8003-00 | A-S | 28 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Estradiol / Norethindrone inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Ingenus Pharmaceuticals, LLC labeler code 50742
- Quetiapine Fumarate 200 mg Tablet, Extended Release NDC 50742-637-10
- Quetiapine Fumarate 300 mg Tablet, Extended Release NDC 50742-638-10
- Quetiapine Fumarate 400 mg Tablet, Extended Release NDC 50742-639-10
- Triazolam .125 mg Tablet NDC 50742-645-01
- Triazolam .25 mg Tablet NDC 50742-646-01
- Carisoprodol 350 mg Tablet NDC 50742-656-01
- Estradiol and Norethindrone Acetate .5 mg; .1 mg Tablet NDC 50742-658-28
- Dolishale Levonorgestrel and Ethinyl Estradiol 90 ug; 20 ug Tablet NDC 50742-659-28
- Phenobarbital, Hyoscyamine Sulfate, Atropine Sulfate, Scopolamine Hydrobromide 16.2 mg/5mL; .1037 mg/5mL; .0194 mg/5mL; .0065 mg/5mL Elixir NDC 50742-665-04
- Phenobarbital, Hyoscyamine Sulfate, Atropine Sulfate, Scopolamine Hydrobromide 16.2 mg/5mL; .1037 mg/5mL; .0194 mg/5mL; .0065 mg/5mL Elixir NDC 50742-666-04
- Phenobarbital, Hyoscyamine Sulfate, Atropine Sulfate and Scopolamine Hydrobromide 16.2 mg; .1037 mg; .0194 mg; .0065 mg Tablet NDC 50742-667-01
- Nicotine Transdermal System 7 mg/24h Patch NDC 50742-668-07
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CARDIOVASCULAR DISORDERS, PROBABLE DEMENTIA, BREAST CANCER, and ENDOMETRIAL CANCER WARNING: CARDIOVASCULAR DISORDERS, PROBABLE DEMENTIA, BREAST CANCER, and ENDOMETRIAL CANCER S ee full prescribing information for complete boxed warning Estrogen Plus Progestin Therapy ● The Women's Health Initiative (WHI) estrogen plus progestin substudy reported increased risks of deep vein thrombosis (DVT), pulmonary embolism (PE), stroke and myocardial infarction (MI) ( 5.1 ) ● The WHI estrogen plus progestin substudy reported increased risks of invasive breast cancer ( 5.2 ) ● The WHI Memory Study (WHIMS) estrogen plus progestin ancillary study of WHI reported an increased risk of probable dementia in postmenopausal women 65 years of age and older ( 5.3 ) ● Do not use estrogen plus progestogen therapy for the prevention of cardiovascular disease or dementia ( 5.1 , 5.3 ) Estrogen-Alone Therapy ● There is an increased risk of endometrial cancer in a woman with a uterus who use unopposed estrogens ( 5.2 ) ● The WHI estrogen-alone substudy reported increased risks of stroke and DVT ( 5.1 ) ● The WHIMS estrogen-alone ancillary study of WHI reported an increased risk of probable dementia in postmenopausal women 65 years of age and older ( 5.3 ) ● Do not use estrogen-alone therapy for the prevention of cardiovascular disease or dementia ( 5.2 , 5.3 ) Estrogen Plus Progestin Therapy Cardiovascular Disorders and Probable Dementia The Women's Health Initiative (WHI) estrogen plus progestin substudy reported increased risks of deep vein thrombosis (DVT), pulmonary embolism (PE), stroke and myocardial infarction (MI) in postmenopausal women (50 to 79 years of age) during 5.6 years of treatment with daily oral conjugated estrogen (CE) [0.625 mg] combined with medroxyprogesterone acetate (MPA) [2.5 mg], relative to placebo [see Warnings and Precautions ( 5.1 ), and Clinical Studies ( 14.5 )] .
The WHI Memory Study (WHIMS) estrogen plus progestin ancillary study of the WHI reported an increased risk of developing probable dementia in postmenopausal women 65 years of age and older during 4 years of treatment with daily CE (0.625 mg) combined with MPA (2.5 mg), relative to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.5 ), and Clinical Studies ( 14.6 )]. Do not use estrogen plus progestogen therapy for the prevention of cardiovascular disease or dementia [ see Warnings and Precautions ( 5.1 , 5.3 ), and Clinical Studies ( 14.5 , 14.6 ) ].
Breast Cancer The WHI estrogen plus progestin substudy also demonstrated an increased risk of invasive breast cancer [see Warnings and Precautions ( 5.2 ), and Clinical Studies ( 14.5 )] . Only daily oral 0.625 mg CE and 2.5 mg MPA were studied in the estrogen plus progestin substudy of the WHI. Therefore, the relevance of the WHI findings regarding adverse cardiovascular events, dementia and breast cancer to lower CE plus other MPA doses, other routes of administration, or other estrogen plus progestogen products is not known.
Without such data, it is not possible to definitively exclude these risks or determine the extent of these risks for other products. Discuss with your patient the benefits and risks of estrogen plus progestogen therapy, taking into account her individual risk profile. Prescribe estrogens with or without progestogens at the lowest effective doses and for the shortest duration consistent with treatment goals and risks for the individual woman.
Estrogen-Alone Therapy Endometrial Cancer There is an increased risk of endometrial cancer in a woman with a uterus who uses unopposed estrogens. Adding a progest ogen to estrogen therapy has been shown to reduce the risk of endometrial hyperplasia, which may be a precursor to endometrial cancer. Adequate diagnostic measures, including directed or random endometrial sampling when indicated, should be undertaken to rule out malignancy in postmeno… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Estradiol and norethindrone acetate tablets are an estrogen and progestin combination indicated in a woman with a uterus for: Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause ( 1.1 ) Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause ( 1.2 ) Limitations of Use: When prescribing solely for the treatment of moderate to severe symptoms of vulvar and vaginal atrophy due to menopause, first consider the use of topical vaginal products. Prevention of Postmenopausal Osteoporosis ( 1.3 ) Limitations of Use: When prescribing solely for the prevention of postmenopausal osteoporosis, first consider the use of non-estrogen medications.
Consider estrogen therapy only for women at significant risk of osteoporosis. Estradiol and norethindrone acetate tablets are indicated for:
1.1 Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause
1.2Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause Limitation of Use When prescribing solely for the treatment of moderate to severe symptoms of vulvar and vaginal atrophy due to menopause, first consider the use of topical vaginal products.
1.3Prevention of Postmenopausal Osteoporosis Limitation of Use When prescribing solely for the prevention of postmenopausal osteoporosis, first consider the use of non-estrogen medications. Consider estrogen therapy only for women at significant risk of osteoporosis.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take a single estradiol and norethindrone acetate 1 mg/0.5 mg or 0.5 mg/0.1 mg tablet orally once daily for the Treatment of Moderate to severe Vasomotor Symptoms due to Menopause and for the Prevention of Postmenopausal Osteoporosis ( 2.1 , 2.3 ) Estradiol and norethindrone acetate 1 mg/0.5 mg tablets are taken orally once daily for the Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause ( 2.2 ) Use estrogen-alone, or in combination with a progestogen, at the lowest effective dose and the shortest duration consistent with treatment goals and risks for the individual woman.
Reevaluate postmenopausal women periodically as clinically appropriate to determine whether treatment is still necessary.
2.1Treatment of Moderate to Severe Vasomotor Symptoms due to Menopause Take a single estradiol and norethindrone acetate tablet orally once daily for the treatment of moderate to severe vasomotor symptoms due to menopause. Estradiol and norethindrone acetate tablets 1 mg/0.5 mg Estradiol and norethindrone acetate tablets 0.5 mg/0.1 mg
2.2Treatment of Moderate to Severe Symptoms of Vulvar and Vaginal Atrophy due to Menopause Take a single estradiol and norethindrone acetate tablet orally once daily for the treatment of moderate to severe symptoms of vulvar and vaginal atrophy due to menopause. Estradiol and norethindrone acetate tablets 1 mg/0.5 mg
2.3Prevention of Postmenopausal Osteoporosis Take a single estradiol and norethindrone acetate tablet orally once daily for the prevention of postmenopausal osteoporosis. Estradiol and norethindrone acetate tablets 1 mg/0.5 mg Estradiol and norethindrone acetate tablets 0.5 mg/0.1 mg
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Estradiol and norethindrone acetate 1 mg/0.5 mg tablet ( 3 ) Estradiol and norethindrone acetate 0.5 mg/0.1 mg tablet ( 3 ) Estradiol and norethindrone acetate tablets, USP are available in two strengths: Each tablet of estradiol and norethindrone acetate 1 mg/ 0.5 mg contains 1 mg of estradiol and 0.5 mg of norethindrone acetate. The tablets are yellow, round, bi-convex tablets debossed "J2" on one side. Each tablet of estradiol and norethindrone acetate 0.5 mg/ 0.1 mg contains 0.5 mg of estradiol and 0.1 mg of norethindrone acetate.
The tablets are pale yellow, round, bi-convex tablets debossed "J1" on one side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Undiagnosed abnormal genital bleeding ( 4 ) Breast cancer or a history of breast cancer ( 4 , 5.2 ) Estrogen-dependent neoplasia ( 4 , 5.2 ) Active DVT, PE, or history of these conditions ( 4 , 5.1 ) Active arterial thromboembolic disease (for example, stroke and MI), or a history of these conditions ( 4 , 5.1 ) Known anaphylactic reaction, angioedema, or hypersensitivity to estradiol and norethindrone acetate tablets ( 4 ) Hepatic impairment or disease ( 4 , 5.10 ) Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders ( 4 ) Estradiol and norethindrone acetate tablets are contraindicated in women with any of the following conditions: • Undiagnosed abnormal genital bleeding [ see Warnings and Precautions ( 5.2 ) ] • Breast cancer or history of breast cancer [ see Warnings and Precautions ( 5.2 ) ] • Estrogen-dependent neoplasia [ see Warnings and Precautions ( 5.2 ) ] • Active DVT, PE, or history of these conditions [ see Warnings and Precautions ( 5.1 ) ] • Active arterial thromboembolic disease (for example, stroke and MI), or a history of these conditions [ see Warnings and Precautions ( 5.1 ) ] • Known anaphylactic reaction, angioedema, or hypersensitivity to estradiol and norethindrone acetate tablets • Hepatic impairment or disease • Protein C, protein S, or antithrombin deficiency, or other known thrombophilic disorders
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Estrogens increase the risk of gall bladder disease ( 5.4 ) Discontinue estrogen if severe hypercalcemia, loss of vision, severe hypertriglyceridemia or cholestatic jaundice occurs ( 5.5 , 5.6 , 5.9 , 5.10 ) Monitor thyroid function in women on thyroid replacement therapy ( 5.11 , 5.18 )
5.1Cardiovascular Disorders Increased risks of PE, DVT, stroke and MI are reported with estrogen plus progestin therapy. Increased risks of stroke and DVT are reported with estrogen-alone therapy. Immediately discontinue estrogen with or without progestogen therapy if any of these occur or is suspected.
Manage appropriately any risk factors for arterial vascular disease (for example, hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or venous thromboembolism (VTE) (for example, personal history or family history of VTE, obesity, and systemic lupus erythematosus). Stroke The WHI estrogen plus progestin substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women in the same age group receiving placebo (33 versus 25 strokes per 10,000 women-years) [see Clinical Studies ( 14.5 )] .
The increase in risk was demonstrated after the first year and persisted. 1 Immediately discontinue estrogen with or without progestogen therapy if a stroke occurs or is suspected. The WHI estrogen-alone substudy reported a statistically significant increased risk of stroke in women 50 to 79 years of age receiving daily CE (0.625 mg)-alone compared to women in the same age group receiving placebo (45 versus 33 strokes per 10,000 women-years, respectively).
The increase in risk was demonstrated in year 1 and persisted [see Clinical Studies ( 14.5 )] . Immediately discontinue estrogen-alone therapy if a stroke occurs or is suspected. Subgroup analyses of women 50 to 59 years of age suggest no increased risk of stroke for those women receiving CE (0.625 mg)-alone versus those receiving placebo (18 versus 21 per 10,000 women-years).
1 Coronary Heart Disease The WHI estrogen plus progestin substudy reported an increased risk (not statistically significant) of coronary heart disease (CHD) events (defined as nonfatal MI, silent MI, or CHD death) in those women receiving daily CE (0.625 mg) plus MPA (2.5 mg) compared to women receiving placebo (41 versus 34 per 10,000 women-years). 1 An increase in relative risk was demonstrated in year 1, and a trend toward decreasing relative risk was reported in years 2 through 5 [see Clinical Studies ( 14.5 )] .
The WHI estrogen-alone substudy reported no overall effect on CHD events in women receiving estrogen-alone compared to placebo 2 [see Clinical Studies ( 14.5 )]. Subgroup analyses of women 50 to 59 years of age, who were less than 10 years since menopause, suggest a reduction (not statistically significant) in CHD events in those women receiving daily CE (0.625 mg)-alone compared to placebo (8 versus 16 per 10,000 women-years). 1 In postmenopausal women with documented heart disease (n=2,763), average 66.7 years of age, in a controlled clinical trial of secondary prevention of cardiovascular disease (Heart and Estrogen/Progestin Replacement Study; HERS), treatment with daily CE (0.625 mg plus MPA (2.5 mg) demonstrated no cardiovascular benefit.
During an average follow-up of 4.1 years, treatment with CE plus MPA did not reduce the overall rate of CHD events in postmenopausal women with established CHD. There were more CHD events in the CE plus MPA- treated group than in the placebo group in year 1, but not during the subsequent years. Two thousand three hundred twenty-one (2,321) women from the original HERS trial agreed to participate in an open label extension of HERS, HERS II.
Average follow-up in HERS II was an additional 2.7 years, for a total of 6.8 years overall. Rates of CHD events were comparable among women in the CE plus MPA group and the placebo group i… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (incidence ≥ 5 percent) with estradiol and norethindrone acetate tablets are: back pain, headache, pain in the extremity, nausea, diarrhea, gastroenteritis, insomnia, emotional lability, upper respiratory tract infection, sinusitis, nasopharyngitis, weight increase, breast pain, post-menopausal bleeding, uterine fibroid vaginal hemorrhage, ovarian cyst, endometrial thickening, viral infection, moniliasis genital, and accidental injury. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ingenus Pharmaceuticals, LLC Toll-Free at 1- 877-748-1970 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
The following serious adverse reactions are discussed elsewhere in the labeling: Cardiovascular Disorders [see Boxed Warning, Warnings and Precautions ( 5.1 )] Malignant Neoplasms [see Boxed Warning, Warnings and Precautions, ( 5.2 )]
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse reactions reported with estradiol and norethindrone acetate tablets 1 mg/0.5 mg by investigators during clinical trials regardless of causality assessment are shown in Table 1. Adverse reactions reported with estradiol and norethindrone acetate tablets 0.5 mg/0.1 mg by investigators during clinical trials regardless of causality assessment are shown in Table 2.
TABLE 2 ALL TREATMENT-EMERGENT ADVERSE REACTIONS REGARDLESS OF RELATIONSHIP REPORTED AT A FREQUENCY OF ≥5 PERCENT WITH ESTRADIOL AND NORETHINDRONE ACETATE TABLETS
0.5MG/0.1 MG E 2 /NETA Tablets 0.5 mg/0.1 mg (n=194) Placebo (n=200) Body as a Whole Back Pain 10% 4% Headache 22% 19% Pain in extremity 5% 4% Digestive System Nausea 5% 4% Diarrhea 6% 6% Respiratory System Nasopharyngitis 21% 18% Urogenital System Endometrial thickening 10% 4% Vaginal hemorrhage 26% 12% E 2 /NETA Tablets = Estradiol and Norethindrone Acetate Tablets Image
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of estradiol and norethindrone acetate tablets. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Genitourinary System Changes in vaginal bleeding pattern and abnormal withdrawal bleeding or flow; breakthrough bleeding; spotting; dysmenorrhea, increase in size of uterine leiomyomata; vaginitis, including vaginal candidiasis; change in amount of cervical secretion; changes in cervical ectropion; pre-menstrual-like syndrome; cystitis- like syndrome; ovarian cancer; endometrial hyperplasia; endometrial cancer.
Breast Tenderness, enlargement, pain, nipple discharge, galactorrhea; fibrocystic breast changes; breast cancer. Cardiovascular Deep and superficial venous thrombosis; pulmonary embolism; thrombophlebitis; myocardial infarction, stroke; increase in blood pressure. Gastrointestinal Nausea, vomiting; changes in appetite; cholestatic jaundice; abdominal pain/cramps, flatulence, bloating; increased incidence of gallbladder disease and pancreatitis.
Skin Chloasma or melasma that may persist when drug is discontinued; erythema multiforme; erythema nodosum; hemorrhagic eruption; loss of scalp hair; seborrhea; hirsutism; itching; skin rash; pruritus. Eyes Retinal vascular thrombosis, intolerance to contact lenses. Central Nervous System Headache; migraine; dizziness; mental depression; chorea; insomnia; nervousness; mood disturbances; irritability; exacerbation of epilepsy; dementia.
Miscellaneous Increase or decrease in weight; edema; leg cramps; changes in libido; fatigue; exacerbation of asthma; increased triglycerides; hypersensitivity; anaphylactoid/anaphylactic reactions.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Inducers and/or inhibitors of CYP3A4 may affect estrogen drug metabolism and decrease or increase the estrogen plasma concentration. ( 7 ) Co-administration of estradiol with norethindrone acetate did not elicit any apparent influence on the pharmacokinetics of norethindrone acetate. Similarly, no relevant interaction of norethindrone acetate on the pharmacokinetics of estradiol was found within the NETA dose range investigated in a single dose study.
Estradiol In-vitro and in-vivo studies have shown that estrogens are metabolized partially by cytochrome P450 3A4 (CYP3A4). Therefore, inducers or inhibitors of CYP3A4 may affect estrogen drug metabolism. Inducers of CYP3A4 such as St.
John's wort ( Hypericum perforatum ) preparations, phenobarbital, carbamazepine, and rifampin may reduce plasma concentrations of estrogens, possibly resulting in a decrease in therapeutic effects and/or changes in the uterine bleeding profile. Inhibitors of CYP3A4 such as erythromycin, clarithromycin, ketoconazole, itraconazole, ritonavir and grapefruit juice may increase plasma concentrations of estrogens and result in adverse reactions. Norethindrone Acetate Drugs or herbal products that induce or inhibit cytochrome P-450 enzymes, including CYP3A4, may decrease or increase the serum concentrations of norethindrone.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Estradiol and norethindrone acetate tablets are not indicated for use in pregnancy. There are no data with the use of estradiol and norethindrone acetate tablets in pregnant women; however, epidemiologic studies and meta-analyses have not found an increased risk of genital or nongenital birth defects (including cardiac anomalies and limb-reduction defects) following exposure to combined hormonal contraceptives (estrogen and progestins) before conception or during early pregnancy. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
8.2Lactation Risk Summary Estrogens plus progestogens are present in human milk and can reduce milk production in breast-feeding women. This reduction can occur at any time but is less likely to occur once breast-feeding is well established. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for estradiol and norethindrone acetate tablets and any potential adverse effects on the breastfed child from estradiol and norethindrone acetate tablets or from the underlying maternal condition.
8.4Pediatric Use Estradiol and norethindrone acetate tablets are not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing estradiol and norethindrone acetate tablets to determine whether those over 65 years of age differ from younger subjects in their response to estradiol and norethindrone acetate tablets. The Women's Health Initiative Studies In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Clinical Studies ( 14.5 )] .
In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.5 )] . The Women's Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen plus progestin or estrogen-alone when compared to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
🧒 Pediatric Use ▾
8.4Pediatric Use Estradiol and norethindrone acetate tablets are not indicated for use in pediatric patients. Clinical studies have not been conducted in the pediatric population.
🧓 Geriatric Use ▾
8.5Geriatric Use There have not been sufficient numbers of geriatric women involved in clinical studies utilizing estradiol and norethindrone acetate tablets to determine whether those over 65 years of age differ from younger subjects in their response to estradiol and norethindrone acetate tablets. The Women's Health Initiative Studies In the WHI estrogen plus progestin substudy (daily CE [0.625 mg] plus MPA [2.5 mg] versus placebo), there was a higher relative risk of nonfatal stroke and invasive breast cancer in women greater than 65 years of age [see Clinical Studies ( 14.5 )] .
In the WHI estrogen-alone substudy (daily CE [0.625 mg]-alone versus placebo), there was a higher relative risk of stroke in women greater than 65 years of age [see Clinical Studies ( 14.5 )] . The Women's Health Initiative Memory Study In the WHIMS ancillary studies of postmenopausal women 65 to 79 years of age, there was an increased risk of developing probable dementia in women receiving estrogen plus progestin or estrogen-alone when compared to placebo. It is unknown whether this finding applies to younger postmenopausal women [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
Since both ancillary studies were conducted in women 65 to 79 years of age, it is unknown whether these findings apply to younger postmenopausal women 8 [see Warnings and Precautions ( 5.3 ), and Clinical Studies ( 14.6 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of estrogen plus progestogen may cause nausea, vomiting, breast tenderness, abdominal pain, drowsiness and fatigue, and withdrawal bleeding may occur in women. Treatment of overdose consists of discontinuation of estradiol and norethindrone acetate tablets therapy with institution of appropriate symptomatic care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate-conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH), and FSH through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women. Progestin compounds enhance cellular differentiation and generally oppose the actions of estrogens by decreasing estrogen receptor levels, increasing local metabolism of estrogens to less active metabolites, or inducing gene products that blunt cellular responses to estrogen. Progestins exert their effects in target cells by binding to specific progesterone receptors that interact with progesterone response elements in target genes.
Progesterone receptors have been identified in the female reproductive tract, breast, pituitary, hypothalamus, and central nervous system.
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman's therapeutic response to estradiol and norethindrone acetate tablets nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
12.3Pharmacokinetics Absorption Estradiol Estradiol is absorbed through the gastrointestinal tract. Following oral administration of estradiol and norethindrone acetate tablets, peak plasma estradiol concentrations are reached within 5 to 8 hours. The oral bioavailability of estradiol following administration of estradiol and norethindrone acetate tablets 1 mg/0.5 mg when compared to a combination oral solution is 53%.
Administration of estradiol and norethindrone acetate tablets 1 mg/0.5 mg with food did not modify the bioavailability of estradiol. Norethindrone Acetate After oral administration, norethindrone acetate is absorbed and transformed to norethindrone. Norethindrone reaches a peak plasma concentration within 0.5 to 1.5 hours after the administration of estradiol and norethindrone acetate tablets.
The oral bioavailability of norethindrone following administration of estradiol and norethindrone acetate tablets 1 mg/0.5 mg when compared to a combination oral solution is 100%. Administration of estradiol and norethindrone acetate tablets 1 mg/0.5 mg with food increases norethindrone AUC 0-72 by 19% and decreases C max by 36%. The pharmacokinetic parameters of estradiol (E 2 ), estrone (E 1 ), and norethindrone (NET) following oral administration of 1 estradiol and norethindrone acetate 1 mg/0.5 mg tablet or 2 estradiol and norethindrone acetate 0.5 mg/0.1 mg tablet(s) to healthy postmenopausal women are summarized in Table 3.
Following continuous dosing with once-daily administration of estradiol and norethindrone acetate tablets 1 mg/0.5 mg, serum concentrations of estradiol, estrone, and norethindrone reached steady-state within two weeks with an accumulation of 33 to 47% above concentrat… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous estrogens are largely responsible for the development and maintenance of the female reproductive system and secondary sexual characteristics. Although circulating estrogens exist in a dynamic equilibrium of metabolic interconversions, estradiol is the principal intracellular human estrogen and is substantially more potent than its metabolites, estrone and estriol, at the receptor level. The primary source of estrogen in normally cycling adult women is the ovarian follicle, which secretes 70 to 500 mcg of estradiol daily, depending on the phase of the menstrual cycle.
After menopause, most endogenous estrogen is produced by conversion of androstenedione, secreted by the adrenal cortex, to estrone in the peripheral tissues. Thus, estrone and the sulfate-conjugated form, estrone sulfate, are the most abundant circulating estrogens in postmenopausal women. Estrogens act through binding to nuclear receptors in estrogen-responsive tissues.
To date, two estrogen receptors have been identified. These vary in proportion from tissue to tissue. Circulating estrogens modulate the pituitary secretion of the gonadotropins, luteinizing hormone (LH), and FSH through a negative feedback mechanism.
Estrogens act to reduce the elevated levels of these hormones seen in postmenopausal women. Progestin compounds enhance cellular differentiation and generally oppose the actions of estrogens by decreasing estrogen receptor levels, increasing local metabolism of estrogens to less active metabolites, or inducing gene products that blunt cellular responses to estrogen. Progestins exert their effects in target cells by binding to specific progesterone receptors that interact with progesterone response elements in target genes.
Progesterone receptors have been identified in the female reproductive tract, breast, pituitary, hypothalamus, and central nervous system.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Estradiol and Norethindrone Acetate Tablets USP, 1 mg/0.5 mg are yellow round biconvex tablets, debossed "J2" on one side, supplied as 28 active tablets in a blister card and are available in the following configurations: Carton of 1 blister cards NDC 50742-657-28 Carton of 3 blister cards NDC 50742-657-84 Carton of 6 blister cards NDC 50742-657-68 Estradiol and Norethindrone Acetate Tablets USP, 0.5 mg/0.1 mg are pale yellow round biconvex tablets, debossed "J1" on one side, supplied as 28 active tablets in a blister card and are available in the following configurations: Carton of 1 blister cards NDC 50742-658-28 Carton of 3 blister cards NDC 50742-658-84 Carton of 6 blister cards NDC 50742-658-68
16.2Storage and Handling Store in a dry place protected from light. Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Estradiol and norethindrone acetate tablets USP, 1 mg/0.5 mg is a single tablet for oral administration containing 1 mg of estradiol and 0.5 mg of norethindrone acetate and the following excipients: lactose monohydrate, starch (corn), polysorbate 80, copovidone, magnesium stearate, polyvinyl alcohol, titanium dioxide, talc, macrogol/polyethylglycol 3350, lecithin (soya), D&C Yellow NO.10 Aluminum lake, FD&C Blue NO.2 Aluminum lake and FD&C Red NO.40 Aluminum lake. Estradiol and norethindrone acetate tablets USP, 0.5 mg/0.1 mg is a single tablet for oral administration containing 0.5 mg of estradiol and 0.1 mg of norethindrone acetate and the following excipients: lactose monohydrate, starch (corn), polysorbate 80, copovidone, magnesium stearate, polyvinyl alcohol, titanium dioxide, talc, macrogol/polyethylglycol 3350, lecithin (soya), D&C Yellow NO.10 Aluminum lake, FD&C Blue NO.2 Aluminum lake and FD&C Yellow NO.6 Aluminum lake.
Estradiol is a white or almost white crystalline powder. Its chemical name is estra-1, 3, 5 (10)- triene-3, 17β-diol hemihydrate with the empirical formula of C 18 H 24 O 2 , ½ H 2 O and a molecular weight of 281.4. The structural formula of E 2 is as follows: Norethindrone acetate (NETA) is a white or yellowish-white crystalline powder.
Its chemical name is 17β -acetoxy-19-nor-17α -pregn-4-en-20-yn-3-one with the empirical formula of C 22 H 28 O 3 and molecular weight of 340.5. The structural formula of NETA is as follows: Product meets USP dissolution test 2. Image Image
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise women to read the FDA-approved patient labeling ( Patient Information ) Vaginal Bleeding Inform postmenopausal women to report any vaginal bleeding to their healthcare provider as soon as possible [see Warnings and Precautions ( 5.2 )] . Possible Serious Adverse Reactions with Estrogen Plus Progestogen Therapy Inform postmenopausal women of possible serious adverse reactions of estrogen plus progestogen therapy including Cardiovascular Disorders, Malignant Neoplasms, and Probable Dementia [see Warnings and Precautions ( 5.1 , 5.2 , 5.3 )] .
Possible Common Adverse Reactions with Estrogen Plus Progest ogen Therapy Inform postmenopausal women of possible less serious but common adverse reactions of estrogen plus progestogen therapy such as headache, breast pain and tenderness, nausea and vomiting. Rx Only Iss: 03/2024 I0115 Rev.D Manufactured for: Ingenus Pharmaceuticals, LLC Orlando, FL 32839-6408 Product of China Image
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Generally, a serum estrogen concentration does not predict an individual woman's therapeutic response to estradiol and norethindrone acetate tablets nor her risk for adverse outcomes. Likewise, exposure comparisons across different estrogen products to infer efficacy or safety for the individual woman may not be valid.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Effects on Vasomotor Symptoms in Postmenopausal Women In a 12-week randomized clinical trial involving 92 subjects, estradiol and norethindrone acetate tablets 1 mg/0.5 mg was compared to 1 mg of estradiol and to placebo. The mean number and intensity of hot flushes were significantly reduced from baseline to week 4 and 12 in both the estradiol and norethindrone acetate tablets 1 mg/0.5 mg and the 1 mg estradiol group compared to placebo (see Figure 2 ). In a study conducted in Europe a total of 577 postmenopausal women were randomly assigned to either estradiol and norethindrone acetate tablets 0.5 mg/0.1 mg, 0.5 mg E2/0.25 mg NETA, or placebo for 24 weeks of treatment.
The mean number and severity of hot flushes were significantly reduced at week 4 and week 12 in the estradiol and norethindrone acetate tablets 0.5 mg/0.1 mg (see Figure 3 ) and 0.5 mg E 2 /0.25 mg NETA groups compared to placebo.
14.2Effects on the Endometrium in Postmenopausal Women Estradiol and norethindrone acetate tablets 1 mg/0.5 mg reduced the incidence of estrogen-induced endometrial hyperplasia at 1 year in a randomized, controlled clinical trial. This trial enrolled 1,176 postmenopausal women who were randomized to one of 4 arms: 1 mg estradiol unopposed (n=296), 1 mg E 2 + 0.1 mg NETA (n=294), 1 mg E 2 + 0.25 mg NETA (n=291), and estradiol and norethindrone acetate tablets 1 mg/0.5 mg (n=295). At the end of the study, endometrial biopsy results were available for 988 women.
The results of the 1 mg estradiol unopposed arm compared to estradiol and norethindrone acetate tablets 1 mg/0.5 mg are shown in Table 4 . TABLE 4 INCIDENCE OF ENDOMETRIAL HYPERPLASIA WITH UNOPPOSED ESTRADIOL AND ESTRADIOL AND NORETHINDRONE ACETATE TABLETS 1 MG/0.5 MG IN A 12-MONTH STUDY Estradiol and norethindrone acetate tablets 1 mg E 2 1 mg E 2 /0.5 mg NETA 1 mg E 2 /0.25 mg NETA 1 mg E 2 /0.1 mg NETA (n=296) (n=295) (n=291 ) (n=294 ) No. of subjects with histological evaluation at the end of the study 247 241 251 249 No.
(%) of subjects with endometrial hyperplasia at the end 36 (14.6%) 1 (0.4%) 1 (0.4%) 2 (0.8%) of the study E 2 = Estradiol NETA = Norethindrone Acetate
14.3Effects on Uterine Bleeding or Spotting in Postmenopausal Women During the initial months of therapy, irregular bleeding or spotting occurred with estradiol and norethindrone acetate tablets 1 mg/0.5 mg treatment. However, bleeding tended to decrease over time, and after 12 months of treatment with estradiol and norethindrone acetate tablets 1 mg/0.5 mg, about 86 percent of women were amenorrheic (see Figure 4 ). In the clinical trial with estradiol and norethindrone acetate tablets 0.5 mg/0.1 mg, 88 percent of women were amenorrheic after 6 months of treatment (See Figure 5 ).
14.4Effects on Bone Mineral Density in Postmenopausal Women The results of two randomized, multicenter, calcium-supplemented (500 to 1,000 mg per day), placebo-controlled, 2 year clinical trials have shown that estradiol and norethindrone acetate tablets 1 mg/0.5 mg and estradiol 0.5 mg are effective in preventing bone loss in postmenopausal women. A total of 462 postmenopausal women with intact uteri and baseline BMD values for lumbar spine within 2 standard deviations of the mean in healthy young women (T-score > - 2.0) were enrolled.
In a US trial, 327 postmenopausal women (mean time from menopause 2.5 to 3.1 years) with a mean age of 53 years were randomized to 7 groups (0.25 mg, 0.5 mg, and 1 mg of estradiol alone, 1 mg estradiol with 0.25 mg norethindrone acetate, 1 mg estradiol with 0.5 mg norethindrone acetate, and 2 mg estradiol with 1 mg norethindrone acetate, and placebo.) In a European trial (EU trial), 135 postmenopausal women (mean time from menopause 8.4 to 9.3 years) with a mean age of 58 years were randomized to 1 mg estradiol with 0.25 mg norethindrone acetate, 1 mg estradiol with 0.5 mg norethindrone acetate, and placebo.
Approximately 58 percent and 67 percent of the randomized subje… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term continuous administration of natural and synthetic estrogens in certain animal species increases the frequency of carcinomas of the breast, uterus, cervix, vagina, testis, and liver.
📚 References ▾
15 REFERENCES 1. Rossouw JE, et al. Postmenopausal Hormone Therapy and Risk of Cardiovascular Disease by Age and Years Since Menopause.
JAMA . 2007; 297:1465-1477. 2.
Hsia J, et al. Conjugated Equine Estrogens and Coronary Heart Disease. Arch Int Med .
2006; 166:357-365. 3. Cushman M, et al.
Estrogen Plus Progestin and Risk of Venous Thrombosis. JAMA . 2004; 292:1573-1580.
4. Curb JD, et al. Venous Thrombosis and Conjugated Equine Estrogen in Women Without a Uterus.
Arch Int Med . 2006; 166:772-780. 5.
Chlebowski RT, et al. Influence of Estrogen Plus Progestin on Breast Cancer and Mammography in Healthy Postmenopausal Women. JAMA .
2003; 289:3234-3253. 6. Stefanick ML, et al.
Effects of Conjugated Equine Estrogens on Breast Cancer and Mammography Screening in Postmenopausal Women With Hysterectomy. JAMA . 2006; 295:1647-1657.
7. Anderson GL, et al. Effects of Estrogen Plus Progestin on Gynecologic Cancers and Associated Diagnostic Procedures.
JAMA . 2003; 290:1739-1748. 8.
Shumaker SA, et al. Conjugated Equine Estrogens and Incidence of Probable Dementia and Mild Cognitive Impairment in Postmenopausal Women. JAMA .
2004; 291:2947-2958. 9. Jackson RD, et al.
Effects of Conjugated Equine Estrogen on Risk of Fractures and BMD in Postmenopausal Women With Hysterectomy: Results From the Women's Health Initiative Randomized Trial. J Bone Miner Res . 2006; 21:817-828.
10. Hendrix SL, et al. Effects of Conjugated Equine Estrogen on Stroke in the Women's Health Initiative.
Circulation . 2006; 113:2425-2434.
📄 Patient Package Insert ▾
Patient Information Estradiol and Norethindrone Acetate (ES-tra-DYE-ol/nor-eth-IN-drone as-i-teyt) Tablets , USP Read this Patient Information before you start using estradiol and norethindrone acetate tablets and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your menopausal symptoms or your treatment.
What are estradiol and norethindrone acetate tablets? Estradiol and norethindrone acetate tablets are prescription medicines that contain two kinds of hormones, an estrogen and a progestogen. What are estradiol and norethindrone acetate tablets used for?
Estradiol and norethindrone acetate tablets are used after menopause to: • R educe moderate to severe hot flushes Estrogens are hormones made by a woman's ovaries. The ovaries normally stop making estrogens when a woman is between 45 and 55 yrs old. This drop in body estrogen levels causes the "change of life" or menopause, the end of monthly menstrual periods.
Sometimes both ovaries are removed during an operation before natural menopause takes place. The sudden drop in estrogen levels causes "surgical menopause." When estrogen levels begin dropping, some women get very uncomfortable symptoms, such as feelings of warmth in the face, neck, and chest, or sudden, intense feelings of heat and sweating ("hot flashes" or "hot flushes"). In some women, the symptoms are mild, and they will not need to use estrogens.
In other women, symptoms can be more severe. • T reat moderate to severe menopausal changes in and around the vagina You and your healthcare provider should talk regularly about whether you still need treatment with estradiol and norethindrone acetate tablets 1.0 mg/0.5 mg to treat these problems. If you use estradiol and norethindrone acetate tablets 1.0 mg/0.5 mg only to treat your menopausal changes in and around your vagina, talk with your healthcare provider about whether a topical vaginal product would be better for you. • H elp reduce your chances of getting osteoporosis (thin weak bones) Osteoporosis from menopause is a thinning of the bones that makes them weaker and easier to break.
If you use estradiol and norethindrone acetate tablets to prevent osteoporosis due to menopause, talk with your healthcare provider about whether a different treatment or medicine without estrogens might be better for you. You and your healthcare provider should talk regularly about whether you still need treatment with estradiol and norethindrone acetate tablets. Who should not use estradiol and norethindrone acetate tablets ?
Do not use estradiol and norethindrone acetate tablets if you have had your uterus (womb) removed (hysterectomy). Estradiol and norethindrone acetate tablets contain a progestogen to decrease the chance of getting cancer of the uterus. If you do not have a uterus, you do not need a progestogen and you should not use estradiol and norethindrone acetate tablets.
Do not start using estradiol and norethindrone acetate tablets if you: • have unusual vaginal bleeding Vaginal bleeding after menopause may be a warning sign of cancer of the uterus (womb). Your healthcare provider should check any unusual vaginal bleeding to find out the cause. • have been diagnosed with a bleeding disorder • currently have or have had certain cancers Estrogens may increase the chance of getting certain types of cancers, including cancer of the breast or uterus (womb). If you have or have had cancer, talk with your healthcare provider about whether you should use estradiol and norethindrone acetate tablets. • had a stroke or heart attack • currently have or have had blood clots • currently have or have had liver problems • are allergic to estradiol and norethindrone acetate tablets or any of its ingredients in it See the list of ingredients in estradiol and norethindrone acetate tablets at the end of this leaflet.
Before you use estradiol and norethindrone acetate tablets , tell your healthca… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Warnings and Precautions, Malignant Neoplasms (5.2) 11/2023
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 0.5mg/0.1mg 1mg/0.5mg
Medicaid utilization by pack size
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |