
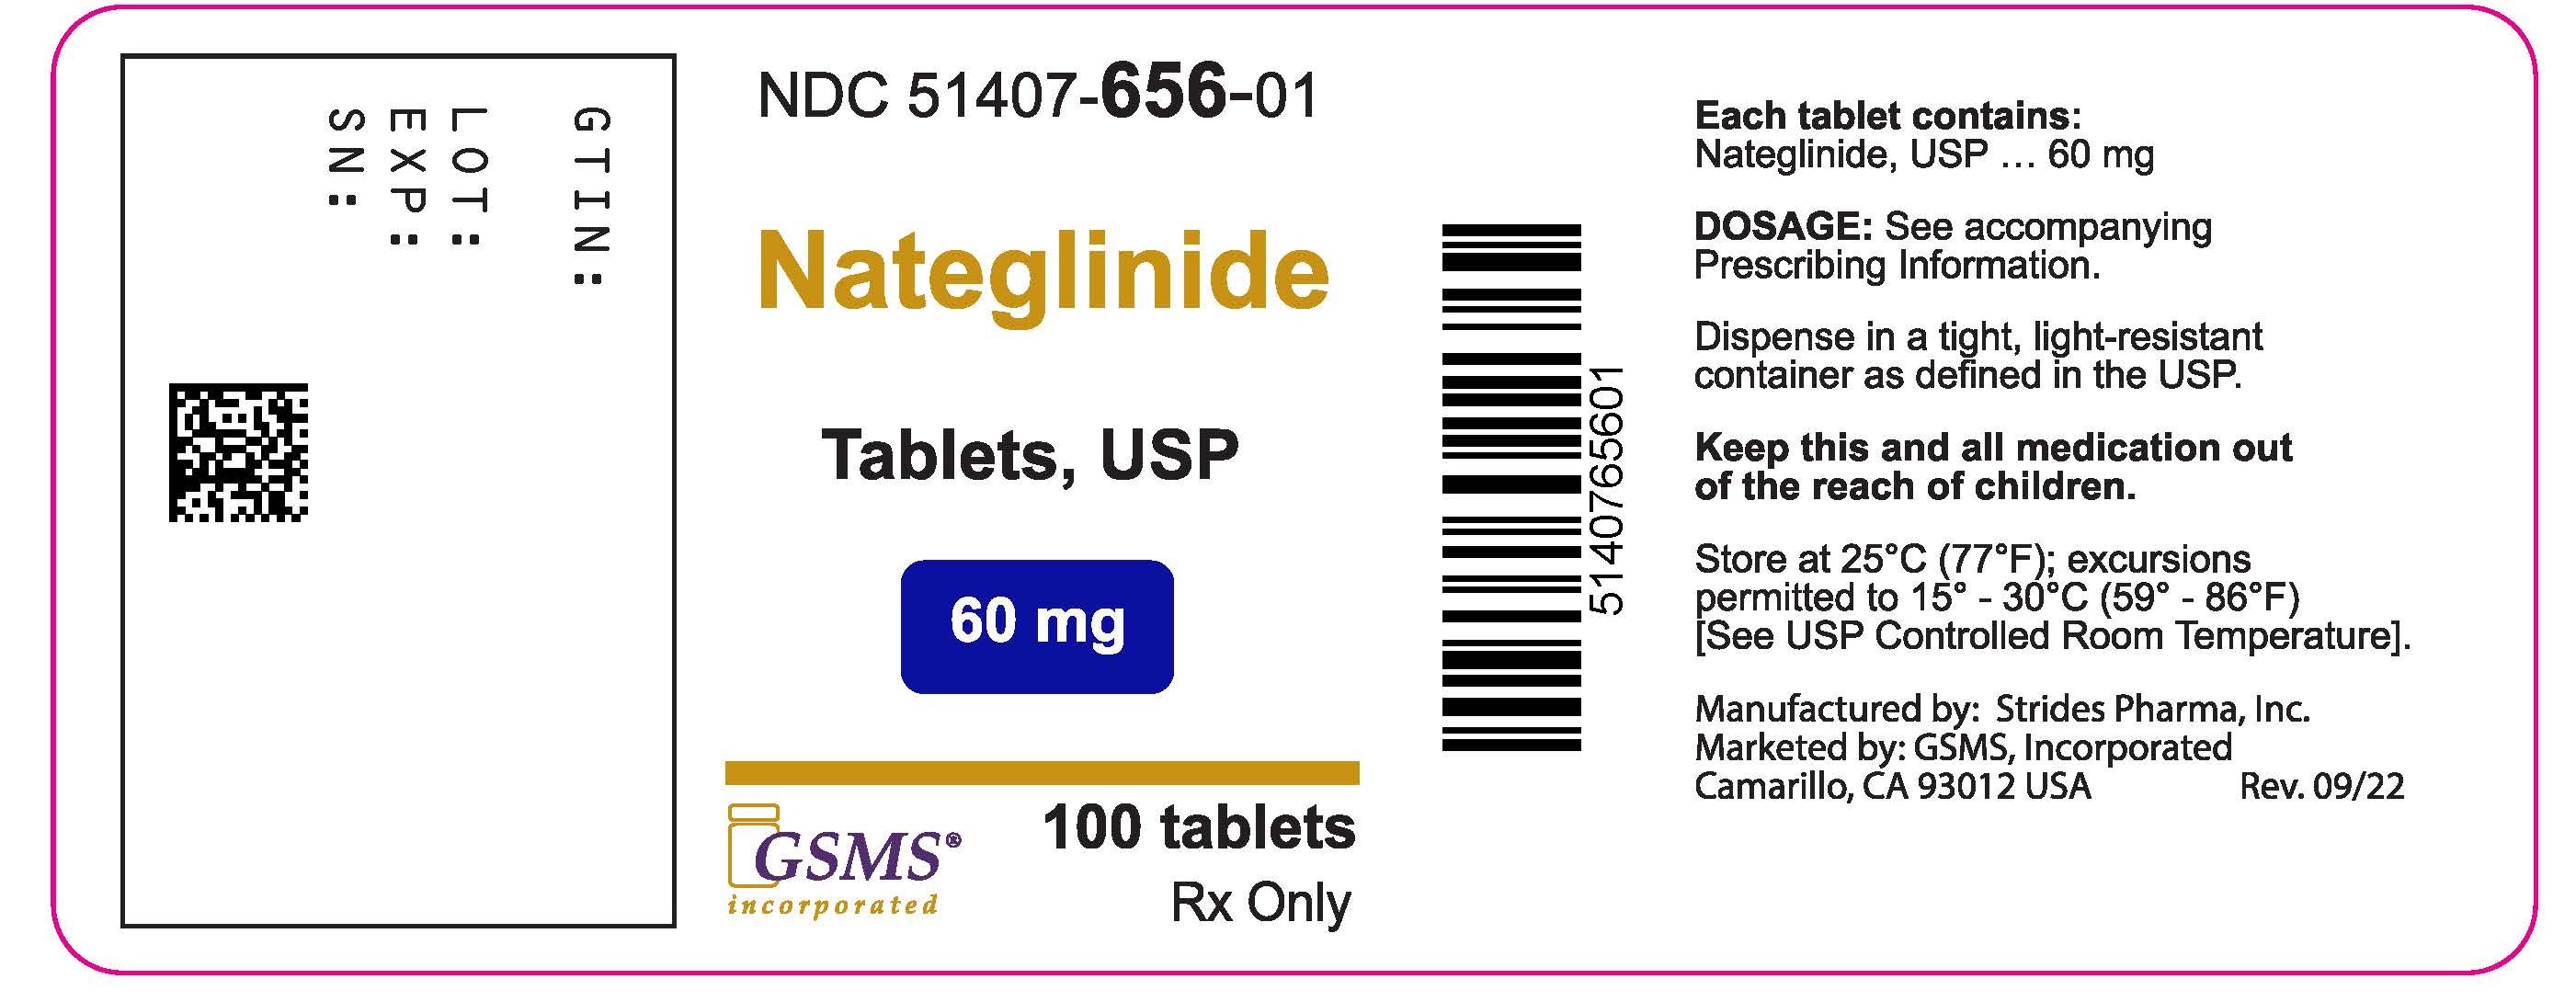
Nateglinide 60 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Glinide class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nateglinide is used alone or in combination with other medications to treat type 2 diabetes (condition in which the body does not use insulin normally and therefore cannot control the amount of sugar in the blood) in people whose diabetes cannot be controlled by diet and exercise alone. Nateglinide belongs to a class of drugs called meglitinides. Nateglinide helps your body regulate the amount of glucose (sugar) in your blood. It decreases the amount of glucose by stimulating the pancreas to release insulin. Over time, people who have diabetes and high blood sugar can develop serious or life-t...
Read the full MedlinePlus article ↗- Nateglinide helps your pancreas release insulin right after you eat, which keeps your blood sugar from spiking too high after meals. It's specifically for type 2 diabetes and is me...
- What exactly does nateglinide do for my diabetes?
- Take it 1 to 30 minutes before each meal — three times a day. Timing matters here because it's designed to match your body's insulin release with the food you're about to eat. If y...
- When exactly should I take my nateglinide tablet?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nateglinide — tap one for details:
Nateglinide may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2683 | $26.83 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nateglinide 60 mg 60687-0673-21 | American | 30 tablets | $0.190 | AB | Availability likely | — |
| Nateglinide 60 mg 72241-0002-04 | Modavar | 90 tablets | $0.190 | AB | Availability likely | — |
| Nateglinide 60 mg 75834-0205-01 | Nivagen | 100 tablets | $0.190 | AB | Discontinued | — |
| Nateglinide 60 mg 16571-0758-01 | Rising | 100 tablets | — | AB | FDA listed | — |
| Nateglinide 60 mgthis 51407-0656-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Nateglinide 60 mg 55111-0328-01 | Dr. | 100 tablets | — | AB | FDA listed | — |
| Nateglinide 60 mg 64380-0167-01 | Strides | 100 tablets | — | AB | FDA listed | — |
| Nateglinide 60 mg 68382-0721-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Nateglinide 60 mg 70771-1015-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Nateglinide 60 mg 71209-0030-04 | Cadila | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 51407-0656-01 You're viewing this | 100 TABLET in 1 BOTTLE, PLASTIC (51407-656-01) | 2022-05-25 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Nateglinide is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. Limitations of Use: Nateglinide should not be used in patients with type 1 diabetes mellitus or for the treatment of diabetic ketoacidosis. Nateglinide is a glinide indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
(1) Limitations of Use : Not for treating type 1 diabetes mellitus or diabetes ketoacidosis (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of nateglinide is 120 mg orally three times daily before meals. The recommended dose of nateglinide is 60 mg orally three times daily before meals in patients who are near glycemic goal when treatment is initiated. Instruct patients to take nateglinide 1 to 30 minutes before meals.
In patients who skip meals, instruct patients to skip the scheduled dose of nateglinide to reduce the risk of hypoglycemia [see Warnings and Precautions (5.1)] . Recommended dose is 120 mg three times daily (2) In patients who are near glycemic goal when treatment is initiated, 60 mg three times daily may be administered. (2) Administer 1 to 30 minutes before meals (2) If a meal is skipped, skip the scheduled dose to reduce the risk of hypoglycemia.
(2, 5.1)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 60 mg tablets: Pink color coated, round biconvex, beveled edge tablet debossed with "P 984" on one side and plain on the other side 120 mg tablets: Orange color coated, oval shaped biconvex, tablet debossed with "P 985" on one side and plain on the other side Tablets: 60 mg and 120 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Nateglinide tablets are contraindicated in patients with a history of hypersensitivity to nateglinide or its inactive ingredients. History of hypersensitivity to nateglinide or its inactive ingredients (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypoglycemia: Nateglinide may cause hypoglycemia. Administer before meals to reduce the risk of hypoglycemia. Skip the scheduled dose of nateglinide if a meal is skipped to reduce the risk of hypoglycemia. (5.1) Macrovascular Outcomes: There have been no clinical studies establishing conclusive evidence of macrovascular risk reduction with nateglinide. (5.2)
5.1Hypoglycemia All glinides, including nateglinide, can cause hypoglycemia [see Adverse Reactions (6.1)] . Severe hypoglycemia can cause seizures, may be life-threatening, or cause death. Hypoglycemia can impair concentration ability and reaction time; this may place an individual and others at risk in situations where these abilities are important (e.g., driving or operating other machinery).
Hypoglycemia can happen suddenly and symptoms may differ in each individual and change over time in the same individual. Symptomatic awareness of hypoglycemia may be less pronounced in patients with longstanding diabetes, in patients with diabetic neuropathy (nerve disease), in patients using medications that block the sympathetic nervous system (e.g., beta-blockers) [see Drug Interactions (7)] , or in patients who experience recurrent hypoglycemia. Factors which may increase the risk of hypoglycemia include changes in meal pattern (e.g., macronutrient content), changes in level of physical activity, changes to coadministered medication [see Drug Interactions (7)] , and concomitant use with other antidiabetic agents.
Patients with renal or hepatic impairment may be at higher risk of hypoglycemia [see Use in Specific Populations (8.6, 8.7), Clinical Pharmacology (12.3)] . Patients should take nateglinide before meals and be instructed to skip the dose of nateglinide if a meal is skipped [see Dosage and Administration (2)] . Patients and caregivers must be educated to recognize and manage hypoglycemia.
Self-monitoring of blood glucose plays an essential role in the prevention and management of hypoglycemia. In patients at higher risk for hypoglycemia and patients who have reduced symptomatic awareness of hypoglycemia, increased frequency of blood glucose monitoring is recommended.
5.2Macrovascular Outcomes There have been no clinical studies establishing conclusive evidence of macrovascular risk reduction with nateglinide.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reaction is also described elsewhere in the labeling: Hypoglycemia [see Warnings and Precautions (5.1)] Common adverse reactions associated with nateglinide (3% or greater incidence) were upper respiratory tract infection, back pain, flu symptoms, dizziness, arthropathy, diarrhea. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Strides Pharma Inc at 1-877-244-9825 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In clinical trials, approximately 2,600 patients with type 2 diabetes mellitus were treated with nateglinide. Of these, approximately 1,335 patients were treated for 6 months or longer and approximately 190 patients for one year or longer.
Table 1 shows the most common adverse reactions associated with nateglinide. Table 1: Adverse Reactions other than Hypoglycemia (%) occurring Greater than or Equal to 2% in Nateglinide-Treated Patients from Pool of 12 to 64 week Placebo Controlled Trials Placebo N = 458 Nateglinide N = 1441 Preferred Term Upper Respiratory Infection 8.1
10.5Back Pain 3.7
4.0Flu Symptoms 2.6
3.6Dizziness 2.2
3.6Arthropathy 2.2
3.3Diarrhea 3.1
3.2Accidental Trauma 1.7
2.9Bronchitis 2.6
2.7Coughing 2.2
2.4Hypoglycemia Episodes of severe hypoglycemia (plasma glucose less than 36 mg/dL) were reported in two patients treated with nateglinide. Non-severe hypoglycemia occurred in 2.4 % of nateglinide treated patients and 0.4 % of placebo-treated patients [see Warnings and Precautions (5.1)] . Weight Gain Patients treated with nateglinide had statistically significant mean increases in weight compared to placebo.
In clinical trials, the mean weight increases with nateglinide 60 mg (3 times daily) and nateglinide 120 mg (3 times daily) compared to placebo were 1.0 kg and 1.6 kg, respectively. Laboratory Test Increases in Uric Acid: There were increases in mean uric acid levels for patients treated with nateglinide alone, nateglinide in combination with metformin, metformin alone, and glyburide alone. The respective differences from placebo were 0.29 mg/dL, 0.45 mg/dL, 0.28 mg/dL, and 0.19 mg/dL.
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of nateglinide. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Hypersensitivity Reactions: Rash, itching, and urticaria Hepatobiliary Disorders: Jaundice, cholestatic hepatitis, and elevated liver enzymes
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 2 includes a list of drugs with clinically important drug interactions when concomitantly administered or withdrawn with nateglinide and instructions for managing or preventing them. Table 2: Clinically Significant Drug Interactions with Nateglinide Drugs That May Increase the Blood-Glucose-Lowering Effect of Nateglinide and Susceptibility to Hypoglycemia Drugs: Nonsteroidal anti-inflammatory drugs (NSAIDs), salicylates, monoamine oxidase inhibitors, non-selective beta-adrenergic-blocking agents, anabolic hormones (e.g., methandrostenolone), guanethidine, gymnema sylvestre, glucomannan, thioctic acid, and inhibitors of CYP2C9 (e.g., amiodarone, fluconazole, voriconazole, sulfinpyrazone) or in patients known to be poor metabolizers of CYP2C9 substrates, alcohol.
Intervention: Dose reductions and increased frequency of glucose monitoring may be required when nateglinide is coadministered with these drugs. Drugs and Herbals That May Reduce the Blood-Glucose-Lowering Effect of Nateglinide and Increase Susceptibility to Hyperglycemia Drugs: Thiazides, corticosteroids, thyroid products, sympathomimetics, somatropin, somatostatin analogues (e.g., lanreotide, octreotide), and CYP inducers (e.g., rifampin, phenytoin and St John's Wort). Intervention: Dose increases and increased frequency of glucose monitoring may be required when nateglinide is coadministered with these drugs.
Drugs That May Blunt Signs and Symptoms of Hypoglycemia Drugs: beta-blockers, clonidine, guanethidine, and reserpine Intervention: Increased frequency of glucose monitoring may be required when nateglinide is coadministered with these drugs. Drugs That May Increase the Potential for Hypoglycemia : Nateglinide dose reductions and increased frequency of glucose monitoring may be required when co-administered (7) Drugs That May Increase the Potential for Hyperglycemia : Nateglinide dose increases and increased frequency of glucose monitoring may be required when co-administered (7) Drugs That May Blunt Signs and Symptoms of Hypoglycemia : Increased frequency of glucose monitoring may be required when co-administered (7)
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Nateglinide is not recommended when breastfeeding (8.2)
8.1Pregnancy Risk Summary The available data from published literature and the applicant's pharmacovigilance with use of nateglinide in pregnant women are insufficient to identify a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy ( see Clinical Considerations ). Nateglinide should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
In animal reproduction studies, there was no teratogenicity in rats and rabbits administered oral nateglinide during organogenesis at approximately 27 and 8 times the maximum recommended human dose (MRHD), respectively, based on body surface area (BSA). The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c > 7 and has been reported to be as high as 20% to 25% in women with a HbA1c > 10. The estimated background risk of miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity.
Data Animal data In embryofetal development studies, nateglinide administered orally during the period of organogenesis was not teratogenic in rats at doses up to 1,000 mg/kg (corresponding to 27 times the MRHD of 120 mg three times per day, based on BSA). In rabbits, embryonic development was adversely affected at 500 mg/kg/day and the incidence of gallbladder agenesis or small gallbladder was increased at a dose of 300 and 500 mg/kg (corresponding to 16 and 27 times the MRHD). No such effects were observed at 150 mg/kg/day (corresponding to 8 times the MRHD).
In a pre- and postnatal development study in rats, nateglinide administered by oral gavage at doses of 100, 300, and 1000 mg/kg/day from gestation day 17 to lactation day 21 resulted in lower body weight in offspring of rats administered nateglinide at 1,000 mg/kg/day (corresponding to 27 times the MHRD).
8.2Lactation Risk summary There are no data on the presence of nateglinide in human milk, the effects on the breastfeeding infant, or the effects on milk production. The drug is present in animal milk. When a drug is present in animal milk, it is likely that the drug will be present in human milk ( see Data ).
Because the potential for hypoglycemia in breast-fed infants, advise women that use of nateglinide is not recommended while breastfeeding. Data In rat reproduction studies, nateglinide and its metabolite are excreted in the milk following oral dose (300 mg/kg). The overall milk: plasma (M/P) concentration ratio of the total radioactivity was approximately 1.4 based on AUC 0-48 values.
The M/P ratio of unchanged nateglinide was approximately 2.2.
8.4Pediatric Use The safety and effectiveness of nateglinide have not been established in pediatric patients.
8.5Geriatric Use 436 patients 65 years and older, and 80 patients 75 years and older were exposed to nateglinide in clinical studies. No differences were observed in safety or efficacy of nateglinide between patients age 65 and over, and those under age 65. However, greater sensitivity of some older individuals to nateglinide therapy cannot be ruled out.
8.6Renal Impairment No dosage adjustment is recommended in patients with mild to severe renal impairment [see Clinical Pharmacology (12.3)] .
8.7 Hepatic Impairment…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The available data from published literature and the applicant's pharmacovigilance with use of nateglinide in pregnant women are insufficient to identify a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy ( see Clinical Considerations ). Nateglinide should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
In animal reproduction studies, there was no teratogenicity in rats and rabbits administered oral nateglinide during organogenesis at approximately 27 and 8 times the maximum recommended human dose (MRHD), respectively, based on body surface area (BSA). The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c > 7 and has been reported to be as high as 20% to 25% in women with a HbA1c > 10. The estimated background risk of miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity.
Data Animal data In embryofetal development studies, nateglinide administered orally during the period of organogenesis was not teratogenic in rats at doses up to 1,000 mg/kg (corresponding to 27 times the MRHD of 120 mg three times per day, based on BSA). In rabbits, embryonic development was adversely affected at 500 mg/kg/day and the incidence of gallbladder agenesis or small gallbladder was increased at a dose of 300 and 500 mg/kg (corresponding to 16 and 27 times the MRHD). No such effects were observed at 150 mg/kg/day (corresponding to 8 times the MRHD).
In a pre- and postnatal development study in rats, nateglinide administered by oral gavage at doses of 100, 300, and 1000 mg/kg/day from gestation day 17 to lactation day 21 resulted in lower body weight in offspring of rats administered nateglinide at 1,000 mg/kg/day (corresponding to 27 times the MHRD).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of nateglinide have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use 436 patients 65 years and older, and 80 patients 75 years and older were exposed to nateglinide in clinical studies. No differences were observed in safety or efficacy of nateglinide between patients age 65 and over, and those under age 65. However, greater sensitivity of some older individuals to nateglinide therapy cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no instances of overdose with nateglinide in clinical trials. However, an overdose may result in an exaggerated glucose-lowering effect with the development of hypoglycemic symptoms. Hypoglycemic symptoms without loss of consciousness or neurological findings should be treated with oral glucose and adjustments in dosage and/or meal patterns.
Severe hypoglycemic reactions with coma, seizure, or other neurological symptoms should be treated with intravenous glucose. As nateglinide is highly protein bound, dialysis is not an efficient means of removing it from the blood.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Nateglinide lowers blood glucose levels by stimulating insulin secretion from the pancreas. This action is dependent upon functioning beta-cells in the pancreatic islets. Nateglinide interacts with the ATP-sensitive potassium (K + ATP ) channel on pancreatic beta-cells.
The subsequent depolarization of the beta cell opens the calcium channel, producing calcium influx and insulin secretion. The extent of insulin release is glucose dependent and diminishes at low glucose levels. Nateglinide is highly tissue selective with low affinity for heart and skeletal muscle.
12.2Pharmacodynamics Nateglinide stimulates pancreatic insulin secretion within 20 minutes of oral administration. When nateglinide is dosed before meals, the peak rise in plasma insulin occurs approximately 1 hour after dosing and falls to baseline by 4 hours after dosing.
12.3Pharmacokinetics In patients with Type 2 diabetes, multiple dose administration of nateglinide over the dosage range of 60 mg to 240 mg shows linear pharmacokinetics for both area under the curve (AUC) and C max . In patients with Type 2 diabetes, there is no apparent accumulation of nateglinide upon multiple dosing of up to 240 mg three times daily for 7 days. Absorption Absolute bioavailability of nateglinide is approximately 73%.
Plasma profiles are characterized by multiple plasma concentration peaks when nateglinide is administered under fasting conditions. This effect is diminished when nateglinide is taken prior to a meal. Following oral administration immediately prior to a meal, the mean peak plasma nateglinide concentrations (C max ) generally occur within 1 hour (T max ) after dosing.
T max is independent of dose. The pharmacokinetics of nateglinide are not affected by the composition of a meal (high protein, fat, or carbohydrate). However, peak plasma levels are significantly reduced when nateglinide is administered 10 minutes prior to a liquid meal as compared to solid meal.
When given with or after meals, the extent of nateglinide absorption (AUC) remains unaffected. However, there is a delay in the rate of absorption characterized by a decrease in C max and a delay in time to peak plasma concentration (T max ). Nateglinide did not have any effect on gastric emptying in healthy subjects as assessed by acetaminophen testing.
Distribution Following intravenous (IV) administration of nateglinide, the steady-state volume of distribution of nateglinide is estimated to be approximately 10 L in healthy subjects. Nateglinide is extensively bound (98%) to serum proteins, primarily serum albumin, and to a lesser extent α 1 acid glycoprotein. The extent of serum protein binding is independent of drug concentration over the test range of 0.1 to 10 mcg/mL.
Elimination In healthy volunteers and patients with type 2 diabetes mellitus, nateglinide plasma concentrations declined with an average elimination half-life of approximately 1.5 hours. Metabolism In vitro drug metabolism studies indicate that nateglinide is predominantly metabolized by the cytochrome P450 isozyme CYP2C9 (70%) and to a lesser extent CYP3A4 (30%). The major routes of metabolism are hydroxylation followed by glucuronide conjugation.
The major metabolites are less potent antidiabetic agents than nateglinide. The isoprene minor metabolite possesses potency similar to that of the parent compound nateglinide. Excretion Nateglinide and its metabolites are rapidly and completely eliminated following oral administration.
Eighty-three percent of the 14 C -nateglinide was excreted in the urine with an additional 10% eliminated in the feces. Approximately 16% of the 14 C -nateglinide was excreted in the urine as parent compound. Specific Populations Renal Impairment No pharmacokinetic data are available in subjects with mild renal impairment (CrCl 60 to 89 mL/min).
Compared to healthy matched subjects, patients with type 2 diabetes mellitus and moderate and severe renal impairment (Cr…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Nateglinide lowers blood glucose levels by stimulating insulin secretion from the pancreas. This action is dependent upon functioning beta-cells in the pancreatic islets. Nateglinide interacts with the ATP-sensitive potassium (K + ATP ) channel on pancreatic beta-cells.
The subsequent depolarization of the beta cell opens the calcium channel, producing calcium influx and insulin secretion. The extent of insulin release is glucose dependent and diminishes at low glucose levels. Nateglinide is highly tissue selective with low affinity for heart and skeletal muscle.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Nateglinide Tablets, USP are supplied in the following package and dose strength forms: 60 mg Pink color coated, round biconvex, beveled edge tablet debossed with "P 984" on one side and plain on the other side. Bottles of 100……………NDC 51407-656-01 120 mg Orange color coated, oval shaped biconvex, tablet debossed with "P 985" on one side and plain on the other side. Bottles of 100……………NDC 51407-657-01 Storage and Handling Store at 25°C (77°F); excursions permitted to 15°C-30°C (59°F-86°F). [See USP Controlled Room Temperature] Dispense in a tight, light resistant container.
📋 Description ▾
11 DESCRIPTION Nateglinide Tablets, USP are an oral blood glucose-lowering drug of the glinide class. Nateglinide, (-)-N-[(trans-4-isopropylcyclohexane)carbonyl]-D-phenylalanine, is structurally unrelated to the oral sulfonylurea insulin secretagogues. The structural formula is as shown: Nateglinide is a white powder with a molecular weight of 317.43.
It is freely soluble in methanol, ethanol, and chloroform, soluble in ether, sparingly soluble in acetonitrile and octanol, and practically insoluble in water. Nateglinide biconvex tablets contain 60 mg, or 120 mg, of nateglinide for oral administration. Inactive Ingredients: colloidal silicon dioxide, croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, povidone, pregelatinized starch (starch 1500 ® ).
Starch 1500 ® is partially pregelatinized maize starch. The 60 mg also contains iron oxide red, polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide. In addition, the 120 mg contains FD&C Yellow #6/Sunset Yellow Aluminum Lake, iron oxide yellow.
Nateglinide structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Administration Instruct patients to take nateglinide 1 to 30 minutes before meals. Instruct patients that skip meals to skip their dose of nateglinide [see Dosage and Administration (2)] . Hypoglycemia Inform patients that nateglinide can cause hypoglycemia and instruct patients and their caregivers on self-management procedures, including glucose monitoring and management of hypoglycemia.
Inform patients that their ability to concentrate and react may be impaired as a result of hypoglycemia. In patients at higher risk for hypoglycemia and patients who have reduced symptomatic awareness of hypoglycemia, increased frequency of blood glucose monitoring is recommended [see Warnings and Precautions (5.1)] . Lactation Advise patients that use of nateglinide is not recommended while breastfeeding [see Use in Specific Populations (8.2)] .
Drug Interactions Discuss potential drug interactions with patients and inform them of potential drug-drug interactions with nateglinide. Distributed by: Strides Pharma Inc. East Brunswick, NJ 00816 Rev.
02/2022 OS984-01-1-11 Marketed by: GSMS, Inc. Camarillo, CA 93012 USA