
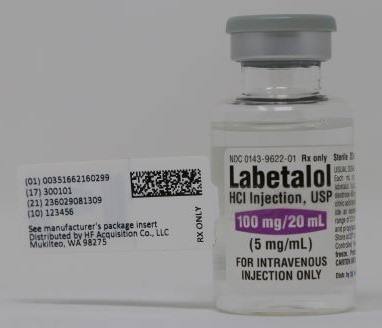
LABETALOL HCl 5 mg/mL Injection, 20 mL — NDC 51662-1602-9 (Billing 51662-1602-09)
This is a package of 20 mL of LABETALOL HCl 5 mg/mL Injection from HF Acquisition Co LLC, DBA HealthFirst, marketed since Aug 2022 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 51662-1602-9 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 51662 labeler · 1602 product · 9 package
- Package marketed since
- Oct 1, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 5166216029 9
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 896771
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Labetalol lowers blood pressure. The tablets are used for high blood pressure, and the IV form is used in the hospital for severe high blood pressure. Keeping blood pressure down r...
- Take them by mouth, usually twice a day, as your prescriber directs. Food increases how much of the drug your body absorbs, so try to be consistent about taking it with or without...
- Dizziness, nausea, tiredness and headache are the most common, and they often fade early in treatment. Standing up slowly helps with lightheadedness. Call your doctor if you get it...
- Please don't stop suddenly. Stopping a beta blocker abruptly can worsen chest pain and, in some cases, lead to a heart attack. If you need to stop, your prescriber will lower the d...
Patient education
Supplement & herbal interactions
Labetalol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J1920 | $0.218 / J1920 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1602-01 51662-1602-1 Main listing | 1 VIAL in 1 BOX, UNIT-DOSE / 20 mL in 1 VIAL | 2022-08-29 | — | Active |
| 51662-1602-09 You're viewing this | 20 mL in 1 VIAL | 2022-10-01 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of LABETALOL HCl 5 mg/mL Injection?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Labetalol Hydrochloride 5 mg/mL 00143-9320-01 | Hikma | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 5 mg/mL 00143-9622-01 | Hikma | 1 vial | $0.185 | AP | Availability likely | — |
| labetalol hydrochloride 5 mg/mL 25021-0317-20 | Sagent | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 5 mg/mL 36000-0322-02 | Baxter | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 5 mg/mL 65145-0124-01 | Caplin | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 5 mg/mL 72266-0102-01 | Fosun | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 5 mg/mL 72572-0350-01 | Civica, | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 5 mg/mL 72603-0146-01 | NorthStar | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 100 mg/20mL 83301-0058-01 | Mullan | 1 vial | $0.185 | AP | Availability likely | — |
| Labetalol Hydrochloride 5 mg/mL 00143-9623-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Labetalol Hydrochloride 5 mg/mL 00409-0125-25 | Hospira, | 25 vials | — | AP | FDA listed | — |
| Labetalol Hydrochloride 5 mg/mL 00409-2267-20 | Hospira, | 1 vial | — | AP | Discontinued | — |
| Labetalol Hydrochloride 5 mg/mL 36000-0324-02 | Baxter | 1 vial | — | AP | FDA listed | — |
| LABETALOL HCl 5 mg/mLthis 51662-1602-09 | HF | 20 ml | — | AP | FDA listed | — |
| Labetalol Hydrochloride 5 mg/mL 65145-0125-01 | Caplin | 1 vial | — | AP | FDA listed | — |
| Labetalol Hydrochloride 5 mg/mL 68083-0111-01 | Gland | 10 vials | — | AP | FDA listed | — |
| Labetalol Hydrochloride 5 mg/mL 72266-0103-01 | Fosun | 1 vial | — | AP | FDA listed | — |
| Labetalol Hydrochloride 200 mg/40mL 83301-0059-01 | Mullan | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Labetalol inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from HF Acquisition Co LLC, DBA HealthFirst labeler code 51662
- KETOROLAC TROMETHAMINE 30 mg/mL Injection, Solution NDC 51662-1594-3
- Ampicillin 250 mg Injection, Powder, For Solution NDC 51662-1595-3
- LIDOCAINE HCl 40 mg/mL Injection, Solution NDC 51662-1596-3
- GENTAMICIN SULFATE 40 mg/mL Injection, Solution NDC 51662-1597-3
- 0.5% LIDOCAINE HCl 5 mg/mL Injection, Solution NDC 51662-1600-3
- GLYCOPYRROLATE .2 mg/mL Injection NDC 51662-1601-1
- XYLOCAINE- MPF (LIDOCAINE HCl ) 20 mg/mL Injection, Solution NDC 51662-1604-3
- 0.25% BUPIVACAINE HCl 2.5 mg/mL Injection, Solution NDC 51662-1606-3
- 0.9% SODIUM CHLORIDE 9 g/1000mL Injection, Solution NDC 51662-1609-1
- Grafco Silver Nitrate (75% Silver Nitrate, 25% Potassium Nitrate) 12.74 mg; 38.21 mg Stick NDC 51662-1611-1
- ATROPINE SULFATE .4 mg/mL Injection NDC 51662-1619-1
- NALOXONE HCl 4 mg/.1mL Spray NDC 51662-1620-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE Labetalol HCl Injection, USP is indicated for control of blood pressure in severe hypertension.
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION Labetalol HCl injection is intended for intravenous use in hospitalized patients. DOSAGE MUST BE INDIVIDUALIZED depending upon the severity of hypertension and the response of the patient during dosing. Patients should always be kept in a supine position during the period of intravenous drug administration.
A substantial fall in blood pressure on standing should be expected in these patients. The patient’s ability to tolerate an upright position should be established before permitting any ambulation, such as using toilet facilities. Either of two methods of administration of labetalol HCl injection may be used: a) repeated intravenous injection, or b) slow continuous infusion.
Repeated Intravenous Injection Initially, labetalol HCl injection should be given in a 20 mg dose (which corresponds to 0.25 mg/kg for an 80 kg patient) by slow intravenous injection over a 2 minute period. Immediately before the injection and at 5 and 10 minutes after injection, supine blood pressure should be measured to evaluate response. Additional injections of 40 or 80 mg can be given at 10 minute intervals until a desired supine blood pressure is achieved or a total of 300 mg of labetalol HCl injection has been injected.
The maximum effect usually occurs within 5 minutes of each injection. Slow Continuous Infusion Labetalol HCl injection is prepared for continuous intravenous infusion by diluting the vial contents with commonly used intravenous fluids (see below). Examples of two methods of preparing the infusion solution are: The contents of either two 20 mL vials (40 mL), or one 40 mL vial, are added to 160 mL of a commonly used intravenous fluid such that the resultant 200 mL of solution contains 200 mg of labetalol HCl, 1 mg/mL.
The diluted solution should be administered at a rate of 2 mL/min to deliver 2 mg/min. Alternatively, the contents of either two 20 mL vials (40 mL), or one 40 mL vial, of labetalol HCl injection are added to 250 mL of a commonly used intravenous fluid. The resultant solution will contain 200 mg of labetalol HCl, approximately 2 mg/3 mL.
The diluted solution should be administered at a rate of 3 mL/min to deliver approximately 2 mg/min. The rate of infusion of the diluted solution may be adjusted according to the blood pressure response, at the discretion of the physician. To facilitate a desired rate of infusion, the diluted solution can be infused using a controlled administration mechanism, e.g., graduated burette or mechanically driven infusion pump.
Since the half-life of labetalol is 5 to 8 hours, steady-state blood levels (in the face of a constant rate of infusion) would not be reached during the usual infusion time period. The infusion should be continued until a satisfactory response is obtained and should then be stopped and oral labetalol HCl started (see below). The effective intravenous dose is usually in the range of 50 to 200 mg.
A total dose of up to 300 mg may be required in some patients. Blood Pressure Monitoring The blood pressure should be monitored during and after completion of the infusion or intravenous injection. Rapid or excessive falls in either systolic or diastolic blood pressure during intravenous treatment should be avoided.
In patients with excessive systolic hypertension, the decrease in systolic pressure should be used as an indicator of effectiveness in addition to the response of the diastolic pressure. Initiation of Dosing with Labetalol HCl Tablets Subsequent oral dosing with labetalol HCl tablets should begin when it has been established that the supine diastolic blood pressure has begun to rise. The recommended initial dose is 200 mg, followed in 6 to 12 hours by an additional dose of 200 or 400 mg, depending on the blood pressure response.
Thereafter, inpatient titration with labetalol HCl tablets may proceed as follows: While in the hospital, the dosage of labetalol HCl tablets may be increased at 1 day intervals to achieve the desired blood pressure r… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Labetalol HCl injection is contraindicated in bronchial asthma, overt cardiac failure, greater-than-first-degree heart block, cardiogenic shock, severe bradycardia, other conditions associated with severe and prolonged hypotension, and in patients with a history of hypersensitivity to any component of the product (see WARNINGS ). Beta-blockers, even those with apparent cardioselectivity, should not be used in patients with a history of obstructive airway disease, including asthma.
⚠️ Warnings ▾
WARNINGS Hepatic Injury Severe hepatocellular injury, confirmed by rechallenge in at least one case, occurs rarely with labetalol therapy. The hepatic injury is usually reversible, but hepatic necrosis and death have been reported. Injury has occurred after both short- and long-term treatment and may be slowly progressive despite minimal symptomatology.
Similar hepatic events have been reported with a related compound, dilevalol HCl, including two deaths. Dilevalol HCl is one of the four isomers of labetalol HCl. Thus, for patients taking labetalol, periodic determination of suitable hepatic laboratory tests would be appropriate.
Laboratory testing should be done at the very first symptom or sign of liver dysfunction (e.g., pruritus, dark urine, persistent anorexia, jaundice, right upper quadrant tenderness, or unexplained “flu-like” symptoms). If the patient has laboratory evidence of liver injury or jaundice, labetalol should be stopped and not restarted. Cardiac Failure Sympathetic stimulation is a vital component supporting circulatory function in congestive heart failure.
Beta-blockade carries a potential hazard of further depressing myocardial contractility and precipitating more severe failure. Although beta-blockers should be avoided in overt congestive heart failure, if necessary, labetalol can be used with caution in patients with a history of heart failure who are well compensated. Congestive heart failure has been observed in patients receiving labetalol HCl.
Labetalol does not abolish the inotropic action of digitalis on heart muscle. In Patients Without a History of Cardiac Failure In patients with latent cardiac insufficiency, continued depression of the myocardium with beta-blocking agents over a period of time can, in some cases, lead to cardiac failure. At the first sign or symptom of impending cardiac failure, patients should be fully digitalized and/or be given a diuretic, and the response should be observed closely.
If cardiac failure continues despite adequate digitalization and diuretic, labetalol therapy should be withdrawn (gradually, if possible). Ischemic Heart Disease Angina pectoris has not been reported upon labetalol discontinuation. However, following abrupt cessation of therapy with some beta-blocking agents in patients with coronary artery disease, exacerbations of angina pectoris and, in some cases, myocardial infarction have been reported.
Therefore, such patients should be cautioned against interruption of therapy without the physician’s advice. Even in the absence of overt angina pectoris, when discontinuation of labetalol is planned, the patient should be carefully observed and should be advised to limit physical activity. If angina markedly worsens or acute coronary insufficiency develops, labetalol administration should be reinstituted promptly, at least temporarily, and other measures appropriate for the management of unstable angina should be taken.
Nonallergic Bronchospasm (e.g., Chronic Bronchitis and Emphysema) Since labetalol HCl at the usual intravenous therapeutic doses has not been studied in patients with nonallergic bronchospastic disease, it should not be used in such patients. Pheochromocytoma Intravenous labetalol has been shown to be effective in lowering blood pressure and relieving symptoms in patients with pheochromocytoma; higher than usual doses may be required. However, paradoxical hypertensive responses have been reported in a few patients with this tumor; therefore, use caution when administering labetalol to patients with pheochromocytoma.
Diabetes Mellitus and Hypoglycemia Beta-adrenergic blockade may prevent the appearance of premonitory signs and symptoms (e.g., tachycardia) of acute hypoglycemia. This is especially important with labile diabetics. Beta-blockade also reduces the release of insulin in response to hyperglycemia; it may therefore be necessary to adjust the dose of antidiabetic drugs.
Major Surgery Do not routinely withdraw chronic beta blocker th… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Labetalol HCl injection is usually well tolerated. Most adverse effects have been mild and transient and, in controlled trials involving 92 patients, did not require labetalol withdrawal. Symptomatic postural hypotension (incidence, 58%) is likely to occur if patients are tilted or allowed to assume the upright position within 3 hours of receiving labetalol HCl.
Moderate hypotension occurred in 1 of 100 patients while supine. Increased sweating was noted in 4 of 100 patients, and flushing occurred in 1 of 100 patients. The following also were reported with labetalol HCl with the incidence per 100 patients as noted: Cardiovascular System:Ventricular arrhythmia in 1.
Central and Peripheral Nervous Systems: Dizziness in 9, tingling of the scalp/skin in 7, hypoesthesia (numbness) and vertigo in 1 each. Gastrointestinal System: Nausea in 13, vomiting in 4, dyspepsia and taste distortion in 1 each. Metabolic Disorders: Transient increases in blood urea nitrogen and serum creatinine levels occurred in 8 of 100 patients; these were associated with drops in blood pressure, generally in patients with prior renal insufficiency.
Psychiatric Disorders: Somnolence/yawning in 3. Respiratory System: Wheezing in 1. Skin: Pruritus in 1.
The incidence of adverse reactions depends upon the dose of labetalol HCl. The largest experience is with oral labetalol HCl (see Labetalol HCl Tablet Product Information for details). Certain of the side effects increased with increasing oral dose, as shown in the following table that depicts the entire US therapeutic trials data base for adverse reactions that are clearly or possibly dose related.
In addition, a number of other less common adverse events have been reported: Cardiovascular: Hypotension, and rarely, syncope, bradycardia, heart block. Liver and Biliary System: Hepatic necrosis, hepatitis, cholestatic jaundice, elevated liver function tests. Hypersensitivity: Rare reports of hypersensitivity (e.g., rash, urticaria, pruritus, angioedema, dyspnea) and anaphylactoid reactions.
The oculomucocutaneous syndrome associated with the beta-blocker practolol has not been reported with labetalol HCl during investigational use and extensive foreign marketing experience. Clinical Laboratory Tests Among patients dosed with labetalol tablets, there have been reversible increases of serum transaminases in 4% of patients tested and, more rarely, reversible increases in blood urea. ADVERSE
🆘 Overdosage ▾
OVERDOSAGE Overdosage with labetalol HCl causes excessive hypotension that is posture sensitive and, sometimes, excessive bradycardia. Patients should be placed supine and their legs raised if necessary to improve the blood supply to the brain. If overdosage with labetalol HCl follows oral ingestion, gastric lavage or pharmacologically induced emesis (using syrup of ipecac) may be useful for removal of the drug shortly after ingestion.
The following additional measures should be employed if necessary: Excessive bradycardia—administer atropine or epinephrine. Cardiac failure—administer a digitalis glycoside and a diuretic. Dopamine or dobutamine may also be useful.
Hypotension—administer vasopressors, e.g., norepinephrine. There is pharmacologic evidence that norepinephrine may be the drug of choice. Bronchospasm—administer epinephrine and/or an aerosolized beta2-agonist.
Seizures—administer diazepam. In severe beta-blocker overdose resulting in hypotension and/or bradycardia, glucagon has been shown to be effective when administered in large doses (5 to 10 mg rapidly over 30 seconds, followed by continuous infusion of 5 mg per hour that can be reduced as the patient improves). Neither hemodialysis nor peritoneal dialysis removes a significant amount of labetalol from the general circulation (<1%).
The oral LD50 value of labetalol HCl in the mouse is approximately 600 mg/kg and in the rat is greater than 2 g/kg. The intravenous LD50 in these species is 50 to 60 mg/kg.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Labetalol combines both selective, competitive, alpha1-adrenergic blocking and nonselective, competitive, beta-adrenergic blocking activity in a single substance. In man, the ratios of alpha- to beta-blockade have been estimated to be approximately 1:3 and 1:7 following oral and intravenous administration, respectively. Beta2-agonist activity has been demonstrated in animals with minimal beta1-agonist (ISA) activity detected.
In animals, at doses greater than those required for alpha- or beta-adrenergic blockade, a membrane stabilizing effect has been demonstrated. Pharmacodynamics The capacity of labetalol to block alpha receptors in man has been demonstrated by attenuation of the pressor effect of phenylephrine and by a significant reduction of the pressor response caused by immersing the hand in ice-cold water (“cold-pressor test”). Labetalol’s beta1-receptor blockade in man was demonstrated by a small decrease in the resting heart rate, attenuation of tachycardia produced by isoproterenol or exercise, and by attenuation of the reflex tachycardia to the hypotension produced by amyl nitrite.
Beta2-receptor blockade was demonstrated by inhibition of the isoproterenol-induced fall in diastolic blood pressure. Both the alpha- and beta-blocking actions of orally administered labetalol HCl contribute to a decrease in blood pressure in hypertensive patients. Labetalol consistently, in dose-related fashion, blunted increases in exercise-induced blood pressure and heart rate, and in their double product.
The pulmonary circulation during exercise was not affected by labetalol HCl dosing. Single oral doses of labetalol HCl administered to patients with coronary artery disease had no significant effect on sinus rate, intraventricular conduction, or QRS duration. The atrioventricular (A-V) conduction time was modestly prolonged in two of seven patients.
In another study, intravenous labetalol slightly prolonged A-V nodal conduction time and atrial effective refractory period with only small changes in heart rate. The effects on A-V nodal refractoriness were inconsistent. Labetalol produces dose-related falls in blood pressure without reflex tachycardia and without significant reduction in heart rate, presumably through a mixture of its alpha-blocking and beta-blocking effects.
Hemodynamic effects are variable, with small, nonsignificant changes in cardiac output seen in some studies but not others, and small decreases in total peripheral resistance. Elevated plasma renins are reduced. Doses of labetalol HCl that controlled hypertension did not affect renal function in mildly to severely hypertensive patients with normal renal function.
Due to the alpha1-receptor blocking activity of labetalol, blood pressure is lowered more in the standing than in the supine position, and symptoms of postural hypotension can occur. During dosing with intravenous labetalol HCl, the contribution of the postural component should be considered when positioning patients for treatment, and patients should not be allowed to move to an erect position unmonitored until their ability to do so is established. In a clinical pharmacologic study in severe hypertensives, an initial 0.25 mg/kg injection of labetalol HCl administered to patients in the supine position decreased blood pressure by an average of 11/7 mmHg.
Additional injections of 0.5 mg/kg at 15 minute intervals up to a total cumulative dose of 1.75 mg/kg of labetalol HCl caused further dose-related decreases in blood pressure. Some patients required cumulative doses of up to 3.25 mg/kg. The maximal effect of each dose level occurred within 5 minutes.
Following discontinuation of intravenous treatment with labetalol HCl, the blood pressure rose gradually and progressively, approaching pretreatment baseline values within an average of 16 to 18 hours in the majority of patients. Similar results were obtained in the treatment of patients with severe hypertension who required urgent bloo… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Labetalol HCl Injection, USP, 5 mg/mL, is supplied in 20 mL (100 mg) multidose vials, individually-boxed (NDC 51662-1602-01) Also available as 20 mL vial (100 mg) NDC 51662-1602-9 Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Do not freeze. Protect from light. To report SUSPECTED ADVERSE REACTIONS CONTACT HEALTHFIRST 11629 49th Pl W. Mukilteo, WA 98275 or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
📋 Description ▾
DESCRIPTION Labetalol Hydrochloride Injection, USP is an adrenergic receptor blocking agent that has both selective alpha1-adrenergic and nonselective beta-adrenergic receptor blocking actions in a single substance. Labetalol hydrochloride (HCl) is a racemate chemically designated as 5-[1-Hydroxy-2-[(1-methyl-3-phenylpropyl)amino]ethyl]-salicylamide monohydrochloride and it has the following structural formula: Labetalol HCl has the molecular formula C19H24N2O3•HCl and a molecular weight of 364.87. It has two asymmetric centers and therefore exists as a molecular complex of two diastereoisomeric pairs.
Dilevalol, the R,R' stereoisomer, makes up 25% of racemic labetalol. Labetalol HCl is a white or off-white crystalline powder, soluble in water. Labetalol HCl Injection, USP is a clear, colorless to light yellow, aqueous, sterile, isotonic solution for intravenous injection.
It has a pH range of 3 to 4. Each milliliter contains 5 mg of labetalol HCl, 45 mg of anhydrous dextrose, 0.1 mg of edetate disodium; 0.8 mg of methylparaben and 0.1 mg of propylparaben as preservatives; and citric acid monohydrate and sodium hydroxide, as necessary, to bring the solution into the pH range. STRUCTURE
⚠️ Precautions ▾
PRECAUTIONS General Impaired Hepatic Function Labetalol HCI injection should be used with caution in patients with impaired hepatic function since metabolism of the drug may be diminished. Hypotension Symptomatic postural hypotension (incidence, 58%) is likely to occur if patients are tilted or allowed to assume the upright position within 3 hours of receiving labetalol HCl injection. Therefore, the patient’s ability to tolerate an upright position should be established before permitting any ambulation.
Intraoperative Floppy Iris Syndrome (IFIS) Intraoperative Floppy Iris Syndrome (IFIS) has been observed during cataract surgery in some patients treated with alpha-1 blockers (labetalol is an alpha/beta blocker). This variant of small pupil syndrome is characterized by the combination of flaccid iris that billows in response to intraoperative irrigation currents, progressive intraoperative miosis despite preoperative dilation with standard mydriatic drugs, and potential prolapse of the iris toward the phacoemulsifcation incisions.
The patient’s ophthalmologist should be prepared for possible modifications to the surgical technique, such as the utilization of iris hooks, iris dilator rings, or viscoelastic substances. There does not appear to be a benefit of stopping alpha-1 blocker therapy prior to cataract surgery. Following Coronary Artery Bypass Surgery In one uncontrolled study, patients with low cardiac indices and elevated systemic vascular resistance following intravenous labetalol HCl treatment experienced significant declines in cardiac output with little change in systemic vascular resistance.
One of these patients developed hypotension following labetalol treatment. Therefore, use of labetalol HCl should be avoided in such patients. High Dose Labetalol HCl Administration of up to 3 g per day as an infusion for up to 2 to 3 days has been anecdotally reported; several patients have experienced hypotension or bradycardia.
Jaundice or Hepatic Dysfunction (see WARNINGS ). Information for Patients he following information is intended to aid in the safe and effective use of this medication. It is not a disclosure of all possible adverse or intended effects.
During and immediately following (for up to 3 hours) labetalol HCl injection, the patient should remain supine. Subsequently, the patient should be advised on how to proceed gradually to become ambulatory and should be observed at the time of first ambulation. When the patient is started on labetalol HCl tablets following adequate control of blood pressure with labetalol HCl injection, appropriate directions for titration of dosage should be provided (see DOSAGE AND ADMINISTRATION ).
As with all drugs with beta-blocking activity, certain advice to patients being treated with labetalol HCl is warranted. While no incident of the abrupt withdrawal phenomenon (exacerbation of angina pectoris) has been reported with labetalol HCl, dosing with labetalol HCl tablets should not be interrupted or discontinued without a physician’s advice. Patients being treated with labetalol HCl tablets should consult a physician at any signs or symptoms of impending cardiac failure or hepatic dysfunction (see WARNINGS ).
Also, transient scalp tingling may occur, usually when treatment with labetalol HCl tablets is initiated (see ADVERSE REACTIONS ). Laboratory Tests Routine laboratory tests are ordinarily not required before or after intravenous labetalol. In patients with concomitant illnesses, such as impaired renal function, appropriate tests should be done to monitor these conditions.
Drug Interactions Since labetalol HCl may be administered to patients already being treated with other medications, including other antihypertensive agents, careful monitoring of these patients is necessary to detect and treat promptly any undesired effect from concomitant administration. In one survey, 2.3% of patients taking labetalol orally in combination with tricyclic antidepressants experienced tremor as… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 51662-1602-1 CARTON LABEL & SERIALIZED LABELING Labetalol HCl Injection, USP 20 mL Carton Image NDC 51662-1602-1 Rx only Labetalol HCL Injection, USP 100 mg/20mL (5 mg/mL) FOR INTRAVENOUS INJECTION ONLY Sterile NDC 51662-1602-1 SERIALIZED LABELING BOX LABELING Serialized LabelING
PRINCIPAL DISPLAY PANEL - VIAL LABELING VIAL LABELING VIAL LABEL
PRINCIPAL DISPLAY PANEL NDC 51662-1602-9 SERIALIZED VIAL 51662-1602-9 SERIALIZED VIAL LABELING VIAL LABEL SERIALIZED VIAL LABEL VIAL LABEL UNBOXED
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |