
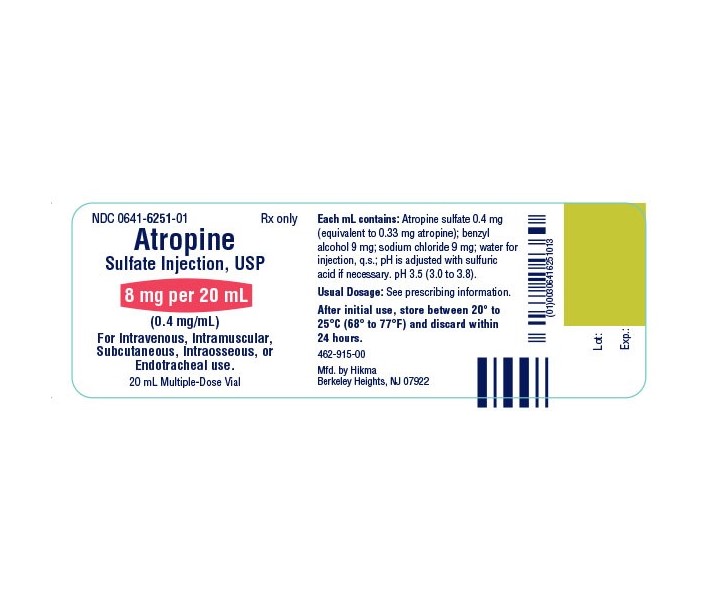
ATROPINE SULFATE .4 mg/mL Injection, 20 mL — NDC 51662-1619-1 (Billing 51662-1619-01)
This is a package of 20 mL of ATROPINE SULFATE .4 mg/mL Injection from HF Acquisition Co LLC, DBA HealthFirst, marketed since Oct 2022 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Atropine Sulfate (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 1190776
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Anticholinergic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the form. The injection is used in emergencies like poisonings and slow heart rhythms, and around surgery to reduce secretions. The eye drops and ointment dilate the...
- Injections are given by a healthcare professional, usually into a vein. ATROPEN is injected into the outer thigh in an emergency, and you should seek medical care right away. Eye p...
- Dry mouth, blurred vision, light sensitivity, a faster heartbeat, flushing, dizziness, and constipation are common. These come from atropine's drying effects. Injection site pain c...
- Seek emergency help for trouble breathing, swelling or a spreading rash, chest pain, a racing or irregular heartbeat, hallucinations, or a high fever with no sweating. Eye pain wit...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Atropine Sulfate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0463 | $0.017 / J0463 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1619-01 You're viewing this Main listing | 20 mL in 1 VIAL | 2022-11-10 | — | Active |
| 51662-1619-03 51662-1619-3 | 10 POUCH in 1 CASE / 1 VIAL in 1 POUCH / 20 mL in 1 VIAL | 2022-10-01 | — | Active |
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of ATROPINE SULFATE .4 mg/mL Injection?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Atropine Sulfate .4 mg/mL 00404-9804-20 | Henry | 1 vial | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 00641-6251-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 16729-0512-43 | Accord | 1 vial | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 51662-1311-01 | HF | 20 ml | — | — | FDA listed | — |
| Atropine Sulfate .4 mg/mLthis 51662-1619-01 | HF | 20 ml | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 63323-0580-20 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 70069-0481-10 | Somerset | 10 vials | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 70518-4188-00 | REMEDYREPACK | 10 vials | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 70518-4329-00 | REMEDYREPACK | 10 vials | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 71872-7037-01 | Medical | 1 vial | — | — | FDA listed | — |
| Atropine Sulfate .4 mg/mL 71872-7316-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 71872-7355-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Atropine Sulfate .4 mg/mL 84549-0580-20 | ProPharma | 20 ml | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
9 mg / 1 mL
UNII LKG8494WBH
Benzyl alcohol is a clear liquid used as a preservative and solvent in medicines. It helps prevent bacterial and fungal growth and dissolves other ingredients to create uniform liquid formulations.
-
9 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII O40UQP6WCF
A strong acid used in small amounts to adjust and maintain the pH balance of a medicine, helping ensure stability and proper dissolution of the active ingredients.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Atropine is indicated for temporary blockade of severe or life threatening muscarinic effects, e.g., as an antisialagogue, an antivagal agent, an antidote for organophosphorus, carbamate, or muscarinic mushroom poisoning, and to treat symptomatic bradycardia.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION
2.1General Administration Inspect parenteral drug products for particulate matter and discoloration prior to administration, whenever solution and container permit. Do not administer unless solution is clear and seal is intact. After initial use, discard unused portion within 24 hours. Intravenous administration is usually preferred, but subcutaneous, intramuscular, endotracheal, and intraosseous administration are possible.
2.2Adult Dosage Table 1: Recommended Dosage in Adult Patients IV=intravenous; IM=intramuscular; SC=subcutaneous; ET=endotracheal *Do not rely on atropine in type II second-degree or third-degree AV block with wide QRS complexes because these bradyarrhythmias are not likely to be responsive to reversal of cholinergic effects by atropine. Atropine has no effect on bradycardia in patients with transplanted hearts.
2.3Pediatric Dosage Table 2: Recommended Dosage in Pediatric Patients IV=intravenous; IM=intramuscular; SC=subcutaneous; IO=intraosseous; ET=endotracheal; *Available evidence does not support the routine use of atropine in emergency intubation of critically ill infants and children except in specific emergency intubations when there is higher risk of bradycardia ** Atropine has no effect on bradycardia in patients with transplanted hearts.
2.4Dosing in Patients with Ischemic Heart Disease Limit the total dose of atropine sulfate to 0.03 to 0.04 mg/kg [see WARNINGS AND PRECAUTIONS (5.2)]. D1 D2
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Atropine Sulfate Injection, USP, 8 mg per 20 mL (0.4 mg per mL), is a non-pyrogenic, isotonic, clear solution and is supplied in a multiple dose glass vial.
⛔ Contraindications ▾
4 CONTRAINDICATIONS None.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS
5.1Hypersensitivity Atropine may cause anaphylaxis.
5.2Worsening of Ischemic Heart Disease In patients with ischemic heart disease, the total dose should be restricted to 2 to 3 mg (maximum 0.03 to 0.04 mg/kg) to avoid atropine-induced tachycardia, increased myocardial oxygen demand and the potential for worsening cardiac ischemia or increasing infarction size.
5.3Acute Glaucoma Atropine may precipitate acute glaucoma.
5.4Pyloric Obstruction Atropine may convert partial organic pyloric stenosis into complete obstruction.
5.5Complete Urinary Retention Atropine may lead to complete urinary retention in patients with prostatic hypertrophy.
5.6Viscid Plugs Atropine may cause thickening of bronchial secretions and formation of viscid plugs in patients with chronic lung disease.
5.7Benzyl Alcohol The preservative benzyl alcohol has been associated with serious adverse events and death in neonates. The “gasping syndrome” (characterized by central nervous system depression, metabolic acidosis, gasping respirations, and high levels of benzyl alcohol and its metabolites found in the blood and urine) has been associated with benzyl alcohol dosages >99 mg/kg/day in neonates and low-birth weight infants. Additional symptoms may include gradual neurological deterioration, seizures, intracranial hemorrhage, hematologic abnormalities, skin breakdown, hepatic and renal failure, hypotension, bradycardia, and cardiovascular collapse.
Although normal therapeutic doses of this product deliver amounts of benzyl alcohol that are substantially lower than those reported in association with the “gasping syndrome”, the minimum amount of benzyl alcohol at which toxicity may occur is not known. Premature and low-birth weight infants may be more likely to develop toxicity. Practitioners administering this and other medications containing benzyl alcohol should consider the combined daily metabolic load of benzyl alcohol from all sources.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described elsewhere in labeling: Hypersensitivity ( 5.1 ) Worsening of Ischemic Heart Disease ( 5.2 ) Acute Glaucoma ( 5.3 ) Pyloric Obstruction ( 5.4 ) Complete Urinary Retention ( 5.5 ) Viscid Plugs ( 5.6 ) The following adverse reactions have been identified during post-approval use of atropine sulfate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Most of the side effects of atropine are directly related to its antimuscarinic action. Dryness of the mouth, blurred vision, photophobia and tachycardia commonly occur. Anhidrosis can produce heat intolerance.
Constipation and difficulty in micturition may occur. Occasional hypersensitivity reactions have been observed, including serious skin rashes. Paralytic ileus may occur.
Exacerbation of reflux has been reported. Larger or toxic doses may produce such central effects as restlessness, tremor, fatigue, locomotor difficulties, delirium, followed by hallucinations, depression, and ultimately, medullary paralysis and death. Large doses can also lead to circulatory collapse.
In such cases, blood pressure declines and death due to respiratory failure may ensue following paralysis and coma.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1 Mexiletine D INTER
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Severe or life-threatening muscarinic events such as acute organophosphate poisoning and symptomatic bradycardia are medical emergencies in pregnancy which can be fatal if left untreated. Life-sustaining therapy for the pregnant woman should not be withheld due to potential concerns regarding the effects of atropine on the fetus. Data Human Data No adequate and well-controlled studies are available regarding use of atropine in pregnant women.
In a cohort study of 401 pregnancies in the first trimester and 797 pregnancies in the second or third trimester, atropine use was not associated with an increased risk of congenital malformation. In a surveillance study, 381 newborns were exposed to atropine during the first trimester; 18 major birth defects were observed when 16 were expected. No specific pattern of major birth defects was identified.
In another surveillance study of 50 pregnancies in the first trimester, atropine use was not associated with an increased risk of malformations. Methodological limitations of these observational studies including the inability to control for the dosage and timing of atropine exposure, underlying maternal disease, or concomitant maternal drug use, cannot definitively establish or exclude any drug- associated risk during pregnancy.
8.2Lactation Risk Summary Trace amounts of atropine have been reported in human milk after oral intake. There are no available data on atropine levels in human milk after intravenous injection, the effects on the breastfed infant, or the effects on milk production. The lack of clinical data during lactation precludes a clear determination of the risk of atropine to an infant during lactation.
Clinical Considerations Minimizing exposure The elimination half-life of atropine is more than doubled in children less than 2 years of age [see CLINICAL PHARMACOLOGY (12.3 )]. To minimize potential infant exposure to Atropine Sulfate Injection, a woman may pump and discard her milk for 24 hours after use before resuming to breastfeed her infant.
8.5Geriatric Use An evaluation of current literature revealed no clinical experience identifying differences in response between elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. SPECIFIC POP
🆘 Overdosage ▾
10 OVERDOSAGE The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Severe or life-threatening muscarinic events such as acute organophosphate poisoning and symptomatic bradycardia are medical emergencies in pregnancy which can be fatal if left untreated. Life-sustaining therapy for the pregnant woman should not be withheld due to potential concerns regarding the effects of atropine on the fetus. Data Human Data No adequate and well-controlled studies are available regarding use of atropine in pregnant women.
In a cohort study of 401 pregnancies in the first trimester and 797 pregnancies in the second or third trimester, atropine use was not associated with an increased risk of congenital malformation. In a surveillance study, 381 newborns were exposed to atropine during the first trimester; 18 major birth defects were observed when 16 were expected. No specific pattern of major birth defects was identified.
In another surveillance study of 50 pregnancies in the first trimester, atropine use was not associated with an increased risk of malformations. Methodological limitations of these observational studies including the inability to control for the dosage and timing of atropine exposure, underlying maternal disease, or concomitant maternal drug use, cannot definitively establish or exclude any drug- associated risk during pregnancy.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Atropine is an antimuscarinic agent since it antagonizes the muscarine-like actions of acetylcholine and other choline esters. Atropine inhibits the muscarinic actions of acetylcholine on structures innervated by postganglionic cholinergic nerves, and on smooth muscles which respond to endogenous acetylcholine but are not so innervated. As with other antimuscarinic agents, the major action of atropine is a competitive or surmountable antagonism which can be overcome by increasing the concentration of acetylcholine at receptor sites of the effector organ (e.g., by using anticholinesterase agents which inhibit the enzymatic destruction of acetylcholine).
The receptors antagonized by atropine are the peripheral structures that are stimulated or inhibited by muscarine (i.e., exocrine glands and smooth and cardiac muscle). Responses to postganglionic cholinergic nerve stimulation also may be inhibited by atropine but this occurs less readily than with responses to injected (exogenous) choline esters.
12.2Pharmacodynamics Atropine-induced parasympathetic inhibition may be preceded by a transient phase of stimulation, especially on the heart where small doses first slow the rate before characteristic tachycardia develops due to paralysis of vagal control. Atropine exerts a more potent and prolonged effect on heart, intestine and bronchial muscle than scopolamine, but its action on the iris, ciliary body and certain secretory glands is weaker than that of scopolamine. Unlike the latter, atropine in clinical doses does not depress the central nervous system but may stimulate the medulla and higher cerebral centers.
Although mild vagal excitation occurs, the increased respiratory rate and (sometimes) increased depth of respiration produced by atropine are more probably the result of bronchiolar dilatation. Accordingly, atropine is an unreliable respiratory stimulant and large or repeated doses may depress respiration. Adequate doses of atropine abolish various types of reflex vagal cardiac slowing or asystole.
The drug also prevents or abolishes bradycardia or asystole produced by injection of choline esters, anticholinesterase agents or other parasympathomimetic drugs, and cardiac arrest produced by stimulation of the vagus. Atropine also may lessen the degree of partial heart block when vagal activity is an etiologic factor. In some patients with complete heart block, the idioventricular rate may be accelerated by atropine; in others, the rate is stabilized.
Occasionally a large dose may cause atrioventricular (A-V) block and nodal rhythm. Atropine in clinical doses counteracts the peripheral dilatation and abrupt decrease in blood pressure produced by choline esters. However, when given by itself, atropine does not exert a striking or uniform effect on blood vessels or blood pressure.
Systemic doses slightly raise systolic and lower diastolic pressures and can produce significant postural hypotension. Such doses also slightly increase cardiac output and decrease central venous pressure. Occasionally, therapeutic doses dilate cutaneous blood vessels, particularly in the “blush” area (atropine flush), and may cause atropine “fever” due to suppression of sweat gland activity in infants and small children.
The effects of intravenous atropine on heart rate (maximum heart rate) and saliva flow (minimum flow) after I.V. administration (rapid, constant infusion over 3 min.) are delayed by 7 to 8 minutes after drug administration and both effects are non-linearly related to the amount of drug in the peripheral compartment. Changes in plasma atropine levels following intramuscular administration (0.5 to 4 mg doses) and heart rate are closely overlapped but the time course of the changes in atropine levels and behavioral impairment indicates that pharmacokinetics is not the primary rate-limiting mechanism for the central nervous system effect of atropine.
12.3 Pharmacokinetics Absorption After…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED Atropine Sulfate Injection, USP is a non-pyrogenic, isotonic, clear solution and is supplied as follows: NDC 51662-1619-1 ATROPINE SULFATE INJECTION, USP 8mg/20mL (0.4mg/mL) 20mL VIAL NDC 51662-1619-2 ATROPINE SULFATE INJECTION, USP 8mg/20mL (0.4mg/mL) 20mL VIAL in a POUCH NDC 51662-1619-3 ATROPINE SULFATE INJECTION, USP 8mg/20mL (0.4mg/mL) 20mL VIAL in a POUCH, 10 POUCHES in a CASE Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. After initial use, store between 20° to 25°C (68° to 77°F) and discard within 24 hours.
HF Acquisition Co LLC, DBA HealthFirst 11629 49th Pl W. Mukilteo, WA 98275
📋 Description ▾
11 DESCRIPTION Atropine Sulfate Injection, USP is a sterile, nonpyrogenic, isotonic, clear solution of atropine sulfate in water for injection with sodium chloride sufficient to render the solution isotonic. It is administered parenterally by subcutaneous, intramuscular or intravenous injection. Each mL contains atropine sulfate, 0.4 mg; benzyl alcohol, 9 mg; sodium chloride 9 mg.
May contain sulfuric acid for pH adjustment. pH 3.5 (3.0 to 3.8). Sodium chloride added to render the solution isotonic for injection of the active ingredient is present in amounts insufficient to affect serum electrolyte balance of sodium (Na+) and chloride (Cl-) ions. Atropine Sulfate, USP is chemically designated lα H, 5α H-Tropan-3-α-ol (±)-tropate (ester), sulfate (2:1) (salt) monohydrate, (C17H23NO3)2 · H2SO4 · H2O, colorless crystals or white crystalline powder very soluble in water.
It has the following structural formula: Atropine Sulfate Structural Formula Atropine, a naturally occurring belladonna alkaloid, is a racemic mixture of equal parts of d- and 1-hyocyamine, whose activity is due almost entirely to the levo isomer of the drug. Sodium Chloride, USP is chemically designated NaCl, a white crystalline powder freely soluble in water. STRUCTURE
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |